Quadrangular & Triangular Spaces
Overview
The posterior scapulo-humeral region is organised around three muscles. Teres minor lies above, a rotator cuff external rotator; teres major lies below, an adductor and internal rotator. The long head of triceps descends vertically between them, passing posterior to teres minor and anterior to teres major, and divides the medial triangular space from the lateral quadrangular space.
The result is three named passages, each carrying a different neurovascular structure:
- Quadrangular (quadrilateral) space, lateral: the axillary nerve and the posterior circumflex humeral artery (PCHA)
- Triangular space, medial: only the circumflex scapular artery, with no major nerve
- Triangular interval, inferior: the radial nerve and profunda brachii artery, on their way into the spiral groove
Why it matters. These boundaries underpin safe posterior shoulder approaches, the deltoid-splitting safe zone, and the recognition of axillary nerve injury after dislocation or proximal humerus fracture. They also explain two uncommon but high-yield entrapments, quadrilateral space syndrome and triangular interval syndrome, and the circumflex scapular pedicle used in scapular and parascapular free flaps.
Anatomy: Boundaries and Contents
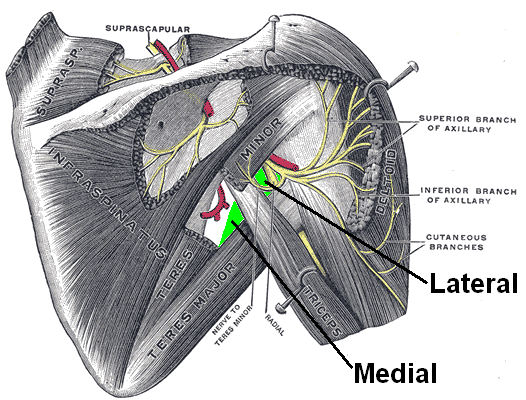
The boundaries. The triangular space has no medial border: it is the space between the muscles as they merge medially. The triangular interval, also called the lower triangular space, lies below teres major and lateral to the long head.
- Superior
- Teres minor (subscapularis and capsule anteriorly)
- Inferior
- Teres major
- Medial
- Long head of triceps
- Lateral
- Surgical neck of humerus
- Nerve
- Axillary
- Artery
- Posterior circumflex humeral
- Superior
- Teres minor
- Inferior
- Teres major
- Medial
- None
- Lateral
- Long head of triceps
- Nerve
- None
- Artery
- Circumflex scapular
- Superior
- Teres major
- Inferior
- -
- Medial
- Long head of triceps
- Lateral
- Shaft of humerus (or lateral head of triceps)
- Nerve
- Radial
- Artery
- Profunda brachii
The quadrangular space transmits structures from the axilla to the posterior shoulder. The axillary nerve passes posterior to the neck of the humerus with the PCHA, which anastomoses with the anterior circumflex humeral artery. Both wind around the surgical neck, where the nerve is at risk in dislocation and proximal humerus fracture.
The triangular space carries the circumflex scapular artery, a branch of the subscapular artery, which curves around the lateral border of the scapula. Collateral circulation around the scapula is robust.
The triangular interval is the entry point into the spiral groove. The radial nerve is visible here, with the profunda brachii artery beside it, before it passes deep to the lateral head of triceps.
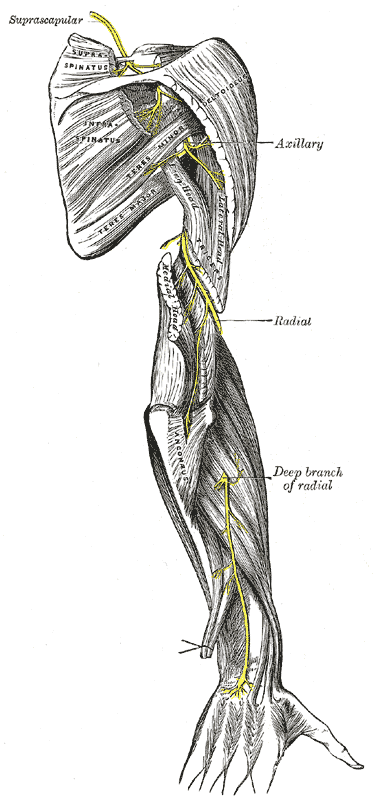
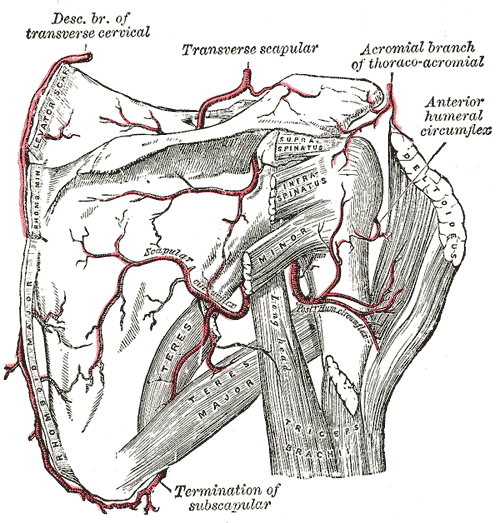
The axillary nerve's branches decide both the deltoid-split safe zone and the pattern of quadrilateral space syndrome:
- Articular branch to the shoulder joint
- Anterior (deep) branch, which winds transversely around the surgical neck deep to deltoid with the PCHA and supplies the anterior and middle deltoid, plus a few sensory twigs. It is the branch endangered by the lateral deltoid-splitting approach and by surgical-neck fractures and implants
- Posterior branch, which supplies the posterior deltoid and teres minor and continues as the superior lateral cutaneous nerve of the arm, the regimental-badge sensory area
A selective posterior-branch lesion gives isolated teres minor, with or without posterior deltoid, denervation: exactly the quadrilateral space syndrome pattern. Deltoid may be spared if the anterior branch is unaffected or if the compression is distal to where the main trunk branches, which is variable.
Candidates often mix up the contents of the triangular space and the triangular interval. Radials use Intervals, not Spaces.
Pathology and Classification of Compression
Quadrilateral space syndrome (QSS) is compression of the axillary nerve and the PCHA in the quadrangular space. The causes are fibrous bands, hypertrophy of the muscles in pitchers and swimmers, and paralabral cysts. The PCHA is the vessel compressed, and in overhead athletes it is prone to aneurysm.
Classification. Compression is dynamic, static or traumatic, and most cases of QSS are dynamic, or functional:
- Dynamic: functional compression, in athletes
- Static: a structural mass, such as a cyst, tumour or osteophyte
- Traumatic: haematoma or scarring after trauma
Triangular interval syndrome is entrapment of the radial nerve at the lower border of teres major.
Clinical Assessment
QSS symptoms. Pain is vague and posterior, with paraesthesia in the regimental-badge area, although this is often absent in chronic cases. Weakness is subtle, fatigue-related and provoked by sustained overhead activity.
The vascular form. Thrombus in the PCHA can embolise distally, giving digital ischaemia, a cold hand or splinter haemorrhages.
QSS signs. Point tenderness over the quadrilateral space, lateral to the scapula, and symptoms reproduced by 1 minute of abduction-external rotation. Atrophy is often the only objective sign.
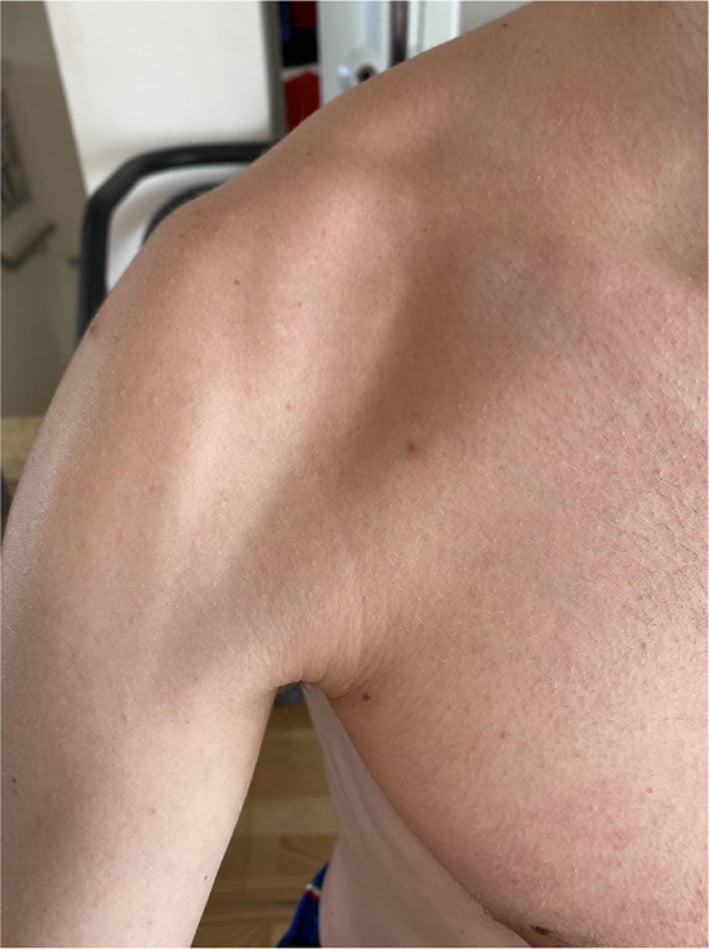
Triangular interval syndrome. Pain radiates down the posterior arm and forearm, with triceps weakness in which the medial head is often relatively spared, as its branch arises more proximally. The wrist and finger extensors weaken if the compression is severe or proximal.
The C7 mimic. Differentiation from C7 radiculopathy is essential. Triangular interval syndrome reproduces symptoms with radial nerve tension testing and local scapular palpation, without cervical provocation.
Axillary Nerve Injury after Dislocation or Fracture
The mechanism. The quadrangular-space anatomy is most often tested through trauma. The axillary nerve is the most commonly injured nerve in anterior shoulder dislocation, is frequently injured in proximal humerus fractures, is vulnerable in inferior dislocation, and is the nerve most at risk in shoulder surgery. The injury is a traction or stretch as the humeral head displaces, usually a neurapraxia or axonotmesis in continuity rather than a transection.
Examine before and after reduction. Document deltoid motor function by palpating the contracting muscle belly, because formal abduction testing is painful and unreliable acutely. Test sensation over the regimental-badge area, the territory of the superior lateral cutaneous nerve. An axillary-nerve palsy is not a contraindication to reduction.
Recovery. The majority recover spontaneously over about 3 to 6 months. Where axonal continuity is preserved the nerve regenerates at roughly 1 mm per day.
When to act. A persistent complete deficit at around 3 to 6 months warrants EMG/NCS and consideration of surgical exploration with nerve grafting, or a nerve transfer, for example a triceps branch of the radial nerve to the axillary nerve. A complete brachial-plexus pattern, an axillary-artery injury, or an irreducible or locked dislocation raises the urgency.
Investigations
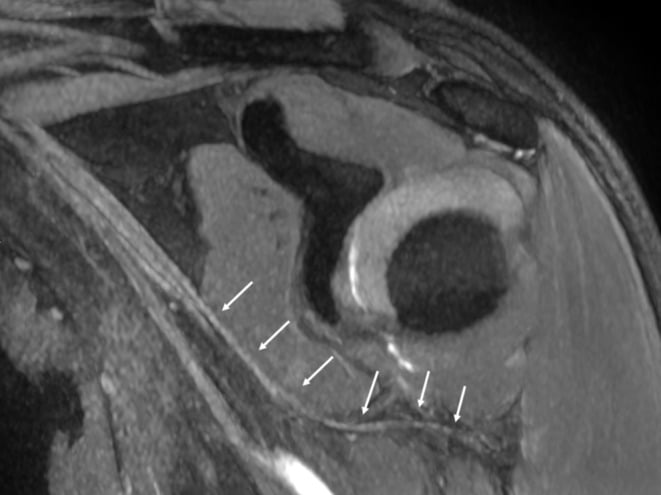
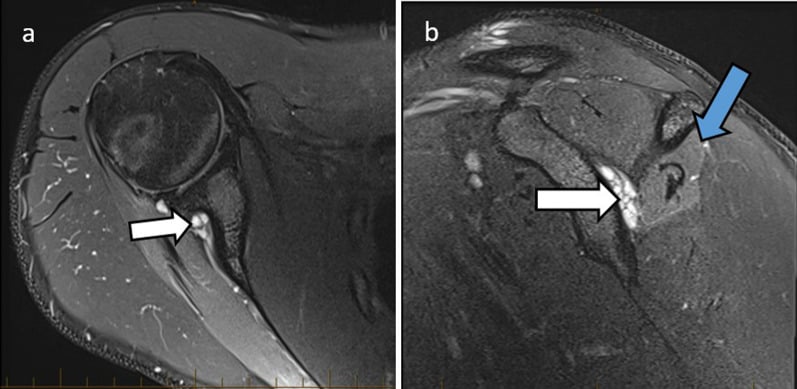
MRI. T1 shows fatty infiltration and T2 or STIR shows oedema, the denervation change of the acute phase. Look for paralabral cysts at the inferior labrum and for fibrous bands.
Teres minor atrophy. Isolated fatty atrophy of teres minor is the imaging hallmark of QSS, and it points to QSS or to isolated axillary nerve pathology such as Parsonage-Turner. It is sensitive but poorly specific, and the controversy below sets out why a single finding does not settle the diagnosis.
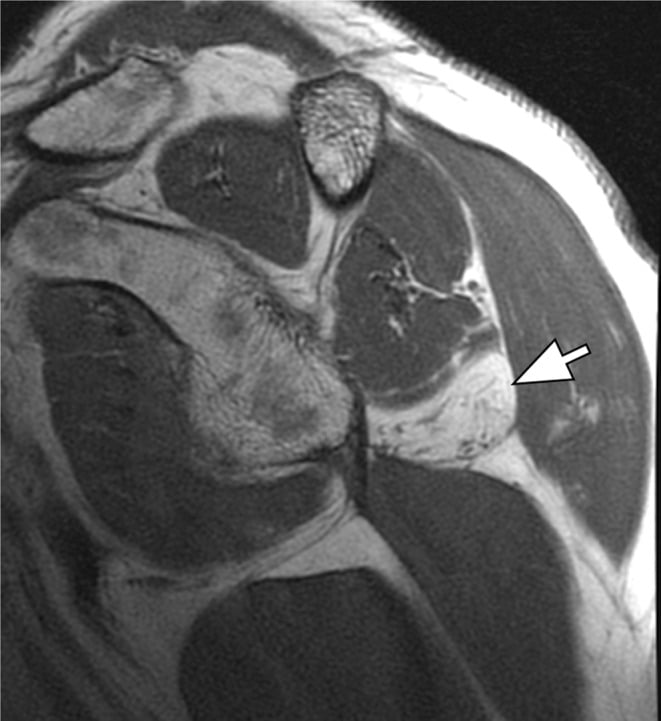
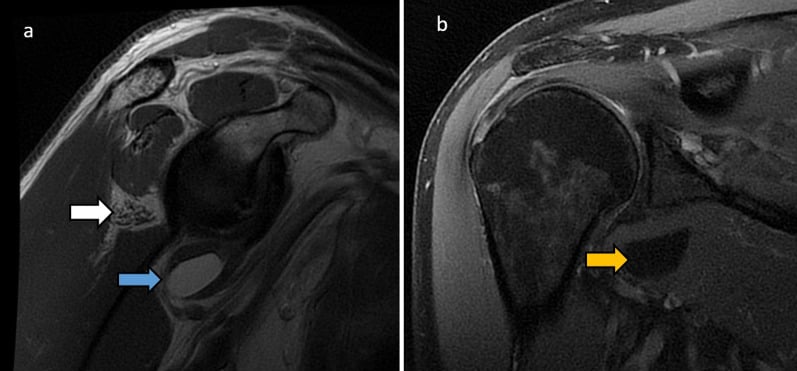
Vascular imaging. MR or CT angiography can show occlusion of the PCHA with abduction, the dynamic compression. Dynamic imaging is key for vascular compression.
Electrodiagnostics. EMG shows positive sharp waves and fibrillations in deltoid and teres minor. Its sensitivity is variable, and nerve conduction studies are often inconclusive.
Differential Diagnosis of Posterior Shoulder Pain & Teres Minor Atrophy
- Distinguishing Feature
- Overhead athlete, dynamic posterior pain
- Atrophy Pattern
- Isolated teres minor (axillary branch)
- Key Test
- Dynamic angiography / abduction-ER provocation
- Distinguishing Feature
- Acute severe pain then patchy palsy
- Atrophy Pattern
- Teres minor +/- deltoid +/- other muscles
- Key Test
- EMG: multifocal denervation
- Distinguishing Feature
- Older patient, cuff pathology on MRI
- Atrophy Pattern
- Teres minor with humeral decentering
- Key Test
- MRI cuff integrity
- Distinguishing Feature
- Spinoglenoid/paralabral cyst
- Atrophy Pattern
- Infraspinatus +/- supraspinatus (NOT teres minor)
- Key Test
- MRI cyst; EMG SSN
- Distinguishing Feature
- Neck pain, dermatomal sensory loss
- Atrophy Pattern
- Multi-muscle myotomal
- Key Test
- Spurling, cervical MRI
- Distinguishing Feature
- Posterior arm/forearm pain, radial bias
- Atrophy Pattern
- Triceps weakness, no teres minor atrophy
- Key Test
- Radial nerve tension test, no cervical provocation
Isolated teres minor atrophy points to the axillary nerve in the quadrilateral space. Isolated infraspinatus atrophy points to the suprascapular nerve at the spinoglenoid notch. Combined deltoid + teres minor denervation localises to the main axillary nerve trunk (e.g. dislocation, Parsonage-Turner).
Management
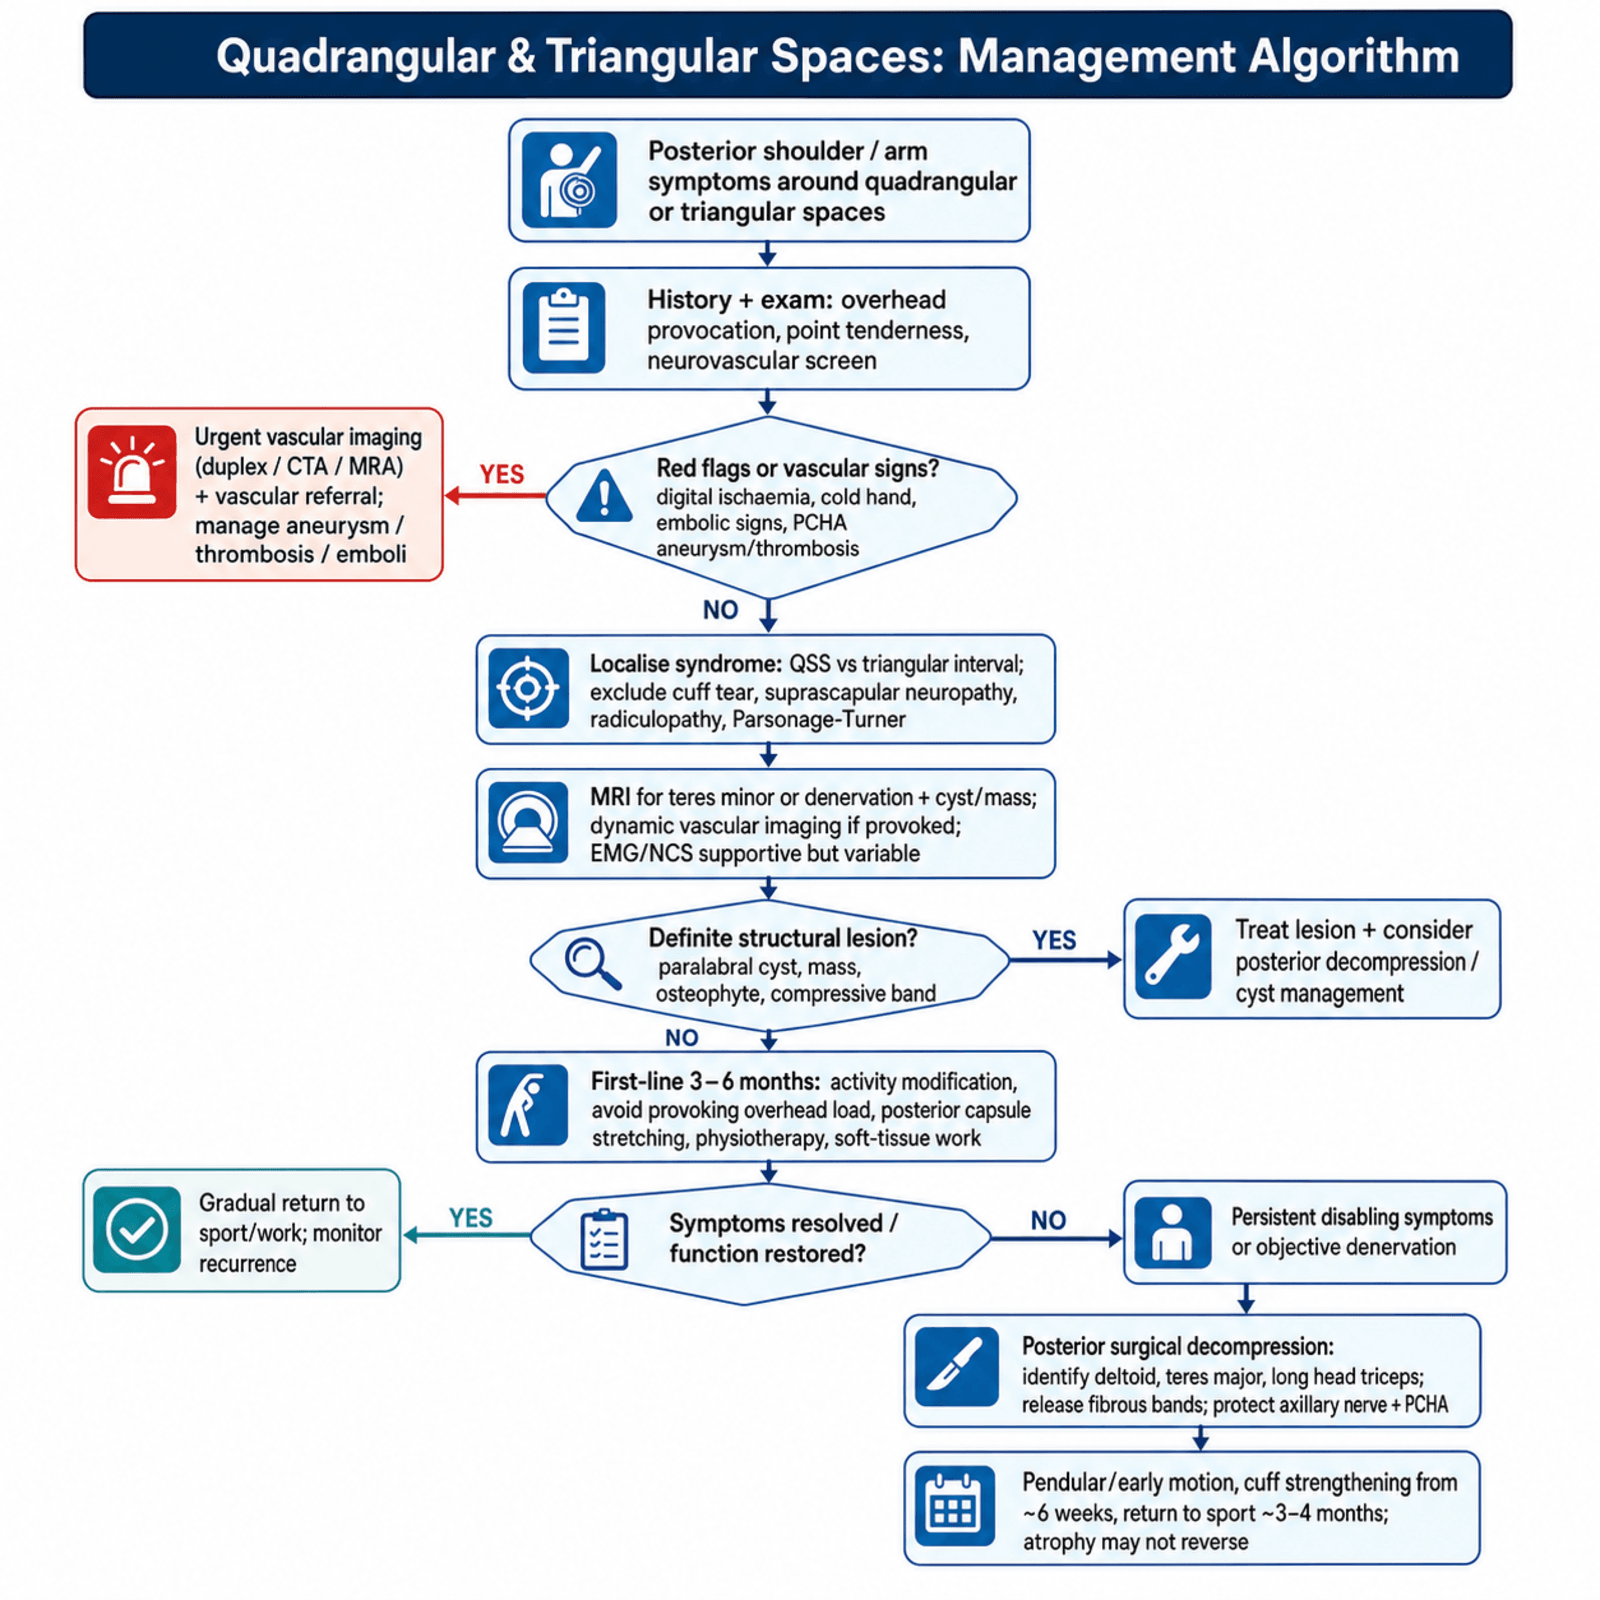
Conservative first. Conservative care is first line for 3-6 months: stretching of the posterior capsule, massage and activity modification. Success is high for functional QSS, and avoidance of the provoking activity, such as overhead throwing, is curative.
Surgical decompression. Indicated for failure of conservative treatment or a definite structural mass such as a cyst, through a posterior approach:
- Incise along the posterior axillary fold
- Identify deltoid, retracted superiorly, and teres major, inferiorly
- Identify the long head of triceps medially
- Release the fibrous bands over the nerve
The PCHA can bleed heavily.
Surgical Considerations
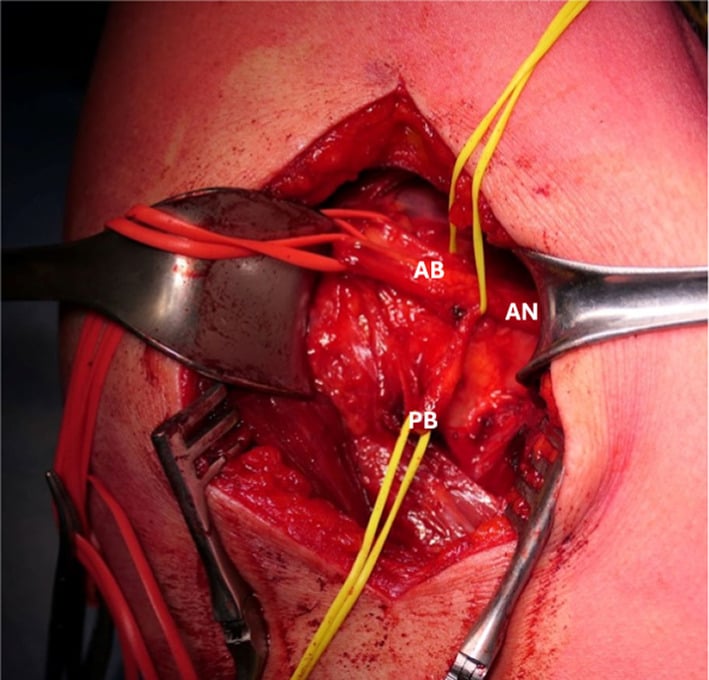
Posterior approach. The interval is between infraspinatus and teres minor. The axillary nerve exits the quadrangular space below teres minor, so stay superior to protect it as it exits.
Lateral deltoid split. The quadrangular space lies deep to deltoid, and the nerve winds around the humerus here. Its anterior branch runs roughly transversely 5 to 7 cm distal to the lateral or anterolateral acromion, but as close as about 3.5 cm in a small patient. Do not carry a deltoid split more than about 5 cm below the acromion, and place a transverse stay suture at the distal apex to stop the split propagating.
Deltopectoral approach. The nerve is also at risk inferiorly as it crosses subscapularis toward the inferior glenoid. Palpate it (the "tug test") before retracting.
Complications
- Nerve injury: iatrogenic injury to the axillary nerve during release, or to the radial nerve during plating
- Recurrence: inadequate release of the fibrous bands
- Bleeding: from the PCHA or circumflex scapular artery, during retraction
- Cosmetic: hypertrophy of the posterior scar
Rehabilitation and Prognosis
Rehabilitation. Pendular exercises start immediately and rotator cuff strengthening from 6 weeks. Overhead athletes return to sport at 3-4 months.
Prognosis. Decompression gives good relief of pain, but atrophy may not reverse.
Guidelines, Registries & Global Practice
Global epidemiology
- Quadrilateral space syndrome is rare and there is no dedicated registry; most evidence is cadaveric or small case series. It predominates in young (20-40y) overhead athletes (volleyball, baseball/cricket bowling, swimming, tennis) and in patients with paralabral cysts.
- Symptoms of digital ischaemia from PCHA disease have been reported in up to roughly a third of elite volleyball players, underlining the vascular variant of the condition.
Society/guideline positions (no condition-specific guideline exists)
- AAOS / ASES (US) and BOA-BESS (UK): no formal guideline for QSS; consensus from upper-limb literature favours prolonged conservative management first, with surgery reserved for refractory cases or a demonstrable structural lesion.
- AO Foundation / EFORT: relevant guidance is on the axillary nerve safe zone in deltoid-splitting and posterior approaches (protect the nerve 5-7 cm distal to the acromion), rather than on QSS itself.
- IOC / sports-medicine consensus: emphasise vascular work-up (Doppler/duplex, angiography) in overhead athletes with hand ischaemia before attributing symptoms to nerve compression alone.
Imaging & practice variation
- High-resource settings: MRI (denervation signal, paralabral cysts) plus MRA/CTA or dynamic duplex ultrasound for the vascular component; arthroscopic or open decompression available.
- Limited-resource settings: diagnosis rests on clinical provocation testing and plain radiographs to exclude bony causes; ultrasound (where skilled operators exist) is a low-cost dynamic tool; management is predominantly conservative.
Controversies & Areas of Uncertainty
Do fibrous bands really cause QSS? Cahill and Palmer's original cadaveric work did not consistently identify discrete bands, yet later dissection (McClelland and Paxinos) found bands in 14 of 16 shoulders, most often between teres major and the long head of triceps. Their pathological significance versus normal anatomical variation remains debated.
Neurogenic or vascular QSS? Whether QSS is primarily an axillary nerve compression or a PCHA disease, with aneurysm or thrombosis and distal embolisation, is unsettled. The two may be distinct entities sharing a name, which affects whether decompression or vascular intervention is appropriate.
Is isolated teres minor atrophy diagnostic? MRI series show that isolated teres minor atrophy is far more often associated with cuff tears, humeral decentering or idiopathic traction than with true compressive QSS, which is rare. The finding is sensitive but poorly specific.
Open or arthroscopic decompression? Evidence is limited to small case series, and no comparative trials define the optimal surgical technique, indications or timing. Most authorities reserve surgery for refractory cases or a demonstrable structural lesion: a paralabral cyst, mass or aneurysm.
MCQ Practice Points
Q: Which structure passes through the Quadrangular Space? A: Axillary Nerve. (And PCHA).
Q: The Triangular Interval transmits which nerve? A: Radial Nerve.
Q: The Triangular Space is bounded inferiorly by which muscle? A: Teres Major.
Q: The Circumflex Scapular Artery is found in which space? A: Triangular Space.
Q: What sensory area is supplied by the axillary nerve after exiting the Quadrangular Space? A: The 'Regimental Badge' area - lateral upper arm over the deltoid insertion. This is via the Superior Lateral Cutaneous Nerve of Arm branch.
Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 25-year-old volleyball player presents with vague posterior shoulder pain and weakness. MRI shows isolated fatty infiltration of Teres Minor. Diagnosis?”
“During a scapular flap harvest, you identify a vessel in the Triangular Space. Which vessel is it and where does it go?”
“Trace the course of the Radial Nerve relative to the Triceps heads.”
Quadrangular Space
- Superior: Teres Minor (Subscapularis anteriorly)
- Inferior: Teres Major
- Medial: Long Head Triceps
- Lateral: Surgical Neck Humerus
- Content: Axillary Nerve
- Content: Posterior Circumflex Humeral Artery
Triangular Space
- Superior: Teres Minor
- Inferior: Teres Major
- Lateral: Long Head Triceps
- Content: Circumflex Scapular Artery
- Note: No major nerve
- Clinical: Scapular Anastomosis
Triangular Interval
- Superior: Teres Major
- Medial: Long Head Triceps
- Lateral: Humerus Shaft
- Content: Radial Nerve
- Content: Profunda Brachii Artery
- Clinical: Interval Syndrome (Radial palsy)
Evidence Base
Cahill's 1983 paper defined the syndrome and the posterior decompression; McClelland's cadaveric study supplies the fibrous-band substrate; and the imaging series (Wilson, Cothran, Friend) consistently show that isolated teres minor atrophy is usually NOT true compressive QSS — most often it accompanies cuff/labral pathology — making the finding sensitive but not specific.
Quadrilateral space syndrome
- Landmark paper that defined the syndrome: compression of the axillary nerve and PCHA in the quadrilateral space
- Symptoms aggravated by forward flexion, abduction and external rotation; constant point tenderness posteriorly
- Subclavian arteriography showed PCHA occlusion with the arm in abduction-external rotation
- Of 18 patients operated via a posterior approach: 8 complete relief, 8 improved, 2 no improvement
The anatomy of the quadrilateral space with reference to quadrilateral space syndrome
- 16 cadaveric shoulders dissected to clarify the anatomy predisposing to QSS
- Fibrous bands present in 14 of 16 shoulders, most commonly between teres major and the long head of triceps
- Where bands were present, both internal and external rotation reduced the cross-sectional area of the quadrilateral space
Teres minor innervation in the context of isolated muscle atrophy
- Combined cadaveric (9 specimens) and radiological study of the teres minor nerve supply
- Marked anatomical variation in origin and length of the teres minor nerve(s), creating multiple potential impingement points
- Of 61 shoulder MRIs, 2 showed isolated teres minor atrophy, clinically distinct from quadrilateral space syndrome
Isolated teres minor atrophy: manifestation of quadrilateral space syndrome or traction injury to the axillary nerve?
- Prospective review of 217 consecutive shoulder MRIs
- Isolated teres minor atrophy in 12 (5.5%), mean age 60, 11 of 12 male
- 92% had associated rotator cuff or labroligamentous tears; none had a quadrilateral space mass
- True QSS appears to be a very rare cause of isolated teres minor atrophy