Direct Impact Injury | Flexion Key Prognostic Factor | Myositis Ossificans Prevention Critical
- Knee flexion at 24 hours is the key prognostic indicator
- Immediate 120 degree flexion position reduces haematoma and speeds recovery
- Myositis ossificans develops in 9-17%, more common with severe grades
- Avoid early aggressive ROM and massage - increases MO risk
- NSAIDs and aspiration have role in preventing myositis ossificans
- “Jackson and Feagin: military cadets in flexion splints recovered in 13 days, against 88 days with extension splinting
- “Never massage a quadriceps contusion - promotes MO development
- “Heterotopic ossification appears on X-ray at 3-4 weeks post-injury
- “Compartment syndrome rare but possible - monitor tight thighs
Overview and Epidemiology
Quadriceps contusions are the second most common injury in contact sports after muscle strains. A direct blunt blow to the anterior thigh causes intramuscular haemorrhage and tissue damage.
Mechanism. The injury is a direct impact, most commonly a knee or helmet striking the front of the thigh.
- Direct blow - knee or helmet strike (most common)
- Contact sports - rugby, Australian football, martial arts, football
- Falls - direct impact onto a hard surface
- Motor vehicle accidents - the dashboard injury
Who. Rugby and Australian Rules football have the highest incidence. In American football it is common in receivers and running backs, in hockey it follows puck or stick trauma, and in combat sports it follows knee strikes.
Anatomy and Pathophysiology
The quadriceps. The rectus femoris is the only biarticular head and a hip flexor. Vastus lateralis is the largest and lies laterally, vastus medialis lies medially, where the VMO is critical for patellar tracking, and vastus intermedius is the deepest, directly on the femur.
Why vastus intermedius. It is the head most commonly injured, because it lies directly on the femur with no muscle posterior to it to provide cushioning. The rectus femoris is protected by the intermedius layer.
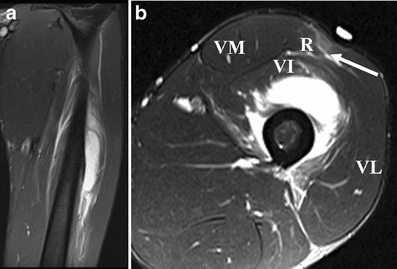
Blood supply. Branches of the profunda femoris, the lateral and medial circumflex femoral arteries, supply the group. That rich supply explains the size of the haematoma that forms, and the intramuscular bleeding is contained by fascia.
Contusion Evolution
Acute haemorrhage into the muscle belly. Vasospasm initially limits bleeding, and the haematoma begins forming in the intramuscular space.
The inflammatory response peaks and oedema develops. Range of movement falls rapidly; this is the critical window for classification by flexion.
Haematoma organisation and fibroblast migration begin, with continued inflammation. The key period for flexion positioning.
Granulation tissue and early scar form. The risk period for myositis ossificans if the tissue is re-injured or aggressively mobilised.
Muscle regeneration, with satellite cell activation. Progressive strengthening is safe to begin if pain-free.
Myositis ossificans. Heterotopic bone forms when pluripotent mesenchymal cells differentiate into osteoblasts instead of myoblasts. The risk factors, and what to do about them, are under Complications.
Classification Systems
Three systems are in use. Ryan and Jackson-Feagin both grade on knee flexion; the third describes where the bleeding lies.
The Ryan classification grades the contusion on knee flexion measured at 24 hours, and it is the most commonly used. It is the most practical because it rests on a single objective measure taken at a standardised time point, which predicts prognosis, guides treatment intensity and helps you counsel athletes and coaches.
- Knee Flexion at 24h
- Greater than 90 degrees
- Gait
- Normal
- Swelling
- Minimal
- Recovery Time
- 2-3 weeks
- Knee Flexion at 24h
- 45-90 degrees
- Gait
- Antalgic
- Swelling
- Moderate
- Recovery Time
- 3-6 weeks
- Knee Flexion at 24h
- Less than 45 degrees
- Gait
- Unable to walk
- Swelling
- Severe
- Recovery Time
- Greater than 6 weeks
Read the recovery column as clinical expectation rather than Ryan's own figures. In his West Point series the mean disability was 13, 19 and 21 days for mild, moderate and severe contusions, and Aronen's midshipmen, placed in 120 degrees of flexion immediately, returned to unrestricted activity in a mean of 3.5 days (see the Evidence Base).
Clinical Assessment
History. Establish the mechanism, the contact event and the speed of impact, and the time since injury, because the grade is assigned at 24 hours. Ask whether the athlete was able to carry on playing: a yes is a poor prognostic sign, suggesting ongoing bleeding. Previous quadriceps contusions are a risk factor for recurrence, and anticoagulation increases the bleeding risk.
Red flags. Ask specifically about:
- Severe pain out of proportion
- Numbness in the leg
- Progressive swelling despite rest
- Inability to bear weight at all
Examination. Look at the site and extent of the swelling, the muscle contour for a bulge or defect, and for ecchymosis, which may appear 24-48 hours later. Feel for the point of maximal tenderness, a palpable haematoma or mass, and warmth. Test resisted knee extension and the straight leg raise, and document any quadriceps lag.
Range of movement is the measurement that matters. Record active and passive knee flexion against the uninjured side, and document the angle at 24 hours for classification. Then repeat it daily in the first week and document the trajectory: a range that plateaus or worsens is a concern.
Function. Gait (antalgic or normal), a single-leg squat for functional strength, and step-up and step-down for eccentric control.
A tense thigh. Compartment syndrome is rare but requires urgent fasciotomy; its signs and the pressure thresholds are under Complications.
- Distinguishing Features
- Direct blunt blow, diffuse intramuscular swelling, ROM loss tracks severity
- Key Investigation
- Clinical grading by 24h flexion; ultrasound for haematoma
- Distinguishing Features
- Indirect eccentric overload (sprinting), pain at musculotendinous junction, no impact history
- Key Investigation
- Ultrasound/MRI showing fibre disruption at junction
- Distinguishing Features
- Persistent firm mass and ROM plateau weeks after contusion
- Key Investigation
- Radiograph at 3-4 weeks (peripheral zoning); CT if uncertain
- Distinguishing Features
- Pain out of proportion, tense compartment, pain on passive stretch, saphenous paraesthesia
- Key Investigation
- Compartment pressure; urgent fasciotomy
- Distinguishing Features
- High-energy mechanism, deformity, inability to bear weight
- Key Investigation
- Plain radiograph
- Distinguishing Features
- Painless enlarging mass, no clear trauma, deep to fascia, more than 5 cm
- Key Investigation
- MRI then biopsy of periphery; do NOT assume myositis ossificans
The Morel-Lavallée lesion. A blunt tangential or shearing blow to the thigh, the same rugby, AFL or road mechanism, can also produce a closed internal degloving. The skin and subcutaneous fat are sheared off the underlying fascia, tearing perforating vessels and lymphatics, and the new potential space fills with a haemolymphatic collection. Unlike a contusion's intramuscular haematoma it sits in the subcutaneous-fascial plane, classically over the greater trochanter or proximal thigh.
It presents as a fluctuant, sometimes mobile swelling with overlying skin hypoaesthesia and ecchymosis, and may enlarge or present late. MRI shows the characteristic fluid collection between fat and fascia, often with a capsule. It is its own diagnosis because management differs: small or acute lesions get compression, persistent collections need percutaneous drainage and sclerodesis (e.g. doxycycline) or operative debridement, and a chronic encapsulated lesion can become infected or recur. Suspect it whenever a "contusion" is fluctuant, superficial and not resolving.
Investigations
Radiographs are not routinely required for a typical contusion. Take one to rule out fracture when a fracture is suspected after significant trauma or the contusion is severe. It also provides a baseline for monitoring myositis ossificans, which becomes visible at 3-4 weeks.
Ultrasound is the first-line imaging for the soft tissue. It quantifies the size of the haematoma, differentiates intramuscular from intermuscular collections, assesses muscle integrity dynamically and can guide aspiration. An acute haematoma is hypoechoic or anechoic and becomes more heterogeneous as it organises; early myositis ossificans shows increased echogenicity before calcification is visible on X-ray.
MRI is reserved for severe grades or diagnostic uncertainty. It quantifies the extent of muscle damage, identifies associated injuries, and is useful for return-to-play decisions in elite athletes.
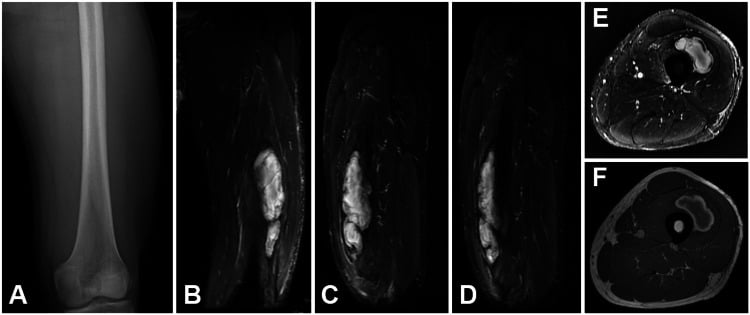
Blood tests are generally not required for a typical sports contusion. CK is elevated with muscle damage; check a coagulation screen if the patient is anticoagulated or bleeding excessively, and a full blood count as a baseline if significant blood loss is suspected.
Imaging myositis ossificans. Radiographs follow the lesion from a normal film to mature bone over 3-6 months.
- X-ray Finding
- Normal
- Clinical Correlation
- Pain, mass may be palpable
- X-ray Finding
- Faint calcification
- Clinical Correlation
- Zoning phenomenon begins
- X-ray Finding
- Mature peripheral bone
- Clinical Correlation
- Central lucency visible
- X-ray Finding
- Mature MO
- Clinical Correlation
- Corticated periphery
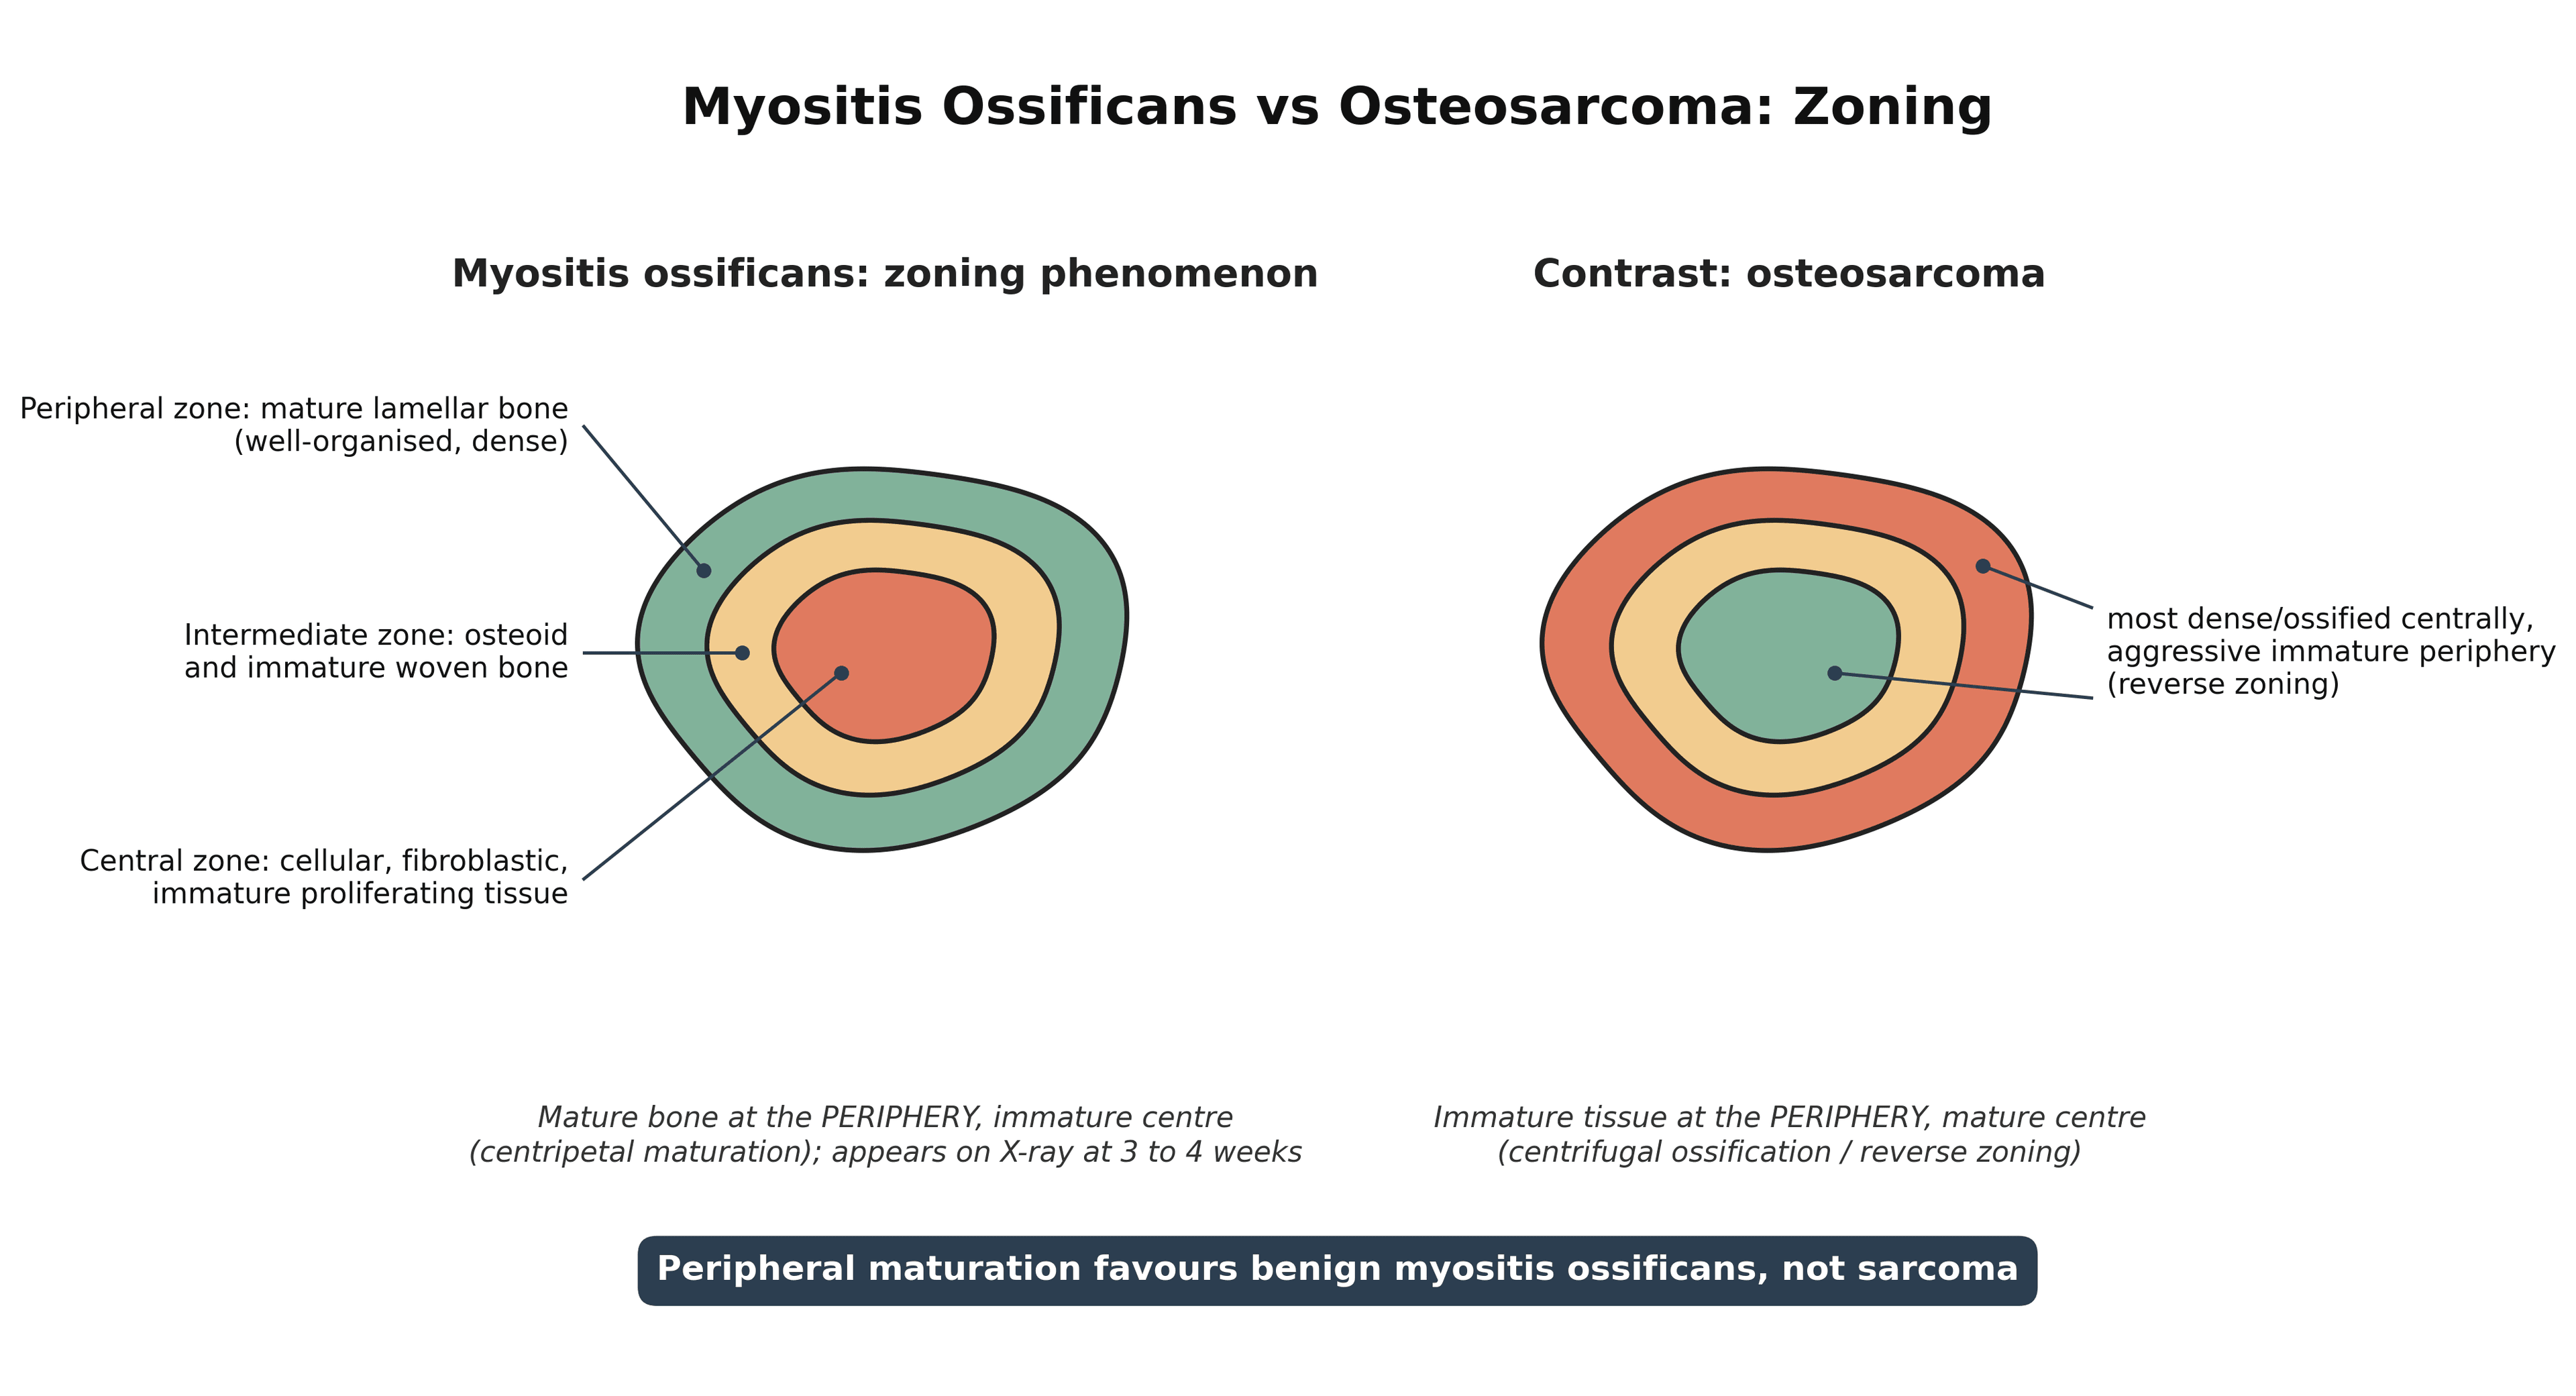
Myositis ossificans has mature bone at periphery (zoning). Osteosarcoma has immature bone peripherally. If uncertain, biopsy the PERIPHERY not the centre to avoid missing malignancy.
Management
First aid. Take the athlete off: they should not continue with the injury. Start RICE immediately.
- Ice - 20 minutes every 2 hours for the first 48-72 hours
- Compression - an elastic wrap, applied with the knee flexed
- Elevation - above heart level
- Crutches - non-weight bearing to partial weight bearing
The flexion position. In the Jackson-Feagin protocol the knee is wrapped in maximal comfortable flexion, aiming for 120 degrees, with an elastic bandage over an ice pack, and held for 24 hours initially. Flexion compresses the haematoma between the rectus femoris and vastus intermedius, limiting its expansion, and keeps the muscle at length, preventing adaptive shortening. In Jackson and Feagin's military study recovery took 13 days, against 88 days with extension splinting.
What to avoid. No heat, massage or aggressive stretching in the first 2-3 weeks. Never massage an acute contusion.
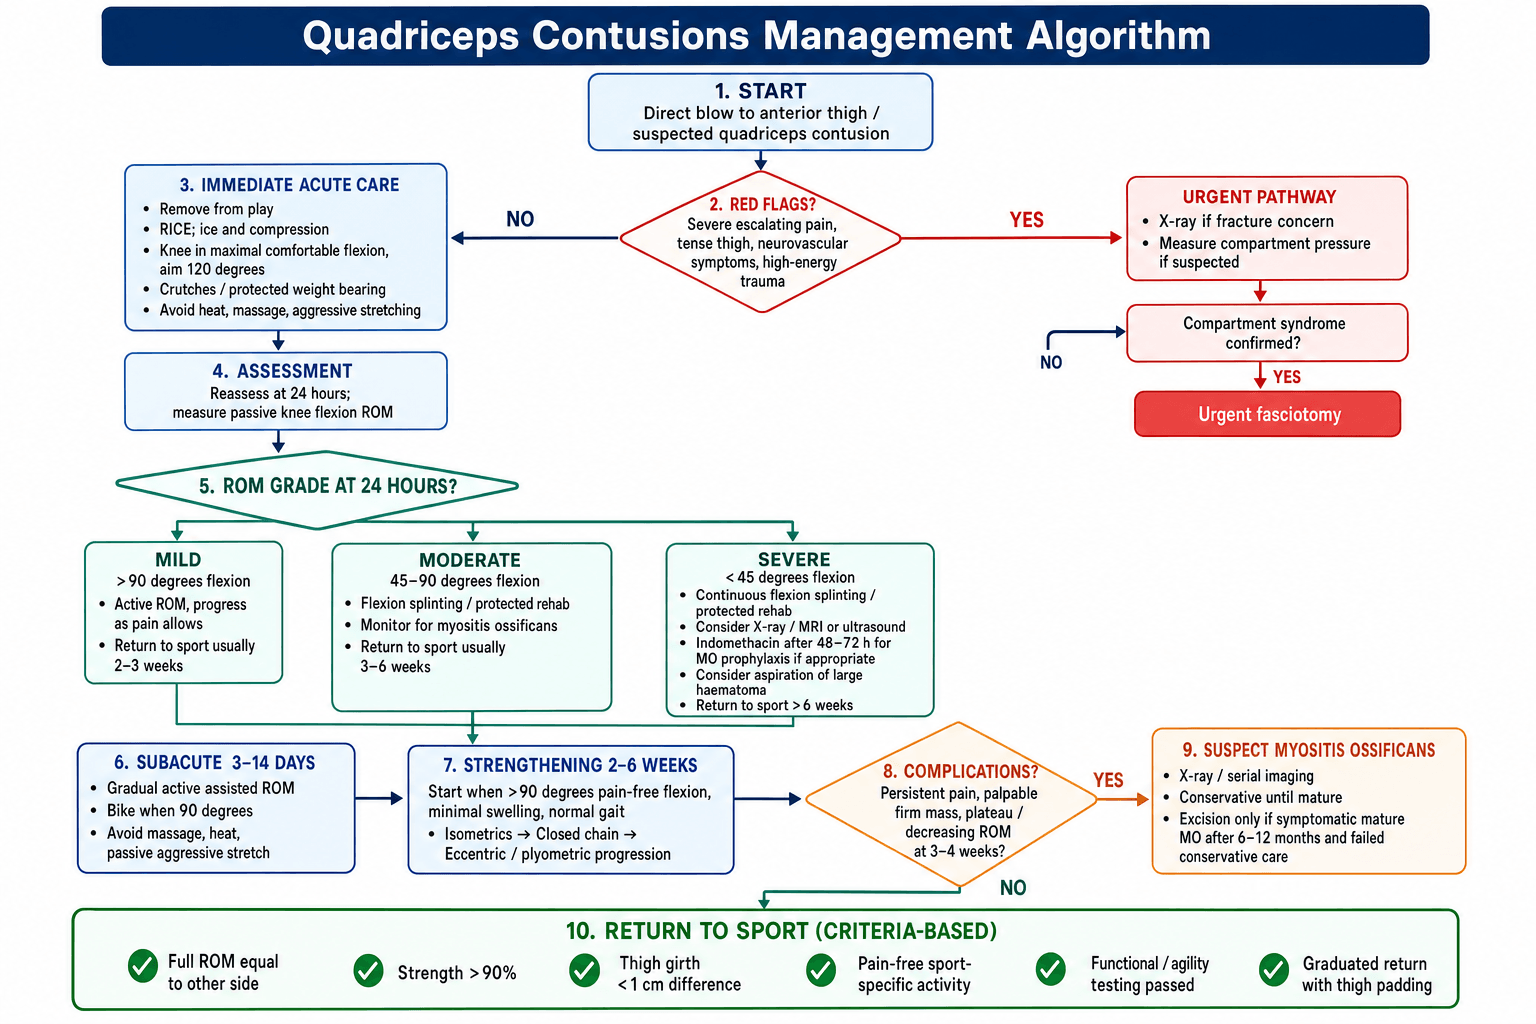
Treatment by grade. Reassess passive knee flexion at 24 hours, grade the injury, and treat the grade:
- Mild (over 90 degrees) - RICE and active range of movement, crutches as needed, progressing as pain allows
- Moderate (45-90 degrees) - flexion splint for 24 hours, protected rehabilitation, consider NSAIDs, and monitor for myositis ossificans
- Severe (under 45 degrees) - continuous flexion splinting and protected rehabilitation; consider indomethacin prophylaxis and MRI, and aspiration of a large haematoma, which may help
Analgesia. Paracetamol is preferred early. NSAIDs are avoided for the first 48-72 hours: early use is controversial, they may increase bleeding, and they are not yet needed.
Why the NSAID is timed. The delay is a genuine trade-off, not only bleeding risk. By inhibiting cyclo-oxygenase and the prostaglandin-driven inflammatory phase, NSAIDs, especially indomethacin, suppress the heterotopic-ossification pathway, which is their value for myositis ossificans prophylaxis. That same early inflammatory phase drives satellite-cell activation and muscle regeneration, and experimental work shows NSAIDs can blunt myoblast proliferation and impair the quality and strength of muscle repair.
So the course is reserved for prophylaxis in moderate-to-severe contusions, where the heterotopic-bone risk outweighs the small regenerative cost, and it starts after 48-72 hours, with indomethacin in the severe grades.
Surgical Technique
When to operate. Surgery is rarely required for a quadriceps contusion. The primary indication is symptomatic mature myositis ossificans that has failed conservative management:
- Persistent pain limiting function after the lesion has matured
- Mechanical symptoms (limited range, catching)
- A large lesion causing cosmetic concern
- Failed conservative management for 6 months or more
When not to. Immature myositis ossificans (less than 6 months, a hot bone scan), an asymptomatic lesion and active infection are contraindications.
Timing and work-up. Excision waits a minimum of 6-12 months from injury, and never less than 6. A mature lesion has corticated margins on imaging and is cold on bone scan, with no active uptake. CT defines the extent of the lesion and its relationship to the neurovascular structures, and MRI assesses the quality of the remaining muscle.
Never excise immature MO - recurrence rates approach 50% with premature surgery. Bone scan confirmation of maturity is mandatory.
Excision. Complete excision with clear margins reduces the risk of recurrence.
- Positioning - supine with a bump under the ipsilateral hip; a tourniquet on the upper thigh if feasible, though it may not be possible, depending on where the lesion lies
- Approach - direct anterior or anterolateral, centred over the lesion, with a longitudinal incision through skin and fascia; identify and protect the lateral femoral cutaneous nerve if the lesion is proximal
- Dissection - dissect the lesion carefully from the surrounding muscle, maintain haemostasis and preserve as much healthy muscle as possible; it usually shells out of the muscle bed
- Excision - remove it completely with a margin of reactive tissue, leave no residual ossified tissue, and irrigate copiously
- Closure - layered closure over a drain, fascia closed if possible, and a compression dressing
After excision. In selected patients adjuvant therapy significantly reduces recurrence.
- Indomethacin - 75 mg daily for 6 weeks, to reduce recurrence of heterotopic ossification; contraindicated if there is a risk of GI bleeding
- Radiation - a single dose of 700 cGy within 72 hours of surgery, reserved for recurrent myositis ossificans or high-risk cases; effective but rarely needed
- Rehabilitation - gentle range of movement from day 1-2, no aggressive stretching, progressive strengthening at 4-6 weeks
Complications
Myositis ossificans traumatica follows 9-17% of quadriceps contusions. The risk factors:
- Severe grade (flexion less than 45 degrees at 24 hours)
- A large intramuscular haematoma
- Treatment delayed more than 72 hours
- Early massage, or over-aggressive rehabilitation with passive stretching too early
- Continuing to play after the injury, or inadequate rest with insufficient immobilisation
- Re-injury before full healing, including a return to sport too soon
- Previous myositis ossificans
Recognising it. Pain persists beyond the expected recovery, a firm mass becomes palpable in the muscle, the range plateaus or falls, and activity hurts. The radiographic course is under Investigations.
Treating it. Initially conservative, waiting for maturation; NSAIDs may limit progression if it is caught early. Excision is reserved for a lesion that is both symptomatic and mature (see Surgical Technique).
Anterior thigh compartment syndrome is rare but reported, particularly with anticoagulation, coagulopathy, a massive contusion or a vascular injury. The signs:
- Pain out of proportion
- Pain on passive knee flexion (stretch)
- A tense thigh compartment
- Paraesthesia in the saphenous nerve distribution
- Weakness of knee extension
Pressures and fasciotomy. Measure compartment pressure if it is suspected. A pressure greater than 30 mmHg, or within 30 mmHg of the diastolic pressure, is concerning, and confirmed compartment syndrome needs emergent fasciotomy.
Thigh compartment syndrome is rare but devastating if missed. Low threshold for pressure measurement in anticoagulated patients or those with severe contusions not improving as expected.
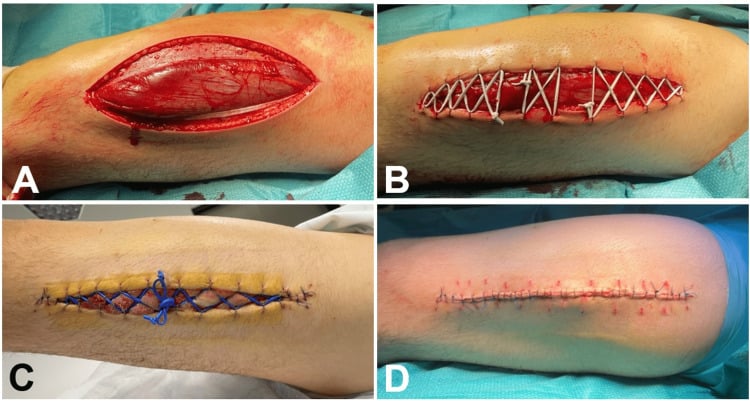
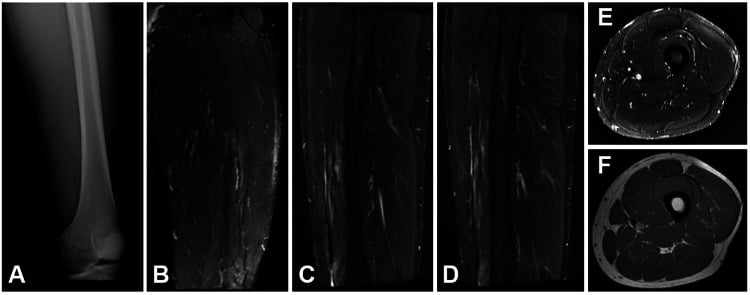
Other complications.
- Recurrent contusion - from returning to sport too early or inadequate protective padding; may lead to chronic pain and myositis ossificans
- Chronic pain - from incomplete healing and scar tissue formation; may require imaging work-up
- Femoral fracture (rare) - a high-energy mechanism; rule it out with an X-ray after significant trauma
- Muscle herniation - through a fascial defect; usually asymptomatic, and repair is rarely needed
Rehabilitation and Return to Sport
Rehabilitation Phases
RICE, 120 degree flexion positioning, crutches and ice every 2 hours, as under Management. The goal is to minimise haematoma size and inflammation: no stretching or strengthening.
Restore range gradually, prevent atrophy and avoid re-injury. Active and active-assisted flexion and prone knee hangs, continued ice, and a progression of pain-free weight bearing; the stationary bike once 90 degrees of flexion is achieved. Avoid massage, heat, aggressive passive stretching and electrical stimulation over the injury site. Progress as pain-free range increases, swelling decreases and gait normalises.
Starts once there is more than 90 degrees of pain-free flexion, minimal swelling and a normal gait. Isometrics progress to isotonics, in sequence: isometrics (quad sets, straight leg raise), closed chain (wall sits, mini squats), light open-chain leg extension, then eccentric loading (step-downs). Pool running and swimming are permitted. Check range daily, compare thigh girth, and use isokinetic testing when available.
Sport-specific drills and agility training, with plyometrics once strength is greater than 80 percent. Non-contact training first, then contact with padding.
Criteria met, then a graduated return: non-contact training, contact training with padding, full contact, full competition. Monitor for any symptoms.
Return to sport. All the criteria must be met; meeting them minimises the risk of re-injury and of myositis ossificans.
- Requirement
- Equal to uninjured side
- Testing Method
- Goniometry
- Requirement
- Greater than 90 percent
- Testing Method
- Isokinetic or 1RM
- Requirement
- Less than 1cm difference
- Testing Method
- Tape measure
- Requirement
- None with activity
- Testing Method
- Functional testing
- Requirement
- Pass hop tests and agility testing
- Testing Method
- Single leg hop for distance
Padding. Protective thigh padding is recommended for the first 2-4 weeks of competition after return, and reduces the risk of re-injury significantly.
The elite athlete. In professional athletes MRI may be used to confirm complete muscle healing before return. Some teams use isokinetic testing, comparing peak torque and total work with the uninjured side, and require more than 90 percent symmetry.
Outcomes and Prognosis
The outlook. Most athletes return to their pre-injury level. Full recovery is expected after a mild or moderate contusion, while a severe one may have a prolonged course. The risk of myositis ossificans by grade is low (under 5%) for mild, moderate (10-15%) for moderate and high (15-20%) for severe contusions. Chronic pain is rare if the injury is properly managed; a recurrent contusion is possible if the return to sport is too early, and myositis ossificans may need delayed excision.
What changes it. Knee flexion at 24 hours remains the key prognostic indicator. Beyond the grade, outcome depends on how early treatment starts, compliance with flexion positioning, avoiding re-injury during recovery and strict adherence to the return-to-sport criteria. Athletes who follow the Jackson-Feagin flexion protocol and meet every criterion have excellent outcomes with low recurrence rates, and premature return is the main risk factor for complications.
Guidelines, Registries & Global Practice
Global epidemiology:
- Figure
- Contusion second only to strain as cause of sports-injury morbidity
- Source
- Beiner & Jokl (PMID 11476532)
- Figure
- Among most common injury categories over five seasons
- Source
- Larruskain et al (PMID 28207979)
- Figure
- 4.82x higher incidence in men vs women (contact exposure)
- Source
- Larruskain et al (PMID 28207979)
- Figure
- 9% of quadriceps contusions (up to 9-17% in series)
- Source
- Ryan et al (PMID 1867338)
The injury is fundamentally a contact-sport problem and is over-represented wherever collision codes dominate (the football codes, rugby, American football, ice hockey, martial arts and combat sports). The driver is exposure to direct blunt impact rather than any geographic or health-system factor.
Guidance and consensus, side by side:
There is no high-level RCT-based guideline body that issues a quadriceps-contusion-specific protocol; practice is built on the West Point/Naval Academy military series and sports-medicine consensus, which are remarkably consistent worldwide.
- Position
- Immediate sustained knee flexion (aim 120 degrees), grade by 24-hour ROM, avoid heat/massage
- Evidence level
- Level IV consensus from prospective military series
- Position
- RICE plus early protected flexion; criteria-based graded return
- Evidence level
- Expert consensus
- Position
- Same acute principles; emphasis on ultrasound/MRI grading and objective return-to-sport testing
- Evidence level
- Expert consensus
- Position
- Exclude fracture and compartment syndrome; conservative care for isolated contusion
- Evidence level
- Expert consensus
There is no joint or implant registry relevant to this soft-tissue injury, so registry-based survival or revision data do not apply.
Global practice variation:
- Typical approach
- Immediate pitch-side flexion bracing, early ultrasound/MRI, isokinetic-guided return
- Reason
- Resourced medical teams, financial stakes of recurrence
- Typical approach
- Clinical grading by ROM, RICE, physiotherapy-led rehabilitation, imaging only if severe or atypical
- Reason
- Cost-effective and adequate for most cases
- Typical approach
- Clinical diagnosis and graded rehabilitation without routine imaging
- Reason
- Imaging access constrained; clinical course usually sufficient
Across every region and resource setting the core message is identical: immediate sustained flexion, grade by 24-hour ROM, avoid heat and massage, and use objective criteria for return to sport. Premature return is the dominant modifiable risk factor for recurrence and myositis ossificans.
MCQ Practice Points
Q: What is the key prognostic indicator for recovery time in quadriceps contusions? A: Knee flexion at 24 hours. Recoveries vary from 2-3 weeks (greater than 90 deg) to greater than 6 weeks (less than 45 deg).
Q: What is the most important acute intervention? A: Immediate 120 degree knee flexion positioning. This compresses the hematoma and prevents stiffness.
Q: What radiographic sign distinguishes Myositis Ossificans from malignancy? A: Zoning Phenomenon. MO has mature cortical bone peripherally with a central lucency. Osteosarcoma is the reverse (central ossification, indistinct margin).
Q: What modalities should be absolutely avoided in the acute phase? A: Heat and Massage. Both increase blood flow and risk of Myositis Ossificans.
Q: What is a mandatory criterion for return to contact sports? A: Full ROM and greater than 90% Strength. Plus protective padding is essential.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 22-year-old rugby player presents 6 hours after a direct knee strike to his anterior thigh. He has marked swelling and can only flex his knee to 30 degrees. How would you manage this player?”
“A footballer returns 4 weeks after a moderate quadriceps contusion with persistent pain and a firm palpable mass in the anterior thigh. X-ray shows early calcification. How would you manage this?”
“A professional AFL player sustained a moderate quadriceps contusion 5 weeks ago. He has regained 100 degrees of knee flexion and wants to return for finals. The coach is putting pressure on medical staff. How do you approach this?”
Classification (Ryan)
- Mild: Flexion greater than 90 degrees at 24h - RTS 2-3 weeks
- Moderate: Flexion 45-90 degrees - RTS 3-6 weeks
- Severe: Flexion less than 45 degrees - RTS greater than 6 weeks
- Prognosis: 24h ROM is key predictor
Acute Management
- IMMEDIATE 120 degree flexion positioning
- RICE protocol - ice 20 min every 2 hours
- Non-weight bearing with crutches
- NSAIDs AFTER 48-72h only (bleeding risk earlier)
Jackson-Feagin Protocol
- Wrap knee in maximal comfortable flexion
- Elastic bandage over ice pack
- Reduced recovery 88 days to 13 days
- Compresses hematoma between muscle bellies
Myositis Ossificans
- Develops in 9-17% of quad contusions
- Visible on X-ray at 3-4 weeks
- ZONING phenomenon = mature bone peripherally
- Surgery only after maturation (6-12 months)
Return to Sport Criteria
- Full ROM equal to uninjured side
- Strength greater than 90 percent (isokinetic)
- Thigh girth within 1cm
- Pain-free with sport-specific activity
Key Exam Points
- Never massage acute quad contusion
- Avoid heat and aggressive stretching early
- MO vs Osteosarcoma: zoning phenomenon key differentiator
- Compartment syndrome rare but possible - high suspicion
Evidence Base
Jackson-Feagin Study (1973) - Landmark
- Severity of injury correlates directly with disability and complication rate
- Heat, massage and premature activity were associated with worse outcomes and myositis ossificans
- Established graded rehabilitation and the principle of early protected motion
Ryan et al - West Point Update (1991) - Landmark Classification
- 24-hour knee ROM is the key prognostic indicator and basis of the grading system
- Mean disability 13 days (mild), 19 days (moderate), 21 days (severe)
- Myositis ossificans in 9%; five risk factors - ROM less than 120 degrees, football mechanism, previous quadriceps injury, treatment delay greater than 3 days, ipsilateral knee effusion
Aronen et al - Immediate 120 degree Flexion Immobilisation (2006)
- Immediate 120 degree flexion held for 24 hours dramatically shortened disability (mean 3.5 days)
- Only 1 case of myositis ossificans on 3- and 6-month radiographs of the first 23 patients
- Earlier intervention from the moment of injury improved results compared with prior series
Diaz et al - Severe Quadriceps Contusions (2003)
- Severe contusions produce large intramuscular haematoma and markedly prolonged recovery
- Imaging (ultrasound/MRI) defines haematoma size and guides rehabilitation
- Highlights need for protected, graded return to avoid re-injury and myositis ossificans
Beiner & Jokl - Contusion Injury and Myositis Ossificans (2002)
- Healing is a balance between muscle regeneration and scar/heterotopic bone formation
- Myositis ossificans is a major debilitating complication of contusion injury
- Reviews risk factors and prevention strategies including avoidance of re-injury and aggressive early mobilisation
Larruskain et al - Contusion Epidemiology in Elite Football (2018)
- Contusions are among the most common injuries in elite football
- Contusion incidence 4.82 times higher in male than female players (95% CI 2.30-10.08)
- Reflects greater contact exposure as the driver of contusion injury