Suprapatellar pain | Deep flexion aggravation | Eccentric loading | Older athlete demographic
- Tenderness at the superior pole of the patella (distal quadriceps insertion)
- Often affects slightly older athletes compared to jumper's knee
- Deep flexion places maximum tensile load on the quadriceps tendon
- Must rule out suprapatellar plica and bipartite patella
- Eccentric strengthening remains the cornerstone of treatment
- “Tenderness is at the suprapatellar insertion (superior pole).
- “Pain is reproduced by resisted extension from deep flexion.
- “Often associated with a 'gap' palpable in ruptures (sulcus sign).
- “Calcification is more common than in patellar tendon.
Overview and Epidemiology
Quadriceps tendinopathy is a degenerative condition of the suprapatellar insertion of the quadriceps tendon. It is less common than patellar tendinitis (jumper's knee), but it is a significant cause of anterior knee pain, particularly in older athletes and weightlifters.
Location is the diagnosis. The distinction from jumper's knee is purely anatomical. Quadriceps tendinopathy is at the superior pole of the patella and patellar tendinopathy at the inferior pole; do not confuse them.
Who. In some series it is roughly a tenth as frequent as patellar tendinitis, and it affects a typically older cohort, over 35-40 years, where patellar tendinitis affects those under 30. Men are affected more often than women, and it is seen in volleyball, basketball and weightlifting (deep squats).
The "jumper's knee" spectrum moves proximal with age. Young and adolescent: tibial tubercle (Osgood-Schlatter). Young adults: patellar tendon (inferior pole). Older adults: quadriceps tendon (superior pole).
Pathophysiology and Mechanisms
The tendon. The quadriceps tendon inserts into the base of the patella at its superior pole, and it is trilaminar. Rectus femoris forms the superficial layer, the conjoined vastus lateralis and vastus medialis the middle layer, and vastus intermedius the deep layer. The layering matters at surgery: debridement requires splitting the tendon, and understanding the layers is crucial for partial-thickness tears.
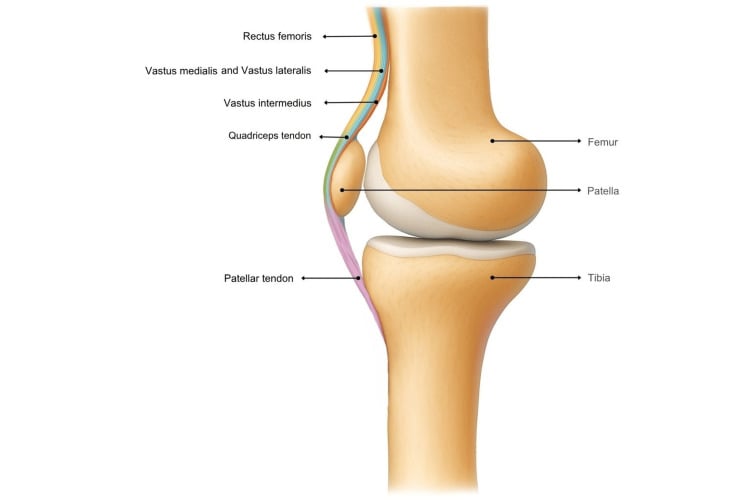
The watershed. The zone 1-2 cm proximal to the superior pole is hypovascular, and this "watershed" is the area most prone to degeneration and rupture.
The lesion. The histology is identical to patellar tendinopathy: angiofibroblastic tendinosis. Microtears form when repetitive eccentric loading outpaces repair, and a traction enthesophyte at the superior pole is common.
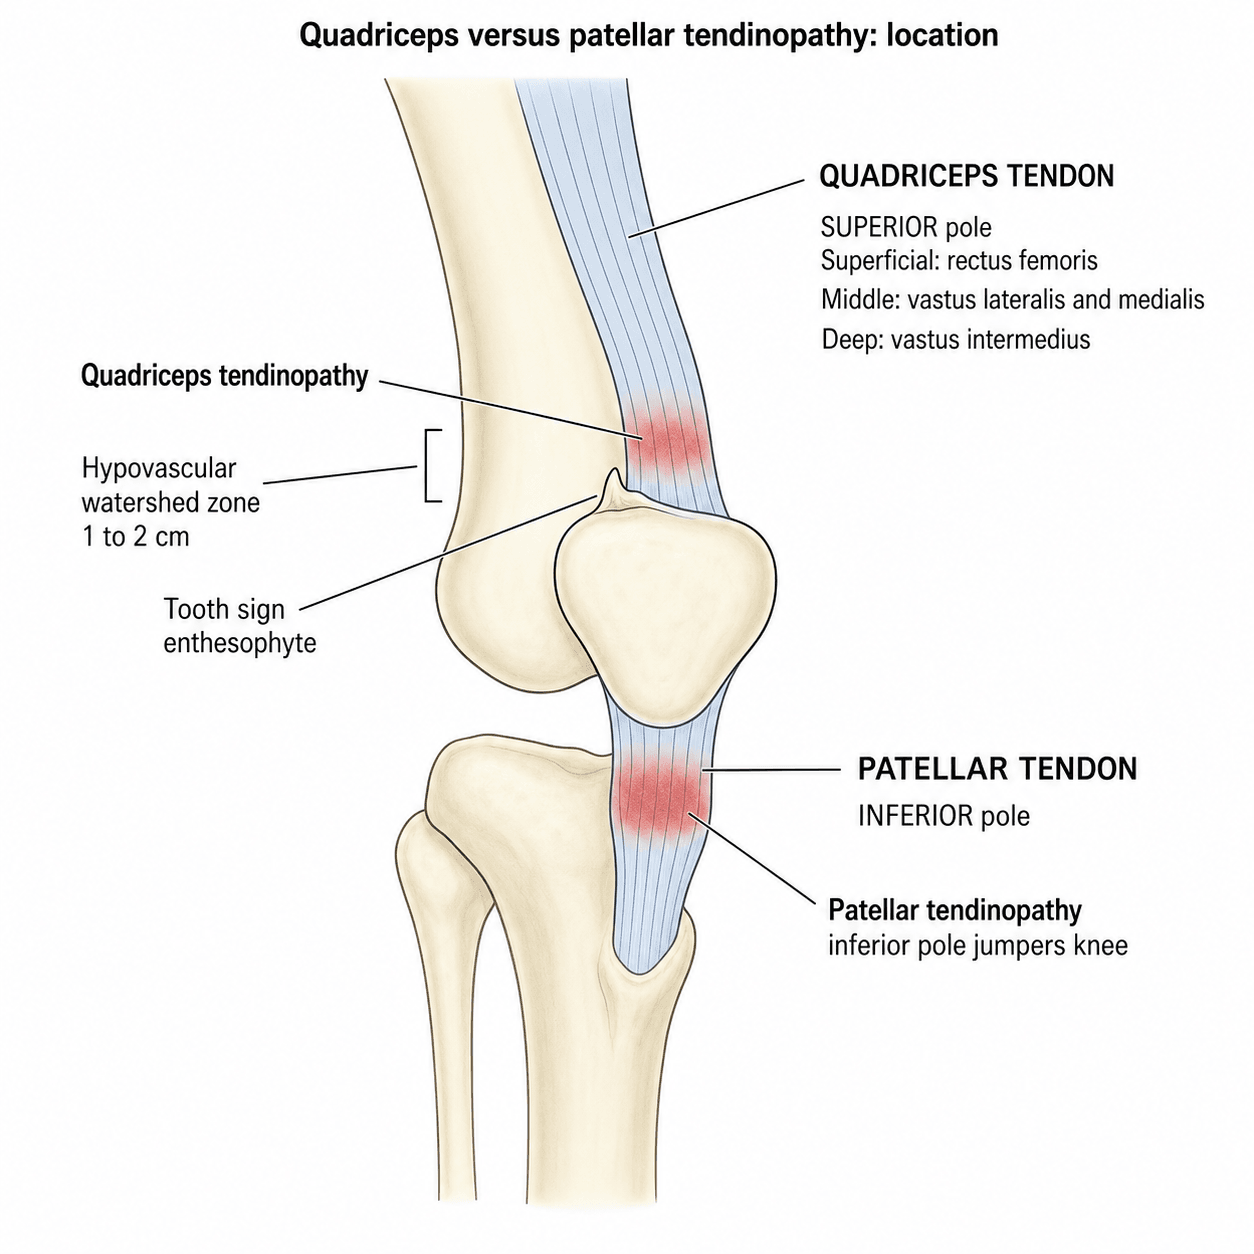
Why deep flexion hurts. The quadriceps tendon is under maximal tension in deep flexion. Deep flexion past 90° also compresses the tendon's deep fibres against the femur and trochlea, so insertional quadriceps tendinopathy is partly a compressive problem, which challenges the older purely tensile-overload model. Pain is often worse at the bottom of a squat, whereas patellar tendinopathy pain is often worse during the descent and deceleration.
Calcification. Calcification is more common in the quadriceps tendon than in the patellar tendon. Calcific tendinitis is a distinct entity, with a self-limiting resorptive cycle and often responsive to barbotage or shockwave, and it should not be lumped with degenerative tendinosis.
Classification Systems
Blazina's staging was originally described for jumper's knee and is applied, in modified form, to the quadriceps tendon. It is simple and clinically relevant.
- Symptoms
- Pain only after activity
- Function
- No functional impairment
- Treatment
- Ice, NSAIDs, eccentric rehab
- Symptoms
- Pain during and after activity
- Function
- Can still compete/perform
- Treatment
- Activity mod + intense rehab
- Symptoms
- Pain during and after
- Function
- Unable to compete at level
- Treatment
- Prolonged rest, consider surgery
- Symptoms
- Complete tendon rupture
- Function
- Loss of extension
- Treatment
- Surgical repair
Blazina aids in decision making. Stage 1/2 is rehab. Stage 3 warrants imaging and discussion of intervention.
Clinical Presentation and Assessment
History. Suprapatellar pain, pain with deep knee flexion such as squatting past 90 degrees, and "start-up" pain, stiffness after sitting. Ask about jumping or heavy lifting.
Examination. Localise the tenderness to the superior pole, load the tendon, and confirm the extensor mechanism is intact.
- Finding
- Tenderness at superior pole of patella
- Significance
- Confirm anatomic location
- Finding
- Pain, especially from deep flexion
- Significance
- Loads quad tendon maximally
- Finding
- Palpable sulcus suprapatellar
- Significance
- Signs of rupture
- Finding
- Lag / Inability
- Significance
- Complete rupture mechanism failure
- Finding
- Medial snapping / tenderness
- Significance
- Differential diagnosis
The extensor mechanism. Always confirm its integrity, because a painful tendon can also be a partially ruptured one. Any extensor lag on active straight leg raise is a red flag.
Systemic disease. Bilateral quadriceps tendon rupture is a classic association with systemic disease and with fluoroquinolone or steroid use, so always ask about the medical history.
REALRupture Risk Factors - REAL-MD
Hook:REAL-MDs check for systemic causes
If a patient presents with bilateral symptoms, particularly if acute-on-chronic pain, screen for systemic risk factors (Renal, Diabetes, Gout).
Differential diagnosis. Suprapatellar plica and bipartite patella must be ruled out.
- Location
- Superior pole insertion
- Aggravating Factor
- Deep squat / deceleration
- Management
- Eccentric rehab
- Location
- Medial suprapatellar
- Aggravating Factor
- Plausible snap/click
- Management
- Injection / resection
- Location
- Superolateral pole
- Aggravating Factor
- Direct trauma / overuse
- Management
- Rest / excision
- Location
- Suprapatellar gap
- Aggravating Factor
- Unable to extend knee
- Management
- Surgical repair
- Location
- Anterior to patella
- Aggravating Factor
- Kneeling / direct pressure
- Management
- Aspiration / protection
Investigations
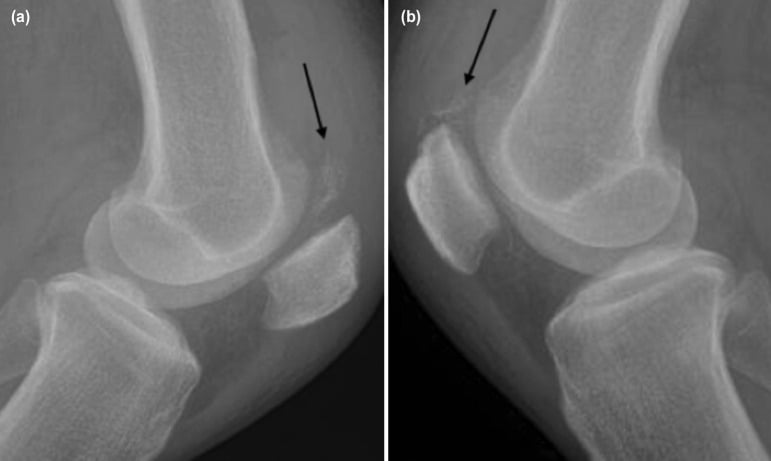
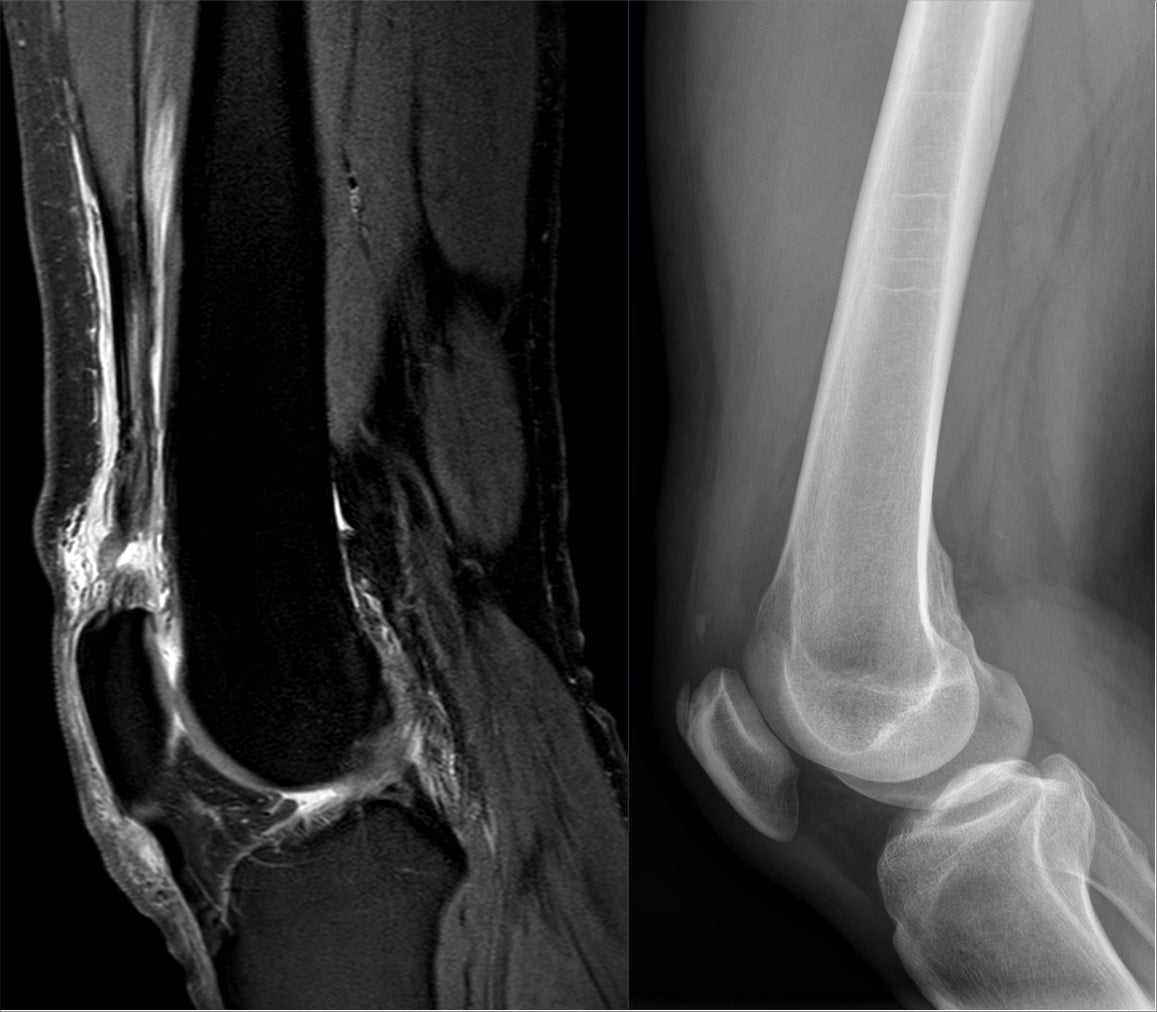
Radiographs. AP, lateral and skyline views. They show calcification and spurs, but the soft tissue is invisible:
- Tooth sign - a traction spur (enthesophyte) at the superior patellar pole
- Calcification - loose bodies or intratendinous calcification (calcific tendinitis)
- Patellar height - alta or baja
- Bipartite patella - usually superolateral (Saupe type III)
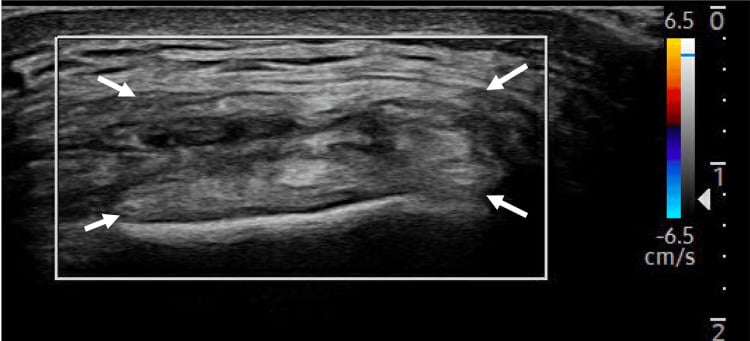
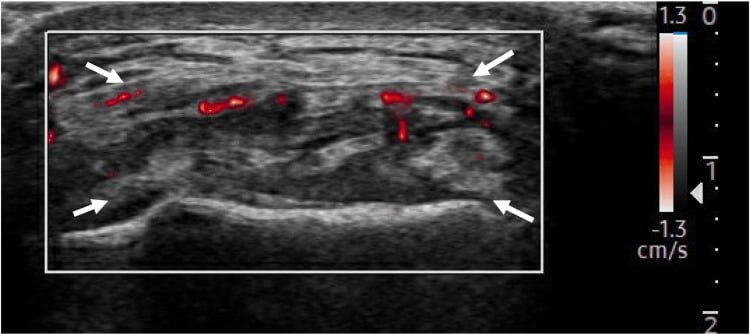
Ultrasound. Excellent for tendon architecture, showing thickening, hypoechogenicity and loss of the fibrillar pattern, and highly sensitive for calcium deposits. It is dynamic, so it can assess impairment through flexion and extension, and it is cheap and good for guiding injection. It is operator dependent.
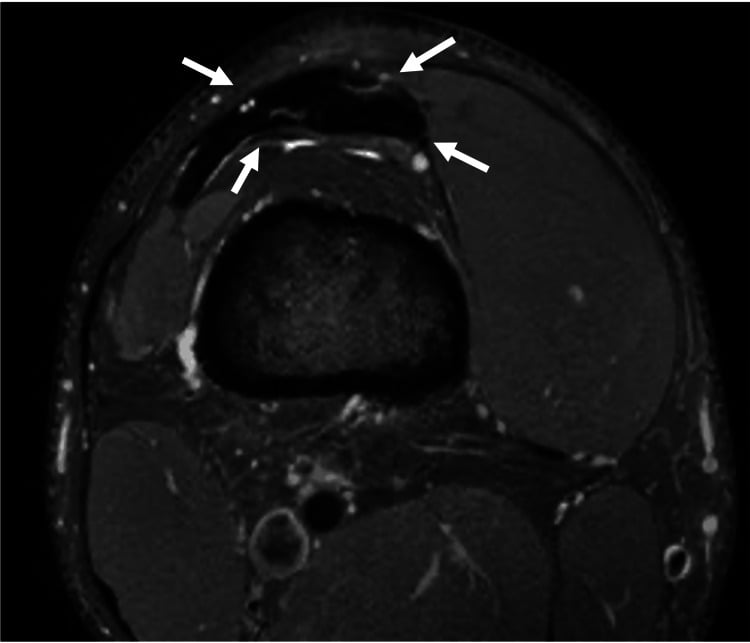
MRI. The gold standard for quantifying degeneration and ruling out intra-articular pathology. Tendinosis appears as T2/STIR hyperintensity in the distal quadriceps tendon and a partial tear as fluid signal interrupting the fibres; the scan also shows internal derangement and oedema. Its drawbacks are cost and a static study.
Management
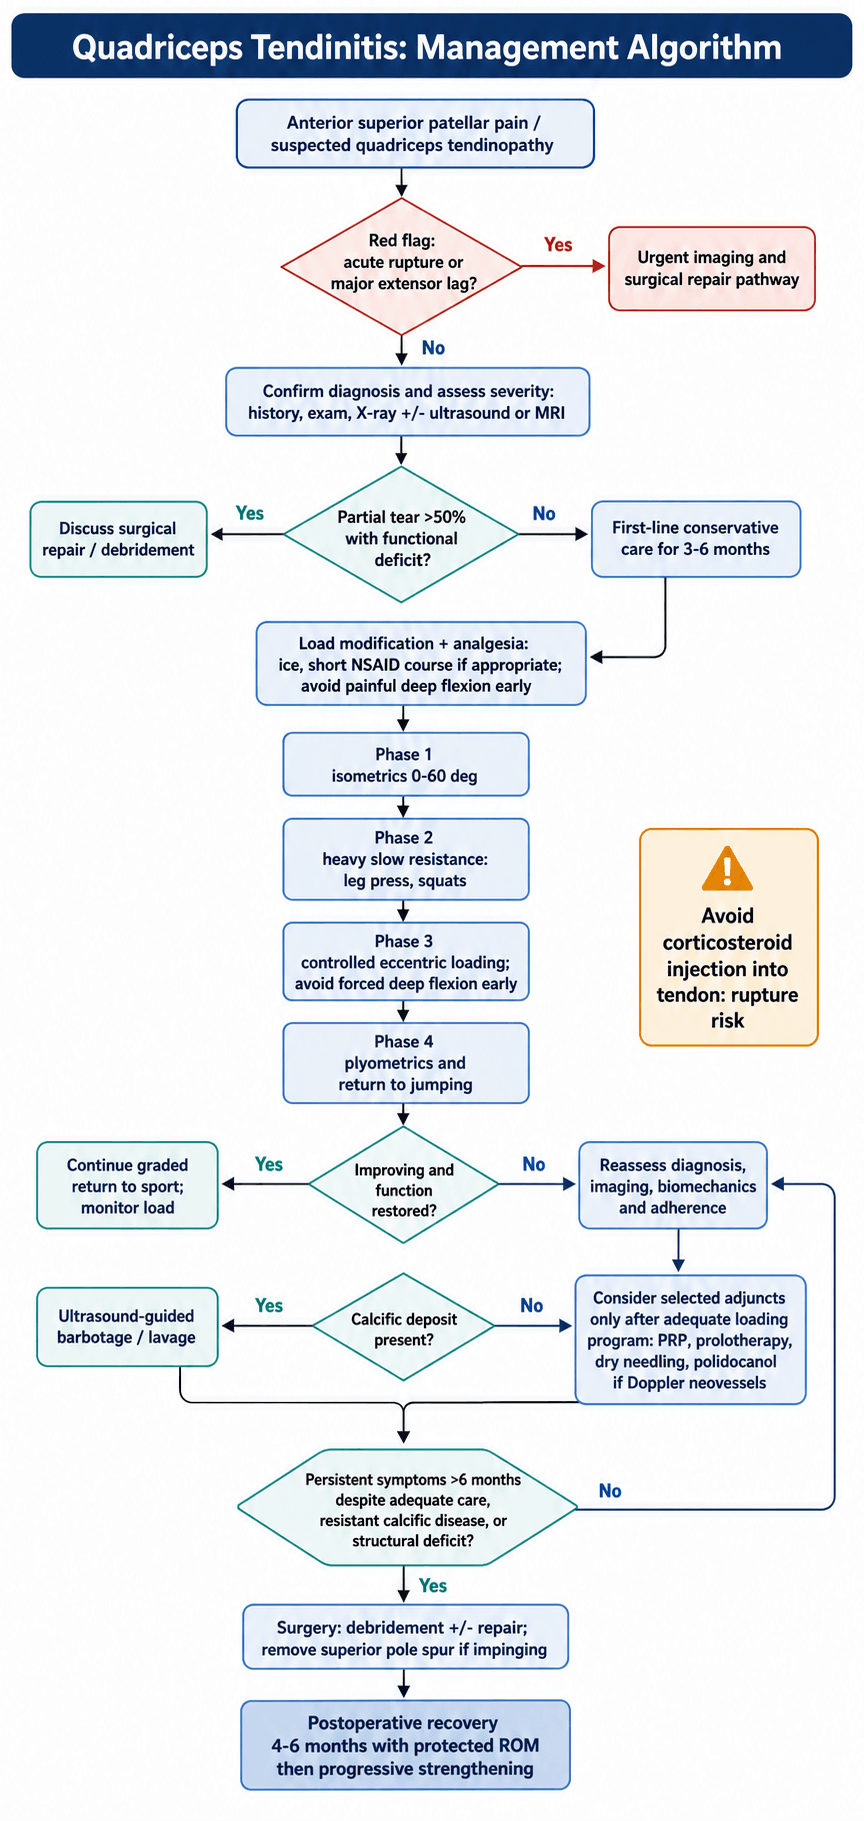
Management mirrors patellar tendinopathy but focuses on control of deep flexion. Standard therapy lasts 3-6 months, in four phases:
- Analgesia - isometric holds (e.g. wall sit at 60°), ice, NSAIDs
- Isotonic - heavy slow resistance (HSR): leg press, squats
- Eccentric, for tendon remodelling - controlled eccentric lowering, e.g. single-leg press lowering
- Plyometric - return to jumping, restoring functional energy storage
Because deep flexion compresses the tendon, early rehab should often limit flexion to 0-60 degrees to avoid compressive load, progressing to deep flexion late.
Surgical Technique
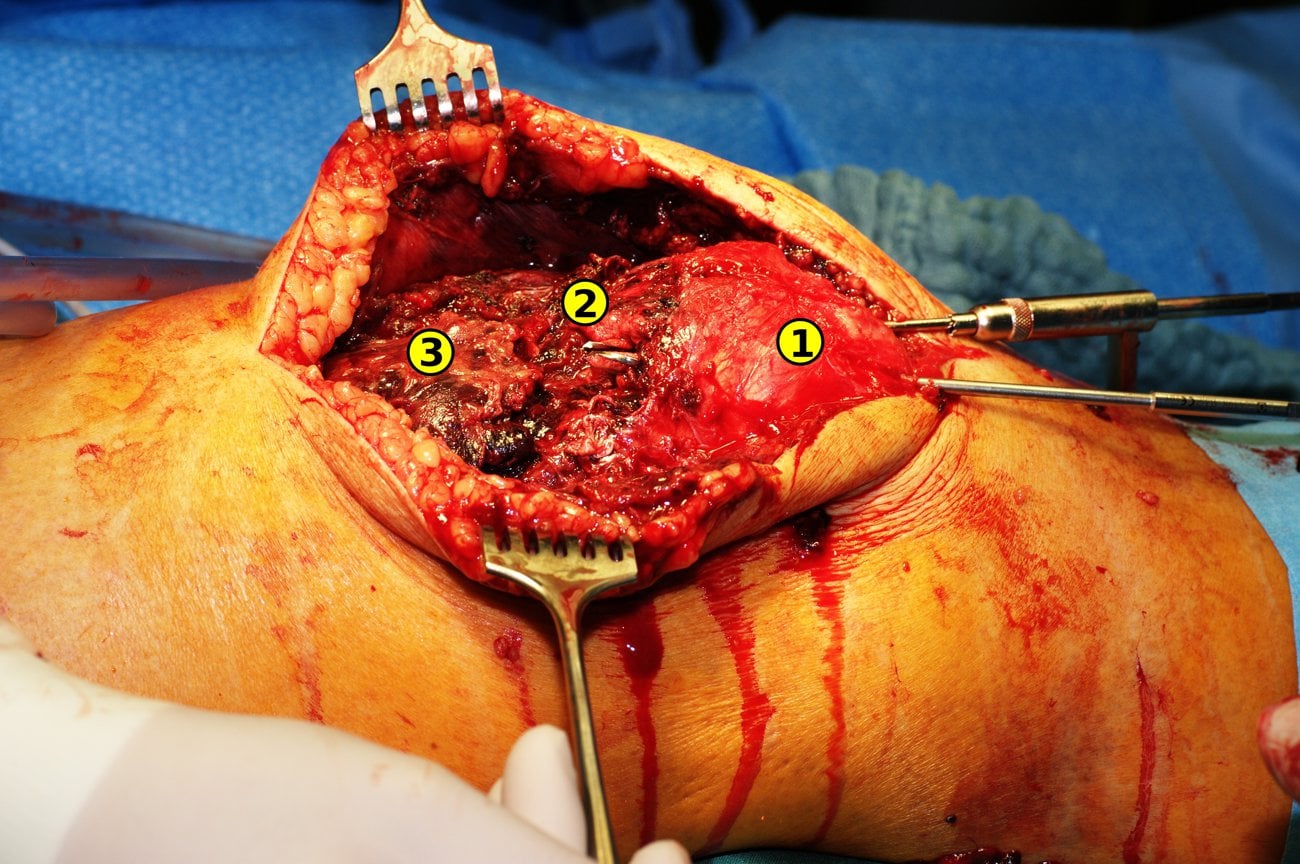
Approach. A midline longitudinal incision extending proximal to the patella exposes the paratenon. The pre-operative MRI guides where to look, and the lesion is often deep and central. Open debridement provides the most reliable access to the multi-layered pathology.
Technique. Incise the paratenon and inspect the tendon, then:
- Tenotomy - a longitudinal split in the tendon gives access to the deep layers
- Debride grey, friable, mucinoid tissue, and scrape the superior pole if cystic change is present
- Remove a traction spur ("tooth") with a rongeur or burr to prevent impingement
- Excise any calcific deposit, white and chalky material
- Close - carefully repair the longitudinal split (Vicryl/PDS), close any defect left by debridement side to side, and close the paratenon to prevent adhesions
After surgery. Protected weight bearing in a brace locked in extension for 2 weeks, then a gradual increase in range of motion.
Complications
- Risk Factors
- Steroid use, aggressive early load
- Management
- Surgical Repair
- Risk Factors
- Incomplete resection, wrong diagnosis
- Management
- Re-imaging / Revision
- Risk Factors
- Prolonged immobilization
- Management
- MUA / Lysis of adhesions
- Risk Factors
- Open surgery
- Management
- Antibiotics +/- Washout
Rupture. Quadriceps rupture is the ultimate failure of tendinosis. It requires urgent repair with suture anchors or transosseous tunnels, and repair delayed beyond 3 weeks has a significantly worse prognosis because of retraction.
Localising an Extensor-Mechanism Rupture: Patella Baja vs Alta
When the extensor mechanism fails, the resting position of the patella on the lateral radiograph localises the level, a classic exam discriminator.
- Typical age
- Usually over 40 years
- Patella position
- Patella BAJA (low-riding) - the unopposed patellar tendon pulls it down
- Active extension
- Lost / extensor lag, suprapatellar gap
- Typical age
- Any age, direct or indirect
- Patella position
- Variable; fragments separate
- Active extension
- Lost if displaced
- Typical age
- Usually under 40 years
- Patella position
- Patella ALTA (high-riding) - the unopposed quadriceps pulls it up
- Active extension
- Lost / extensor lag, infrapatellar gap
Measuring it. The Insall-Salvati ratio is patellar-tendon length divided by patella length, normally about 0.8 to 1.2. A high ratio is alta (patellar-tendon rupture) and a low ratio is baja (quadriceps rupture).
Whatever the level, the message is the same: a palpable gap with loss of active extension, or an extensor lag, is an extensor-mechanism rupture needing prompt repair, not a "strain".
Postoperative Care and Rehabilitation
- Goal: protect the repair and let the wound heal
- Brace in extension
- WBAT in extension
- Isometric quads
- Goal: regain range of motion
- Unlock brace 0-30, then 0-60, then 0-90
- Active flexion, passive extension
- Avoid active extension against resistance
- Goal: strength
- Wean brace
- Start concentric strengthening
- Progress to eccentric loading
- Goal: power and sport
- Plyometrics
- Return to sport criteria (limb symmetry index greater than 90%)
Post-op rehab for quadriceps tendon debridement is typically slower than (arthroscopic) patellar tendon debridement because the muscle belly itself is often more affected by the surgical approach (muscle violation) and inhibition.
Outcomes and Prognosis
Conservative treatment has a high success rate, 70-90%, with compliance to activity modification and rehabilitation. Surgery gives good results, 80-90% satisfaction, in appropriately selected patients.
Recurrence can occur if the biomechanics (training errors, flexibility) are not addressed. Calcific tendinitis has an excellent prognosis with lavage or excision.
Guidelines, Registries & Global Practice
Global epidemiology:
- Quadriceps tendinopathy is substantially less common than patellar tendinopathy ("jumper's knee"), affecting an older cohort (typically over 35-40 years), with male predominance and a strong association with jumping/weightlifting sports.
- Complete quadriceps tendon rupture has an estimated incidence of roughly 1 per 100,000 per year, peaks in men over 40, and is over-represented in patients with chronic kidney disease, diabetes, hyperparathyroidism, gout and systemic inflammatory disease.
- There is no implant or arthroplasty registry that tracks tendinopathy; epidemiology is drawn from cohort series rather than national registries.
Side-by-side society positions (loading-led, injection-cautious):
- Loading
- Progressive resistance (HSR / eccentric) first-line
- Injections
- PRP optional in recalcitrant cases; steroid discouraged
- Surgery
- Reserved for failed prolonged rehab
- Loading
- Structured physiotherapy and load management first-line
- Injections
- Limited routine injection role; avoid intratendinous steroid
- Surgery
- Specialist referral after failed conservative care
- Loading
- Exercise therapy cornerstone; ESWT as adjunct
- Injections
- PRP considered; heterogeneous evidence acknowledged
- Surgery
- Debridement for chronic recalcitrant tendinosis
- Loading
- Graded loading and relative rest; manage training load
- Injections
- Caution with injectables in-season; no steroid
- Surgery
- Last resort; protect return-to-sport timeline
Registry & high- vs limited-resource practice:
- High-resource settings: ready access to ultrasound and MRI allows confident differentiation of tendinosis from partial/complete tear; ultrasound-guided barbotage and shockwave are widely available; supervised graded loading programmes are standard.
- Limited-resource settings: diagnosis is clinical and radiographic (the "tooth sign" enthesophyte and the palpable suprapatellar gap of rupture become critical); home-based isometric and heavy-slow-resistance programmes are emphasised because they need minimal equipment; acute rupture repair is prioritised over advanced adjuncts.
- Across all settings the consensus is identical on two points: progressive mechanical loading is the cornerstone, and intratendinous corticosteroid is contraindicated because of rupture risk.
Controversies and Areas of Uncertainty
Extrapolated evidence. Almost every high-quality loading and injection trial studied the patellar tendon, not the quadriceps tendon. The shared eccentric-loading biology makes extrapolation reasonable, but it should be acknowledged honestly in a viva rather than quoting "Level I evidence for quadriceps tendinopathy".
Decline squats or heavy slow resistance. Classic eccentric decline-squat protocols can provoke compressive, insertional pain at the superior pole in quadriceps disease, and they may impinge it if deep flexion is forced too early. Heavy slow resistance and isometric-led progression are increasingly preferred, especially early.
Surgery for tendinosis. The evidence for debridement is largely low-level case series. Selection (failed prolonged rehabilitation, a structural partial tear, a symptomatic enthesophyte) matters more than the specific technique.
MCQ Practice Points
Q: Which layer of the quadriceps tendon is deepest? A: Vastus Intermedius. (Superficial: RF, Middle: VL/VM, Deep: VI).
Q: Which antibiotic class is associated with tendon rupture? A: Fluoroquinolones (e.g., Ciprofloxacin).
Q: Where is the 'watershed' zone of hypovascularity in the quad tendon? A: 1-2 cm proximal to the superior pole of the patella.
Q: A patient on dialysis with knee pain likely has pathology in which tendon? A: Quadriceps tendon (strongly associated with renal failure/secondary hyperparathyroidism).
Q: What is the 'Tooth Sign' on lateral knee X-ray? A: A traction enthesophyte (spur) at the superior pole of the patella, indicative of chronic quadriceps tendinopathy.
Q: Where is a bipartite patella typically located? A: Superolateral pole (Saupe Type III).
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“A 45-year-old weightlifter presents with chronic pain just above the patella. It hurts deep in the squat. X-rays show a small spur at the superior pole. How do you manage him?”
“A 55-year-old diabetic male presents with bilateral suprapatellar pain and difficulty climbing stairs. He has a history of renal disease. What is your concern?”
“Ultrasound reports a 1cm calcific deposit in the quadriceps tendon of a 35-year-old female. She has failed physiotherapy. Options?”
Key Facts
- Insertion: Superior pole of patella
- Age group: Older (over 40) than Jumper's Knee
- Deep flexion (greater than 90°) aggravates pain
- Systemic link: Renal, Diabetes, Steroids
Imaging
- X-ray: Tooth sign (spur) at superior pole
- US/MRI: Hypoechoic/High signal in critical zone
- Hypovascular zone: 1-2cm proximal to insertion
- Always rule out partial tear
Management
- Isometrics to HSR to Eccentrics
- Limit deep flexion in early phase
- Barbotage for calcific deposits
- Surgery for failed conservative / rupture
Red Flags
- Bilateral symptoms (Systemic cause)
- Extensor lag (Rupture)
- Inability to SLR (Rupture)
- Fluoroquinolone use
Evidence Base
Several landmark trials are drawn from the patellar tendon (jumper's knee) literature because high-quality, tendon-specific quadriceps trials are scarce; the loading biology is shared, but the limitation should be stated explicitly in a viva.
Khan et al. - Histopathology of Common Tendinopathies
- Review of symptomatic Achilles, patellar, ECRB and rotator cuff tendons.
- Symptomatic tendons show disorganised collagen, increased mucoid ground substance and fibroblastic/myofibroblastic proliferation with neovascularisation.
- The most significant feature is the ABSENCE of inflammatory cells - this is tendinosis, not tendinitis.
Kongsgaard et al. - Corticosteroid vs Eccentric vs Heavy Slow Resistance
- RCT of 39 men with patellar tendinopathy: corticosteroid injection (CORT) vs eccentric decline squats (ECC) vs heavy slow resistance (HSR), 12 weeks.
- All three improved VISA-P and pain at 12 weeks, but CORT deteriorated by 6-month follow-up while ECC and HSR were maintained.
- HSR produced the highest treatment satisfaction and increased collagen turnover.
Rio et al. - Isometric Exercise Induces Analgesia
- Single-blind randomised cross-over in SIX volleyball players with patellar tendinopathy - the effect size is large but the sample is very small.
- A single bout of isometric contractions reduced single-leg decline squat pain from 7.0 to 0.17 out of 10, against 6.33 to 3.75 for isotonic (p less than 0.001), with the 45-minute effect also measured.
- Isometrics released cortical inhibition (27.5 to 55.0 per cent) and increased maximal voluntary isometric contraction by 18.7 per cent; isotonic contractions did not alter inhibition.
Rio et al. - Isometric vs Isotonic In-Season RCT
- In-season RCT of 20 jumping athletes: isometric leg-extension holds vs isotonic leg extension over 4 weeks.
- Both reduced pain, but isometric contractions produced significantly greater immediate analgesia throughout the trial.
- Week-one analgesic response correlated with VISA-P improvement at 4 weeks.
Filardo et al. - PRP in Tendon Disorders
- Systematic review (Level I-IV) of PRP across Achilles, patellar, lateral elbow and rotator cuff tendons.
- Patellar tendon appeared to benefit from PRP, whereas Achilles did not; rotator cuff surgical augmentation showed no benefit.
- Overall evidence remains heterogeneous with variable PRP preparations.
Boublik et al. - Quadriceps Tendon Tears in NFL Players
- Case series of 14 distal quadriceps tendon tears in NFL players (1994-2004).
- Eccentric contraction was the commonest mechanism; prodromal symptoms and predisposing factors were usually absent.
- Despite timely surgical repair only 50% returned to regular-season play - a guarded prognosis even in elite athletes.
Elattar et al. - Management of Chronic Quadriceps Tendon Rupture
- Critical analysis review of chronic quadriceps tendon rupture.
- Delayed diagnosis leads to poorer results regardless of treatment - timely diagnosis and repair of acute injury are imperative.
- Chronic cases require V-Y lengthening, vastus advancement or autograft/allograft augmentation owing to retraction and patellar migration.