Congenital vs Acquired Instability
- Radiocapitellar Line: A line drawn through the centre of the radial neck must bisect the capitellum in ALL views.
- Monteggia Lesion: Any ulnar fracture must have a reduced radial head. If not, it's a Monteggia.
- Nursemaid's Elbow: Subluxation of the annular ligament, not a true dislocation. Reduction is clinical (Hyperpronation).
- Congenital Signs: Bilateral, Dome shaped radial head (convex), Hypoplastic capitellum.
- “Always x-ray the Elbow in any forearm fracture.
- “Check the PIN (Finger extension) - commonly injured in anterior dislocations.
- “In children, plastic deformation of the ulna can cause radial head dislocation (Bado Type I equivalent).
Overview and Epidemiology
Terms. A dislocation is complete loss of articular contact; a subluxation is partial loss, the nursemaid's elbow being the familiar example. A congenital dislocation is a developmental anomaly present at birth, and a traumatic one is acquired, usually through high energy.
Who. In children the injury is common, peaking at 4-10 years for the Monteggia lesion and 1-4 years for the nursemaid's elbow. In adults an isolated dislocation is rare: the head usually leaves the joint as part of a complex fracture-dislocation, a terrible triad or a Monteggia.
Mechanism. The nursemaid's elbow is axial traction on a pronated forearm. The Monteggia lesion follows a fall on the outstretched hand, with pronation producing Type I and flexion Type II.
Anatomy
The articulation. The radial head is concave and articulates with the convex capitellum, the centre of rotation of the radiocapitellar joint; the head is not perfectly circular but more oval. It sits in the radial notch, an indentation on the proximal ulna, and together they form the proximal radioulnar joint (PRUJ), a trochoid or pivot joint. The radius moves with the ulna in flexion and extension, and rotates around it in pronation and supination.
The safe zone. Hardware on the head belongs in the 90° arc that does not articulate with the ulna, the non-articular surface, which corresponds to the tripod position laterally. The head's extra-osseous supply comes from the radial recurrent artery entering the neck and its intra-osseous supply is poor, leaving a watershed area in the lateral portion of the head, the same safe zone.
Stabilisers. The primary stabilisers:
- Ulnohumeral joint - the coronoid is the primary stabiliser against posterior subluxation
- MCL, anterior bundle - the primary stabiliser against valgus
- LCL (LUCL) - the primary stabiliser against varus and posterolateral rotatory instability (PLRI)
Of the secondary stabilisers, the radial head is an important one against valgus if the MCL is cut, and the anterior capsule resists extension.
The annular ligament is the primary stabiliser of the PRUJ. It arises from the anterior and posterior margins of the sigmoid notch and is tighter around the neck than around the head, a funnel shape that prevents distal migration and is the anatomy behind the nursemaid's elbow.
Load and length. The radial head transmits 60% of the axial load at the elbow and, with the interosseous membrane, prevents proximal migration of the radius. Excise it and the radius migrates proximally, ulnar variance becomes positive, and the result is DRUJ pain.
The posterior interosseous nerve. The PIN winds around the radial neck within supinator, which makes it highly susceptible to injury in anterior (Type I) or lateral (Type III) dislocations; an anterior dislocation often causes a PIN neurapraxia. During lateral dissection the nerve is safe if the forearm is pronated, and supination brings it closer to the surgical field in the Kaplan approach.
Other nerves and vessels. The median nerve can be entrapped in the joint in rare medial dislocations, and the ulnar nerve is at risk in the Type IV Monteggia or during a medial approach to the coronoid. The recurrent radial artery, the leash of Henry, must be ligated to mobilise supinator. The radial artery lies anterior to the bicipital tuberosity.
Classification Systems
Bado. The Monteggia lesion is classified by the direction in which the radial head dislocates, and the apex of the ulnar angulation points the same way.
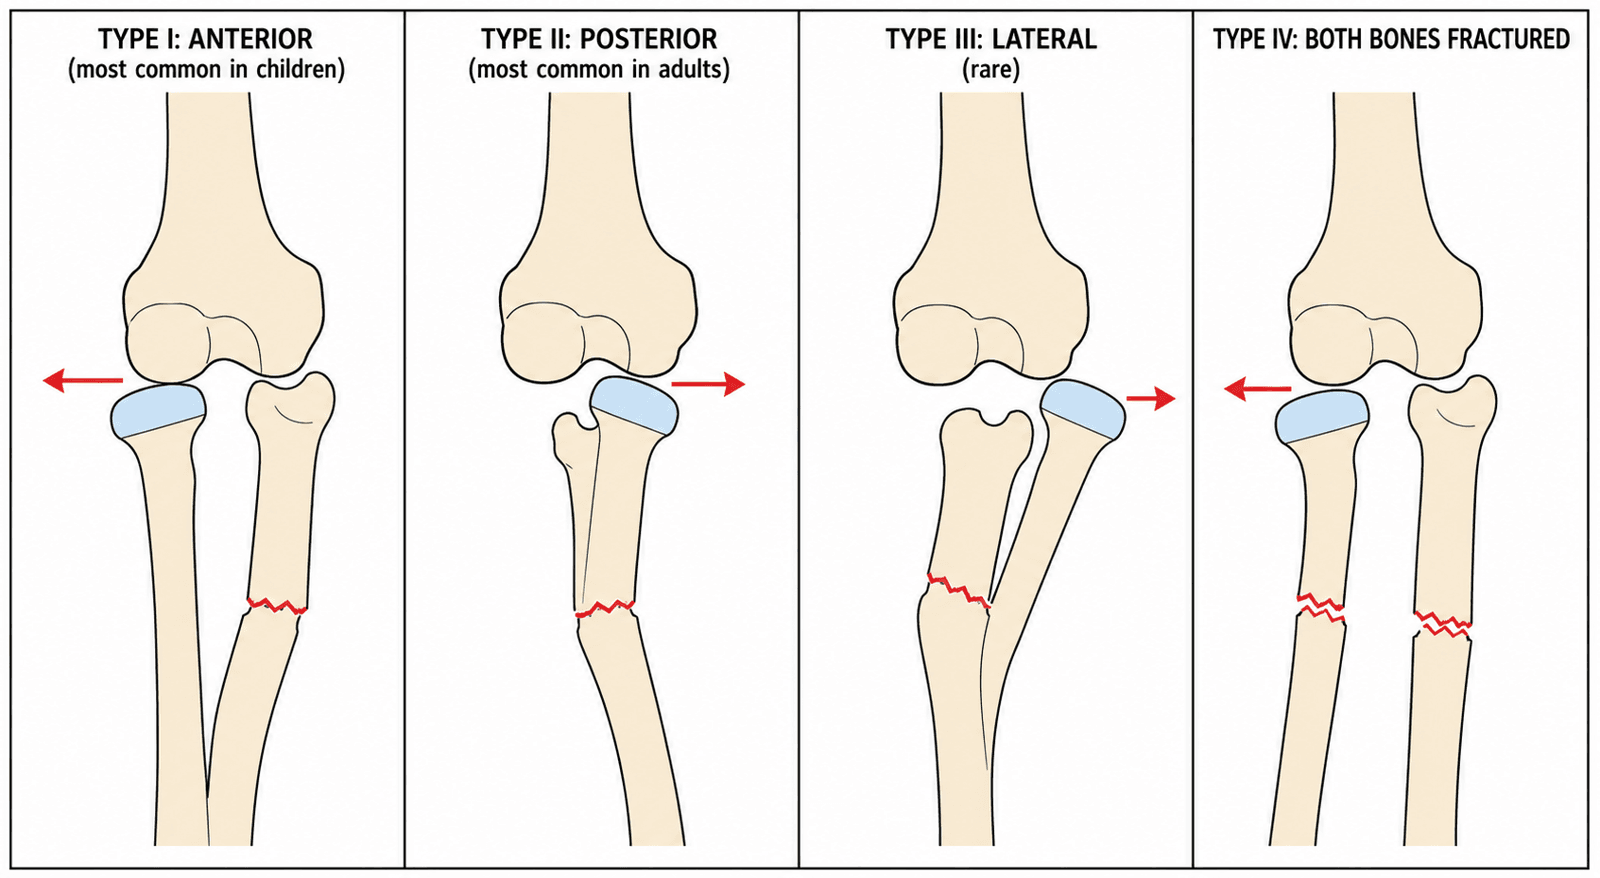
- Type I, anterior - anterior head, anterior ulnar apex; most common in children (70%)
- Type II, posterior - posterior head, posterior ulnar apex; most common in adults (80%) and associated with radial head fractures
- Type III, lateral - lateral head, lateral ulnar apex; rare, and associated with PIN palsy
- Type IV - fracture of both radius and ulna with dislocation
Hotchkiss. Radial head fractures, often associated with the dislocation, are graded by Hotchkiss:
- Type I - non-displaced (less than 2mm): stiff but stable, treated non-operatively
- Type II - displaced (greater than 2mm) but reconstructible: ORIF with a lag screw or plate
- Type III - comminuted and not reconstructible: excision if the MCL is intact, replacement if it is torn
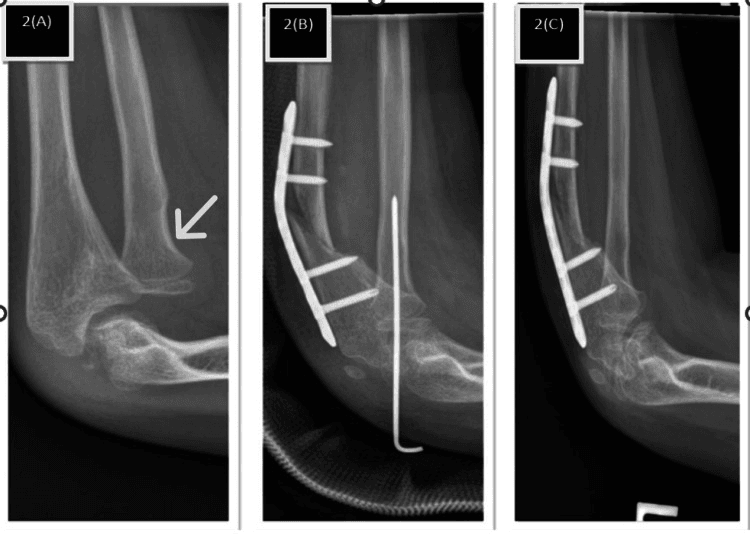
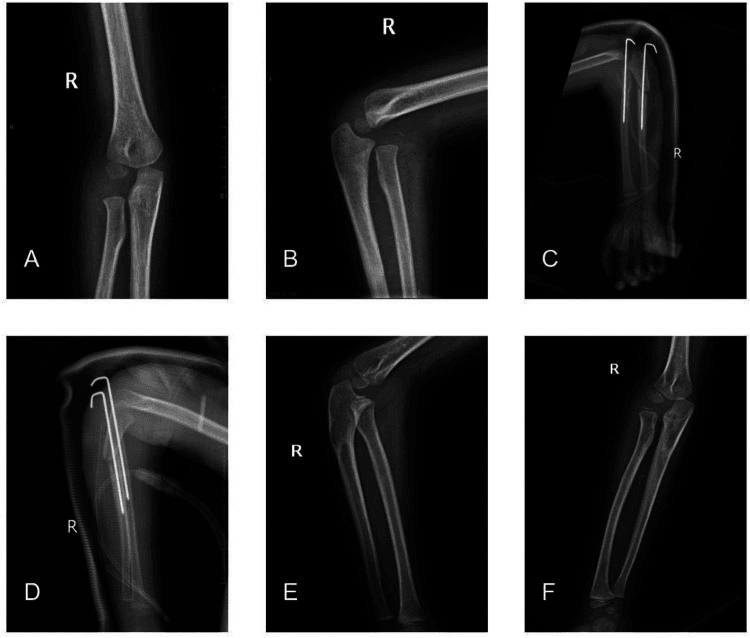
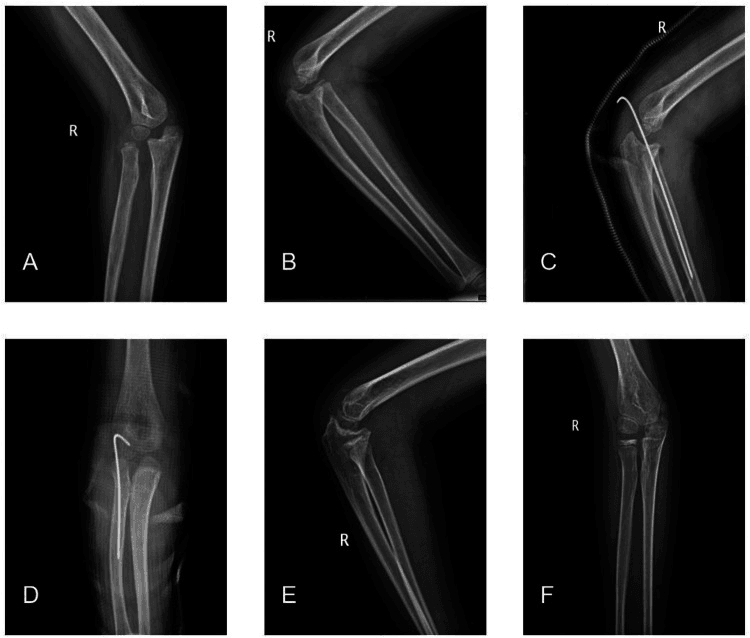
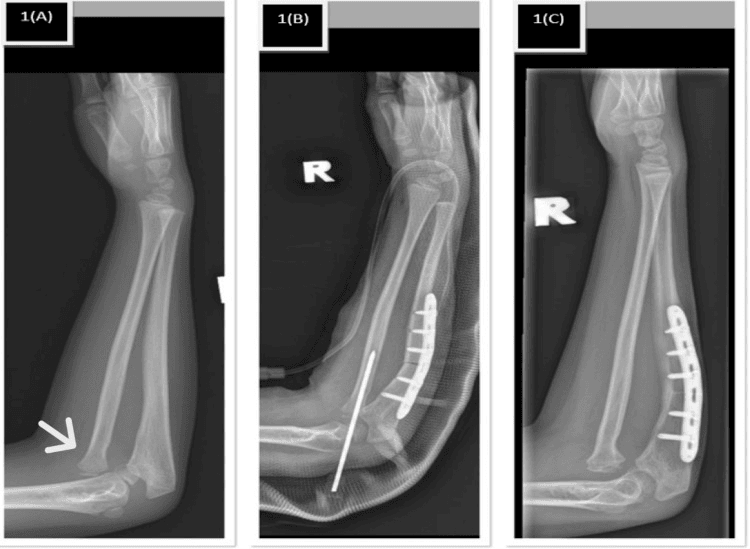
The bowed ulna. In a child the head may be out because the ulna is bowed by plastic deformation, and a bowed ulna in a child is a fracture. When the ulna is bowed and the head is out, the head must be reduced, and the ulna straightened, often by osteoclasis, to allow it to reduce.
Congenital Radial Head Dislocation: Why You Leave It Alone
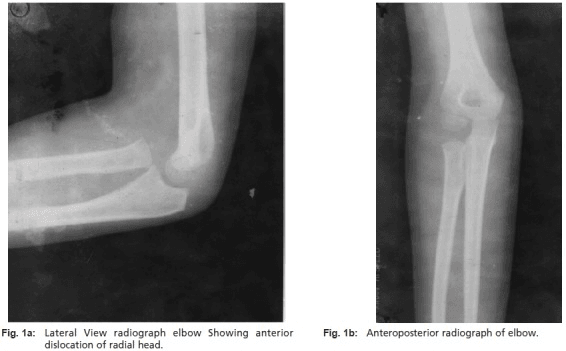
A lesion from birth. Congenital dislocation is rare, a primary developmental anomaly present at birth. The radiocapitellar joint never formed normally, and the radiographic signature that results is what separates it from an acquired dislocation:
- Congenital
- Frequently bilateral (60%)
- Traumatic (acquired)
- Unilateral
- Congenital
- Dome-shaped, convex
- Traumatic (acquired)
- Concave (normal)
- Congenital
- Hypoplastic
- Traumatic (acquired)
- Normal
- Congenital
- Short (negative ulnar variance)
- Traumatic (acquired)
- May be bowed by plastic deformation in a child
- Congenital
- Usually anterior
- Traumatic (acquired)
- Congenital
- Often syndromic
- Traumatic (acquired)
- Trauma, or missed trauma
Associated syndromes.
- Nail-patella syndrome - hypoplastic nails, absent patellae, radial head dislocations
- Klippel-Feil syndrome - cervical fusion, low hairline, radial head involvement
- Cornelia de Lange syndrome - multiple anomalies
- Ehlers-Danlos syndrome - ligamentous laxity leading to habitual dislocation
Usually functional and painless. Most children adapt well, with a near-normal, painless range of movement into early adulthood. The dislocation is frequently an incidental finding, or noticed only as a lateral prominence or a modest loss of rotation.
Why reduction fails. The joint surfaces have remodelled to incongruent shapes, a convex head against a deficient capitellum, so an attempted reduction cannot restore a congruent joint. It produces pain and stiffness, and the head re-dislocates. Do not reduce; observe.
When to operate. Surgery is reserved for the symptomatic adult, in whom radial head excision can relieve pain, accepting some loss of strength and unpredictable results. Reduction or reconstruction is not indicated for the established congenital head.
Clinical Assessment
History. In a child aged 1-4 the story is of being pulled up by the arm, then crying, with the arm held by the side. Acute trauma is a fall on the outstretched hand. The chronic presentation is loss of movement and a prominence on the lateral elbow, which is the radial head.
Examination. The nursemaid's elbow is held in extension and pronation, the child resists supination, and if it is acute there is no swelling. A fracture brings swelling, bruising and deformity of the ulna. Palpate the radial head: is it in the joint, and does it rotate?
The PIN. Check thumb extension. A PIN palsy loses thumb extension (EPL) and finger extension (EDC), but wrist extension through ECRL is preserved, in radial deviation.
- Discriminating Feature
- Age 1-4, axial pull, arm pronated and refused use, no swelling
- Imaging Clue
- Radiographs normal (often not needed)
- Key Action
- Closed reduction (hyperpronation)
- Discriminating Feature
- Trauma, ulnar tenderness, head out on imaging
- Imaging Clue
- Disrupted radiocapitellar line + ulnar fracture or bow sign
- Key Action
- Restore the ulna (reduce/ORIF or osteoclasis)
- Discriminating Feature
- Lateral prominence, lost rotation, weeks-months after injury
- Imaging Clue
- Ulnar malunion, convex remodelled head, dome capitellum
- Key Action
- Ulnar osteotomy + open reduction
- Discriminating Feature
- Painless, often bilateral, frequently syndromic
- Imaging Clue
- Dome/convex head, hypoplastic capitellum, short ulna
- Key Action
- Do NOT reduce; observe (excision in adulthood if painful)
- Discriminating Feature
- Localised tenderness, painful rotation, effusion
- Imaging Clue
- Fracture line, fat pad sign, head congruent
- Key Action
- Treat fracture (non-op / ORIF / replacement)
- Discriminating Feature
- Wrist (DRUJ) pain with elbow injury, axial load mechanism
- Imaging Clue
- Positive ulnar variance, proximal radial migration
- Key Action
- Preserve/replace radial head; never excise alone
Investigations
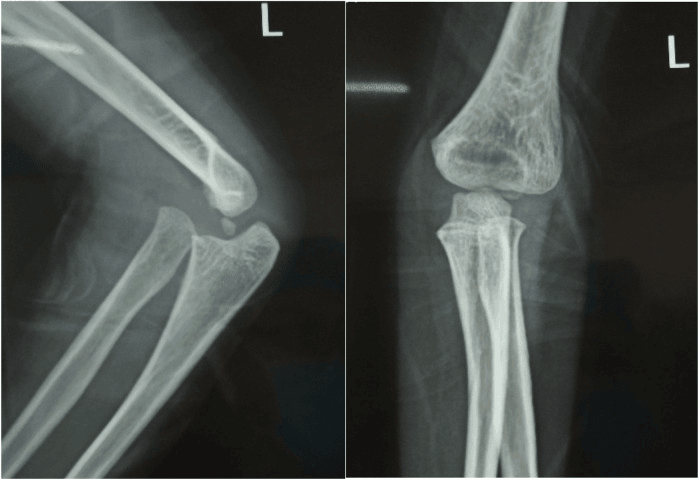
Radiographs. AP and lateral films of the elbow are mandatory, and on them you check the radiocapitellar line, the ulna for bowing from plastic deformation, and the shape of the capitellum, round or flat. Forearm films exclude shaft fractures, and wrist films exclude a Galeazzi injury, a radius fracture with DRUJ dislocation.
- Normal Value
- Intersects Capitellum
- Pathology
- Dislocation
- Technique
- Draw line through centre of radial neck. Must hit capitellum in ALL views.
- Normal Value
- Straight posterior border
- Pathology
- Plastic Deformation
- Technique
- Draw line along posterior border of proximal ulna. Max deviation greater than 1mm suggests deformation.
- Normal Value
- Concave
- Pathology
- Congenital
- Technique
- Convex or dome-shaped head indicates congenital dislocation.
- Normal Value
- Neutral
- Pathology
- Longitudinal Instability
- Technique
- Positive variance (=Proximal migration of radius) suggests Essex-Lopresti lesion.
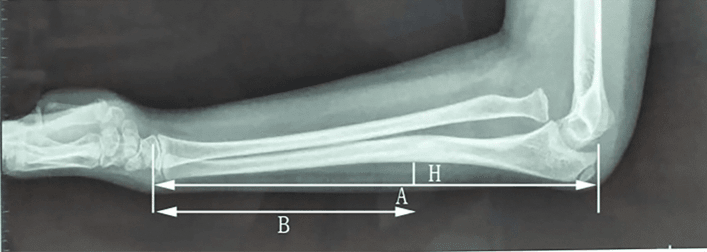
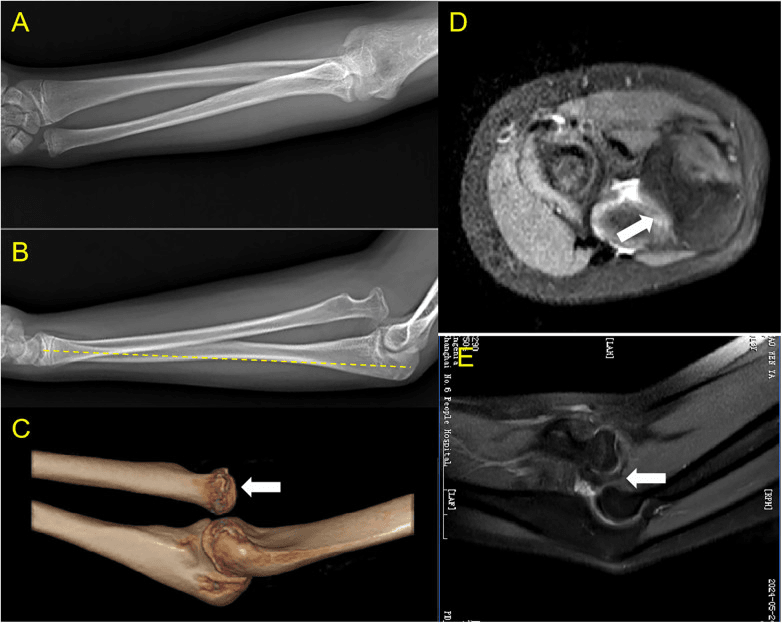
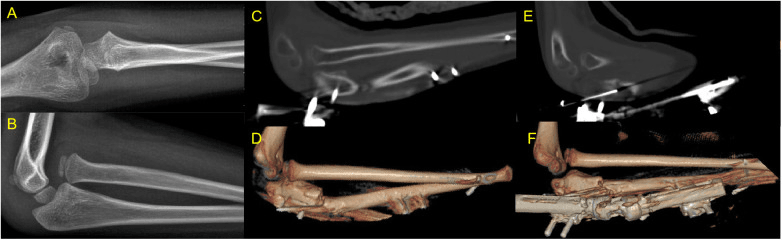
CT is indicated in chronic cases, to assess articular congruity and to plan correction of the ulnar deformity, and in the adult Type II Monteggia, to look for a coronoid fracture. 3D reconstruction is essential for understanding the "shotgun" deformity of the proximal ulna in comminuted Monteggia fractures.
MRI is rarely indicated in the acute setting. It is useful in chronic "painful clicking", to look for loose bodies or plica, and it can assess the integrity of the PIN when the nerve is not recovering.
Associated injuries. Work through them as a checklist:
- Coronoid fracture - in 10-15% of radial head dislocations; pathognomonic for the terrible triad
- LCL rupture - always present in dislocation, usually avulsed from the lateral epicondyle
- MCL rupture - with valgus instability or high-energy trauma
- DRUJ injury - in the Type IV Monteggia or Essex-Lopresti longitudinal instability, so always examine the wrist
- Capitellar shear fracture - the radial head can shear off the capitellum or trochlea as it dislocates
Applying the Radiocapitellar Line Correctly (and Its Pitfalls)
The missed Monteggia is the most common cause of litigation in paediatric orthopaedics, and the radiocapitellar line, the single most important sign in this topic, is how it is caught. It only works if it is drawn and read correctly.
Draw it through the neck, not the shaft. Take the line along the long axis of the radial neck and proximal radius. The radial head sits slightly anterior to the shaft axis, so a line taken off the shaft can falsely seem to miss, or hit, the capitellum. Drawn through the neck, it should pass through the capitellum in every view and every degree of forearm rotation.
It needs a true lateral. A malrotated or oblique film can make a normal line look displaced or hide a real dislocation. Confirm on a true AP and lateral, adding an oblique if in doubt; the line holding on one view does not exclude a dislocation on another.
The very young elbow is a trap. The capitellum does not ossify until about 1 year of age, so before then there is no bony capitellum to aim at; judge the cartilaginous position with ultrasound or against the contralateral elbow. Mild normal variability also exists, and a line that just clips the capitellar edge with a straight ulna is usually normal.
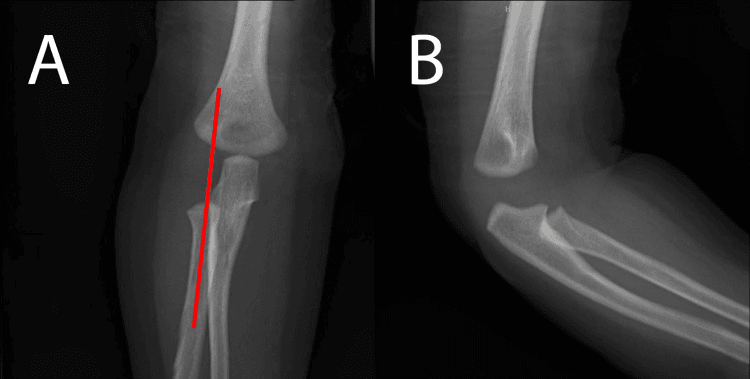
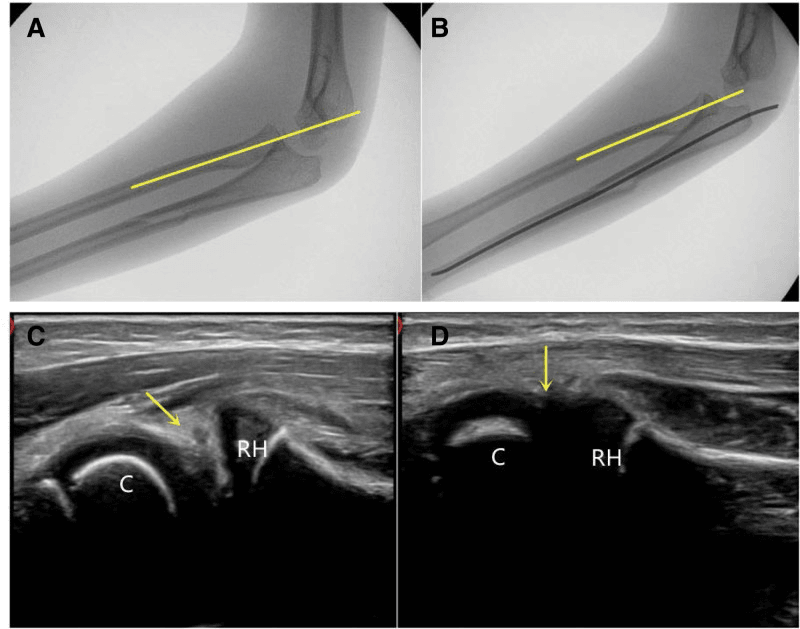
Pair it with the ulna. A disrupted radiocapitellar line should send you straight to the ulna, looking for a fracture or the plastic ulnar bow sign of a Monteggia lesion, rather than accepting an "isolated" dislocation.
Management Algorithm
The pulled elbow is a subluxation, reduced closed. Hyperpronation is the first-line manoeuvre and is more effective than supination-flexion:
- Hyperpronation - hold the elbow at 90° and firmly pronate the wrist. It usually clicks, with a high success rate
- Supination-flexion - supinate the wrist, then flex the elbow
Afterwards. The child should use the arm within 10-15 minutes, and no cast is needed.
Surgical Techniques
Indications. An irreducible acute dislocation, or chronic reconstruction.
Approach. Kocher, through the interval between anconeus (radial nerve) and ECU (PIN), or Kaplan, between EDC and ECRB. The internervous plane is safe distally, but the PIN is at risk proximally if the dissection extends too far anteriorly.
- Interval
- Anconeus / ECU
- Pros
- Safer for PIN (if not extended too far)
- Cons/Risks
- Less anterior exposure. Hard to see coronoid.
- Interval
- EDC / ECRB
- Pros
- Excellent anterior exposure (Coronoid access)
- Cons/Risks
- High risk of PIN injury (Nerve crosses field).
Technique.
- Position supine, the arm over the chest or on a hand table, with a high arm tourniquet
- Make a lateral incision over the radial head, extending distally towards the ulna
- Develop the Kocher interval, elevate anconeus posteriorly and incise the capsule anterior to the LUCL
- Identify the radiocapitellar joint and remove interposed soft tissue; the annular ligament may be folded in
- Reduce the head: flexion and pronation usually reduce it
- Annular ligament repair is difficult. If the head is stable leave it; if unstable, reconstruct it (Bell-Tawse, using a triceps strip)
- Close the interval (anconeus fascia) securely
Planning. Template the radial head size from the normal side if bilateral films are available. In a chronic case measure the ulnar length discrepancy, because the ulna may need lengthening by 1-2cm. Have a small-fragment set (3.5mm), a mini-fragment set (2.0/2.4mm, for head and coronoid) and radial head replacement options (Simplex or modular) available.
The comminuted "shotgun" ulna. Extend the incision distally and expose the shaft. Reduce the shaft first to restore length; the proximal fragments often "explode" outwards.
The coronoid. After fixing the ulna, check the coronoid. If it is fractured it must be fixed, with a suture lasso or screws, as it prevents posterior instability.
Head height. If replacing the head, do not overstuff the joint: the prosthetic head should be level with the coronoid tip, and overstuffing causes stiffness and capitellar wear.
The LCL. Reattach it with suture anchors to the isometric point on the lateral epicondyle, the centre of curvature of the capitellum.
Arthroscopy. If the reduction is in doubt, an arthroscope, where available, shows the radiocapitellar joint from inside.
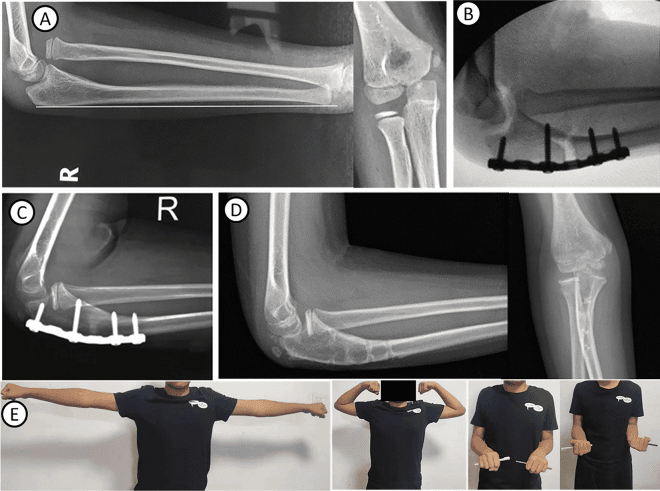
Complications
PIN palsy. Common in Type I and III lesions, and usually resolves after reduction. It is also an iatrogenic risk of the Kaplan approach.
Recurrent dislocation. The result of failing to reduce the ulna anatomically, or failing to recognise plastic deformation.
Stiffness. The most common complication, and common after open reduction. A loss of 10-15° of extension is common and functional, but lost flexion is poorly tolerated; lost pronation and supination is common if the interosseous membrane was injured.
Heterotopic ossification. Common in adults with a head injury or prolonged intubation. Indomethacin prophylaxis is indicated for the high-risk patient.
Radioulnar synostosis. Cross-union between radius and ulna. The risk factors are a single incision for both bones or extensive dissection, delayed fixation, and head injury. It is excised once the bone scan is "cold", at 12-18 months.
Implant removal. Plates on the proximal ulna are prominent and often need removal, with a 40% removal rate.
Postoperative Care
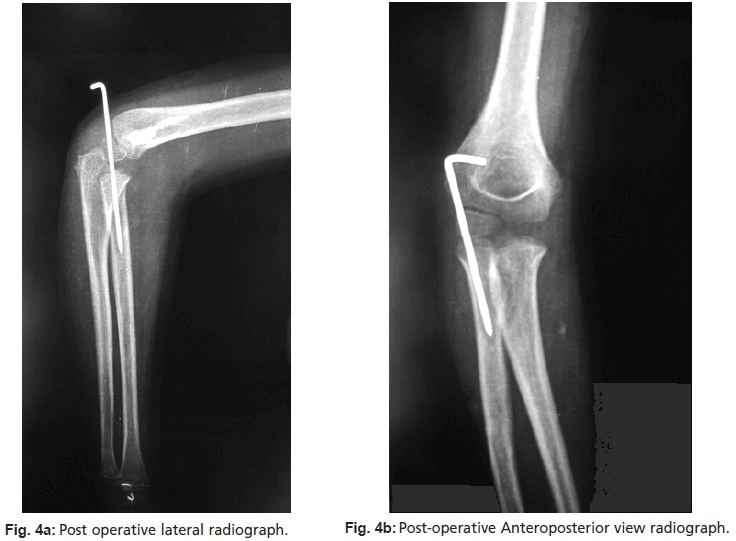
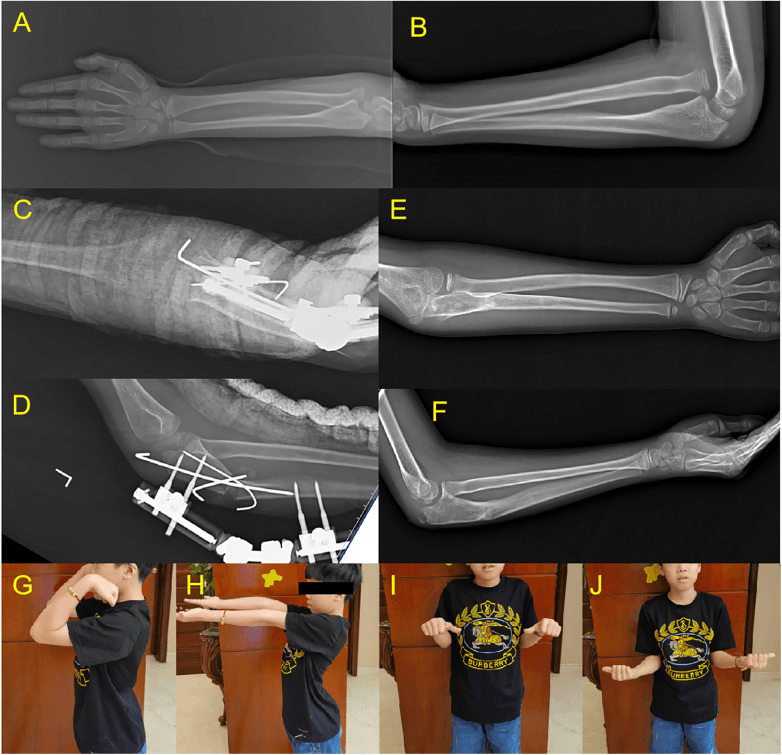
After surgery. Splint for 2 weeks, then protected motion in a hinged brace, and avoid heavy lifting for 3 months.
Rehabilitation after adult Monteggia fixation runs in phases:
- Phase 1 (weeks 0-2) - long arm splint, elevation for oedema, finger and shoulder movement
- Phase 2 (weeks 2-6) - splint and sutures removed; hinged elbow brace (0-100°); active assisted flexion and extension; forearm rotation with the elbow at 90°, which protects the LCL; avoid varus stress (shoulder abduction)
- Phase 3 (weeks 6-12) - wean the brace; static progressive (turnbuckle) splinting if stiff; begin strengthening (Theraband)
- Phase 4 (month 3 onwards) - work hardening; return to sport, waiting for solid union at 4-6 months if the sport is a contact one
Outcomes/Prognosis
Nursemaid's elbow. Excellent, with 100% recovery, but recurrence is high until age 5.
Acute Monteggia. A Type I in a child does excellently if reduced, with 90% good or excellent outcomes. A Type II in an adult is variable, with a high risk of stiffness and heterotopic ossification, and the Mayo Elbow Performance Score (MEPS) averages 85.
Chronic missed Monteggia. Without surgery the prognosis is poor, with progressive valgus and PIN palsy. Osteotomy has a 70% success rate but a high complication rate, from stiffness and nerve injury.
Scoring the MEPS.
- Pain (45 points) - none 45, moderate 30, severe 0
- Motion (20 points) - an arc greater than 100° 20, 50-100° 15, less than 50° 5
- Stability (10 points) - stable 10, unstable 0
- Function (25 points) - combing hair, feeding and similar tasks
A score greater than 90 is excellent, and 75-89 is good.
Guidelines, Registries & Global Practice
Global epidemiology:
- Pulled elbow (nursemaid's) is among the most common upper-limb presentations in children under 5 worldwide, peaking at 1-4 years with a female and left-arm predominance; recurrence is frequent until ligamentous maturity around age 5.
- Monteggia lesions are uncommon (about 1-2% of forearm fractures); Bado type I predominates in children and type II in adults.
- Missed/chronic Monteggia is a recognised global source of avoidable disability and medicolegal claims, driven by failure to apply the radiocapitellar line on every paediatric elbow/forearm film.
Side-by-side guidance (where emphasis differs):
- Key Position
- Anatomic restoration of ulnar length and alignment is the primary determinant of radial head reduction in Monteggia.
- Practical Point
- Fix the ulna first; reassess radiocapitellar congruity intra-operatively.
- Key Position
- Every forearm/elbow injury in a child must have the radiocapitellar line checked to avoid the missed Monteggia.
- Practical Point
- Document the line on AP and lateral views.
- Key Position
- Proximal ulnar fixation must reproduce the dorsal angulation/bow; long plates and length restoration are stressed.
- Practical Point
- Beware the 'shotgun' comminuted proximal ulna — restore length via the shaft first.
- Key Position
- Low threshold to image the contralateral elbow and to differentiate congenital from traumatic dislocation.
- Practical Point
- Bilateral, dome-shaped head = congenital; do not reduce.
There is no dedicated radial head dislocation registry; radial head arthroplasty data are captured indirectly within elbow arthroplasty and implant series rather than national joint registries (NJR, AOANJRR, AJRR), which focus on hip/knee/shoulder. Most evidence is therefore Level IV case series.
- Well-resourced: CT/3D planning for comminuted proximal ulna, modular radial head implants, hinged external fixators, and intra-operative imaging are routinely available.
- Limited-resource: Reliance on plain radiographs and the radiocapitellar line, plate or even K-wire/ex-fix ulnar fixation, and biological annular reconstruction (triceps/forearm fascia) rather than implants. Early recognition of the plastic Monteggia is the single highest-yield, low-cost intervention.
Related pages: Monteggia Fractures and Paediatric Monteggia Fractures are what most of these dislocations actually are - the ulnar injury is the lesion and the radial head is the sign, which is the single most important idea on this page; Nursemaid's Elbow for the subluxation that is not a dislocation at all and is reduced in clinic by hyperpronation, and which must never be confused with the traumatic dislocation that needs a radiograph; Radial Head Fractures and Radial Head Arthroplasty for the adult injury at the same joint and the implant decisions behind the overstuffing discussion above; Terrible Triad of the Elbow for the dislocation that takes the coronoid and the radial head with it; and Essex-Lopresti Injuries for the longitudinal instability to exclude before the radial head is ever excised.
Controversies & Areas of Uncertainty
- Is truly isolated radial head dislocation real? Lincoln and Mubarak found a definable ulnar injury in every "isolated" case, yet rare genuinely isolated traumatic dislocations are reported. Practically, treat every paediatric "isolated" dislocation as a plastic Monteggia and scrutinise the ulna.
- Acute vs delayed osteotomy in missed Monteggia: No consensus on the upper time limit for attempting reduction. Many achieve good results up to 1-3 years from injury, challenging older teaching that reconstruction beyond a few months is futile. Outcome depends more on chronicity and ulnar remodelling than a fixed cut-off age.
- Annular ligament reconstruction — necessary or not? Some series (e.g. single-incision techniques) report stable reductions from ulnar osteotomy alone without formal annular reconstruction, questioning routine Bell-Tawse-type reconstruction and its stiffness/synostosis risk.
- Imaging before reduction of pulled elbow: Routine radiographs are not required in a classic presentation; films are reserved for atypical history or failed reduction, where occult fracture prevalence remains low.
- Stable Monteggia radial head — fix, replace or leave: In adult Bado II with comminuted radial head, the threshold for replacement vs excision vs fixation after restoring ulnar length is debated; excision is avoided where longitudinal/DRUJ instability coexists.
- PIN palsy — when to explore: Most resolve with observation after reduction, but persistent palsy beyond 3 months with nerve entrapment in the radiocapitellar joint may warrant exploration; the exact timing for surgery is not standardised.
MCQ Practice Points
Q: Which X-ray sign is pathognomonic for congenital dislocation? A: Convex (Dome-shaped) Radial Head and Hypoplastic Capitellum.
Q: Which nerve is most at risk in a Type I Monteggia fracture? A: Posterior Interosseous Nerve (PIN).
Q: What is the most successful maneuver for reducing a pulled elbow? A: Hyperpronation.
Q: What structure prevents proximal migration of the radius? A: The Central Band of the Interosseous Membrane.
Q: A posterior dislocation of the radial head with a posterior angulated ulna fracture is which Bado type? A: Type II.
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“A 6-year-old child presents with a radial head dislocation. There is no obvious fracture on X-ray.”
“You see an adult with a chronic, asymptomatic radial head dislocation. They are worried about appearance.”
“You perform an open reduction of a radial head dislocation in a child using a Kocher approach. Post-operatively, the child cannot extend their thumb.”
Radiocapitellar Line
- Line through center of radial neck
- Must bisect capitellum in ALL views
- Check AP, lateral, and oblique views
- Disruption indicates dislocation
Bado Classification
- I: Anterior (Extension) - Most common in children
- II: Posterior (Flexion) - Most common in adults
- III: Lateral
- IV: Both bones (radius and ulna)
Paediatric vs Adult
- Paeds: Closed Reduction (Cast)
- Adult: ORIF (Plate)
- Paeds: Anterior (Type I) most common
- Adult: Posterior (Type II) most common
Red Flags
- Plastic Ulnar Bowing in children
- PIN Palsy (finger extension weakness)
- Bilateral = likely Congenital
- Dome-shaped radial head = Congenital
Nursemaid's Elbow
- Hyperpronation technique preferred
- Audible click = successful reduction
- Immediate use of arm post-reduction
- No imaging needed if classical presentation
Evidence
Hyperpronation vs Supination/Flexion (RCT)
- Prospective randomised trial, 90 children under 6 with nursemaid's elbow (84 analysed).
- First-attempt success 95% (39/41) with hyperpronation vs 77% (34/44) with supination/flexion.
- Hyperpronation required fewer attempts and often succeeded after supination had failed (5/6 cross-over successes).
- Overall reduction 97.5% hyperpronation vs 86% supination.
Chronic Monteggia: Open Reduction, Annular Reconstruction and Ulnar Osteotomy
- 15 children with chronic Monteggia lesions (mean age 8 years; chronicity 6 weeks to 2 years).
- Treated with open reduction, annular ligament reconstruction using forearm fascia, and ulnar osteotomy via a single incision.
- Functional result excellent in 11, good in 3, poor in 1; flexion arc improved in all (mean 27.7 degrees).
- Modest loss of pronation (mean 16 degrees in 6 cases).
The Ulnar Bow Sign — 'Isolated' Traumatic Radial Head Dislocation
- Retrospective review identified a definable ulnar injury in EVERY case of so-called isolated radial head dislocation.
- Described the 'ulnar bow sign': deviation of the posterior ulnar border from a straight line on a true lateral.
- Truly isolated radial head dislocation is essentially a myth — look for plastic deformation of the ulna.