AORI Classification | Constraint Selection | Bone Loss Management | Outcomes
- Aseptic loosening is the most common indication for revision TKA (50% of cases)
- AORI classification guides bone loss management: Type 1 (intact), Type 2 (damaged), Type 3 (deficient)
- Constraint progression: PS to CCK to hinged based on bone loss and soft tissue competence
- Infection must be ruled out in ALL cases before revision - aspirate, inflammatory markers, culture
- Two-stage revision is gold standard for chronic PJI with antibiotic spacer interval
- “AORI Type 3 requires structural support (metaphyseal sleeve, cone, or bulk allograft)
- “Constrained condylar knee (CCK) for MCL/LCL insufficiency but intact bone stock
- “Rotating hinge for massive bone loss or global instability
- “Modular stems for stability and load sharing, cemented distally in diaphysis
Overview and Epidemiology
Revision TKA is technically demanding, and compared with the primary operation it brings higher complication rates, longer operative times and inferior functional outcomes. National registries record over 100,000 primary TKAs annually in high-income settings, with far greater volumes worldwide, so the burden of revision surgery is substantial.
Who is revised. The mean age at revision is 65-70 years, younger than at primary TKA, and women outnumber men 2:1, the same ratio as for the primary. Revision comes a mean of 7-10 years after the index operation.
How it compares with a primary. Every measure is worse:
- Complication rate 20-30%, against 5-10% after a primary
- Operative time 2-3 hours, against 1-1.5 hours
- Functional scores 70-80% of those after primary TKA
- Survivorship 85-90% at 10 years, against 95% for a primary
- Re-revision risk 15-20% within 5 years
Indications for Revision TKA
Aseptic loosening is the most common indication, about half of all revisions, with instability and infection behind it. Technical error is a further reason to revise: malrotation, malalignment or a component size mismatch.
- Frequency
- 50%
- Key Features
- Radiolucent lines over 2mm, progressive, painful
- Treatment Approach
- Revise components, address bone loss, stems
- Frequency
- 20%
- Key Features
- MCL/LCL insufficiency, flexion-extension gap imbalance
- Treatment Approach
- Increase constraint (CCK or hinge), soft tissue reconstruction
- Frequency
- 15%
- Key Features
- Chronic pain, effusion, elevated inflammatory markers
- Treatment Approach
- Two-stage revision with antibiotic spacer
- Frequency
- 10%
- Key Features
- Focal osteolysis, thin poly, no gross loosening
- Treatment Approach
- Poly exchange, curettage and grafting of lesions
- Frequency
- 3-5%
- Key Features
- Less than 90° flexion, failed manipulation
- Treatment Approach
- Open arthrolysis, poly exchange, consider hinge
Every revision knee must have infection excluded before an aseptic revision goes ahead; the workup is set out under Investigations. Proceeding with aseptic revision in the setting of occult infection results in failure in over 90% of cases.
Anatomy and Biomechanics
Metaphysis and diaphysis. The metaphysis, the wide flared bone at the joint, gives the components their primary support, and it is the region that revision bone loss compromises; the AORI classification grades that damage. The diaphysis, the narrow shaft below, is where stems gain fixation.
The collateral ligaments. The MCL prevents valgus instability and the LCL prevents varus instability, so their integrity determines how much constraint the revision needs. Intraoperative stress testing settles it: one deficient collateral means a CCK, both mean a hinge.
The popliteal artery runs posterior to the knee joint, approximately 1cm from the posterior capsule, and it is at greater risk in revision than in primary TKA.
- The posterior capsule is attenuated by prior surgery, wear and loosening
- Anatomical planes are lost, so neurovascular structures are difficult to identify
- Posterior releases for stiff knees bring instruments close to the artery
Stay subperiosteal, use retractors carefully, avoid blind posterior releases and handle the tissues gently.
Classification Systems
The Anderson Orthopaedic Research Institute (AORI) classification is the gold standard for grading bone loss in revision TKA, and it guides the choice of augments, stems and structural grafts. Each grade maps to a reconstruction. Type 1 defects can be managed with standard components, Type 2 needs augmentation, and Type 3 demands structural support from a metaphyseal sleeve, cone or bulk allograft.
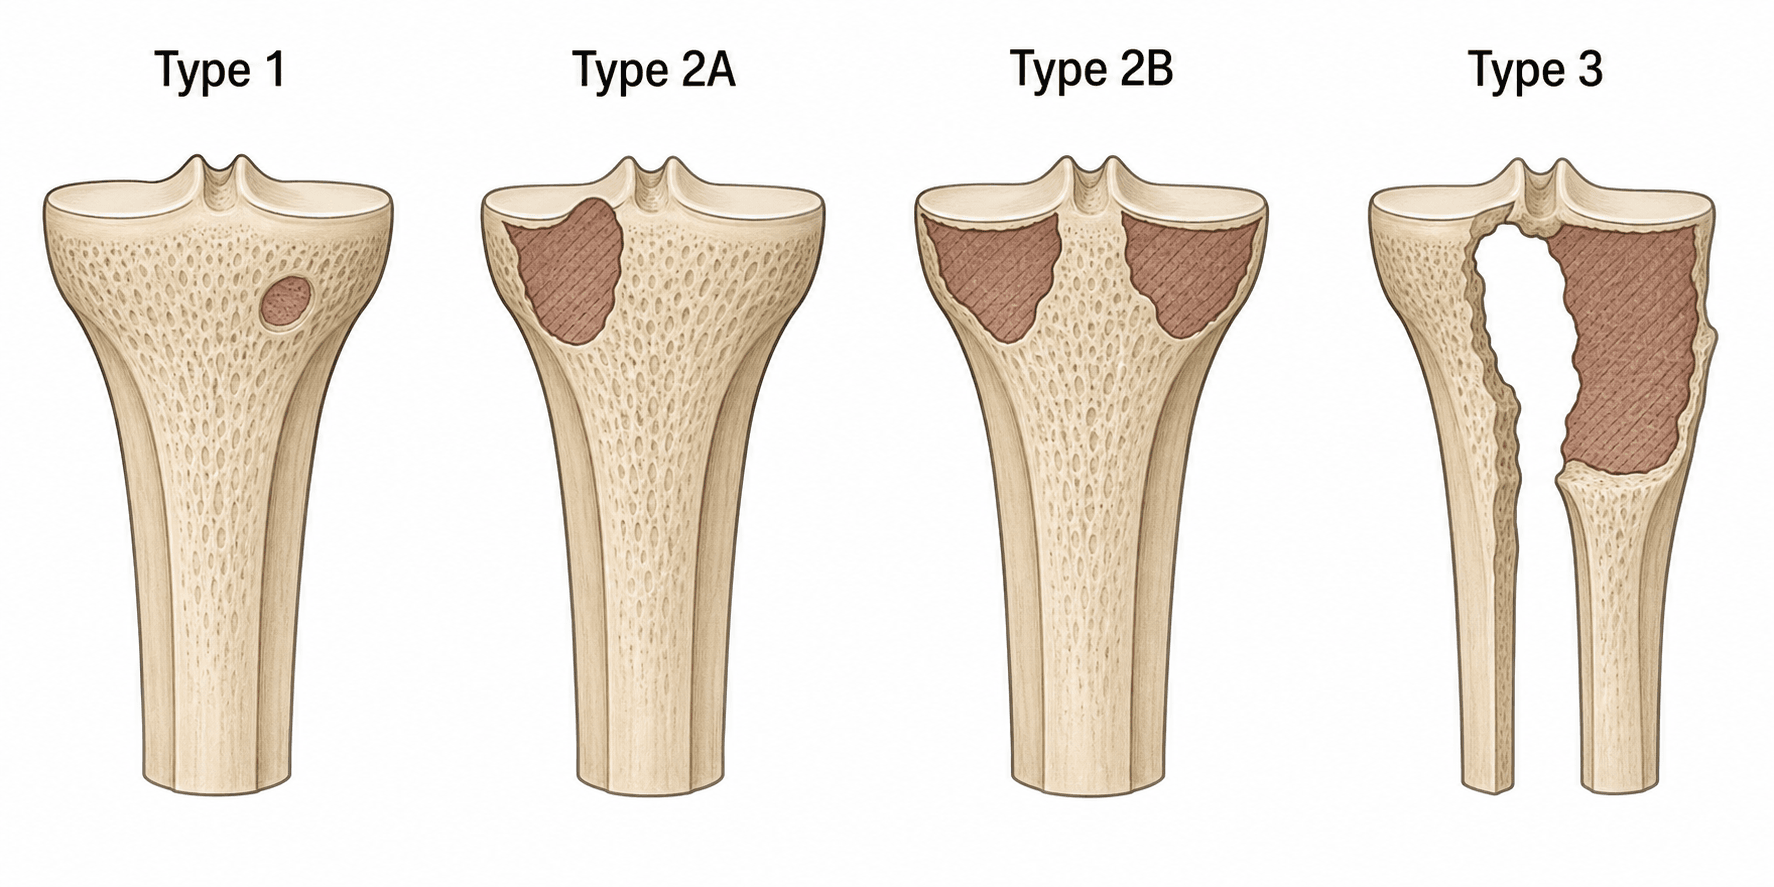
- Description
- Intact metaphyseal bone with cancellous defects only
- Bone Loss
- Minimal - contained defects
- Treatment
- Standard components, cement fill or morcellised graft
- Description
- Damaged metaphysis - one femoral condyle
- Bone Loss
- Moderate - unilateral condylar loss
- Treatment
- Metal augments (blocks), cement, or autograft
- Description
- Damaged metaphysis - both femoral condyles
- Bone Loss
- Moderate - bilateral condylar loss
- Treatment
- Bilateral metal augments or step-cut sleeves
- Description
- Deficient metaphysis - major loss affecting stability
- Bone Loss
- Severe - threatens component stability
- Treatment
- Metaphyseal sleeve, cone, or structural allograft
Femoral bone loss is common at the posterior condyles, because of posterior capsular release and wear patterns.
Clinical Assessment
The painful TKA. A painful TKA is not automatically a loose TKA. Up to a quarter of painful TKAs have no identifiable intra-articular cause, and revising these blindly worsens outcomes. Before committing to revision, systematically exclude infection (always first), then the intrinsic and extrinsic causes.
History. Localise the pain and characterise it as start-up, activity-related or constant, then correlate it with imaging and aspiration. Ask about the onset, mechanical symptoms such as locking and catching, prior infections and previous surgeries.
Examination. Record the range of motion, varus-valgus and AP drawer stability, any extensor lag, the integrity of the wound and the neurovascular status.
- Typical Features
- Rest/night pain, effusion, warmth, early failure, sinus
- Key Discriminating Test
- ESR/CRP, aspiration (WBC/PMN%, culture), alpha-defensin
- Action
- Exclude in EVERY case before any aseptic revision
- Typical Features
- Start-up pain, progressive, late onset
- Key Discriminating Test
- Progressive radiolucent lines, subsidence; bone scan if equivocal
- Action
- Revise components, address AORI bone loss
- Typical Features
- Giving way, recurrent effusion, gap imbalance
- Key Discriminating Test
- Stress radiographs, exam under anaesthesia
- Action
- Increase constraint (CCK/hinge), rebalance
- Typical Features
- Late, often painless until lysis advanced
- Key Discriminating Test
- Focal lysis on radiographs, thin poly, CT for lesions
- Action
- Poly exchange, debride and graft lysis
- Typical Features
- Anterior knee pain, patellar maltracking
- Key Discriminating Test
- Rotational CT (Berger protocol), skyline view
- Action
- Component revision if internal rotation excessive
- Typical Features
- Hip/spine pathology, neuropathic, vascular claudication
- Key Discriminating Test
- Hip/spine exam and imaging, vascular assessment
- Action
- Treat the true source - do NOT revise the knee
- Typical Features
- Patellar clunk, tendinitis, bursitis, CRPS
- Key Discriminating Test
- Clinical exam, ultrasound; CRPS is a clinical diagnosis
- Action
- Targeted non-operative management first
Investigations
Excluding infection. Serum ESR and CRP come first; an elevated value suggests infection. The knee is then aspirated for a synovial WBC, PMN% and culture (aerobic, anaerobic and fungal). The diagnostic findings for PJI on aspiration:
- Synovial WBC greater than 3000 cells/µL
- PMN greater than 80%
- Positive culture
When the answer is unclear. Alpha-defensin or synovial CRP is added if clinical suspicion is high, and alpha-defensin is confirmatory if the aspiration is equivocal. Consider aspiration biopsy if imaging shows loosening. If infection is suspected but the aspiration is negative, nuclear medicine imaging (Tc-99m, Indium-111 WBC) is used.
Imaging.
- AP and lateral radiographs for component position, alignment, radiolucent lines and osteolysis
- Long-leg alignment films for the mechanical axis
- CT if severe bone loss is suspected, to quantify the defects and plan the reconstruction
Planning. From the imaging, estimate the AORI grade, set the constraint level from bone loss and ligament integrity, and plan augments and stems for Type 2 and 3 defects. Make sure CCK and hinge implants, sleeves and cones are available.
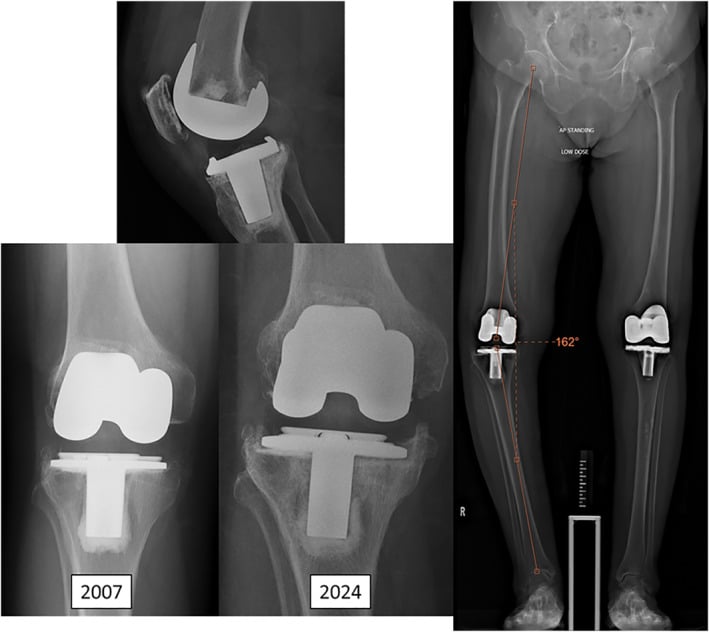
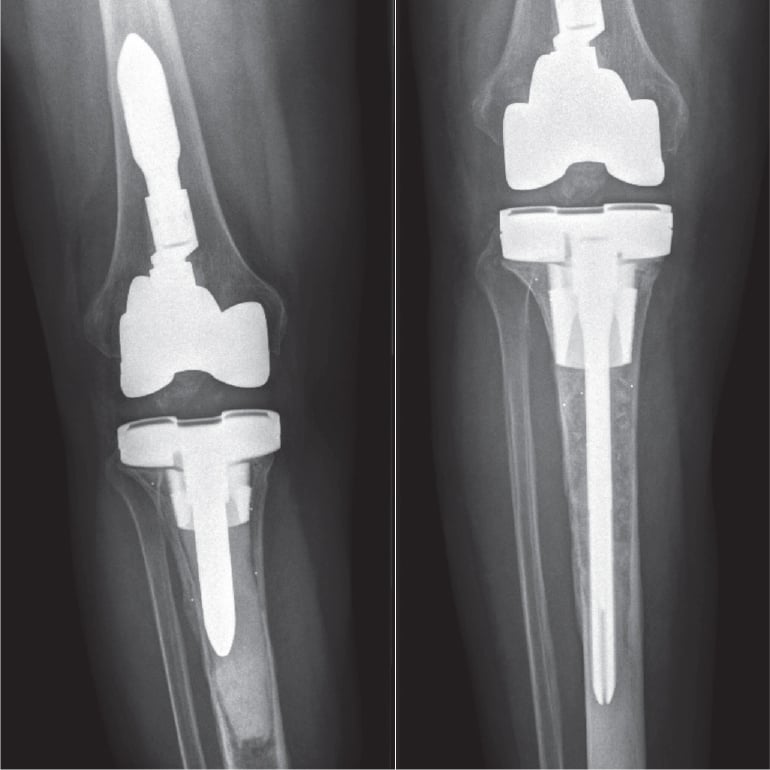
Constraint Selection
The ladder. Start with the least constraint possible, PS if feasible. Escalate to a CCK if one collateral ligament is deficient or there is moderate bone loss, and use a rotating hinge only for massive bone loss (AORI Type 3) or global instability. Over-constraining increases interface stress and loosening risk; under-constraining risks instability.
What decides it. Cruciate-retaining implants need an intact PCL and are rarely used in revision. The constraint decision, made finally at trialling, rests on:
- Bone loss (AORI grade)
- Collateral ligament integrity (MCL and LCL competence)
- Flexion-extension gap balance
- Extensor mechanism function
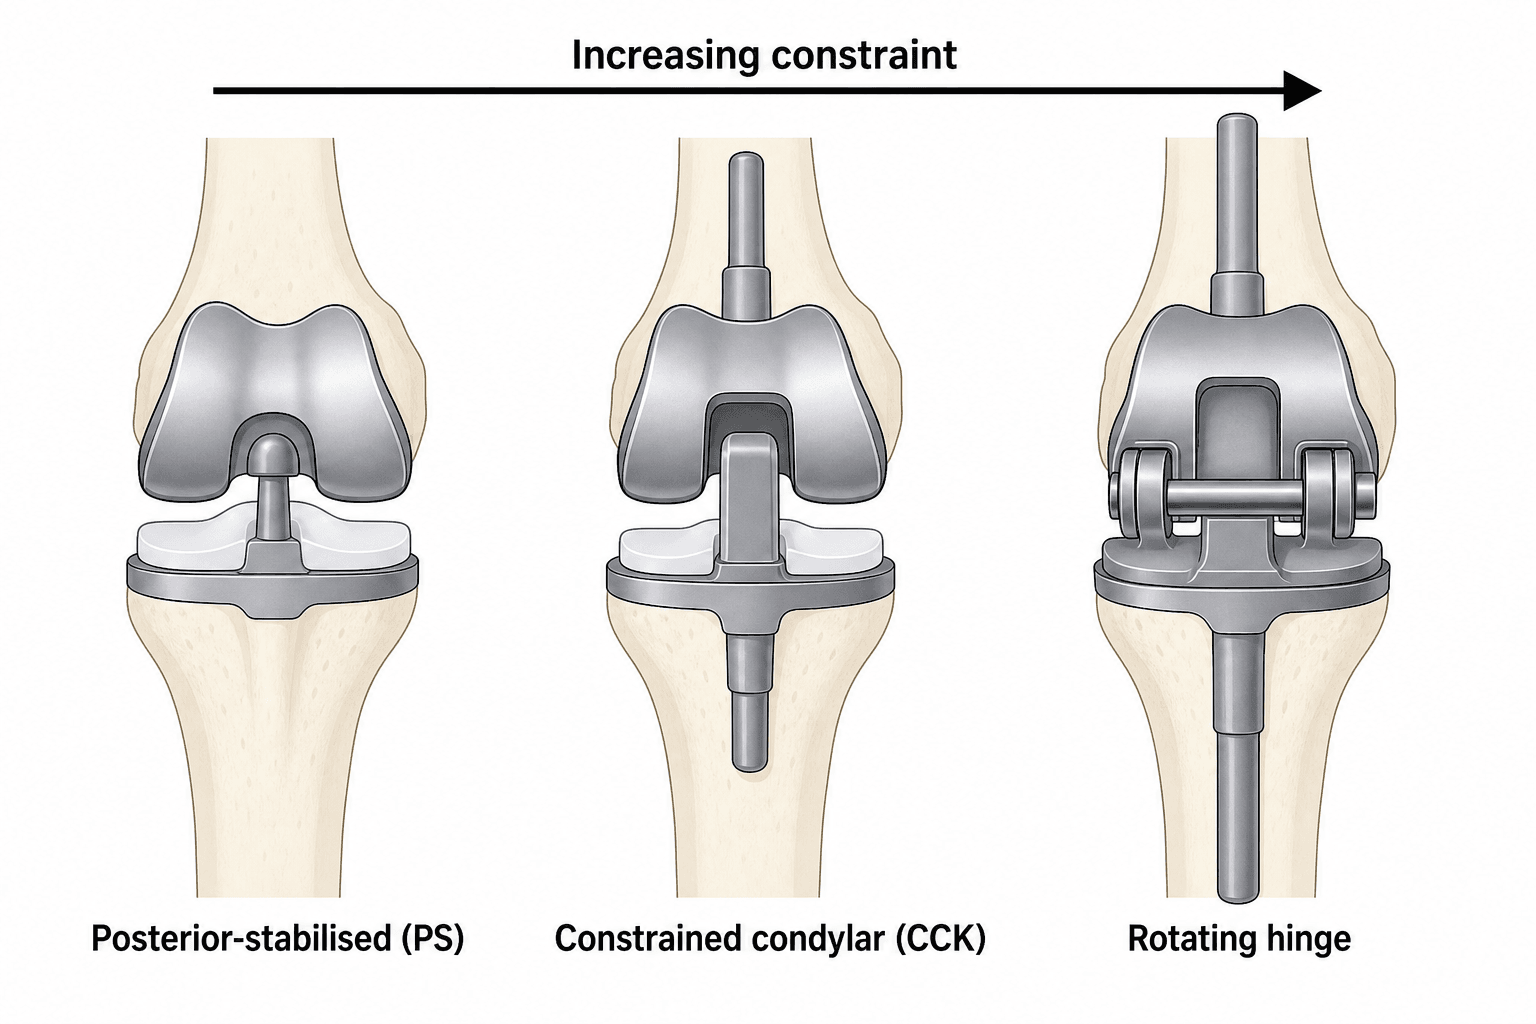
- PS
- Collaterals only
- CCK
- Polyethylene post (5-10°)
- Hinge
- Mechanical hinge (0°)
- PS
- Requires balance
- CCK
- Tolerates 3-5mm imbalance
- Hinge
- Tolerates any imbalance
- PS
- Intact metaphysis
- CCK
- AORI Type 1-2
- Hinge
- AORI Type 3 acceptable
Posterior-stabilised. Indicated for AORI Type 1 bone loss with intact MCL and LCL, balanced flexion-extension gaps and simple aseptic loosening or polyethylene wear. It needs adequate metaphyseal bone stock, no significant instability and a good extensor mechanism, and it may need stems for fixation.
- Lowest constraint, so the least interface stress
- Better preservation of range of motion
- Lower revision rate than a hinge, and a familiar implant
- Unsuitable for moderate to severe bone loss, and risks instability if mis-selected
In practice PS revision is rarely used; most revisions require at least CCK constraint.
Constrained condylar knee. Indicated for AORI Type 2A/2B bone loss, insufficiency of the MCL or the LCL, flexion-extension gap imbalance and moderate instability. A taller post and deeper cam give more constraint than a PS, and a wider tibial baseplate adds stability; it is compatible with modular augments and accepts modular stems for fixation. The CCK is the most commonly used implant in revision TKA, balancing constraint with survivorship.
Rotating hinge. Indicated for AORI Type 3 bone loss, insufficiency of the MCL and the LCL (global instability), massive bone loss requiring structural grafts, and extensor mechanism disruption (with repair). The mechanical hinge allows flexion-extension only, and a rotating bearing reduces torque at the interfaces. Long cemented stems are mandatory, and it accepts metaphyseal sleeves and cones.
Rotating hinge knees have higher complication rates than a CCK:
- Aseptic loosening 10-15% at 10 years (5-8% for CCK)
- Infection 8-10% (4-6% for CCK)
- Periprosthetic fracture 5-8%, from increased stress at the stem tip
- Bushing wear, which requires long-term surveillance
Use a hinge only when absolutely necessary. It is not a first-line option.
Management Algorithm
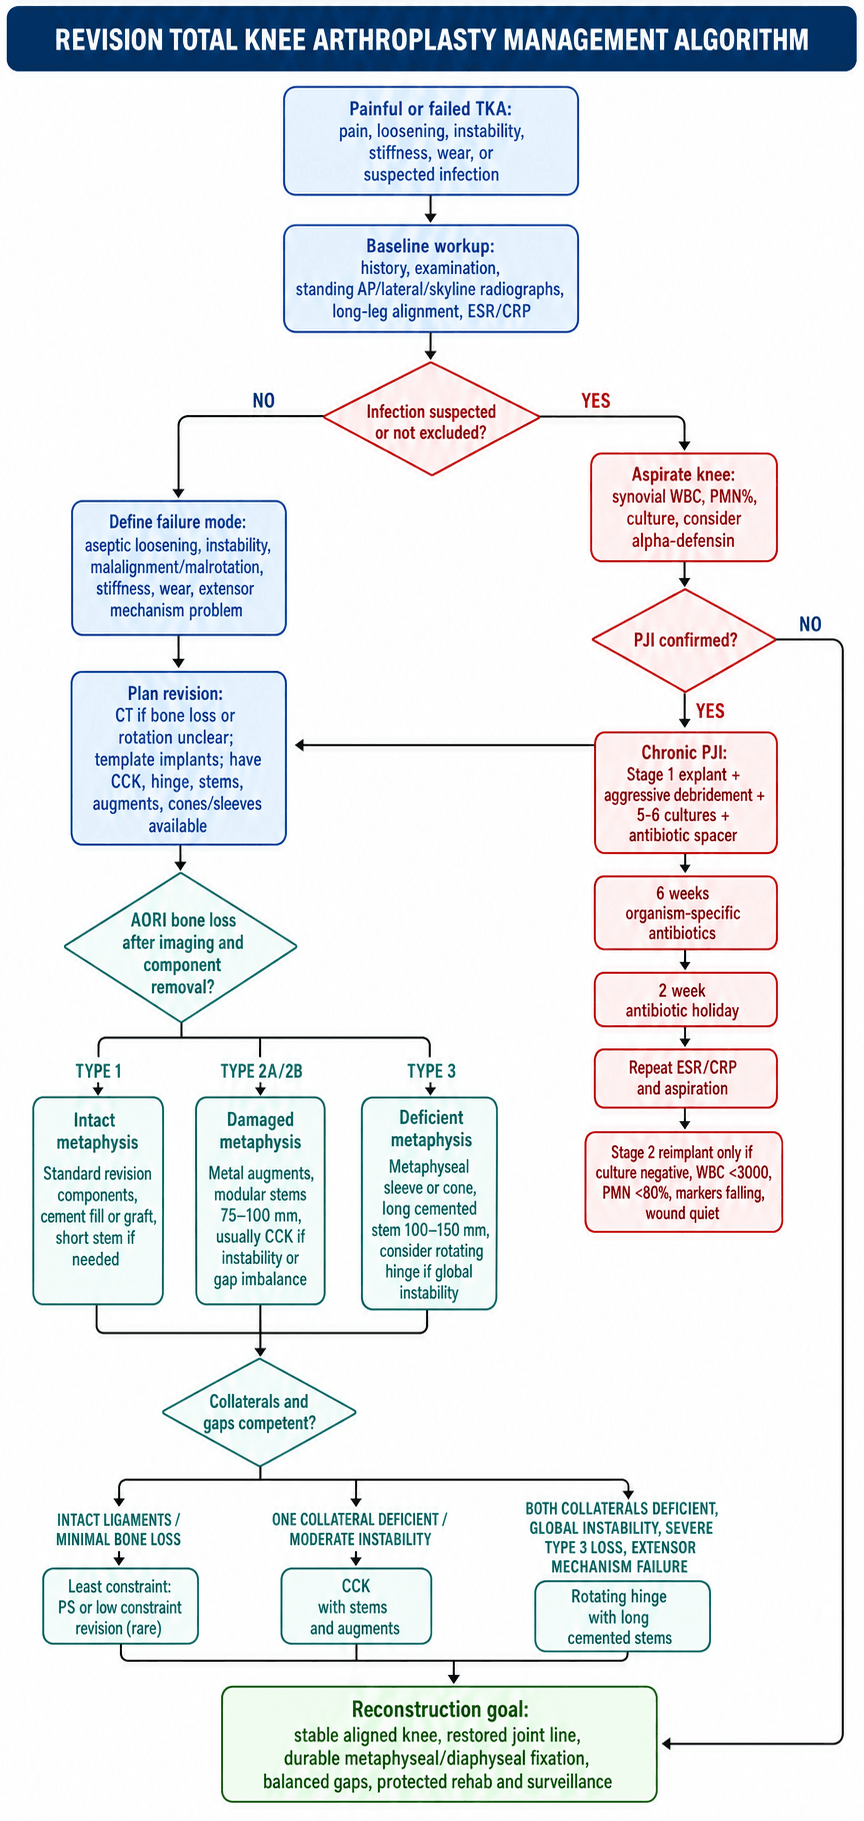
Every revision follows the same sequence, whatever the failure mode:
- Rule out infection first, by aspiration and ESR/CRP
- Assess bone loss by AORI grade, from imaging and then the intraoperative findings
- Evaluate the soft tissues: collateral ligament integrity and the extensor mechanism
- Select the constraint, PS to CCK to hinge, from the bone loss and the instability
- Plan the reconstruction: augments for Type 2, sleeves or cones for Type 3, stems for stability
Chronic PJI goes down the two-stage pathway described in its own section below.
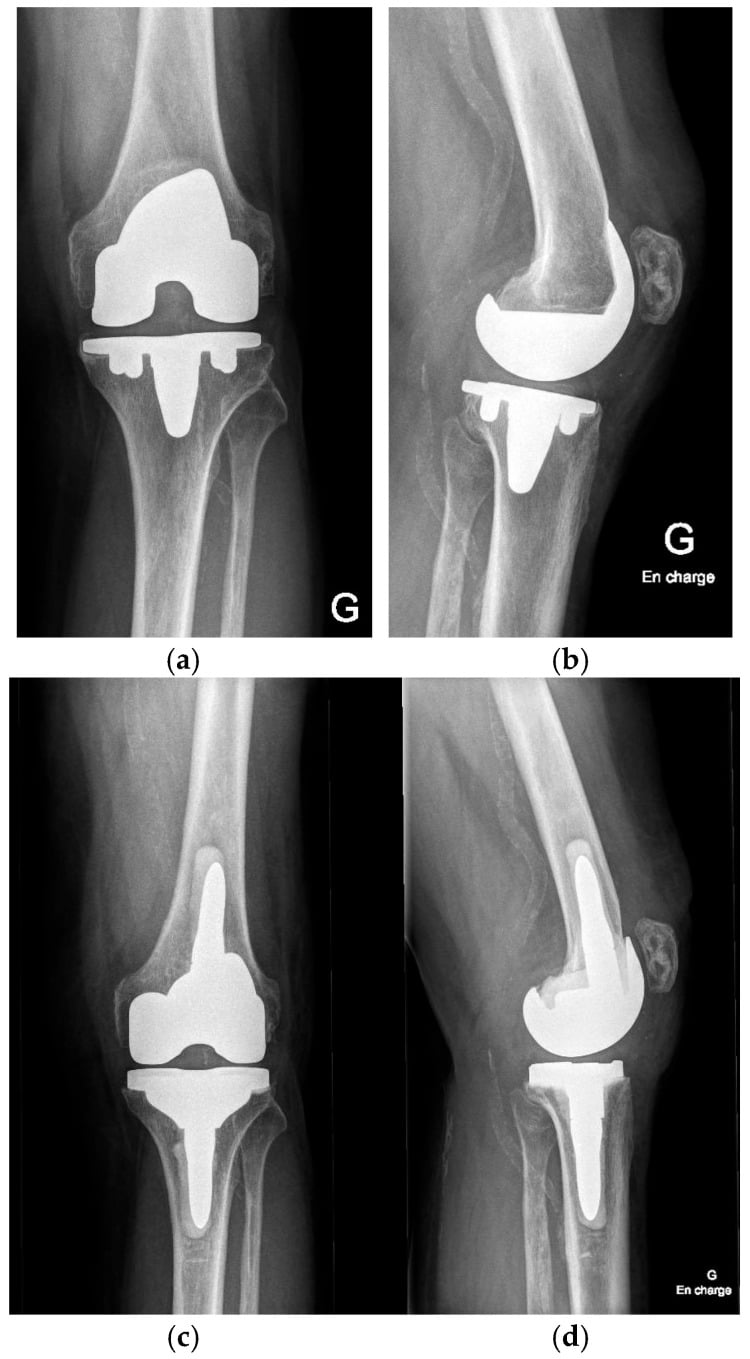
Confirming it. Radiolucent lines greater than 2mm that progress, with component subsidence, indicate loosening. Infection is still excluded by aspiration (WBC, PMN%, culture); ESR and CRP are normal or mildly elevated. Assess collateral ligament integrity from the examination and prior radiographs.
Reconstruction by grade. Remove the loose components and cement, and make the final assessment of bone loss at that point.
- Type 1: standard components (PS or CCK), cement fill, short stems
- Type 2: metal augments, modular stems, CCK constraint
- Type 3: metaphyseal sleeve or cone, long cemented stems, hinge constraint
Surgical Technique
Consent. Consent covers the complications tabulated under Complications (infection, which is higher than after a primary, aseptic loosening, periprosthetic fracture, which is higher with stems, stiffness and neurovascular injury, with the popliteal artery at risk), the risk of re-revision, and DVT/PE, for which standard prophylaxis is required.
Equipment. Revision is not the day to discover a missing tray:
- Revision implant system with CCK and hinge options
- Metal augment blocks (5mm, 10mm, 15mm)
- Modular stems in various lengths (50-150mm)
- Metaphyseal sleeves and cones for Type 3 defects
- Component removal and cement removal sets
- C-arm, essential for alignment and stem placement
- Pulse lavage for high-volume irrigation
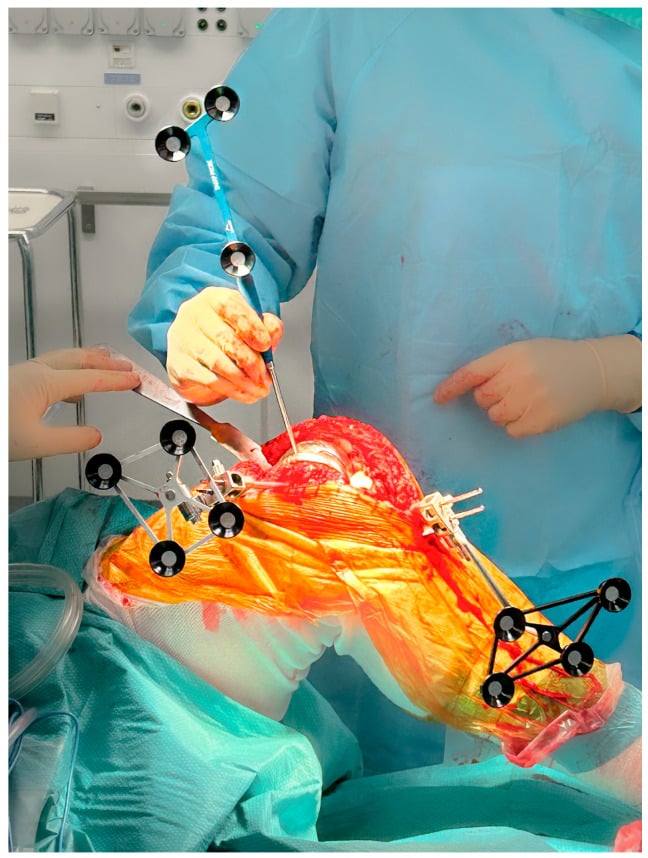
- Incision. Use the prior incision if feasible, the most lateral if there are several scars, and extend it proximally and distally as needed, often to 20-25cm. Raise full-thickness medial and lateral skin flaps to preserve their blood supply.
- Arthrotomy. A medial parapatellar arthrotomy is the standard approach, extended proximally into vastus medialis obliquus if tight. Dense scar tissue is common; release adhesions carefully.
- Patellar eversion. Attempt gentle eversion and do not force it if tight. If the patella will not evert, consider a quadriceps snip (45° oblique extension of VMO) or a tibial tubercle osteotomy (TTO), which is indicated for severe stiffness, patella baja or the need for extensile exposure.
- Releases. Release scar from the suprapatellar pouch and the medial and lateral gutters, protecting the popliteal artery behind a possibly attenuated capsule. Note MCL and LCL integrity for the constraint decision.
Restoring the Joint Line
A stable, well-fixed revision can still function poorly if the joint line is not restored. In revision TKA the joint line is easily elevated (proximalised), because distal femoral bone is lost or resected and the temptation is to "build down" the tibia or under-augment the distal femur.
What an elevated line does. The collaterals are only isometric about the native joint line, so an elevated line leaves them non-isometric and lax in mid-flexion: mid-flexion instability. By lowering the patella relative to the trochlea it also produces patella baja, with anterior knee pain, impingement and lost flexion.
Bringing it back. Restore the joint line to its native level using bony landmarks, and prefer distal femoral augments, which restore distal femoral offset, over building up the tibia.
- Approximate relationship to the native joint line
- Joint line lies about 25-30 mm distal
- Approximate relationship to the native joint line
- Joint line lies about 25 mm distal
- Approximate relationship to the native joint line
- Joint line lies about 1-1.5 cm proximal to it
- Approximate relationship to the native joint line
- Sits about 1 cm above the joint line; a low-lying patella (baja) signals an elevated joint line
- Approximate relationship to the native joint line
- Secondary references when the primary landmarks are obscured
Diaphyseal Stem Fixation: Cemented vs Cementless
Why stems. Modular stems provide rotational stability and load sharing, protecting the metaphyseal bone-implant interface. They reduce stress at that interface and improve survivorship, and in most revisions they are not optional.
- AORI Type 1: short stems, 50-75mm, press-fit or cemented
- AORI Type 2: 75-100mm, press-fit in the metaphysis and cemented in the diaphysis
- AORI Type 3: 100-150mm, fully cemented in the diaphysis (14-16cm fixation length)
- Rotating hinge: long cemented stems, always
Cemented or cementless. The diaphyseal stem can be fixed cemented or cementless (press-fit), a genuine, frequently examined controversy; the metaphyseal cone and sleeve hardware itself is covered in the dedicated bone-loss topic.
- Cementless (press-fit)
- Tight canal-filling diaphyseal cortical fit
- Cemented
- Cement mantle in the diaphysis - immediate fixation
- Cementless (press-fit)
- Needs good diaphyseal cortical bone
- Cemented
- Works in osteoporotic or wide/mismatched canals
- Cementless (press-fit)
- Stem can DICTATE position (bowed canal causes malalignment); use an offset coupler to recentre the component
- Cemented
- Component positioned independently of the canal axis (cement fills the offset)
- Cementless (press-fit)
- End-of-stem ('tip') pain in roughly 10-15%
- Cemented
- Cement burden; harder to remove at any future re-revision
- Cementless (press-fit)
- Easier to remove
- Cemented
- More difficult (cement removal)
The compromise. Neither is universally superior. The contemporary compromise endorsed by current reviews is dual-zone (hybrid) fixation: biological metaphyseal fixation with a cone or sleeve, combined with a relatively short fully cemented stem.
Two-Stage Revision for Periprosthetic Joint Infection
Two-stage revision is the gold standard for chronic periprosthetic joint infection (PJI) in the knee, with infection control rates of 85-90%.
Two-Stage Protocol
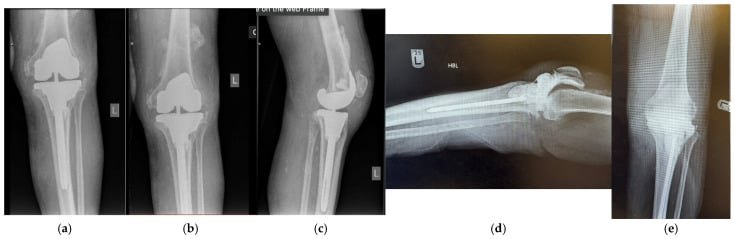
Remove all components (femur, tibia, polyethylene) and all cement, and debride aggressively: synovectomy and removal of all infected tissue and necrotic bone. Send multiple cultures (5-6) from different areas, aerobic, anaerobic and fungal. Place a static (block) or articulating spacer (prefabricated, or hand-made with a mould), with vancomycin and tobramycin or gentamicin in the cement, organism-directed if the organism is known.
Organism-specific therapy based on the intraoperative cultures, with an ID consult, for 6-8 weeks, typically 6. Check ESR and CRP weekly; they should trend downward. The patient weight-bears as tolerated with the spacer in situ, and articulating spacers allow range of motion.
Stop all antibiotics for 2 weeks before reimplantation, to clear them from the system so the aspiration is accurate. ESR and CRP should be normalising, but may not be fully normal.
Aspirate the knee through the spacer for culture and cell count, and judge the result against the reimplantation criteria.
Remove the spacer, much as in any revision, debride again, remove the spacer cement and make the final AORI grading. Implant CCK or hinge components, according to bone loss and instability, with augments and stems as needed for Type 2 and 3 defects. Organism-directed antibiotics in the cement may be considered, though this is controversial. Six weeks of organism-directed oral antibiotics follow, with an ID consult.
Criteria for reimplantation. Before Stage 2 the aspiration and markers should show:
- Synovial WBC less than 3000 cells/µL
- PMN less than 80%
- Negative culture (or a low virulence organism with biofilm coverage)
- ESR and CRP trending down (not necessarily normal)
Do NOT proceed to Stage 2 if the aspiration is positive (WBC greater than 3000 or PMN greater than 80%), ESR and CRP are not trending down, there are clinical signs of infection (wound drainage, erythema), or the patient is medically unstable. Proceeding with persistent infection results in failure over 90% of the time.
- Advantages
- Simple, inexpensive, high antibiotic elution
- Disadvantages
- No ROM, muscle atrophy, difficult Stage 2
- Use Case
- Severe bone loss, unable to achieve stability
- Advantages
- Maintains ROM, easier Stage 2, patient mobility
- Disadvantages
- More expensive, lower antibiotic concentration
- Use Case
- Moderate bone loss, able to achieve stability
- Advantages
- Customisable, high antibiotic dose, maintains ROM
- Disadvantages
- Technically demanding, spacer fracture risk
- Use Case
- When prefab spacer unavailable or special sizing needed
Complications
- Incidence
- 5-10% at 10 years
- Risk Factors
- AORI Type 3, hinged implants, inadequate fixation
- Management
- Re-revision with longer stems, structural grafts, increase constraint
- Incidence
- 4-8%
- Risk Factors
- Diabetes, obesity, prior infection, prolonged surgery
- Management
- Two-stage revision with spacer, 6-8 weeks antibiotics
- Incidence
- 3-5%
- Risk Factors
- Osteoporosis, long stems, stress riser at stem tip
- Management
- ORIF if stem stable, revision if stem loose, consider strut allografts
- Incidence
- 5-10%
- Risk Factors
- Under-constraining, flexion-extension gap imbalance, poly wear
- Management
- Increase constraint (PS to CCK to hinge), thicker poly, revise components
- Incidence
- 10-15%
- Risk Factors
- Arthrofibrosis, oversized components, overstuffing joint
- Management
- Manipulation under anaesthesia (within 12 weeks), open arthrolysis, poly exchange
- Incidence
- 2-5%
- Risk Factors
- Multiple prior surgeries, TTO, patellar fracture
- Management
- Primary repair if acute, allograft reconstruction if chronic, consider gastrocnemius flap
- Incidence
- Less than 1%
- Risk Factors
- Popliteal artery injury during exposure, common peroneal nerve palsy
- Management
- Vascular repair emergently if arterial, nerve exploration if palsy (often traction neurapraxia)
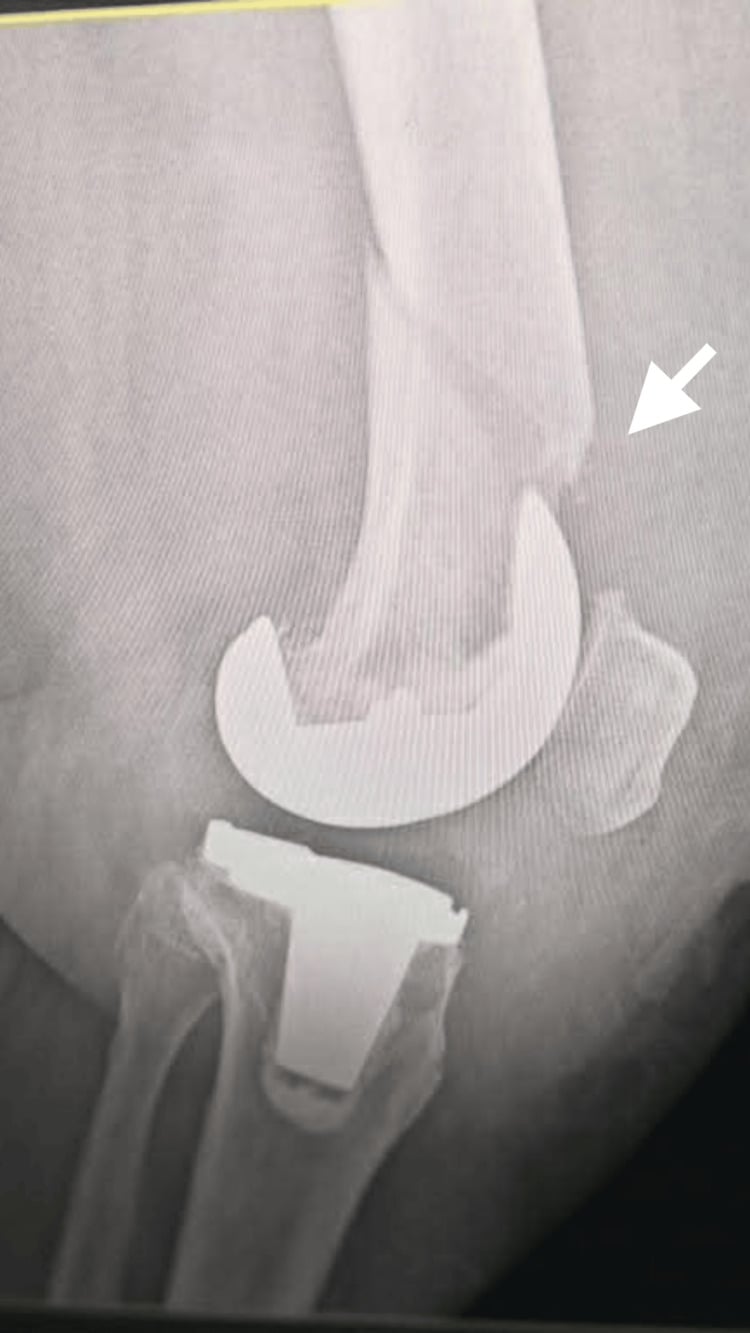
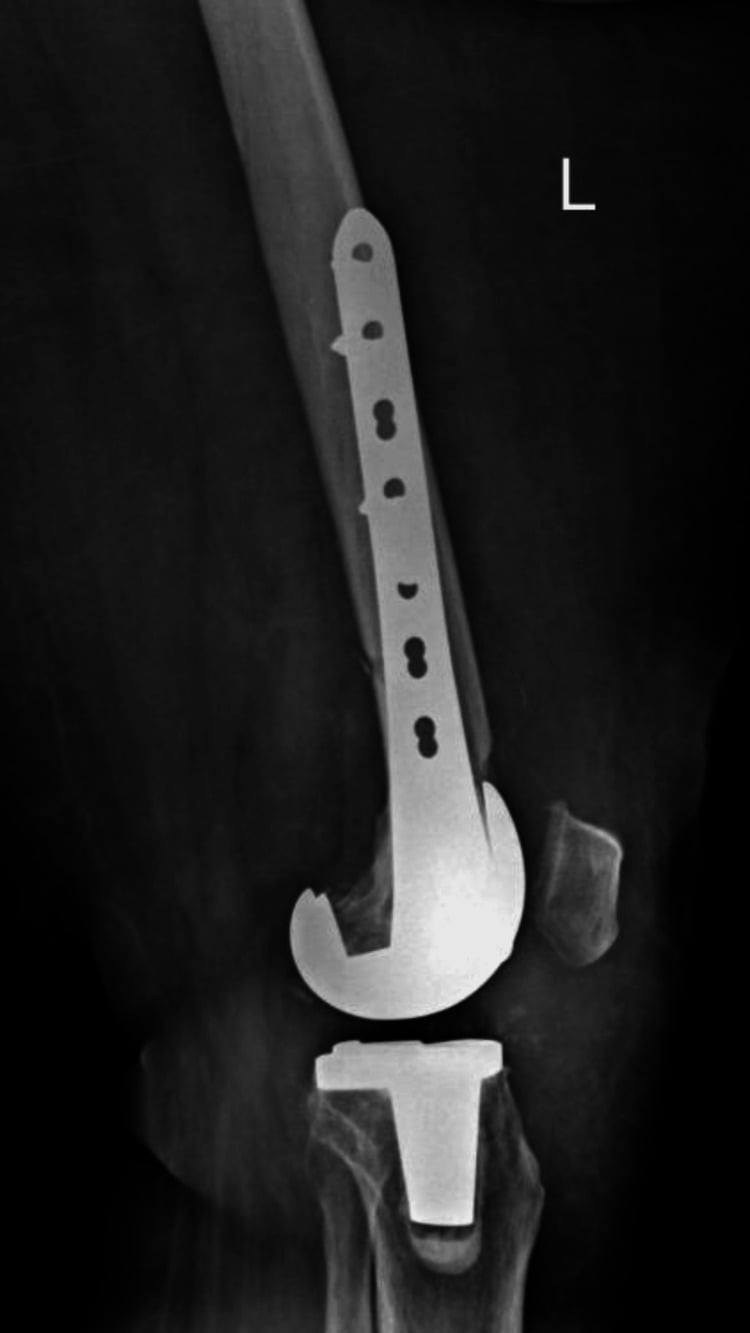
Fracture at the stem tip. Periprosthetic fractures often occur at the stem tip, a stress riser in osteoporotic bone. When the stem is stable, ORIF is with a plate and strut allograft; a loose stem is revised to a longer one.
- Use cemented stems in osteoporotic bone (better load sharing)
- Bypass prior stress risers by 2 cortical diameters, extending the stem past screw holes
- Consider strut allografts prophylactically in very osteoporotic bone
- Weight-bearing precautions (TDWB) for 6-12 weeks if high risk
Postoperative Care and Rehabilitation
Most revisions weight-bear as tolerated from the start and begin range of motion immediately, aiming for 0-110° by 6 weeks. A tibial tubercle osteotomy changes that: the tubercle must heal, and weight-bearing is protected until it does.
Rehabilitation Timeline
DVT prophylaxis is chemical (enoxaparin or rivaroxaban) and mechanical (SCDs), with multimodal analgesia (paracetamol, NSAIDs, opioids as needed). The patient sits out of bed on day 1 and walks with a frame on day 2. Range of motion starts with CPM or bedside physiotherapy, aiming for 0-90° by discharge.
Progress to full weight-bearing with an assistive device, and from frame to stick to independent walking. Active-assisted and passive range of motion, with quadriceps work: straight leg raises, quad sets and terminal knee extension. Staples come out at 2 weeks; watch the wound for infection. Radiographs at 6 weeks check alignment and component position and look for early loosening.
Discontinue the assistive device once the gait is safe without a limp. Progress resistance training for the quadriceps, hamstrings and hip abductors, add stairs, sit-to-stand and balance work, and aim for 0-120° flexion. Light ADLs only, avoiding high impact (running, jumping).
Independent ADLs, driving at 8-12 weeks and return to work at 12-16 weeks. Low-impact activity only (cycling, swimming, golf). Annual radiographs and clinical review monitor for loosening, wear and osteolysis. Pain improves in 80-85% of patients.
Outcomes and Prognosis
- Survivorship (10 yr)
- 90-95%
- Functional Outcome
- Good - similar to primary TKA
- Re-revision Risk
- 5-8%
- Survivorship (10 yr)
- 85-90%
- Functional Outcome
- Fair - 70-80% of primary
- Re-revision Risk
- 10-15%
- Survivorship (10 yr)
- 80-85%
- Functional Outcome
- Fair to poor - 60-70% of primary
- Re-revision Risk
- 15-20%
- Survivorship (10 yr)
- 80-85% (infection control 85-90%)
- Functional Outcome
- Fair - 60-70% of primary
- Re-revision Risk
- 20-25%
- AORI Type 3 bone loss (requires structural grafts, higher failure)
- Rotating hinge implant (higher loosening and infection rates)
- Multiple prior revisions (re-revision risk doubles with each revision)
- Chronic PJI (two-stage has lower function than aseptic revision)
- BMI over 35 (higher infection and complication rates)
- Extensor mechanism insufficiency (quadriceps dysfunction limits function)
Counsel patients realistically: revision TKA does NOT achieve primary TKA outcomes.
Guidelines, Registries & Global Practice
Revision TKA is a globally rising burden driven by an ageing population and expanding primary TKA volumes. Across major national registries the leading reasons for revision are broadly consistent - infection, aseptic loosening and instability dominate - but exact proportions, implant choices and PJI protocols vary by region. Candidates for any board should know the common diagnostic framework (ICM/EBJIS for PJI, AORI for bone loss) and where major guidelines genuinely differ.
Global epidemiology
- Rising volume: registry data consistently report year-on-year growth in revision TKA tracking the global rise in primary TKA (de Steiger/AOANJRR, PMID 35271977)
- Leading failure modes: infection, aseptic loosening and instability predominate across registries
- Demographics: mean age 65-70 at revision; female predominance mirrors primary TKA
- Time to revision: bimodal - early failures (infection, instability, malposition) vs late (loosening, wear)
- AOANJRR distal femoral replacement for periprosthetic fracture: cumulative second-revision 12% at 6 years; infection (37%) and aseptic loosening (33%) the main re-revision causes (PMID 35271977)
- German EPRD: aseptic revision higher after constrained vs unconstrained TKA (3.3% vs 2.8% at 7 years); ligament instability the commonest aseptic cause in unconstrained TKA (PMID 39313693)
- Registries (NJR, AJRR, AOANJRR, SHAR, NZJR) are the primary source of real-world implant survival
MCQ Practice Points
Q: A revision TKA patient has bone loss affecting both tibial plateaus but the metaphyseal rim is intact. What AORI grade is this and what reconstruction is appropriate? A: AORI Type 2B (damaged metaphysis, both condyles/plateaus involved). Appropriate reconstruction includes bilateral metal augments (5-15mm blocks) cemented to the host bone, with a modular tibial baseplate and press-fit stem (75-100mm length, cemented in diaphysis) for rotational stability and load sharing. Type 2B requires augmentation but does NOT need structural grafts (sleeves/cones).
Q: What is the key difference in indications between a CCK and a rotating hinge implant in revision TKA? A: CCK (constrained condylar knee) is indicated for AORI Type 1-2 bone loss with MCL or LCL insufficiency (one collateral deficient), or moderate flexion-extension gap imbalance (3-5mm). Rotating hinge is reserved for AORI Type 3 bone loss (deficient metaphysis), MCL and LCL insufficiency (global instability), or massive flexion-extension gap imbalance. CCK provides varus-valgus constraint through a taller post (5-10° laxity) but still relies on collaterals; hinge is a mechanical hinge allowing only flexion-extension (0° varus-valgus laxity).
Q: What are the criteria for proceeding to Stage 2 reimplantation after a two-stage revision for chronic PJI? A: Criteria include: (1) Completed 6-8 weeks IV antibiotics organism-specific, (2) 2-week antibiotic holiday to clear antibiotics from system, (3) Aspiration of knee joint showing synovial WBC less than 3000 cells/µL and PMN less than 80%, (4) Negative culture (or low-virulence organism with biofilm antibiotic coverage planned), (5) ESR and CRP trending downward (may not normalize completely, but should be improving). All criteria must be met before reimplantation - proceeding with persistent infection results in failure in over 90% of cases.
Q: What is the recommended stem fixation technique in revision TKA for AORI Type 3 defects? A: Long cemented stems (100-150mm length) with 14-16cm cemented fixation in the diaphysis. The stem provides load sharing and bypasses the deficient metaphysis (Type 3). Cementation technique: place cement restrictors, pressurize cement in the diaphyseal canal, insert stem and allow polymerization. Press-fit fixation in the metaphysis is inadequate for Type 3 defects - must have diaphyseal fixation. Stem length should bypass any stress risers (prior screw holes) by 2 cortical diameters to prevent periprosthetic fracture.
Q: What are the advantages of metaphyseal sleeves over structural bulk allografts for AORI Type 3 defects? A: Metaphyseal sleeves have superior survivorship (92% at 5 years vs 78% for allografts), lower complication rates (10% vs 25%, particularly nonunion and resorption seen with allografts), biological fixation through osseointegration (porous-coated titanium), and faster rehabilitation (immediate press-fit stability vs waiting for graft incorporation). Allografts have risks of nonunion (10-15%), resorption over time, disease transmission (very low but non-zero), and technically demanding shaping/fixation. Sleeves are now first-line treatment for Type 3 defects.
Q: How do functional outcomes and survivorship of revision TKA compare to primary TKA? A: Revision TKA has inferior outcomes to primary TKA: (1) Functional scores 70-80% of primary TKA (worse with hinge or two-stage), (2) Survivorship 85-90% at 10 years vs 95% for primary TKA, (3) Re-revision rate 15-20% at 5 years vs 2-3% for primary, (4) Complication rate 20-30% vs 5-10% for primary. Patients must be counseled realistically - revision TKA does NOT restore primary TKA function and has higher risk of failure. Two-stage revisions for PJI have even worse outcomes (60-70% function, 80-85% survivorship).
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 68-year-old woman presents with progressive medial knee pain 8 years after primary TKA. Examination shows stable knee with full extension and 110° flexion, no effusion. Radiographs demonstrate 2mm radiolucent lines under the medial tibial baseplate and small focal osteolysis. ESR 18, CRP 8. How would you assess and manage this patient?”
“A 72-year-old diabetic man with prior TKA presents with chronic pain and recurrent effusions for 6 months. He has had two aspirations showing low-grade coagulase-negative staph. ESR 45, CRP 22. You have performed Stage 1 debridement and spacer placement. Walk me through your Stage 2 planning and technique.”
“Intraoperatively during revision TKA, after component removal you find severe tibial bone loss - the entire medial and lateral plateaus are gone down to the metaphyseal-diaphyseal junction (AORI Type 3). How do you reconstruct this defect?”
Key Indications
- Aseptic loosening: 50% of revisions - radiolucent lines, subsidence, pain
- Instability: 20% - MCL/LCL insufficiency, flexion-extension gap imbalance
- Infection (PJI): 15% - two-stage revision gold standard (85-90% control)
- Polyethylene wear/osteolysis: 10% - focal lysis, thin poly
- Stiffness: 3-5% - less than 90° flexion, failed manipulation
AORI Bone Defect Classification
- Type 1 (Intact): Metaphyseal bone intact - standard components, cement fill
- Type 2A (Damaged one): One condyle/plateau - metal augment, cement, stem
- Type 2B (Damaged both): Both condyles/plateaus - bilateral augments, stem
- Type 3 (Deficient): Metaphysis deficient - sleeve/cone/allograft, long stem (14-16cm)
Constraint Selection Algorithm
- PS: AORI Type 1, intact MCL and LCL, balanced gaps (rarely used in revision)
- CCK: Type 2, MCL OR LCL deficient, 3-5mm gap imbalance (most common)
- Rotating hinge: Type 3, MCL AND LCL deficient, massive bone loss, global instability
- Increase constraint as bone loss worsens and soft tissue insufficiency increases
Surgical Technique Pearls
- Rule out infection FIRST: ESR/CRP, aspirate (WBC, PMN%, culture) in ALL cases
- Component removal: Peripheral osteotomes, circumferential disruption, preserve bone
- Cement removal: Meticulous debridement - final AORI only visible after cement out
- Stems: Modular, 75-100mm Type 2, 100-150mm Type 3, cemented in diaphysis (14-16cm)
- Metaphyseal sleeves: Press-fit biological fixation for Type 3, 92% survivorship at 5 years
Two-Stage Revision Protocol
- Stage 1: Debridement, explant, antibiotic spacer (vancomycin + tobramycin in cement)
- 6-8 weeks IV antibiotics organism-specific (ID consult), then 2-week holiday
- Reimplantation criteria: WBC less than 3000, PMN less than 80%, negative culture, ESR/CRP trending down
- Stage 2: Remove spacer, debride again, revise with CCK/hinge, augments/stems as needed
- Infection control: 85-90%, but re-revision risk 20-25%, function 60-70% of primary
Complications and Outcomes
- Aseptic loosening: 5-10% at 10 years (higher with hinge, Type 3 defects)
- Infection: 4-8% (higher than primary 1-2%)
- Periprosthetic fracture: 3-5% (stem tip stress riser, osteoporotic bone)
- Survivorship: 85-90% at 10 years (vs 95% primary), re-revision 15-20% at 5 years
- Function: 70-80% of primary TKA (worse with hinge or two-stage)
Evidence Base and Key Trials
Tantalum Femoral Cones for Severe Femoral Bone Loss (AORI Type 3)
- Single-institution series: 159 tantalum metaphyseal femoral cones in 157 patients, mean follow-up 5 years
- 5-year survivorship 96% with cone aseptic loosening as the endpoint
- 5-year survivorship 84% for revision of the cone for any reason, 70% free of any reoperation
- All 134 unrevised cones were radiographically well-fixed without loosening
- Aseptic cone failure was associated with hinged TKA used for a Type 3 defect
Metaphyseal Sleeves for Bone Loss in Revision TKA
- Prospective series: 96 knees revised with metaphyseal sleeves, 83 with minimum 2-year follow-up (mean 2.4 years)
- Sleeves used predominantly for AORI Type 2B defects (femoral and tibial revisions)
- Mean Knee Society function score improved from 47.9 to 61.1 points
- No progressive radiolucent lines were seen around the metaphyseal sleeves
- Only 2 of 73 tibial components (2.7%) required revision for aseptic loosening at short-term follow-up