High-Energy Posterior Pelvic Injuries | Denis Zones | Neurological Risk
- Denis zones predict NEUROLOGICAL injury risk (lateral to central progression)
- CT is ESSENTIAL - 30-50% missed on plain radiographs
- Zone III involves sacral canal = cauda equina symptoms (bowel/bladder/sexual)
- Spinopelvic dissociation = complete disconnection of spine from pelvis
- Document bowel, bladder, sexual function (sacral roots S2-S4)
- “Zone I: 5-10% neuro injury (L5 nerve - foot drop risk)
- “Zone II: 25-30% neuro injury (S1-S2 roots - plantarflexion/sensation)
- “Zone III: Up to 60% neuro injury (cauda equina - emergency!)
- “U-shaped and H-shaped fractures = spinopelvic dissociation = highest neuro rate
- “SI screws must avoid foramina and target S1 body (safe corridor)
Overview and Epidemiology
Sacral fractures occur in approximately 45% of pelvic ring injuries and are among the most commonly missed fractures in trauma. Dense bony overlap makes them difficult to see on plain radiographs, and CT is essential for diagnosis.
The keystone. The sacrum is the posterior keystone of the pelvic ring, transferring weight from the spine to the lower limbs, and the posterior structures provide 60% of ring stability. A sacral fracture can occur in isolation, as a stress fracture or after a fall, or as part of a complex pelvic ring injury in a vertical shear, lateral compression or APC pattern, often in the setting of polytrauma.
Why it matters. Neurological injury complicates 5-60% of these fractures, depending on the zone the fracture line crosses.
Two populations. The distribution is bimodal. Young patients sustain high-energy injuries, from motor vehicle accidents and falls, through vertical shear and lateral compression mechanisms. Elderly patients sustain insufficiency fractures through osteoporotic bone, and these are common.
Anatomy and Biomechanics
The bone. The sacrum is a triangular bone of five fused vertebrae (S1-S5) forming the posterior wall of the pelvis. It articulates with L5 above, the coccyx below and the ilia at the sacroiliac joints on each side.
Three regions from lateral to medial. The Denis zones follow the anatomy, and each region carries its own neural structure:
- The ala is the lateral, wing-like extension. The L5 nerve root exits under it and runs on its anterior surface. Zone I fractures occur here.
- The foramina are anterior and posterior openings that transmit the S1-S4 roots. Zone II fractures pass through them.
- The sacral canal is central and houses the cauda equina. Zone III fractures involve it and carry the highest neurological risk.
What each root does. L5 serves great toe extension and ankle dorsiflexion, S1 ankle plantarflexion and the ankle jerk, and S2-S4 bowel, bladder and sexual function.
Classification Systems
Denis classification. Denis divides the sacrum into three longitudinal zones by position relative to the sacral foramina, and the reason it endures is that the zones predict which neural structures are at risk and therefore what deficit to look for. Read the injury rates as approximate and directional. They derive from Denis's original 1988 retrospective analysis of 236 sacral fractures, in an era before routine CT, in which zone assignment and neurological assessment were not standardised and patients with subtle sphincter or sexual dysfunction would have been under-counted.
The rank order, Zone I lowest and Zone III highest, is robust and is what examiners want. The precise percentages vary between series and should not be quoted to a patient as a personal risk.
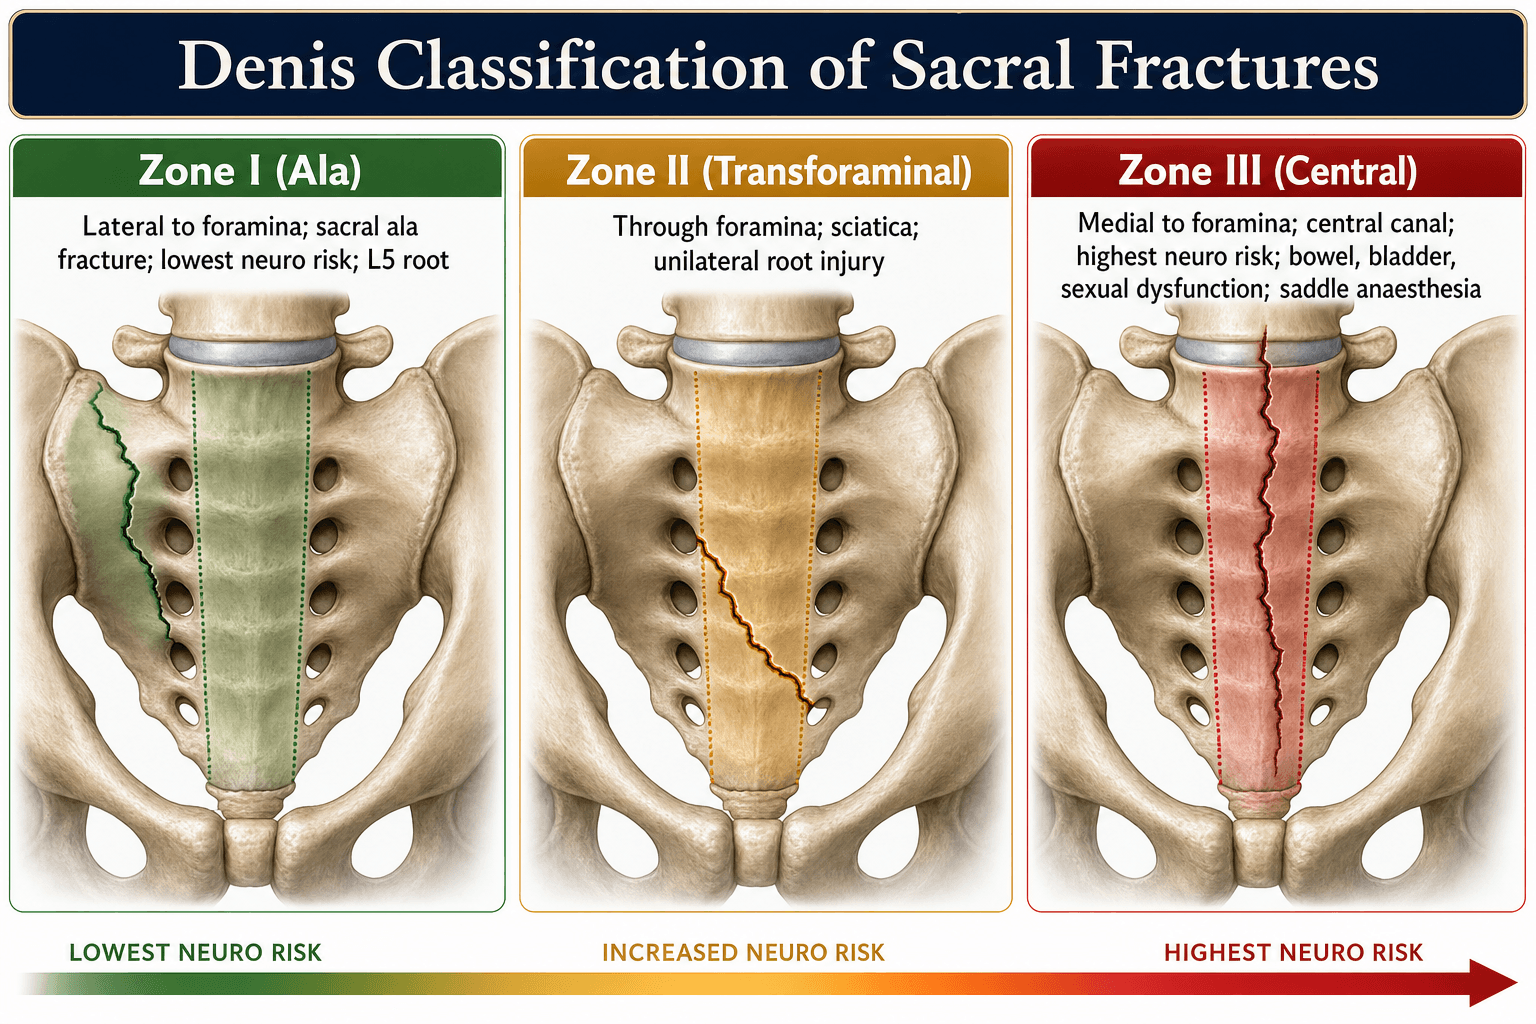
- Zone I
- Lateral to foramina
- Zone II
- Through foramina
- Zone III
- Medial to foramina
- Zone I
- Alar region
- Zone II
- Transforaminal
- Zone III
- Sacral canal
- Zone I
- L5
- Zone II
- S1-S4 roots
- Zone III
- Cauda equina
- Zone I
- 5-10%
- Zone II
- 25-30%
- Zone III
- Up to 60%
- Zone I
- Foot drop
- Zone II
- Weak plantarflexion
- Zone III
- Bowel/bladder/sexual
- Zone I
- Usually stable
- Zone II
- Variable
- Zone III
- Usually unstable
Zone I (alar). The fracture lies in the wing, lateral to the foramina, where it can injure the L5 root on the anterior alar surface. The deficit is a foot drop with weak great toe extension and sensory loss over the dorsum of the foot.
Zone II (transforaminal). The line runs through one or more foramina, and this is the most common traumatic pattern. The deficit follows the root: S1 gives weak plantarflexion and an absent ankle jerk, S2 sensory loss over the posterior thigh, and S3-S4 variable bowel and bladder dysfunction.
Zone III (central). The fracture lies medial to the foramina and enters the sacral canal, putting the cauda equina and all the sacral roots at risk. The result is a cauda equina syndrome: bowel, bladder and sexual dysfunction, saddle anaesthesia and variable lower limb weakness.
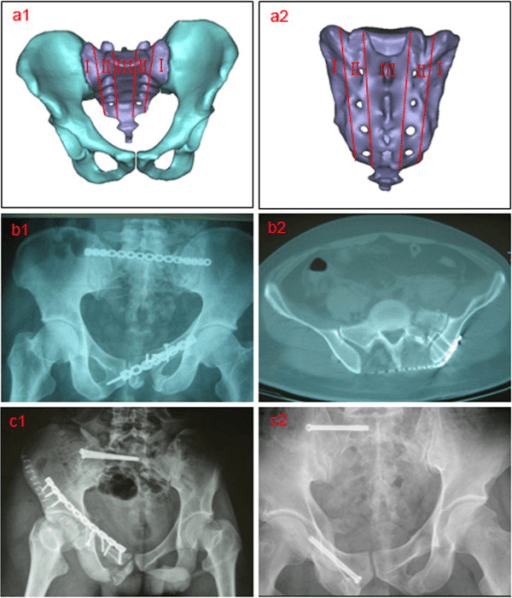
Roy-Camille classification of transverse fractures. Roy-Camille described three types of transverse upper-sacral fracture, and the position of the lumbar spine at the moment of impact decides which one results: flexion (kyphosis) produces types 1 and 2, extension (lordosis) produces type 3.
- Type 1: kyphotic angulation of the upper fragment with no translation
- Type 2: kyphotic angulation plus posterior translation of the upper fragment
- Type 3: complete anterior translation of the upper fragment
A type 4 was added later by Strange-Vognsen and Lebech: a segmentally comminuted upper sacrum that is not displaced relative to the lower fragment, caused by axial load with the lumbar spine in the neutral position. It is a separate description, not part of the original three.
The type describes morphology rather than prognosis. In lumbopelvic-fixation series it is the degree of translational displacement and residual kyphosis, not the Roy-Camille type, that tracks with neurological recovery.
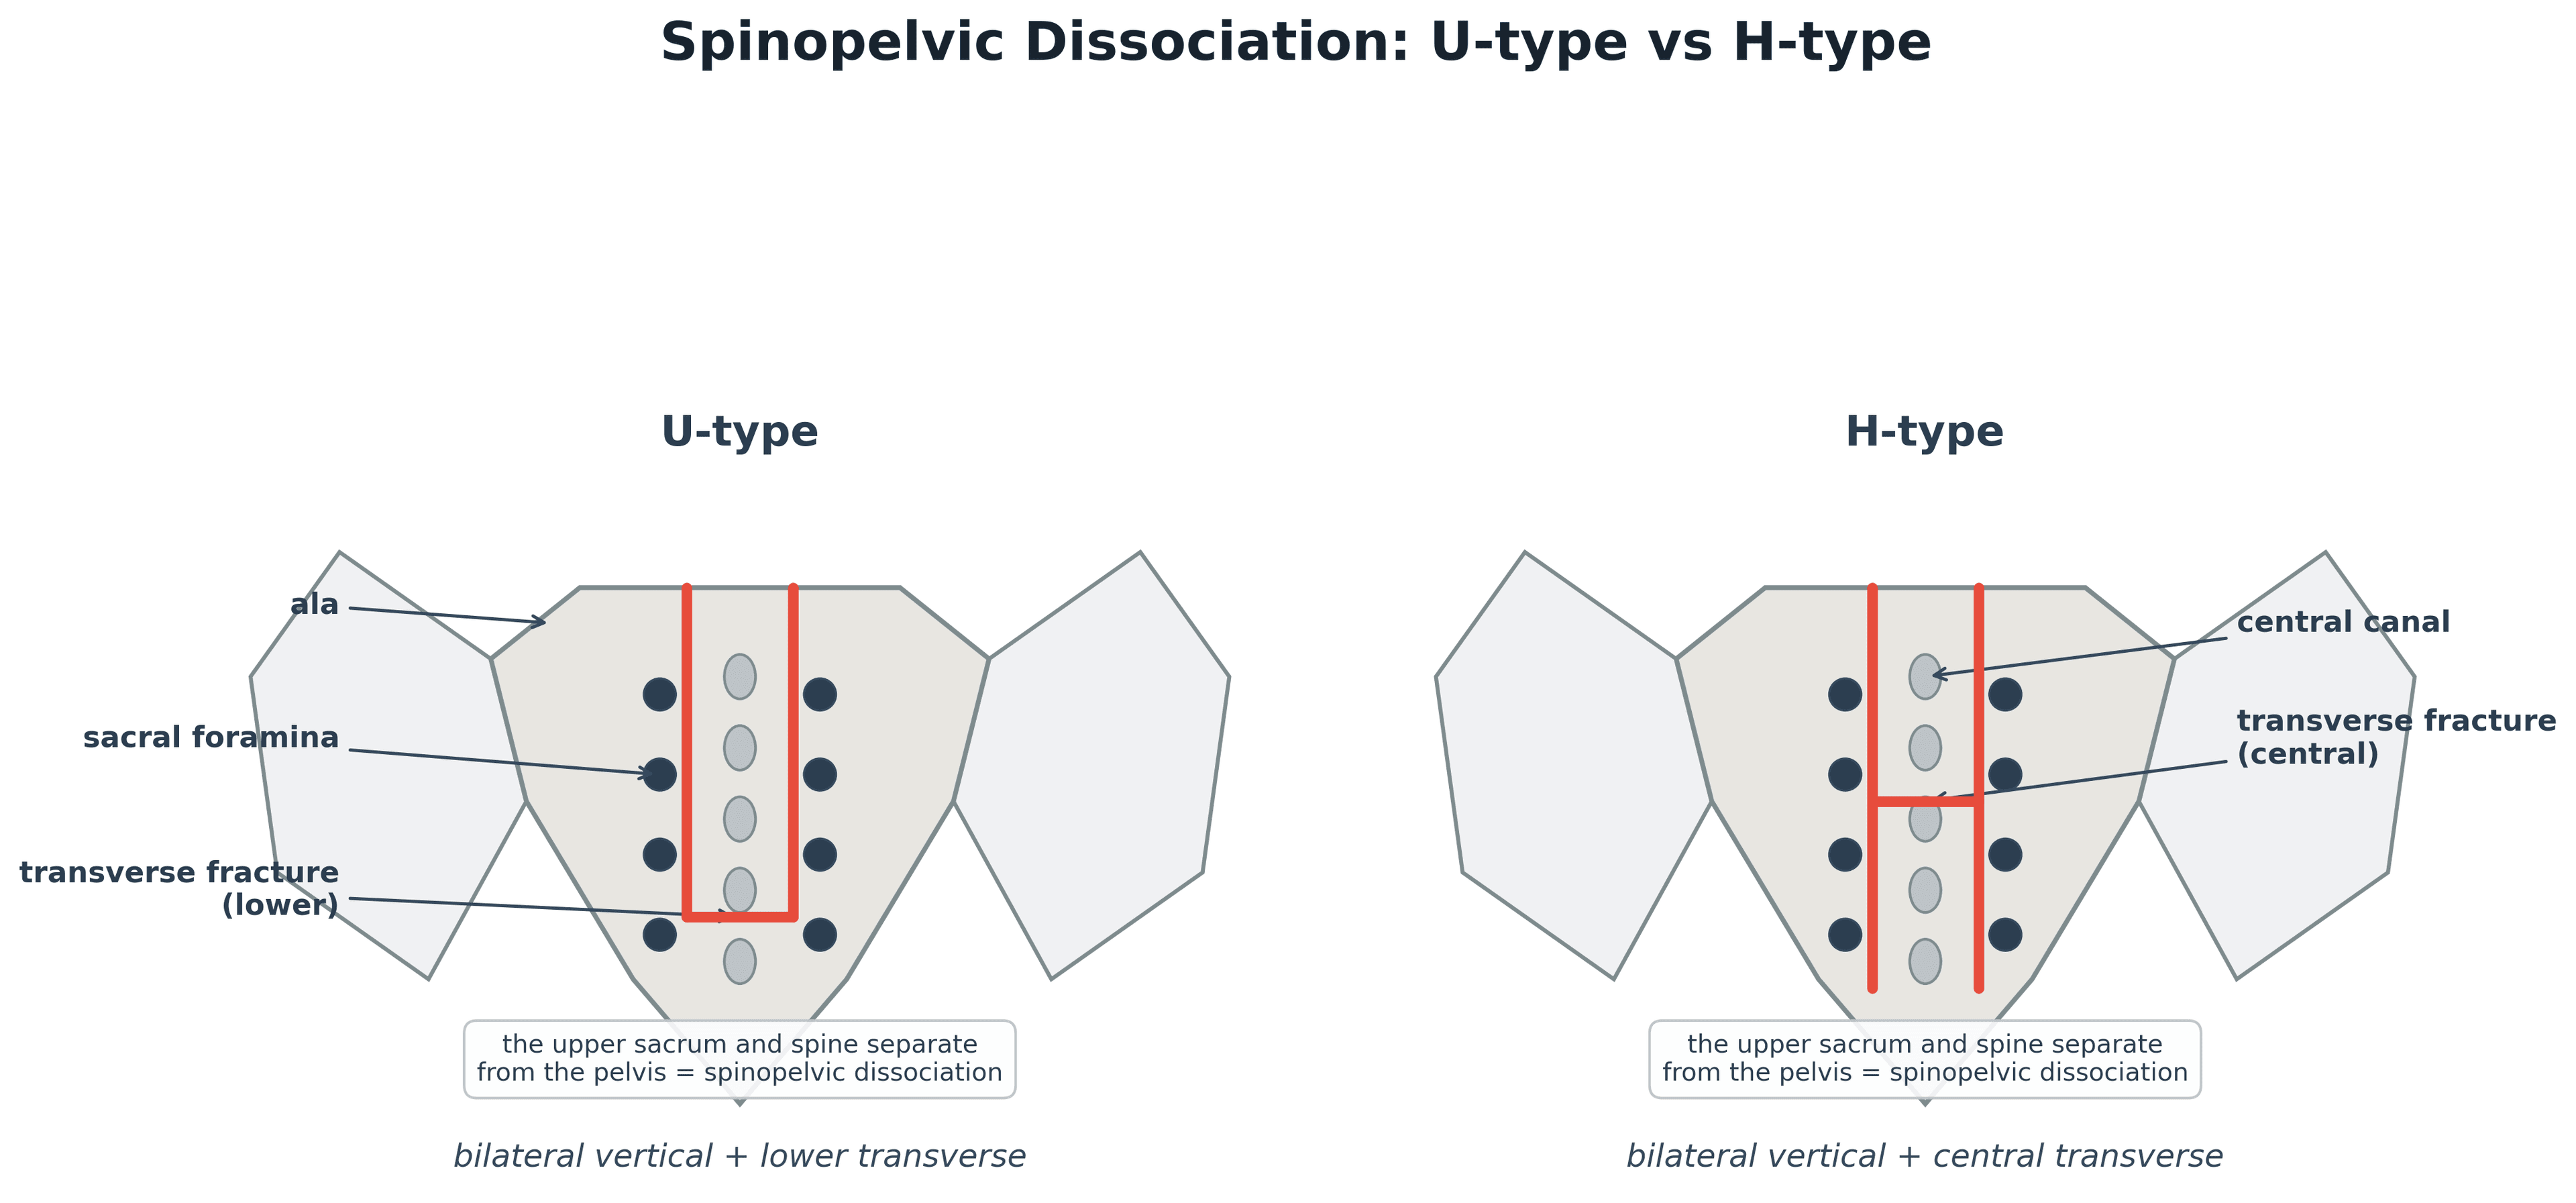
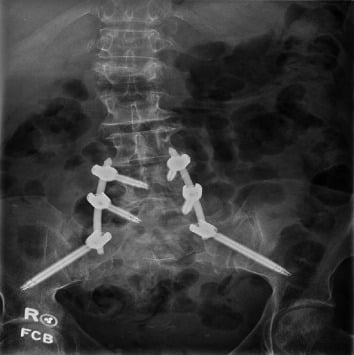
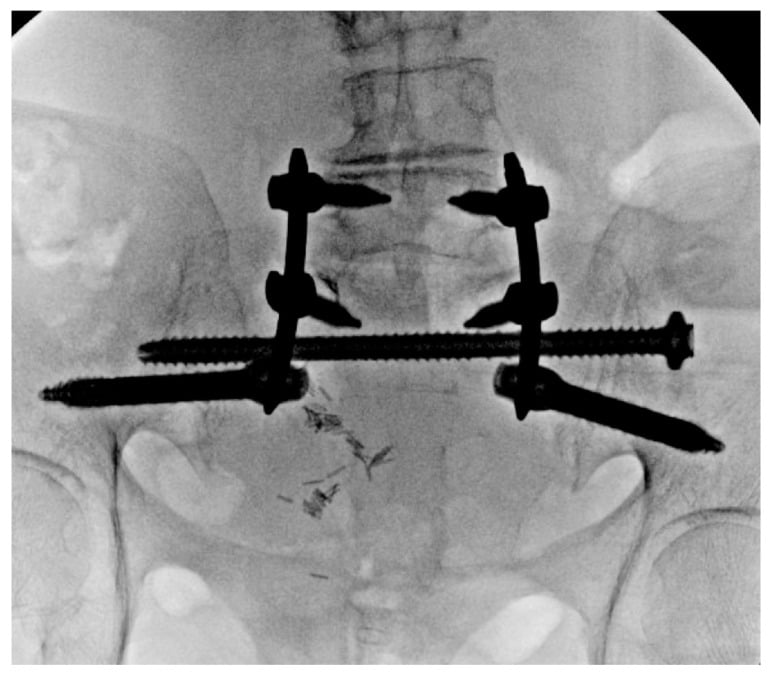
Spinopelvic dissociation. This is a complete disconnection of the spine from the pelvis. Bilateral vertical fractures through the sacrum are joined by a connecting transverse fracture, so the upper sacrum moves with the spine while the lower sacrum and pelvis move independently. On imaging it appears as a discontinuity between spine and pelvis. It carries the highest neurological injury rates, often greater than 60%, and requires lumbopelvic fixation.
U-type and H-type. The shape of the fracture lines names the pattern:
- H-type: bilateral vertical fractures connected by a transverse fracture, forming an H
- U-type: bilateral vertical fractures through the ala connected by a transverse fracture through the body, a complete spinopelvic dissociation
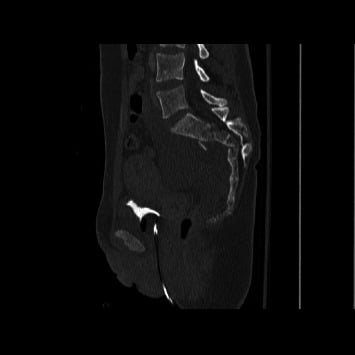
Gibbons classification. Denis predicts risk by fracture location; the Gibbons classification grades the actual sacral nerve deficit and is used to track recovery. It is the score quoted in outcome studies of spinopelvic dissociation.
- Grade 1: no deficit
- Grade 2: sensory deficit only
- Grade 3: lower-limb motor deficit
- Grade 4: bowel or bladder (sphincter) dysfunction
The grade carries prognostic weight: higher grades, especially sphincter involvement, recover least reliably, and the change in Gibbons grade is the standard way to report neurological outcome after decompression and fixation. Pair it with a documented bulbocavernosus reflex and perianal (S2-S4) examination so the baseline deficit is unambiguous.
Clinical Assessment
Context. Sacral fractures occur in the context of major trauma, and assessment follows ATLS principles. The history separates high-energy injuries (motor vehicle and motorcycle accidents, falls from height, pedestrians struck) from low-energy ones: falls in the elderly and osteoporosis-related insufficiency fractures.
Look and feel. Inspect for ecchymosis over the sacrum, where a Morel-Lavallee lesion is possible, gluteal swelling and the posture of the lower limbs. Palpate for sacral and SI joint tenderness, a step-off or crepitus.
Rectal examination. It assesses rectal tone (S2-S4) and rules out an open fracture by feeling for bony fragments.
Document DETAILED neurological examination in ALL sacral fractures. Include motor function (L5-S1), sensory examination, rectal tone, bulbocavernosus reflex, and specifically ask about bowel, bladder, and sexual function. Zone III fractures can cause permanent cauda equina syndrome.
The neurological examination. Examine and record by level:
- Motor: hip extension (L5-S1), knee flexion (S1-2), great toe extension (L5), the key test, ankle plantarflexion (S1-2) and ankle dorsiflexion (L4-5)
- Sensory: dorsum of the foot (L5), lateral foot (S1), posterior thigh (S2) and the perianal saddle area (S2-S4)
- Reflexes: ankle jerk (S1-2), bulbocavernosus reflex and anal wink (S2-S4)
- Questions: urinary retention or incontinence, faecal incontinence, erectile dysfunction in men, vaginal sensation in women
Investigations
Plain radiographs. They miss 30-50% of sacral fractures, so a normal film does not exclude one. Each view has a limited job:
- AP pelvis: often inadequate; look for asymmetry, cortical disruption and disrupted foraminal lines
- Lateral sacrum: better visualisation and an assessment of kyphosis, but still often inadequate
- Ferguson view (AP sacrum): a 30-degree cephalad tilt that shows the foramina better; rarely used in acute trauma
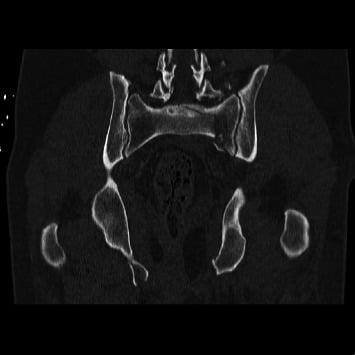
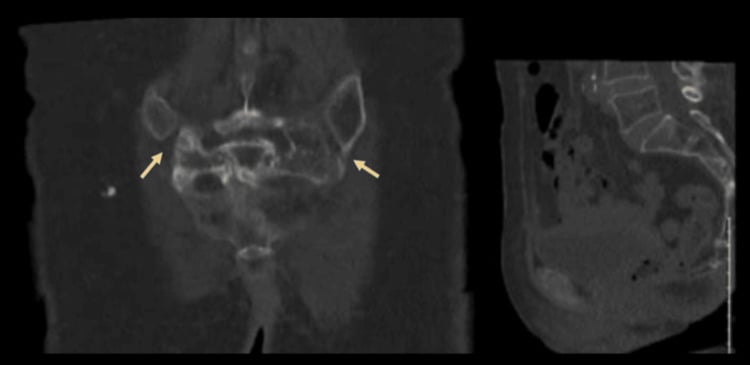
CT is mandatory. It defines the fracture pattern precisely and is the basis of classification and surgical planning. Read it for the Denis zone, a transverse versus longitudinal line, displacement and comminution, foraminal compromise, sacral canal involvement and associated pelvic injuries. 3D reconstruction is excellent for surgical planning, demonstrates complex patterns and is a communication tool.
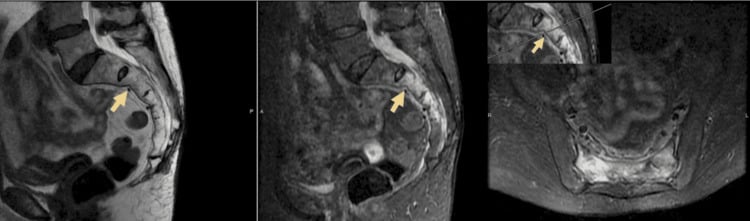
MRI. Indicated for a neurological deficit, suspected cauda equina compression, insufficiency fractures (the oedema pattern) and soft-tissue assessment. It shows nerve root compression, canal stenosis, bone marrow oedema and soft-tissue injury.
Management Algorithm
The decision. Management is organised by Denis zone, and within each zone by displacement, pelvic-ring stability and the neurological findings.
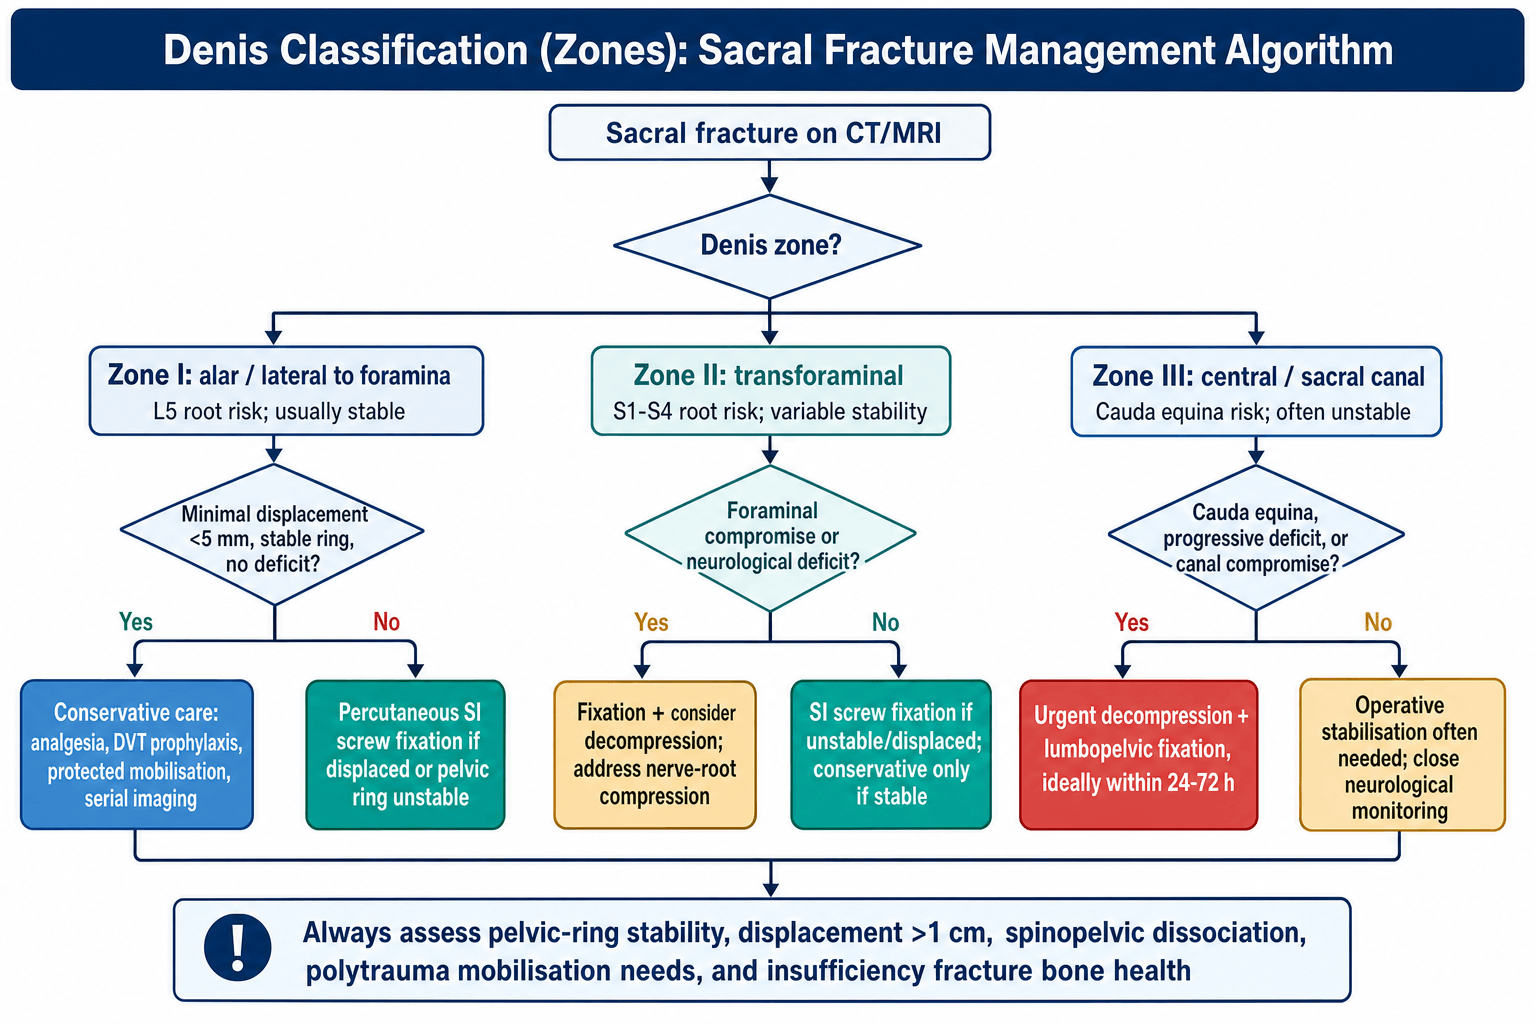
Zone I. Often conservative if minimally displaced, stable and neurologically intact. Percutaneous SI screw fixation if the fracture is displaced or the pelvic ring unstable.
Zone II. SI screws are common. Foraminal compromise or a neurological deficit means fixation, with decompression considered and the nerve-root compression and deficit addressed; without them, SI screw fixation if unstable or displaced, and conservative care only if stable.
Zone III. Urgent decompression if the canal is compromised, and lumbopelvic fixation is often needed. A progressive deficit makes it a surgical emergency; without cauda equina, a progressive deficit or canal compromise, operative stabilisation is still often needed, with close neurological monitoring.
Indications. Conservative treatment suits:
- Zone I with minimal displacement (less than 5mm)
- A stable pelvic ring
- No neurological deficit
- Insufficiency fractures, as first line
Protocol. Bed rest for the first 2-4 weeks, then progressive, pain-guided mobilisation with walking aids and weight-bearing as tolerated, supported by physiotherapy. Analgesia runs from paracetamol and NSAIDs to opioids, with LMWH as DVT prophylaxis. Serial radiographs are taken at 1, 2 and 6 weeks.
Expected course. Most heal at 6-12 weeks. Return to function is gradual, and late complications are watched for.
Surgical Technique
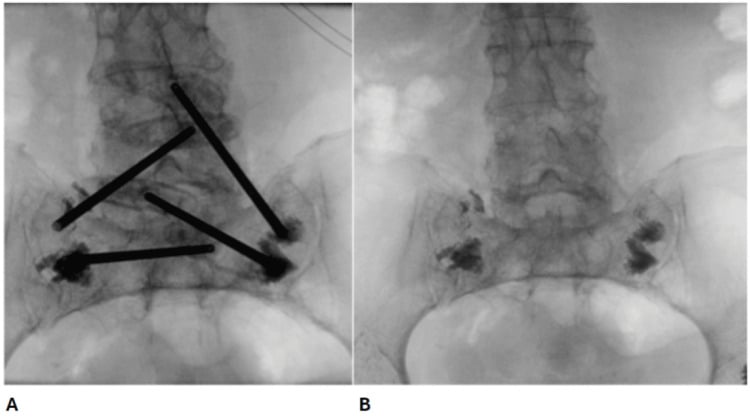
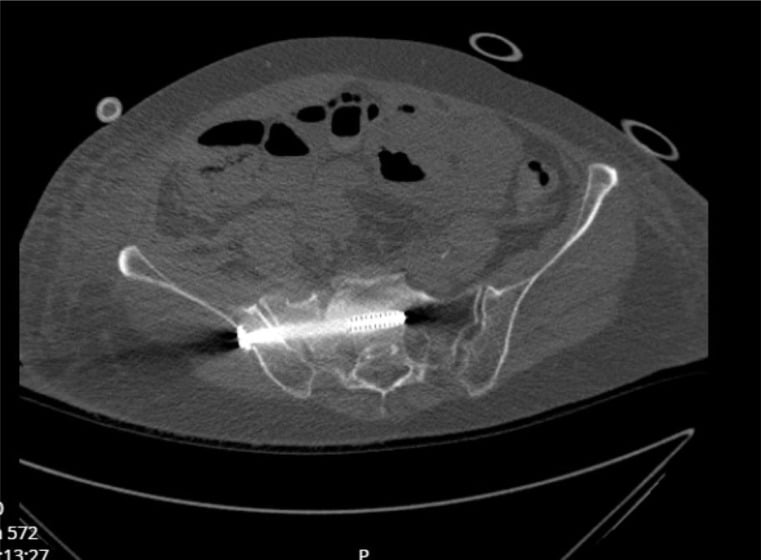
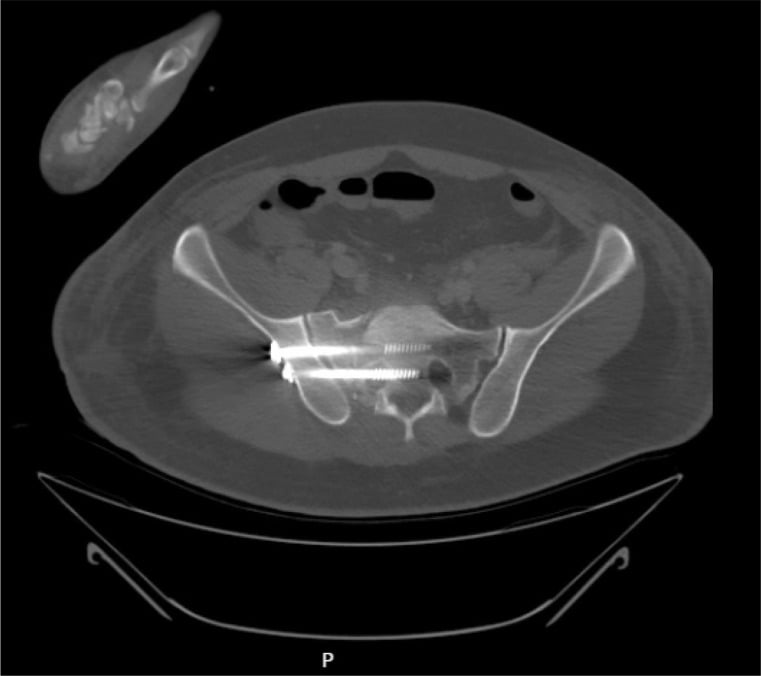
Percutaneous sacroiliac screws. Indicated for Zone I and II fractures, longitudinal sacral fractures, SI joint instability, and stable to moderately unstable patterns. The patient lies supine on a radiolucent table, with lateral decubitus as the alternative. The implants are 7.3mm or 7.0mm cannulated screws over guidewires with cannulated instruments, under fluoroscopy in inlet, outlet and lateral views.
Steps.
- Imaging set-up. A true inlet view (beam angled caudally, roughly 40 degrees) judges anterior-posterior translation; a true outlet view (beam angled cephalad, roughly 40 degrees) shows the foramina and vertical translation. Add a lateral sacral view and mark the S1 body corridor.
- Entry point. Posterior ilium lateral to the SI joint, approximately 1cm superior to the greater sciatic notch, avoiding the L5 nerve anteriorly.
- Guidewire. Advance under fluoroscopy, checking all three views continuously, targeting the S1 body (the safe zone) and avoiding the sacral canal medially and a breach of the anterior cortex.
- Screw. Measure the guidewire depth, insert the cannulated screw over the wire, ensure bicortical purchase and confirm the final position in all views.
- S2 screw (optional). For greater stability, entered more cephalad with a similar technique.
Dangers. The L5 nerve anterior to the ala, the sacral canal medially, the anterior vascular structures, and dysmorphic sacral variants.
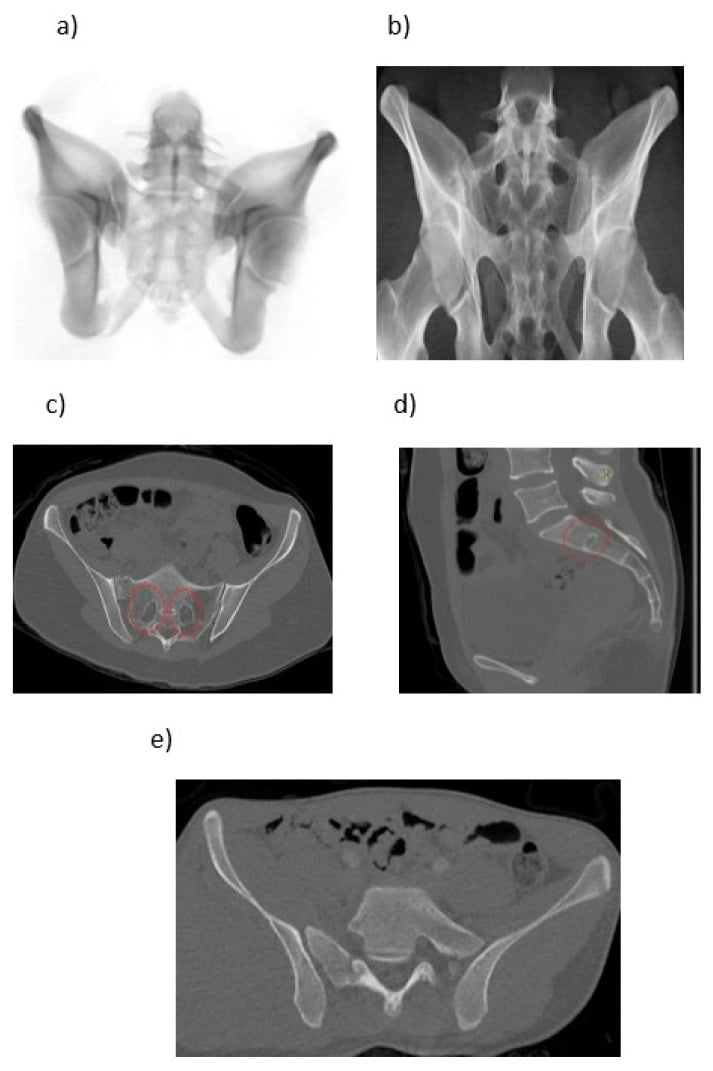
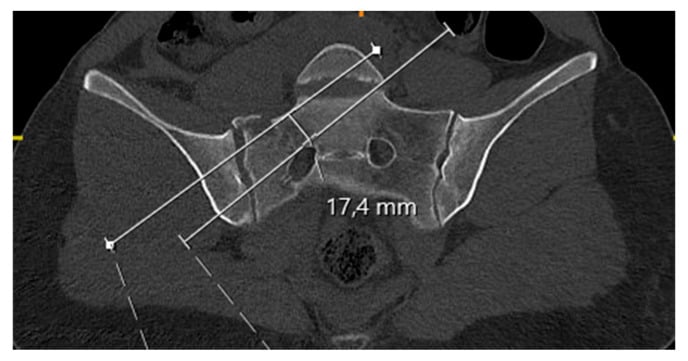
Sacral dysmorphism is a common anatomical variant rather than a pathology, and it decides where a screw can safely go. Recognise it on the outlet view and axial CT: the upper sacral segment is not recessed into the pelvis (the S1 body sits at or in front of a line joining the iliac crests), there are mammillary processes (large, transverse-process-like alar prominences), an acute alar slope, a residual S1-S2 disc, non-circular, tongue-shaped upper sacral foramina, and an irregular tongue-in-groove sacroiliac joint.
What changes. The S1 osseous corridor becomes narrow and obliquely oriented, so a straight transsacral (transiliac-transsacral) screw at S1 may not fit at all. In a CT study of 280 healthy pelves, 11% had no transsacral S1 corridor, and dysmorphism was commoner in women (16% versus 7%, corridors also smaller). Crucially the deficit is compensated at the next level: a transverse S2 corridor was present in 279 of 280 pelves, and S1 and S2 corridor diameters vary inversely. So when S1 will not accept a transsacral implant, S2 usually will; alternatively place an oblique, segment-specific S1 screw that stops short of crossing the midline. Measure both corridors on preoperative CT with coronal and sagittal reformats rather than discovering the problem with a guidewire.
SCREWSCREW - SI Screw Safe Placement
Hook:Use SCREW safely - target S1 body with three fluoroscopic views
Complications
Neurological injury. The most significant complication, at the zone-dependent rates set out under Classification. It may be permanent, especially in Zone III, so document the baseline and monitor closely.
Haemorrhage. Presacral venous plexus injury forms part of the pelvic haemorrhage of ring injuries and is usually managed with the pelvic trauma protocol. Angioembolisation is used if bleeding continues, and surgical exploration is rarely required.
Thromboembolism. Pelvic trauma carries a high DVT risk, and prolonged immobility increases it. Chemical prophylaxis with LMWH is essential, alongside mechanical compression devices and early mobilisation when possible.
Infection. Wound infection occurs in surgical cases and deep infection is rare. The risk is higher with open fractures, and prophylactic antibiotics are given per protocol.
Postoperative Care
Monitoring. Neurological observations, especially if decompression was performed, with motor and sensory function checked four-hourly initially, bowel and bladder function, wound checks and DVT prophylaxis.
Analgesia. Multimodal, with intravenous opioids initially and transition to oral medication, adding neuropathic agents (gabapentin, pregabalin) if needed. Early pain control is essential for neurological recovery and patient comfort.
Outcomes and Prognosis
Union. SI screw fixation achieves union in greater than 90% and lumbopelvic fixation in greater than 85%, with higher rates the more stable the fixation. Union typically occurs within 12-16 weeks with appropriate management.
Without surgery. Most fractures heal with conservative treatment, and insufficiency fractures have good healing rates, but residual pain may persist even with union.
Guidelines, Registries & Global Practice
OrthoVellum is a worldwide resource. The principles below describe the global standard of care and the key regional differences a candidate may be examined on at any board.
Global Epidemiology
Two distinct populations sustain sacral fractures. In Denis's defining series, sacral fractures were identified in approximately 30% of pelvic injuries (236 of 776), and modern series report sacral involvement in a large proportion of pelvic-ring trauma. The condition has a bimodal distribution: high-energy axial-loading or vertical-shear injuries in younger patients (motor-vehicle crashes, falls and jumps from height), and low-energy fragility (insufficiency) fractures in elderly osteoporotic patients, which are increasingly common as populations age.
- What it describes
- Longitudinal zone relative to foramina (I alar, II transforaminal, III central)
- What it changes in management
- Predicts neurological risk; flags Zone III for canal assessment and decompression
- What it describes
- Morphology of transverse upper-sacral fractures (Types 1-3)
- What it changes in management
- Guides reduction of kyphosis and the need for stabilisation
- What it describes
- Bilateral vertical fractures with a transverse component
- What it changes in management
- Identifies spinopelvic dissociation requiring lumbopelvic fixation
- What it describes
- Morphology plus neurological and modifier subtypes
- What it changes in management
- Standardises reporting and severity grading for comparison
Guidance Across Boards and Societies
- Practical position
- CT is mandatory; iliosacral or transsacral screws for posterior ring; triangular osteosynthesis for vertically unstable and dissociation patterns
- Evidence base
- Cadaveric biomechanics (Schildhauer 2003) and large operative series
- Practical position
- Major pelvic trauma to a specialist centre; early CT; documented lumbosacral and perianal neurological exam
- Evidence base
- Consensus standards, expert opinion
- Practical position
- Spinopelvic dissociation treated as a spinal injury: reduction quality and lumbopelvic fixation prioritised
- Evidence base
- Level IV series (Lindahl 2014)
- Practical position
- Conservative care first; bone-health work-up and anti-osteoporosis therapy; augmentation/fixation for refractory pain or instability
- Evidence base
- Level IV-V, technical reports (Tjardes 2008)
Because no high-level randomised evidence exists for most operative decisions, recommendations are largely consensus- and biomechanics-driven and converge internationally: CT for diagnosis, neurological documentation, and stabilisation of unstable or neurologically threatened patterns.
Registry and Series Evidence
Unlike arthroplasty, sacral-fracture fixation is not tracked by dedicated implant registries; the evidence base is observational. Key signals from operative series: triangular osteosynthesis resists cyclic failure far better than an isolated iliosacral screw (Schildhauer 2003), and in spinopelvic dissociation the quality of reduction, not the timing of surgery or use of laminectomy, predicts neurological and functional recovery, with around 42% of patients still having a poor clinical outcome despite fixation (Lindahl 2014).
Global Practice Variation
- High-resource settings: intraoperative 3D imaging or navigation for screw placement, dedicated pelvic-trauma teams, and ready CT/MRI.
- Limited-resource settings: greater reliance on fluoroscopy-guided technique and clinical neurological assessment; conservative management of stable patterns is appropriate worldwide.
- Fragility fractures: management is broadly conservative everywhere, but access to cement augmentation, navigated augmented screws and structured bone-health/falls-prevention services varies markedly.
Exam Focus Points
High-Yield Concepts
DENIS ZONES = NEUROLOGICAL RISK: Zone I = 5-10% (L5), Zone II = 25-30% (S1-S2), Zone III = Up to 60% (cauda equina). The zones move lateral to medial, with risk increasing toward the canal. Zone III involves the sacral canal and can cause bowel/bladder/sexual dysfunction.
Key Numbers
- 30-50%: Miss rate on plain X-ray
- Zone I: 5-10% neuro injury
- Zone II: 25-30% neuro injury
- Zone III: Up to 60% neuro injury
Surgical Decision-Making
- Stable, minimally displaced Zone I
- No neurological deficit
- Insufficiency fractures
- Neurological deficit with canal compromise
- Unstable pelvic ring
- Spinopelvic dissociation
- Zone III with cauda equina
Special Patterns
- U-shaped/H-shaped: Spinopelvic dissociation, lumbopelvic fixation required
- Insufficiency fractures: Conservative first, sacroplasty if refractory
Special Patterns
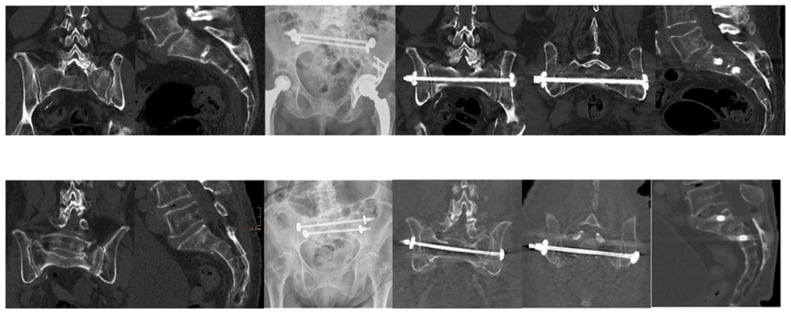
Insufficiency fractures. The insufficiency fracture is a different disease from a high-energy sacral fracture: weakened bone, most commonly osteoporotic, failing under normal physiological load. The patient is elderly, with low back or buttock pain of gradual onset and no significant trauma. Radiographs are often negative initially and usually normal; MRI shows a bone marrow oedema pattern and CT subtle fracture lines.
Management. Usually conservative, with analgesia and osteoporosis treatment, and sacroplasty if the pain is refractory. The fracture is graded by the Rommens-Hofmann FFP system rather than by Denis alone, malignancy must be excluded before the diagnosis is accepted, and the fracture is a sentinel event for untreated bone disease. It is covered in full in sacral insufficiency fracture.
Denis was designed for high-energy trauma; the osteoporotic insufficiency fracture is better classified by the Fragility Fractures of the Pelvis (FFP) classification of Rommens and Hofmann, which grades by instability and directs treatment:
- FFP I: anterior-only injury (isolated rami); conservative
- FFP II: non-displaced posterior injury (sacral ala crush or non-displaced sacral fracture, often with anterior fractures); conservative first, percutaneous fixation if pain or mobilisation fails
- FFP III: displaced unilateral posterior injury; reduction and fixation
- FFP IV: bilateral displaced posterior injury (including bilateral sacral or U-type fragility patterns); fixation, often bilateral or transsacral/lumbopelvic
The practical message: most FFP I-II are managed conservatively with analgesia, early mobilisation and a bone-health work-up, while persistent pain or progressive displacement (II to III to IV) is the trigger for percutaneous (often cement-augmented) iliosacral or transsacral fixation. This is the framework examiners now expect for the elderly sacral insufficiency fracture.
Stress fractures. Seen in athletes, military recruits and long-distance runners, with activity-related pain of gradual onset that improves with rest. Management is activity modification and a bone health assessment, and the fracture typically heals with rest.
Viva Scenarios
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“A 28-year-old motorcyclist is brought in after a high-speed collision. CT shows a Zone II sacral fracture with displacement through the left S1 and S2 foramina. He has 4/5 left ankle plantarflexion and absent left ankle jerk. Describe your assessment and management.”
“Explain the Denis classification for sacral fractures. Why is this classification clinically important?”
“A 75-year-old woman with osteoporosis presents with 6 weeks of low back and buttock pain. X-rays are unremarkable. MRI shows bone marrow edema in the sacrum bilaterally. What is the diagnosis and management?”
MCQ Practice Points
Q: What are the neurological injury rates for each Denis zone? A: Zone I (alar) = 5-10% (L5 nerve), Zone II (transforaminal) = 25-30% (S1-S2 roots), Zone III (central) = up to 60% (cauda equina). Zones move lateral to medial with increasing neurological risk.
Q: What is the miss rate for sacral fractures on plain X-ray? A: 30-50% of sacral fractures are missed on plain radiographs. CT is mandatory for diagnosis and classification. MRI is best for neurological assessment.
Q: What is the safe zone for SI screw placement? A: The S1 body is the target. Use three fluoroscopic views (inlet, outlet, lateral). L5 nerve is at risk anteriorly, sacral canal at risk medially. Watch for dysmorphic sacrum.
Q: What is spinopelvic dissociation and how is it treated? A: Complete disconnection of spine from pelvis seen in U-shaped or H-shaped sacral fractures. Requires lumbopelvic fixation (triangular osteosynthesis) with L4/L5 pedicle screws to bilateral iliac screws.
Q: Why is Zone III a surgical emergency? A: Zone III involves the sacral canal causing cauda equina syndrome with bowel, bladder, and sexual dysfunction (S2-S4). Early decompression (less than 72 hours) improves neurological outcomes.
Denis Classification
- Zone I = lateral to foramina (alar) = L5 nerve = 5-10%
- Zone II = through foramina = S1-S2 roots = 25-30%
- Zone III = medial/central = cauda equina = up to 60%
- Zones move lateral to medial = increasing neuro risk
Key Imaging
- CT MANDATORY - X-rays miss 30-50%
- Ferguson view = 30 degrees cephalad tilt
- MRI for neurological assessment
- Look for U-type or H-type patterns
Surgical Indications
- Neurological deficit with canal compromise
- Spinopelvic dissociation (U-type/H-type)
- Unstable pelvic ring
- Zone III with cauda equina
SI Screw Technique
- Target S1 body (safe zone)
- Three views: inlet, outlet, lateral
- L5 at risk anteriorly
- Canal at risk medially
Complications
- Chronic SI pain: 30-40%
- Neurological deficit (zone-dependent)
- Bowel/bladder/sexual dysfunction (S2-S4)
- Implant removal: 10-15%
Key Numbers
- 45% of pelvic fractures involve sacrum
- 30-50% missed on plain X-ray
- Greater than 90% union with operative fixation
- 72 hours = optimal decompression window
Evidence and Guidelines
Denis Classification: The Defining Study (236 cases)
- Retrospective analysis of 236 sacral fractures (from 776 pelvic injuries) plus 39 cadavers established the three-zone classification. Neurological deficit was present in roughly 6% of Zone I, 28% of Zone II and 57% of Zone III injuries, with the rate rising as the fracture line moves medially towards the central canal. Routine pelvic radiographs were 'almost useless' for these injuries; CT was crucial.
Transverse Sacral Fractures and Delayed Diagnosis
- Literature review of 90 transverse sacral fractures (29 articles, 1975-2006). Roughly 97% had neurological impairment ranging from radiculopathy to bowel/bladder disturbance. Because of associated polytrauma these fractures are frequently missed in the acute stage; CT is required, and surgically treated patients tended to have better stability and neurological outcomes.