Calcaneal Apophysitis | The Commonest Paediatric Heel Pain | Traction Overuse | Self-Limiting
- Traction apophysitis: Repetitive Achilles/plantar fascia pull on the calcaneal apophysis during the growth spurt - it is an overuse injury, not inflammation of a joint
- Clinical diagnosis: A positive mediolateral squeeze test of the posterior calcaneus is usually enough - imaging is NOT required for a typical presentation
- Self-limiting: Settles once the apophysis fuses (around skeletal maturity); no long-term sequelae are described
- Treatment is conservative: Load management, calf stretching, heel cushioning/orthoses - surgery has no role
- Radiographs do not confirm it: Sclerosis and fragmentation of the apophysis are common in asymptomatic children - X-rays are to exclude mimics, not to make the diagnosis
- “The single most common cause of heel pain in the 8-14 year athlete
- “Bilateral in roughly 60% - but always examine both heels and the hip
- “Squeeze test positive, single-leg heel raise reproduces pain
- “Reassure: this resolves with growth and leaves no lasting damage
Overview and Epidemiology
Sever's disease (calcaneal apophysitis) is a traction apophysitis of the posterior calcaneus and the single most common cause of heel pain in active children and early adolescents. James Warren Sever described it in 1912. It is a benign, self-limiting overuse condition of the growing skeleton, not a true "disease" in the pathological sense, and calcaneal apophysitis is the more accurate descriptive term.
Who gets it. The peak age is 8 to 14 years, and girls tend to present a little earlier than boys, mirroring their earlier skeletal maturation. It is bilateral in a high proportion of cases, frequently quoted at around 60%.
The sports. The condition is strongly associated with running and jumping sports: soccer, Australian football, basketball, gymnastics, track, tennis and dance. Higher body mass index and high training volume are recurrent risk associations.
Intrinsic risk factors. Skeletal immaturity, an open apophysis, is the prerequisite. Beyond that, limited ankle dorsiflexion is the most consistently reported intrinsic risk factor, and the others are:
- Gastrocnemius-soleus tightness, which increases traction across the apophysis
- Rapid growth, with bone outpacing the soft-tissue envelope
- Pronated or cavus foot postures, which alter heel loading
- Higher body mass index, which increases impact load
Extrinsic risk factors. These belong to the sport, the training and the kit:
- High-impact sport: running, jumping, kicking, sprinting
- Rapid increases in training volume or intensity
- Hard surfaces and poor footwear, which increase peak heel pressures
- Cleated or flat boots with little heel cushioning, football boots for example
- Multiple concurrent sports, with inadequate recovery between sessions
Pathophysiology and Anatomy
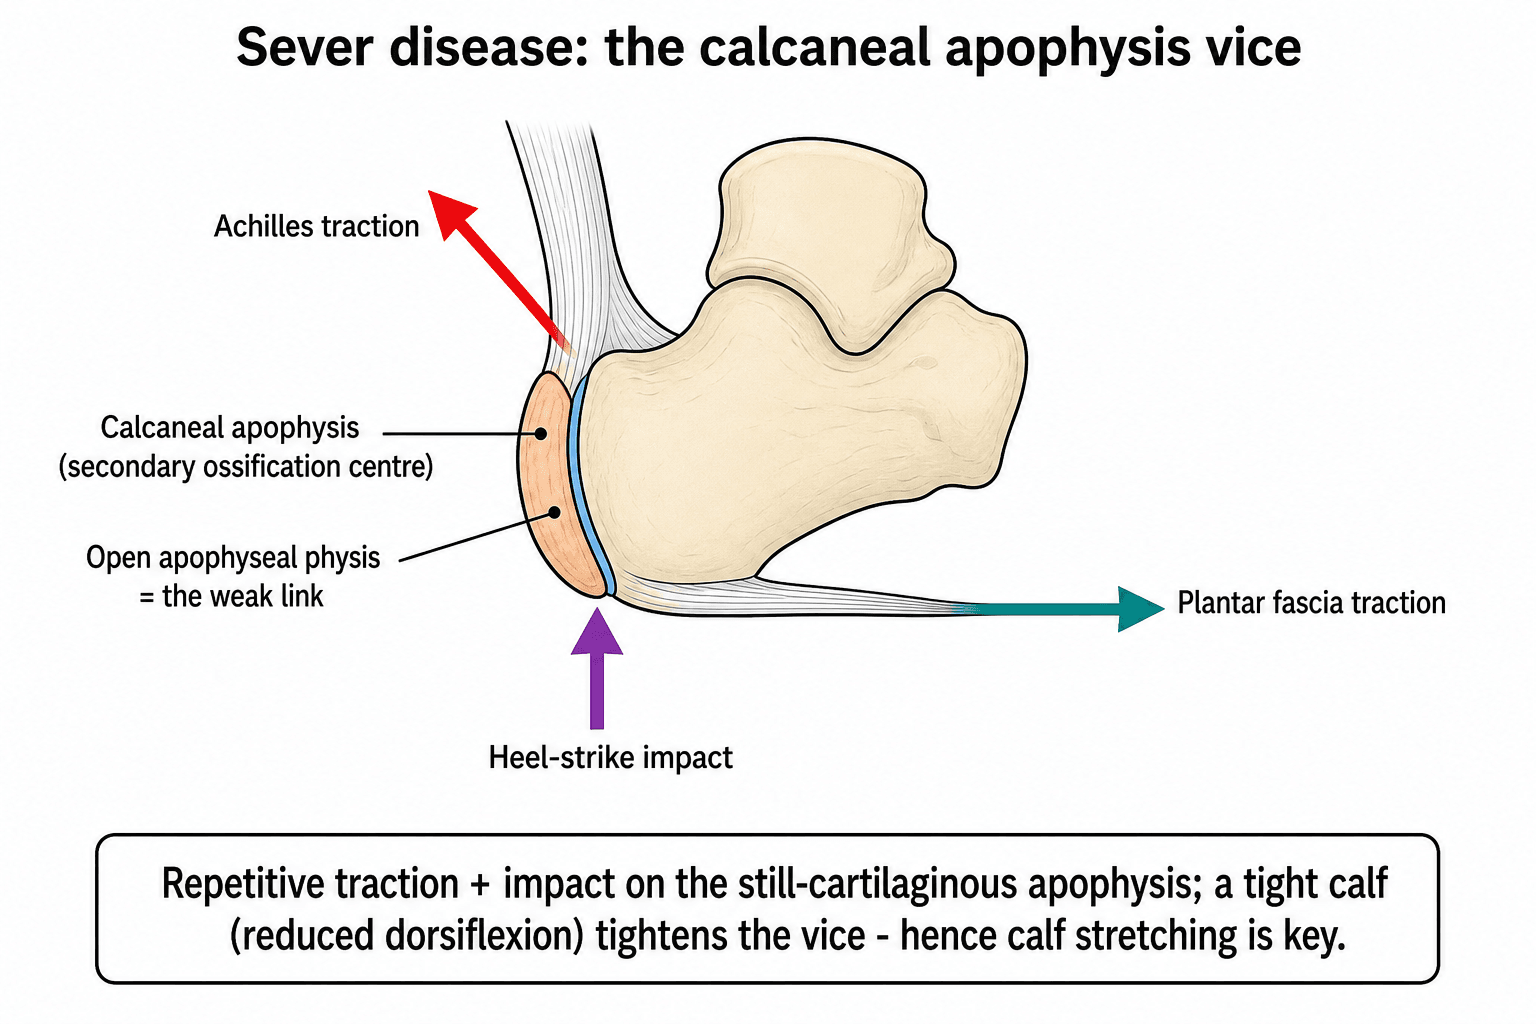
The calcaneal apophysis. The posterior calcaneus develops a secondary ossification centre, the apophysis, which appears in childhood and fuses around the end of skeletal growth. The Achilles tendon inserts onto the posterosuperior apophysis and the plantar fascia originates from the inferior aspect of the calcaneal tuberosity, so the still-cartilaginous growth plate is sandwiched between two strong tractioning structures.
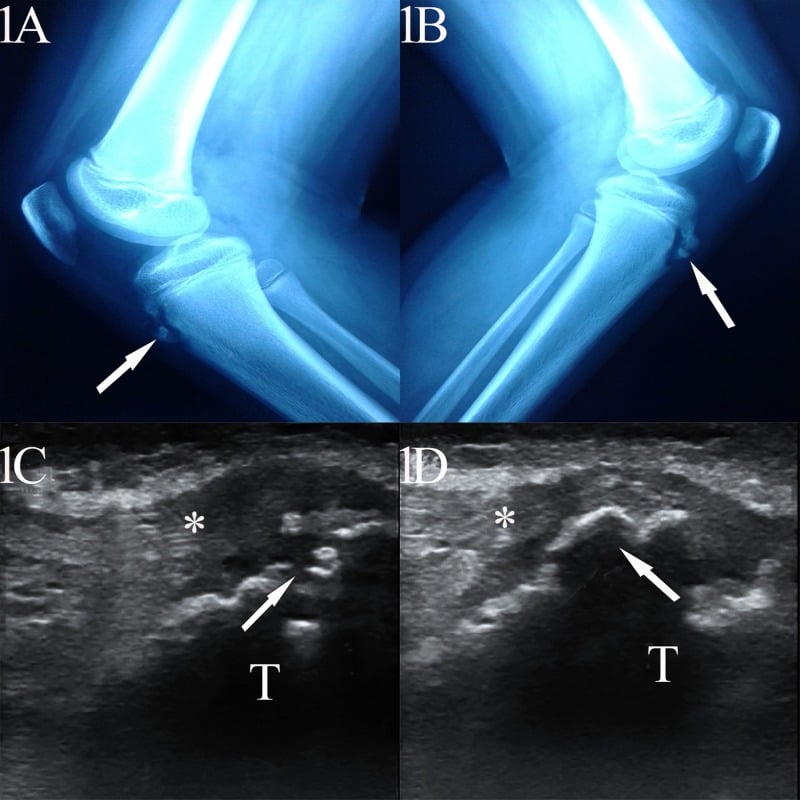
The weak link. The cartilaginous physis between the apophysis and the calcaneal body is the weak link during growth. It is the heel's equivalent of the tibial tubercle in Osgood-Schlatter disease and the inferior patellar pole in Sinding-Larsen-Johansson syndrome.
Why the growth spurt. During the adolescent growth spurt the calcaneus lengthens faster than the gastrocnemius-soleus-Achilles complex can accommodate, so the muscle-tendon unit becomes relatively tight. Repetitive impact loading then produces microtrauma at the vulnerable junction, which is the essence of a traction apophysitis.
The vice. Picture the apophysis held in a vice: the Achilles pulls from above and behind, the plantar fascia pulls from below, and ground-reaction impact hammers it from beneath at heel strike. A tight calf (reduced ankle dorsiflexion) tightens the vice, which is why limited dorsiflexion stands out among the risk factors and why calf stretching is a cornerstone of treatment.
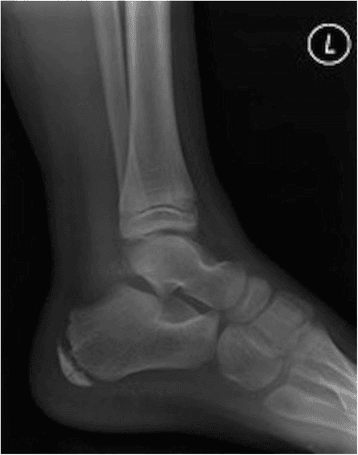
Microtrauma, not inflammation. The condition is a repetitive microtrauma or overuse phenomenon rather than a primary inflammatory or avascular process. Cyclical tensile and compressive loading of the still-cartilaginous apophyseal plate produces microscopic injury and a reparative response. The radiographic sclerosis and fragmentation often seen are largely a feature of normal apophyseal ossification under load, which is why identical appearances occur in pain-free children.
Development. The apophysis passes through four stages, and they set the age window in which the condition is seen.
- Approx. age (years)
- 0-7
- Description
- Posterior calcaneus largely cartilaginous
- Clinical Relevance
- Apophysitis rare at this age - investigate atypical pain
- Approx. age (years)
- 7-9
- Description
- Secondary ossification centre becomes radiographically visible
- Clinical Relevance
- Onset of the vulnerable period
- Approx. age (years)
- 9-12
- Description
- Apophysis ossifying, growth spurt, high sport load
- Clinical Relevance
- Peak incidence of Sever's disease
- Approx. age (years)
- 12-15+
- Description
- Apophysis fuses to the calcaneal body
- Clinical Relevance
- Symptoms resolve as fusion completes
Classification and Severity
There is no universally adopted formal classification. Sever's disease is graded pragmatically by symptom severity and functional impact, which directly guides the intensity of treatment.
- Symptoms
- Heel pain only after sport, settles with rest, no limp
- Impact on Activity
- Completes training and play
- Treatment Emphasis
- Calf stretching, heel cushioning, continue sport
- Symptoms
- Pain during and after sport, mild limp afterwards
- Impact on Activity
- Performance and participation affected
- Treatment Emphasis
- Reduce load, heel raise/orthosis, formal physiotherapy
- Symptoms
- Pain on everyday walking, persistent limp, pain at rest with activity
- Impact on Activity
- Unable to play sport
- Treatment Emphasis
- Relative rest from impact, NSAIDs for flares, consider short immobilisation
What the grade decides. Grading dictates how much load to remove, not whether to operate: you never operate. Milder cases need only activity modification and cushioning. More severe cases need a genuine reduction in impact loading for a period, with a graded return as the squeeze test becomes painless, and every grade shares the same favourable endpoint at skeletal maturity.
Clinical Assessment
History. The story is posterior heel pain that comes with activity and eases with rest, often during a growth spurt. Ask about the sport: its type and frequency, any recent increase in load, the surface and the footwear. The pain is often bilateral, so examine both heels regardless, and a limp after sport is present in moderate-to-severe cases.
Red flags. Any of these makes the heel atypical for Sever's and mandates further investigation rather than reassurance:
- Night pain or rest pain, which raises tumour or infection
- Fever or systemic upset, which raises osteomyelitis or malignancy
- Warmth or raised inflammatory markers, which should make you think of osteomyelitis
- Swelling or a true effusion
- Acute trauma or a sudden onset, which raises a calcaneal fracture or stress fracture
- Focal bony tenderness away from the apophysis, which suggests a tumour or cyst
- Pain unrelated to activity, which should make you reconsider the diagnosis and demands imaging and review
- Hip or thigh symptoms, which mean the hip must be cleared for SCFE and Perthes
Inspection. Watch the gait for an antalgic limp or toe-walking to offload the heel. Compare both heels for swelling, redness or deformity, which are usually absent in Sever's, and note the foot posture (pronation or cavus) and the footwear.
The squeeze test. The mediolateral squeeze, or calcaneal compression, test compresses the posterior calcaneus from both sides at the apophysis; reproduction of the pain is the hallmark finding. The tenderness localises to the posterior calcaneus, not to the Achilles substance or its midportion, and focal bony tenderness away from the apophysis would suggest a mimic.
Range of motion. Ankle dorsiflexion is typically reduced by a tight gastrocnemius-soleus; measure it with the knee extended and flexed. Subtalar and midfoot motion are usually normal, and a true effusion or restricted, painful global ankle motion is atypical and should prompt review.
Provocation and the hip. A single-leg heel raise or hopping reproduces the posterior heel pain. Always examine the hip, because SCFE and Perthes can refer pain distally, and complete the limb assessment with a neurovascular check.
The mediolateral calcaneal squeeze test is the signature clinical sign. Combined with the right age, activity-related posterior heel pain and a tight calf, a positive squeeze test is generally sufficient to diagnose Sever's disease without imaging.
Investigations
Sever's disease is a clinical diagnosis. Investigations are used to exclude mimics, not to confirm apophysitis.
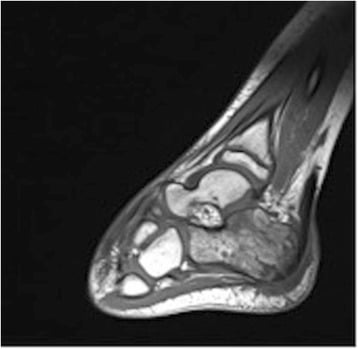
When not to image. In the classic picture (typical age, activity-related posterior heel pain, a positive squeeze test, no red flags and no systemic features) routine radiographs add nothing. They risk overdiagnosis from incidental apophyseal sclerosis, and the unnecessary anxiety that comes with it.
When to image. Imaging earns its place when there is:
- An atypical age or presentation
- Night pain, rest pain or systemic upset
- Focal bony tenderness away from the apophysis
- A history of significant trauma
- Failure to settle with appropriate conservative care
- What It Shows
- Apophyseal sclerosis/fragmentation (non-specific); excludes fracture, cyst, tumour
- Role in Sever's
- Only if red flags or atypical - to exclude mimics
- What It Shows
- Raised in infection or inflammatory arthritis
- Role in Sever's
- If infection or systemic illness suspected
- What It Shows
- The apophysis, adjacent tendon or bursa and other soft tissue; user-dependent
- Role in Sever's
- Selective - atypical or refractory cases
- What It Shows
- Marrow oedema, occult fracture, osteomyelitis, tumour
- Role in Sever's
- Reserved for red flags, persistent symptoms, diagnostic uncertainty or to exclude serious mimics
Reading the radiograph. Radiographs are obtained to exclude other pathology, not to grade Sever's. When one is taken, the lateral calcaneus may show the changes below, and every one of them is non-specific. Treat the child, not the X-ray.
- Appearance
- Increased density of the apophysis
- Caution
- Also seen in asymptomatic children
- Appearance
- Multiple ossification fragments
- Caution
- Normal variant of ossification
- Appearance
- Irregular, dense apophysis
- Caution
- Does not correlate with pain
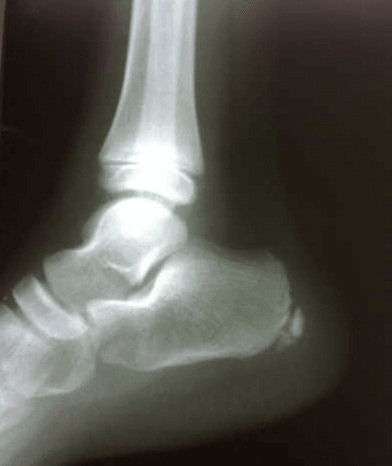
Because apophyseal sclerosis and fragmentation occur in pain-free children, a "positive-looking" X-ray does not prove Sever's and a "normal-looking" apophysis does not exclude it. Use imaging to answer a specific question (is this infection, fracture, cyst or tumour?) rather than to label the apophysitis.
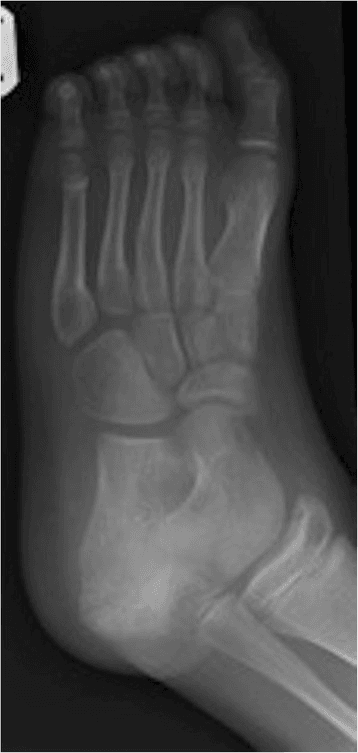
Immature anatomy. The open growth plates and developmental ossification of a child's foot must be recognised before the calcaneal apophysis is interpreted. Normal skeletal immaturity can be mistaken for fragmentation or injury.
Differential Diagnosis
Anchoring. The danger, in the exam and in clinic, is anchoring on "Sever's" and missing a serious mimic: calcaneal osteomyelitis, a unicameral or aneurysmal bone cyst, a calcaneal stress fracture or, in any child with hip or thigh symptoms, SCFE or Perthes referring pain to the knee or leg.
- Distinguishing Features
- 8-14y, activity-related posterior heel pain, positive squeeze test, tight calf
- Key Action
- Clinical diagnosis, conservative management
- Distinguishing Features
- Pain at rest/night, fever, focal tenderness, raised CRP/ESR
- Key Action
- URGENT - bloods, imaging (MRI), treat infection
- Distinguishing Features
- Acute or rapid onset, focal tenderness, positive squeeze but trauma/overload history
- Key Action
- Imaging (MRI/bone scan), offload
- Distinguishing Features
- Localised pain, possible pathological fracture, focal lytic lesion on X-ray
- Key Action
- Imaging and onward referral
- Distinguishing Features
- Pain in tendon substance or insertion, older/adolescent, less typical in young children
- Key Action
- Examine the tendon; manage as soft-tissue pathology
- Distinguishing Features
- Plantar medial heel pain, worse on first steps, uncommon in young children
- Key Action
- Clinical; consider if plantar rather than posterior pain
- Distinguishing Features
- Stiff, painful hindfoot, recurrent sprains, peroneal spasm
- Key Action
- Imaging (CT/MRI) of the hindfoot
- Distinguishing Features
- Hip/thigh/knee symptoms, altered hip rotation
- Key Action
- ALWAYS examine the hip in paediatric leg pain
- Infection - a child with rest/night pain, fever or raised inflammatory markers has osteomyelitis until proven otherwise, not Sever's.
- Referred hip pathology - SCFE and Perthes can present with distal leg pain. Examining the hip in every child with leg or heel pain is both good practice and a recurrent viva and medicolegal point.
In a child, posterior heel pain is far more likely to be apophysitis than tendinopathy. Treating a growing child as if they had adult Achilles tendinopathy (aggressive eccentric loading into pain, for example) misses the point: the goal is to offload the apophysis and manage training load.
Related Traction Apophysitides
Sever's is one of a family of traction apophysitides: overuse injuries of a secondary ossification centre (apophysis) where a strong tendon repetitively pulls on the still-cartilaginous physis during growth. Examiners frequently ask you to name the others. They share the same principles: a peak in the growth spurt, a clinical diagnosis, resolution at apophyseal fusion, and management by load modification, stretching and reassurance rather than surgery.
- Apophysis
- Calcaneal apophysis
- Tractioning structure
- Achilles (and plantar fascia)
- Typical age
- 8-14 y
- Apophysis
- Tibial tubercle
- Tractioning structure
- Patellar tendon (insertion)
- Typical age
- 10-15 y
- Apophysis
- Inferior pole of patella
- Tractioning structure
- Patellar tendon (origin)
- Typical age
- 10-13 y
- Apophysis
- Base of the 5th metatarsal
- Tractioning structure
- Peroneus brevis
- Typical age
- 8-13 y
- Apophysis
- Medial humeral epicondyle
- Tractioning structure
- Flexor-pronator origin / UCL (throwing)
- Typical age
- 9-14 y
Management
Management is entirely conservative, built on load management, calf flexibility, heel offloading and reassurance. There is no role for surgery, and corticosteroid injection is not used.
Education and activity modification. This is first line. Explain the benign, self-limiting natural history to the child and parents, then reduce, do not abolish, impact sport: cut volume and intensity to a pain-tolerable level and substitute lower-impact cross-training, such as cycling or swimming, during flares. Address footwear, choosing a cushioned heel and avoiding hard, flat or worn-out shoes.
Symptom relief. Use it as needed: ice to the heel after activity, simple analgesia or short-course NSAIDs for painful flares only, and relative rest during severe flares.
Heel offloading. A core measure. Heel cups, heel raises or foot orthoses reduce load on the apophysis, and custom foot orthoses may outperform off-the-shelf heel lifts in some trials, though both reduce pain. For barefoot-sport athletes such as gymnasts and dancers, specific heel braces are an alternative.
Physiotherapy. The other core measure. Gastrocnemius-soleus stretching addresses the tight calf and limited dorsiflexion, with eccentric and concentric calf and foot strengthening as tolerated. A graded return-to-sport programme is guided by symptoms and the squeeze test.
Escalation. Genuinely refractory or severe symptoms call for a period of relative rest and, occasionally, a short spell of immobilisation (a walking boot or cast, for example) for a few weeks to break the cycle. If symptoms do not respond, reassess the diagnosis: re-examine, and image to exclude mimics. Extracorporeal shockwave therapy has been described, but the evidence base is weak.
Do not impose complete, prolonged rest. It deconditions the child and is rarely necessary; load modification is the goal.
A clean answer is: "Sever's disease is a clinical diagnosis. I would reassure the family, modify training load rather than stop sport completely, prescribe calf stretching and heel cushioning or orthoses, and use ice and simple analgesia for flares. I would explicitly state there is no role for surgery or injection, and that it resolves with skeletal maturity - while making sure I have excluded infection, fracture and referred hip pathology."
Complications and Prognosis
Natural history. Symptoms wax and wane with activity, and may persist or recur for months to a couple of years while the child is still growing and active. The condition resolves spontaneously once the calcaneal apophysis fuses, around skeletal maturity, and the prognosis is excellent: no long-term structural sequelae, deformity, growth disturbance or arthritis are described. The clinician's role is accurate diagnosis, exclusion of mimics, symptom control and reassurance.
What goes wrong. The main "complication" is missed time from sport and parental anxiety, both mitigated by reassurance. The only serious risk is a missed mimic: infection, fracture, tumour or referred hip pathology. The remaining pitfalls are iatrogenic:
- Deconditioning from unnecessary prolonged rest
- Overtreatment or overinvestigation of a benign condition
- Failure to reassess when symptoms do not follow the expected course
The most therapeutic intervention is often accurate reassurance: this is a common, benign overuse condition of the growing heel that does not cause lasting damage and reliably resolves with growth, provided serious mimics have been excluded.
Guidelines, Registries & Global Practice
Global epidemiology. Calcaneal apophysitis is a worldwide condition of the skeletally immature, running and jumping athlete and is consistently reported as the most common cause of paediatric heel pain. A systematic review of risk factors (1265 children, mean age 10.7 years) identified limited ankle dorsiflexion, increased plantar pressures, foot malalignment and higher body mass index as recurrent associations (DOI). There is no dedicated registry; surveillance comes from sports-medicine cohorts and treatment trials rather than arthroplasty-style national registries.
Guideline landscape. No major society publishes a Sever's-specific guideline; recommendations are drawn from paediatric overuse-injury and apophysitis guidance, which is strikingly consistent across systems - the diagnosis is clinical and management is conservative.
- Position
- Activity modification, calf stretching, heel cushioning/orthoses; reassurance about the self-limiting course
- Imaging Stance
- Clinical diagnosis; radiograph only for atypical features or to exclude other pathology
- Evidence Basis
- Expert consensus, supported by small RCTs
- Position
- Primary-care conservative management, load modification, physiotherapy; referral reserved for red flags
- Imaging Stance
- Imaging not routine; reserved for diagnostic uncertainty or trauma
- Evidence Basis
- CKS-type narrative guidance, consensus-based
- Position
- Conservative care, family education; avoid overinvestigation of incidental apophyseal change
- Imaging Stance
- Selective imaging only
- Evidence Basis
- Consensus / practice standards
- Position
- Load management, calf flexibility and graded return; flag prolonged or atypical courses
- Imaging Stance
- Ultrasound or MRI selectively for atypical or refractory cases
- Evidence Basis
- Cohort and RCT evidence (Level 2-3)
- Position
- Training-load monitoring during growth spurts; gradual return-to-sport progression
- Imaging Stance
- Clinical diagnosis emphasised
- Evidence Basis
- Consensus / sports guidance
The main international variation is in imaging threshold and use of orthoses, not in the core approach: management is uniformly conservative worldwide. Higher-resource and elite-sport settings use ultrasound/MRI more liberally and prescribe custom orthoses, while primary-care systems keep the diagnosis clinical and favour simple heel cushioning. Randomised evidence suggests no in-shoe device is clearly superior in the medium term (DOI), so cost and preference reasonably guide device choice.
Medicolegal Considerations:
Key documentation points:
- History of gradual, activity-related posterior heel pain in a child of typical age
- Documentation of a positive squeeze test and reduced ankle dorsiflexion
- Explicit screening for red flags (night pain, fever, systemic upset, trauma)
- Hip examination performed to exclude referred SCFE/Perthes
- Discussion of the benign, self-limiting natural history and a plan for review if symptoms do not follow the expected course
Don't Miss the Mimics: Failing to recognise calcaneal osteomyelitis or referred hip pathology in a child labelled with "Sever's" is a recognised source of harm and litigation. Document the red-flag screen and hip examination in every case.
Prevention Strategies:
- Training-load management during growth spurts (progress volume before intensity)
- Calf flexibility work and attention to footwear with adequate heel cushioning
- Awareness among coaches and parents that activity-related heel pain in this age group is usually benign but should be assessed
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“An 11-year-old boy who plays a lot of football presents with a 6-week history of pain at the back of both heels. The pain is worse after matches and he sometimes limps off the pitch. He is otherwise well.”
“A 9-year-old presents with heel pain. This child also wakes at night with pain, feels generally unwell, and on examination has a low-grade fever, warmth over the heel and focal bony tenderness. An X-ray shows a sclerotic, fragmented calcaneal apophysis.”
“A 13-year-old competitive gymnast has had calcaneal apophysitis confirmed clinically. Despite calf stretching and activity advice over 8 weeks she still has limiting bilateral heel pain and is missing competitions. The family is anxious and asking whether she needs surgery.”
Key Anatomy
- Calcaneal apophysis = secondary ossification centre at posterior heel
- Achilles inserts above, plantar fascia originates below - the 'sandwich'
- Cartilaginous physis is the weak link during growth
- Apophysis fuses around skeletal maturity
Diagnosis
- Clinical diagnosis - imaging NOT required if typical
- Mediolateral calcaneal squeeze test positive
- Age 8-14 years, activity-related posterior heel pain
- Reduced ankle dorsiflexion (tight calf); often bilateral
Treatment
- Load MODIFICATION, not complete rest
- Calf (gastrocnemius-soleus) stretching
- Heel cushioning / heel raise / foot orthoses
- Ice and short-course NSAIDs for flares
- No surgery, no injection - ever
Imaging Indications
- Night or rest pain (tumour, infection)
- Fever or systemic upset (osteomyelitis)
- Significant trauma (fracture)
- Atypical age or failure of conservative care
Red Flags (NOT Sever's)
- Night/rest pain, fever = infection or tumour
- Focal bony tenderness away from apophysis
- Acute trauma = fracture / stress fracture
- Hip or thigh symptoms = SCFE, Perthes
Prognosis
- Excellent - self-limiting with skeletal maturity
- No long-term deformity or arthritis
- Symptoms may fluctuate for months while still growing
- Reassurance is a key part of treatment
Evidence Base
Sever's disease has a modest but growing evidence base, dominated by conservative-treatment trials and risk-factor studies. Because the underlying mechanism is shared with other paediatric apophysitides, some principles are extrapolated from that broader literature and labelled where relevant.
Read every trial below against one fact stated at the top of this page: the condition is self-limiting and settles when the apophysis fuses. Not one of these randomised trials contains a NO-TREATMENT arm — they compare a device against another device, so they can show which option relieves symptoms faster but cannot show that any of them changes the course. This is not a quibble: it is the most likely explanation for the central result below, that James found every group equal by 6 and 12 months. Children in all arms got better, which is exactly what a self-limiting apophysitis in a growing child does anyway. So the bedside conversation is not "which treatment works best" but "what makes the next few months comfortable while growth does the curing" — an argument for starting cheap and simple, and against escalating to expensive custom devices on a belief no trial has tested.
Footwear and Foot Orthoses: 12-Month Factorial RCT
- Factorial 2x2 randomised trial in 124 children aged 8-14 with calcaneal apophysitis
- Compared heel raises versus prefabricated orthoses, with or without footwear replacement
- A relative advantage of heel raises over prefabricated orthoses was seen only at the 2-month point in the physical domain
- By 6 and 12 months there was no advantage of any one treatment over another - all groups improved
Custom Foot Orthoses vs Heel-Lifts: CONSORT-Compliant RCT (n=208)
- Randomised trial of 208 children aged 9-12 with calcaneal apophysitis over 12 weeks
- Custom-made polypropylene foot orthoses versus off-the-shelf heel-lifts
- Both groups improved in pain (VAS) and pressure-pain threshold (algometry)
- Custom orthoses produced significantly greater improvement (VAS reduction approximately 69% vs heel-lifts)
Conservative Treatment: Systematic Review of RCTs
- Systematic review of 8 randomised controlled trials of conservative treatment
- Interventions included insoles, therapeutic exercises, kinesio taping and foot orthoses
- Good overall methodological quality (mean PEDro score 6.75)
- Conservative treatment was an effective option for relieving Sever's disease symptoms
Risk and Associated Factors: Systematic Review
- Systematic review of 11 observational studies (1265 participants, mean age 10.7 years)
- Limited ankle dorsiflexion was the most frequently identified intrinsic risk factor
- Increased plantar pressures and foot malalignment were also associated
- Higher body mass index, age, sex, sport participation and other osteochondroses were implicated