Progressive Degeneration | Posterior Wear | Cuff Status Critical
- Posterior glenoid wear (retroversion) is the hallmark deformity
- Axillary lateral X-ray is mandatory for diagnosis
- Cuff status determines surgical option (Anatomic vs Reverse)
- Non-operative management is first line but has limits
- Inflammatory arthritis erodes centrally (medialisation)
- “Loss of external rotation is the earliest and most sensitive sign of OA
- “Function often preserved longer than in hip/knee OA
- “'Goat's Beard' osteophyte endangers axillary nerve
- “Young patients have high failure rates with arthroplasty
Overview and Epidemiology
Glenohumeral osteoarthritis (GHOA) is a chronic degenerative condition: progressive loss of articular cartilage with subchondral sclerosis, cyst formation and osteophytes. It is the end stage of joint failure and brings significant pain, stiffness and functional limitation. It is often called "wear and tear", but the pathophysiology involves a complex interplay of mechanical, biochemical and genetic factors.
Who. Symptomatic disease affects roughly 3-5% of people over 60, and radiographic changes are far more common, in up to ~30% of the elderly. Men and women are affected in broadly similar numbers (approximately 1:1), in contrast to the female predominance of hand and knee OA. A substantial minority develop clinically significant bilateral disease over time.
The trend. Shoulder arthroplasty is among the fastest-growing joint replacements globally, driven largely by the expansion of reverse TSA indications. An increasing younger cohort aged 50-60 presents with end-stage disease ("the young OA patient"), posing a biological and mechanical dilemma for how long a reconstruction must last.
Aetiology. Primary, idiopathic OA is the most common form and has a strong genetic component. The secondary causes are:
- Post-traumatic - intra-articular fractures (head-split, impression fractures) or damage from a previous dislocation; tuberosity malunion can also alter the mechanics and lead to eccentric wear
- Capsulorrhaphy arthropathy - an iatrogenic OA after historical instability operations (Putti-Platt, Magnuson-Stack) that over-tightened the anterior structures, forcing the head posteriorly and grinding out the joint like a mortar and pestle
- Metabolic - haemochromatosis ("iron fist, iron shoulder"), gout, CPPD (chondrocalcinosis)
- Osteonecrosis - humeral head collapse with secondary glenoid wear, common after prolonged steroid use or alcohol abuse
- Post-infectious - chondrolysis after previous septic arthritis; a prior Staphylococcus aureus infection is a red flag
- Inflammatory - rheumatoid arthritis, psoriatic arthritis, ankylosing spondylitis
- Neuropathic - Charcot arthropathy (syringomyelia, diabetes), with massive destruction and debris
Rheumatoid arthritis wears the joint differently. Pannus produces concentric central erosion ("acetabularisation") rather than posterior wear. The bone is osteopenic and the cuff is often thin or torn.
Molecular pathogenesis. At a cellular level OA is an active metabolic disorder rather than passive wear alone. IL-1 and TNF-alpha drive the catabolic enzymes (MMPs) that degrade the type II collagen matrix, and chondrocytes undergo senescence and apoptosis. The subchondral bone stiffens (sclerosis) and transfers more load to the cartilage, accelerating wear in a vicious cycle, while TGF-beta and BMPs drive osteophyte formation in an attempt to stabilise the joint surface area.
How it progresses. The degeneration follows a predictable pattern, often described in four stages:
- Cartilage fibrillation. Initial softening and focal loss of cartilage, usually starting at the centre of the glenoid. This asymptomatic phase can last years.
- Posterior erosion. As the anterior capsule tightens and the posterior capsule stretches, the humeral head subluxes posteriorly and the eccentric load wears the posterior glenoid rim. This creates the classic Walch B2 (biconcave) deformity: the head carves a second articular surface (the neoglenoid) while the anterior native surface (the paleoglenoid) remains relatively preserved.
- Osteophyte formation. Large osteophytes form in the inferior recess of the joint. The inferior humeral osteophyte, the "goat's beard", increases the articular surface area to distribute load but mechanically blocks adduction and rotation; it can become massive, obliterating the axillary pouch and wrapping around the surgical neck.
- Contracture and stiffness. Subscapularis and the anterior capsule become fibrotic and contracted, producing the characteristic fixed internal-rotation contracture (loss of external rotation), while the posterior capsule becomes attenuated and lax. The patient loses the ability to cock the arm to throw or to reach behind the head.
Anatomy and Biomechanics
Normal anatomy. The glenoid is naturally retroverted about 2-8 degrees relative to the scapular body, while the scapula itself is anteverted on the chest wall. The radius of curvature of the glenoid is larger than that of the humeral head, and this mismatch allows translation. In OA the mismatch is lost as the joint becomes congruent and stiff.
Pathoanatomy. Glenoid retroversion is the hallmark: the posterior lip wears down, creating a slope that pushes the head out the back. The humeral head flattens and enlarges (hypertrophic OA), and the long head of biceps is often frayed or subluxed or dislocated medially.
The axillary nerve. It runs along the inferior border of subscapularis and lies immediately deep to the inferior osteophyte and capsule. The goat's beard therefore endangers it, and inferior capsular release is the danger zone, open or arthroscopic.
Classification Systems
The Walch classification describes glenoid morphology on CT and helps plan anatomic TSA.
- Description
- Centered Head
- Features
- A1: Minor central erosion A2: Major central erosion (Protrusio)
- Description
- Posterior Subluxation
- Features
- B1: Posterior narrowing/sclerosis B2: Biconcave (Paleo/Neo glenoid)
- Description
- Dysplastic
- Features
- Native retroversion over 25 degrees (Hypoplasia of neck)
The B2 glenoid is the difficult one. Its exposure and fixation are technically challenging, and the retroversion has to be dealt with by eccentric reaming or an augmented glenoid.
Clinical Assessment
History. The pain is deep and posterior, a "toothache" that is worse at night, and the course is chronic and progressive over years. Stiffness shows as difficulty reaching the back pocket (internal rotation) or washing the hair (external rotation and abduction). Function is often surprisingly well preserved until the late stages compared with hip or knee OA. Check for bilateral disease or other joint involvement, looking for rheumatoid arthritis or haemochromatosis.
Examination. Inspection shows supraspinatus and infraspinatus wasting from disuse and an anterior prominence (head subluxation). The posterior joint line is tender and there is coarse crepitus throughout the range. Loss of external rotation is the earliest and the most sensitive sign.
What else it could be. Cuff integrity must be established, because it separates primary OA (intact cuff) from cuff tear arthropathy (torn cuff). Frozen shoulder restricts motion globally, without arthritic changes. Assess axillary nerve function, and screen the cervical spine, which is mandatory because C5/6 radiculopathy is a mimic.
- X-ray Features
- Osteophytes, Sclerosis, Posterior Wear
- Cuff Status
- Intact
- Key Pearl
- Stiff, grinding, posterior pain
- X-ray Features
- Femoralization of acromion, High riding head
- Cuff Status
- Torn (Massive)
- Key Pearl
- Weakness, Pseudoparalysis
- X-ray Features
- Central erosion (Medialization), Osteopenia
- Cuff Status
- Variable (often thinning)
- Key Pearl
- Bilateral, systemic symptoms
- X-ray Features
- Crescent sign, Collapse, Glenoid spared
- Cuff Status
- Intact
- Key Pearl
- Risk factors: Steroids, Alcohol
Always consider infection in patients with rapid progression of symptoms, rest pain out of proportion, or systemic symptoms. Gout and CPPD can also present acutely ("Pseudogout"). Aspiration is required if effusion + warmth are present.
Investigations
Radiographs are the cornerstone of diagnosis, and one view in particular carries the case:
- True AP (Grashey) - shows the true joint space, obliterated in OA ("bone on bone"), with subchondral cysts and sclerosis
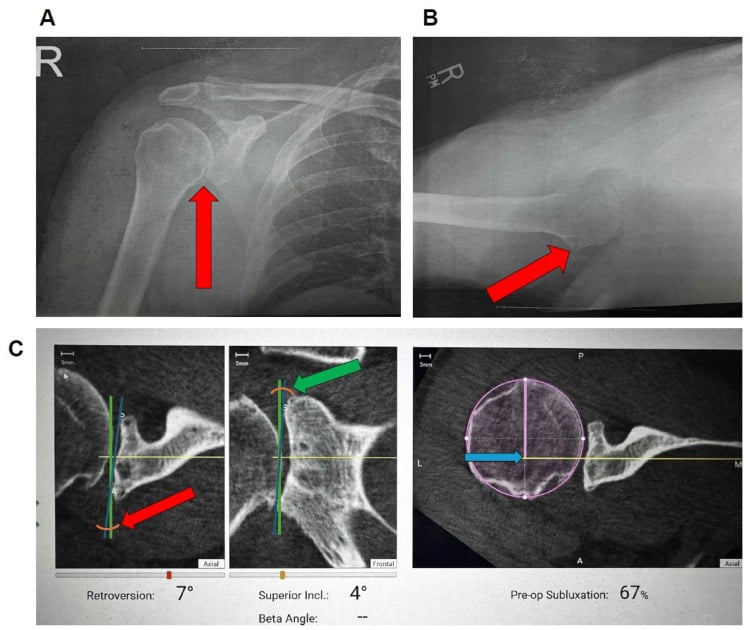
- Axillary lateral - the most important view: it shows posterior subluxation (the head sits behind the glenoid centre line), allows retroversion to be estimated, and shows biconcavity, the tell-tale sign of a B2 glenoid
- Outlet - acromial shape (types 1-3) and the acromiohumeral distance, where under 7mm suggests a cuff tear
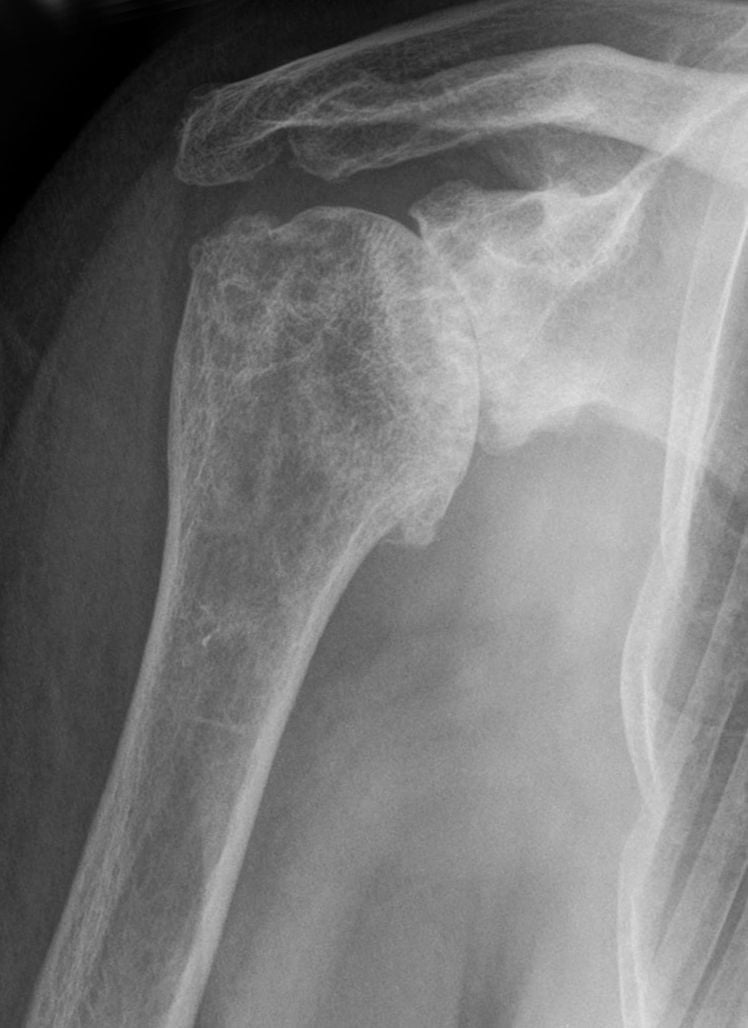
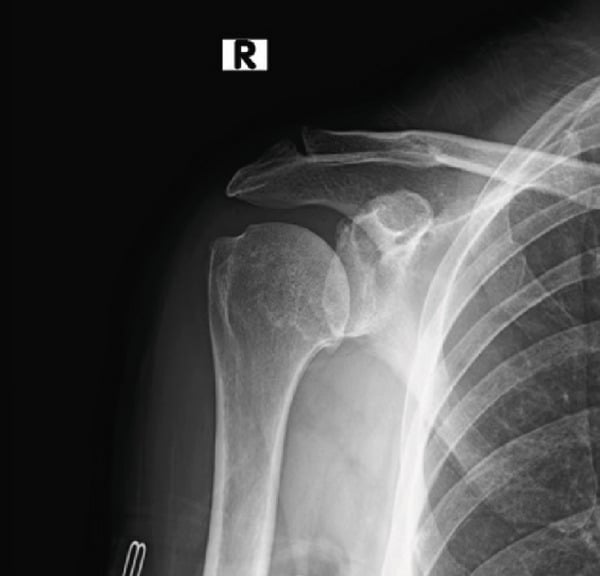
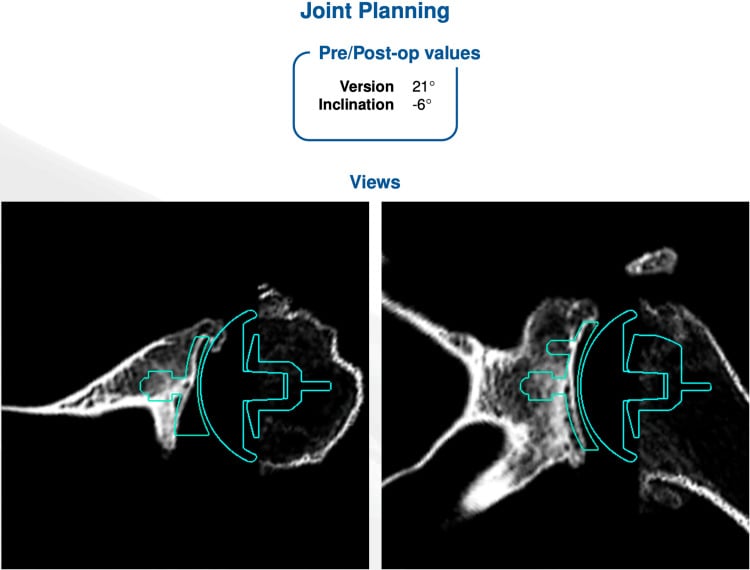
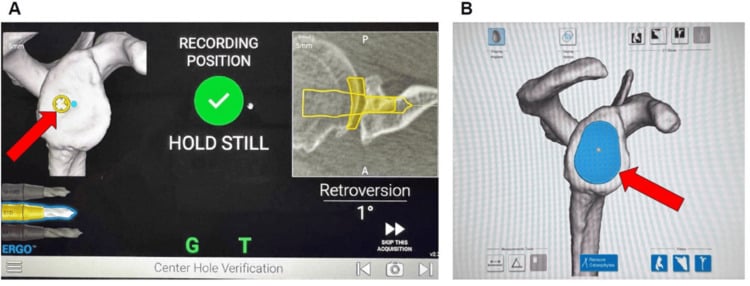
CT is mandatory for all arthroplasty planning in modern practice. It defines the Walch type (A, B or C), and 3D reconstructions are used to generate patient-specific instrumentation (PSI) guides. It measures:
- Glenoid version - at the mid-glenoid level (the Friedman method, below)
- Glenoid inclination - superior or inferior tilt
- Bone stock - the depth of the glenoid vault, which usually needs to be over 25mm to support peg fixation
MRI assesses the cuff, and is indicated when cuff strength is equivocal, there is a history of tear, or the head rides high on the radiograph. Rotator cuff integrity is the binary switch for surgical decision-making. Goutallier grade 3 or 4 fatty infiltration (fat greater than muscle) indicates an irreparable cuff, and anatomic TSA is then contraindicated because the concavity-compression mechanism is lost.
Measuring Glenoid Version: Friedman vs Corrected Methods
How version is measured, and why the number can mislead, is a favourite examiner probe in B2 planning.
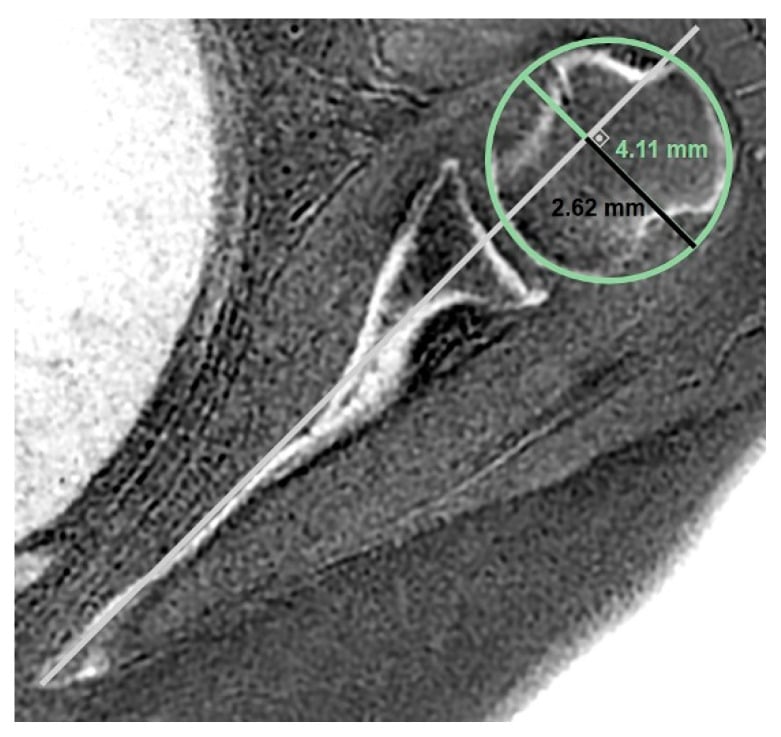
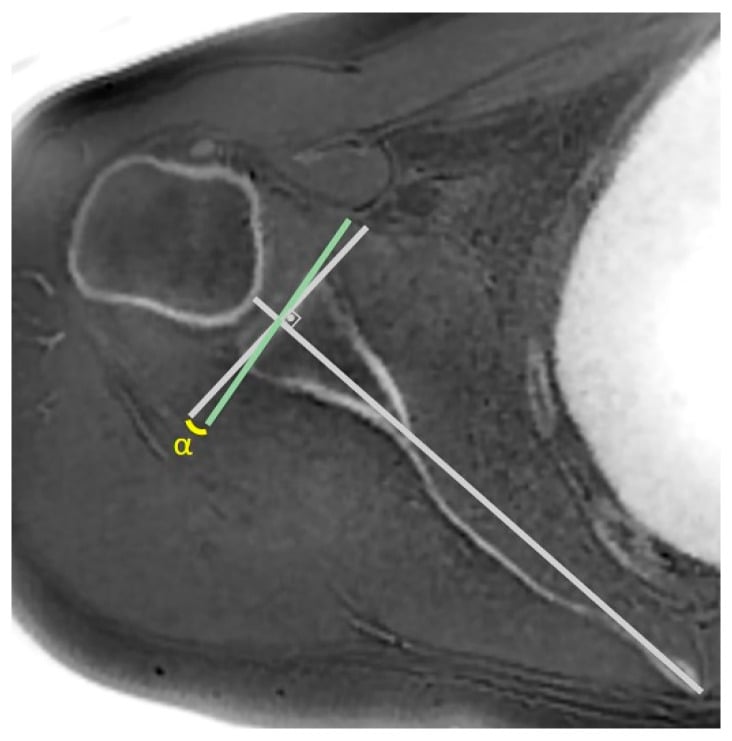
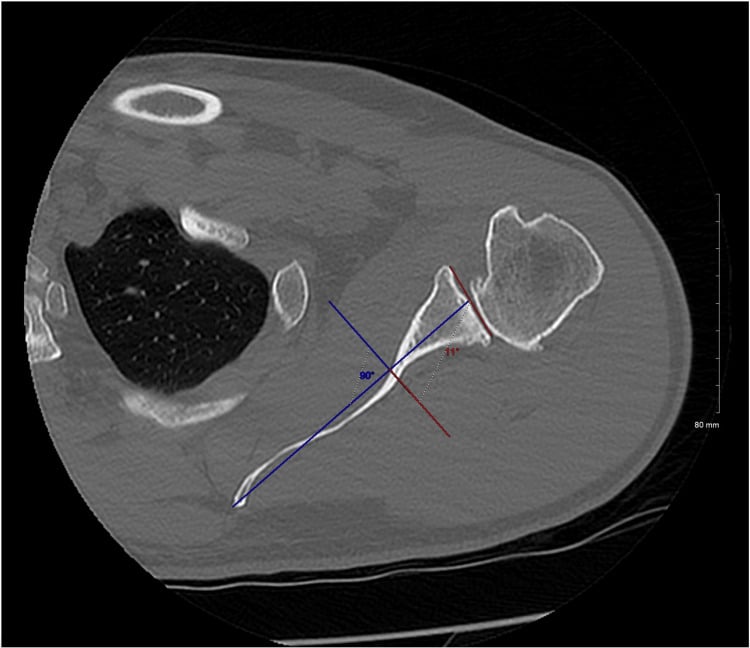
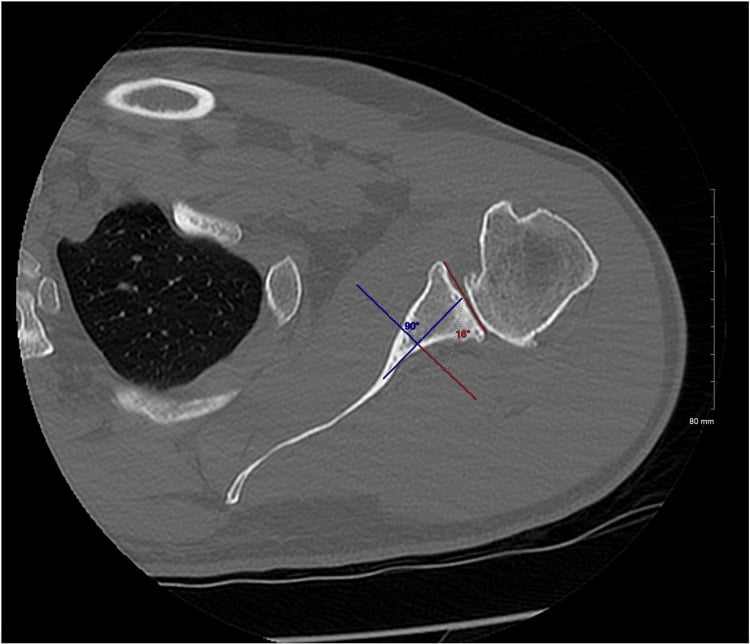
The Friedman method. On an axial CT slice at the mid-glenoid, a reference line is drawn from the tip of the medial scapular border to the centre of the glenoid face. Version is the angle between the glenoid articular line and the perpendicular to that scapular axis, and posterior tilt is reported as retroversion. It is simple and reproducible on a single slice.
Two dimensions overestimate. A single axial slice is only truly accurate if the scan plane matches the scapular plane, and patient positioning tilts the scapula in the gantry. Raw 2D axial measurements therefore tend to overestimate retroversion relative to scapular-plane-corrected 3D measurements. Correcting to the true scapular plane, by 3D reconstruction or reformatting, gives smaller and more reliable version values and underpins patient-specific planning.
Which surface you measure to. In a biconcave B2 glenoid the surface is split into the native anterior paleoglenoid and the worn posterior neoglenoid. Measuring to the paleoglenoid rim, as the classic Friedman line tends to, captures the premorbid version; measuring to the intermediate or neoglenoid surface captures the functional version the humeral head actually articulates against. The "corrected" or intermediate-glenoid technique references this functional surface, which is what determines how much retroversion must be neutralised.
In practice. Modern practice combines the modified Walch type with 3D, scapular-plane-corrected version and inclination rather than a single 2D number. That combination decides whether eccentric reaming alone will suffice or whether an augment or a reverse TSA is needed.
Management Algorithm
Non-operative first. Conservative management is first line for all patients, particularly those with mild symptoms or significant comorbidities.
- Education - activity modification, avoiding heavy overhead lifting and push-ups
- Physiotherapy - gentle stretching (pulleys, stick exercises) to prevent capsular contracture, and strengthening of the periscapular stabilisers (trapezius, rhomboids, serratus) and deltoid; avoid aggressive internal-rotation stretching if it is painful
- Analgesia - paracetamol (Osteo), NSAIDs (naproxen, celecoxib) during flares, topical diclofenac gel
Injections. Corticosteroid is a potent anti-inflammatory and provides 3-6 months of relief, but multiple injections can degrade soft tissue and bone quality. Do not inject within 3 months before elective arthroplasty: meta-analysis shows injection within 3 months raises periprosthetic joint infection risk, with no excess risk beyond 3 months (Akhtar et al, Cureus 2024).
Hyaluronic acid and PRP. Hyaluronic acid (viscosupplementation) has a lubricant effect, is expensive, and its evidence is mixed (AAOS guidelines: inconclusive). PRP delivers growth factors, but the current Level 1 evidence is weak or conflicting and it is not considered standard of care. Decisions about injections should be shared with the patient, balancing short-term relief against long-term risks.
- Indication
- Mechanical symptoms, Young
- Pros
- Low risk
- Cons
- No long term benefit
- Indication
- Young (under 50), Good glenoid
- Pros
- No poly wear
- Cons
- Glenoid erosion pain
- Indication
- Classic OA, Intact Cuff
- Pros
- Best function
- Cons
- Glenoid loosening
- Indication
- Cuff Tear OA, Elderly (over 70)
- Pros
- Dependable
- Cons
- Limited rotation
Joint-Preserving Surgery: Comprehensive Arthroscopic Management (CAM)
The young, high-demand patient with end-stage glenohumeral OA is the hardest reconstructive problem, and comprehensive arthroscopic management (CAM) is the joint-preserving option in that setting. It is a single-sitting arthroscopic bundle that addresses every pain generator in the arthritic shoulder without burning arthroplasty bridges, and its individual steps are what examiners probe:
- Chondroplasty and debridement of unstable cartilage flaps, with removal of loose bodies
- Synovectomy of inflamed synovium
- Humeral osteoplasty - excision of the goat's beard to restore clearance and relieve the mechanical adduction block
- Capsular release, especially anteroinferior, to regain the external rotation lost to the internal-rotation contracture
- Axillary nerve neurolysis or decompression - the nerve is identified and protected during the osteoplasty and inferior release
- Biceps tenotomy or tenodesis when the long head is a frayed pain source
- Subacromial decompression or bursectomy where there is concomitant impingement, with selective microfracture of small contained focal defects
Selection matters more than technique. CAM relieves pain and delays arthroplasty best when the joint space is preserved and the joint concentric. A severely narrowed, bone-on-bone glenohumeral space (in the region of 2 mm or less), large bipolar Walch B posterior wear or a grossly incongruent joint predicts early failure and progression to arthroplasty. Because it removes no bone stock that a later replacement needs, CAM is best framed to the patient as buying time rather than a cure.
Surgical Management
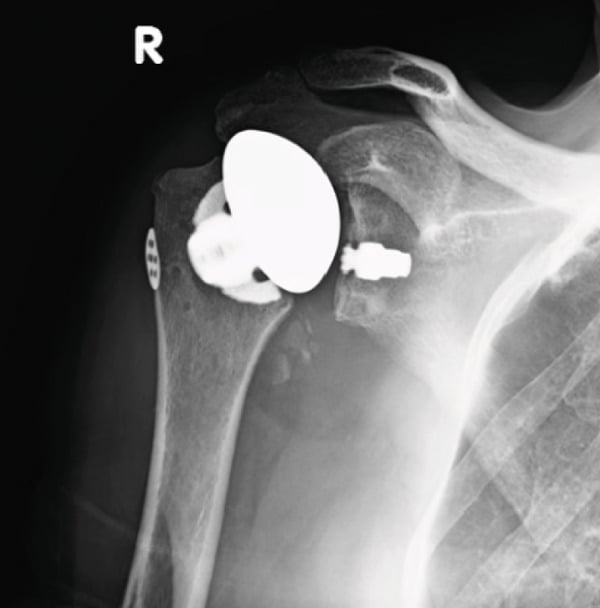
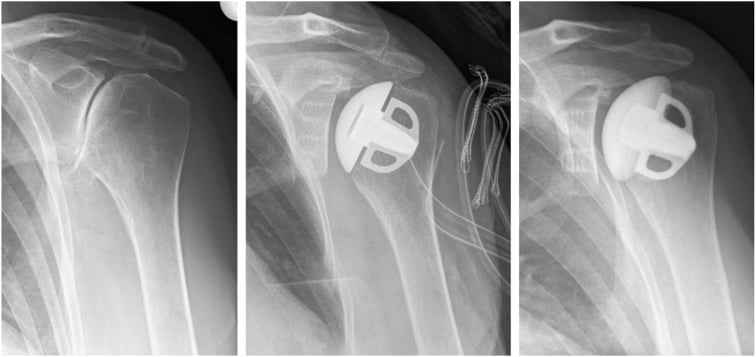
Anatomic total shoulder arthroplasty is the gold standard for primary OA with an intact rotator cuff. It replicates the anatomy and relies on concavity compression by the intact cuff to centre the ball in the socket.
The components. The humeral head is polished cobalt-chrome (or ceramic), fixed with a standard stem, a short stem or stemless (metaphyseal fixation). The glenoid is ultra-high molecular weight polyethylene (UHMWPE), usually cemented, pegged or keeled.
RIPContraindications to aTSA
Hook:RIP: Don't do an anatomic TSA if the shoulder mechanisms are dead (Cuff/Deltoid).
Patients under 50 years old are the most challenging. Arthroplasty has high failure rates (Poly wear, Loosening). Exhaust all non-operative measures. Consider Hemi or Arthroscopic Debridement (CAM).
Surgical Technique
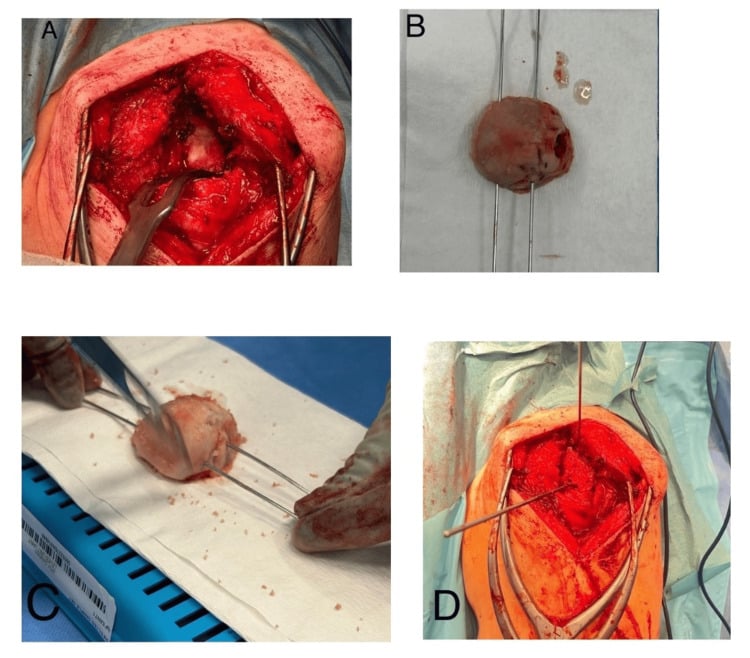
The deltopectoral approach is standard for shoulder arthroplasty. The interval lies between deltoid (axillary nerve) and pectoralis major (lateral and medial pectoral nerves), and the incision is 12-15cm for anatomic TSA, extended for complex cases. The landmarks are the coracoid medially, the deltoid insertion laterally and the bicipital groove, which guides you to subscapularis.
The cephalic vein is the lighthouse of the interval and is retracted laterally with deltoid. It can be ligated if needed, but is best preserved to minimise oedema.
Complications
- Risk
- under 1%
- Management
- Washout vs Revision
- Pearl
- C. acnes is #1 cause
- Risk
- 1-2% per year
- Management
- Revision to Reverse
- Pearl
- Radiolucent lines common
- Risk
- 1-3%
- Management
- Repair or Reverse
- Pearl
- Avoid early active IR
- Risk
- Rare
- Management
- Observation
- Pearl
- Axillary N. most at risk
Deep infection. The under-1% risk is for primary cases and is higher after revision. Cutibacterium acnes (formerly Propionibacterium) dominates: a slow-growing anaerobe that colonises the hair follicles (the dermoglandular unit). Diagnosis is difficult, because ESR and CRP are often normal and radiographs may show only nonspecific loosening; definitive diagnosis requires tissue culture held for 14 days. Prevention rests on benzoyl peroxide preparation before surgery, minimising traffic, laminar flow and vancomycin powder (debated).
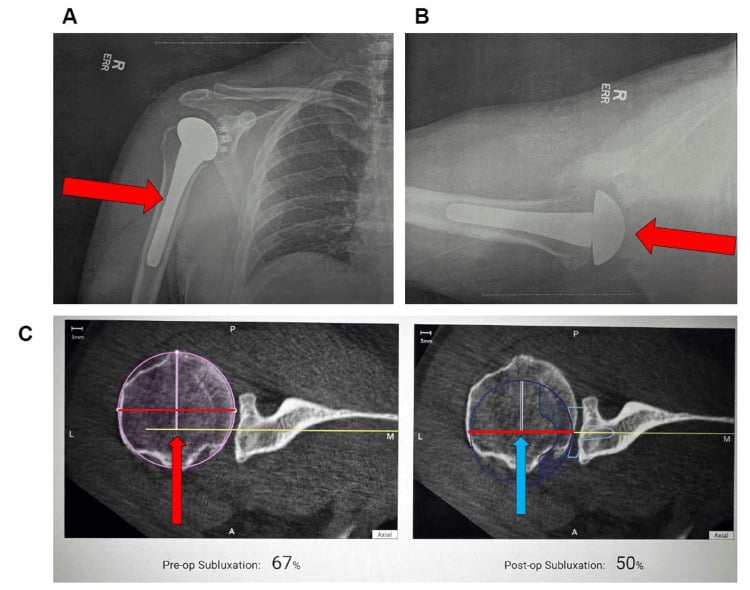
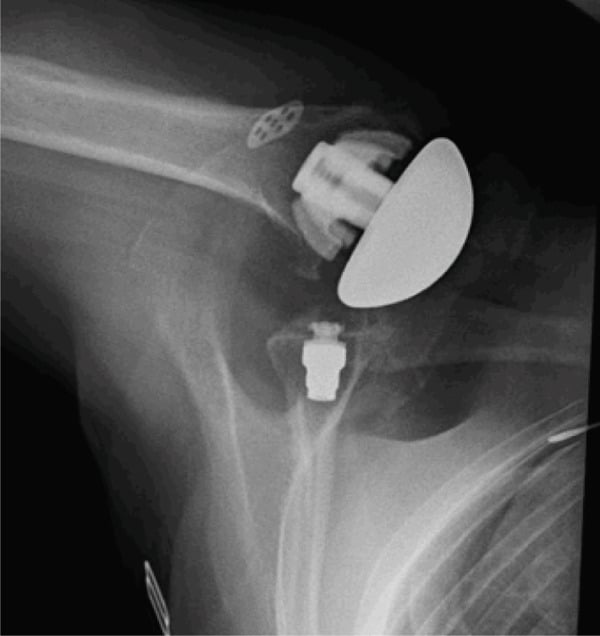
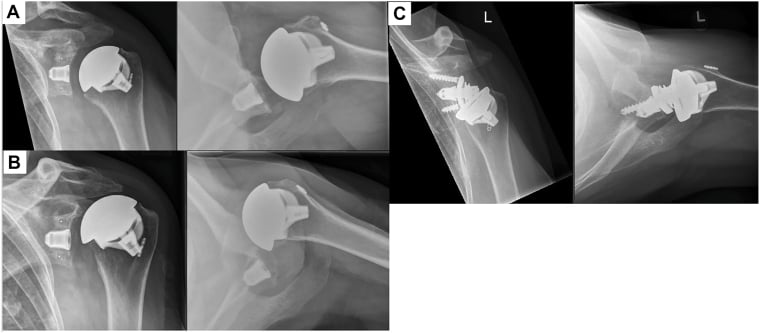
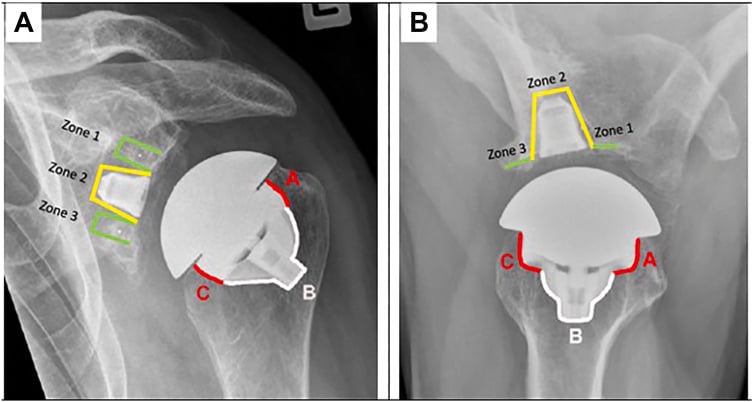
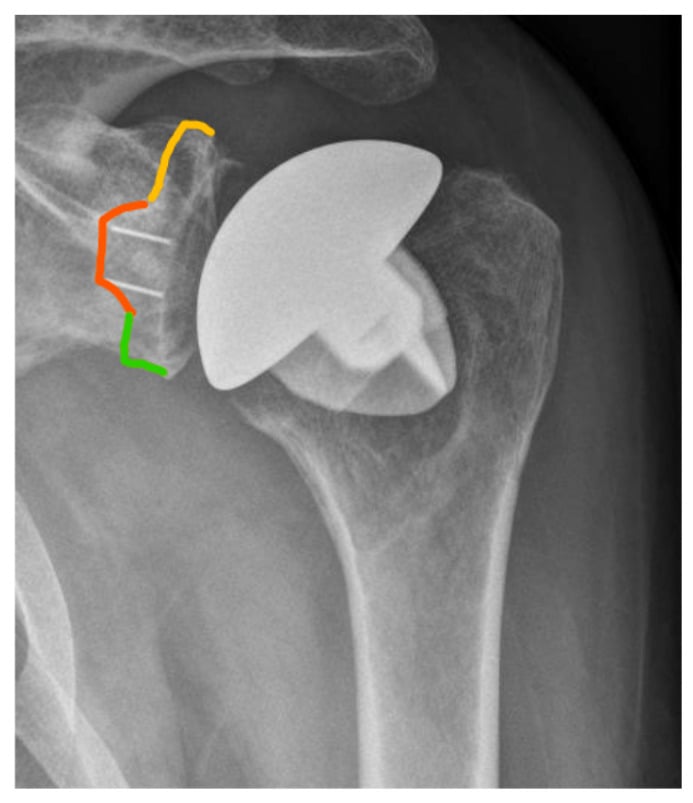
Glenoid loosening is the most common mode of long-term failure in anatomic TSA. The mechanism is the "rocking horse" phenomenon: if the head is not centred, because of cuff imbalance or uncorrected retroversion, eccentric loading at the glenoid edge toggles the component until the cement bond fails. Radiologically, loosening shows as radiolucent lines over 2mm around the pegs or keel.
Subscapularis failure is rupture of the repair or failure to heal, with aggressive early rehabilitation, poor tissue quality and over-tensioning as the risk factors. The consequence is anterior instability (dislocation), loss of active internal rotation, and pain. Pectoralis major transfer is the salvage option for an irreparable subscapularis.
Postoperative Care
Rehab Phases
- Sling day and night, removed for hygiene and exercises
- No active internal rotation, to protect the subscapularis repair
- No lifting over 1kg (a cup of tea)
- External rotation limited to neutral or 30 degrees, depending on intraoperative tension
- Pendulums, passive elevation (pulley or supine) to tolerance, and elbow, wrist and hand range of motion
- Wean off the sling; the goal is functional range
- Active-assisted then active elevation
- Hydrotherapy, cuff isometrics and scapular control
- Restore power and endurance with Theraband resistance (IR, ER, abduction)
- Late return to the gym (chest press, row)
- Return to sport: golf (chip and putt at 3-4m, drive at 6m), swimming, tennis (doubles preferred over singles); avoid heavy contact sports
Outcomes and Prognosis
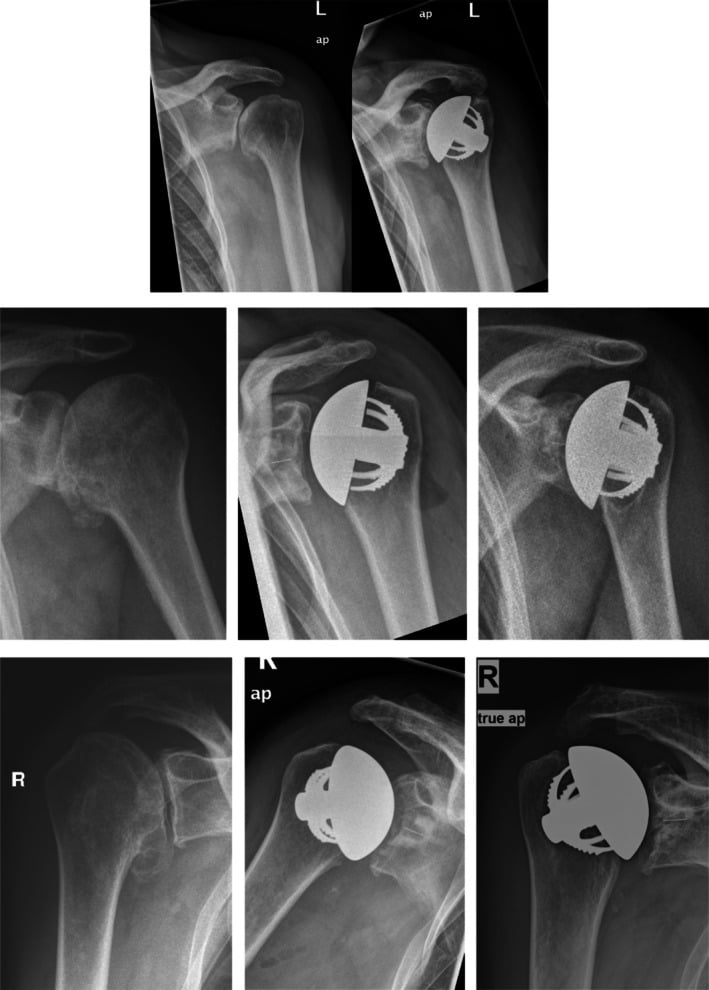
Survivorship. Anatomic TSA survivorship is excellent: 90-95% at 10 years and 80% at 15 years.
Function. Anatomic TSA gives better internal and external rotation than reverse TSA and allows the patient more "normal" activities, although heavy loading is discouraged to protect the glenoid.
Guidelines, Registries & Global Practice
Global Epidemiology
- Symptomatic GHOA affects ~3-5% of adults over 60; radiographic disease is far more prevalent. Demand for shoulder arthroplasty is rising faster than for hip or knee, driven chiefly by expanding reverse TSA indications across high-income health systems.
- Younger, higher-demand patients (under 60) form a growing share of arthroplasty referrals worldwide and consistently show higher revision rates.
Society Guidance, Side by Side
- Position on Shoulder OA Management
- Evidence-based glenohumeral OA work supports NSAIDs and physiotherapy first; intra-articular corticosteroid offers short-term relief; viscosupplementation and PRP have inconclusive/limited evidence. TSA recommended over hemiarthroplasty when glenoid bone stock allows.
- Position on Shoulder OA Management
- Stepwise care: analgesia, activity modification and physiotherapy before surgery. Anatomic TSA for intact-cuff OA; reverse TSA for cuff-deficient or complex glenoid deformity. Emphasis on shared decision-making and realistic expectations.
- Position on Shoulder OA Management
- Supports 3D CT planning and the modified Walch classification for glenoid morphology; growing endorsement of reverse TSA for B2/B3/C deformity where anatomic glenoid fixation is at risk.
- Position on Shoulder OA Management
- Restore version and centre the head; correct B2 retroversion with eccentric reaming (limited) or augments; protect the axillary nerve during inferior release; robust subscapularis repair after anatomic TSA.
Registry Evidence (Joint Picture)
- Revision rate: National joint registries (AOANJRR, NJR UK, the Nordic registries) report cumulative revision of primary shoulder arthroplasty for OA in the region of ~5-10% at 10 years.
- Age effect: Younger patients (under 55) have roughly double the revision risk of patients over 75 — consistent across registries.
- Prosthesis choice: Total shoulder arthroplasty has lower revision rates than hemiarthroplasty for OA. Reverse TSA revision rates are broadly comparable to anatomic TSA in the short-to-medium term, but very long-term (over 15 years) data remain richest for anatomic TSA.
- Fixation: Cemented all-polyethylene glenoids show superior survivorship to uncemented metal-backed glenoids in anatomic TSA (metal-backed designs failed through polyethylene dissociation and construct over-stiffening).
High- vs Limited-Resource Practice Variation
- Well-resourced settings: Routine preoperative 3D CT planning, patient-specific instrumentation or navigation, and an increasing default to reverse TSA for elderly and deformed glenoids.
- Resource-limited settings: CT and modern implants may be scarce; hemiarthroplasty or non-operative management retains a larger role, and stemmed cemented implants are often preferred for availability and cost.
Exam-Ready Practice Points
- Quote a revision figure in the "~5-10% at 10 years" range and note the strong age effect.
- Understand why metal-backed glenoids fell out of favour (polyethylene dissociation, construct over-stiffening).
- Reverse TSA usage is expanding rapidly, but anatomic TSA remains the functional benchmark for the intact-cuff patient with adequate glenoid bone stock.
- Higher-volume surgeons and centres have lower complication rates (volume-outcome relationship).
- Indications for hemiarthroplasty are now narrow (very young patients for bone preservation, insufficient glenoid bone stock, or AVN with a spared glenoid).
Related pages: Total Shoulder Arthroplasty (Anatomic) is the operation this page decides on and carries the implant, glenoid-fixation and technique detail in full; Reverse Total Shoulder Arthroplasty for the alternative now offered even with an intact cuff - note the Friedman comparison carded above is a single manufacturer's registry with unmatched baselines, and that page records the gap between implant and functional survivorship; Rotator Cuff Arthropathy for the cuff-deficient arthritis that changes the operation entirely and in which anatomic replacement fails by rocking-horse loosening; Shoulder Arthroplasty Complications and Revision Shoulder Arthroplasty for glenoid loosening, instability, infection and what follows them; Stemless Shoulder Arthroplasty for the humeral-side alternative in good bone; Avascular Necrosis of the Shoulder for the secondary arthritis with a preserved glenoid, where a humeral-only solution still has a place; Adhesive Capsulitis for the stiff shoulder that mimics early arthritis and must not be operated on; and Rheumatoid Hand and Wrist for inflammatory arthropathy, where the bone stock, the cuff and the medical management are all different.
MCQ Practice Points
Q: What is the primary deformity of the glenoid in Osteoarthritis? A: Retroversion (Posterior wear). This leads to posterior subluxation of the humeral head.
Q: Which X-ray view is essential for assessing glenoid version? A: Axillary Lateral. An AP view often underestimates posterior wear.
Q: What clinical sign suggests a rotator cuff tear in the setting of OA? A: Weakness/Lag or superior migration (high riding head) on X-ray. Stiffness is typical of OA; Weakness (Pseudoparalysis) suggests Cuff Tear Arthropathy.
Q: What is the most common organism in shoulder PJI? A: Cutibacterium acnes. It requires extended culture incubation (14 days).
Q: Why is active infection a contraindication for TSA? A: High recurrence. Infection must be cleared (antibiotics/debridement) before implantation.
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“A 60M presents with global loss of ROM. X-rays show mild OA. Discuss your differential.”
“You are planning a TSA for a B2 Glenoid. How do you manage the retroversion?”
“Counsel a patient on the specific risks of Anatomic TSA.”
“A 45M heavy labourer presents with severe primary OA. Intact cuff. He cannot work due to pain. Discuss your management strategy.”
Diagnosis
- Night Pain
- Loss of ER
- Crepitus
- Axillary X-ray (Posterior wear)
Classification
- Walch A (Concentric)
- Walch B (Posterior/Biconcave)
- Walch C (Dysplastic/Retroverted)
- Samilson-Prieto (Osteophytes)
Treatment
- Non-op first
- Intact Cuff → Anatomic TSA
- Cuff Tear → Reverse TSA
- Young → Hemi/Preservation
Complications
- Subscap Failure
- Glenoid Loosening
- Infection (C. acnes)
- Periprosthetic Fracture
Pearls
- B2 Glenoid needs correction
- Axillary nerve at risk inferiorly
- Protect subscap post-op
- Stiffness = OA; Weakness = Cuff
Evidence
- Total beats Hemi
- Pegged beats Keeled
- LTO = peel for subscap healing
- Augments for B2
Evidence Base
Walch Glenoid Classification (Original Description)
- Type A (centered head, symmetric wear) in 59 percent, Type B (posterior subluxation, asymmetric posterior wear) in 32 percent, Type C (dysplastic retroversion over 25 degrees) in 9 percent.
- Humeral head position relative to the glenoid predicted the pattern of glenoid erosion.
- Posterior subluxation drives the exaggerated posterior wear of Type B glenoids.
Modified Walch Classification (3D CT)
- Added the B3 (monoconcave, retroversion at least 15 degrees or subluxation 70 percent) and D (anteversion) types and refined A2.
- Interobserver reliability improved from kappa 0.39 (original) to 0.70 with 3D CT and the modified system.
- Intraobserver reliability improved from 0.61 to 0.88.
Augmented Glenoid for B2/B3 Bone Loss
- Stepped augmented components restored anatomy in B2 glenoids with central peg osteolysis (10 percent) equivalent to non-augmented A1 glenoids (5 percent).
- B3 glenoids had significantly higher central peg osteolysis (29 percent) and more component medialization.
- Version and inclination were corrected without significant difference between groups.
Anatomic vs Reverse TSA for OA with Intact Cuff
- At a mean of 41 months, aTSA and rTSA had similar outcome scores, motion and satisfaction.
- aTSA achieved greater external rotation (exceeding the MCID).
- Complications were significantly higher with aTSA (4.9 vs 2.2 percent); revision rates were similar.
Subscapularis Management: LTO vs Peel
- Lesser tuberosity osteotomy (95 percent) and subscapularis peel (100 percent) had statistically equivalent CT healing rates.
- No significant difference in subscapularis fatty infiltration, strength or clinical scores at 1 year.
- Both techniques showed a small postoperative increase in fatty infiltration.
Shoulder Arthroplasty in Patients 50 Years or Younger
- Estimated survival was 84 percent (TSA) and 75 percent (hemi) at 20 years.
- Glenoid arthrosis after hemiarthroplasty and motion-limiting soft-tissue problems drove unsatisfactory outcomes.
- Pain relief and motion improved reliably, but many results were rated unsatisfactory long term.
Hemiarthroplasty vs Total Shoulder Arthroplasty (RCT)
- TSA provided significantly greater pain relief (p=0.002) and internal rotation (p=0.003) than hemiarthroplasty.
- 3 of 25 hemiarthroplasty patients required revision to resurface the glenoid.
- TSA added cost, operative time and blood loss but no TSA had been revised at follow-up.
Preoperative Corticosteroid Injection and PJI Risk
- Injection within 3 months of TSA raised periprosthetic joint infection risk (RR 1.12, 95% CI 1.04-1.20).
- No increased risk when the injection was given more than 3 months before surgery (RR 1.02).
- Three months is the safest interval between injection and arthroplasty.