Material Properties | Stress-Strain Curves | Young's Modulus | Mechanical Testing
- Stress (σ) is force per unit area (N/m² or Pa) - describes intensity of internal forces
- Strain (ε) is change in length divided by original length (dimensionless) - describes deformation
- Elastic modulus (Young's modulus E) is stress divided by strain - measures stiffness
- Elastic region: reversible deformation following Hooke's law (σ = Eε)
- Yield point: transition from elastic to plastic deformation with permanent change
- “Stiffness (E) and strength (ultimate tensile stress) are independent - high E does not mean high strength
- “Stress concentration at notches, holes, or defects can exceed local yield stress despite low average stress
- “Ductile materials yield before fracture (warning); brittle materials fracture suddenly
- “Bone modulus (17 GPa) much lower than metal (110-240 GPa) - explains stress shielding with implants
Overview and Fundamental Definitions
Stress, strain and elastic modulus are the fundamental concepts in biomechanics and materials science that describe how a material responds to applied force. They are essential for implant design, for fracture mechanics and for interpreting clinical failures: stress shielding, plate fracture at screw holes, and a metal that yields with warning against a ceramic that fractures suddenly.
Stress. Stress (σ) is force per unit area, σ = F / A, and describes the intensity of the internal forces within a material that resist an external load. With force in newtons and area in square metres, stress is in pascals (Pa = N/m²). The pascal is the SI unit but too small for practical use, so the megapascal (MPa, 10⁶ Pa) is the common unit for bone and soft tissue and the gigapascal (GPa, 10⁹ Pa) for metals and ceramics.
Normal and shear stress. Normal stress acts perpendicular to a surface, as tension or compression: tensile stress pulls apart and is positive, compressive stress pushes together and is negative. Shear stress acts parallel to the surface, from a tangential force.
Strain. Strain (ε) is the relative change in length of a material when it is loaded, ε = ΔL / L₀, the change in length over the original length, both in metres. It is therefore dimensionless, a pure number, often expressed as a percentage (strain × 100) or as microstrain (με = strain × 10⁶). Stress describes the intensity of the internal forces and strain the relative deformation; both are needed to characterise how a material responds to loading.
Types of strain. Tensile strain is extension and positive; compressive strain is shortening and negative. Shear strain (γ) is angular deformation, measured in radians, and for small angles γ ≈ displacement / thickness.
Worked examples. The arithmetic is simple once the units are consistent.
- A 1000 N force pulling on a rod of 10 mm² (10 × 10⁻⁶ m²) gives a tensile stress of 1000 / (10 × 10⁻⁶) = 100 MPa
- A specimen 100 mm long that extends by 1 mm has a strain of 1 / 100 = 0.01, or 1%
- A 500 N force parallel to a 100 mm² surface gives a shear stress of 5 MPa
Principles and Core Concepts
Elastic modulus. Elastic modulus (E), or Young's modulus, is a material property that measures stiffness: resistance to elastic, reversible deformation. It is the slope of the stress-strain curve in the linear elastic region, E = σ / ε, expressed in Pa, MPa or GPa because strain is dimensionless. A high E means a small strain for a given stress. It is not the same as strength.
Hooke's law. Rearranged, the definition gives σ = E × ε. For a given stress, a higher E means lower strain; for a given strain, a higher E means higher stress, so more force is needed. A stiff material (steel, ceramics) needs a large force for a small deformation, whereas a compliant one (rubber, soft tissue) deforms a great deal under a small force.
- Elastic Modulus (GPa)
- 1050
- Category
- Ultra-stiff
- Clinical Use
- Reference, not used clinically
- Elastic Modulus (GPa)
- 380
- Category
- Very stiff, brittle
- Clinical Use
- Femoral head bearings
- Elastic Modulus (GPa)
- 210-240
- Category
- Very stiff
- Clinical Use
- Femoral heads, stems
- Elastic Modulus (GPa)
- 200
- Category
- Stiff
- Clinical Use
- Plates, screws, stems
- Elastic Modulus (GPa)
- 110
- Category
- Moderately stiff
- Clinical Use
- Stems, cages, plates
- Elastic Modulus (GPa)
- 70
- Category
- Between titanium and bone
- Clinical Use
- Reference
- Elastic Modulus (GPa)
- 17
- Category
- Moderate
- Clinical Use
- Native tissue
- Elastic Modulus (GPa)
- 2-3
- Category
- Low
- Clinical Use
- Cemented fixation
- Elastic Modulus (GPa)
- 0.1-1
- Category
- Very low
- Clinical Use
- Native tissue
- Elastic Modulus (GPa)
- 0.01 (10 MPa)
- Category
- Very compliant
- Clinical Use
- Native tissue
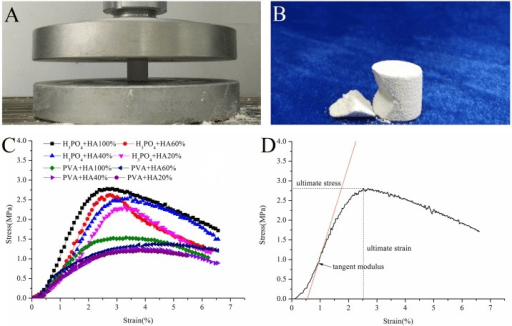
The stress-strain curve. The curve characterises a material's behaviour from initial loading to failure, and each of its regions has a distinct mechanical significance.
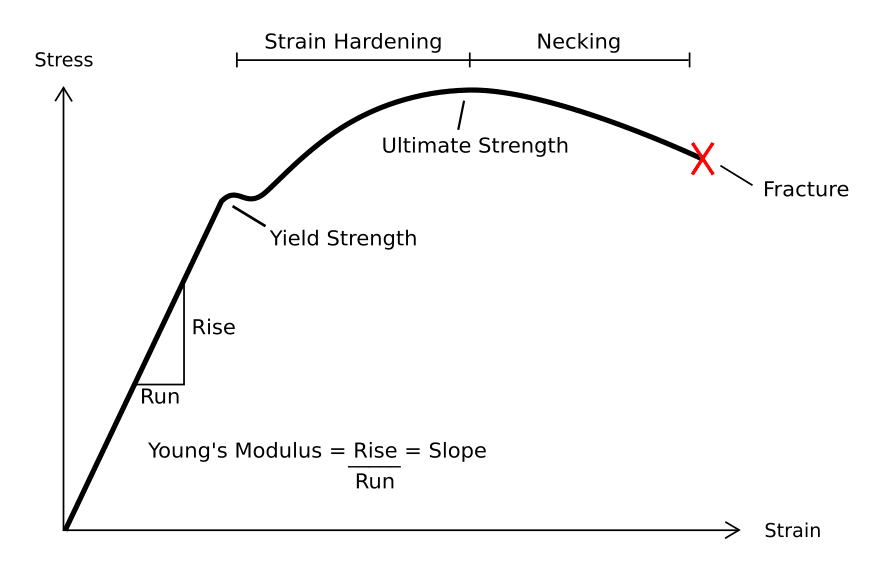
Elastic region. Stress is proportional to strain (Hooke's law) and the slope is the elastic modulus. The deformation is reversible: the material returns to its original shape when the load is removed. The strains are small, typically under 0.5% for metals.
Yield point. The transition from elastic to plastic deformation; beyond it the deformation is permanent. For metals, yield is typically defined at the 0.2% offset, a line parallel to the elastic slope offset by 0.2% strain, and the yield stress (σ_y) is the stress at the yield point.
Plastic region. Deformation is permanent, and strain increases faster than stress, so the curve flattens. Metals work harden (strain harden) as dislocations interact and increase the resistance to further deformation, and ductile materials can reach large strains here before they fracture.
Ultimate tensile strength. The peak stress on the curve and the maximum load-bearing capacity of the material. After it, necking begins, a local reduction in cross-section, and stress falls as the material thins.
Fracture. The material fails completely. Ductile fracture follows significant plastic deformation and necking and leaves a cup-and-cone surface; brittle fracture is sudden, with minimal plastic deformation and a flat fracture surface.
Classification of Material Behaviour
By deformation. An elastic material deforms reversibly, with stress proportional to strain: metals below yield behave this way, and rubber is elastic but non-linear. A plastic material deforms permanently after yield and dissipates energy as heat, as metals do beyond yield. A viscoelastic material's behaviour depends on time, which shows as creep, stress relaxation and hysteresis; biological tissues and polymers are viscoelastic.
- Characteristics
- Reversible, rate-independent
- Examples
- Metals (elastic region)
- Characteristics
- Permanent, irreversible
- Examples
- Metals (beyond yield)
- Characteristics
- Time-dependent, rate-dependent
- Examples
- Bone, cartilage, soft tissues
By failure mode. A ductile material undergoes large plastic deformation before it fractures, which gives warning; stainless steel and titanium fail this way. A brittle material fractures suddenly and catastrophically, with minimal plastic deformation; ceramics are brittle, and so is cortical bone under impact.
- Ductile Material
- Large (greater than 5-10%)
- Brittle Material
- Minimal (less than 1%)
- Example
- Steel vs ceramic
- Ductile Material
- Yes (visible yielding)
- Brittle Material
- No (sudden fracture)
- Example
- Metal bends, ceramic shatters
- Ductile Material
- Cup-and-cone, fibrous
- Brittle Material
- Flat, crystalline
- Example
- Ductile vs brittle fracture
- Ductile Material
- High
- Brittle Material
- Low
- Example
- Absorbs energy vs cracks easily
- Ductile Material
- Preferred (safety)
- Brittle Material
- Avoided (catastrophic failure)
- Example
- Implant material choice
Factors affecting ductility. Lower temperature reduces ductility (the ductile-to-brittle transition), and so does faster loading, as in impact against slow tension. Smaller grains increase both strength and ductility, and alloying elements affect it.
Ductility is clinically preferred - gives warning before failure. Brittle materials (ceramics) fail catastrophically without warning. This is why metal implants are preferred for load-bearing applications despite higher modulus.
Differentiating Confusable Mechanical Properties
Examiners frequently probe whether candidates can distinguish properties that sound similar but are mechanically independent; this is the basic-science equivalent of a differential diagnosis. Stiffness describes elastic deformation and strength describes the load at failure, and high stiffness does not imply high strength.
- Definition
- Resistance to elastic deformation (σ/ε)
- Curve Feature
- Slope of elastic region
- Independent Of
- Strength - a stiff material can be weak (ceramic)
- Definition
- Stress at failure or onset of plastic deformation
- Curve Feature
- Peak / yield stress level
- Independent Of
- Stiffness - titanium is less stiff but can be stronger than steel
- Definition
- Energy absorbed before fracture; resistance to crack propagation
- Curve Feature
- Total area under the curve
- Independent Of
- Stiffness and strength individually
- Definition
- Capacity for plastic strain before fracture
- Curve Feature
- Length of plastic region
- Independent Of
- Strength - a strong material may still be brittle
- Definition
- Resistance to surface indentation
- Curve Feature
- Not shown on tensile curve
- Independent Of
- Bulk modulus; correlates loosely with wear
- Definition
- Stress sustainable for many cycles
- Curve Feature
- Below UTS; S-N curve
- Independent Of
- Static strength - failure occurs below UTS
Saying a material is "strong because it is stiff" is the single most common error. Diamond and alumina are extremely stiff yet brittle (low toughness); titanium is less stiff than steel (110 against 200 GPa) yet some alloys exceed steel in tensile strength. Stiffness, strength, toughness, and fatigue resistance are four separate properties.
Material Property versus Structural Property
Material properties. Elastic modulus, yield stress and ultimate tensile strength are intrinsic to the material and independent of size or shape, a value per unit area and strain. You cannot change a material's modulus by making the object bigger.
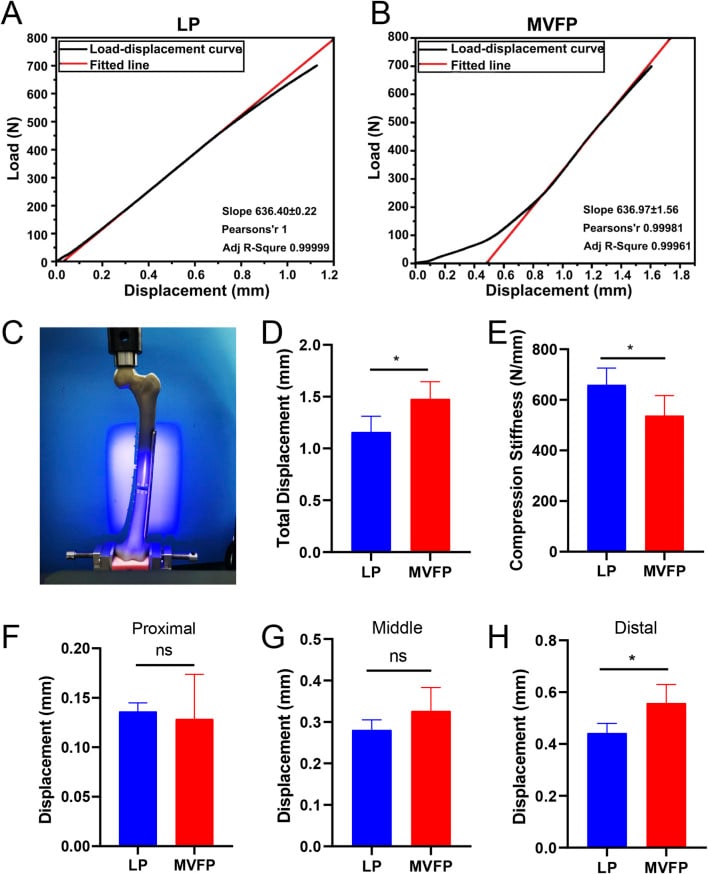
Structural properties. A structural (extrinsic) property describes how a whole object deforms under load, its rigidity or stiffness, and depends on both the material and its geometry. Bending rigidity is E × I, where I is the second moment of area (area moment of inertia), a purely geometric term.
Why geometry dominates. I scales steeply. For a solid cylinder, bending and torsional rigidity are proportional to the radius to the fourth power, so doubling a nail's diameter increases its bending rigidity roughly 16-fold; a plate's bending rigidity is proportional to its thickness cubed. Because I depends on how far the material lies from the neutral axis, a hollow tube (a nail) is nearly as stiff as a solid rod of the same outer diameter for far less material.
Why it matters clinically. Exchange (reamed) nailing for a diaphyseal nonunion works largely by fitting a larger-diameter, stiffer nail, a geometric change rather than a change in material modulus. Stress shielding likewise is driven by the structural stiffness of the stem (E × geometry), not E alone: a thick cobalt-chrome stem and a thin one of the same alloy shield very differently.
Modulus is a fixed material property. A whole bone or implant is made stiffer by changing its geometry (second moment of area), not its modulus.
Tissue Mechanical Properties
Bone as a two-phase composite. Bone's stiffness and strength arise from hydroxyapatite mineral, stiff, hard and brittle, which resists compression, embedded in a matrix of type I collagen, compliant and tough, which resists tension.
Strength asymmetry. Bone is strongest in compression, weaker in tension and weakest in shear. The mineral carries compressive load well, while tensile and shear loads fall on the collagen and the mineral-collagen interface, which is why many bending fractures fail on the tension (convex) side first.
Each phase alone. Removing either phase confirms the model. Demineralised bone (collagen only, after acid treatment) becomes rubbery and flexible and can be tied in a knot; deproteinised bone (mineral only, after ashing or heating) becomes brittle chalk that crumbles. Neither phase alone has bone's toughness: the composite is tougher than either component.
Cortical bone. Its elastic modulus is 17-20 GPa and its ultimate tensile strength 130-150 MPa. The osteonal (longitudinal) orientation of its collagen and mineral makes it anisotropic, in contrast to every metal on this page, which is isotropic, one modulus describing it in any direction. Cortical bone is stiffest and strongest along the osteonal long axis, materially less stiff across it and lower again in shear, which is why a spiral fracture follows the plane of maximum tension rather than the plane of maximum shear. The 17 GPa quoted throughout this page is the longitudinal figure; loaded transversely, the same bone is considerably more compliant.
Two consequences worth carrying. Quoting a single stiffness ratio between implant and bone (110/17) is an approximation that holds only for axial loading. And when a viva asks why bone fails the way it does in torsion, the answer is anisotropy, not geometry alone.
Viscoelasticity. The collagen and fluid content make bone rate-dependent: modulus and strength rise with loading rate, which is relevant to high-energy trauma, so a fall and a slow bend do not test the same material behaviour. Hydration matters too, and a dried cadaveric specimen is stiffer and more brittle than living bone.
Cancellous bone. Its elastic modulus is 0.1-1 GPa and varies with density: apparent density correlates with modulus (ρ²). The trabecular architecture gives it its energy-absorbing capacity, and apparent modulus and strength depend on trabecular architecture, density and processing as well as tissue composition.
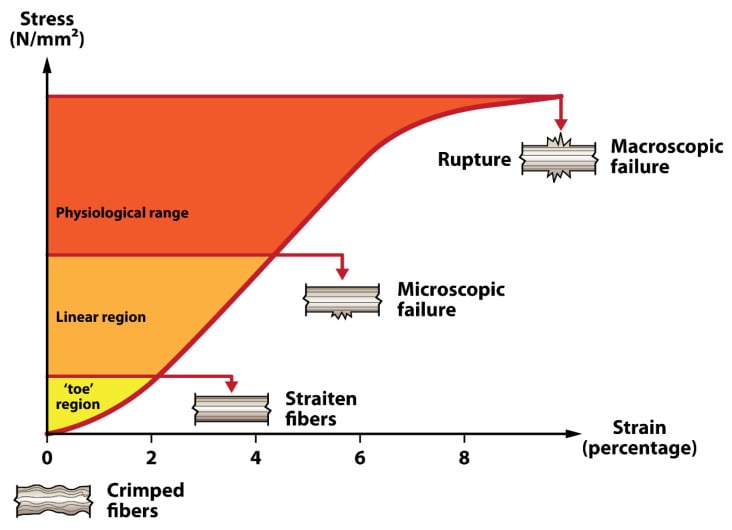
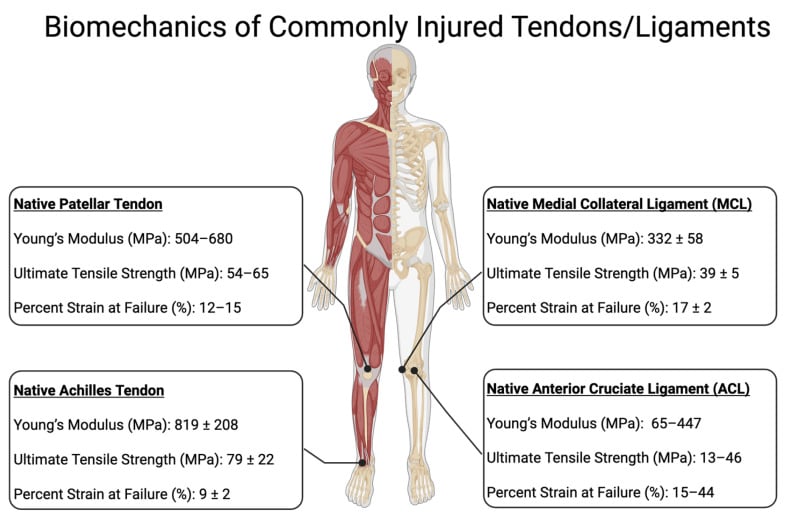
Tendons and ligaments. Tendon has a modulus of 1-2 GPa and is highly anisotropic. Its curve begins with a toe region as the crimped collagen fibres uncrimp, continues through a linear region of fibre stretching, and ends in a failure region of fibre rupture. Like other biological tissues it is viscoelastic, its behaviour rate-dependent.
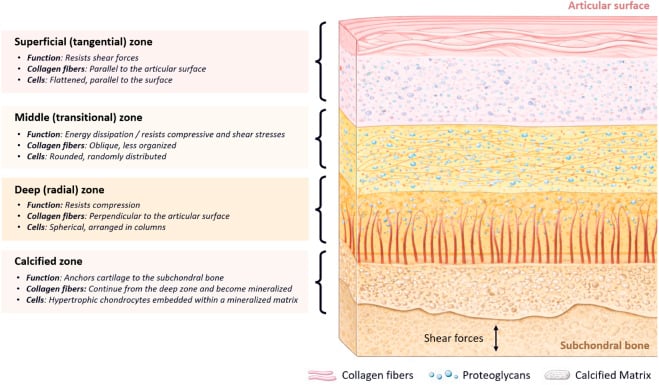
Articular cartilage. Cartilage is viscoelastic and biphasic, a solid phase of collagen and proteoglycan and a fluid phase of water. Its compressive modulus at equilibrium is 0.5-1 MPa; its tensile modulus, carried by the collagen network, is 5-25 MPa.
Laboratory Testing Methods
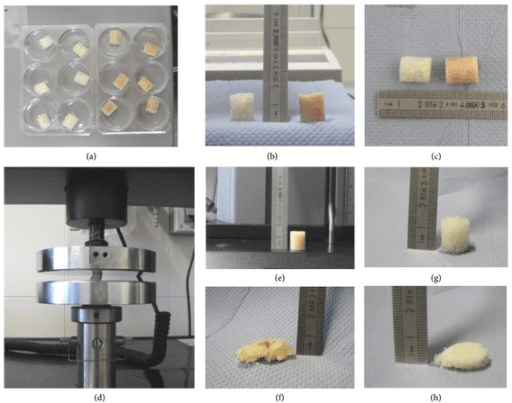
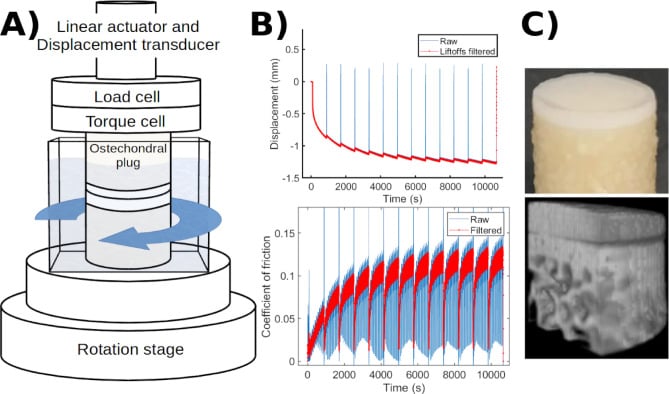
Tensile testing. A dog-bone specimen is pulled at a constant rate while load and elongation are recorded. The result is the stress-strain curve, from which E, yield stress and ultimate strength are measured.
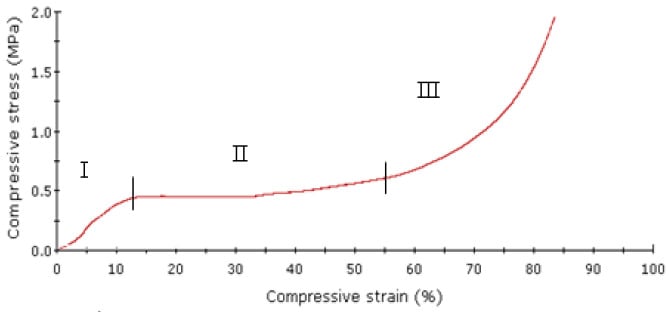
Compression testing. A cylindrical specimen is compressed. It is important for bone, which is stronger in compression, and has to take account of buckling and friction.
- Specimen
- Dog-bone
- Properties Measured
- E, yield, UTS, ductility
- Specimen
- Cylinder
- Properties Measured
- Compressive strength, E
- Specimen
- Beam
- Properties Measured
- Flexural modulus, strength
- Specimen
- Various
- Properties Measured
- Cycles to failure, S-N curve


Fatigue testing. The specimen is loaded cyclically at submaximal stress, and the result is plotted as an S-N curve, stress against the number of cycles to failure. Some materials have an endurance limit, a stress below which life is infinite. Fatigue testing is essential for implant qualification, because implants must withstand millions of loading cycles.
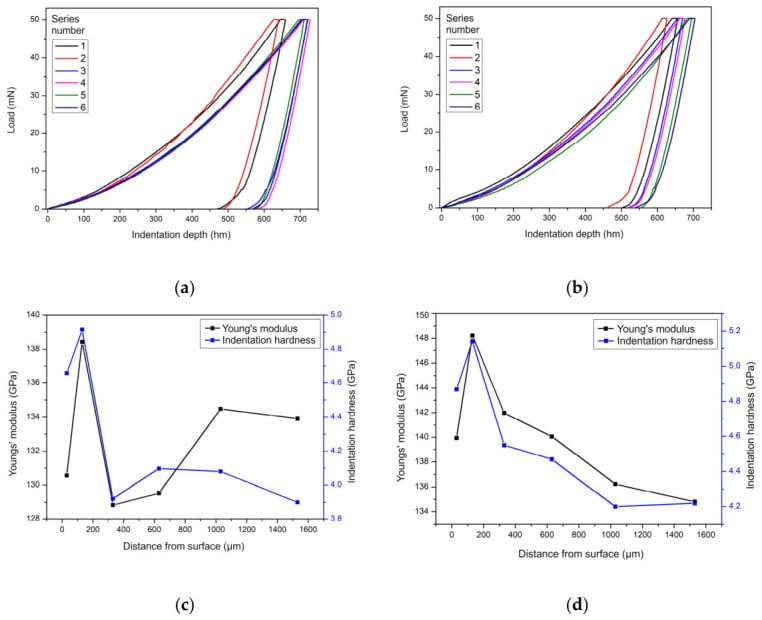
Hardness testing. Hardness is resistance to indentation, measured by the Brinell, Rockwell and Vickers methods.
Fracture Healing and Rehabilitation
Perren's strain theory. Perren linked mechanics to biology: the tissue that forms in a fracture gap is determined by the interfragmentary strain, gap change / gap width.
- Greater than 10%: fibrous tissue; high strain prevents bone formation
- 2-10%: cartilage and endochondral ossification
- Less than 2%: direct bone healing, which absolute stability (compression) allows
Load bearing and load sharing. A stiff plate is load bearing and shields the bone from stress; flexible fixation is load sharing but carries a risk of motion. Fixation balances the two for optimal healing.
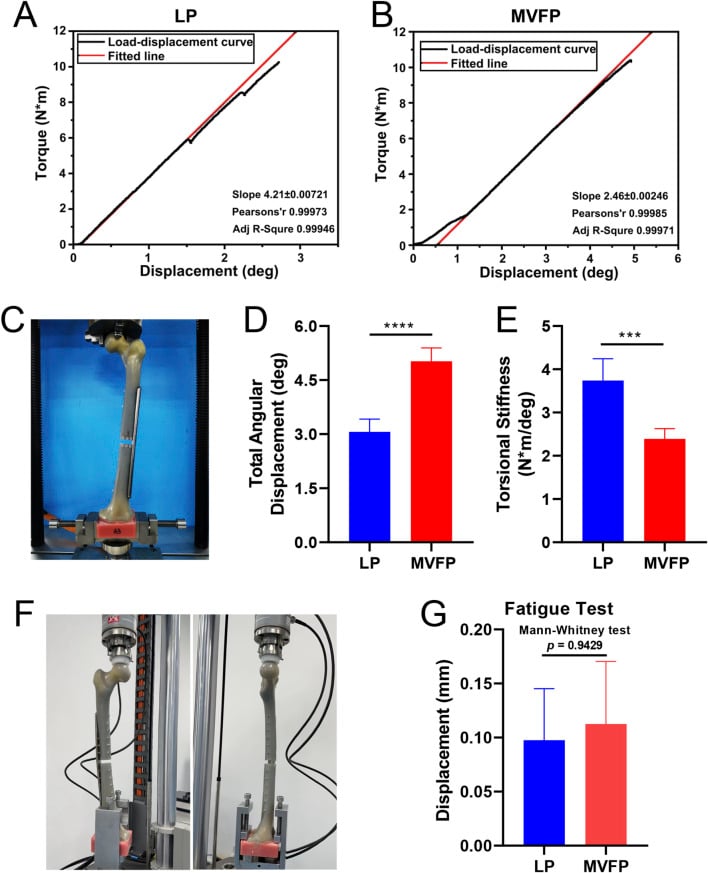
Loading and rehabilitation. Some loading is beneficial for bone healing and controlled motion for cartilage health, whereas prolonged immobilisation causes osteopenia. The task is to balance protection with beneficial stress.
Weight-bearing protocols. Protocols are based on implant strength and stability and on bone quality, and progress gradually.
- Recommendation
- WBAT immediately
- Rationale
- Secure fixation
- Recommendation
- Protected initially
- Rationale
- Load bearing
- Recommendation
- WBAT often
- Rationale
- Load sharing design
Wolff's law is fundamental to rehabilitation. Early protected weight-bearing promotes healing and prevents disuse osteopenia. Balance with implant stability requirements.
Clinical Relevance
Stress shielding. A metal stem (E = 110-240 GPa) is roughly 6-15 times stiffer than cortical bone (E = 17 GPa). For a given deformation the stiff implant carries the majority of the load, and the proximal bone experiences reduced stress.
Wolff's law. Bone adapts to the loading it carries: increased stress brings bone deposition, and decreased stress triggers osteoclastic resorption. Around a stiff stem the result is proximal bone loss, 20-40% being common, progressive over years and most pronounced in Gruen zone 7 (the calcar).
- Effect
- Most resorption
- Clinical Concern
- Periprosthetic fracture
- Effect
- Significant loss
- Clinical Concern
- Revision bone stock
- Effect
- Maintained
- Clinical Concern
- Stem fixation preserved
Consequences. The bone stock left for revision is weakened, there is a risk of periprosthetic fracture if the stem fails, and the loss may affect implant longevity.
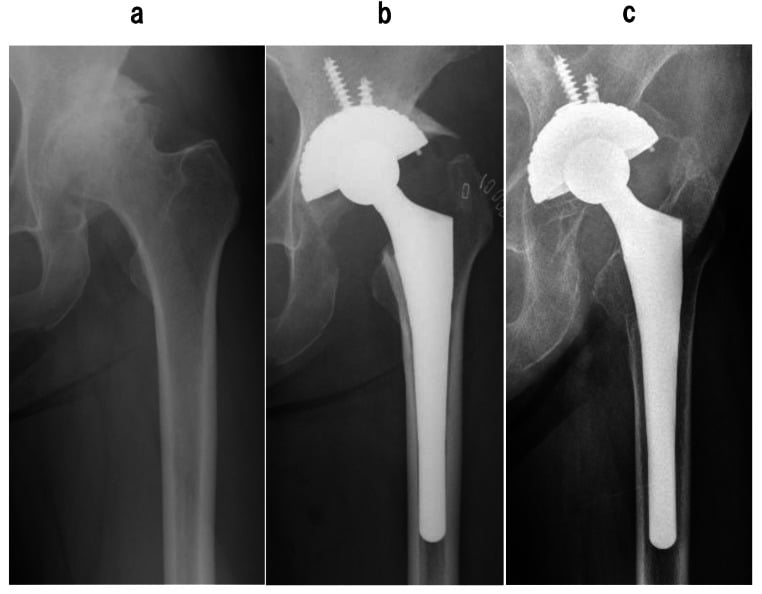
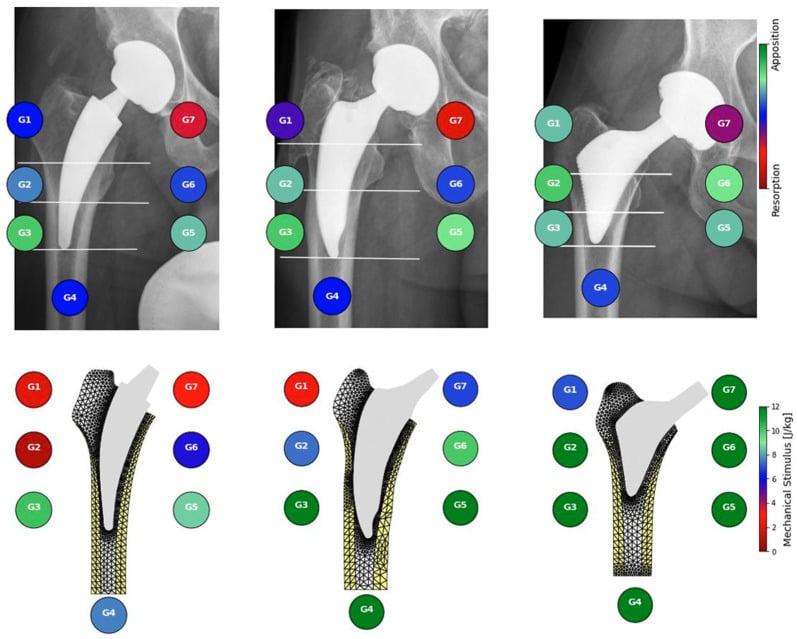
Reducing stress shielding. The mitigation strategies are these.
- Lower-modulus materials (titanium 110 GPa against steel 200 GPa)
- Flexible stem designs allowing proximal load transfer
- Porous-coated stems with proximal ingrowth
- Proper stem sizing, avoiding undersizing
- Hydroxyapatite coating for biological fixation
Stress concentration. Geometric discontinuities (holes, notches, corners) create a local elevation of stress. The stress concentration factor is local stress divided by average stress, and the local stress can exceed the yield point even when the average stress is low, which explains where cracks start in plates. It shows clinically as:
- Plate fracture at screw holes in delayed unions
- Screw breakage at thread roots
- Fatigue crack initiation at stress concentrations
- New stress risers created by modifying an implant (drilling, notching)
Prevention. Avoid unnecessary holes or modifications to implants, use smooth transitions between sections, and place screws with proper technique. Early bone healing reduces the cyclic loading the implant must bear.
Implant Design Considerations
Designing for fatigue. Implants experience millions of loading cycles, and fatigue failure occurs below the ultimate strength. The S-N curve predicts fatigue life, and the design aim is infinite life, below the endurance limit.
Plate fracture in nonunion. Cyclic loading at stress concentrations initiates a crack at a screw hole, and the crack propagates until the plate fractures. Prevention is to achieve bone healing, which reduces the number of cycles, together with appropriate implant selection and avoiding unnecessary holes or modifications.
Plate fracture = biological failure. The plate is doing its job but the bone did not heal. Treatment is to address the nonunion (bone graft), not just replace the plate.
- Effect
- Local stress elevation
- Design Solution
- Smooth transitions
- Effect
- Failure below UTS
- Design Solution
- Design for endurance
- Effect
- Material degradation
- Design Solution
- Appropriate alloys
- Effect
- Surface loss
- Design Solution
- Hard bearing surfaces
Finite element analysis. FEA is a computer simulation of stress distribution used in implant design: it identifies high-stress regions, predicts failure modes and guides design optimisation. Its results require validation by mechanical testing, by cadaveric testing for clinical relevance and by fatigue testing for durability, so understand the concept but know its limitations.
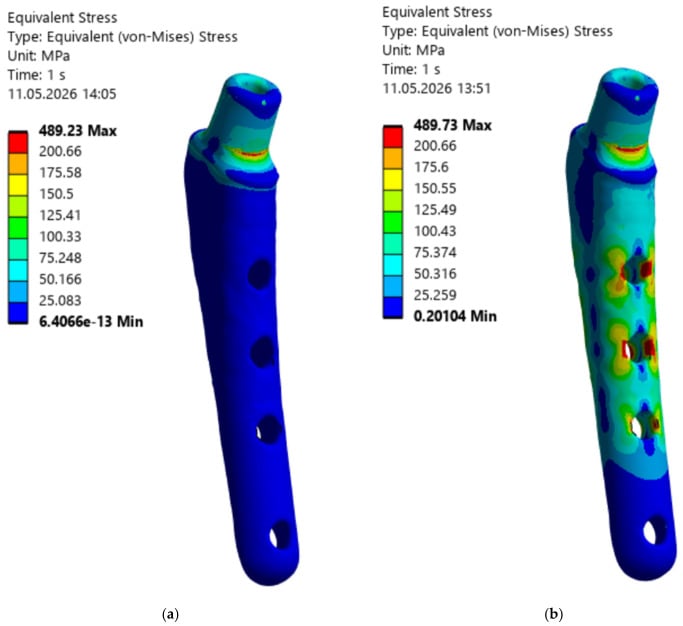
Clinical Applications
Stiffness in material selection. A lower modulus reduces stress shielding, so titanium (110 GPa) is preferred for stems, while steel or cobalt-chrome (200+ GPa) is acceptable for plates.
Strength in material selection. An implant must exceed physiological loads with a safety factor and needs fatigue strength for cyclic loading. Its yield strength defines the safe operating range, separating safe loading from damaging deformation.
- Key Property
- Low modulus (reduce shielding)
- Material Choice
- Titanium
- Key Property
- Wear resistance
- Material Choice
- CoCr, ceramic
- Key Property
- Strength, stiffness
- Material Choice
- Steel, titanium
- Key Property
- Low modulus, fatigue
- Material Choice
- PMMA
Outcomes. Material properties affect implant longevity: fatigue resistance is critical, bearings need wear resistance, and osseointegration needs biocompatibility. Titanium stems show less proximal bone loss, porous coatings improve load transfer, and designs have evolved to reduce shielding.
- Material
- Steel (200 GPa)
- Outcome Impact
- High stress shielding
- Material
- Titanium (110 GPa)
- Outcome Impact
- Reduced shielding
- Material
- Composite/porous
- Outcome Impact
- Bone-matched modulus
Registry data. AOANJRR data show that material affects revision rates, the bearing surface affects wear and stem design affects stress shielding; long-term follow-up is essential. Future directions include personalised implant design, 3D printing for complex geometries and novel materials such as composites.
Material science advances continue to improve outcomes. HXLPE reduced wear, titanium reduced stress shielding. Future: Bone-matched modulus materials may further improve long-term outcomes.
Guidelines, Registries & Global Practice
Standards, Societies and Global Consensus
Stress-strain behaviour is examined as core basic science across fellowship curricula worldwide. Implant materials are governed by international standards rather than country-specific guidance, and the underlying mechanics are universal.
- Scope
- Implant metallic materials (Ti, CoCr, stainless steel)
- Relevance to Stress-Strain
- Defines composition and minimum mechanical properties (yield, UTS)
- Scope
- Ti-6Al-4V ELI, 316L steel, cast CoCr
- Relevance to Stress-Strain
- Standard modulus and strength specifications for implants
- Scope
- Hip stem fatigue testing
- Relevance to Stress-Strain
- Cyclic stress to validate endurance limit
- Scope
- Fixation strategy
- Relevance to Stress-Strain
- Absolute vs relative stability map onto interfragmentary strain
Examiners expect the candidate to move from definition (E = σ/ε) to clinical decision: modulus mismatch causes stress shielding, stress concentration causes implant failure at holes, and interfragmentary strain governs fracture healing. The numbers (steel 200, titanium 110, cortical bone 17 GPa) anchor the discussion.
Related pages: Viscoelasticity for the rate- and time-dependent behaviour this page's linear stress-strain curve deliberately sets aside, and which is what makes bone a different material at impact speed than under a slow bend; Bone Remodeling for the Wolff's-law biology that turns the modulus mismatch quantified here into actual proximal bone loss, and for why that loss plateaus in a way the Weinans simulation does not predict; Stress Concentration for what happens to these stresses at a hole or notch, and for the fatigue notch factor Kf that governs implant life rather than the elastic modulus itself; Fatigue Failure for failure below yield after repeated cycles, which is how implants actually break; Titanium Alloys, Stainless Steel and Cobalt-Chrome Alloys for the three structural moduli tabulated above and the reasons the lowest is not always the right choice; PMMA Bone Cement for the intermediate-modulus layer that Weinans found reduced resorption relative to an uncemented stem of the same alloy; Implant Fracture Biomechanics and Screw Biomechanics for material versus structural stiffness in a real construct - the distinction this page's own section draws; Bone Healing for the tissue differentiation that Perren's strain theory predicts; and Osteoporosis for the disease that the Burstein card shows changes bone quantity and architecture rather than the material properties of the tissue itself.
Controversies and Areas of Uncertainty
How much stress shielding is clinically harmful? Densitometric proximal bone loss is consistently demonstrated around stiff stems, but its true effect on long-term survivorship and revision risk remains debated. Many high-modulus stems perform well for decades, so radiographic stress shielding does not equate to clinical failure.
The "ideal" implant modulus. Bone-matched-modulus implants (porous or composite) are theoretically attractive but risk excessive interface micromotion, fixation failure and unfavourable strain distribution. The optimal trade-off between low modulus (less shielding) and adequate stiffness (stable fixation) is unresolved.
Validity of the 0.2% offset yield for biological tissue. The offset definition is a metallurgical convention. Bone and soft tissue are viscoelastic and anisotropic, so a single yield value oversimplifies their rate- and direction-dependent behaviour.
Strain thresholds in Perren's theory. The often-quoted strain bands (under 2% for primary healing, over 10% favouring fibrous tissue) are approximate and derived largely from models and animal data. Exact human thresholds and the role of dynamic versus static strain are still being refined.
Translating bench data to in vivo. Quoted modulus and strength values come from standardised specimens. Real implants experience complex multiaxial, cyclic loading, corrosion and biological interfaces that bench tests only partly capture.
Q: What does elastic modulus (Young's modulus) measure? A: Stiffness - resistance to elastic deformation. E = σ / ε (stress divided by strain). Units: GPa. High modulus = stiff (small deformation for given stress). NOT the same as strength.
Q: What is the formula for stress? A: Stress (σ) = Force / Area (units: Pa, MPa, GPa). Describes intensity of internal forces. Tensile stress is positive (pulling), compressive stress is negative (pushing).
Q: What is the significance of the yield point on a stress-strain curve? A: Transition from elastic (reversible) to plastic (permanent) deformation. Below yield: material returns to original shape when unloaded. Above yield: permanent deformation occurs. Defined at 0.2% offset for metals.
Q: What causes stress shielding in THA? A: Modulus mismatch - metal stem (110-240 GPa) much stiffer than bone (17 GPa). Stem carries majority of load, proximal bone experiences reduced stress, Wolff's law causes bone resorption and osteopenia.
Q: What is a stress concentration factor? A: Ratio of local maximum stress to average stress at a geometric discontinuity (hole, notch, corner). Typical value for circular hole is 3. Explains why cracks initiate at screw holes in plates.
MCQ Practice Points
Q: What is the difference between stress, strain, and Young's modulus?
A: Stress (σ): Force per unit area (F/A), units MPa or GPa. Strain (ε): Change in length divided by original length (ΔL/L), dimensionless (or %). Young's modulus (E): Ratio of stress to strain (E = σ/ε), measures stiffness. High modulus = stiff material, small deformation for given stress.
Q: What are the regions of a typical stress-strain curve for a ductile material?
A: (1) Elastic region: Linear, reversible deformation, Hooke's law applies (σ = Eε). (2) Yield point: Transition to plastic deformation (0.2% offset definition). (3) Plastic region: Permanent deformation, strain hardening. (4) Ultimate tensile strength (UTS): Maximum stress. (5) Fracture point: Material failure. Area under curve = toughness (energy absorption).
Q: What is the clinical significance of elastic modulus mismatch in orthopaedic implants?
A: Modulus mismatch causes stress shielding. Cortical bone: ~17-20 GPa. Titanium: ~110 GPa. CoCr: ~210 GPa. Stainless steel: ~200 GPa. Stiffer implant carries more load, bone experiences reduced stress, Wolff's law causes bone resorption. Ti preferred for uncemented stems (closer modulus to bone). PMMA (~2-3 GPa) provides gradual load transfer.
Q: What is the difference between ductile and brittle materials?
A: Ductile materials (metals): Large plastic deformation before failure, stress-strain curve shows plateau, high toughness, "warning" before failure (bending). Brittle materials (ceramics, PMMA): Minimal plastic deformation, sudden catastrophic failure, low toughness, high strength in compression but weak in tension. Bone is relatively brittle compared to metals.
Q: What is stress concentration and why is it important in implant design?
A: Stress concentration is local amplification of stress at geometric discontinuities (holes, notches, corners, thread roots). Stress concentration factor (K) = local stress / average stress. For circular hole: K approximately 3. Clinical relevance: Plates fail at screw holes (stress risers), fractures initiate at implant corners. Reduce via smooth transitions, avoiding sharp corners.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“Examiner shows stress-strain curve and asks: Explain the regions of this curve and define elastic modulus.”
“A patient has proximal bone loss around a cemented femoral stem 5 years after THA. Explain the biomechanical mechanism.”
“Why do fracture fixation plates tend to break at screw holes rather than between holes?”
Fundamental Definitions
- Stress (σ): Force / Area, units: Pa, MPa, GPa (N/m²)
- Strain (ε): ΔL / L₀, dimensionless or %, relative deformation
- Elastic modulus (E): σ / ε, stiffness, units: GPa
- Hooke's law: σ = E × ε (elastic region only)
Elastic Modulus Values
- Cobalt-chrome: 210-240 GPa (very stiff)
- Stainless steel 316L: 200 GPa (stiff)
- Titanium Ti-6Al-4V: 110 GPa (moderately stiff)
- Cortical bone: 17 GPa (moderate)
- PMMA cement: 2-3 GPa (low)
- Cancellous bone: 0.1-1 GPa (very low)
- Articular cartilage: 10 MPa = 0.01 GPa (very compliant)
Stress-Strain Curve Regions
- 1. Elastic: Linear, reversible, slope = E, follows Hooke's law
- 2. Yield: Transition to permanent deformation, 0.2% offset definition
- 3. Plastic: Permanent deformation, work hardening, strain increases faster
- 4. Ultimate tensile strength: Peak stress, maximum load capacity
- 5. Fracture: Complete failure, ductile (necking) vs brittle (sudden)
Ductile vs Brittle
- Ductile: Large plastic deformation (greater than 5%), yields before fracture (warning)
- Brittle: Minimal plastic deformation (less than 1%), sudden fracture (no warning)
- Ductile fracture: Cup-and-cone, fibrous appearance
- Brittle fracture: Flat, crystalline appearance
- Clinical: Ductile preferred (safety), brittle avoided (catastrophic)
Key Concepts
- Stiffness (E) and strength (σ_UTS) are independent properties
- High E does not mean high strength (e.g., ceramics stiff but brittle)
- Stress concentration: Local stress at notches/holes exceeds average stress
- Stress concentration factor: Local stress / average stress (typically 3 for holes)
- Explains crack initiation at screw holes in plates
Stress Shielding
- Metal implant (110-240 GPa) much stiffer than bone (17 GPa)
- Stiff implant carries majority of load for given deformation
- Proximal bone experiences reduced stress
- Wolff's law: Bone remodels to loading, reduced stress causes resorption
- 20-40% proximal bone loss common with stiff stems (Gruen zone 7)
- Mitigation: Titanium (110 GPa), flexible design, porous proximal coating
Mechanical Testing
- Tensile test: Dog-bone specimen, constant strain rate, plot σ vs ε
- Compression test: Similar but compressive loading, specimen bulges
- Four-point bending: For brittle materials, avoids gripping stress
- Properties measured: E, σ_y, σ_UTS, ductility (% elongation)
Evidence Base and Research
Titanium Alloys in Total Joint Replacement
- Titanium alloys offer lower elastic modulus, superior biocompatibility, and better corrosion resistance than stainless steel and cobalt-based alloys
- Metastable beta titanium alloys can reach reduced modulus with superior strain-controlled and notch fatigue resistance
- Poor shear strength and wear resistance limit titanium use as bearing surfaces
- Lower modulus narrows but does not eliminate the gap with bone (cortical bone ~17 GPa)