Antibiotic timing 30-60 min | Chlorhexidine-alcohol prep | MRSA decolonisation | Normothermia & glycaemic control | Bundle compliance
- Antibiotic prophylaxis in the 2 hours before incision gave the lowest infection rate in Classen's cohort (0.6 per cent); giving it too EARLY was as bad as giving it late
- Chlorhexidine-alcohol skin prep gave a 41 per cent relative reduction in SSI versus povidone-iodine (Darouiche), though in clean-contaminated rather than clean implant surgery
- MRSA decolonisation reduced S. aureus SSI by 61 per cent, and the carrier-targeted bundle reduced Gram-positive SSI by 59 per cent (Schweizer)
- Normothermia reduced wound infection from 19 to 6 per cent in Kurz's colorectal RCT - a large effect, but extrapolated to orthopaedics
- Glycaemic control matters even without diabetes: sustained hyperglycaemia gave OR 4.9 for 30-day SSI in orthopaedic trauma (Richards)
- “Never use a razor for hair removal - shaving creates microabrasions that raise infection risk; clip, and only if hair genuinely obstructs
- “Single-dose prophylaxis is sufficient for most cases; continuing beyond 24 hours drives resistance without reducing infection
- “Surveillance runs to 90 days for implant surgery against 30 days without an implant, for deep and organ/space SSI
- “Operative duration is an independent risk factor - the longer the case, the higher the risk, and it is one of the few intra-operative factors the surgeon directly controls
Surgical Site Infection Prevention (Perioperative)
SSI prevention is a high-yield exam topic. Examiners expect knowledge of evidence-based bundles, Australian antibiotic guidelines (TG), timing of prophylaxis, skin preparation agents, and specific considerations for implant surgery. Know the differences between clean, clean-contaminated, and contaminated wounds and their prophylaxis requirements.
Definitions and Classification
Depth. The CDC classifies a surgical site infection by the deepest layer it reaches, and the definition fixes how long a unit must keep watching. The classification drives surveillance, benchmarking and quality improvement, and deep and organ/space infections carry significantly higher morbidity and cost.
- Superficial incisional - within 30 days, skin and subcutaneous tissue only, with at least one of purulent drainage, organisms on culture, or signs of infection (pain, swelling, redness, heat), or a wound deliberately opened by the surgeon (unless culture negative)
- Deep incisional - within 30 days, or 90 days if an implant is present; involves fascia and muscle, with purulent drainage from the deep space, dehiscence, or an abscess or infection seen on imaging or re-exploration. It is the most concerning in orthopaedics because of implant involvement
- Organ/space - any anatomical structure opened or manipulated at surgery: septic arthritis, osteomyelitis, epidural abscess, and in orthopaedics prosthetic joint and spinal implant infection. It has the highest morbidity and often requires implant removal
Wound class. The second axis is how contaminated the wound was at operation. The class must be documented intra-operatively, because it determines antibiotic duration and SSI surveillance.
- Definition
- Elective, non-traumatic, no GI/GU/respiratory entry
- SSI rate
- 1-3%
- Orthopaedic examples
- THA, TKA, spinal fusion
- Definition
- Controlled entry to GI/GU/respiratory tract
- SSI rate
- 5-10%
- Orthopaedic examples
- Spine with intradural pathology
- Definition
- Open traumatic wound (less than 4 hours) or a major break in sterile technique
- SSI rate
- 10-15%
- Orthopaedic examples
- Open fracture Grade 1-2
- Definition
- Established infection, devitalised tissue
- SSI rate
- 15-40%
- Orthopaedic examples
- Open fracture Grade 3, debridement for osteomyelitis
Prophylaxis by class. The class sets what the antibiotic is for:
- Class I - a single dose of cefazolin is standard
- Class II - a single dose, which may add anaerobic cover
- Class III - extended prophylaxis for 24-72 hours
- Class IV - therapeutic antibiotics, which are treatment rather than prophylaxis
Epidemiology and Risk Factors
The patient. Some risk is fixed and some can be changed before an elective operation, which is where most of the prevention effort goes.
- Non-modifiable - age (over 65 increases risk 1.5-2 times, and the very young are also at risk), male sex (slightly higher risk), and genetic variants of immune function
- Diabetes - poor control is the most significant, an HbA1c over 8%
- Obesity - BMI over 30, with risk rising 2-3 times per 5-unit increase
- Smoking - relative risk 1.5-3 times, and impaired wound healing
- Malnutrition - albumin under 35 g/L, pre-albumin under 18 mg/dL
- Immunosuppression - steroids, chemotherapy, biologics
- Anaemia - haemoglobin under 110 g/L
- Remote infection - urinary tract, skin, dental abscess
- Other comorbidities - renal, hepatic and cardiac disease
The operation. Duration is among the most important surgical factors the surgeon can change, which makes efficient technique and adequate staffing part of infection control: each hour increases risk 1.5 times. Contaminated wounds carry 10-15 times the risk of clean ones, revision surgery 2-4 times (scarring, altered anatomy, retained organisms) and emergency surgery 2-3 times, since there is no opportunity to optimise beforehand. Implants add foreign material on which biofilm forms, and greater tissue trauma adds risk, minimally invasive surgery being lower risk.
Technique and environment. Surgical skill has a learning-curve effect. A haematoma increases SSI risk 3-fold, and seromas and other collections in unmanaged dead space, and devitalised tissue from rough handling add to it. In the theatre, each additional person raises bacterial counts, flash sterilisation increases risk, and team turnover during the case counts against it; the effect of laminar-flow ventilation is debated (see Theatre Environment).
The implant. Rougher surfaces carry a higher biofilm risk, there is some evidence that titanium carries a lower risk than stainless steel, and more hardware means more surface area. Antibiotic-loaded cement reduces risk in arthroplasty.
The institution. Higher surgical volume generally goes with lower SSI rates; academic versus community hospitals vary with case mix. What moves the rate at hospital level:
- Resources - nursing ratios, infection control programmes, a culture of safety and quality improvement
- Process - compliance with prophylaxis bundles, surveillance with feedback, surgeon-specific outcome reporting, multidisciplinary SSI prevention teams
- Infrastructure - appropriate air exchanges, laminar flow for implant surgery, well-maintained sterilisation equipment, dedicated orthopaedic theatres rather than shared facilities
- Quality improvement - regular audit and feedback, root cause analysis of infections, standardised protocols and checklists, staff education, patient engagement
Australian hospitals are increasingly adopting comprehensive SSI prevention bundles as part of quality and safety frameworks, and the National Safety and Quality Health Service (NSQHS) Standards specifically address infection prevention and control.
Pre-operative Optimisation
Glycaemic control. Hyperglycaemia is one of the most important modifiable risk factors, and glycaemic control is perhaps the single most modifiable factor with the strongest evidence base across all surgical specialties; in diabetics it is the most impactful. Every 1% rise in HbA1c above 7% increases SSI risk by approximately 20%.
- Measure HbA1c; the target for elective surgery is under 7%
- Consider delaying non-urgent surgery if HbA1c is over 8%
- Review and optimise diabetic medication, with endocrinology input for poorly controlled diabetes
Smoking. Smoking increases SSI risk 1.5-3 fold. Nicotine causes vasoconstriction and reduces tissue perfusion, carbon monoxide occupies haemoglobin and reduces oxygen delivery, neutrophil function is impaired, and epithelialisation and collagen synthesis are delayed. Recovery after stopping follows a timeline:
- 24 hours - COHb normalises and oxygen delivery improves
- 48-72 hours - nicotine effects diminish and ciliary function returns
- 2 weeks - circulation and lung function improve
- 4 weeks - wound complication risk starts to fall; cessation for 4 weeks reduces complications by 50%
- 8 weeks - optimal risk reduction, approaching non-smoker levels
Stopping for a minimum of 4 weeks gives meaningful risk reduction and 8 weeks is ideal. Brief perioperative cessation of less than 2 weeks may paradoxically increase risk through the stress response. Nicotine replacement is acceptable, since its peripheral effects are less harmful, though nicotine products are best avoided immediately perioperatively if possible.
Getting a smoker to stop. Address smoking at the surgical decision, not at the pre-admission clinic when there is little time left to intervene. Refer to cessation services immediately, document cessation in the pre-operative assessment, educate on the risks and benefits, and consider delaying elective surgery. Behavioural support increases success rates; the options are structured telephone or behavioural counselling, nicotine replacement, general practitioner management plans and pre-admission clinic cessation programmes.
Nutrition. Malnutrition significantly increases SSI risk and impairs wound healing. The difficulty is identifying at-risk patients early enough to intervene, and routine albumin screening at pre-operative assessment identifies many who would otherwise be missed.
- Albumin - target over 35 g/L; below it, SSI risk rises 2-3 times
- Pre-albumin - target over 18 mg/dL (shorter half-life); under 15 mg/dL indicates severe malnutrition
- Transferrin under 200 mg/dL suggests protein depletion; a lymphocyte count under 1500 indicates immune compromise
- BMI under 18.5 is malnutrition; unintentional weight loss of more than 10% in 6 months counts
- Dietary intake assessment by food record or nutritionist review
Look for it in the elderly (higher prevalence), cancer patients (cachexia), inflammatory arthritis (chronic disease malnutrition) and revision patients (chronic illness, previous complications). Treatment is protein supplementation at 1.5-2.0 g/kg/day, high-calorie supplements, micronutrients (vitamin C, zinc, vitamin A) and enteral nutrition if oral intake cannot meet needs, for a minimum of 7-14 days before surgery. Oral supplements reduce complications by 30-50% in malnourished surgical patients, with less SSI, better wound healing, shorter stay and lower mortality. In high-income settings this runs through dietitian referral at the pre-admission clinic and a multidisciplinary team in major orthopaedic centres.
The rest of the list. Treat remote infections, lose weight before elective procedures if time permits, and hold immunosuppressants when it is safe to do so.
Do not delay urgent or emergency surgery for medical optimization. The benefits of delaying surgery must outweigh the risks of the underlying condition progressing. For trauma and acute infections, proceed with surgery and optimize concurrently.
MRSA screening. MRSA colonisation increases SSI risk 2-9 fold in carriers. Screen universally before high-risk procedures (arthroplasty, spinal instrumentation) with a nasal swab PCR, which gives results in 24 hours, adding throat, perineum and wounds in high-risk patients. Screen at least 1 week before surgery, to leave time for decolonisation.
Decolonisation. For a positive screen:
- Mupirocin 2% nasal ointment to both nares, twice daily for 5 days
- Chlorhexidine 4% body wash daily for 5 days
- Wash bedding and clothing during treatment
- Re-swab after completion to confirm clearance
Povidone-iodine nasal antiseptic is an alternative to mupirocin, chlorhexidine-alcohol body wipes are convenient for inpatients, and recurrent colonisation is treated with an extended 10-day course. The evidence supports decolonisation particularly for MRSA carriers undergoing implant surgery, where it reduces SSI rates by 40-60%.
Effectiveness of a Bundled Intervention of Decolonization and Prophylaxis to Decrease Gram-Positive Surgical Site Infections After Cardiac or Orthopedic Surgery
- 39 studies in cardiac and total joint replacement surgery
- Nasal decolonisation alone reduced S. aureus SSI by 61 per cent (17 studies; pooled RR 0.39, 95% CI 0.31-0.50), and worked whether everyone was decolonised (0.40, 0.29-0.55) or only carriers were (0.36, 0.22-0.57)
- The bundle of decolonisation plus glycopeptide prophylaxis, applied to MRSA carriers only, reduced Gram-positive SSI by 59 per cent (7 studies; RR 0.41, 0.30-0.56)
- CRUCIALLY, glycopeptide prophylaxis cut MRSA infections (RR 0.40, 0.20-0.80) but was a NON-SIGNIFICANT RISK FACTOR for meticillin-SENSITIVE S. aureus infection (RR 1.47, 0.91-2.38) - which is precisely why the glycopeptide is targeted at known carriers rather than given to everyone
Pre-operative bathing. A 4% chlorhexidine gluconate wash the night before and the morning of surgery reduces skin bacterial counts by 90% and may reduce SSI by 30-40% when combined with other measures, with most benefit in implant surgery (arthroplasty, spinal instrumentation). It is a simple intervention with good evidence and minimal risk, and should be standard for all implant surgery.
- Wash the entire body including hair, avoiding eyes, ears and mucous membranes
- Rinse thoroughly, pat dry with a clean towel, and put on clean clothes
Compliance depends on the patient understanding why, access to the product (cost, availability), cultural bathing practices and mobility. Hospitals supply a wash kit at the pre-admission clinic with written and verbal instructions and a demonstration video, confirm compliance as a checklist item on the day, and run an inpatient protocol for those admitted beforehand. Povidone-iodine surgical scrub (less commonly used), plain soap and water (if antiseptic is contraindicated) and commercial bathing wipes are the alternatives. In Australia, chlorhexidine bathing is increasingly included in enhanced recovery protocols for arthroplasty, and some hospitals provide free wash kits to all joint replacement patients, which is cost-effective given what an SSI costs.
Antibiotic Prophylaxis
Timing. The dose is given so that tissue levels are therapeutic when bacteria are inoculated. Given too early, levels decline before wound closure; given too late, bacteria are already established in the wound. The standard window is 30-60 minutes before skin incision, and 60 minutes for vancomycin because of its slow infusion. Classen's cohort (below) shows both arms of the curve: the lowest rate came with prophylaxis in the 2 hours before incision, and doses given 2-24 hours before incision did worst of all.
Agents (eTG / Therapeutic Guidelines). A single dose 30-60 minutes before incision covers most procedures.
- Cefazolin 2 g IV (3 g if weight over 120 kg) - standard for clean orthopaedic surgery
- Flucloxacillin 2 g IV - an alternative, with a narrower spectrum and less resistance pressure
- Vancomycin 15-20 mg/kg IV over 60-90 minutes - if MRSA risk or beta-lactam allergy
- Add gentamicin 4-6 mg/kg IV for contaminated wounds
Re-dosing. Cefazolin has a half-life of about 2 hours and is re-dosed at two half-lives, about 4 hours, in a long procedure. Vancomycin's long half-life (6-8 hours) means most cases need no re-dose, and a single dose of gentamicin is usually sufficient.
- Tourniquet - give the dose before inflation to ensure wound-bed levels; re-dose after release if the tourniquet is applied more than once
- Blood loss - re-dose after significant loss, over 1500 mL
- Revision surgery - broader spectrum may be indicated, case by case
Documentation. Verify on the checklist (WHO surgical safety checklist), record the time of administration, confirm the antibiotic and dose, and document any re-dose in the anaesthetic record.
The Timing of Prophylactic Administration of Antibiotics and the Risk of Surgical-Wound Infection
- 2847 patients undergoing elective clean or clean-contaminated procedures, with timing observed prospectively
- PREOPERATIVE (within 2 hours before incision) gave the lowest rate: 10 of 1708, 0.6 per cent
- PERIOPERATIVE (within 3 hours after incision) gave 1.4 per cent (4/282) - RR 2.4, but NOT statistically significant (P=0.12, 95% CI 0.9-7.9), so this penalty is a trend rather than a demonstrated effect
- POSTOPERATIVE (more than 3 hours after incision) gave 3.3 per cent (16/488; RR 5.8, CI 2.6-12.3)
- EARLY administration 2-24 hours BEFORE incision gave 3.8 per cent (14/369; RR 6.7, CI 2.9-14.7) - the WORST result in the study. The counterintuitive point worth remembering is that giving the antibiotic too early is as harmful as giving it late
Stewardship. Appropriate use prevents SSI while minimising resistance. Use the narrowest effective spectrum, give a single dose for clean surgery (additional doses are rarely beneficial), give no routine post-operative antibiotics, and stop by 24 hours after surgery in most cases. Any extended course needs a documented indication.
Extending prophylaxis. It is controversial and generally not recommended. Retained haematoma and prolonged drains are possible exceptions, though debatable; discuss with infectious diseases before extending, and never extend out of fear or anxiety about infection.
Overuse. It takes four forms: treating colonisation (positive cultures without symptoms of infection), empirical treatment without infection (abnormal results, low-grade fever), extended courses without a clear endpoint, and broad-spectrum cover without culture guidance. The resistance concerns are MRSA rates rising with vancomycin overuse, ESBL organisms, multidrug-resistant Gram-negatives, and Clostridium difficile from broad-spectrum use.
What eTG says. Single-dose cefazolin for clean orthopaedic surgery, discontinued within 24 hours, with the choice guided by local resistance patterns. It does not recommend routine prophylaxis for dental procedures after joint replacement; the question is controversial and decided patient by patient.
Monitoring. Hospital antibiograms, SSI rates stratified by antibiotic choice, C. difficile rates as a marker of overuse, and surgeon-specific feedback. Stewardship needs institutional commitment from pharmacy, infectious diseases and surgeons, and education about resistance is key to changing prescribing culture.
Extended antibiotic prophylaxis (greater than 24 hours post-operatively) for routine clean orthopaedic surgery has no evidence of benefit and contributes to antibiotic resistance. Do not continue antibiotics simply because drains remain in place or out of anxiety about infection. Treat infections, do not prevent them with prolonged antibiotics.
Skin Preparation and Hair Removal
Chlorhexidine-alcohol. 2% chlorhexidine gluconate in 70% isopropyl alcohol is the most effective agent, superior to povidone-iodine in meta-analyses and reducing SSI by about 40% against it. It acts immediately, persists for 6 hours or more, and covers Gram-positive and Gram-negative organisms and fungi. It is first-line for orthopaedic skin preparation under the NSQHS infection prevention standards, and theatres should stock alternatives for contraindications.
Povidone-iodine. 10% solution, or 0.7% iodine with alcohol, is slower (2 minutes to maximal effect), persists for only 1-2 hours, covers spores, and is less effective at reducing SSI. It is the agent when chlorhexidine is contraindicated:
- Allergy
- Mucous membranes, where chlorhexidine causes irritation
- Neuraxial procedures, because of the risk of chlorhexidine neurotoxicity
Keep chlorhexidine away from the eyes and ears, where it risks eye damage and ototoxicity.
Application. Paint from clean to dirty, centrifugally from the incision. Allow 2-3 minutes for antiseptic action and 3 minutes of drying, which is essential for efficacy and for fire prevention: an alcohol-based prep that is still wet when the drapes go on is a fire risk. Do not wipe it off, which removes the residual antiseptic, and do not let it pool in skin folds or under the patient, where it causes chemical burns and is a fire hazard.
Chlorhexidine-Alcohol versus Povidone-Iodine for Surgical-Site Antisepsis
- 849 adults undergoing CLEAN-CONTAMINATED surgery in six hospitals, randomised to chlorhexidine-alcohol scrub or povidone-iodine scrub and paint
- Overall SSI 9.5 per cent with chlorhexidine-alcohol versus 16.1 per cent with povidone-iodine (P=0.004; RR 0.59, 95% CI 0.41-0.85)
- Superficial incisional infection 4.2 versus 8.6 per cent (P=0.008) and deep incisional infection 1 versus 3 per cent (P=0.05)
- ORGAN-SPACE infection was NOT reduced: 4.4 versus 4.5 per cent - the benefit is confined to the incisional layers
- Adverse events were similar in the two groups
Hair removal. Do not remove hair unless it interferes with surgery. If it must go, clip it immediately before surgery, in the holding area or theatre and not the night before, and never shave: a razor increases SSI risk 2-3 times. Its microscopic cuts are portals of entry, the inflammation they cause impairs local immunity, and the longer the interval between shaving and incision, the longer the bacteria have to proliferate and the higher the risk. The move from routine shaving to selective clipping has significantly reduced SSI rates in orthopaedic surgery, and it is a simple, low-cost intervention with strong evidence.
Clipping. Use electric clippers with single-use disposable heads, clip in the direction of hair growth, and use minimal pressure to avoid skin irritation. Depilatory creams carry a lower SSI risk than razors, similar to clipping, but need 10-15 minutes of application, can irritate or sensitise the skin, and are not commonly used in orthopaedics for want of time.
By site. In spine surgery the areas are large, so consider leaving the hair where possible; hand surgery usually needs no removal; hip arthroplasty needs minimal clipping of the surgical site only. Patients who prefer to shave beforehand should be told the evidence against it.
Theatre Environment
Standard ventilation. At least 15 air changes per hour (Australian Standard AS 1668), positive pressure relative to the corridors, HEPA (high-efficiency particulate air) filtration, a filtered, temperature-controlled supply, and humidity of 30-60%.
Laminar flow. Unidirectional airflow over the surgical field at 300-400 air changes per hour in the laminar zone gives ultra-clean air of fewer than 10 colony-forming units per cubic metre, reducing airborne bacteria by 90-99% against conventional ventilation. It is recommended for arthroplasty and spinal instrumentation.
The laminar-flow debate. Some studies show an SSI reduction and others no benefit. The benefit is clearest in total joint arthroplasty in older studies and may be overcome by modern prophylaxis bundles. Swedish data suggest benefit, and laminar flow is mandatory for arthroplasty there; UK data are mixed, the SPARE trial showing no benefit with modern prophylaxis. Laminar flow is not mandated but is common in dedicated arthroplasty theatres, with increasing use in public and private joint replacement centres; AS/NZS 1668 and AS/NZS ISO 14644 set the ventilation standards. Consensus supports it for high-risk implant surgery as part of comprehensive infection prevention, despite the mixed evidence.
Traffic. Bacterial counts rise 10-35% with each additional person in theatre, and high-traffic cases (teaching, complex cases with several teams) have a higher SSI risk. Each door opening raises counts, disrupts laminar flow and changes the pressure gradient.
- Keep doors closed except for essential entry and exit; use pass-through windows for supplies where possible
- Keep only essential staff in the room and standardise who may enter (credentials, need-to-know); restrict entry, exit and movement during critical periods such as implant insertion, when non-essential personnel should leave
- Limit conversation over the sterile field and do not talk directly over an open wound
- Masks reduce but do not eliminate droplet dispersal: turn away to cough or sneeze and replace a wet mask, which filters less well
Attire. Appropriate surgical attire for everyone in the room: a head covering over all the hair, a mask covering nose and mouth completely, no jewellery, watches or artificial nails, and dedicated theatre shoes not worn outside the suite.
Enforcement. The circulating nurse monitors compliance, every team member is empowered to speak up about a break in sterile technique, and the surgeon leads, backed by regular education and audit of theatre discipline. The cultural change is challenging but essential.
The "sterile cockpit" concept borrowed from aviation safety means during critical phases of surgery (implant insertion, bone grafting, wound closure), all non-essential activity ceases - no phone calls, no teaching conversations, no equipment handoffs. This reduces distractions and contamination risk. Some Australian hospitals use it during implant insertion and wound closure, with no entry or exit, no talking and minimal movement.
Sterile Technique and Draping
Surgical hand preparation. An alcohol-based rub is preferred and recommended by WHO and CDC: it gives superior antisepsis to a traditional scrub, is faster, irritates the skin less and needs no water. Most Australian hospitals now use rubs as the primary method with scrub solution as backup, and AS 4815-2001 defines the requirements for surgical hand preparation.
- Rub - 60-80% alcohol with emollients and an antiseptic (chlorhexidine or povidone-iodine), 2-3 mL applied to dry hands and forearms and rubbed until completely dry (2-3 minutes)
- Scrub - chlorhexidine 4% or povidone-iodine 7.5% for 2-6 minutes (first case of the day versus subsequent), systematic washing of hands and forearms, nails cleaned for the first case only to avoid damaging the nail beds, rinsing with the hands higher than the elbows so water flows distally, and drying with a sterile towel, hands first and then forearms
The common errors are rushing, missing the nail beds and interdigital spaces, contaminating scrubbed hands on the tap or by splashes, and gowning before the hands are dry.
Gloving. Double gloving is recommended for implant surgery because it reduces exposure through perforations. Use closed gloving for the first pair, change the outer gloves if contaminated or hourly, consider indicator systems that show perforations, and consider thicker, more puncture-resistant orthopaedic gloves.
Draping. Drape from clean (the operative site) to dirty (the periphery), covering the area closest to the anaesthetist first, without reaching over unsterile areas. A drape once placed is not moved: if it is malpositioned, remove it and use a new sterile drape. Secure drapes with adhesive, towel clips or staples so they cannot shift, and cover extremities first with a waterproof stockinette below the tourniquet, impervious to strike-through and secured at both ends. Hip arthroplasty may use full-body or extremity drapes, spine needs expansive draping for multiple levels and possible extension, and trauma needs a wide field for incision flexibility.
Incise drapes. Plain or iodine-impregnated plastic adhesive drapes are applied over dry, prepared skin and incised through. Their efficacy is controversial: plain adhesive drapes may increase SSI risk through skin maceration, and iodine-impregnated drapes, which may be better than plain, show no clear benefit but no harm. Many surgeons still use them for the perceived benefits of isolating the skin edge and keeping sponges off the skin. If used, they must adhere completely, without wrinkles or lifted edges.
Keeping the field sterile. Only sterile items touch the sterile field, an unsterile person stays at least 30 cm away, and a contaminated drape or item is replaced. The scrub nurse or technician watches the field throughout the case.
Normothermia and Intra-operative Glycaemic Control
Normothermia. Warm the patient from before the operation and keep core temperature above 36°C throughout it. Kurz's trial (below) is the landmark evidence.
Intra-operative glucose. Target 6-10 mmol/L perioperatively, monitoring diabetics more often (every 2-4 hours), with insulin infusion protocols for major surgery. Avoid hypoglycaemia: a glucose under 4 mmol/L increases complications. Each 1 mmol/L increase in perioperative glucose above 6.1 mmol/L increases SSI risk by 20%. Tight control (under 8 mmol/L) reduces deep SSI by 50%, and the benefit is seen in patients with and without diabetes.
The eTG protocol for diabetics.
- Continue long-acting insulin, reduced by 20-25%
- Hold short-acting insulin on the day of surgery
- Use a variable-rate insulin infusion for prolonged fasting
- Resume the normal regimen once eating and drinking, adjusting on frequent glucose checks
Perioperative Normothermia to Reduce the Incidence of Surgical-Wound Infection and Shorten Hospitalization
- 200 patients undergoing colorectal surgery randomised to routine thermal care or additional warming, with surgeons blinded to allocation
- Final intra-operative core temperature 34.7 degrees in the hypothermia group versus 36.6 in the normothermia group
- Surgical-wound infection in 18 of 96 (19 per cent) with hypothermia versus 6 of 104 (6 per cent) with normothermia, P=0.009
- Sutures were removed a day later and hospitalisation was prolonged by 2.6 days (about 20 per cent) in the hypothermia group
- The proposed mechanism is thermoregulatory vasoconstriction reducing subcutaneous oxygen tension, impairing neutrophil oxidative killing and collagen deposition
Surgical Technique and Closure
Tissue handling. Minimise trauma with gentle retraction and appropriate instruments, preserve the blood supply by avoiding excessive periosteal stripping, do not crush soft tissue in clamps, limit electrocautery, which devitalises tissue, and irrigate regularly to remove debris and bacteria. These factors are surgeon-controlled and are major opportunities to reduce SSI risk.
Haemostasis. Achieve meticulous haemostasis before closure, using cautery, topical agents and tourniquet timing. Tranexamic acid reduces bleeding and transfusion.
Dead space. Eliminate it where possible with a layered closure and by tacking soft tissue to bone, so that fluid cannot accumulate.
Irrigation. Irrigate copiously before closure (3-9 litres for arthroplasty), with a final irrigation after implant insertion, and remove all the fluid before closing. Normal saline is standard and is equal to antibiotic or antiseptic irrigation. Pulse lavage may increase soft-tissue damage, so low pressure is preferred.
Dilute povidone-iodine lavage. A specific, low-cost bundle adjunct: the wound is irrigated with dilute aqueous povidone-iodine before closure to reduce the bacterial load at the moment of closure, then rinsed out with saline. Full-strength or alcohol-based povidone-iodine is cytotoxic to chondrocytes and osteoblasts and must never be poured into an open wound, and the lavage is avoided in iodine allergy. Some randomised and cohort data, notably in spine and arthroplasty, report reduced SSI/PJI, but the results are heterogeneous, so it is an adjunct within the bundle and never a substitute for correctly timed systemic prophylaxis.
A dilute aqueous povidone-iodine lavage (about 0.35%, roughly 3 minutes, then rinse) before closure is a cheap adjunct that lowers wound bacterial load. Keep it dilute and aqueous - full-strength or alcoholic povidone-iodine is cytotoxic and unsafe in an open wound - and remember the SSI/PJI evidence is mixed: it complements, never replaces, timely weight-adjusted systemic prophylaxis.
Closure. The goals are to eliminate dead space, approximate the layers precisely, minimise tension on the wound edges and protect the wound from contamination. Layered closure reduces dead-space complications. Use absorbable braided suture (Vicryl, PDS) in the deep fascia, which needs no removal, close the subcutaneous layer to eliminate dead space and reduce tension, and avoid permanent sutures deep, which cause a foreign-body reaction. Monofilament is used for skin, with lower infection than braided.
The skin. Subcuticular closure leaves no suture tracts and has the lowest SSI risk; multiple RCTs show it reduces SSI compared with staples. Skin adhesive or strips add support.
- Advantages
- No suture tracts, cosmesis
- SSI Considerations
- Lowest SSI risk
- Advantages
- Fast, cost-effective
- SSI Considerations
- Higher SSI than subcuticular
- Advantages
- Strong, adjustable tension
- SSI Considerations
- Suture tract risk
Drains. A drain may reduce haematoma but is a portal for bacterial entry, and meta-analyses show no clear SSI benefit and possible harm with prolonged use. Many surgeons have eliminated drains for routine arthroplasty, and the trend in clean cases is towards no drain, tranexamic acid to reduce bleeding and meticulous technique to eliminate dead space. Consider one for:
- Extensive soft-tissue dissection, as in revision arthroplasty
- Bleeding diathesis or anticoagulation
- A large dead space that cannot be eliminated
- Two-stage revision for infection (debridement and spacer)
Wound drains are controversial for SSI prevention. While they remove potential fluid collections, they provide a portal for bacterial entry. If used, employ closed suction drains, use strict aseptic technique for management, and remove within 24-48 hours. Never use drains in clean cases without significant dead space.
Managing a drain. Use a closed suction system only (no open drains in clean orthopaedic surgery), keep suction on at all times and empty the reservoir when it is two-thirds full, using clean gloves and a no-touch technique. Secure the drain with a suture or adhesive and monitor the volume and character of the output. Remove it early, at 24-48 hours, or when output falls below 30-50 mL per 24 hours in some protocols; the balance is between preventing haematoma and closing an infection portal, and nothing supports drainage beyond 48 hours. To remove it, release the suction first, which reduces pain and prevents tissue injury, clean the site with antiseptic, withdraw it in one smooth motion, apply an occlusive dressing and watch the site for leakage or infection.
Wound Healing
The phases of healing set the timing of the post-operative wound rules.
- Haemostasis (immediate, minutes to hours) - platelet aggregation and clot formation, vasoconstriction followed by vasodilation, growth factor release; its SSI relevance is haematoma
- Inflammation (days 1-4) - neutrophil and macrophage infiltration, debris removal and bacterial killing; the immune response is critical and the phase should not be disrupted
- Proliferation (days 4-21) - fibroblast migration and collagen synthesis, angiogenesis and granulation tissue; epithelialisation begins at 48-72 hours, and the wound needs protection
- Remodelling (weeks to months) - collagen reorganisation, reaching maximum strength of about 80% of normal at 6-12 weeks, with scar maturation continuing for 1-2 years; late infection is still possible
What impairs healing. Locally, infection, ischaemia, haematoma and tension; systemically, diabetes, smoking, malnutrition and steroids; and among medications, NSAIDs, chemotherapy and anticoagulants. The modifiable ones are optimised before surgery, and the wound is disturbed as little as possible during the inflammatory phase.
Post-operative Prevention
The first dressing. The dressing is the first line of defence after surgery. Apply a sterile, absorbent, occlusive dressing with a waterproof outer layer in theatre before the drapes come down, secure but not constrictive, to avoid a tourniquet effect. Leave it intact for at least 48-72 hours, the epithelialisation period, during which a waterproof dressing prevents bacterial ingress.
Changing it. Each change is a contamination risk, so change it only when needed: visible saturation or strike-through, odour, soiling with blood or drainage, a patient reporting wetness or loosening, or a dressing that is no longer adherent. Use strict aseptic technique (clean gloves, antiseptic) and document the appearance each time (drainage, erythema, oedema).
Negative pressure wound therapy. Increasingly used for high-risk wounds, NPWT maintains a clean, moist environment, reduces oedema and promotes healing. It may reduce SSI in high-risk patients (obesity, diabetes, revision), the evidence being strongest in trauma and high BMI. Prophylactic use typically runs 5-7 days, and it is expensive compared with a standard dressing.
Showering. Keep the wound dry for 48-72 hours; after epithelialisation, brief showers are allowed without soaking, patting the wound dry immediately. Some protocols allow showering from day 1 under a waterproof dressing. No swimming or bathing until the wound is fully healed, a minimum of 2-3 weeks.
Sutures and staples. Removal timing depends on the site and the patient:
- Upper limb - 10-14 days
- Lower limb - 14-21 days (higher tension, slower healing)
- Spine - 14-21 days
- Earlier in children (faster healing) or when there are complications; later in the elderly, diabetics and smokers (slower healing), or when healing is delayed
Clean the wound with antiseptic and remove alternate sutures or staples first to test the wound; if the edges separate, stop and leave the rest. Apply adhesive strips for support for 7-10 days and a simple dressing for 24-48 hours. Signs of superficial infection may need earlier removal to allow drainage, and a suture abscess is treated by removing the suture, culturing and treating the infection. Once healed, the wound is protected from trauma and excessive moisture, the scar can be managed with massage and silicone sheets, and late dehiscence is rare but serious.
Absorbable subcuticular sutures. They need no removal, support the wound for 4-6 weeks as they absorb, may reduce SSI risk because there are no suture tracts, save the patient a visit and the discomfort of removal, but cost more than staples or nylon.
Post-operative glucose. Hyperglycaemia after surgery increases SSI risk even in non-diabetics, from the stress response (cortisol, catecholamines). It is more common after major surgery, long cases and significant trauma, and usually resolves as the stress response settles over 48-72 hours. A glucose over 10 mmol/L doubles SSI risk, and each 1 mmol/L above 6 mmol/L increases risk by 10-20%; the benefit of control is seen with and without diabetes. It is an often-overlooked part of prevention, with strong evidence, and easily modified with the right protocol.
- Targets - under 10 mmol/L for the first 48 hours in all patients; 6-10 mmol/L in diabetics; avoid hypoglycaemia under 4 mmol/L
- Monitoring - point-of-care fingerstick glucose at least 6-hourly for the first 24-48 hours after major surgery, and 2-4-hourly in diabetics or on an insulin infusion, for a minimum of 48 hours and until the patient is eating normally and glucose is stable
- Treatment - treat glucose over 10 mmol/L even in non-diabetics; a variable-rate insulin infusion gives proactive, better control for major surgery, whereas a sliding scale is reactive and less ideal; resume home medications once oral intake is tolerated, with endocrinology for difficult cases and diabetes team liaison, and teach the patient how glucose relates to the signs of infection
Many Australian hospitals monitor glucose after major orthopaedic surgery regardless of diabetic status, and standardised insulin protocols improve consistency and safety.
Relationship of Hyperglycemia and Surgical-Site Infection in Orthopaedic Surgery
- 790 orthopaedic trauma patients with isolated injuries and NO history of diabetes; 268 open fractures (33.9 per cent); 21 thirty-day SSIs in total (2.7 per cent)
- Two or more glucose values of 200 mg/dL or more (11.1 mmol/L) occurred in 294 patients (37.2 per cent): SSI in 13 of 294 (4.4 per cent) versus 8 of 496 (1.6 per cent), P=0.02
- A hyperglycaemic index of 1.76 or more (equivalent to 140 mg/dL) occurred in 134 patients (17.0 per cent): SSI in 10 of 134 (7.5 per cent) versus 11 of 656 (1.7 per cent), P<0.001
- On multivariable regression, two or more values above 200 mg/dL gave OR 2.7 (95% CI 1.1-6.7) and a raised hyperglycaemic index gave OR 4.9 (CI 2.0-11.8), each after adjusting for open fracture (itself OR 3.2 and 3.3)
- Age, race, comorbidities, injury severity and blood transfusion were NOT associated with the outcome
The rest of early care. Keep the patient warm, mobilise early when appropriate, and use analgesia that avoids immunosuppressive doses of NSAIDs. Within enhanced recovery (ERAS), early mobilisation reduces complications, multimodal analgesia limits opioid use, early nutrition supports healing, and a shorter hospital stay does not increase SSI.
Patient Education and Follow-up
Why it matters. Arthroplasty patients are often discharged within 1-3 days under enhanced recovery protocols, and most SSIs, 50-70%, present after discharge. That makes education and self-monitoring critical, and the threshold for assessing a worrying wound should be low.
Before surgery. Teach the signs of infection, how to care for the wound and dressing, exactly when to contact the surgeon, why restrictions protecting the wound and limiting activity matter, and the patient's own part in hygiene and taking medication.
At discharge. Give written information in plain language with pictures of normal and infected wounds, a 24-hour contact number, the follow-up schedule, and the red flags that need immediate attention. Beyond the signs in the mnemonic below, pain that increases after initial improvement, chills, malaise and confusion in the elderly are warnings.
WOUND WATCHSSI Warning Signs for Patients
Hook:Tell patients to WATCH their WOUND for these warning signs
Barriers. Health literacy (education, language), cognitive impairment, living alone with little support, and distance or lack of transport all limit what a patient can do. Interpreters, involving family in the teaching, community nursing for wound care, telehealth follow-up for remote patients and simplified written material with pictures address them.
Follow-up. The first visit is at 10-14 days for a wound check and suture removal, the second at 6 weeks for clinical and radiographic assessment, with further visits as symptoms or risk factors dictate and patient-initiated contact whenever there is concern. Surveillance extends to 90 days after implant surgery.
Recognising and Managing SSI
Recognition. The features stack with depth:
- Superficial - erythema more than 1 cm from the wound edge, warmth and tenderness, purulent discharge, dehiscence
- Deep - the superficial signs plus systemic features: fever over 38°C, pain disproportionate to that expected, raised CRP and ESR
- Organ/space - a joint effusion (prosthetic joint infection), a neurological deficit (spinal epidural abscess), a sinus tract, loosening on imaging
- Superficial
- Skin/subcutaneous
- Deep
- Fascia/muscle
- Organ/Space
- Joint/bone
- Superficial
- Usually absent
- Deep
- Often present
- Organ/Space
- Usually present
- Superficial
- Normal/mild rise
- Deep
- Elevated CRP
- Organ/Space
- High CRP/ESR
- Superficial
- Not required
- Deep
- May help
- Organ/Space
- Essential
Red flags. These need urgent action: rapidly spreading erythema (necrotising fasciitis), crepitus (gas-forming organisms), signs of systemic sepsis (hypotension, altered consciousness) and neurological deterioration (spinal infection).
- Distinguishing features
- Purulent drainage, spreading erythema, fever, rising CRP/ESR, positive deep culture
- Management
- Open/debride, culture-directed antibiotics
- Distinguishing features
- Painless fluctuant swelling, serous (clear) fluid, no fever, normal inflammatory markers
- Management
- Observe; aspirate only if symptomatic, avoid repeated aspiration (infection risk)
- Distinguishing features
- Tense swelling, bruising, low-grade pain, may track; risk factor for secondary SSI
- Management
- Observe small; evacuate if large/expanding or compromising closure
- Distinguishing features
- Superficial erythema/warmth without deep collection or purulent drainage
- Management
- Oral antibiotics, mark margins, review for progression
- Distinguishing features
- Well-demarcated erythema/itch under dressing or along suture line, no systemic features
- Management
- Remove offending agent, topical care, antihistamine
- Distinguishing features
- Pain out of proportion, crepitus, dusky skin, rapid spread, systemic toxicity
- Management
- Surgical emergency: urgent debridement, broad-spectrum antibiotics, resuscitation
Investigations. A superficial swab is of limited value because it often grows colonisers; deep tissue culture is the gold standard. Blood tests are an FBC (leucocytosis, left shift), CRP (useful for monitoring), ESR (raised in chronic infection) and blood cultures if there are systemic signs. Fluid collections are aspirated, and 5 or more intra-operative specimens are taken for PJI.
- Best For
- Early detection, monitoring
- Limitations
- Non-specific
- Best For
- Organism identification
- Limitations
- False negatives if on antibiotics
- Best For
- Soft tissue/epidural abscess
- Limitations
- Metal artefact, cost
- Best For
- PJI diagnosis
- Limitations
- Requires lab processing
Imaging. Radiographs show implant loosening, gas and bony change; ultrasound finds fluid collections and guides aspiration; MRI shows soft-tissue involvement and epidural abscess; CT gives detailed bony assessment and localises an abscess.
Diagnosing PJI (MSIS). Any one of:
- Two positive cultures with the same organism
- A sinus tract communicating with the joint
- Three of five minor criteria (ESR/CRP, WBC, PMN%, positive culture, histology)
Stop antibiotics 2 weeks before sampling if it is safe, take multiple specimens to increase sensitivity, and culture for 14 days for slow-growing organisms.
Treatment by depth.
- Superficial - open the wound if purulent, local wound care, oral antibiotics for cellulitis (5-7 days if needed); usually resolves with conservative measures
- Deep, no implant - surgical debridement and IV antibiotics, stepping down to oral as it improves, for 2-4 weeks
- Deep, with implant - DAIR or revision, with antibiotics for 6 weeks to lifelong
DAIR or revision. DAIR (debridement, antibiotics, implant retention, with exchange of modular components) is used for early infection, within 4 weeks of surgery, where its outcomes are best; long-term suppressive antibiotics may be needed afterwards.
- Favours revision
- Chronic infection (greater than 4 weeks)
- Favours revision
- Implant loosening
- Favours revision
- Resistant organisms (MRSA, difficult to treat)
- Favours revision
- Sinus tract formation
Revision options. One-stage (remove, debride and reimplant at one sitting), two-stage (remove, spacer and antibiotics, reimplant at 6-12 weeks), or salvage by arthrodesis, resection arthroplasty or amputation.
Risk-Adjusted Surveillance: The NNIS Risk Index
SSI rates are key surgical quality metrics: they are publicly reported in many jurisdictions and tied to pay-for-performance incentives and hospital accreditation. Raw rates cannot be compared between surgeons or units without risk adjustment, because case-mix differs.
The classic instrument is the NNIS (National Nosocomial Infections Surveillance) risk index (CDC), which scores each operation 0 to 3 by adding one point each for:
- Wound class III or IV (contaminated or dirty/infected)
- ASA physical status 3, 4 or 5 (significant systemic disease) at the time of surgery
- Operative duration beyond the procedure-specific "T-point", the 75th-percentile (upper-quartile) operating time for that procedure
SSI risk rises stepwise with the score, so a unit doing sicker, longer, dirtier cases can be compared fairly against one doing short clean elective lists. The three components are the same three drivers the prevention bundle targets: wound contamination, host physiology and operative duration. A later refinement substitutes endoscope or laparoscope use for some procedures, but the three-component logic is the examinable core.
Prevention Bundles
The idea. A bundle combines several evidence-based interventions for a synergistic effect. Bundles reduce SSI by 40-60% compared with individual interventions (Level 2, multiple studies), and compliance with every element is what matters: partial compliance gives partial benefit, and checklist use improves compliance dramatically.
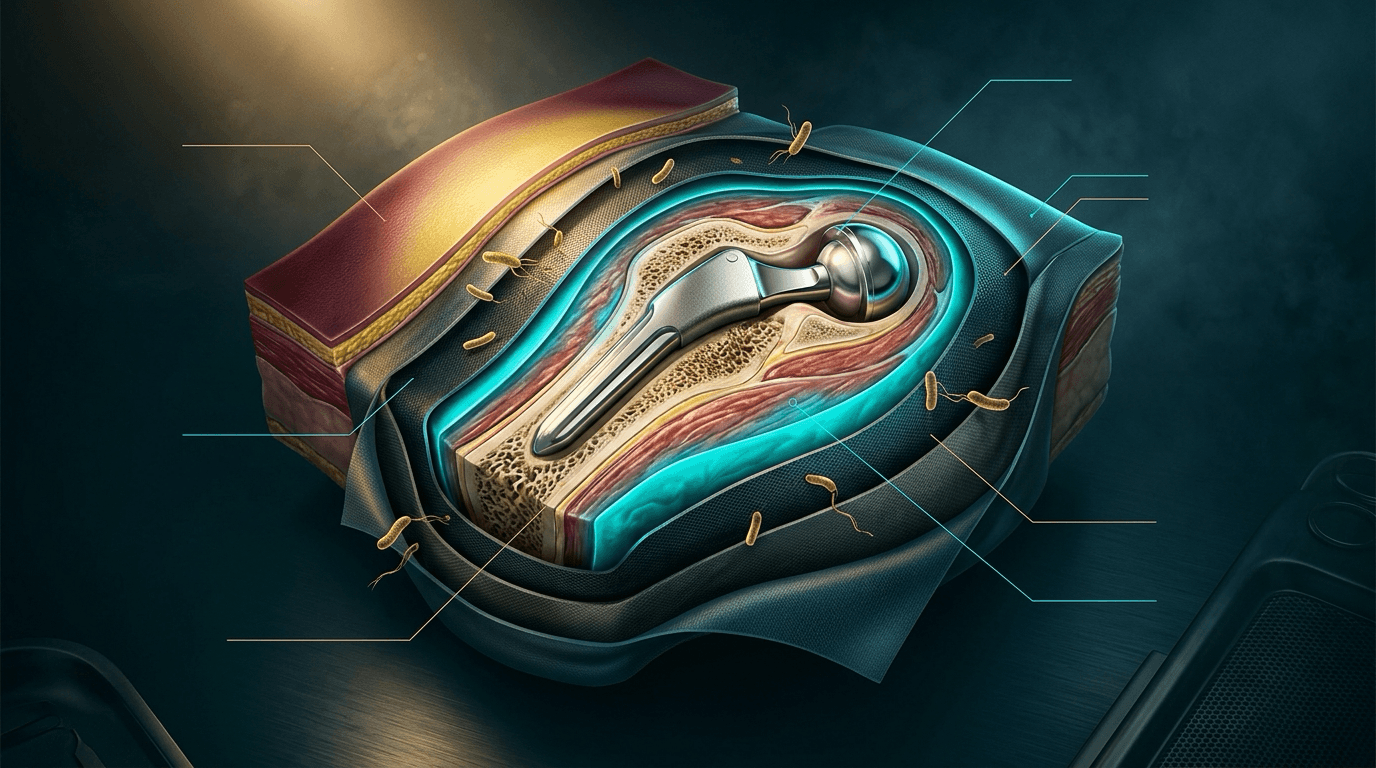
Core bundle.
- Appropriate antibiotic selection and timing (60 minutes pre-incision)
- Glucose control (less than 10 mmol/L perioperatively)
- Normothermia (greater than 36°C intraoperatively)
- Chlorhexidine-alcohol skin preparation
- Appropriate hair removal (clippers, not razors)
- Sterile technique and theatre discipline
Enhanced bundle for implant surgery. 7. MRSA screening and decolonisation 8. Pre-operative chlorhexidine bathing 9. Laminar flow operating theatres 10. Antibiotic-loaded cement (cemented arthroplasty) 11. Intrawound vancomycin (spinal instrumentation) 12. Negative pressure wound therapy (high-risk wounds)
Making it work. Bundles are most effective when built into routine workflow rather than added as extra tasks. They are checklist-driven (the WHO surgical safety checklist plus institution-specific items), need education and buy-in from surgeons, anaesthetists and nurses, are sustained by audit and feedback on compliance and SSI outcomes with continuous improvement (PDSA cycles), and are owned by the whole team rather than surgery alone. Success needs leadership commitment, dedicated resources and sustained effort. Many Australian hospitals have adopted arthroplasty bundles based on international guidelines (AAOS, NICE, CDC), with state-based initiatives tracking compliance and outcomes.
What gets in the way. Complexity, cost (NPWT and laminar flow are expensive), cultural resistance, time pressure before surgery, and unclear ownership of compliance. Compliance with bundles typically varies between 70% and 90%, improvements are hard to sustain, true SSI rates are hard to measure accurately, and patient factors are not fully modifiable.
- evidenceLevel
- Level 1 (RCT, meta-analysis)
- ssirReduction
- 50-70%
- implementation
- Standard, checklist verification
- cost
- Low ($5-20 per case)
- evidenceLevel
- Level 1 (RCT, meta-analysis)
- ssirReduction
- 40-50%
- implementation
- Standard, product availability
- cost
- Low ($10-30 per case)
- evidenceLevel
- Level 2 (cohort studies)
- ssirReduction
- 30-50%
- implementation
- Protocol-driven, monitor compliance
- cost
- Low ($20-50 per case)
- evidenceLevel
- Level 1 (meta-analysis)
- ssirReduction
- 50% vs razors
- implementation
- Education, equipment availability
- cost
- Very low ($2-5 per case)
- evidenceLevel
- Level 1 (RCT, meta-analysis)
- ssirReduction
- 40-60% in carriers
- implementation
- Screening programme, patient compliance
- cost
- Moderate ($50-100 per case screened)
- evidenceLevel
- Level 1 (RCT)
- ssirReduction
- 30-40%
- implementation
- Warming devices, protocol
- cost
- Moderate ($30-100 per case)
- evidenceLevel
- Level 2-3 (observational, mixed results)
- ssirReduction
- 20-50% (variable data)
- implementation
- Infrastructure, capital expense
- cost
- Very high (millions for installation)
- evidenceLevel
- Level 2 (meta-analysis observational)
- ssirReduction
- 50-70%
- implementation
- Surgeon adoption, formulary
- cost
- Low ($10-30 per case)
- evidenceLevel
- Level 2 (RCT in subgroups)
- ssirReduction
- 30-50% in high-risk
- implementation
- Product availability, training
- cost
- High ($200-500 per case)
- evidenceLevel
- Level 1 (RCT, meta-analysis)
- ssirReduction
- 30-50%
- implementation
- Standard in many centres
- cost
- Moderate ($100-300 per case)
Consequences of SSI
For the patient. An SSI means 7-14 additional days in hospital, more operations (debridement, revision), weeks to months of antibiotics, functional impairment and disability, and psychological distress. With an implant, prosthetic joint infection is the most devastating, and infection leads to loosening and failure, chronic osteomyelitis, revision or removal, and limb salvage procedures or amputation.
- Frequency
- 90% of SSIs
- Consequence
- 2-3x hospital costs
- Frequency
- 50-80% of deep SSI
- Consequence
- Additional morbidity
- Frequency
- 30-50% of PJI
- Consequence
- Major revision surgery
- Frequency
- 2-3x increase
- Consequence
- Sepsis, complications
Cost. In additional Australian dollars, a superficial SSI costs $5,000-10,000, a deep SSI $30,000-50,000, and a PJI requiring revision $100,000-200,000, before lost productivity and disability.
Medicolegal. SSI is one of the most commonly litigated surgical complications. Document the prevention measures taken, and include SSI risk in informed consent.
Guidelines, Registries & Global Practice
Global Epidemiology
- SSI is among the most common healthcare-associated infections worldwide and the leading hospital-acquired infection in many low- and middle-income settings, where the pooled cumulative incidence is around 5.6 per 100 surgical procedures, markedly higher than in high-income countries (Allegranzi et al., Lancet 2011).
- Reported orthopaedic SSI rates rise sharply with wound class and implant burden: conventionally quoted as roughly 1-3 per cent for clean elective arthroplasty or fusion, rising to 15-40 per cent for dirty or infected wounds. These bands are the standard teaching figures rather than values from a single cited series, and real rates vary widely with registry, surveillance intensity and follow-up duration.
- Meticillin resistance is a global driver of practice variation: in the small subset of developing-country studies that reported resistance at all (eight studies, 290 isolates), 54 per cent of S. aureus was meticillin-resistant - enough to shape decolonisation and glycopeptide-prophylaxis policy, but too narrow a base to quote as a worldwide prevalence.
Burden of Endemic Health-Care-Associated Infection in Developing Countries: Systematic Review and Meta-Analysis
- 220 studies included from 271 selected, covering publications from 1995 to 2008, funded by the World Health Organization
- Surgical-site infection was the LEADING hospital-acquired infection, pooled cumulative incidence 5.6 per 100 surgical procedures - strikingly higher than proportions recorded in developed countries
- Pooled healthcare-associated infection prevalence in high-quality studies was 15.5 per 100 patients (95% CI 12.6-18.9), much higher than reported from Europe and the USA
- Adult intensive-care infection density was 47.9 per 1000 patient-days (CI 36.7-59.1), at least three times US figures
- Gram-negative bacilli were the commonest isolates; meticillin resistance was found in 158 of 290 S. aureus isolates (54 per cent), but from just EIGHT studies, because very few articles reported resistance at all
Major Guidelines, Side by Side
Core recommendations converge internationally, with the main differences being emphasis (e.g. weight-based vancomycin, glucose targets) rather than direction.
- Antibiotic prophylaxis
- Single pre-incision dose; no prolongation after closure
- Skin prep
- Alcohol-based chlorhexidine (strong)
- Key distinctive points
- Recommends nasal mupirocin +/- CHG for S. aureus carriers in cardiothoracic/orthopaedic; advises against prolonged post-op prophylaxis
- Antibiotic prophylaxis
- Weight-adjusted pre-incision dose; stop after closure for clean/clean-contaminated
- Skin prep
- Alcohol-based agent unless contraindicated
- Key distinctive points
- Perioperative glycaemic target less than ~11.1 mmol/L; maintain normothermia
- Antibiotic prophylaxis
- Single dose at induction; redose for long cases/major blood loss
- Skin prep
- Alcohol-based CHG (or povidone-iodine if contraindicated)
- Key distinctive points
- Do not use razors; consider NPWT and antimicrobial sutures in selected wounds
- Antibiotic prophylaxis
- Cefazolin first-line; vancomycin for MRSA/severe allergy
- Skin prep
- Alcohol-based CHG
- Key distinctive points
- Emphasises MRSA screening/decolonisation and glycaemic control before arthroplasty
- Antibiotic prophylaxis
- Cefazolin 2g (3g if greater than 120 kg); single dose, stop by 24h
- Skin prep
- Chlorhexidine-alcohol first-line (NSQHS Standard 3)
- Key distinctive points
- Mandatory SSI surveillance; antimicrobial stewardship embedded in accreditation
Registry & Surveillance Evidence
National joint registries quantify deep infection as a leading cause of revision and benchmark performance, while national surveillance networks track SSI rates and prophylaxis compliance.
- Role in SSI/PJI
- Tracks revision for infection after hip/knee/shoulder arthroplasty; benchmarks units
- Role in SSI/PJI
- Reports PJI as a major revision indication across large US cohorts
- Role in SSI/PJI
- Reports prosthetic joint infection rates and revision causes by implant and surgeon
- Role in SSI/PJI
- Long-running data on infection-related revision and prophylaxis (e.g. antibiotic cement)
- Role in SSI/PJI
- Population-level SSI rates, prophylaxis-timing and bundle-compliance auditing
Global Practice Variation
- High- vs limited-resource settings: higher baseline SSI rates in low-resource settings reflect supply, sterilisation and surveillance constraints; WHO guidance is deliberately implementable without high-cost infrastructure (e.g. relies on bundles rather than laminar flow).
- Laminar-flow ventilation: retained in many high-income arthroplasty theatres but not universally mandated; benefit is debated once modern bundles are in place.
- MRSA decolonisation: universal vs targeted screening differs by local MRSA prevalence and funding; not uniformly reimbursed.
- Intrawound vancomycin (spine): widely adopted despite predominantly observational evidence, with regional differences driven by stewardship policy.
The world standard of care is a multimodal bundle (correctly timed weight-adjusted prophylaxis, alcohol-based chlorhexidine skin prep, normothermia, glycaemic control, clipping not shaving) plus mandatory SSI surveillance with audit and feedback. Regional differences a candidate may be examined on include MRSA decolonisation policy, laminar-flow use, antibiotic-loaded cement, and intrawound vancomycin in spine surgery.
Special Considerations: Implant Surgery
Arthroplasty. Prosthetic joint infection is catastrophic, so arthroplasty takes the enhanced bundle.
- Before - MRSA screening and decolonisation (universal for arthroplasty); dental clearance, treating active dental infection at least 2 weeks before; no active dermatitis, psoriasis or skin infection; strict glycaemic control, smoking cessation and weight optimisation; albumin over 35 g/L; remote infections (urinary, respiratory, skin) cleared
- During - laminar flow when available; body exhaust suits (controversial, some data support them); double gloving with indicator systems; antibiotic-loaded cement for cemented implants; strict traffic discipline; dilute povidone-iodine lavage (some surgeons use it); extended prophylaxis is controversial and a single dose is usually sufficient
- After - strict wound monitoring for early PJI, glucose under 10 mmol/L for 48 hours, and teaching that PJI can arise years later. Antibiotic prophylaxis for later dental, urological or GI procedures is controversial (see Stewardship)
Antibiotic cement. It reduces early PJI by 30-50% in cemented arthroplasty, with most benefit in high-risk patients (revision, immunosuppression, diabetes). Gentamicin is the commonest agent, being broad-spectrum and heat-stable, and prophylactic rather than therapeutic doses are used because of concern about resistance. Most surgeons use it for cemented primary TKA, there is less consensus for THA (which is more often uncemented), and it is standard in revision.
Spinal instrumentation. Spinal implant infections have devastating consequences. Posterior approaches, multiple levels, long fusions and revision carry higher risk than anterior, single-level, short constructs, and obesity (BMI over 35), diabetes, smoking and immunosuppression add to it. Some surgeons extend prophylaxis to 24 hours for multi-level cases, which is controversial. Prevention adds subfascial drains removed at 24-48 hours, layered closure, NPWT for high-risk wounds (obesity, revision, long fusions), minimal muscle stripping with percutaneous techniques where feasible, meticulous haemostasis, copious irrigation to remove bone debris and bacteria, and a shorter operative time.
Intrawound vancomycin. 1-2 g of powder is applied to the wound before closure, giving a high local concentration without systemic toxicity. Retrospective studies show it reduces SSI by 50-70%, and it has been widely adopted despite a lack of Level 1 or RCT data; its cost is minimal compared with treating an infection. Resistance is a concern that needs monitoring, and some hospitals restrict it on the formulary.
Open fractures. Give antibiotics early, within 1 hour of presentation (the "golden hour"). eTG recommends cefazolin 2 g IV plus gentamicin 4-6 mg/kg IV for Gustilo Grade 2-3, adding benzylpenicillin (penicillin G) for farm injuries or gross contamination to cover clostridia. Continue for 24-72 hours: 24 hours for Grade 1 and 48-72 hours for Grade 2-3; eTG bases the duration on grade and wound condition rather than arbitrary time limits.
Debridement and cover. Irrigation and debridement within 6-12 hours is ideal, though the timing is controversial. Recent evidence suggests that antibiotic administration matters more than debridement timing, that debridement within 24 hours is acceptable if antibiotics are given urgently, and that the historic 6-hour rule is less supported by modern data. Grade 3 injuries return to theatre at 24-48 hours for serial debridement, NPWT reduces infection in Grade 2-3, and delayed closure or early coverage is planned with plastic surgery.
Fixation. External fixation for severe contamination (damage control); early definitive fixation if the soft tissues permit, which reduces infection compared with delay. Antibiotic-coated implants are emerging but not standard. Adjuncts are tranexamic acid (reduces blood loss and may reduce infection), local antibiotic delivery with beads or cement spacers for severe contamination, and bead pouches for temporary elution before second-stage definitive fixation. Open fractures need orthopaedic trauma, plastic surgery and infectious diseases working together.
Effect of Intrawound Vancomycin Application in Spinal Surgery on the Incidence of Surgical Site Infection: a Meta-Analysis
- 27 studies and 17,321 patients - 7,423 treated with vancomycin powder against 9,898 controls
- SSI incidence in the vancomycin groups was 0.39 times that of controls, significant at P<0.01
- The effect held in INSTRUMENTED spinal surgery: OR 0.31 (95% CI 0.19-0.50), P<0.01
- Vancomycin did NOT affect SSI incidence in patients without internal fixation (P=0.17) or undergoing deformity correction (P=0.25) - so the benefit tracks the presence of metalwork
MCQ Practice Points
Q: What is the optimal timing for prophylactic antibiotic administration in orthopaedic surgery?
A: Antibiotics should be administered within 60 minutes before incision (ideally 30-60 minutes). For vancomycin or fluoroquinolones, start infusion 60-120 minutes before incision due to longer infusion times. Goals: achieve adequate tissue levels at time of incision. Redosing required if surgery exceeds 1-2 half-lives of antibiotic (e.g., cefazolin every 3-4 hours) or blood loss exceeds 1500mL. Discontinue within 24 hours postoperatively - extended prophylaxis does not reduce SSI and increases resistance/C. difficile risk.
Q: What is the recommended antibiotic prophylaxis for patients with penicillin allergy undergoing arthroplasty?
A: Depends on allergy severity: Mild penicillin allergy (rash only, no anaphylaxis): Cefazolin is safe (cross-reactivity less than 1% with 1st-generation cephalosporins). Severe/anaphylactic allergy: Vancomycin 15mg/kg (covers gram-positives including MRSA) plus or minus gentamicin or aztreonam (for gram-negative coverage). Alternative: Clindamycin 600-900mg. Note: Vancomycin alone does not cover gram-negatives. In MRSA-colonized patients, add vancomycin to cefazolin regardless of allergy status.
Q: What patient factors increase risk of surgical site infection in orthopaedic surgery?
A: Modifiable factors: Diabetes (HbA1c greater than 7.5%, glucose greater than 200mg/dL perioperatively), smoking (cease 4 weeks preoperatively), obesity (BMI greater than 40), malnutrition (albumin less than 3.5g/dL, TLC less than 1500), S. aureus nasal colonization (treat with mupirocin). Non-modifiable: Advanced age, immunosuppression, ASA score greater than 2, previous surgery at same site. Preoperative optimization: Glucose control, smoking cessation, nutritional supplementation, MRSA decolonization (chlorhexidine washes, nasal mupirocin).
Q: What is the role of chlorhexidine skin preparation in preventing surgical site infection?
A: Chlorhexidine-alcohol is superior to povidone-iodine for SSI prevention (NEJM POISE study - 40% reduction in superficial SSIs). Key points: Alcohol component provides rapid kill; chlorhexidine has residual activity. Allow to dry completely (2-3 minutes) before draping - reduces fire risk and optimizes antisepsis. Contraindicated: Near eyes, ears, mucous membranes. Preoperative chlorhexidine bathing (night before and morning of surgery) reduces skin bacterial colonization. Combine with nasal decolonization for MRSA carriers.
Q: What intraoperative measures reduce surgical site infection risk?
A: Antibiotic cement in arthroplasty (particularly revision surgery, high-risk patients). Laminar airflow theatres - controversial, may not reduce SSI vs conventional flow. Body exhaust suits - reduce bacterial shedding from surgical team. Minimize traffic in operating theatre. Maintain normothermia (hypothermia impairs neutrophil function). Glycemic control (glucose less than 180-200mg/dL). Wound irrigation with saline; antiseptic irrigation (dilute povidone-iodine, chlorhexidine) - evidence mixed. Double gloving and glove changes every 2 hours or after contamination.
Summary
Surgical site infection prevention in orthopaedic surgery requires a comprehensive, evidence-based approach spanning the entire perioperative period. Success depends on implementing multiple interventions in a bundled fashion, as no single measure is sufficient.
Pre-operatively, focus on modifiable risk factors: glycemic control (HbA1c less than 7%, perioperative glucose less than 10 mmol/L), smoking cessation (minimum 4 weeks), nutritional optimization, MRSA screening and decolonization, and pre-operative chlorhexidine bathing. These interventions can reduce SSI risk by 40-70% in high-risk patients.
Intra-operatively, meticulous attention to antibiotic timing (30-60 minutes before incision), skin preparation (chlorhexidine-alcohol preferred), appropriate hair removal (clipping not shaving), maintenance of normothermia, operating room discipline, and surgical technique are critical. Each element has Level 1 evidence supporting efficacy.
Post-operatively, appropriate wound care, continued glucose monitoring, early drain removal if used, and comprehensive patient education ensure continued infection prevention and early detection if infection occurs.
Special considerations for implant surgery include enhanced protocols such as laminar flow operating rooms, antibiotic-loaded cement for cemented arthroplasty, and intrawound vancomycin for spinal instrumentation. Open fractures require early antibiotics (within 1 hour), timely debridement, and appropriate soft tissue management.
For exam preparation, focus on evidence levels for interventions, guidelines (eTG and international consensus), timing of antibiotic prophylaxis, skin preparation agents, and comprehensive bundle approaches. Understanding both the evidence and practical implementation demonstrates clinical competence and commitment to patient safety.
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“A 68-year-old woman with type 2 diabetes (HbA1c 8.5%) and BMI 34 is scheduled for total knee arthroplasty in 6 weeks. Walk me through your approach to SSI prevention in the pre-operative period.”
“You are about to start a total hip arthroplasty. The patient has been brought to the operating room and is anesthetized. Walk me through your SSI prevention checklist before you make the incision.”
Pre-operative Optimization
- Glycemic control: HbA1c less than 7% for elective surgery, perioperative glucose less than 10 mmol/L
- MRSA screening and decolonization: Mupirocin 2% nasal + chlorhexidine 4% wash x 5 days
- Smoking cessation: Minimum 4 weeks (ideally 8 weeks) for meaningful SSI reduction
- Nutritional assessment: Albumin greater than 35 g/L, supplement if deficient (7-14 days)
- Chlorhexidine bathing: Night before and morning of surgery reduces bacterial load 90%
Antibiotic Prophylaxis
- Timing: 30-60 minutes before incision (60 min for vancomycin)
- Cefazolin 2g IV (3g if weight greater than 120 kg) - standard for clean orthopaedic
- Vancomycin 15-20 mg/kg IV if MRSA or beta-lactam allergy (over 60-90 min)
- Re-dosing: Every 4 hours for cefazolin if prolonged case (after 2 half-lives)
- Duration: Single dose (no benefit beyond 24 hours post-op for clean surgery)
Skin Preparation
- Chlorhexidine-alcohol 2%/70% preferred (40% SSI reduction vs povidone-iodine)
- Application: Centrifugal from incision, 3-minute drying time essential
- Hair removal: Clipping only if necessary (never shaving - increases SSI 2-3x)
- Timing: Clip immediately before surgery (not night before)
- Avoid: Chlorhexidine near eyes, ears (ototoxicity) and neuraxial procedures (neurotoxicity)
Intra-operative Measures
- OR environment: Laminar flow for arthroplasty, minimize traffic, closed doors
- Normothermia: Maintain greater than 36°C (forced air warming, warm IV fluids)
- Sterile technique: Proper hand prep (alcohol rub or scrub), sterile draping
- Surgical technique: Minimize tissue trauma, meticulous hemostasis, eliminate dead space
- Irrigation: Copious normal saline (3-9 L for arthroplasty), final irrigation before closure
Post-operative Care
- Dressing: Occlusive, waterproof, leave intact 48-72 hours (epithelialization period)
- Glucose control: Continue monitoring, target less than 10 mmol/L for 48 hours
- Drains: Early removal 24-48 hours if used (controversial - many avoid for routine cases)
- Patient education: WOUND WATCH signs (warmth, oozing, uncontrolled pain, new fever, dehiscence)
- Monitoring: First visit 10-14 days, low threshold for patient-initiated contact if concerns
Implant Surgery Specifics
- Arthroplasty: MRSA screening, laminar flow, antibiotic cement (reduces PJI 30-50%)
- Spine instrumentation: Intrawound vancomycin powder 1-2g (reduces SSI 50-70%)
- Trauma/open fractures: Early antibiotics (within 1 hour), cefazolin + gentamicin for Grade 2-3
- Negative pressure wound therapy: High-risk wounds (obesity, revision, trauma, long fusions)
- Enhanced surveillance: 90 days for implant surgery vs 30 days for non-implant
Risk Factors (High-Yield)
- Patient: Diabetes (especially HbA1c greater than 8%), obesity (BMI greater than 30), smoking, malnutrition, immunosuppression
- Surgical: Duration (each hour increases risk 1.5x), implants, revision surgery, contaminated wounds
- Modifiable: Glucose, smoking (4-8 weeks cessation), nutrition, MRSA, remote infections
- Non-modifiable: Age (greater than 65), male sex, genetics, emergency surgery
Guidelines, Standards & Registry
- eTG (Therapeutic Guidelines): Cefazolin first-line for clean orthopaedic, single dose, stop by 24 hours
- NSQHS Standards: Infection prevention and control requirements, SSI surveillance
- AOANJRR: Registry tracks PJI rates for arthroplasty, surgeon and institution-specific data
- MRSA screening: increasingly adopted for high-risk arthroplasty
Evidence Base Summary
Key Evidence Sources
- Antibiotic prophylaxis timing (multiple RCTs)
- Chlorhexidine-alcohol vs povidone-iodine (Cochrane)
- MRSA decolonisation (meta-analysis)
- Hair clipping vs shaving (meta-analysis)
- Normothermia maintenance (RCT)
- Bundle approach effectiveness
- Glucose control targets
- Intrawound vancomycin (spine)
- Antibiotic-loaded cement (arthroplasty)
- Finding
- Antibiotic timing critical
- Impact
- 30-60 min window standard
- Finding
- ChlorPrep superior
- Impact
- Chlorhexidine-alcohol first line
- Finding
- MRSA decolonisation works
- Impact
- 58% SSI reduction
- Finding
- Intrawound vancomycin
- Impact
- 66% reduction in spine SSI