Safe Dislocation | Trochanteric Flip Osteotomy | MFCA Preservation | Retinacular Vessels | FAI | Intra-articular Access | AVN Prevention
- The entire premise of the Ganz technique is that the deep branch of the medial femoral circumflex artery (MFCA) is preserved by leaving the posterior soft-tissue envelope and the retinacular flap on the posterosuperior femoral neck undisturbed - this is why AVN is rare when the technique is performed correctly
- The trochanteric osteotomy must be performed anterior to the trochanteric fossa and must NOT extend into the piriformis fossa - the MFCA runs along the posterosuperior femoral neck within the retinacular flap and is at its most vulnerable during osteotomy and dislocation
- Surgical dislocation gives 360-degree visualisation of the femoral head and entire acetabulum - no other approach provides equivalent access while preserving femoral head vascularity
- Indications include femoroacetabular impingement (FAI) treatment, intra-articular loose body removal, acetabular labral repair, femoral head osteochondral lesions, Pipkin fractures, and early AVN staging
- The approach is performed in the lateral decubitus position with the leg draped free, allowing controlled anterior dislocation of the hip by flexion, adduction and external rotation
- “Examiners want you to demonstrate understanding of the vascular anatomy - the MFCA and its retinacular branches are the KEY to why this approach works safely
- “The trochanteric osteotomy is NOT a standard greater trochanteric osteotomy - it is an anterior, thin-slice osteotomy that leaves the posterior soft-tissue envelope intact
- “The most dangerous step is anterior dislocation - the hip must be gently flexed, adducted and externally rotated; forceful manipulation can tear the retinacular vessels
- “Always mention the Bernese group (Ganz) when discussing this technique - it is their landmark contribution to hip preservation surgery
Surgical Hip Dislocation (Ganz Trochanteric Flip)
Overview and Indications
The Ganz surgical dislocation of the hip is a joint-preserving approach that gives 360-degree visualisation of the femoral head and the entire acetabulum while preserving the head's blood supply. Reinhold Ganz and colleagues developed it at the University of Bern (Inselspital) in the 1990s and published it as a reproducible technique in 2001. It has transformed the management of young adult hip pathology, particularly femoroacetabular impingement (FAI).
The principle. A specific anterior trochanteric flip osteotomy preserves the posterior soft-tissue envelope, including the short external rotators and the MFCA retinacular branches. The hip can then be dislocated anteriorly without devascularising the femoral head.
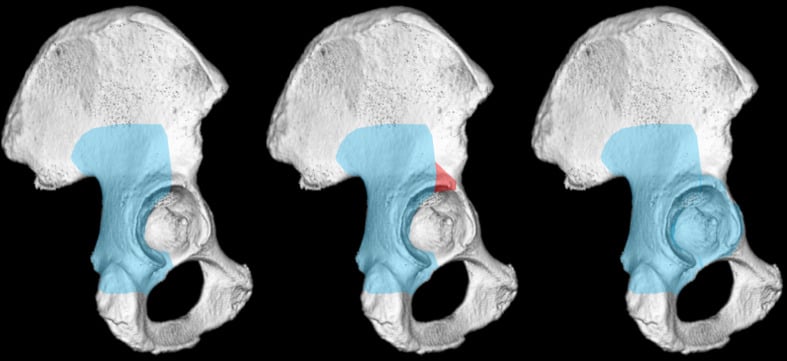
Indications. The operation is chosen when the femoral head and acetabulum need to be seen and treated in full:
- Femoroacetabular impingement - cam, pincer or mixed, requiring osteochondroplasty, acetabuloplasty, labral repair or refixation
- Intra-articular loose bodies - synovial chondromatosis, fracture fragments, osteochondral loose bodies
- Femoral head fractures - Pipkin type I and II, allowing ORIF with direct joint visualisation
- Acetabular fractures - posterior wall, transverse and T-type fractures where joint surface visualisation is essential for anatomic reduction
- Early avascular necrosis - staging, core decompression or bone grafting under direct vision
- Chondral and osteochondral lesions - assessment and treatment of femoral head defects, and comprehensive evaluation of acetabular and femoral chondral damage, particularly when planning realignment procedures
- Slipped capital femoral epiphysis (SCFE) - the modified Dunn procedure, realigning the epiphysis with vascular protection
- Synovial pathology - pigmented villonodular synovitis (PVNS), other synovial disease and tumours requiring complete synovectomy
- Complex labral and capsular pathology - labral reconstruction with grafts, refixation in the setting of dysplasia or FAI, and capsular plication for instability
- Extra-articular impingement - greater trochanteric and trochanteric-pelvic impingement requiring osteoplasty
- Septic arthritis - formal open debridement in severe septic arthritis when arthroscopic washout is insufficient
Relative indications.
- Legg-Calve-Perthes disease deformity correction in the healed stage
- Post-traumatic deformity of the femoral head or acetabular rim
- Ischiofemoral impingement requiring lesser trochanteric osteoplasty
- Revision after failed hip arthroscopy with residual impingement
Contraindications. Examiners test whether you know when not to open the hip joint.
- Advanced osteoarthritis (Tonnis grade 3)
- Obesity - a BMI greater than 35-40 makes positioning and exposure difficult
- Severe dysplasia, where a periacetabular osteotomy is more appropriate
- Active infection
- Pre-existing femoral head avascular necrosis with collapse, where the head is already unsalvageable
- Best approach
- Ganz surgical dislocation (trochanteric flip)
- Reasoning
- 360-degree visualisation of femoral head and acetabulum; allows osteochondroplasty, labral repair, and direct assessment of chondral damage; preserves femoral head vascularity
- Best approach
- Hip arthroscopy
- Reasoning
- Less invasive; faster recovery; equivalent outcomes for isolated labral repair in experienced hands; but limited for complex or combined FAI pathology
- Best approach
- Kocher-Langenbeck or surgical dislocation
- Reasoning
- Surgical dislocation provides direct joint surface visualisation and is preferred when femoral head assessment is critical; Kocher-Langenbeck provides posterior column access without dislocation
- Best approach
- Ganz surgical dislocation
- Reasoning
- Allows extraction of loose fragments, ORIF of the femoral head, and assessment of femoral head vascularity; the approach itself does not devascularise the head when performed correctly
Relevant Anatomy and Vascular Considerations
The blood supply. The adult femoral head is supplied predominantly by the deep branch of the medial femoral circumflex artery (MFCA). The artery of the ligamentum teres contributes, but it is variable and usually insufficient to sustain the head alone.
The extracapsular course. The deep branch arises from the profunda femoris, passes posteriorly between the pectineus and iliopsoas tendons, then runs between obturator externus and adductor brevis. It crosses posterior to the obturator externus tendon and anterior to the conjoint tendon of obturator internus and the gemelli, then pierces the capsule at the posterosuperior aspect of the femoral neck. At the base of the neck it forms an extracapsular anastomotic ring with branches of the lateral femoral circumflex and inferior gluteal arteries; staying extracapsular during the approach protects it.
The intracapsular course. At the capsule the MFCA gives off retinacular branches that run along the posterosuperior femoral neck beneath a synovial fold, the retinaculum of Weitbrecht. These superior retinacular arteries, also called the lateral epiphyseal arteries, are its terminal branches and the dominant supply to the weight-bearing segment of the head.
Why the flip is safe. The osteotomy is made anterior to the insertion of the external rotators, so the entire retinacular vascular chain stays within the posterior soft tissues and the retinacular fold on the neck. The short external rotators are left attached in the Ganz technique, but the vessel's shield is obturator externus, not the conjoint tendon it passes in front of: keep obturator externus intact and never divide it. The moments of greatest vascular risk are the osteotomy, which must stay anterior, and the dislocation, which must be gentle.
The greater trochanter. The osteotomy is planned around its attachments:
- Gluteus medius inserts on the posterosuperior and lateral greater trochanter
- Gluteus minimus inserts on the anterior facet
- Vastus lateralis originates from the inferior aspect
- The trochanteric (digital) fossa is the posterior depression where the obturator externus tendon inserts; the osteotomy must not extend into it
- The piriformis fossa is the entry point for the deep branch of the MFCA and must be protected
The capsule. The hip capsule attaches centrally to the acetabular labrum and transverse ligament, and on the femur to the intertrochanteric line anteriorly and to the femoral neck posteriorly at mid-neck level. The inferior capsule is left alone, because additional retinacular vessels may be present there.
Internervous Plane and Surgical Interval
The Ganz surgical dislocation does not follow a classic internervous plane. It is a soft-tissue preserving approach that maintains the neurovascular integrity of the posterior structures.
The superficial layer. A lateral or posterolateral incision of approximately 15-20 cm is centred over the greater trochanter, either straight (standard) or slightly curved posteriorly (the modified Gibson approach). The iliotibial band is incised in line with the skin, and in a Gibson-type approach the gluteus maximus fibres are split bluntly along their posterior border.
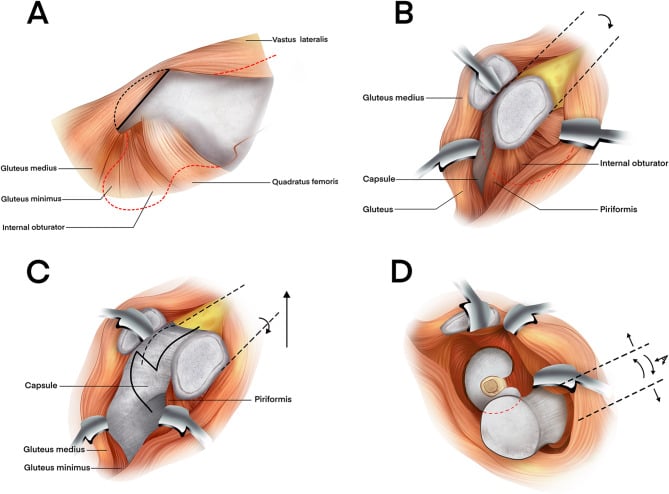
The deep layer: the trochanteric flip. The osteotomy leaves gluteus medius attached to the fragment superiorly and vastus lateralis inferiorly, creating a mobile fragment that is flipped anteriorly with its muscles. The short external rotators (piriformis, obturator internus, gemelli) are not detached and remain on the intact posterior femur. With gluteus minimus elevated off the capsule, the capsule lies exposed anteriorly, superiorly and posterosuperiorly.
The trochanteric osteotomy must be:
- Thin - approximately 1-1.5 cm at the base
- Cut in the sagittal plane, directed from posterior to anterior
- At the junction of the greater trochanter and the femoral neck
- Kept out of the trochanteric fossa and the piriformis fossa
A thick or mal-directed osteotomy risks lacerating the MFCA as it enters the retinacular fold.
Patient Positioning and Setup
Position. Lateral decubitus with the affected hip uppermost, stabilised with a peg-board, beanbag or lateral hip positioner. The leg is draped completely free: flexion, adduction and external rotation dislocate the hip, and extension, abduction and internal rotation serve the reduction and the acetabular work.
The dependent side. Make sure the peroneal nerve of the dependent leg is free of pressure at the fibular head, and protect the axilla and brachial plexus of the dependent arm with an axillary roll.
Anaesthesia. General anaesthesia with muscle relaxation is preferred so that the hip dislocates under control and without resistance. Supplemental regional blocks (lumbar plexus or fascia iliaca) may be used for post-operative analgesia.
No traction table. The assistant provides manual traction as needed during dislocation and reduction, and a sterile pocket or leg holder may support the leg while the hip is dislocated.
Fluoroscopy. The C-arm is positioned for AP and lateral views of the hip, to confirm the osteotomy position, the adequacy of the femoral neck osteoplasty, and the reduction and fixation of the trochanteric fragment.
Instruments. Standard hip instrumentation, plus fine osteotomes for the femoral neck osteoplasty, a femoral head sizer or templating guide, suture anchors for labral refixation, and a small fragment set for the trochanter (typically 3.5 mm or 4.5 mm screws).
Surgical Technique
Exposure. Through the skin incision the fascia lata and gluteus maximus are split. The anterior border of gluteus medius is identified and the trochanteric bursa is excised.
The osteotomy. It is marked and cut with an oscillating saw, beginning at the posterosuperior aspect of the greater trochanter just posterior to its tip, and directed anteriorly and distally to exit just distal to the anterior trochanteric ridge. The saw must stay anterior to the piriformis fossa.
The flip. The fragment, with gluteus medius superiorly and vastus lateralis inferiorly, is mobilised anteriorly. Gluteus minimus is carefully elevated off the anterior capsule, preserving the muscle belly, and the fragment is flipped to expose the anterior and superior capsule, which is cleaned of overlying tissue.
The capsulotomy. A Z-shaped capsulotomy exposes the femoral head and the labrum. The first limb runs along the anterosuperior acetabular rim, from the anterior margin of the reflected head of rectus femoris towards the posterosuperior rim. The second limb runs from the end of the first along the femoral neck at the head-neck junction.
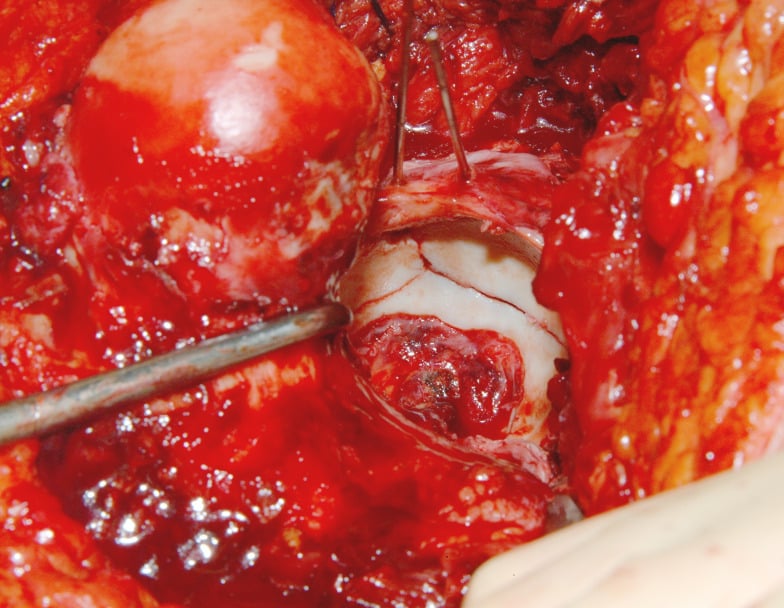
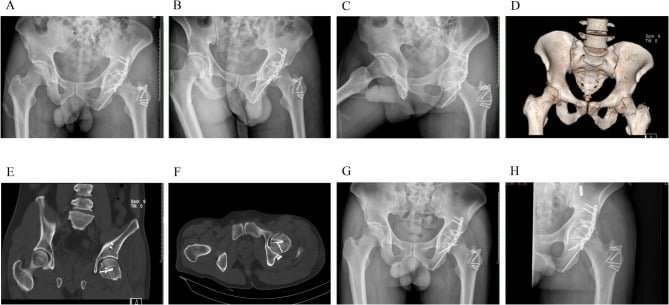
The posterosuperior femoral neck is the territory of the retinacular vessels. During the entire procedure - capsulotomy, dislocation, femoral osteoplasty, and reduction - NO dissection or retraction should occur on the posterosuperior neck surface. The MFCA retinacular branches run in the synovial fold here and are the sole dominant blood supply to the weight-bearing femoral head. Even minor trauma to these vessels can cause segmental AVN.
The extended retinacular flap. This evolution of the basic technique departs deliberately from the rule above. After the flip and capsulotomy, the synovial retinacular fold carrying the MFCA terminal branches is mobilised off the posterosuperior neck as a soft-tissue flap, and a step of trochanter can be raised with it as a second osteotomy. The vessels then travel with the flap instead of being tethered to the neck, which frees the surgeon to resect the metaphyseal neck and reposition the epiphysis without putting them on stretch.
The modified Dunn procedure. The highest-stakes application of surgical dislocation, and the one that depends on the extended flap. It treats moderate-to-severe and unstable SCFE: the callus and metaphyseal prominence are removed, and the epiphysis is reduced anatomically onto the neck under direct vision and fixed. The deformity is corrected at its source while the flap protects perfusion, which is often monitored intra-operatively.
Despite the elegant vascular protection, the modified Dunn in unstable SCFE still carries a real AVN risk, reported in a meaningful minority. It is a specialist procedure, the consent and risk discussion is critical, and it is not a guaranteed AVN-free operation.
Relative femoral neck lengthening. A named deformity correction through surgical dislocation, for the coxa breva / coxa magna with a high-riding (over-grown) greater trochanter seen after healed Legg-Calve-Perthes disease or post-SCFE/AVN deformity. The short, wide neck and relatively overgrown trochanter cause abductor weakness (a shortened lever arm, Trendelenburg), extra-articular trochanteric-pelvic impingement, and intra-articular impingement from the aspherical head.
After the trochanteric flip, the redundant lateral femoral neck is resected and contoured down to the head-neck junction (head-neck osteochondroplasty), and the greater trochanter is distalised and advanced, re-fixed more distally and laterally. This lengthens the neck relative to the trochanter, restores the abductor lever arm and offset, and relieves both intra- and extra-articular impingement. The same MFCA-protecting principles apply, with an extended retinacular flap for major neck reshaping, so the head is not devascularised.
A healed-Perthes hip with coxa breva, a high trochanter and a positive Trendelenburg is the classic indication for relative neck lengthening with trochanteric distalisation and advancement through a surgical dislocation.
Structures at Risk and Complications
The Ganz surgical dislocation has a well-documented safety profile when performed by experienced surgeons, but it carries specific risks from the trochanteric osteotomy, the vascular anatomy and the nearby nerves.
Avascular necrosis. The most feared complication, reported at 0-2% in large series when the technique is performed correctly, and catastrophic in a young patient. When it occurs it is usually technique-dependent: the MFCA or its retinacular branches are lacerated, stretched or thrombosed during the osteotomy or the dislocation. AVN typically declares itself within the first 12-24 months, with progressive groin pain and radiographic change. The risk factors:
- An incorrect osteotomy, too thick or too posterior, entering the piriformis fossa
- Short external rotators divided too close to the femur
- Forceful dislocation, tearing the retinacular vessels
- Pre-existing compromised vascularity, as after SCFE or Perthes disease
Trochanteric nonunion or malunion. Reported in approximately 1-3%, this is the most common mechanical complication. Inadequate fixation, poor bone quality, early weight-bearing and a large fragment all raise the risk. Nonunion or migration of the fragment presents with lateral hip pain, weakness on abduction and a positive Trendelenburg sign; treatment ranges from observation of an asymptomatic fibrous union to revision fixation with bone grafting.
Nerve injury. Sciatic neuropraxia from retraction occurs in approximately 1%, the peroneal division being more susceptible, and most cases resolve within 3-6 months. The nerve is at risk during posterior capsular exposure and acetabular work, and careful retraction, avoiding prolonged posterior retraction, protects it. The superior gluteal nerve is at risk with excessive proximal dissection.
Heterotopic ossification. Reported in approximately 5-8% without prophylaxis, and more common after extensive acetabular rim work or bone grafting. Indomethacin 75 mg daily for 3-6 weeks, or a single post-operative dose of radiation (700 cGy), reduces the risk.
Abductor weakness. Transient weakness of abduction is common after the osteotomy and gluteus medius dissection, and most patients recover strength by 6-12 months. Weakness persists in some, and persistent weakness may indicate trochanteric nonunion or failure of the gluteus medius repair.
Infection. Deep infection is rare (less than 1%) but catastrophic in a young patient with a native hip. Standard peri-operative antibiotic prophylaxis (cephalosporin or clindamycin) is mandatory.
Femoral neck fracture. Rare but reported, particularly after extensive cam osteoplasty, where over-resection of the neck cortex weakens its structural integrity. Resecting more than 30% of the femoral neck diameter significantly increases the risk.
Chondral damage and arthrosis. Intra-operative assessment may reveal more extensive damage than pre-operative imaging suggested, changing the prognosis. Pre-existing chondral damage may progress despite successful impingement correction, leading to early osteoarthritis; the long-term risk depends on the degree of that damage and is a limitation of the underlying pathology rather than a complication of the technique.
Persistent impingement and stiffness. Inadequate resection of the cam or pincer lesion leaves residual impingement and persistent symptoms, so intra-operative fluoroscopic confirmation of adequate resection is essential. Post-operative stiffness and adhesions causing persistent impingement are further sources of ongoing pain.
Reoperation. Hardware removal, trochanteric refixation or progression to arthroplasty are reported in approximately 5-15% of cases at long-term follow-up.
In the viva, lead with AVN and trochanteric nonunion, then mention sciatic neuropraxia, HO and abductor weakness. Examiners want to see that you understand WHY AVN is rare with this technique (vessel preservation) and HOW it occurs when it does.
Guidelines, Registries and Global Practice
There is no single universal guideline for surgical hip dislocation; practice follows evidence-based principles and surgeon experience. Several international organisations have published guidance relevant to the indications and technique:
- AAOS (US): no AAOS clinical practice guideline addresses surgical hip dislocation, and the AAOS guideline on non-arthroplasty management of hip osteoarthritis does not make a recommendation on labral refixation. The preference for refixation over resection rests on the surgical literature - Espinosa and the series that followed it - not on a guideline endorsement.
- UK practice: surgical dislocation is used as a joint-preserving option for complex FAI, femoral head (Pipkin) fractures and intra-articular pathology requiring direct visualisation, and is concentrated in specialist hip preservation units. This reflects referral practice and the Non-Arthroplasty Hip Registry rather than a published British Hip Society recommendation on the technique.
- EFORT/European consensus: European centres (particularly Bern, Munich, Lausanne, and other high-volume hip preservation centres) have extensive experience with the Ganz technique. European practice has historically favoured open surgical dislocation more than North American practice, where hip arthroscopy gained earlier widespread adoption.
- No national arthroplasty registry specifically tracks surgical dislocation procedures, as they are joint-preserving operations. However, conversion rates to total hip arthroplasty after surgical dislocation are tracked in institutional series and provide surrogate survivorship data.
- Large institutional series from Bern, Melbourne, and Boston report conversion to THA in approximately 10-15% at 10 years, predominantly in patients with pre-existing chondral damage or advanced FAI at the time of the index procedure.
- The Australian Orthopaedic Association National Joint Replacement Registry (AOANJRR) captures data on patients who subsequently undergo THA after hip preservation procedures, providing real-world conversion rate data.
- European surgeons (particularly in Switzerland, Germany, and France) have the longest experience with surgical dislocation and continue to favour it for complex FAI pathology. The Bernese group's influence remains strong.
- North American practice has shifted toward hip arthroscopy as the first-line treatment for FAI, with surgical dislocation reserved for complex or revision cases, pincer-type FAI requiring extensive rim work, and femoral head fractures. The threshold for open dislocation varies significantly between centres.
- Asian practice, particularly in Japan and South Korea, follows a similar pattern with arthroscopy as first-line and surgical dislocation for complex cases.
- In low- and middle-income settings, surgical dislocation may be more commonly used than arthroscopy due to the lower capital equipment costs (no arthroscopy tower required), though the technical expertise required limits its availability.
- The modified Dunn procedure (surgical dislocation for SCFE deformity correction in the acute or chronic setting) is increasingly adopted in paediatric orthopaedic centres worldwide, with specific protocols for vascular monitoring.
- Combined approaches (surgical dislocation with periacetabular osteotomy for FAI with dysplasia) are performed in specialist centres for complex hip deformity.
- Advances in hip arthroscopy continue to expand the scope of what can be treated arthroscopically, narrowing the indications for open dislocation, but the Ganz approach remains essential for pathology that cannot be addressed arthroscopically.
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“A 28-year-old male semi-professional footballer presents with 18 months of progressive left groin pain, worse with deep flexion and twisting activities. Examination reveals limited internal rotation (10 degrees) and a positive anterior impingement test. Radiographs show a prominent cam lesion at the anterosuperior femoral head-neck junction with an alpha angle of 72 degrees. The acetabular coverage appears normal. MRI confirms a full-thickness chondral defect on the anterosuperior acetabulum with a stable labral tear. Discuss your management.”
“A 35-year-old man sustained a posterior fracture-dislocation of the right hip in a high-speed motor vehicle accident. The hip was reduced in the emergency department within 4 hours. Post-reduction CT shows a Pipkin type II fracture (a displaced infra-foveal fragment of the femoral head) with a small posterior wall acetabular fracture. The hip is concentrically reduced. Discuss the surgical management.”
One-liner
- Safe surgical dislocation of the hip via trochanteric flip osteotomy, developed by Ganz in Bern, preserving the MFCA and its retinacular branches
- Provides 360-degree visualisation of the femoral head and acetabulum without devascularising the femoral head
Vascular anatomy (critical)
- Deep branch of the MFCA is the dominant blood supply to the femoral head
- Runs along the posterosuperior femoral neck within the retinacular fold
- Pierces the capsule posterosuperiorly, protected by the obturator externus tendon
- Terminal branches are the lateral epiphyseal (superior retinacular) arteries
- AVN rate 0-2% when technique is correct
Indications
- Head fractures (Pipkin), Impingement (FAI), Peri-articular pathology (PVNS)
- Acetabular fractures needing joint visualisation, Chondral assessment
- Capsular/labral repair, Extra-articular impingement
- SCFE (modified Dunn), Septic arthritis debridement
Trochanteric osteotomy rules
- Sagittal plane, posterior to anterior direction
- Approximately 1-1.5 cm thick at the base
- Must NOT extend into piriformis fossa or trochanteric fossa
- Gluteus medius stays attached superiorly, vastus lateralis inferiorly
- Short external rotators are NEVER divided
Key steps
- Lateral decubitus, leg free
- Anterior trochanteric flip with gluteus medius and vastus lateralis attached
- Z-shaped capsulotomy (anterosuperior rim to posterosuperior neck)
- Gentle anterior dislocation (flexion, adduction, external rotation)
- Perform femoral and acetabular work under direct 360-degree vision
- Reduce gently, fix trochanter with 2-3 bicortical screws
Complications
- Femoral head AVN (0-2%, technique-dependent)
- Loss of trochanteric fixation (1-3%)
- Iatrogenent nerve injury (sciatic neuropraxia approximately 1%)
- Persistent pain/stiffness, HO (5-8% without prophylaxis)
- Gluteal weakness (usually recovers 6-12 months)
- Unrecognised chondral damage changes prognosis
- Arthrosis progression (related to pre-existing damage)
- Reoperation approximately 5-15% at long-term follow-up
- Deep infection less than 1%
Contraindications
- Advanced OA (Tonnis grade 3)
- BMI greater than 35-40 (positioning and exposure difficulties)
- Severe dysplasia (PAO is more appropriate)
- Pre-existing AVN with femoral head collapse
- Active infection
Evidence Base
Ganz R, Gill TJ, Gautier E, Ganz K, Krugel N, Berlemann U - Surgical Dislocation of the Adult Hip: a Technique with Full Access to the Femoral Head and Acetabulum Without the Risk of Avascular Necrosis
- The landmark description: 213 hips dislocated over a period of seven years, including 19 patients who underwent simultaneous intertrochanteric osteotomy
- Perfusion of the femoral head was verified INTRA-OPERATIVELY, and to the date of publication none of the hips had subsequently developed avascular necrosis
- The authors report little morbidity associated with the technique, and that it allows treatment of a range of conditions which may not respond well to other methods including arthroscopy
- The approach gives full access to the femoral head and acetabulum, and opens the possibility of joint-preserving procedures such as cartilage transplantation
Gautier E, Ganz K, Krugel N, Gill T, Ganz R - Anatomy of the Medial Femoral Circumflex Artery and Its Surgical Implications
- Neoprene-latex injection and dissection of 24 cadaver hips; the deep branch of the MFCA was the dominant arterial supply to the femoral head in ALL specimens, and its extracapsular course was constant
- The exact relationships are the examinable part, and they are not symmetrical: the deep branch crosses POSTERIOR to the tendon of OBTURATOR EXTERNUS, then crosses ANTERIOR to the conjoint tendon of gemellus inferior, obturator internus and gemellus superior, perforating the capsule at the level of gemellus superior
- Intracapsularly it runs along the posterosuperior neck and divides into two to four subsynovial retinacular vessels
- There is a usable landmark: a trochanteric branch is constantly present at the proximal border of QUADRATUS FEMORIS, and it marks the level of the obturator externus tendon
- THE DECISIVE EXPERIMENT: obturator externus alone protected the deep branch from disruption or stretch during dislocation of the hip IN ANY DIRECTION, after serial release of every other soft-tissue attachment of the proximal femur including a complete circumferential capsulotomy
Espinosa N, Rothenfluh DA, Beck M, Ganz R, Leunig M - Treatment of Femoroacetabular Impingement: Preliminary Results of Labral Refixation
- 52 patients (60 hips) having rim trimming and femoral osteochondroplasty through a surgical dislocation; the torn labrum was RESECTED in the first 25 hips and the intact portion REATTACHED in the next 35 - a sequential, not randomised, comparison
- At two years, excellent results in 28 per cent of the resection group against 80 PER CENT of the reattachment group; good in 48 versus 14 per cent, moderate in 20 versus 6, and poor in 4 versus none
- Clinical scores were significantly better after reattachment at one year (p = 0.0001) and at two years (p = 0.01)
- Radiographic signs of osteoarthritis were significantly more prevalent after resection at one year (p = 0.02) and at two years (p = 0.009)
Beck M, Leunig M, Parvizi J, Boutier V, Wyss D, Ganz R - Anterior Femoroacetabular Impingement: Part II. Midterm Results of Surgical Treatment
- A SMALL series: 14 men and five women, mean age 36 years (range 21 to 52), treated by surgical dislocation and offset creation, followed for a mean of 4.7 years (range 4 to 5.2)
- 13 hips rated excellent to good on the Merle d'Aubigne score - that is 13 of 19, not the 80 to 85 per cent often quoted - with the pain component improving from 2.9 to 5.1 points
- There was NO avascular necrosis of the femoral head
- Five of the 19 went on to total hip arthroplasty: two with grade 2 osteoarthrosis, two with grade 1 but severe acetabular cartilage damage, and one with an untreated ossified labrum
- In stable hips without subluxation of the head into the acetabular cartilage defect, no additional joint space narrowing occurred
Notzli HP, Siebenrock KA, Hempfing A, Ramseier LE, Ganz R - Perfusion of the Femoral Head During Surgical Dislocation of the Hip: Monitoring by Laser Doppler Flowmetry
- Intra-operative laser Doppler flowmetry with a high-energy 20 mW laser measured femoral head perfusion in 32 hips undergoing debridement requiring dislocation or subluxation, with the probe placed in the anterosuperior quadrant of the head
- Position DID affect perfusion, and this is the practical message: with the head reduced, external rotation in both extension and flexion REDUCED blood flow
- During subluxation or dislocation, flow was impaired specifically when the posterosuperior femoral neck was allowed to REST ON THE POSTERIOR ACETABULAR RIM - the one intra-operative position to avoid
- The changes were reversible: a pulsatile signal returned when the hip was reduced or simply taken out of an extreme position
- After final reduction the signal was initially about 12% below baseline but tended to recover to baseline within 30 minutes