Two Articulations | Increased Jump Distance | Reduced Dislocation | Beware IPD
- Two articulations: small head within mobile polyethylene liner, liner articulates with metal shell
- Increased jump distance from larger effective head size reduces impingement and dislocation
- Intraprosthetic dislocation (IPD) is unique complication - liner dissociates from head
- Primary indications: high-risk primary THA and revision for instability
- AOANJRR data shows excellent survivorship and low revision rates for instability
- “Dual mobility has TWO bearing surfaces - not just a larger head
- “Jump distance is distance the head must travel to dislocate - larger with dual mobility
- “IPD occurs when mobile liner separates from femoral head (early vs late types)
- “Modern designs have improved liner retention reducing IPD risk
Overview and Historical Development
Dual mobility total hip arthroplasty uses a bearing with two articulation surfaces to reduce the risk of dislocation. Professor Gilles Bousquet developed the concept in response to the high dislocation rates of early THA designs.
History. Bousquet introduced the concept in 1974 at the University Hospital of Saint-Etienne, France: a 22mm cobalt-chrome head within a large mobile polyethylene liner, designed to increase the effective head size and the range of motion before impingement. Early designs reduced instability but had high IPD rates. France and the rest of Europe used it widely from the 1980s onwards; the USA followed after FDA approval in 2009, with increasing use since then. Multiple manufacturers now make modern designs with improved liner retention mechanisms.
The biomechanical principle is that hip dislocation requires the femoral head to "jump" over the acetabular rim. Dual mobility increases this jump distance by creating a larger effective head size (the outer diameter of the mobile liner, typically 40-55mm) compared to the actual femoral head (22-28mm). This larger effective head increases the range of motion before impingement and makes dislocation mechanically more difficult.
Current use. Dual mobility accounts for 10-25% of primary THA in some European countries, with France the highest, and 15-20% of primary THA in Australasia (AOANJRR data). Adoption in the USA is increasing, particularly for high-risk cases. The two main indications are high-risk primary THA and revision for instability.
Indications and Patient Selection
Dual mobility earns its place in primary THA in patients whose baseline dislocation risk is elevated.
Neuromuscular disorders. Parkinson's disease (impaired proprioception, rigidity), cerebral palsy (spasticity, muscle imbalance), multiple sclerosis (weakness, spasticity), prior stroke with residual weakness or spasticity, and muscular dystrophy.
Cognitive impairment. Dementia or Alzheimer's disease, post-stroke cognitive deficit, inability to follow hip precautions, and psychiatric disorders affecting compliance.
Anatomical risk factors. Abductor muscle deficiency or tears, prior hip surgery with soft tissue damage, spinopelvic imbalance (flat lumbar spine, fixed sagittal imbalance), high BMI (over 35) with increased soft tissue laxity, and developmental dysplasia of the hip (DDH) with abnormal anatomy.
Medical and patient factors. High fall risk (multiple comorbidities, frailty), anticipated poor compliance, substance abuse affecting adherence, and a patient anxious about instability.
Femoral neck fracture in the elderly. A displaced intracapsular fracture in a frail elderly patient with a high dislocation risk (cognitive impairment, prior falls) can be treated with either a hemiarthroplasty or a THA with dual mobility.
Anatomy and Biomechanics
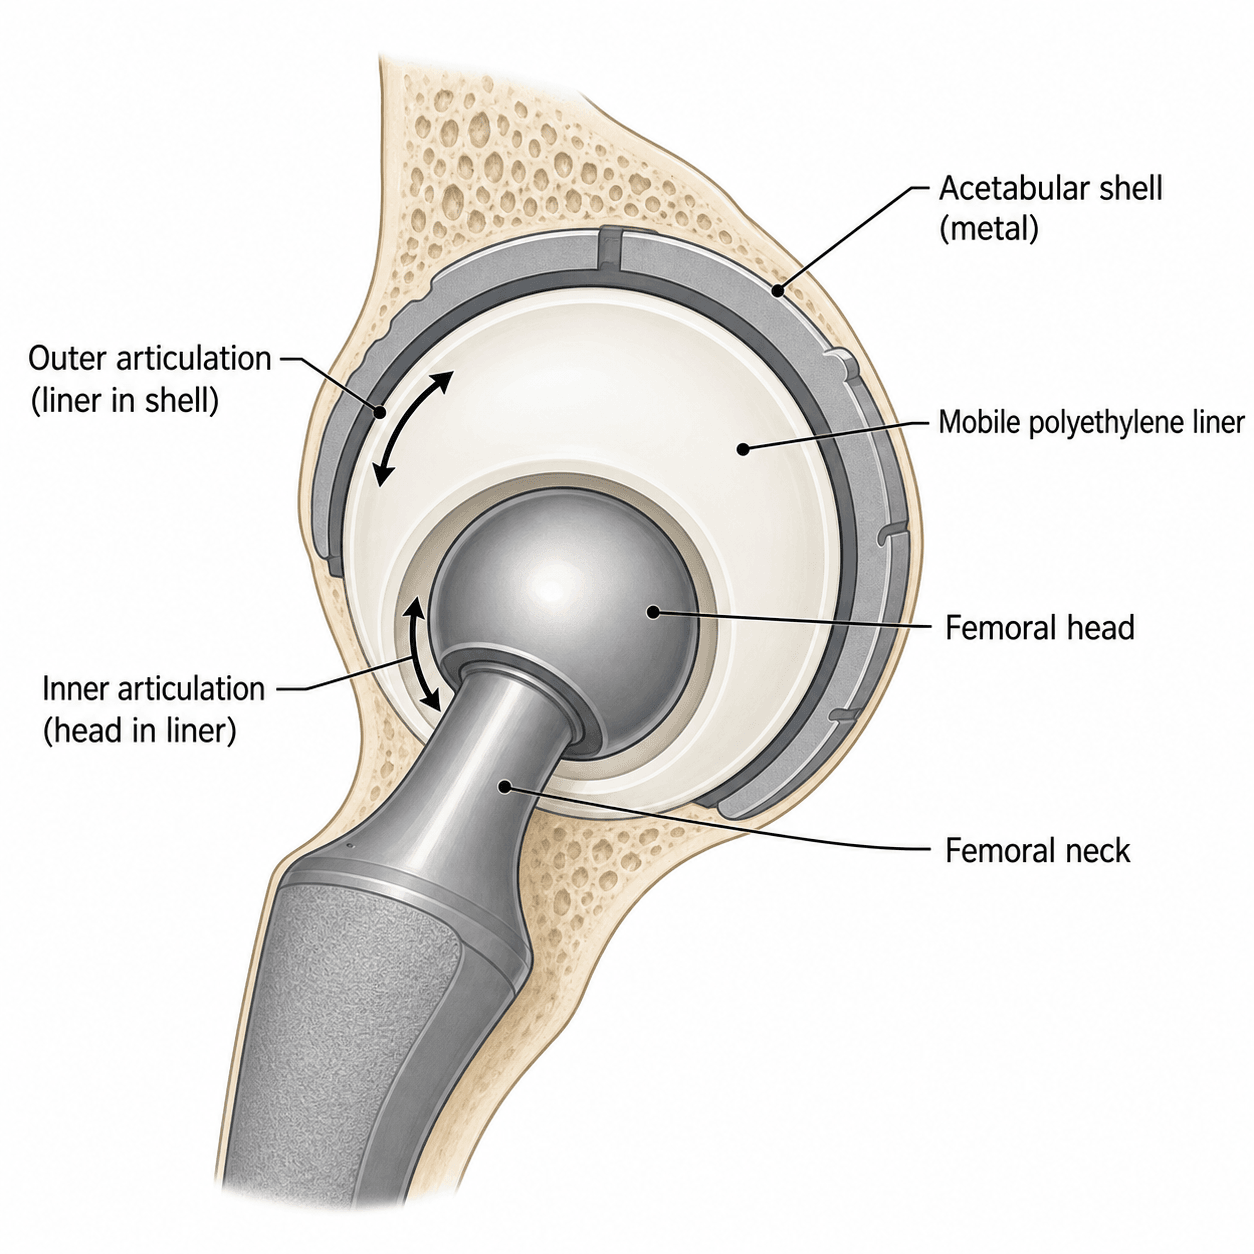
The acetabular side. A metal shell, typically titanium with a porous coating for bone ingrowth, in sizes typically from 44mm to 66mm. Inside it sits the mobile liner of highly cross-linked polyethylene (HXLPE), free to move within the shell, with a liner retention mechanism whose enhanced design features are there to prevent dissociation.
The femoral side. A standard femoral stem, the same as in conventional THA and cemented or uncemented, carrying a small femoral head.
Two articulations. The primary, intraprosthetic articulation is the small head rotating within the mobile liner. The secondary, extraprosthetic articulation is the liner rotating within the metal shell. A standard THA has one articulation, and its effective head is simply its actual head diameter, 28-40mm; in dual mobility the effective head is the outer diameter of the liner, which improves the head-to-neck ratio.
Classification Systems
- Era
- 1970s-1990s
- Key Features
- Bousquet design, cemented metal-backed cup, standard polyethylene
- Limitations
- High wear rates, frequent IPD (5-10%)
- Era
- 1990s-2000s
- Key Features
- Improved liner retention, cementless options, enhanced polyethylene
- Limitations
- Reduced IPD but still concerns about wear
- Era
- 2000s-present
- Key Features
- HXLPE, advanced retention mechanisms, multiple bearing options
- Limitations
- Low IPD (under 1%), acceptable wear rates
What changed. Liner retention mechanisms brought IPD down from 5-10% to under 1%, HXLPE significantly reduced volumetric wear, uncemented options improved long-term fixation, and modular designs allow flexibility at revision. Together these took dual mobility from experimental to mainstream.
Clinical Assessment and Patient Evaluation
History. Establish the primary diagnosis (osteoarthritis, AVN, femoral neck fracture, inflammatory arthritis), then the things that decide whether dual mobility is worth considering:
- Dislocation risk factors - prior dislocation, neuromuscular disorder, cognitive status, fall history
- Comorbidities - Parkinson's disease, stroke, dementia, epilepsy, substance use
- Function - mobility aids, independence, living situation
- Prior hip surgery - previous THA, osteotomy, fracture fixation, arthroscopy
- Medications - those affecting balance, and anticoagulation
Examination.
- Gait: Trendelenburg sign (abductor weakness) and neuromuscular abnormalities
- Hip range of motion: flexion, extension, abduction, adduction, rotation
- Abductor strength: resisted abduction and single leg stance
- Leg length discrepancy, if present
- Baseline neurovascular function, documented
- Cognition: orientation and the ability to follow instructions
- Spinal alignment: sagittal balance, lumbar lordosis, flexibility
Risk stratification. The findings sort the patient into a dislocation-risk tier, and the tier sets the strength of the case for dual mobility. At the moderate tier the choice is a shared decision with the patient about its benefits.
- Patient Factors
- Young, active, no risk factors, primary OA, good bone/soft tissue
- Consider Dual Mobility?
- Optional - standard THA acceptable
- Patient Factors
- Elderly, high BMI, mild cognitive impairment, prior hip surgery
- Consider Dual Mobility?
- Consider dual mobility - discuss risks/benefits
- Patient Factors
- Neuromuscular disease, dementia, recurrent dislocation, abductor deficiency
- Consider Dual Mobility?
- Strong indication for dual mobility
- Patient Factors
- Revision for instability, multiple prior dislocations, combined risk factors
- Consider Dual Mobility?
- Dual mobility gold standard
Investigations and Imaging
Plain radiographs are essential. The AP pelvis shows both hips, bone quality, dysplasia and prior hardware; the lateral hip shows femoral offset and gives an estimate of version. Look for bone loss, dysplasia, protrusio, prior surgery and acetabular defects.
CT is selective: in revision, for bone stock, component position and osteolysis; in the complex primary with severe dysplasia, prior fracture or bone loss; to measure acetabular and femoral version; and with 3D reconstruction to plan complex anatomy.
MRI is also selective: for a suspected gluteus medius or minimus tear, for staging AVN (it is the gold standard for early AVN), and for soft tissue evaluation when infection or tumour is suspected.
Spinopelvic imaging is for high-risk patients: prior dislocation, spinal fusion, flat back syndrome and the elderly. A standing lateral spine radiograph measures lumbar lordosis, pelvic incidence, sacral slope and pelvic tilt; a sitting lateral shows the change in pelvic tilt, which is spinopelvic mobility. A flat lumbar spine puts the hip at high risk of posterior dislocation when sitting (pelvic retroversion), and a stiff spine, with limited compensatory motion, increases the demands on the hip.
Bloods and work-up. Routine preoperative tests are FBC, UEC, a coagulation profile, and group and antibody screen, with ECG and CXR as the anaesthetic assessment requires. Where infection is suspected, send ESR and CRP (elevated suggests infection), aspirate for culture if this is a revision or there is concern, and complete a PJI workup in any revision case. A bone density scan is worth requesting if osteoporosis is a concern, because it affects the choice of fixation; cardiac and respiratory workup follow the comorbidities.
Templating. Digital templating plans the component sizes (acetabular shell and femoral stem), the restoration of offset and leg length, and the target inclination and anteversion.
Management Algorithm
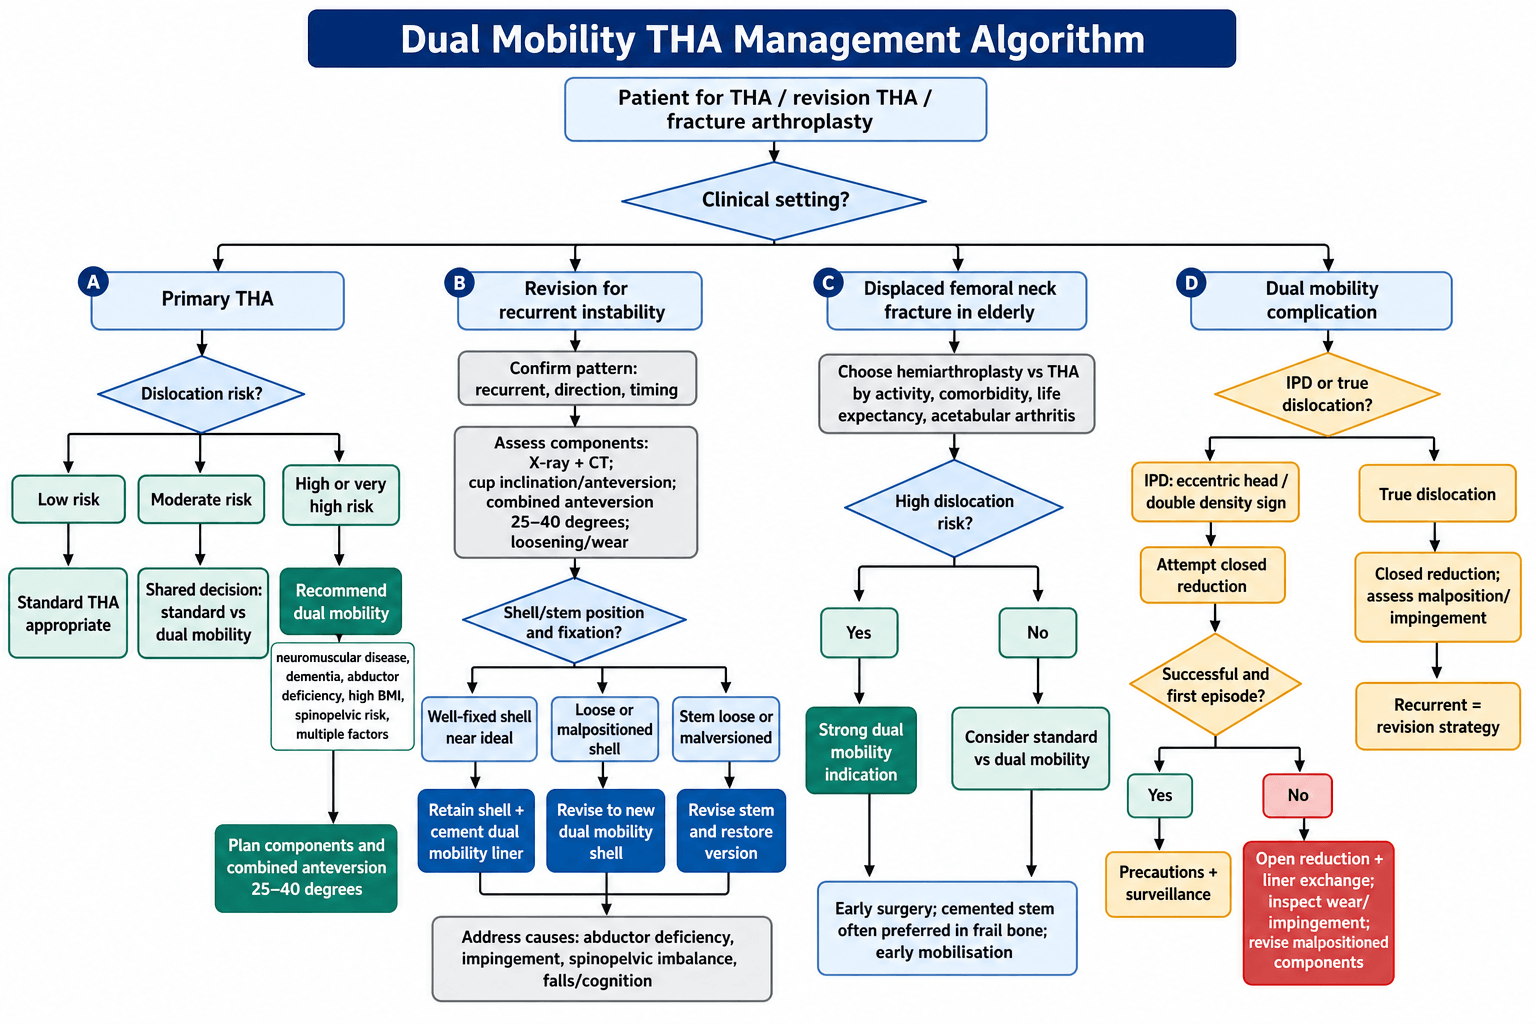
- Assess dislocation risk with the stratification table under Clinical Assessment.
- Counsel the patient. Explain the dislocation benefit and the unique complication, IPD, with the figures in the complications table. Review recovery and precautions, which may be relaxed with dual mobility, and make it a shared decision for the moderate-risk patient.
- Select components. Choose the dual mobility system, size the acetabular shell on the native acetabulum, select the femoral stem on canal geometry, and plan the combined anteversion (targets under Surgical Technique).
- Choose the approach on surgeon experience. Posterior is the most common for dual mobility; anterior or anterolateral is also suitable, with standard soft tissue protection whichever is used.
Surgical Technique
Dual mobility can be used with any standard THA approach. The choice rests on surgeon experience and patient anatomy, not on the implant.
Posterior. The most commonly used approach for dual mobility, with excellent acetabular exposure for shell positioning. Capsular repair matters for stability, as with all THA, using standard posterior soft tissue repair techniques.
Anterolateral. Good visualisation of the acetabulum and preservation of the posterior capsule, through an abductor split or detachment.
Direct anterior. Increasingly popular for dual mobility: an intermuscular interval with no muscle cutting and good component positioning, though it may be more challenging for larger shells.
Dual Mobility vs the Constrained Liner
The constrained liner is repeatedly cited as the inferior alternative for instability, and its failure mechanism explains why. A constrained liner achieves stability by mechanically capturing the femoral head, typically with a metal locking or reinforcing ring around the polyethylene rim (or a captured tripolar bearing), so the head cannot leave the liner without overcoming the ring. Dual mobility achieves stability biomechanically, through a larger effective head and a greater jump distance.
- Dual mobility
- Larger effective head and increased jump distance (biomechanical)
- Constrained liner
- Mechanical capture of the head by a locking/reinforcing ring
- Dual mobility
- Increased (large head-to-neck ratio)
- Constrained liner
- Reduced - the constraining rim limits motion and increases impingement
- Dual mobility
- Head moves within the mobile liner and the force is dissipated
- Constrained liner
- Force is transmitted as torque to the fixation interfaces
- Dual mobility
- Intraprosthetic dislocation (rare with modern designs)
- Constrained liner
- Locking-ring failure, liner-shell dissociation, acetabular loosening
- Dual mobility
- Higher survivorship, lower re-dislocation (pooled figures under Outcomes)
- Constrained liner
- Inferior survivorship and higher dislocation/loosening
- Dual mobility
- First-line for recurrent instability and high-risk hips
- Constrained liner
- Salvage only when capture is the sole option (e.g. irreparable abductor deficiency in a very low-demand patient)
Complications
- Incidence
- 0.5-1% (modern designs)
- Management
- Urgent open reduction with liner exchange
- Incidence
- 0.5-2% primary, 2-5% revision (vs 3-5% and 10-15% with standard THA)
- Management
- Gentle closed reduction under anaesthesia with fluoroscopy, then assess for malposition or impingement
- Incidence
- 1-3% (more with ceramic heads)
- Management
- Usually benign, rarely requires revision
- Incidence
- Theoretical concern, rare clinically
- Management
- Surveillance radiographs, revision if osteolysis
- Incidence
- Very rare with modern designs (under 0.5%)
- Management
- Revision with liner exchange, assess shell stability
Wear and osteolysis. Modern HXLPE makes this rare. It is watched for on surveillance radiographs (schedule under Postoperative Care), and progressive osteolysis is treated by revision with bone grafting and new components.
Standard THA complications still apply. Infection, periprosthetic fracture, neurovascular injury and leg length discrepancy carry the same risk as in standard THA; loosening may carry a potentially higher polyethylene wear load.
Postoperative Care and Rehabilitation
The protocol is standard THA postoperative care. Hip precautions and long-term surveillance follow the timeline.
- Standard THA postoperative care
- Mobilisation day of surgery or day 1 (per institutional protocol)
- Weight bearing as tolerated (unless femoral/acetabular bone concerns)
- DVT prophylaxis per guidelines
- Progressive mobilisation with physiotherapy
- Stairs training before discharge
- Wound care education
- Discharge planning for home support if needed
- Wound check and suture/staple removal (day 10-14)
- Progressive walking distance and activities
- Weaning from walking aids as tolerated
- Return to driving (4-6 weeks, when off opioids and good control)
- Light activities of daily living
- X-ray at 6 weeks (AP pelvis and lateral hip)
- Assess component position and bone ingrowth
- Progressive strengthening exercises
- Return to sedentary work
- Recreational activities as tolerated
- Full functional recovery expected by 3-6 months
- Return to full activities including sports (discuss with surgeon)
Hip precautions. The traditional standard THA precautions are no flexion over 90 degrees, no adduction past the midline and no internal rotation. The increased stability of dual mobility may allow reduced or no formal precautions, and the current trend is for many surgeons to reduce or eliminate them. The decision stays patient-specific, weighing cognitive status, compliance and fall risk.
The benefit of dual mobility is that many surgeons feel comfortable eliminating or significantly reducing hip precautions. The increased jump distance and range of motion before impingement provide inherent stability. However, this remains surgeon-dependent, and high-risk patients (cognitive impairment, prior dislocation) may still benefit from precautions.
Long-term surveillance. Annual AP pelvis and lateral hip radiographs for the first 2-5 years look for osteolysis, component migration and wear, and pain, clicking or a sense of instability prompts a symptomatic review. After 5 years, radiographs every 2-3 years can be considered if the patient is asymptomatic.
Guidelines, Registries & Global Practice
Hip instability is the leading early cause of revision THA worldwide, and dual mobility has become a globally accepted strategy to address it. The picture below is evidence-led rather than tied to any single health system.
Global epidemiology and burden of instability
- Dislocation is among the commonest indications for early revision THA; pooled comparative data show dual-mobility cups cut dislocation roughly six-fold versus fixed-bearing cups (dislocation risk ratio 0.16) (Romagnoli et al. Int Orthop 2018; DOI).
- Dual mobility was conceived by Gilles Bousquet in Saint-Etienne, France (early 1970s); long-term modern-generation cementless cups now show no intraprosthetic dislocation or osteolysis at 10-16 years (Gaillard/Batailler et al. J Arthroplasty 2019; DOI).
- Use is highest in France and continental Europe, rising in Australasia and North America (FDA clearance for modular dual mobility, 2009).
Major guidance, side by side
- Position on dual mobility
- Recognises dual mobility as an option to reduce instability, especially in revision and high-risk primary THA; emphasises individualised selection
- Evidence level / note
- Consensus / moderate-quality evidence
- Position on dual mobility
- Implant choice guided by ODEP benchmarking and NJR outcome data; dual mobility used for instability-risk and recurrent dislocation rather than as a default primary bearing
- Evidence level / note
- Registry-anchored guidance
- Position on dual mobility
- Supports dual mobility (and large heads) as constructs that raise jump distance and head-neck ratio for unstable or revision hips
- Evidence level / note
- Expert / principle-based
- Position on dual mobility
- Endorses dual mobility for high-dislocation-risk primary THA, femoral neck fracture in the elderly and revision for instability
- Evidence level / note
- Consensus, Level III evidence base
Registry evidence (instability and survivorship)
- Signal
- Lower revision for dislocation than fixed-bearing THA; comparable overall cumulative revision; rising utilisation
- Practice point
- Favoured for revision instability and frail FNF
- Signal
- Used with ODEP benchmarking; instability/revision indications predominate over routine primary use
- Practice point
- Bearing choice tied to outcome data
- Signal
- Steadily increasing dual-mobility use in primary and revision THA
- Practice point
- Adoption reflects instability-prevention strategy
- Signal
- Support dual mobility for elderly femoral neck fracture and instability-risk hips
- Practice point
- Strong trauma-arthroplasty signal
Global practice variation
- High-resource settings: dual mobility increasingly routine for revision instability and elderly femoral neck fracture; debate persists about routine use in young, high-demand primary THA owing to polyethylene wear concerns.
- Limited-resource settings: higher implant cost and supply constraints limit uptake; standard fixed-bearing THA with optimised component position and head size remains the mainstay, with dual mobility reserved for highest-risk hips.
- Bearing trends: modern HXLPE liners and improved retention mechanisms have largely resolved the first-generation IPD/wear problem; ceramic-head dual mobility is under evaluation but carries limited long-term data.
For any board, the world standard is consistent: dual mobility is the construct of choice for revision instability and a strong option for high-dislocation-risk primary THA and elderly femoral neck fracture. Registries (AOANJRR, NJR, AJRR, Nordic) show reduced instability revision with comparable overall survivorship; the main unresolved question is wear in young, high-demand patients.
MCQ Practice Points
Q: What is the primary biomechanical advantage of dual mobility THA that reduces dislocation risk? A: Increased jump distance due to larger effective head size. The outer diameter of the mobile polyethylene liner (typically 40-55mm) acts as the effective head, creating a larger head-to-neck ratio and requiring greater displacement to dislocate (12-18mm jump distance vs 5-8mm for standard 32mm head).
Q: What is the strongest evidence-based indication for dual mobility THA? A: Revision THA for recurrent instability. Meta-analyses and registry data show dual mobility reduces re-dislocation from 10-15% to 2-5% and has superior outcomes compared to constrained liners or large head revision. This is the gold standard approach for recurrent THA dislocation.
Q: A patient presents 4 weeks after dual mobility THA with hip pain and X-ray showing the femoral head medialized and eccentric within the acetabular component. What is the diagnosis? A: Intraprosthetic dislocation (IPD). The femoral head has escaped the retentive rim of the polyethylene liner while the liner remains in the shell. Early IPD (under 3 months) suggests technical error such as incomplete liner seating or impingement. Management is urgent open reduction with liner exchange, and the marks are lost by offering closed reduction: the retentive rim is designed to resist the head passing back through it, so it cannot be re-captured closed, and while you try, the bare head is articulating on the metal shell and generating metallosis. Confirm the diagnosis, identify the implant, image the migrated liner if it is not in the shell, then operate and correct the underlying cause.
Q: How many articulation surfaces does a dual mobility THA have and what are they? A: Two articulations: (1) Primary/intraprosthetic articulation - small femoral head (22-28mm) rotating within mobile polyethylene liner, (2) Secondary/extraprosthetic articulation - mobile liner rotating within metal shell. Both articulations contribute to overall motion with typically 60-70% occurring at the intraprosthetic and 30-40% at the extraprosthetic surface.
Q: According to AOANJRR data, what is the revision rate for dislocation with dual mobility THA compared to standard THA? A: Dual mobility has significantly lower revision for dislocation - approximately 0.3% at 5 years compared to 1.1% for standard THA. This represents a 70% reduction in dislocation revision risk. Overall survivorship is comparable between dual mobility and standard THA.
Q: Which patient populations are considered high-risk for THA dislocation and may benefit from dual mobility? A: High-risk populations include: (1) Neuromuscular disorders (Parkinson's, cerebral palsy, prior stroke, MS), (2) Cognitive impairment (dementia, psychiatric disorders), (3) Anatomical factors (abductor deficiency, spinopelvic imbalance, DDH), (4) Medical factors (high fall risk, obesity, prior dislocation history), (5) Femoral neck fracture in frail elderly.
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“A 72-year-old woman with severe hip osteoarthritis is scheduled for primary THA. She has a history of Parkinson's disease with moderate tremor and rigidity, but is cognitively intact and independently mobile with a walking stick. Her daughter asks if there's anything you can do to reduce the risk of hip dislocation, which happened to a friend. How would you counsel this patient about dual mobility THA?”
“A 68-year-old man underwent primary THA via posterior approach 3 years ago for osteoarthritis. He has had four posterior dislocations, all reduced in the emergency department. The last dislocation was 2 weeks ago. CT scan shows well-positioned components (cup 40 degrees inclination, 20 degrees anteversion, stem in 15 degrees anteversion). What are your options for managing his recurrent instability and why would you choose dual mobility?”
“You performed a dual mobility THA 6 weeks ago using a posterior approach. The patient presents to ED reporting the hip 'went out' while bending to tie shoes. On examination, the leg is slightly shortened and internally rotated, but less deformity than a typical dislocation. AP pelvis X-ray shows the femoral head appears eccentric within the acetabular component, medialized relative to the shell. What has happened and how do you manage this?”
CORE DESIGN PRINCIPLES
- Two articulations: head-in-liner (intraprosthetic) + liner-in-shell (extraprosthetic)
- Small head (22-28mm) in mobile polyethylene liner
- Effective head size = outer liner diameter (40-55mm)
- Increased jump distance (12-18mm vs 5-8mm standard)
- Larger head-to-neck ratio reduces impingement
- Both articulations contribute to motion (60% intra, 40% extra)
KEY INDICATIONS
- Primary THA: Neuromuscular (Parkinson's, CP, stroke), cognitive impairment, abductor deficiency
- Primary THA: High fall risk, femoral neck fracture in elderly, prior hip surgery
- Revision THA: Recurrent instability (GOLD STANDARD), complex revision with bone loss
- Other: Oncologic reconstruction, radiation pelvis, prior infection with soft tissue compromise
- Relative: BMI over 35, spinopelvic pathology, hypermobility syndromes
OUTCOMES AND EVIDENCE
- Dislocation rate: 0.5-2% primary, 2-5% revision (vs 3-5% and 10-15% standard)
- AOANJRR: 0.3% revision for dislocation at 5 years (vs 1.1% standard)
- Survivorship: 95-98% at 5 years (comparable to standard THA)
- Re-dislocation in revision: 2-5% dual mobility vs 10-15% other options
- Meta-analyses: Dual mobility superior to constrained liner for revision instability
INTRAPROSTHETIC DISLOCATION (IPD)
- Unique complication: Liner dissociates from head (head medializes, liner stays in shell)
- Incidence: 0.5-1% with modern designs (higher with older designs)
- Early IPD (under 3 months): Technical error (incomplete seating, impingement)
- Late IPD (over 3 months): Polyethylene wear, liner deformation
- X-ray signs: Eccentric head, medialized position, double density sign
- Management: urgent open reduction + liner exchange. Do NOT attempt closed reduction - the retentive rim cannot re-capture the head, and the bare head on the metal shell makes metallosis. Closed reduction belongs to TRUE dislocation, where it can itself cause an iatrogenic IPD if forced
SURGICAL TECHNIQUE
- Any standard approach (posterior most common)
- Acetabular shell: Standard positioning (40 degrees inclination, 15-25 degrees anteversion)
- Critical: Meticulous liner insertion (clean/dry shell, ensure full seating, audible click)
- Femoral component: Standard technique, 10-15 degrees stem anteversion
- Combined anteversion: 25-50 degrees (Ranawat safe zone)
- Intraoperative stability test: Full ROM, no impingement
AOANJRR KEY DATA
- Usage: rising in high-income settings; 18% of primary THA in Australia per AOANJRR (2023), up from 5% in 2010
- Dislocation revision: 70% reduction vs standard THA
- Femoral neck fracture: Lower revision than hemiarthroplasty or standard THA
- Revision instability: Lowest re-revision rate among all options
- Overall survivorship: Comparable to standard THA (no increase in other failures)
EXAM TRAPS AND PEARLS
- Don't confuse dual mobility with just a large head - it has TWO articulations
- IPD is specific to dual mobility - know diagnosis (X-ray signs) and management
- Revision for instability: Dual mobility is gold standard (superior to constrained)
- Can often eliminate or reduce hip precautions with dual mobility
- Modern HXLPE has acceptable wear rates despite larger surface area
- Bousquet developed in France 1970s - know the history
Outcomes and Evidence Synthesis
Primary THA.
- Dislocation: roughly six-fold lower than fixed-bearing cups (dislocation risk ratio 0.16) (Romagnoli et al. Int Orthop 2018; DOI).
- Intraprosthetic dislocation: about 1.1% across 10,783 primary dual-mobility THAs, mostly first-generation designs (Darrith et al. Bone Joint J 2018; DOI).
- Survivorship: approximately 98% at mean 8.5 years pooled, and approximately 98% at 10 years with no IPD/osteolysis for a modern cementless cup at 10-16 years (Gaillard/Batailler et al. J Arthroplasty 2019; DOI).
Revision THA for instability. Against constrained liners, dual mobility gives higher survivorship (94.7% vs 81.0%) and lower dislocation (2.6% vs 11.0%) (Van Eecke et al. Hip Pelvis 2020; DOI). Against large femoral heads, the only RCT to date found no significant dislocation difference, both strategies giving low rates (Weintraub/Darrith et al. J Arthroplasty 2023; DOI). Patient satisfaction is high when the instability resolves, and it is the most cost-effective approach for recurrent dislocation.
Femoral neck fracture. Dislocation is roughly halved (RR 0.47) and revision reduced (RR 0.77) against conventional THA, with a small increase in heterotopic ossification (Santiago et al. J Orthop Surg Res 2025; DOI). Dual mobility reduces dislocation against standard hemiarthroplasty or THA, particularly in the frail elderly with cognitive impairment, and AOANJRR data show it reduces dislocation in femoral neck fracture with a lower revision rate for instability.
Registries. Real-world joint registries (AOANJRR, NJR, AJRR and the Nordic registries) corroborate these findings - lower revision for instability with comparable overall survivorship - and are summarised in the Guidelines, Registries & Global Practice section below. The AOANJRR figures are a 70% reduction in revision for dislocation with comparable overall survivorship (95-98% at 5 years).
Wear performance. Linear wear rates are acceptable with modern HXLPE (0.05-0.1mm/year). Osteolysis is rare with modern HXLPE dual mobility (under 2% at 10 years), and revision for wear is very low (under 1% at 10 years).
Patient-reported outcomes. Function scores (Oxford Hip Score, HOOS), return to activity and quality of life are comparable to standard THA, quality of life improving from the preoperative baseline, and satisfaction rates are high (85-95%).
Evidence Base
Darrith, Courtney & Della Valle. Outcomes of dual mobility components in THA: systematic review
- Systematic review of 54 studies. For 10,783 PRIMARY dual mobility THAs: intraprosthetic dislocation (IPD) 1.1%, extra-articular dislocation 0.46%, aseptic loosening 1.3%, overall survivorship 98.0% at mean 8.5 years.
- For 3008 REVISION dual mobility THAs: IPD 0.3%, extra-articular dislocation 2.2%, survivorship 96.6% at 5.4 years.
- IPD was low and largely limited to earlier (first-generation) designs.
Romagnoli et al. Efficacy of dual-mobility cup in preventing dislocation after THA: meta-analysis of comparative studies
- Meta-analysis of 15 comparative studies, 2408 THAs (50.6% dual-mobility, 49.4% fixed-bearing).
- Dislocation risk ratio 0.16 (95% CI 0.09-0.28) favouring dual mobility - roughly a six-fold reduction in dislocation risk.
- Benefit held across primary, revision, trauma and elective subgroups and in high-risk patients.
AOANJRR - Australian Orthopaedic Association National Joint Replacement Registry
- National registry capturing essentially all hip arthroplasties performed in Australia, used here as a representative example of registry evidence.
- Dual-mobility bearings are associated with lower revision for dislocation/instability than fixed-bearing THA, particularly in revision and femoral-neck-fracture settings, with comparable overall cumulative revision.
- Registry use of dual mobility has risen over the last decade, reflecting growing surgeon confidence.
Santiago et al. Dual mobility versus conventional THA for femoral neck fractures: systematic review and meta-analysis including registry data
- 3 RCTs plus 10 cohort studies, 21,585 patients (4887 dual mobility, 16,698 conventional THA).
- Dual mobility lowered dislocation (RR 0.47, 95% CI 0.34-0.65) and revision (RR 0.77, 95% CI 0.67-0.89) versus conventional THA.
- Trade-offs: higher heterotopic ossification (RR 1.98, 95% CI 1.22-3.20) and worse functional scores at six to nine months - and the size of that difference deserves attention, because a standardised mean difference of 1.65 (95% CI 0.75-2.55) is a LARGE effect, not the slight one it is often reported as, even though it is measured early and on heterogeneous instruments.
- Meta-regression found the posterior approach did NOT alter the dislocation benefit (p = 0.76), which removes the usual objection that dual mobility only helps because it is used with riskier approaches.
- Three randomised trials and ten cohort studies; the authors call for larger randomised trials to confirm long-term efficacy and safety.