Mechanical vs Kinematic vs Restricted Kinematic | Patient-Specific Alignment | Evolution of TKA Philosophy
- Mechanical alignment targets neutral 0° ± 3° hip-knee-ankle axis with perpendicular cuts - gold standard for 40+ years
- Kinematic alignment restores native joint line obliquity and ligament isometry - gaining popularity since 2014
- Restricted kinematic alignment combines KA principles with safety boundaries (HKA 0° ± 3°) to avoid extreme outliers
- 20% of patients report dissatisfaction with MA-TKA despite correct alignment - driver for alternative techniques
- No Level 1 evidence shows long-term superiority of any alignment philosophy - decision based on surgeon experience and patient anatomy
- “Mechanical axis: line from femoral head centre to ankle centre - MA-TKA aims for 0° deviation
- “Kinematic axis: reproduces native joint line orientation - constitutional HKA averages 1.3° varus
- “Safe zone debate: Restricted KA limits alignment to HKA 0° ± 3° to avoid catastrophic outliers
- “Forgotten joint score higher with KA in short-term studies - less clear at 5+ years
Overview and Evolution of TKA Alignment
The alignment debate is one of the most significant philosophical shifts in orthopaedic surgery over the past decade. For over 40 years mechanical alignment was the undisputed gold standard, the conventional technique since Insall in the 1970s and 1980s. Its principle is that a neutral mechanical axis (0° ± 3°) distributes load evenly across the medial and lateral compartments and so maximises implant longevity.
Despite excellent survivorship with mechanical alignment (greater than 95% at 15 years), 20% of patients report dissatisfaction with their TKA. Common complaints include feeling the knee is "not natural," inability to forget the joint, and persistent anterior knee pain. These outcomes drove the search for alternative alignment philosophies.
What mechanical alignment does to the native knee. It creates a horizontal joint line in most patients, which alters ligament lengths and so requires releases to balance the gaps. It changes patellofemoral and tibiofemoral tracking, and it is one size for all, ignoring the wide individual variation in constitutional alignment.
Alignment Philosophy Evolution
A neutral hip-knee-ankle axis, every cut perpendicular to the mechanical axis, and the gaps balanced by soft-tissue release.
Co-level resections restore the pre-arthritic joint line obliquity and ligament isometry with minimal releases. Forgotten joint scores and patient satisfaction are higher in the short term, and data beyond 10 years are limited.
The kinematic approach with the final alignment capped at 3° varus or 3° valgus, and component position adjusted if the safe zone is exceeded. Emerging evidence suggests satisfaction similar to KA with potentially safer boundaries.
Anatomy and Biomechanics
Axes and Measurements
Every philosophy is defined against the same axes, measured on a standing long-leg radiograph.
- Definition
- Line from femoral head centre to ankle centre
- Normal Value
- 0° ± 2° (neutral to slight varus)
- Clinical Significance
- MA-TKA target - used for load distribution assessment
- Definition
- Midline of femoral or tibial shaft
- Normal Value
- Femur: 5-7° valgus to mechanical axis
- Clinical Significance
- Intramedullary alignment guides reference this axis
- Definition
- Angle between femoral and tibial mechanical axes
- Normal Value
- 1.3° varus average (range 3° varus to 3° valgus)
- Clinical Significance
- Primary alignment measurement - defines constitutional alignment
- Definition
- Angle of distal femur and proximal tibia surfaces
- Normal Value
- Distal femur 3° valgus, proximal tibia 3° varus
- Clinical Significance
- KA-TKA aims to restore this native obliquity
Reading the table. The native knee is not neutral: its joint line is oblique, "normal" alignment covers a wide spectrum between individuals, and the native collateral ligaments are isometric throughout the range of motion. The anatomical and mechanical axes of the femur diverge, which is why an intramedullary guide, lying along the anatomical axis, must be set in valgus for the distal femoral cut to be perpendicular to the mechanical axis.
The CPAK Classification and Arithmetic HKA
Two measures of the native knee. The Coronal Plane Alignment of the Knee (CPAK) classification, from the MacDessi 2021 study, is the modern shared language for the native knee phenotype, used to choose and report an alignment strategy. It describes a knee by two values, both derived from the bony joint-line angles, the lateral distal femoral angle (LDFA) and the medial proximal tibial angle (MPTA).
- Arithmetic HKA (aHKA) = MPTA minus LDFA. It estimates constitutional limb alignment: a negative value is constitutional varus, a positive value valgus, and a value near zero a neutral limb. It is used because the true pre-arthritic HKA cannot be measured once the knee is worn.
- Joint line obliquity (JLO) = MPTA plus LDFA. It describes the orientation of the joint line: a low sum is apex-distal (more horizontal), a high sum apex-proximal.
Nine phenotypes. Combining aHKA (varus, neutral, valgus) with JLO (low, neutral, high) gives Types I to IX. The distribution is similar in healthy and osteoarthritic knees: Types I, II and V predominate (varus-to-neutral limbs with a neutral-to-apex-distal joint line), and Types VII to IX are rare.
Why it matters. CPAK helps predict which knees gain most from a kinematic or restricted strategy, and which phenotypes already sit inside the restricted safe zone. In the MacDessi data the balance advantage of kinematic over mechanical alignment was significant in Types I, II and IV, and varus phenotypes that fall inside the safe zone are the natural candidates for restricted kinematic alignment.
Load Distribution
Mechanical alignment aims for an equal 50/50 split between the medial and lateral compartments. The theoretical advantage is uniform polyethylene wear; the cost is that the perpendicular cuts, the horizontal joint line and the releases needed to balance the gaps may alter native kinematics and ligament tension.
Kinematic alignment reproduces the native pre-arthritic distribution, typically 60/40 medial to lateral, by keeping an oblique joint line and the native ligament lengths. The concern is the potential for asymmetric polyethylene wear.
Extreme varus or valgus alignment (greater than 5°) concentrates loads on polyethylene rim, leading to accelerated wear, deformation, and potential catastrophic failure. This is the primary concern with unrestricted kinematic alignment and drives the "safe zone" concept in restricted KA.
Ligament Behaviour
Mechanical alignment changes ligament lengths, because it changes the orientation of the joint line. The MCL is typically lengthened in varus knees corrected to neutral and the LCL in valgus knees, so systematic releases are needed to reach a rectangular extension gap and a parallel flexion gap.
Kinematic alignment keeps them. Restoring the joint line obliquity leaves the MCL and LCL isometric through the range of motion, with minimal to no releases, and in theory improves proprioception and satisfaction. Restricted kinematic alignment preserves the ligaments when possible but releases if needed to stay within the HKA 0° ± 3° safe zone, accepting some ligament modification to avoid extreme alignment.
Classification of Alignment Philosophies
Four philosophies are described here, and functional alignment is increasingly counted as a fifth.
Traditional Mechanical Alignment (MA-TKA)
The principle. Every knee is given a 0° hip-knee-ankle axis, with a ± 3° tolerance, so that load is shared equally between the compartments. The distal femoral and proximal tibial cuts are made at 90° to their respective mechanical axes, creating a horizontal joint line, and a rectangular extension gap and parallel flexion gap are then achieved by systematic ligament releases.
What it ignores. The same target is used for every patient, whatever their native alignment and joint line obliquity. The knee is resurfaced to a new alignment rather than restored to its own.
- Advantages
- Excellent long-term data (greater than 95% survivorship at 15 years)
- Disadvantages
- 20% patient dissatisfaction despite correct alignment
- Advantages
- Well-established, reproducible, taught universally
- Disadvantages
- Requires systematic ligament releases, alters native anatomy
- Advantages
- Predictable mechanical outcomes
- Disadvantages
- Lower forgotten joint scores, less natural feeling
- Advantages
- Proven longevity, wide acceptable alignment range
- Disadvantages
- No clear advantage over KA in randomised trials to 5 years
Mechanical alignment is the foundation from which the alternative techniques evolved, and surgeons who use those alternatives still need to know it.
Functional Alignment: The Fifth Philosophy
Balance first. Functional alignment (FA) uses neither mechanical alignment's fixed neutral nor kinematic alignment's pure native anatomy as its target. It takes intra-operative gap and laxity data from navigation or a robot and co-adjusts bone resections, implant position and selective releases together to balance the knee in flexion and extension, while keeping limb and component alignment within a defined safe boundary. Because the plan is refined live from measured gaps and laxity, FA in practice depends on computer navigation or robotics.
Where it sits. Like restricted KA it caps coronal outliers. Unlike pure KA it will adjust bony cuts to achieve balance rather than just reproduce anatomy, and unlike MA it does not force everyone to neutral; its proponents regard it as the most individualised of the strategies.
Caveats. It requires enabling technology, its boundaries are not standardised between authors, and like KA and restricted KA it lacks long-term comparative survivorship data.
Investigations
The choice between MA, KA and restricted KA often depends on constitutional alignment measured on long-leg radiographs, so imaging is planned around them.
Imaging Protocol for Alignment Planning
Both legs if possible, to assess the constitutional alignment of the contralateral knee. Measure the hip-knee-ankle (HKA) angle, look for extra-articular deformity (femoral or tibial shaft bowing), and determine the mechanical axis deviation (MAD), the distance from the knee centre to the mechanical axis line.
Weight-bearing full-extension view. Measure the joint line convergence angle (JLCA) and the tibial varus/valgus angle, assess the medial and lateral joint space to estimate cartilage wear, and identify osteophytes and bone loss.
Assess the posterior slope of the native tibia, patellar height (Insall-Salvati ratio), posterior femoral condylar wear and any flexion contracture.
Assess patellofemoral tracking and tilt, and identify patellar subluxation or dysplasia. The findings influence the decision on femoral component rotation and alignment.
Advanced Imaging for Kinematic Alignment
CT-based planning. A CT of the entire lower limb, hip to ankle, lets software reconstruct the anatomy in three dimensions and identify the pre-arthritic joint line. Patient-specific cutting guides are then manufactured to restore constitutional alignment, making kinematic alignment reproducible without the intraoperative caliper technique and with less intraoperative decision-making. The price is cost, the imaging and planning lead time, and a plan that cannot be adjusted intraoperatively.
MRI-based planning. MRI sequences can show the remaining cartilage thickness in the medial and lateral compartments, which helps predict the bone resections for the co-level technique, and may identify subchondral bone oedema suggesting an overload pattern. Custom cutting guides can be designed from MRI as well as CT.
Clinical Assessment and Pre-operative Planning
The choice of philosophy begins with what the history and examination show about the patient's alignment, deformity and ligaments.
History. The questions that shape the choice:
- Constitutional alignment - review old radiographs if available
- The contralateral knee - is it arthritic, and what is its alignment?
- Activity level - a high-demand patient may benefit from the "natural feel" of KA
- Expectations - discuss the forgotten-joint concept against implant longevity
- Prior surgery - a previous osteotomy or fracture may limit options
Examination. The findings that matter:
- Deformity magnitude - mild (under 5°), moderate (5-10°) or severe (greater than 10°)
- Correctability on varus and valgus stress - fixed or correctable
- Competence of the medial and lateral collateral ligaments
- Patellofemoral tracking - maltracking may influence rotational alignment
- Range of motion - a severe flexion contracture may limit KA options
Management Algorithm
Patient factors guide the choice of philosophy, and no single approach is universally superior.
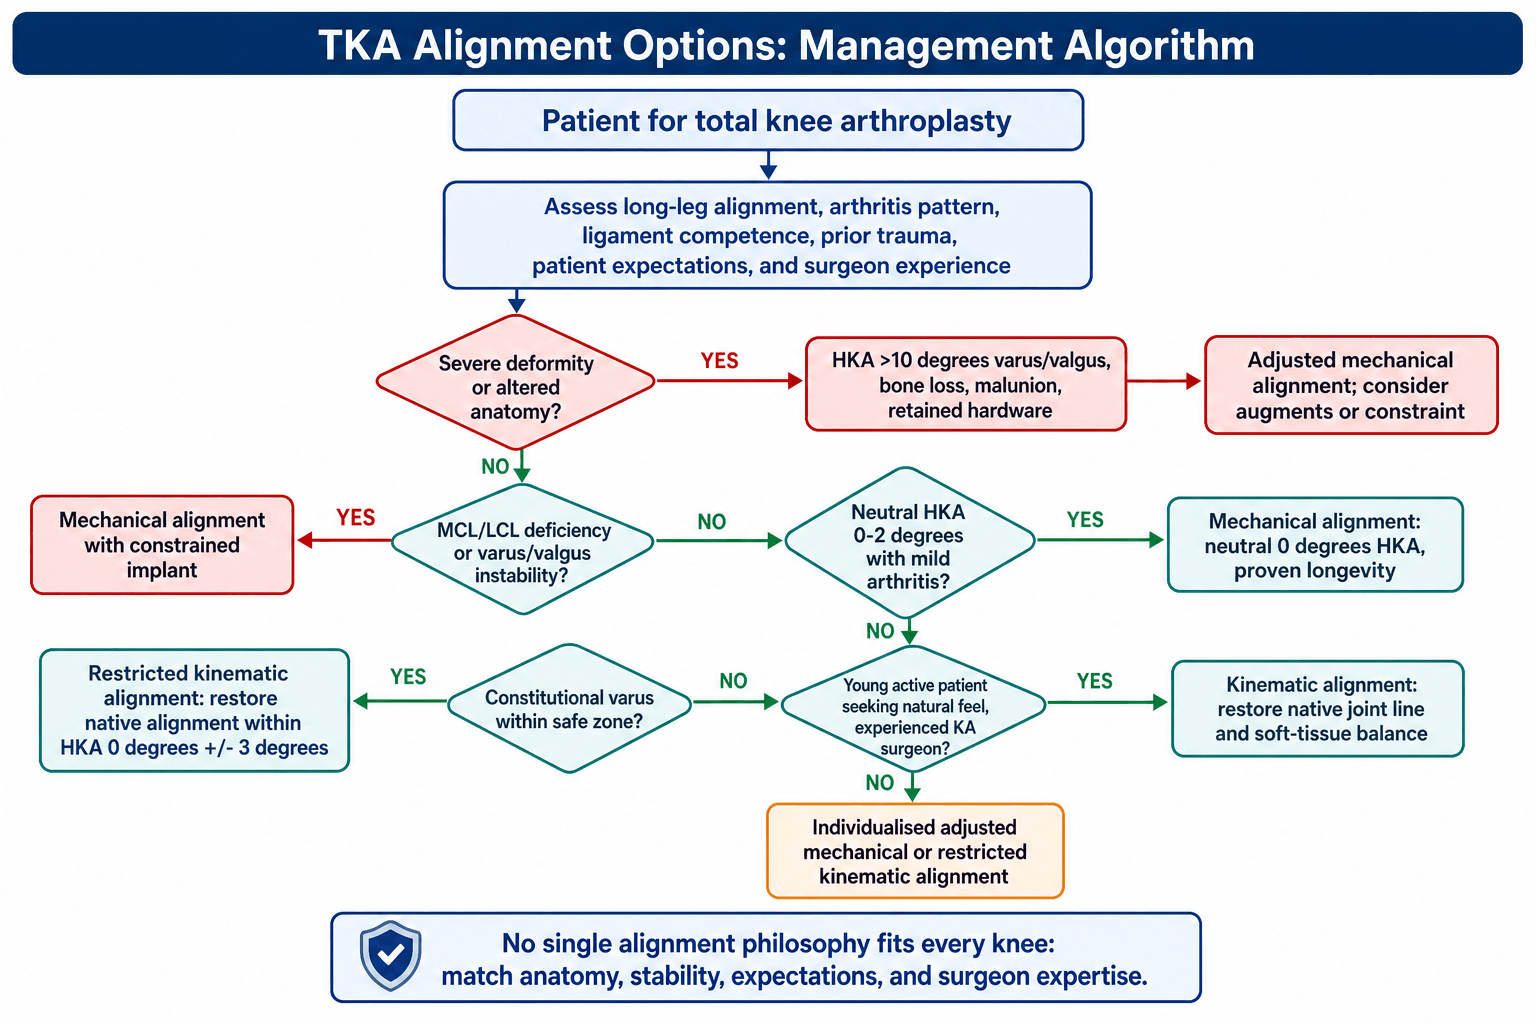
- Constitutional Alignment
- Neutral HKA 0-2° on the contralateral knee, mild arthritis
- Recommended Philosophy
- Mechanical Alignment
- Rationale
- Traditional approach works well - proven long-term outcomes and longevity
- Constitutional Alignment
- HKA 3-5° varus bilaterally, no previous trauma
- Recommended Philosophy
- Restricted Kinematic Alignment
- Rationale
- Restore native alignment within HKA 0° ± 3° safe zone
- Constitutional Alignment
- Any alignment, well-preserved ligaments, minimal deformity, high expectations for natural feel
- Recommended Philosophy
- Kinematic Alignment (if experienced surgeon)
- Rationale
- Maximise patient satisfaction and forgotten joint - requires advanced technique, no long-term data beyond 10 years
- Constitutional Alignment
- HKA greater than 10° varus or valgus, severe bone loss
- Recommended Philosophy
- Adjusted Mechanical Alignment
- Rationale
- Cannot safely restore KA - may need constrained implant
- Constitutional Alignment
- MCL or LCL deficiency, varus/valgus instability
- Recommended Philosophy
- Mechanical Alignment with constrained implant
- Rationale
- Cannot achieve stability with KA - need implant constraint
- Constitutional Alignment
- Prior fracture, malunion, retained hardware
- Recommended Philosophy
- Adjusted Mechanical Alignment
- Rationale
- Anatomy already altered - difficult to define native alignment
The choice of alignment philosophy must be individualised based on patient anatomy, surgeon experience, and patient expectations. Beware the surgeon who uses only one technique for all patients - this ignores the spectrum of knee pathology.
Surgical Technique by Alignment Type
Mechanical Alignment Surgical Steps
MA-TKA Step-by-Step
Enter the femoral canal at the intercondylar notch, anterior to the PCL insertion, with a rod 1mm smaller than the canal width. The rod lies along the anatomical axis, so the cutting block is set at 5-7° valgus to it. Resect typically 9mm (range 8-10mm) from the least worn condyle, measured with the block caliper, and verify with navigation, if used, that the cut is perpendicular to the mechanical axis.
Place the extramedullary rod along the tibial crest, aimed at the centre of the ankle (talar dome) and centred medial-lateral on the tibial spines. Set the block perpendicular (0°) to the mechanical axis, confirmed against the ankle, and resect 8-10mm from the least worn plateau. The posterior slope should match the native slope, typically 3-5°.
Spacer blocks and a tensiometer or calipers measure the medial and lateral gaps, aiming for a rectangular gap with equal tension. If it is asymmetric, release incrementally: the superficial MCL from the proximal tibia for a tight medial side in a varus knee, and the ITB, popliteus and lateral head of gastrocnemius for a tight lateral side in a valgus knee.
Set 3° external rotation to the posterior condylar axis (Whiteside's line parallel). The transepicondylar axis is the preferred and most accurate alternative, or the cut can be made parallel to the cut tibial surface with a balanced flexion gap. Avoid internal rotation, which causes patellar maltracking and anterior knee pain. The AP dimension is set from the bone cuts and implant size.
With the femoral trial in place, assess the gap at 90° of flexion. It should equal the extension gap in height and be equal medially and laterally; correct it with the flexion-gap rules below.
Verify stability through the full range of motion with trial components. The patella should centralise without lateral tilt or subluxation, and the mechanical axis should pass through the centre of the knee (navigation or alignment rod). Insert the definitive components with the cement technique appropriate to the implant design.
Correcting the flexion gap. The distal femoral cut only affects the extension gap, so it is not the tool for a flexion-gap problem.
- Tight - downsize the femur (retains less posterior condyle), increase the posterior tibial slope, or release the PCL in a CR knee
- Loose - upsize the femur or reduce the slope; a thicker insert tightens both gaps, so it applies only when flexion and extension are loose together
- Asymmetric - adjust femoral component rotation
- Severe imbalance - consider a posterior-stabilised or constrained implant
Releases. In severe varus the MCL may need pie-crusting or a posteromedial release. The sequences on each side:
- Tight Side
- Medial compartment tight
- Release Sequence
- 1. Osteophytes. 2. Deep MCL (posterior capsule). 3. Superficial MCL (pie-crust). 4. Semimembranosus
- Endpoint
- Equal medial-lateral tension in extension
- Tight Side
- Lateral compartment tight
- Release Sequence
- 1. Osteophytes. 2. ITB. 3. Popliteus. 4. Lateral head gastrocnemius. 5. LCL (rare)
- Endpoint
- Equal medial-lateral tension in extension
- Tight Side
- Posterior capsule tight
- Release Sequence
- 1. Osteophytes. 2. Posterior capsule release. 3. Increase distal femoral resection (last resort)
- Endpoint
- Full extension achieved with balanced gaps
Complications and Concerns by Alignment Type
- MA-TKA Risk
- Symmetric 50/50 loading - predictable wear pattern
- KA-TKA Risk
- Asymmetric loading in varus knees - long-term wear unknown
- Prevention Strategy
- Restricted KA limits extreme alignment - stay within HKA 0° ± 3°
- MA-TKA Risk
- Requires releases to achieve rectangular gaps - risk of over-release
- KA-TKA Risk
- Minimal releases - preserves native tension, but may leave asymmetry
- Prevention Strategy
- Careful gap assessment and incremental releases in MA
- MA-TKA Risk
- 20% report knee does not feel natural despite correct alignment
- KA-TKA Risk
- Higher forgotten joint scores - more natural feeling
- Prevention Strategy
- Set realistic expectations pre-operatively regardless of technique
- MA-TKA Risk
- Ligament over-release common - mid-flexion laxity
- KA-TKA Risk
- Preserved ligament lengths - theoretically less mid-flexion instability
- Prevention Strategy
- Avoid aggressive releases - consider thicker insert if unstable
- MA-TKA Risk
- Altered Q-angle and trochlear orientation with neutral alignment
- KA-TKA Risk
- Preserved native trochlear groove orientation - less maltracking risk
- Prevention Strategy
- Femoral rotation critical in both techniques - avoid internal rotation
- MA-TKA Risk
- MA safe zone 0° ± 3° prevents edge loading in vast majority
- KA-TKA Risk
- Unrestricted KA may create HKA greater than 5° - edge loading risk
- Prevention Strategy
- Restricted KA with HKA 0° ± 3° boundary mitigates this concern
- MA-TKA Risk
- Traditional concern with MA malalignment greater than 3°
- KA-TKA Risk
- Unknown long-term risk with constitutional varus alignment
- Prevention Strategy
- Long-term registry data needed - currently limited to 10 years KA
Stiffness after mechanical alignment. Aggressive gap balancing and scar tissue can leave the knee stiff.
Kinematic risks are still theoretical. Constitutional varus may overload the medial bone-implant interface, an incorrect caliper measurement fails to restore the joint line, and in severe deformity stability cannot be achieved without releases.
Mechanical alignment has 40+ years of registry data showing excellent survivorship (greater than 95% at 15 years). Kinematic alignment has only 10 years maximum follow-up, with most studies under 5 years. The true test of KA will be 15-20 year survivorship - whether asymmetric loading and constitutional varus alignment lead to accelerated polyethylene wear or aseptic loosening. This uncertainty must be disclosed to patients when choosing KA.
Differential Diagnosis of the Painful or Dissatisfied TKA
Before a poor result is blamed on the alignment philosophy, the painful or dissatisfied TKA must be worked up systematically. Malalignment is only one of several causes, and infection must always be excluded first.
- Key Distinguishing Features
- Rest/night pain, warmth, effusion, early or persistent symptoms
- Decisive Investigation
- ESR/CRP, then aspiration (cell count, culture, alpha-defensin)
- Relation to Alignment
- Must exclude first - unrelated to alignment philosophy
- Key Distinguishing Features
- Activity-related pain, varus/valgus thrust, asymmetric wear
- Decisive Investigation
- Standing long-leg radiograph (HKA), CT for component position
- Relation to Alignment
- Directly related - HKA outside safe zone, tibial component outlier
- Key Distinguishing Features
- Anterior knee pain, patellar maltracking, stiffness
- Decisive Investigation
- CT rotational profile (Berger protocol)
- Relation to Alignment
- Rotational, not coronal - distinct from KA/MA debate
- Key Distinguishing Features
- Giving way, recurrent effusion, sense of insecurity
- Decisive Investigation
- Stress radiographs, examination under anaesthesia
- Relation to Alignment
- Over-release in MA or unbalanced gaps in any technique
- Key Distinguishing Features
- Start-up pain, progressive symptoms, radiolucent lines
- Decisive Investigation
- Serial radiographs, bone scan if equivocal
- Relation to Alignment
- May follow extreme alignment but also fixation/implant factors
- Key Distinguishing Features
- Hip or spine pathology, neuropathic features, normal knee imaging
- Decisive Investigation
- Hip and spine assessment, diagnostic injection
- Relation to Alignment
- Unrelated - a common cause of 'unexplained' TKA pain
Postoperative Care and Follow-Up
Postoperative care is similar across the alignment philosophies. The difference lies in patient-reported satisfaction and "naturalness", which may be higher with kinematic alignment.
Rehabilitation (Common to All Alignment Types)
TKA Rehabilitation Timeline
Same-day or day 1 mobilisation with physiotherapy, weight-bearing as tolerated with a walking aid, and passive and active-assisted range-of-motion exercises. DVT prophylaxis is aspirin 100mg daily (Australian standard) or LMWH if high risk, with multimodal analgesia (paracetamol, NSAIDs, opioids as needed).
Discharge is typically on day 2-4, depending on mobility and social support. The goals are walking 50+ metres, negotiating stairs safely and 0-90° of motion, through quadriceps strengthening, knee flexion exercises and gait re-education. The wound is checked at 2 weeks, with suture or staple removal.
Range of motion 0-110° by 6 weeks, with progressive resistance exercises and a stationary bike. The walking aid is weaned by 4-6 weeks, and driving typically resumes at 4-6 weeks after a right knee TKA.
Range of motion 0-120° by 12 weeks, though it may plateau at 115-120°, which is acceptable. Low-impact activities (golf, swimming, cycling) resume, and sedentary work by 6-12 weeks depending on its demands.
Pain, stiffness and function continue to improve for up to 12 months. Higher-impact activities (tennis, skiing) may resume by 6-12 months if desired and cleared. Clinical and radiographic review at 6 weeks, 3 months and 12 months.
Alignment-Specific Considerations
After mechanical alignment the standard protocol applies without specific modification. Extensive medial or lateral releases may bring more stiffness, early flexion is emphasised if the posterior capsule was released, and an over-released knee is tested for mid-flexion laxity and may need a brace.
After kinematic alignment the range-of-motion goals are often reached earlier, and postoperative stiffness is typically less than after MA, because ligament lengths are preserved and fewer releases are made. The knee may feel "natural" earlier, so balance exercises are emphasised; radiographic follow-up is the same, watching for alignment drift.
Long-Term Surveillance
- Clinical Assessment
- Wound healing, ROM, gait, pain level
- Radiographic Assessment
- Standing AP and lateral knee - component position
- Red Flags
- Wound dehiscence, excessive pain, ROM under 70°
- Clinical Assessment
- ROM, function, return to activities
- Radiographic Assessment
- Standing long-leg radiograph - confirm alignment
- Red Flags
- Persistent instability, ROM plateau under 90°
- Clinical Assessment
- Oxford Knee Score, Forgotten Joint Score, satisfaction
- Radiographic Assessment
- Standing AP/lateral - radiolucent lines, wear
- Red Flags
- Radiolucent lines greater than 2mm, component migration
- Clinical Assessment
- Symptoms, function, any changes
- Radiographic Assessment
- Every 2-5 years or if symptomatic
- Red Flags
- New pain, swelling, instability, loss of function
Kinematic alignment patients require specific attention to alignment on follow-up long-leg radiographs. Confirm HKA angle is maintained (should match immediate post-op). Any drift toward further varus (in constitutional varus patients) may indicate medial component subsidence or polyethylene wear - requires close monitoring and may warrant earlier revision.
Regardless of alignment philosophy, counsel patients that TKA outcomes mature over 12 months. Peak pain relief at 3-6 months, peak function at 6-12 months. Approximately 80-90% patient satisfaction overall (varies by alignment type - KA may be higher). Realistic ROM expectations: 0-115° is acceptable, 0-120° is excellent. Activities to avoid: High-impact running, jumping sports, contact sports. Implant longevity is best established for mechanical alignment - kinematic alignment long-term data still emerging.
Guidelines, Registries & Global Practice
Global Epidemiology and the Case for Individualised Alignment
In asymptomatic young adults, 32% of men and 17% of women have constitutional varus (native mechanical alignment 3° varus or more) - Bellemans 2011. The CPAK study of 1,000 knees confirmed only a minority of healthy or arthritic knees sit at true neutral, and the same nine phenotype distribution is seen worldwide in healthy and osteoarthritic populations.
Knee osteoarthritis is among the leading global causes of years lived with disability, and TKA volumes are rising steeply across high-income countries and increasingly in middle-income settings. The major joint registries (AOANJRR, NJR, AJRR and others) together capture well over a million primary TKAs, making them the dominant source of survivorship evidence globally.
Guidance and Position Statements Side by Side
- Position on Alignment
- No single alignment target mandated; emphasises shared decision-making and registry-tracked outcomes
- Evidence Level
- Consensus / observational
- Practical Message
- Neutral MA remains the benchmark; alternative strategies acceptable with informed consent
- Position on Alignment
- Focus on use of proven, registry-monitored implants (ODEP-rated) rather than prescribing an alignment philosophy
- Evidence Level
- Registry / HTA-based
- Practical Message
- Implant survivorship and unit audit prioritised over alignment dogma
- Position on Alignment
- Recognise the shift from systematic MA toward individualised (kinematic / restricted-kinematic / functional) alignment
- Evidence Level
- Level 1-2 RCTs, short-mid term
- Practical Message
- Restricted boundaries advocated to avoid extreme outliers
- Position on Alignment
- Promote phenotype-based individualised alignment within a defined safe zone
- Evidence Level
- Level 1 (balance) + classification
- Practical Message
- Use CPAK to describe native anatomy and select alignment strategy
No major body endorses a single universal alignment target. Across guidelines the common thread is: use a registry-monitored implant, avoid extreme coronal outliers, counsel on the immature long-term data for KA, and share the decision with the patient. This is the globally defensible position to take in any viva.
Registry Evidence at a Glance
- Region
- Australia
- Relevant Signal
- Marked coronal malalignment historically linked to higher revision in MA-TKA; high overall survivorship
- Limitation for Alignment Research
- Alignment philosophy (KA vs MA) not separately coded
- Region
- England, Wales, NI, IoM
- Relevant Signal
- Drives ODEP implant benchmarking; both well-aligned MA implants show excellent 10-15 year survival
- Limitation for Alignment Research
- Records implant and fixation, not surgeon alignment target
- Region
- USA
- Relevant Signal
- Largest TKA volume captured; supports the neutral safe-zone concept for MA
- Limitation for Alignment Research
- Heterogeneous reporting, alignment intent not captured
Global Practice Variation
- Predominant Practice
- Mechanical alignment taught as the foundation
- Driver
- Reproducibility, exam syllabi, established survivorship
- Direction of Travel
- Gradual uptake of restricted-KA / functional alignment
- Predominant Practice
- Rising kinematic, restricted-kinematic and functional alignment
- Driver
- Access to navigation, robotics and PSI; patient demand for 'natural feel'
- Direction of Travel
- Phenotype-based individualised alignment expanding
- Predominant Practice
- Manual mechanical alignment predominates
- Driver
- Cost, lack of navigation/robotics, surgeon familiarity
- Direction of Travel
- MA likely to remain standard; conventional instrumentation reliable
Wherever they practise, surgeons should master mechanical alignment as the foundation and understand kinematic and restricted-kinematic philosophies - the global trend is toward individualised alignment guided by native phenotype and patient expectation, within evidence-based safe boundaries.
MCQ Practice Points
Q: What is the mechanical axis of the lower limb and how does it differ from the anatomical axis? A: The mechanical axis is a line drawn from the center of the femoral head to the center of the ankle (talus dome) on a standing long-leg radiograph. It represents the load-bearing axis of the lower limb. The anatomical axis is the midline of the femoral or tibial shaft. The femoral mechanical axis typically differs from the femoral anatomical axis by approximately 5-7° in the coronal plane (anatomical axis is more valgus). This 5-7° difference is why the distal femoral cut in mechanical alignment TKA is made 5-7° valgus relative to the anatomical axis (referenced by intramedullary alignment rod) to achieve a cut perpendicular to the mechanical axis.
Q: What is the normal HKA angle and what does deviation from neutral signify? A: The HKA angle is measured on a standing long-leg radiograph as the angle between the femoral mechanical axis and the tibial mechanical axis. Normal average is 1.3° varus (range 3° varus to 3° valgus) - representing constitutional alignment. Mechanical alignment TKA targets 0° ± 3° (neutral alignment). Deviations beyond 3° from neutral (i.e., greater than 3° varus or greater than 3° valgus) are associated with increased revision rates in mechanical alignment TKA based on registry data. Kinematic alignment accepts constitutional alignment as the target, while restricted kinematic alignment limits to HKA 0° ± 3° to avoid extreme outliers.
Q: What is the fundamental principle of kinematic alignment and how does it differ from mechanical alignment? A: The fundamental principle of kinematic alignment is to restore the native joint line obliquity and ligament isometry by performing co-level bone resections that account for cartilage wear. This reproduces the patient's pre-arthritic (constitutional) alignment. The technique uses caliper measurement of remaining cartilage on medial and lateral sides, then resects bone equal to implant thickness PLUS cartilage wear on each side independently. This contrasts with mechanical alignment which creates perpendicular cuts to the mechanical axis (horizontal joint line) and targets neutral 0° HKA alignment regardless of constitutional alignment. KA preserves native ligament lengths (minimal releases), while MA requires systematic ligament balancing to achieve rectangular gaps.
Q: What are the safe zone boundaries for restricted kinematic alignment and what is the rationale? A: Restricted kinematic alignment (rKA) combines kinematic principles with defined safety boundaries to avoid extreme outliers. The HKA safe zone is 0° ± 3° (same as traditional mechanical alignment acceptable range). Component position limits are: femoral component 5° varus to 10° valgus from mechanical axis, tibial component 5° varus to 5° valgus from mechanical axis, and tibial slope 0-7° posterior. The rationale is based on (1) historical mechanical alignment registry data showing increased failure rates with HKA deviation beyond 3°, (2) concern for edge loading with extreme varus or valgus causing rim contact on polyethylene, and (3) theoretical risk of accelerated wear or aseptic loosening with asymmetric loading patterns. rKA allows patient-specific alignment restoration when constitutional anatomy is within safe boundaries, but adjusts alignment (via bone cuts or ligament releases) if exceeding thresholds.
Q: What is the Forgotten Joint Score and what does the evidence show comparing kinematic vs mechanical alignment? A: The Forgotten Joint Score (FJS) is a patient-reported outcome measure (scale 0-100, higher is better) that assesses how often a patient is aware of their artificial joint during activities of daily living. Questions focus on joint awareness during walking, stairs, sitting, and recreation. Several randomised trials and cohorts report a trend toward higher patient-reported and "natural feel" scores with KA at 2-5 years (Dossett 2014 showed better Oxford, WOMAC and Knee Society scores; Blakeney 2019 showed higher KOOS). However, the pooled individual-data meta-analysis (Woon and Young 2018) found no significant WOMAC or KSS function difference and only a small KSS pain advantage. The patient-reported edge for KA is therefore real but modest and inconsistent, whether it is sustained beyond 5-10 years is unknown, and FJS is a surrogate that does not measure implant survivorship.
Q: What is the longest follow-up data available for kinematic alignment TKA and how does it compare to mechanical alignment? A: Mechanical alignment has decades of registry and cohort data, with well-designed implants commonly reporting greater than 95% survivorship at 15 years - the benchmark for long-term implant survivorship. Kinematic alignment evidence is dominated by randomised trials and cohorts with 2-5 year follow-up, with relatively few series reaching 10 years and none reaching mature 15-year comparative survivorship. The highest-level synthesis, the Woon and Young (2018) individual-data meta-analysis of four RCTs, found broadly similar patient-reported outcomes between KA and MA at short to mid-term. The critical knowledge gap is whether KA's restored constitutional (often varus) alignment and more asymmetric loading leads to accelerated polyethylene wear or aseptic loosening at 15-20 years - this remains unproven either way. National registries do not yet separately code alignment philosophy, so registry-level long-term comparison is immature. Patients must be counselled about this uncertainty when choosing KA.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 65-year-old active male presents with end-stage medial compartment osteoarthritis. Standing long-leg radiograph shows constitutional varus alignment of 4° (HKA 4° varus) bilaterally. He has read about kinematic alignment online and asks if it is appropriate for him. Discuss your approach to TKA alignment in this patient.”
“You have decided to perform kinematic alignment TKA using the caliper technique (Howell method). Walk me through your surgical technique for distal femoral and proximal tibial bone cuts in a patient with medial compartment osteoarthritis.”
“You performed a kinematic alignment TKA on a patient with constitutional varus of 5°. You restored the full 5° varus alignment. At 18 months post-operatively, the patient presents with medial knee pain and difficulty with activities. Radiographs show maintained 5° varus alignment and subtle medial tibial component subsidence. Discuss your assessment and management.”
Alignment Definitions
- Mechanical axis = Hip center to ankle center (load-bearing axis)
- HKA angle = Angle between femoral and tibial mechanical axes (normal 1.3° varus)
- Anatomical axis = Femoral/tibial shaft midline (differs from mechanical by 5-7°)
- Joint line obliquity = Native distal femur 3° valgus, proximal tibia 3° varus
Three Main Philosophies
- Mechanical Alignment (MA): Neutral 0° ± 3° HKA, perpendicular cuts, 40+ years data
- Kinematic Alignment (KA): Restore native joint line, co-level resection, 10 years max data
- Restricted KA: Kinematic within HKA 0° ± 3° safe zone - compromise approach
- MA = 95%+ survivorship 15 years | KA = Higher forgotten joint scores 2-5 years
MA-TKA Technique
- Distal femur: 5-7° valgus from anatomic axis (9mm resection), perpendicular to mechanical
- Proximal tibia: 0° perpendicular to mechanical axis (8-10mm resection)
- Femoral rotation: 3° external rotation from posterior condylar axis
- Gap balancing: Rectangular extension gap, parallel flexion gap via ligament releases
KA-TKA Technique
- Measure cartilage wear with calipers on medial and lateral sides
- Co-level resection: Bone cut = Implant thickness + Cartilage wear (each side independent)
- Femoral rotation: 0° from posterior condylar axis (not 3° external rotation)
- No ligament balancing - preserve native tension, minimal releases
Restricted KA Boundaries
- HKA safe zone: 0° ± 3° (cap varus/valgus at 3° boundary)
- Femoral component: 5° varus to 10° valgus from mechanical axis
- Tibial component: 5° varus to 5° valgus from mechanical axis
- Edge loading risk if HKA greater than 5° - restrict to prevent catastrophic outlier
Outcomes and Evidence Base
Patient-Reported Outcomes
- Mechanical Alignment
- 78-82 at 2 years
- Kinematic Alignment
- 85-88 at 2 years
- Clinical Significance
- Higher is better - KA patients more likely to forget artificial joint
- Mechanical Alignment
- 38-42 at 2 years
- Kinematic Alignment
- 40-43 at 2 years
- Clinical Significance
- Minimal clinically important difference 5 points - no clear advantage
- Mechanical Alignment
- 85-90 at 2 years
- Kinematic Alignment
- 88-92 at 2 years
- Clinical Significance
- Small improvement with KA - unclear if sustained long-term
- Mechanical Alignment
- 80% satisfied (20% dissatisfied)
- Kinematic Alignment
- 85-90% satisfied (10-15% dissatisfied)
- Clinical Significance
- Consistent trend favouring KA in multiple studies
The Forgotten Joint Score asks patients how often they are aware of their artificial joint during activities of daily living. Higher scores (range 0-100) indicate better ability to "forget" the joint. The 5-10 point advantage for KA over MA reported at 2-5 years is the strongest patient-reported outcome difference claimed between alignment philosophies, but it is not consistent: the restricted-KA meta-analysis (Gao 2025) and the ten-year randomised trial (Gibbons 2025) found no difference in FJS.
Radiographic Outcomes and Survivorship
Evidence Timeline by Follow-Up Duration
Multiple RCTs (Dossett 2014; Calliess 2017) show at least non-inferior, and in some series superior, patient-reported outcomes with KA versus MA, with no excess of complications, revision or radiographic loosening at 1-2 years. Dossett reported better Oxford, WOMAC and Knee Society scores with KA at 2 years.
The Woon and Young 2018 individual-data meta-analysis of four RCTs (229 PSI-KA vs 229 MA) found no significant difference in WOMAC, KSS function or KSS combined, with only a small KSS pain advantage for KA. No patient subgroup benefited preferentially, which tempers claims of clear KA superiority.
Long-term comparative data remain sparse: most KA series have follow-up under 10 years, and no large randomised cohort has reached 15-year survivorship. This is the principal evidence gap when counselling patients on KA.
Major national registries (AOANJRR, NJR, AJRR and others) collectively capture over a million TKAs and historically link marked coronal malalignment to higher revision in mechanically aligned TKA. KA and restricted KA are not yet separately coded, so registry-level long-term comparison is immature.
Current evidence is Level 1-2 for the short term (2-5 years), showing non-inferior or superior patient satisfaction with KA. Beyond 5 years, the ten-year randomised trial of Gibbons et al. (2025) found no difference between KA and MA in patient-reported outcomes or survivorship. No Level 1 evidence exists beyond 10 years for any alignment philosophy - we rely on registry data and case series for long-term survivorship.
Evidence Base and Key Studies
Randomised Controlled Trial of Kinematically and Mechanically Aligned TKR: Two-Year Clinical Results (Dossett et al.)
- Blinded RCT: 88 patients randomised to KA (patient-specific guides) vs MA (conventional instruments)
- At 2 years all outcomes favoured KA: mean Oxford Knee Score 40 vs 33 (p equals 0.005)
- Mean WOMAC 15 vs 26 (p equals 0.005) and combined Knee Society Score 160 vs 137 (p equals 0.005)
- Greater mean flexion with KA (121° vs 113°, p equals 0.002); odds ratio for a pain-free knee 3.2-4.9
PSI Kinematic versus Non-PSI Mechanical Alignment in TKA: A Prospective Randomised Study (Calliess et al.)
- RCT: 200 patients randomised (100 KA with custom guides vs 100 MA, manual)
- WOMAC and combined Knee Society Score improved in both, significantly favouring KA at 12 months
- KA restored the pre-morbid flexion-extension axis without altering the joint line
- More poor-outcome outliers occurred in the KA group; deviation from the plan correlated with worse outcomes
Kinematic Alignment in TKA Better Reproduces Normal Gait Than Mechanical Alignment (Blakeney et al.)
- Matched case-control: 18 KA vs 18 MA TKAs vs healthy controls, 3D gait analysis
- KA knee kinematics did not differ significantly from healthy controls in sagittal ROM, max flexion or rotation
- MA knees showed reduced ROM, lower max flexion and increased external tibial rotation versus healthy
- Post-operative KOOS was higher after KA than MA (74.2 vs 60.7, p equals 0.034)
Restoring Constitutional Alignment with a Restrictive Kinematic Protocol Improves Soft-Tissue Balance: An RCT (MacDessi et al.)
- Superiority RCT: 63 patients (70 knees) restricted KA vs 62 patients (68 knees) MA, sensor-quantified balance
- Mean intercompartmental pressure difference at 10° flexion 11.7 psi (KA) vs 32.0 psi (MA), difference 20.3 psi (p less than 0.001)
- The advantage held across the arc, not just in extension: 14.8 vs 25.2 psi at 45 degrees (p = 0.004) and 11.7 vs 19.1 psi at 90 degrees (p less than 0.002)
- Optimal balance (ICPD 15 psi or less) achieved in 80% of KA vs 35% of MA knees (p less than 0.001)
- Bone recuts needed in 9% (KA) vs 49% (MA); tibiofemoral lift-off in 13% vs 43% (both p less than 0.001)
Coronal Plane Alignment of the Knee (CPAK) Classification (MacDessi et al.)
- Radiological analysis of 500 healthy and 500 osteoarthritic knees defining nine CPAK phenotypes
- Phenotypes based on arithmetic HKA (constitutional alignment) and joint line obliquity
- Types I, II and V predominate; similar distribution in healthy and arthritic knees
- In a 138-knee randomised cohort, KA achieved optimal balance more often than MA in every phenotype, significantly so in Type I (100% vs 15%), Type II (78% vs 46%) and Type IV (89% vs 0%)