Alignment Philosophies in TKA
- Presenting KA as proven superior. It is NOT at long-term follow-up — a Level I 10-year RCT found no PROM or survivorship difference vs MA. Short/medium-term meta-analytic gains are real but small; MA remains the validated reference standard.
- Forgetting KA's durability concern. Pure KA may leave the tibia in varus with an oblique joint line — the long-term effect on implant survivorship is unproven (the reason MA is still the default).
- Blaming an unhappy textbook-neutral knee on alignment by default. Work the dissatisfied TKA up broadly first (infection, instability, malrotation, extensor mechanism, expectations) — alignment is only one possible contributor.
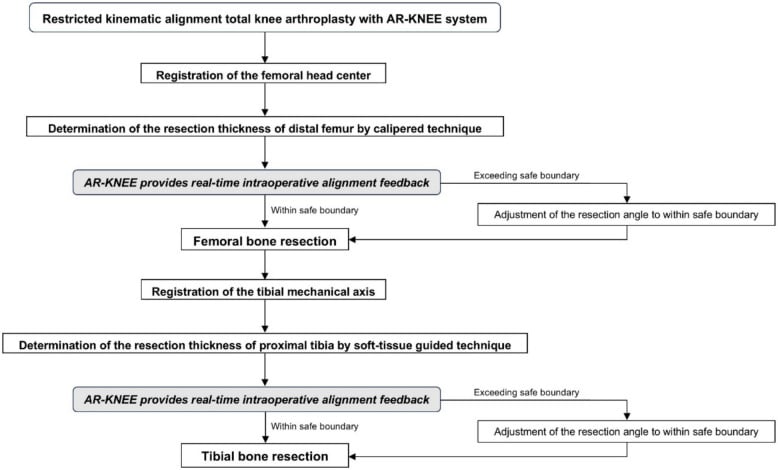
- Muddling the spectrum. Be precise: MA = limb-based neutral; KA = native joint lines; rKA = KA within safe boundaries; FA = robotically balanced to the soft-tissue envelope within limits.
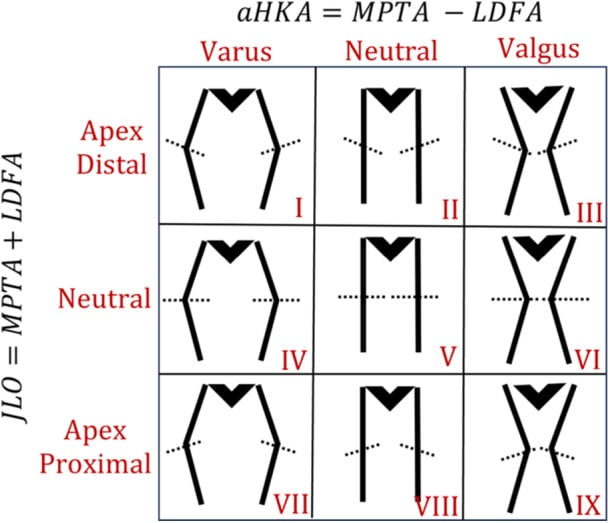
- Mis-stating CPAK. CPAK = aHKA (constitutional alignment) + joint-line obliquity → 9 phenotypes — it phenotypes the knee, it is not an alignment technique.
Overview
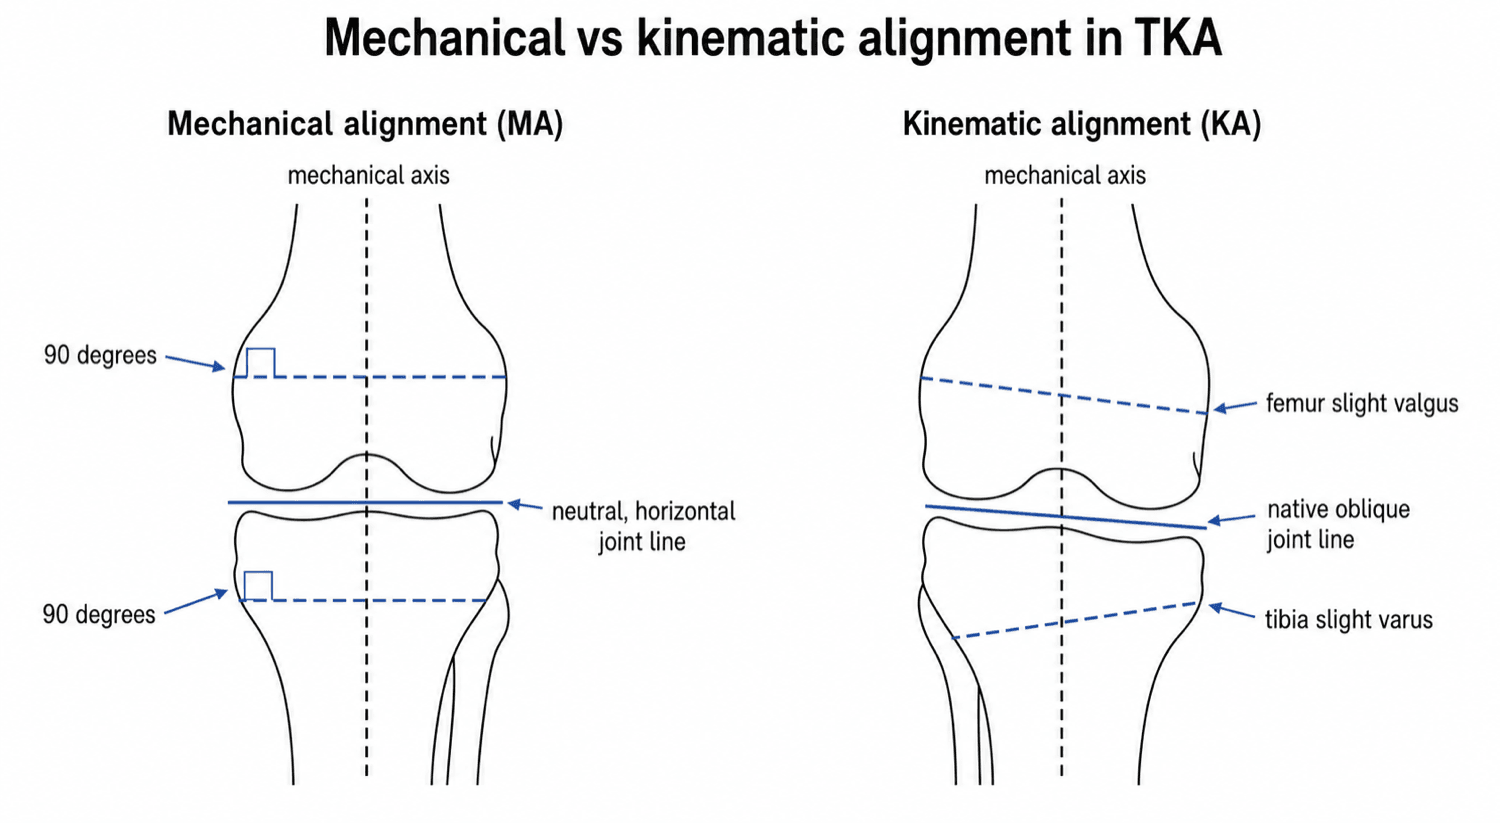
"What target should the components hit?" The philosophies sit on a spectrum between two poles: mechanical alignment, which references the limb's mechanical axes and accepts soft-tissue releases to balance a neutral knee; and kinematic alignment, which references the patient's own pre-arthritic joint surfaces and balances by restoring native anatomy. Restricted kinematic and functional alignment are bounded hybrids. The debate matters because a stubborn minority of patients remain dissatisfied after a well-performed mechanically-aligned TKA.
The shift away from "neutral for everyone" rests on the observation that constitutional (native) lower-limb alignment is highly variable — many healthy people have constitutional varus or valgus. Mechanical alignment normalises all of these to neutral, which alters each individual's joint line and frequently requires ligament releases to balance. Individualised philosophies try to respect native anatomy instead. Robotics and navigation are the enabling tools that make precise, reproducible execution of these individualised targets possible.
Concepts: the philosophies in detail
Mechanical alignment
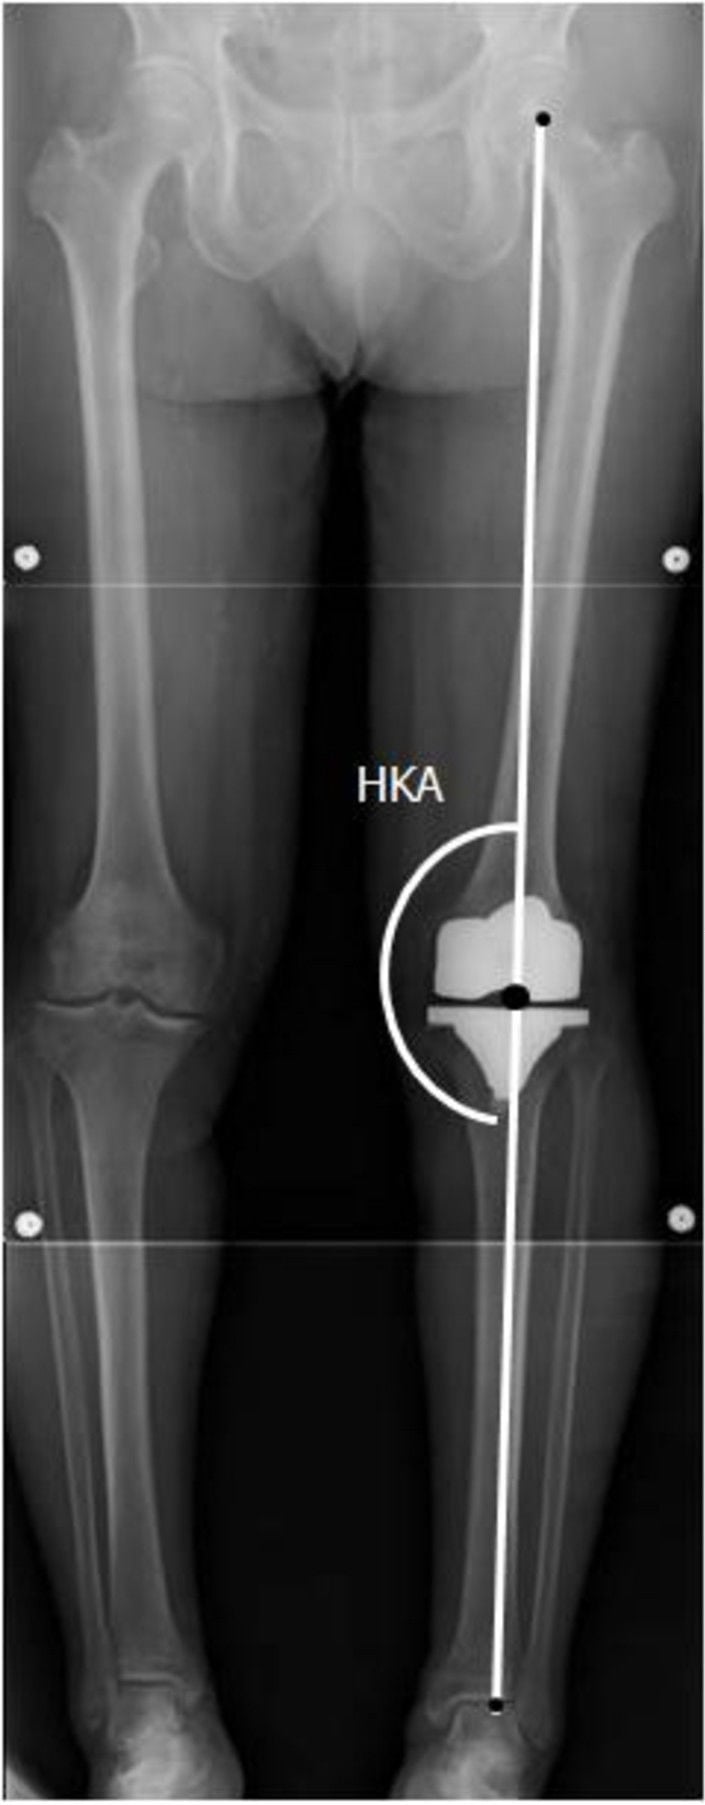
- Target: neutral hip-knee-ankle (HKA) axis; femoral and tibial components perpendicular to their respective mechanical axes; a horizontal joint line.
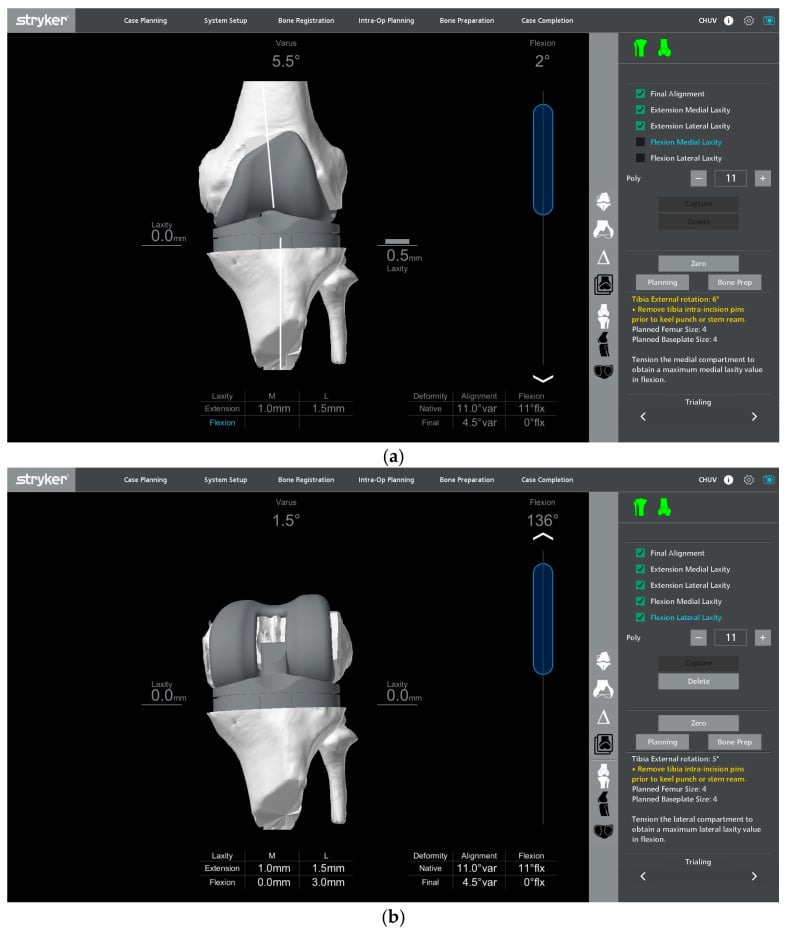
- Balancing: by soft-tissue releases to equalise gaps around the neutral cuts.
- Rationale: reproducible, validated long-term survivorship; even load distribution.
- Status: the historical and current reference standard.
- Reference
- Neutral limb mechanical axis
- Balancing
- Soft-tissue releases around neutral cuts
- Status / concern
- Validated reference standard
- Reference
- Joint line ~3° from mechanical axis
- Balancing
- Restores historical native obliquity
- Status / concern
- Largely historical
- Reference
- Pre-arthritic constitutional joint lines
- Balancing
- Anatomy-led, fewer releases
- Status / concern
- Concern: residual tibial varus, durability unproven
- Reference
- Constitutional, within safe boundaries
- Balancing
- Anatomy-led within limits
- Status / concern
- Pragmatic bounded middle ground
- Reference
- Native anatomy, robotically tuned
- Balancing
- Balanced to soft-tissue envelope within limits
- Status / concern
- Comparable to MA at 2y, fewer releases
Alignment philosophy is debated in the coronal plane, but the examiner expects the axial (rotational) and sagittal planes too — and malrotation is a key cause of the dissatisfied knee:
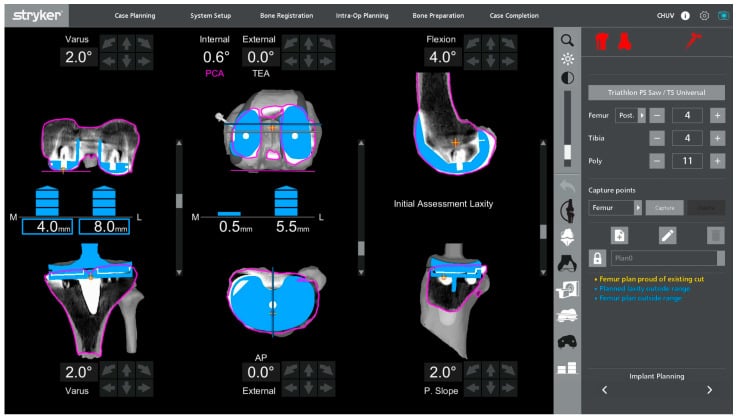
- Femoral rotation (sets the flexion gap and patellar tracking): aim parallel to the surgical transepicondylar axis (TEA) (medial sulcus to lateral epicondyle), or perpendicular to Whiteside's line (the anteroposterior trochlear axis), or about 3° of external rotation off the posterior condylar axis (the posterior condylar angle is ~3°). KA instead sets femoral rotation to the patient's native flexion axis.
- Femoral internal malrotation causes patellar maltracking/lateral subluxation, anterior knee pain and flexion instability/stiffness — a classic cause of the unhappy TKA.
- Tibial rotation: reference the medial third of the tibial tubercle; combined femoral and tibial internal rotation correlates with anterior knee pain (Berger).
- Sagittal plane: preserve an appropriate posterior tibial slope (native ~5 to 10°; too much risks flexion instability, too little reduces flexion / over-tightens the PCL in a cruciate-retaining knee) and set the femoral component flexion to avoid anterior notching or over-flexion.
Constitutional alignment & the CPAK classification
The conceptual basis for individualised alignment is that constitutional limb alignment varies widely across healthy people. To describe and compare this systematically, the Coronal Plane Alignment of the Knee (CPAK) classification was developed.
CPAK characterises a knee using two parameters derived from radiographs:
- The arithmetic HKA (aHKA), which estimates the patient's constitutional limb alignment (varus, neutral, or valgus), and
- The joint line obliquity (JLO), the orientation of the joint line (apex distal, neutral, or apex proximal).
Combining three categories of each yields nine CPAK phenotypes, numbered across the matrix. You need the common ones by name, because the literature now reports outcomes by type:
- Constitutional alignment (aHKA)
- Varus
- Joint line (JLO)
- Apex distal
- Frequency (healthy / arthritic)
- 26.4% / 19.4%
- Constitutional alignment (aHKA)
- Neutral
- Joint line (JLO)
- Apex distal
- Frequency (healthy / arthritic)
- 39.2% / 32.2% - the commonest knee there is
- Constitutional alignment (aHKA)
- Varus
- Joint line (JLO)
- Neutral
- Frequency (healthy / arthritic)
- less common, but behaves like Type I
- Constitutional alignment (aHKA)
- Neutral
- Joint line (JLO)
- Neutral
- Frequency (healthy / arthritic)
- 15.4% / 14.6%
- Constitutional alignment (aHKA)
- Varus / neutral / valgus respectively
- Joint line (JLO)
- Apex proximal
- Frequency (healthy / arthritic)
- rare in both populations
The boundaries are set at one standard deviation of the pooled 1,000-knee dataset and are examinable: neutral aHKA is 0° ± 2° (varus below -2°, valgus above +2°), and neutral JLO is 180° ± 3° (apex distal below 177°, apex proximal above 183°). Note the deliberate vocabulary - JLO is described as apex distal / apex proximal rather than varus / valgus, because "varus joint line" is ambiguous: it can arise from tibial varus in a neutrally aligned limb or from femoral valgus in a valgus limb, and reusing the limb-alignment words for an independent variable is what the classification exists to stop.
The Type V row is the whole argument, and it is worth saying out loud in a viva: CPAK Type V - neutral constitutional alignment with a neutral joint line - is precisely what mechanical alignment aims to create, and it is the natural state of only about 15% of knees. Conversely 76% of healthy and 67% of arthritic knees have an apex-distal joint line, and around 32% and 30% respectively are constitutionally varus. Mechanical alignment is therefore not a restoration for most patients; it is a reconstruction toward a configuration they never had. That is the honest case for individualised alignment, and it is an anatomical case rather than an outcome one - which is exactly why it has proved easier to demonstrate in the operating theatre than in patient-reported scores.
The validating work bears that out where it should. Kinematic alignment achieved optimal intra-operative soft-tissue balance more often than mechanical across every phenotype, and the gap was widest exactly where the theory predicts - in the constitutionally varus knees. Type I: 100% balanced with KA versus 15% with MA. Type IV: 89% versus 0%. These are intra-operative pressure measurements, not outcomes, and the same authors are careful to say the link between phenotype and patient outcome still needs establishing.
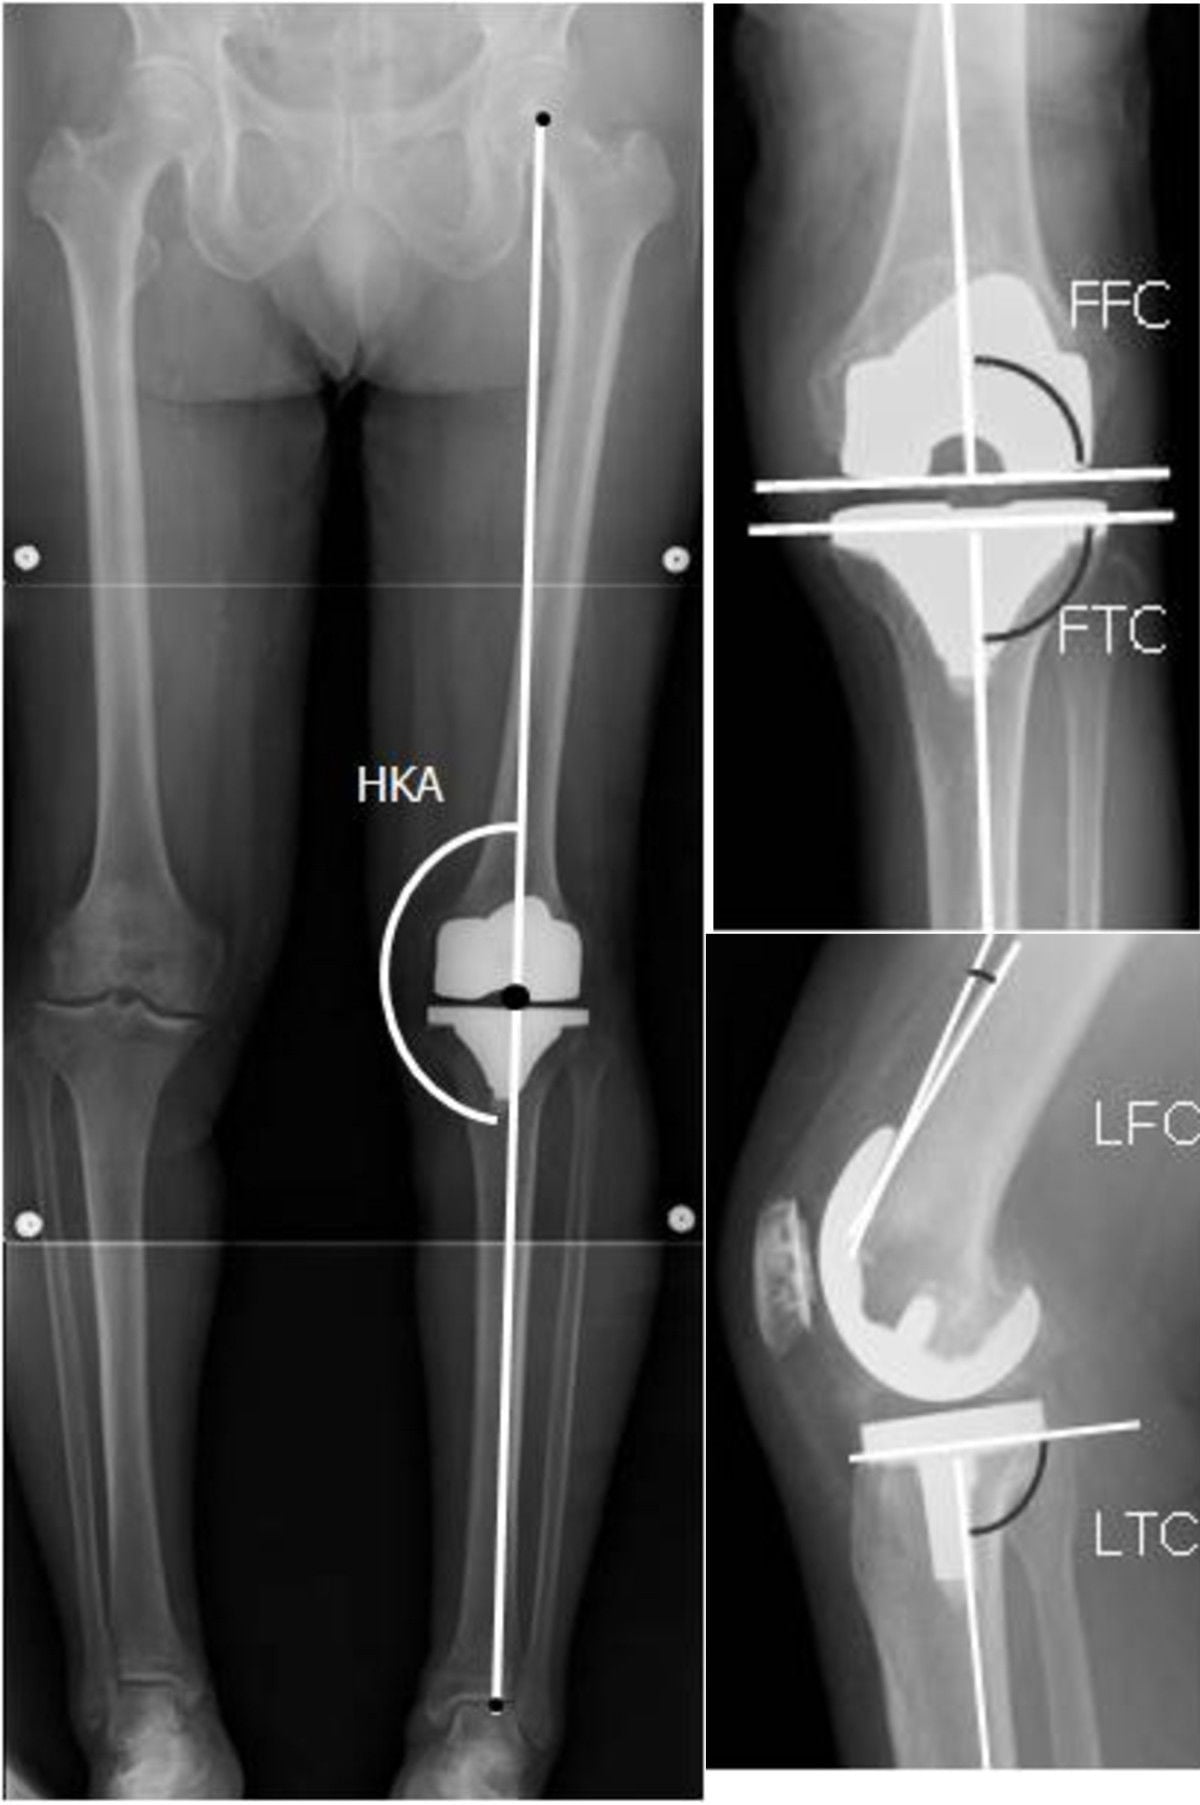
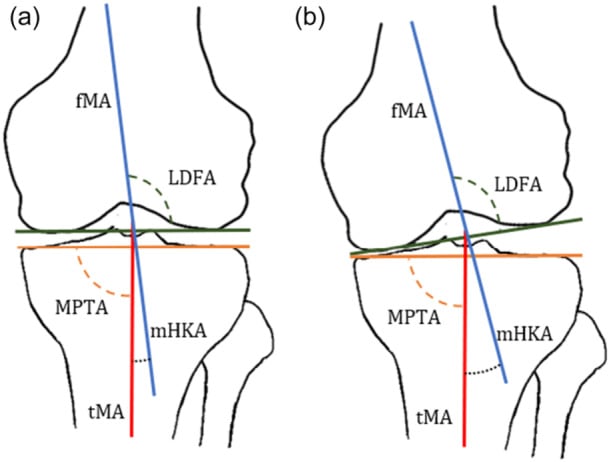
Each philosophy is defined by the angles it cuts and measures — know the parameters:
- mLDFA (mechanical lateral distal femoral angle): femoral mechanical axis to the distal femoral joint line; normal ~85 to 90° (mean ~87.5°); a higher value = distal femoral varus.
- MPTA (medial proximal tibial angle): tibial mechanical axis to the proximal tibial joint line; normal ~85 to 90° (mean ~87°); a lower value = tibial varus.
- JLCA (joint line convergence angle): the angle between the femoral and tibial joint lines; normal ~0 to 2° — it reflects intra-articular wear/laxity.
- aHKA (arithmetic HKA) = MPTA − mLDFA: estimates constitutional alignment by removing the wear/JLCA; neutral 0° ± 2° (more negative = varus, more positive = valgus).
- JLO (joint line obliquity) = MPTA + mLDFA: the joint-line orientation; neutral around 180°, apex-distal vs apex-proximal at the extremes. (aHKA and JLO are the two CPAK axes.)
- The coronal target by philosophy: MA cuts both femur and tibia perpendicular to their mechanical axes (mLDFA = MPTA = 90°, neutral HKA 180°); KA recreates the patient's native mLDFA/MPTA (often femur in slight valgus, tibia in slight varus); rKA does the same but caps each cut and the overall HKA within a few degrees of neutral.
Guidelines, registries & global practice
Alignment philosophy is one of the most actively debated topics in international knee arthroplasty. Practice is genuinely divided: mechanical alignment remains the most widely taught and registry-validated approach, while kinematic, restricted-kinematic and (with the spread of robotics) functional alignment have substantial and growing adoption — particularly in Australasia and Europe, where much of the constitutional-alignment and CPAK work originated.
- What the evidence shows
- No difference; MA reference standard
- Best supporting evidence
- Level I 10-year RCT (Gibbons/Young 2024)
- What the evidence shows
- KA better on some scores (WOMAC/KSS/flexion)
- Best supporting evidence
- Meta-analysis (Liu 2022)
- What the evidence shows
- Better KSS/WOMAC, same revision rate
- Best supporting evidence
- Meta-analysis (Gao 2025)
- What the evidence shows
- Comparable at 2y, fewer releases
- Best supporting evidence
- Insall Award RCT (Young 2025)
- What the evidence shows
- CPAK (9 phenotypes)
- Best supporting evidence
- MacDessi 2021
National joint registries continue to validate the long-term survivorship of mechanically-aligned TKA, and long-term registry data for kinematic and functional alignment are still maturing. The pragmatic global position: mechanical alignment is the safe, validated default; individualised alignment is a reasonable, boundaried alternative that reduces soft-tissue releases and is increasingly executed with robotics, but its long-term superiority remains unproven and should be presented to patients as such.
Mnemonics & memory aids
MAKRFThe alignment spectrum
Hook:From limb-based (M) to joint-based (K), with bounded middle ground (R, F).
CPAKWhat CPAK is built from
Hook:CPAK = arithmetic HKA × joint-line obliquity → nine knee phenotypes (a language, not a technique).
Viva practice
Exam viva
Practise clinical reasoning and management decisions out loud
“An examiner asks you to outline the alignment philosophies in total knee arthroplasty and state which you would use.”
“A patient is unhappy a year after a well-performed, neutrally-aligned TKA - radiographs are textbook. How do you think about alignment here?”
Exam cheat sheet
- Frame it as a spectrum: MA (limb-based, reference standard) → KA (joint-line-based) with rKA and FA as bounded middle ground.
- Rationale for individualisation: constitutional alignment varies (most knees not neutral); MA neutralises everyone, altering the joint line and needing releases. CPAK = 9 phenotypes (aHKA + JLO).
- The honest evidence: short/medium-term meta-analytic gains for KA/rKA on some scores, but a Level I 10-year RCT shows NO PROM or survivorship difference → MA remains the reference standard.
- KA's long-term concern: residual tibial varus and an oblique joint line of unknown durability.
- FA: comparable to MA at 2y with far fewer releases (16% vs 65%); benefit is subgroup-specific (CPAK Type I).
- Don't present KA as proven superior, and don't blame an unhappy textbook-neutral knee on alignment by default.
The philosophies
- MA: neutral HKA, perpendicular cuts (reference standard)
- KA: restore constitutional joint lines
- rKA: kinematic within safe boundaries
- FA: robotic balance to the soft-tissue envelope
Concepts
- Constitutional alignment varies (most knees not neutral)
- CPAK: 9 phenotypes (aHKA + JLO)
- KA/FA need fewer soft-tissue releases
- KA concern: residual tibial varus / oblique joint line
The evidence
- 10y RCT: no PROM/survivorship difference (KA = MA)
- Meta-analyses: modest KA/rKA score gains (WOMAC/KSS)
- FA: comparable at 2y, far fewer releases (16% vs 65%)
- MA remains the validated reference standard
Clinical relevance: what the evidence actually shows
The honest synthesis — which is what a viva rewards — is that the evidence is nuanced and, at the highest level, equivocal:
- Short/medium-term signals favour individualised alignment on some measures. Meta-analyses of randomised trials report better WOMAC, Knee Society Scores and flexion for kinematic alignment versus mechanical, and restricted kinematic alignment similarly improves some functional scores — though many differences are small and not consistent across every outcome.
- The best long-term randomised evidence shows equivalence. A Level I RCT with 10-year follow-up found no difference in any patient-reported outcome or in survivorship between kinematic and mechanical alignment, mirroring its own 2-year and 5-year results, and concluded that mechanical alignment remains the reference standard.
- Functional alignment is comparable to mechanical at 2 years in randomised data, while requiring fewer soft-tissue releases, with benefits that appear subgroup-specific (notably CPAK Type I knees).
- The inconsistency is not random, and naming the pattern is what separates a good answer from a recited one. Look at which scores move. The positives in both meta-analyses sit on WOMAC and the Knee Society Score. The negatives sit on the Oxford Knee Score, the KOOS and the Forgotten Joint Score. That split is reproducible rather than noisy, and the FJS is the telling one, because it measures the very thing individualised alignment claims to deliver — a knee the patient stops noticing. It is null three times over: null in the restricted-kinematic meta-analysis, null as the designated primary endpoint of the functional-alignment randomised trial (64.4 versus 70.1, p=0.10), and null at ten years in the Level I kinematic-versus-mechanical trial. An intervention whose proposed mechanism is a more natural-feeling knee has repeatedly failed on the instrument built to detect a natural-feeling knee, while succeeding on older, broader scores. That does not make individualised alignment wrong, and the reduction in soft-tissue releases is a genuine and reproducible finding — but it means the case for it currently rests on surgical process (fewer releases, easier balance, less need to correct a knee towards a target it never had) rather than on demonstrated patient benefit, and you should say so in exactly those terms.
Individualised alignment (KA/rKA/FA) reliably reduces the need for soft-tissue releases and may offer small early functional or balance advantages in selected knees, but it has not been shown to improve long-term function or implant survivorship over mechanical alignment. MA remains the validated reference standard; individualised philosophies are reasonable, evolving alternatives best executed within safe boundaries and with robotic/navigated precision.
Evidence Base
No Difference in 10-year Clinical or Radiographic Outcomes Between Kinematic and Mechanical Alignment in TKA: A Randomized Trial
- Single-centre, multisurgeon RCT of 99 patients (50 mechanical, 49 kinematic alignment) with 10-year follow-up.
- No difference in any patient-reported outcome at 10 years; survivorship free from revision 96% (MA) vs 91% (KA), not significantly different (p = 0.38).
- Mirrors the same trial's 2- and 5-year results; the authors conclude mechanical alignment remains the reference standard, citing the unknown long-term impact of tibial component varus in KA.
The John N. Insall Award: Functional Versus Mechanical Alignment in Total Knee Arthroplasty: A Randomized Controlled Trial
- RCT in robotic TKA comparing functional alignment (n=123) and mechanical alignment (n=121).
- Functional alignment required far fewer soft-tissue releases (16% vs 65%); the primary outcome (Forgotten Joint Score) was comparable at 2 years.
- Some secondary scores favoured functional alignment (KOOS Symptoms and Quality of Life), with a specific benefit in CPAK Type I knees - the CONSTITUTIONALLY VARUS, APEX-DISTAL phenotype, not the neutral one, which is exactly the group in which mechanical alignment demands the largest departure from native anatomy; survivorship comparable.
The long-term equivalence of KA and MA comes from Gibbons et al. 2025 (DOI), the functional-vs-mechanical comparison from Young et al. 2025 (DOI), the short/medium-term meta-analytic signals from Liu et al. 2022 (DOI) and Gao et al. 2025 (DOI), and the CPAK classification from MacDessi et al. 2021 (DOI).