Prevention Strategies | MUA Timing | Revision Options | Outcomes
- MUA timing: Most effective between 6-12 weeks post-TKA, avoid after 6 months due to fracture risk
- Flexion under 90° significantly impacts activities of daily living and quality of life
- Risk factors, in order: preoperative ROM first - the review cited on this page calls it the most important risk factor, and it is the one you can measure in clinic before committing. Then previous knee surgery, occult infection, component malposition or overstuffing, CRPS, and age under 50
- Prevention is key: optimal component positioning, early mobilisation, aggressive physiotherapy
- Manipulation gains are markedly better early - 36.5 degrees of flexion gained versus 17, and final ROM 119 versus 95, comparing MUA within 12 weeks against later. But late is not futile: the systematic review cited here concludes MUA can still be effective performed late, and arthroscopy combined with MUA remains useful up to a year after the index knee. Act early; do not refuse a patient who presents late
- “MUA can be repeated if first attempt unsuccessful, but diminishing returns after second manipulation
- “Arthroscopic lysis of adhesions (3-6 months) has better outcomes than late revision
- “Component malposition (especially oversized femoral component) is a correctable mechanical cause
- “Always rule out infection and CRPS before attributing stiffness to arthrofibrosis alone
Overview and Epidemiology
A stiff knee replacement is one of the most common reasons for patient dissatisfaction after an otherwise technically successful arthroplasty. Stiffness requiring intervention has an incidence of 1-5%, and the working definition is flexion under 90° at 12 weeks after TKA.
Why 90° is the line. Flexion under 90° prevents normal activities of daily living: climbing stairs, rising from chairs, and getting into and out of vehicles. Mild stiffness, flexion of 90-110°, may not significantly affect function. The flexion each task needs:
- Walking - 0-70°
- Ascending stairs - 0-83°
- Descending stairs - 0-90°
- Sitting comfortably - 90-100°
- Rising from a chair - 95° minimum
- Tying shoes - 110-120°
Extension matters as well. Extension deficits over 10° cause limping, anterior knee pain and difficulty with level walking; the grading is under Clinical Assessment.
The expected course. Motion improves gradually with physiotherapy over the first 6 weeks, by which point the knee should have reached 90° of flexion at minimum. It typically plateaus at 110-120° by 12 weeks, and little further improvement is expected at 6-12 months.
Why timing matters. A knee that is not progressing by 6 weeks, or that plateaus under 90°, should be considered for intervention before the 12-week mark. Outcomes worsen significantly when treatment is delayed, so early recognition is critical.
Aetiology and Risk Factors
The knee before surgery. Preoperative flexion under 90° is the strongest predictor of stiffness. The other knee-specific factors:
- Flexion contracture over 10° - soft tissue contracture
- Previous knee surgery - scar tissue and adhesions
- Patella baja - extensor mechanism dysfunction
- Chronic effusion - synovial inflammation
Sex. The only sex-specific data on this page found no difference. In 5,414 revision TKAs the odds of needing manipulation were 1.0 for men versus women (p = 0.85). Female sex is widely quoted as a risk factor for stiffness and may yet prove to be one for primary TKA, but no study cited here supports a numerical multiplier, and the study that measured it directly found nothing. Do not quote a figure.
Age. Age under 50 is real and large: after revision TKA the odds of manipulation are 6.5 times higher (p less than 0.0001). Younger patients also carry higher expectations and activity demands.
Other patient factors. These add to the risk:
- BMI over 35 - mechanical disadvantage
- Diabetes - impaired healing, a tendency to fibrosis
- Smoking - delayed healing, fibrosis
- Inflammatory arthritis - rheumatoid and psoriatic arthritis
- Occult infection - persistent inflammation
- CRPS - sympathetic dysfunction impairs rehabilitation
- Poor pain tolerance and psychological overlay
What can be changed. Previous knee surgery, genetic predisposition, inflammatory arthritis and diabetes are not modifiable. Component positioning, gap balancing, joint line restoration, pain control, early mobilisation and psychological factors are, and prevention concentrates on them.
Technical causes. Each technical error has a recognisable mechanism and clinical finding, and a flexion-extension gap mismatch causes overstuffing.
- Mechanism
- Overstuffs patellofemoral joint, limits flexion
- Clinical Finding
- Anterior knee pain, inability to flex past 90°
- Prevention
- Template preoperatively, size down if between sizes
- Mechanism
- Patellar maltracking, Q-angle increase
- Clinical Finding
- Patella subluxation, anterior pain with flexion
- Prevention
- Use transepicondylar axis, avoid rotating internally
- Mechanism
- Patella baja, extensor mechanism tightening
- Clinical Finding
- Difficulty with stairs, anterior impingement
- Prevention
- Restore anatomical joint line (use distal femoral cut)
- Mechanism
- Overstuffed posterior compartment
- Clinical Finding
- Hard endpoint to flexion, pain
- Prevention
- Balance gaps, posterior femoral condyle recession
- Mechanism
- Overstuffing both flexion and extension
- Clinical Finding
- Global stiffness, pain throughout arc
- Prevention
- Choose thinnest poly for balanced gaps
Prevention starts in clinic. Template for component size, plan the osteophyte removal, set realistic goals from the preoperative range, and counsel patients with flexion under 90° about the risk of stiffness.
Prevention in theatre. These measures prevent the mechanical causes of stiffness:
- Restore joint line height to within 5mm of anatomic
- Balance the flexion and extension gaps to within 2mm
- Avoid oversizing, sizing down if borderline
- Set rotation from the transepicondylar axis and Whiteside's line
- Remove all osteophytes, especially posterior femoral
- Test motion on the table: at least 120° of flexion
Rehabilitation after the primary, the other half of prevention, is set out under Postoperative Care.
Anatomy and Biomechanics
Kinematics after TKA. The native knee flexes through 0-135°, and a typical TKA through 0-120°. With flexion the femur translates posteriorly by 10-15mm (rollback) and the tibiofemoral contact point moves posteriorly, while patellofemoral tracking is critical for pain-free flexion. Stiffness disrupts these kinematics through adhesions or mechanical impingement.
Where the scar forms. Primary arthrofibrosis targets the periarticular soft tissues with excessive collagen deposition:
- Suprapatellar pouch - the most common site; adhesions here limit flexion
- Posterior capsule - contracture limits flexion, and scar limits rollback
- Quadriceps and patellar tendons - shortening or tethering impairs gliding
- Periarticular soft tissue - inflammation causes global fibrosis
How the scar develops. Arthrofibrosis passes through four phases, and the phase decides what treatment can still achieve.
Inflammatory phase, 0-2 weeks. Surgical trauma triggers an inflammatory cascade with cytokine release (IL-1, TNF-α), fibrin deposition and myofibroblast activation. Clinically there is swelling, pain, and motion limited by effusion and muscle guarding. Prevention at this stage focuses on controlling inflammation and early mobilisation.
Proliferative phase, 2-6 weeks. Fibroblasts proliferate and deposit immature type III collagen, and adhesions form between the synovium and the surrounding tissues. Motion may plateau as the adhesions mature, with a "rubbery" endpoint to passive flexion. This is the window where aggressive physiotherapy is most effective, before the collagen matures.
Maturation phase, 6-12 weeks. Type III collagen is converted to type I, stronger and less elastic, and cross-linking increases the tensile strength of the scar. The endpoint is firm, adhesions are palpable, and motion is progressively lost if untreated. This is the optimal window for manipulation, before the collagen fully matures: maximal gain with minimal fracture risk.
Chronic phase, over 12 weeks. The scar is dense and mature with extensive cross-linking, and heterotopic ossification may develop in the posterior capsule. The endpoint is hard, physiotherapy brings minimal improvement, and the knee may feel like a "bony block" on examination. Manipulation is less effective and carries a higher fracture risk, so arthroscopic lysis or revision is considered.
Emerging evidence suggests genetic factors influence the fibrotic response after TKA:
- TGF-β1 polymorphisms - associated with increased collagen production
- MMP gene variants - reduced matrix metalloproteinase activity impairs scar remodelling
- Family history - patients with a family history of keloids or Dupuytren's contracture are at higher risk
None of this is modifiable, but awareness helps identify high-risk patients for closer monitoring of motion after surgery.
Joint line height. Elevating the joint line, through excessive distal femoral resection or an undersized femoral component, produces patella baja (Insall-Salvati ratio under 0.8), anterior impingement between the patella and the polyethylene insert, functional tightening of the extensor mechanism, and a mechanical block to flexion at 70-90°. It is a correctable mechanical cause: it needs revision to restore anatomical joint line height and does not respond to manipulation or physiotherapy alone.
Localising the Cause by the Arc Affected
Before labelling a stiff TKA "arthrofibrosis", note which part of the arc is lost: flexion, extension, or both. The pattern localises the mechanical cause and tells you which lever to pull at revision, because a knee tight only in flexion has a different problem from one that cannot fully extend.
- Likely mechanical cause
- Tight flexion gap; oversized or anteriorly-positioned femoral component; retained posterior femoral osteophytes; patella baja / elevated joint line; inadequate posterior tibial slope
- Corrective lever
- Downsize or reposition the femoral component, remove posterior osteophytes, restore joint-line height, reassess polyethylene thickness
- Likely mechanical cause
- Tight extension gap; retained posterior osteophytes tenting the capsule; posterior capsular contracture; under-resected distal femur
- Corrective lever
- Remove posterior osteophytes, posterior capsular release, recut distal femur or use a thinner polyethylene
- Likely mechanical cause
- Overstuffing (oversized components or polyethylene), true arthrofibrosis, infection, CRPS
- Corrective lever
- Exclude infection and CRPS first; downsize if overstuffed; MUA or arthroscopic lysis for arthrofibrosis
Tight in flexion only points to the flexion gap; unable to extend fully points to the extension gap; tight throughout suggests overstuffing, true arthrofibrosis, or - never forget - infection or CRPS. A uniformly stiff, hot, painful knee is infection until proven otherwise.
Patellar Clunk Syndrome and Patellar Crepitus
The lesion. Patellar clunk syndrome is a complication of posterior-stabilised (PS) designs, which have an intercondylar femoral box. A fibrous nodule forms at the junction of the posterior quadriceps tendon and the superior pole of the patella. As the knee actively extends from deep flexion (around 30-45 degrees) the nodule catches on the superior edge of the box and jumps free.
The symptom. A painful, audible or palpable clunk, classically on rising from a chair or climbing stairs. Suspect it when a "catching" or stiff PS TKA has a discrete, reproducible clunk, and distinguish it from the milder, diffuse patellar crepitus. Newer femoral box geometries have reduced its incidence.
- Patellar clunk
- Discrete fibrous nodule at the quadriceps-superior patella junction
- Patellar crepitus
- Diffuse peripatellar fibrosynovial tissue / softer scar
- Patellar clunk
- Painful audible or palpable clunk as the knee actively extends from flexion (around 30-45 degrees)
- Patellar crepitus
- Grinding or crepitus through the arc, usually milder
- Patellar clunk
- Nodule catches on the superior edge of the intercondylar femoral box of a posterior-stabilised implant
- Patellar crepitus
- Synovial tissue impinges in the patellofemoral track
- Patellar clunk
- Arthroscopic (or open) excision of the nodule, usually with peripatellar debridement - reliably relieves symptoms
- Patellar crepitus
- Often responds to observation and physiotherapy; arthroscopic debridement if persistent
Classification of TKA Stiffness
Stiffness is classified by cause, by severity and by timing, and each of the three changes what is done.
By cause. Stiffness is primary, an idiopathic fibrotic response, or secondary to a mechanical or inflammatory cause. Primary arthrofibrosis is a diagnosis of exclusion: correctable mechanical and inflammatory causes are always ruled out first.
- Definition
- Idiopathic fibrotic response, no clear cause
- Risk Factors
- Genetic predisposition, smoking
- Management Approach
- Early aggressive PT, MUA if persistent
- Definition
- Component malposition or sizing error
- Risk Factors
- Oversized components, malrotation, patella baja
- Management Approach
- Identify and correct mechanical cause
- Definition
- Infection, CRPS, inflammatory arthritis
- Risk Factors
- Wound complications, pain out of proportion
- Management Approach
- Treat underlying condition first
By severity. Flexion grades the stiffness, and the grade guides management. Type III stiffness often indicates an underlying mechanical problem that needs revision rather than manipulation alone. Flexion over 110° gives near-normal function.
- Flexion ROM
- 90-110° flexion
- Functional Impact
- Minimal ADL limitation, though cannot rise from low chairs; patient often satisfied
- Management
- Continue PT, consider MUA if patient desires more ROM
- Flexion ROM
- 70-90° flexion
- Functional Impact
- Cannot rise from chairs, stair difficulty
- Management
- MUA indicated at 6-12 weeks
- Flexion ROM
- Under 70° flexion
- Functional Impact
- Significant functional disability, wheelchair risk
- Management
- MUA likely to fail, consider arthroscopic lysis or revision
By timing. The time since surgery tracks the maturity of the scar, and it sets the treatment. The 6-12 week window is critical, and outcomes decline rapidly after it.
- Time since TKA
- Under 6 weeks
- What is happening
- Normal postoperative inflammation, pain-limited ROM
- Management
- Aggressive physiotherapy, pain control, reassurance. Too early for MUA - may improve with conservative measures
- Time since TKA
- 6-12 weeks
- What is happening
- Adhesions forming, collagen deposition
- Management
- The MUA window - most effective intervention period, success rate highest and fracture risk lowest
- Time since TKA
- 3-6 months
- What is happening
- Mature adhesions, established fibrosis
- Management
- Arthroscopic lysis of adhesions if MUA failed - better outcomes than late open revision
- Time since TKA
- Over 6 months
- What is happening
- Dense mature scar, component malposition
- Management
- Revision TKA to correct mechanical causes. MUA carries a high fracture risk - avoid
Clinical Assessment
History. The pattern of onset and pain points towards the cause:
- Onset - gradual or sudden; sudden suggests a component problem
- Progression - improving, static or worsening
- Pain - anterior points to the patellofemoral joint, global to overstuffing
- Functional loss - the specific activities affected
- Compliance - physiotherapy attendance and home exercise
- Previous surgery - prior procedures increase risk
- CRPS symptoms - pain out of proportion, allodynia
Examination. Measure flexion actively and passively and feel the endpoint, hard or soft. Any flexion contracture over 10° is significant, and an extension deficit shows as a limp. Persistent wound drainage suggests infection, a chronic effusion suggests infection or instability, and patellar maltracking suggests a rotation error. Allodynia and temperature change are the neurovascular signs of CRPS.
Measuring motion. Use a goniometer with the patient supine and the knee over the edge of the bed, measuring actively and passively. Record flexion (normal 0-120°) and extension (normal 0°, a positive number meaning a flexion contracture) separately; the arc of motion is flexion minus extension lag. Extension deficit grades gait:
- 0-5° - normal gait pattern
- 5-10° - mild limp, anterior knee pain
- Over 10° - significant gait abnormality
Infection is the most important diagnosis not to miss. Its warning signs are persistent wound drainage, fever and a raised CRP/ESR, and the threshold for aspiration is low if there is any suspicion.
Three causes of a stiff or painful TKA are not in the table below:
- Component loosening - pain with weight-bearing, radiolucent lines
- Instability - giving way, effusion, pain with pivoting
- Periprosthetic fracture - sudden onset after manipulation
Differential diagnosis. Each cause of restricted motion has a feature that separates it and a test that confirms it.
- Typical Features
- Gradual ROM loss, soft/'rubbery' endpoint, no malposition
- Key Discriminator
- Diagnosis of exclusion once mechanical and infective causes excluded
- Confirmatory Test
- Normal inflammatory markers and well-positioned components on imaging
- Typical Features
- Effusion, warmth, rest/night pain, persistent drainage
- Key Discriminator
- Pain out of proportion with raised inflammatory markers
- Confirmatory Test
- ESR/CRP then synovial aspiration (cell count, culture, alpha-defensin)
- Typical Features
- Hard mechanical block, anterior pain, maltracking patella
- Key Discriminator
- Hard endpoint plus malrotation/oversizing on CT
- Confirmatory Test
- CT with metal-artefact reduction (rotation, sizing)
- Typical Features
- Anterior impingement, difficulty on stairs, flexion block
- Key Discriminator
- Low Insall-Salvati ratio (under 0.8), elevated joint line
- Confirmatory Test
- Lateral radiograph (patellar height, joint-line measurement)
- Typical Features
- Allodynia, swelling, temperature/colour change, disproportionate pain
- Key Discriminator
- Pain and autonomic signs out of proportion to findings
- Confirmatory Test
- Clinical (Budapest criteria); imaging to exclude other causes
- Typical Features
- Progressive loss of ROM, palpable firmness or mass, late presentation
- Key Discriminator
- Bone formation (often posterior capsule) limiting the arc
- Confirmatory Test
- Radiographs / CT showing ectopic bone
Investigations
Radiographs first. AP, lateral and skyline patellar views. The aim is to identify any correctable mechanical cause before planning manipulation or revision:
- Component position and alignment, with rotation on the AP and lateral
- Joint line height - within 5mm of the contralateral side
- Patellar height - an Insall-Salvati ratio under 0.8 is patella baja
- Overstuffing
- Heterotopic ossification in the posterior capsule
- Loosening - radiolucent lines, subsidence
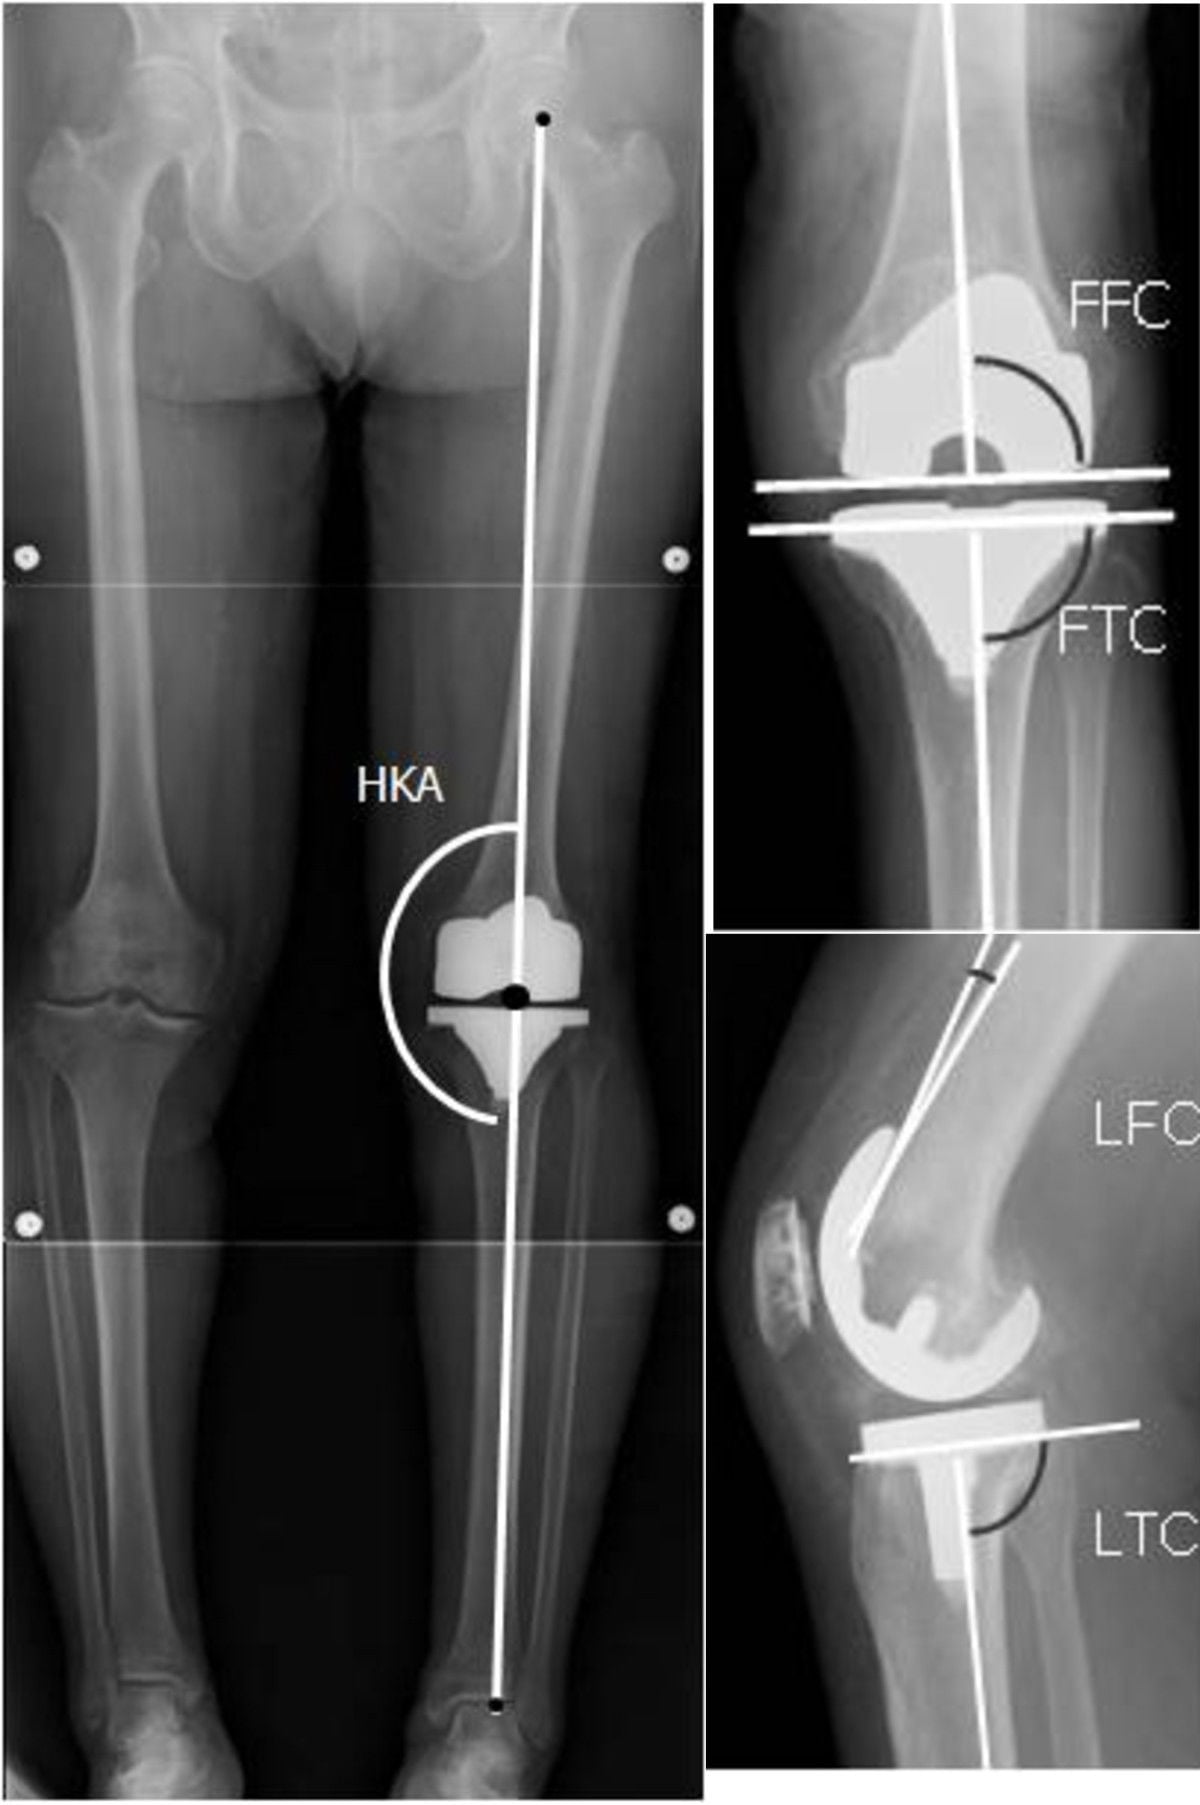
Bloods if infection is suspected. Infection must be ruled out before any manipulation or revision:
- ESR over 30mm/hr - concerning
- CRP over 10mg/L - concerning at 6 weeks or more after TKA
- White cell count - usually normal even in infection
Aspiration. If the ESR or CRP is raised, or there is clinical suspicion, the synovial fluid is analysed:
- Cell count over 3000 cells/μL - concerning
- Neutrophil (PMN) percentage over 80% - concerning
- Culture - the gold standard, but may be negative
- Alpha-defensin - high sensitivity for infection
CT for planning. CT with metal artefact reduction is most useful when planning revision for component malposition. It assesses femoral and tibial component rotation, identifies anterior bony or soft-tissue impingement, and measures alignment against the mechanical axis.
MRI. Rarely indicated. It assesses the soft tissues when lysis of adhesions is being considered, and the integrity of the extensor mechanism.
Management Algorithm
Cause before timing. Infection, CRPS and fracture are ruled out first, and imaging looks for a mechanical cause: component malposition, overstuffing, patella baja or a joint-line error. A mechanical cause goes down the revision pathway at any time, because physiotherapy alone will fail and manipulation alone is not relied on. Only when there is none does timing decide the treatment.
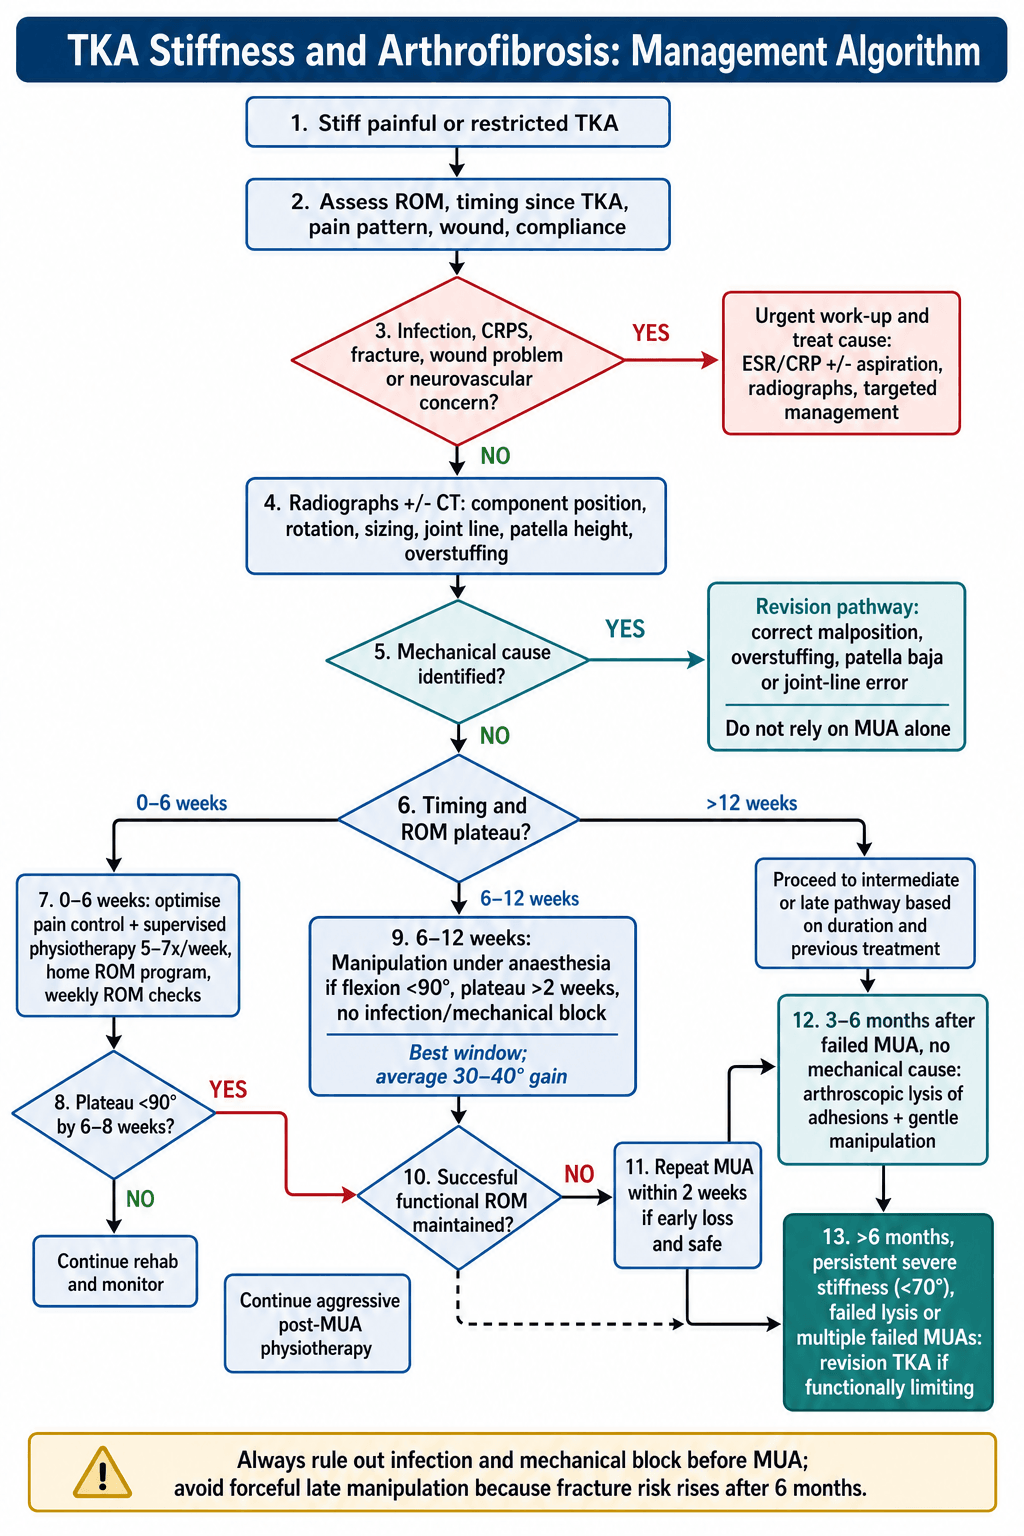
Who. Conservative treatment is for the knee under 6 weeks from surgery with slow but improving motion, typically flexion of 70-90°:
- Flexion over 70° and progressing
- No mechanical cause identified
- A patient compliant with physiotherapy
Pain control. Multimodal analgesia, with paracetamol, and NSAIDs if not contraindicated. Opioids are limited because they impair motivation for rehabilitation, and CRPS is addressed early if suspected.
Physiotherapy. Five to seven sessions a week initially, progressing motion in both flexion and extension, with heat before stretching and ice after. The home programme is heel slides, wall slides and prone hangs, and the goal is a gain of 10-15° of flexion a week.
Knowing when to stop. Measure motion weekly. A plateau under 90° by week 6 means planning manipulation before week 12, and if there is no improvement by 6-8 weeks, conservative management has failed and intervention is indicated. Physiotherapy is not continued indefinitely without progress.
When the first manipulation fails. Failure means a gain under 10°, or motion lost within 2 weeks. The options:
- Repeat MUA within 2 weeks - success rate 50-60%
- Arthroscopic lysis at 3-6 months, if there is no mechanical cause
- Revision TKA if a mechanical cause is identified
- Accept the limitation if flexion is over 90° and the patient is satisfied
What not to do is continue physiotherapy indefinitely without progress, or manipulate repeatedly after two attempts, with diminishing returns and an increasing fracture risk.
Surgical Technique: Manipulation Under Anaesthesia
Before theatre. Rule out infection with a recent CRP and ESR, and consider aspiration. Review the imaging to confirm there is no component malposition, and arrange immediate aggressive physiotherapy for afterwards. The ideal timing is 6-12 weeks; avoid manipulation after 6 months.
Consent. Discuss realistic goals for motion and the specific risks: fracture of the supracondylar femur, tibial plateau or patella; loss of some of the gain over time; the need for a second manipulation if the first is unsuccessful; no improvement; the standard risks of a general or spinal anaesthetic; and revision if an underlying mechanical cause is found. The figures are in the complications table.
Anaesthesia. General or spinal, as long as it gives complete muscle relaxation.
Technique. Gentle progressive force is safer than a single aggressive manipulation, and the whole procedure takes 5-10 minutes.
- Position. Supine on a standard operating table, the leg free-draped to allow full range, the surgeon at the side of the operative knee. An assistant is optional and can provide counter-pressure. No tourniquet, so that the vascular status can be assessed.
- Examine under anaesthesia. Document passive flexion and extension before manipulating, feel the endpoint (hard means a mechanical block), and palpate for effusion and crepitus. A hard mechanical block means stopping and obtaining imaging, because revision may be needed.
- Extension first. This step is often overlooked. With a hand under the heel, apply gentle extension force aiming for full extension (0°). With a flexion contracture over 10° a "pop" may be heard or felt as the adhesions release. Avoid hyperextension force, which risks the PCL.
- Longitudinal traction. With one hand on the proximal tibia and one on the distal femur, traction along the tibial axis distracts the joint and reduces the compression force on the components during flexion.
- Progressive flexion. One hand stabilises the femur and the other flexes through the proximal tibia with steady force, in 10-15° increments, listening for crepitus or a "pop" as the adhesions break. The goal is at least 120° of flexion; sudden jerking movements risk fracture.
- Final assessment. Record the maximum passive flexion achieved and cycle through the range several times. Check MCL and LCL stability for laxity after the manipulation, examine for crepitus (component damage), and palpate for effusion or haematoma.
Afterwards. Both knees can be manipulated in the same session if needed. Aggressive physiotherapy starts on day 1, and CPM can be considered, though it is controversial; the protocol is under Postoperative Care.
The highest-risk patients have osteoporosis (T-score under -2.5), long-stemmed revision components, rheumatoid arthritis with its poor bone quality, or a knee more than 6 months from surgery, with mature bone ingrowth. The supracondylar femur is the most common fracture; the tibial plateau and patella can also break.
If a fracture is suspected, obtain radiographs immediately after the manipulation, before the patient wakes, and proceed directly to fixation if one is found. Prevention is gentle progressive force, no manipulation after 6 months, and DEXA screening in high-risk patients.
Complications
The complications of manipulation, with their incidence, what raises the risk, and how each is managed:
- Incidence
- 1-3% overall, 5-10% after 6 months
- Risk Factors
- Osteoporosis, late manipulation, excessive force
- Management
- ORIF with locking plate, may need revision to long stem
- Incidence
- 30-40% lose some ROM over time
- Risk Factors
- Poor PT compliance, mechanical cause unaddressed
- Management
- Repeat MUA if within 6 months, revision if mechanical
- Incidence
- 5-10% significant bleeding
- Risk Factors
- Anticoagulation, aggressive force
- Management
- Ice, compression, aspiration if tense
- Incidence
- Under 1% with proper technique
- Risk Factors
- Excessive varus/valgus stress during manipulation
- Management
- Bracing, may require ligament reconstruction
- Incidence
- 15-25% see minimal ROM gain
- Risk Factors
- Mechanical cause, mature adhesions (over 12 weeks)
- Management
- Consider arthroscopic lysis or revision
- Incidence
- Under 1% (similar to primary TKA)
- Risk Factors
- Haematoma, wound compromise
- Management
- Aspiration, antibiotics, possible I&D
Postoperative Care and Rehabilitation
Day 0-1. The goals are to control pain and swelling and protect the range achieved. Multimodal analgesia (paracetamol, NSAIDs, consider a regional block) avoids over-reliance on opioids, with cryotherapy for 20 minutes every 2 hours and elevation at rest. CPM runs 6-8 hours a day: its benefit is controversial, but it may help pain. Motion is measured with a goniometer within 24 hours, and weight-bearing is as tolerated.
Days 2-7. Physiotherapy twice daily, inpatient or at home, to maintain the range achieved at manipulation and begin active exercises. Sessions combine active and active-assisted exercises (heel slides, wall slides), passive stretching by the therapist, quadriceps sets and ankle pumps, with ice after each session. The goal is to stay within 5-10° of the post-manipulation range, documented daily by the physiotherapist.
Weeks 2-6. The critical period. Physiotherapy runs five to seven sessions a week, with a home programme three times a day (heel slides, prone hangs, wall slides), progressive quadriceps and hamstring strengthening, and functional work on stairs and transfers. Motion is measured weekly and should hold or improve slightly; a plateau or a loss of over 10° prompts consideration of a repeat manipulation within 2 weeks.
Weeks 6-12. Physiotherapy three to four sessions a week, progressing to simulated daily activities (car transfers, prolonged sitting) with daily home exercises, aiming for a return to normal activities by 12 weeks. A gradual 5-10° loss of flexion from the peak is expected and acceptable. Motion is recorded monthly, and driving resumes when flexion is over 90° and comfortable.
Beyond 12 weeks. Physiotherapy as needed for maintenance, the home programme three to four times a week indefinitely, and annual follow-up with documented motion. A gradual loss is accepted while motion stays over 90°, the functional threshold, but a sudden loss is a red flag for infection or a component problem.
With poor compliance, 40-50% of patients lose all their gains from manipulation within 6 weeks. Home exercises, three times a day at minimum, are as important as formal sessions, and passive therapy alone is insufficient: the patient has to take an active part. Consider the psychological barriers to compliance, such as depression, low motivation and pain catastrophising.
Patient compliance with home exercises, 5-7 times a week at minimum, is one of the critical success factors after manipulation.
The surgeon's part is to start physiotherapy immediately (it cannot wait 1-2 weeks), monitor motion weekly for the first 6 weeks, keep a low threshold to intervene on a plateau or loss, with a repeat manipulation if significant motion is lost within 2 weeks, and make sure the patient understands they cannot be a passive recipient of care. Physiotherapy after manipulation is as important as the manipulation itself.
Outcomes and Prognosis
What predicts a good manipulation. Five factors separate good results from poor ones:
- Good Prognosis
- 6-12 weeks post-TKA (75-85% success)
- Poor Prognosis
- Over 12 weeks (50% success) or over 6 months (under 30%)
- Good Prognosis
- Over 70° before MUA (better baseline)
- Poor Prognosis
- Under 70° (likely mechanical cause)
- Good Prognosis
- Primary arthrofibrosis (idiopathic)
- Poor Prognosis
- Mechanical malposition (requires revision)
- Good Prognosis
- Aggressive PT 5-7x/week
- Poor Prognosis
- Poor PT compliance (ROM loss)
- Good Prognosis
- Primary TKA only
- Poor Prognosis
- Multiple prior surgeries (more scar)
Motion after a successful manipulation. Some loss over time is expected, but most patients keep functional motion over 90° if the initial manipulation succeeded:
- Immediately - average 120° of flexion
- 6 weeks - typically 110-115°, a 5-10° loss
- 3 months - stabilises at 105-110°
- 1 year - 60-70% maintain motion within 10° of their post-manipulation flexion
- 2 years - 30-40% experience further loss, usually still functional over 90°
Function. With flexion over 90° after successful treatment, independent daily activities, stair climbing and driving return, and patient satisfaction is 70-80%. With persistent flexion under 90°, daily activities are significantly limited, assistive devices are needed, driving is unsafe, and 60-70% are dissatisfied.
Satisfaction. Patients value functional improvement over absolute numbers of degrees. What satisfies them is absolute motion over the 90° threshold, a gain of 20° or more (perceived as meaningful), relief of anterior knee pain, the ability to do what they want, and expectations set by realistic counselling before surgery.
Guidelines, Registries & Global Practice
Global Epidemiology
- Stiffness needing intervention: ~1-5% of primary TKAs; a single-centre European series reported a 4.5% MUA rate (Ipach 2011)
- After revision TKA: ~1.7% require MUA, most within 3 months (Dowdle 2018, US database of 5,414 revisions)
- Strongest patient predictors: low pre-operative ROM, younger age, previous knee surgery, inflammatory arthritis
- Stiffness is a leading cause of dissatisfaction despite a technically sound implant, and a recognised but uncommon revision indication worldwide
- No single agreed numeric definition; commonly flexion under 90° and/or a flexion contracture over 10° with functional limitation
- Functional thresholds are broadly consistent across guidelines: ~83° to descend stairs, ~90-95° to rise from a chair
- Reported incidence depends heavily on the threshold and the denominator (primary vs revision), explaining the wide 1-5% range
Guidance and Consensus, Side by Side
- Position on Stiffness & MUA
- Emphasises optimal component positioning, gap balancing and early structured rehabilitation; MUA reserved for failure of supervised therapy, ideally early.
- Evidence Level
- Mostly Level III-IV (expert/registry-informed)
- Position on Stiffness & MUA
- Supports structured post-TKA rehabilitation; reserves manipulation/surgery for persistent functional restriction after physiotherapy. No routine CPM.
- Evidence Level
- Guideline-level, low-moderate underlying evidence
- Position on Stiffness & MUA
- Routine CPM not justified - no clinically important effect on ROM, pain or function (RCT meta-analysis).
- Evidence Level
- Level I (24 RCTs)
- Position on Stiffness & MUA
- Low threshold for MUA within 12 weeks; markedly better flexion gain and Knee Society scores than late MUA.
- Evidence Level
- Level III
- Position on Stiffness & MUA
- Track stiffness/arthrofibrosis as a discrete revision indication; outcomes better than revision for infection or instability when a mechanical cause is corrected.
- Evidence Level
- Registry (Level III)
Registry Evidence
- AOANJRR (Australia), NJR (England & Wales), AJRR (USA) all record stiffness/arthrofibrosis as a distinct, relatively uncommon reason for revision (typically a single-digit percentage of all TKA revisions)
- Peak timing for stiffness-related revision is within the first 6-12 months after the primary
- Re-revision burden is lower for stiffness than for infection or instability
- Registries cannot capture MUA or arthroscopic lysis (non-revision procedures), so they underestimate the true stiffness burden
- Most stiffness is managed without revision - physiotherapy, then MUA, then arthroscopic lysis
- Revision gives good results only when a correctable mechanical cause is identified (malrotation, oversizing, joint-line elevation, patella baja)
- Counsel patients that registry-defined "revision for stiffness" represents the severe end of a much larger spectrum
Key documentation requirements:
Preoperative consent (primary TKA):
- Discuss stiffness risk (1-5% require intervention)
- Document preoperative ROM (low preop ROM predicts postop stiffness)
- Set realistic expectations for ROM improvement
Postoperative management:
- Document ROM at each visit (objective measure)
- Document physiotherapy compliance and progress
- If ROM not improving by 6 weeks, document discussion of MUA option
MUA consent:
- Fracture risk (1-3%, higher if osteoporotic or over 6 months)
- Recurrence risk (30-40% lose some ROM over time)
- Need for repeat MUA or revision if unsuccessful
- Aggressive PT requirement postoperatively
Common litigation issues:
- Delayed recognition of stiffness (waiting too long past 12-week optimal window)
- Component malposition not identified before MUA (should obtain imaging)
- Fracture during MUA in high-risk patient (should screen for osteoporosis)
- Inadequate postoperative physiotherapy arrangement (ROM gains lost)
Defensive strategies:
- Image all stiff knees before MUA (rule out mechanical cause)
- Document ROM objectively with goniometer at each visit
- Discuss MUA early if ROM plateaus under 90° before 12 weeks
- Obtain DEXA in high-risk patients before MUA after 3 months
Global Practice Variation
Where management genuinely differs by region or resource setting:
- CPM use: still common in some North American and parts of European practice despite Level I evidence (Harvey 2014) showing no clinically important benefit; many UK and Australasian units have abandoned routine CPM. The world standard is early active mobilisation and structured physiotherapy.
- Rehabilitation intensity and access: high-resource systems offer frequent supervised physiotherapy, lowering the threshold for early MUA within the 12-week window; in limited-resource settings, home-based or less frequent therapy delays recognition, so stiffness may present later and beyond the optimal MUA window.
- Timing thresholds: most groups favour MUA within 12 weeks (Issa 2014), but some retain a benefit window out to ~6 months before moving to arthroscopic lysis/open arthrolysis (Fitzsimmons 2010), reflecting genuine uncertainty at the margins.
- Referral and follow-up cadence (a sensible global default): physiotherapy review at ~2, 6 and 12 weeks; surgeon review at 6 weeks if flexion under 90°; arrange MUA promptly when indicated within the optimal window; cross-sectional imaging (CT) if a mechanical cause is suspected.
MCQ Practice Points
Q: What is the optimal timing window for manipulation under anesthesia after TKA? A: 6-12 weeks post-TKA. Success rate is highest (75-85%) in this window because adhesions are forming but collagen has not yet matured and cross-linked. After 12 weeks, success drops to 50% or lower. After 6 months, fracture risk increases significantly (5-10%) due to mature bone ingrowth around components.
Q: Which intraoperative technical factor is most commonly associated with postoperative TKA stiffness? A: Femoral component oversizing. Oversizing the femoral component overstuffs the patellofemoral joint, increases patella contact stress, and mechanically limits flexion. This is preventable by templating preoperatively and sizing down if between sizes. Other mechanical factors include internal rotation (femoral or tibial), elevated joint line, and tight flexion gap.
Q: What is the minimum flexion required for activities of daily living, and why is this threshold clinically important? A: 90° flexion. This threshold allows stair climbing (83° required for descent), rising from standard chair (95° ideal but 90° minimum), and entering/exiting vehicles. Flexion under 90° causes significant functional disability and is the definition of TKA stiffness requiring intervention. Extension to 0° is also critical for normal gait.
Q: What is the most serious complication of manipulation under anesthesia after TKA, and what factors increase this risk? A: Supracondylar femur fracture (1-3% overall incidence). Risk factors include osteoporosis (T-score under -2.5), manipulation after 6 months post-TKA (mature bone ingrowth makes fracture more likely), long-stemmed revision components (stress riser), and excessive force. Prevention includes gentle progressive manipulation, pre-screening with DEXA in high-risk patients, and avoiding manipulation after 6 months.
Q: A patient has flexion of 70° at 4 months post-TKA despite two MUAs. Radiographs show proper component alignment. What is the next step in management? A: Arthroscopic lysis of adhesions. At 4 months, the patient is in the 3-6 month window where arthroscopic lysis has better outcomes than open revision TKA. Two failed MUAs indicate mature adhesions unlikely to respond to further manipulation. If no mechanical cause on imaging (ruled out component malposition, patella baja, overstuffing), arthroscopic débridement of suprapatellar scar and adhesion release is the next step before committing to revision surgery.
Q: What does the evidence show regarding continuous passive motion (CPM) machines for preventing TKA stiffness? A: CPM does NOT meaningfully improve final ROM, pain or function. The Cochrane review (Harvey et al, 2014; 24 RCTs, 1,445 patients) found CPM increased short-term active flexion by only about 2° - not clinically important - with no clinically important effect on pain, function or quality of life. A possible reduction in manipulation rate (control 7.2% vs CPM 1.6%) rests on very low-quality evidence. Early active mobilisation and structured physiotherapy are the priorities, and routine CPM is not justified.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 68-year-old woman is 8 weeks post-TKA. She is compliant with physiotherapy but has plateaued at 80° flexion for the past 2 weeks. She can walk with a cane but cannot climb stairs or rise from a standard chair. Examination shows flexion 80° actively and passively, extension lag 5°, no effusion, wound healed, neurovascularly intact. What is your assessment and management?”
“Walk me through your technique for manipulation under anesthesia for this patient. What are the key steps, and what complications are you trying to avoid?”
“The same patient underwent MUA at 10 weeks with immediate postoperative flexion of 110°, but at 6-week follow-up she is back to 75° flexion despite compliant physiotherapy. CT scan shows internal rotation of the femoral component by 8° relative to the transepicondylar axis. How do you manage this now?”
Key Definitions
- Stiffness = flexion under 90° at 12 weeks post-TKA with functional limitation
- Functional threshold = 90° flexion (stair climbing, chair rising, vehicle entry)
- Extension deficit over 10° causes limping and anterior knee pain
- Incidence requiring intervention = 1-5% of all TKAs
Risk Factors
- Previous surgery (prior knee procedures increase fibrosis)
- Technical malposition (oversizing, internal rotation, elevated joint line)
- Active infection (rule out with ESR/CRP before MUA)
- Preoperative flexion - THE dominant risk factor; the review cited here calls preoperative ROM the single most important one
- Age under 50: odds of MUA 6.5x higher after revision TKA. Female sex is not listed - the only sex-specific study cited here found odds of 1.0, p = 0.85
MUA Timing and Technique
- Optimal window = 6-12 weeks post-TKA (75-85% success)
- Success drops to 50% after 12 weeks, under 30% after 6 months
- Technique: Extension first, then progressive flexion with traction to 120° goal
- Complications: Fracture 1-3% (supracondylar femur most common), recurrence 30-40%
- Postop aggressive PT critical to maintain ROM gains
Management Algorithm
- Under 6 weeks + improving = aggressive PT, pain control, wait
- 6-12 weeks + flexion under 90° = MUA (best success window)
- 3-6 months + failed MUA = arthroscopic lysis of adhesions
- Mechanical cause identified = revision TKA to correct (not MUA)
- Always rule out infection and CRPS before attributing to arthrofibrosis
Revision Indications
- Component rotation (internal rotation over 5° significant)
- Polyethylene (downsize if overstuffed)
- VMO release (vastus tethering)
- Anterior impingement (patella baja, femoral overhang)
- Femoral component size (downsize if oversized)
Evidence Base and Key Studies
Effect of Timing of Manipulation Under Anaesthesia on ROM and Functional Outcomes After TKA
- Review of 144 manipulations among 2,128 TKAs; stratified by timing (under 6 weeks, 7-12 weeks, 13-26 weeks, over 26 weeks)
- Early MUA (under 12 weeks): mean flexion gain 36.5° vs 17° for late MUA
- Early MUA: higher final ROM (119° vs 95°) and higher Knee Society objective (89 vs 84) and function (88 vs 83) scores
- No significant difference between Group I (under 6 weeks) and Group II (7-12 weeks)
- Manipulation after 26 weeks gave unsatisfactory clinical outcomes
- The 144 manipulations were performed in 133 patients (88 women, 45 men), so a minority underwent more than one
- Mean follow-up was 51 months (range 12 to 81), and a MEDIATION ANALYSIS showed that timing contributed to outcome independently of the range-of-motion gain itself - the timing effect is not simply a proxy for how much motion was won on the table
Stiffness in Total Knee Arthroplasty
- Narrative review of the pathogenesis, risk factors and treatment of the stiff TKA
- Pre-operative range of motion identified as the most important patient risk factor
- Associations described with diabetes, reflex sympathetic dystrophy, juvenile RA and ankylosing spondylitis
- Surgery-related factors (soft-tissue imbalance, component malpositioning, incorrect sizing) cited as the most common cause
- Closed manipulation and arthrolysis give unpredictable results; revision is reserved for documented surgical error
How to Treat the Stiff Total Knee Arthroplasty? A Systematic Review
- Systematic review of 20 studies (mostly Level IV) on MUA, arthroscopy and open arthrolysis for the stiff TKA
- ROM gains after MUA and after arthroscopy (with or without MUA) are broadly similar; open arthrolysis gives inferior gains
- MUA is more successful when performed early but can still be effective when performed late
- Arthroscopy combined with MUA remains useful up to 1 year after the index TKA
- Clinically important complication rates are similar for MUA and arthroscopy