Notta's Node | A1 Pulley Stenosis | Observation vs Surgery Decision
- Notta's Node = palpable FPL tendon nodule at A1 pulley - pathognomonic finding
- NOT truly congenital - rarely noticed before 6 months, likely acquired in infancy
- Spontaneous resolution is common, but the reported rate ranges from about a third to three-quarters - 32% at 5 years in a US cohort, 37% at 5 and 50% at 8 years in a Singaporean one, 63% then 76% in Korean cohorts followed longer. Two things drive the spread: how long you wait, and how many families elect surgery before resolution has a chance to occur. Median time to resolution is around 48 months, so it is NOT complete by age 3
- No steroid injections in children - unlike adult trigger finger
- A1 pulley release is definitive treatment - near 100% success rate
- “Notta's node = FPL nodule at A1 pulley = pathognomonic
- “Not congenital - acquired, presents after 6 months
- “Thumb most common digit (opposite to adults where ring/middle)
- “Radial digital nerve at risk during release - crosses palmar to surgical site
Overview and Epidemiology
What it is. Paediatric trigger thumb is a stenosing tenosynovitis of the flexor pollicis longus (FPL) tendon at the A1 pulley. It is often called "congenital trigger thumb", but it is not truly congenital: it is rarely present at birth, most cases are noticed after 6 months of age, and it is thought to be acquired in early infancy. Calling it congenital is a common exam trap.
True congenital conditions are present at birth. Trigger thumb is extremely rare in neonatal screening examinations but becomes apparent at 6-12 months, which suggests an acquired pathology developing after birth.
Who. It affects 0.3-0.5% of children, approximately 3 per 1000, and is typically noticed between 6 months and 3 years. Boys and girls are affected equally. Roughly 16-30% of cases are bilateral (16% in the Leung series of 209 thumbs, PMID 21979473), so both thumbs are always examined. It is usually sporadic, not genetic, and has no strong association with other congenital hand anomalies.
Why it happens. The cause is unknown, and the theories are:
- Size mismatch: the FPL tendon grows faster than the A1 pulley, causing stenosis
- Repetitive microtrauma: thumb sucking or gripping patterns
- Intrinsic tendon abnormality: primary FPL nodule formation
Not the adult disease. Paediatric trigger thumb is not the childhood version of adult trigger finger, and the differences decide management. Steroid injection, first-line in the adult, is not used in children, because of concerns about steroid effects on developing tissues and because of the high rate of spontaneous resolution.
- Paediatric Trigger Thumb
- Thumb (95%+)
- Adult Trigger Finger
- Ring finger, then middle
- Paediatric Trigger Thumb
- Unknown - NOT overuse
- Adult Trigger Finger
- Overuse, inflammation, diabetes
- Paediatric Trigger Thumb
- About a third to three-quarters, over roughly 4 years
- Adult Trigger Finger
- Rare
- Paediatric Trigger Thumb
- A1 pulley release
- Adult Trigger Finger
- A1 pulley release
- Paediatric Trigger Thumb
- Near 100%
- Adult Trigger Finger
- 95-97%
Pathophysiology and Mechanisms
The thumb pulleys. The thumb's pulley system differs from the fingers', and the A1 pulley at the MCP joint is where triggering occurs.
- Location
- MCP joint level
- Function
- Primary site of triggering
- Location
- Proximal phalanx
- Function
- Main stabiliser
- Location
- IP joint
- Function
- Variable anatomy
Notta's node. The characteristic finding is a palpable nodule of the FPL tendon at the level of the A1 pulley, formed of metaplastic fibrocartilage within the tendon. The nodule becomes entrapped proximal to the A1 pulley and prevents extension of the IP joint. It may be present without triggering if it remains proximal to the pulley.
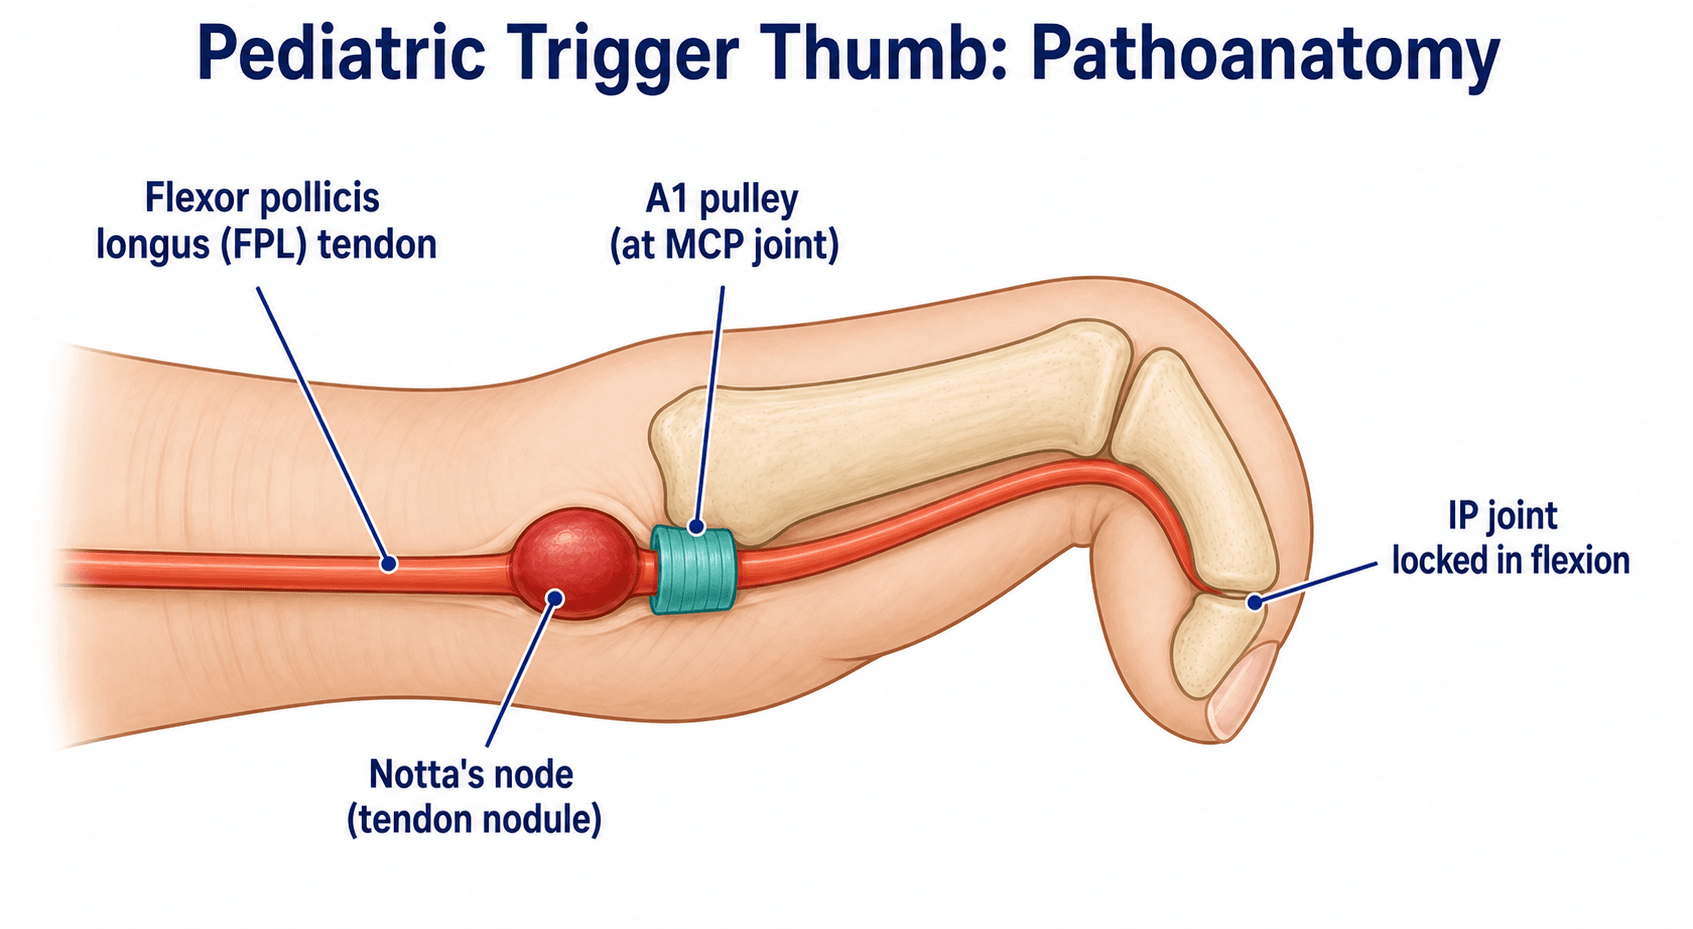
The surgical anatomy. The A1 pulley lies at the MCP joint crease, with the FPL tendon running through it and the sesamoids deep to it. The ulnar digital nerve lies in a dorsal position and is more protected than the radial.
The radial digital nerve of the thumb is at greatest risk during A1 pulley release. It crosses palmar to the surgical site at the level of the MCP crease, and it may be tethered by the natatory ligament, which limits its mobility.
Classification Systems
Severity grading. Trigger thumb is graded by the severity of presentation, from a history of catching to a flexion contracture that cannot be extended passively. Most paediatric cases present as Grade III or IV, with fixed IP flexion.
- Description
- Pain or history of catching
- Clinical Finding
- No locking, Notta's node palpable
- Treatment
- Observation
- Description
- Demonstrable catching
- Clinical Finding
- Actively correctable triggering
- Treatment
- Observation or surgery
- Description
- Locking
- Clinical Finding
- Passively correctable fixed flexion
- Treatment
- Surgery if over age 3
- Description
- Fixed flexion contracture
- Clinical Finding
- Cannot extend passively
- Treatment
- Surgery recommended
Age matters more than grade. In adult trigger finger the grade guides treatment; in the child the age is more important in deciding management, and even Grade IV thumbs may resolve spontaneously in children under 18 months. The age bands, with their resolution rates, are set out under Management.
Clinical Assessment
The presentation. Parents usually say the thumb is always bent, that it makes a clicking sound, or that the child cannot straighten it. Pain on moving the thumb is a less common complaint.
Examination. Work through the thumb in order:
- Inspection: fixed flexion of the IP joint, typically 25-30 degrees
- Palpation: Notta's node at the MCP crease, which feels like a small pea
- Active extension: the child cannot actively extend the IP joint
- Passive extension: may be possible, with a palpable or audible click
- Contralateral thumb: always examine it for bilateral involvement
FLEXFLEX - Clinical Features
Hook:FLEXion deformity with Lump = paediatric trigger thumb
The differential. Other causes of a flexed thumb in a child are separated by the joint involved and by the absence of Notta's node. Clasped thumb and trigger thumb are different conditions requiring different management.
- Joint involved
- IP joint (fixed flexion)
- Notta's node
- Present (palpable at A1 pulley)
- Key differentiating feature
- Pathognomonic FPL nodule; isolated IP flexion
- Joint involved
- MCP joint (flexion + adduction)
- Notta's node
- Absent
- Key differentiating feature
- Thumb-in-palm; deficient/absent extensor (EPL/EPB) tendons
- Joint involved
- Variable / unstable
- Notta's node
- Absent
- Key differentiating feature
- Underdeveloped thenar muscles, unstable MCP (Blauth classification)
- Joint involved
- Multiple joints, symmetrical
- Notta's node
- Absent
- Key differentiating feature
- Multiple congenital contractures; rigid; other limbs involved
- Joint involved
- MCP and IP, dynamic
- Notta's node
- Absent
- Key differentiating feature
- Upper motor neuron signs, spasticity, varies with tone
- Joint involved
- PIP/MCP of a finger
- Notta's node
- Variable
- Key differentiating feature
- Additional flexor-mechanism pathology; higher recurrence after isolated A1 release
Red flags. Any of these calls for further investigation:
- Multiple digit involvement (suggests a syndromic condition)
- Associated hand anomalies
- Neurological signs
- Family history of connective tissue disorders
- Failure to respond to expected treatment
A child with multiple trigger digits (rather than an isolated trigger thumb) should prompt evaluation for a mucopolysaccharidosis (MPS) or other storage disorder (e.g. Hurler, Hunter, Scheie). Trigger digits in these children are typically accompanied by diffuse hand stiffness, carpal tunnel syndrome, and a "claw"/stiff hand, and may be the presenting feature. Look for coarse facial features, organomegaly, developmental concern and corneal clouding, and refer for metabolic screening — isolated A1 release will not address the underlying disease.
Investigations
A clinical diagnosis. Fixed IP flexion with a palpable Notta's node at the A1 pulley is pathognomonic, and investigations are rarely required. They are needed only when the diagnosis is uncertain or the features are atypical:
- Trauma history (to exclude a phalanx fracture)
- Suspected bony abnormality
- Atypical presentation
- Multiple digit involvement
- Failed surgical release (to evaluate for incomplete release)
- Indication
- Atypical presentation, trauma history
- Findings
- Normal in trigger thumb; excludes bony pathology
- Indication
- Diagnostic uncertainty
- Findings
- Thickened A1 pulley, FPL nodule
- Indication
- Rarely indicated
- Findings
- Soft tissue detail if diagnosis unclear
Management Algorithm
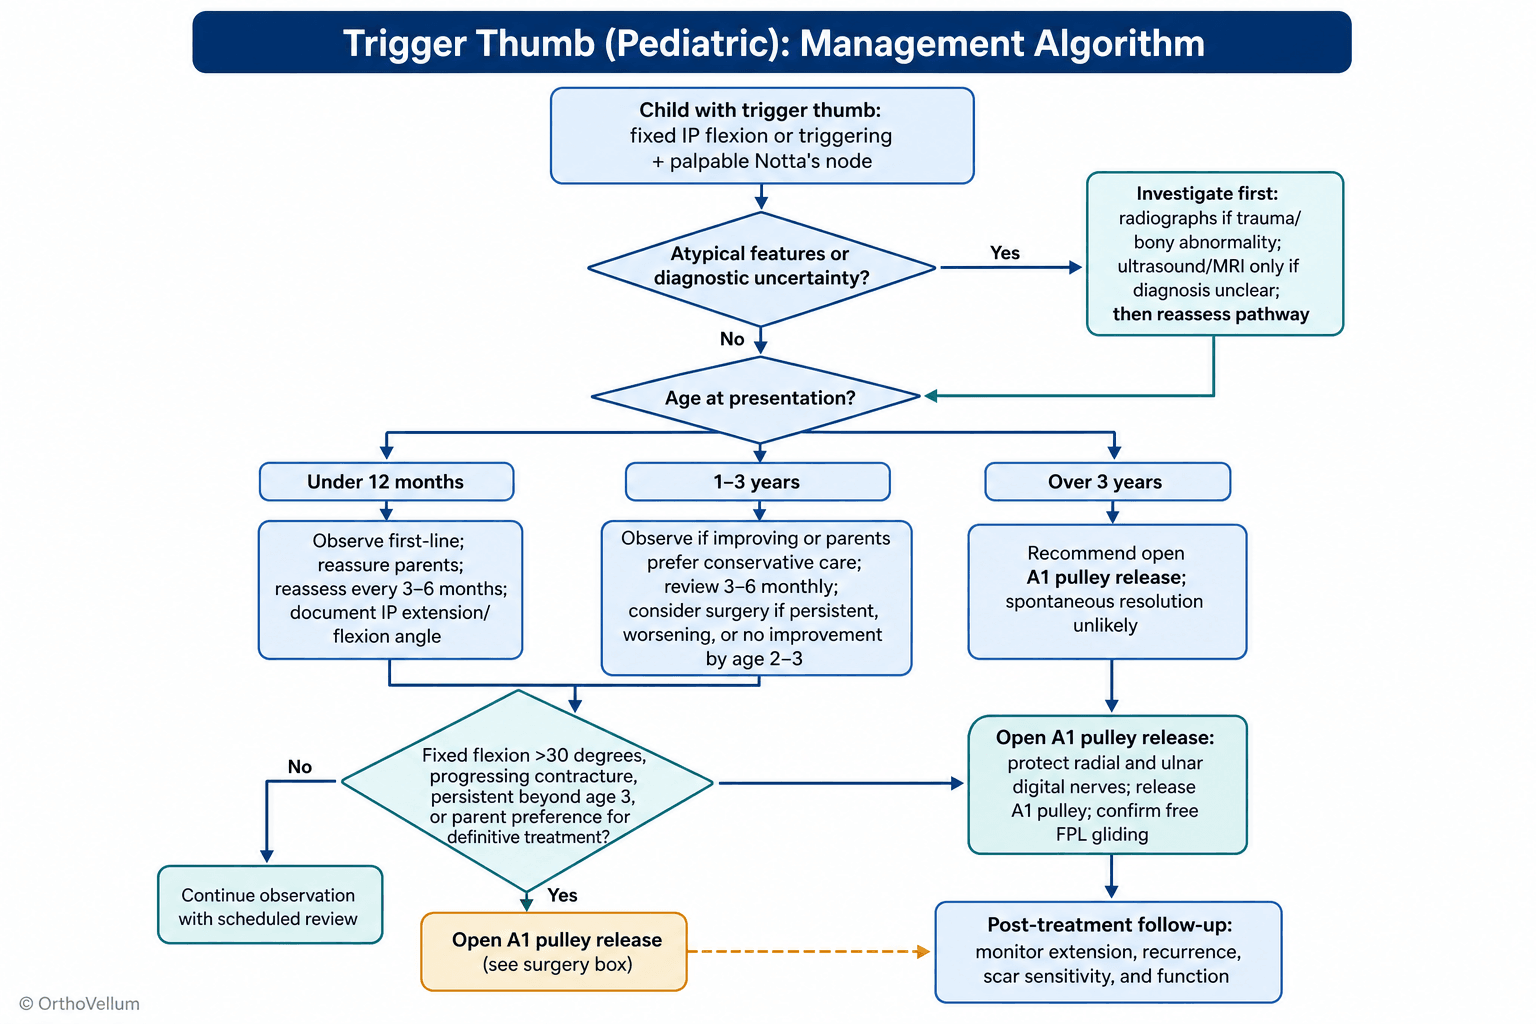
The decision. The key decision is observation or surgical release, and it turns mainly on the child's age and the duration of symptoms.
Why the resolution rates disagree. This is the most examinable thing about the natural history. Across the studies cited on this page the figure runs from 0% to 76%, and the differences are methodological rather than biological:
- How long the cohort was followed. Baek et al (JBJS Am 2008, PMID 18451388) reported 63% at a median of 48 months; the same Korean group then reported 75.9% at a median of 87 months (5+ years) in an extended cohort (Baek & Lee, Clin Orthop Surg 2011, PMID 21629478). Resolution keeps accruing for years, so a five-year figure and an eight-year figure are not the same measurement. The Singaporean cohort makes the same point within one study: 37% at 5 years, 50% at 8.
- How many families chose surgery first. The US cohort found only 32% resolved at 5 years, but 43% had elected surgery, and those thumbs can never appear in the resolution numerator. Its authors put it plainly: a third resolved, "but most parents desired eventual surgical release." The 1991 series in which every thumb came to operation reflects a practice that did not wait at all.
- What counted as resolution. Complete correction of the flexion deformity is a stricter endpoint than improvement, and most series that did not achieve resolution still recorded deformities that were improving.
What to quote. The resolution rate is partly a measure of parental patience, and the number you quote should carry the horizon it was measured over. A defensible counselling line is that with genuine observation over four to five years, roughly half to three-quarters of thumbs correct, most of the rest improve, and delaying surgery does not appear to worsen the surgical result.
By age. The age bands below sit uneasily with the cohorts above, in which median time to resolution is about four years and resolution is not complete by age 3. Quote them with that in mind.
- High spontaneous resolution rate (50-60%)
- Observation is first-line treatment
- Parent education and reassurance
- 30-40% still resolve spontaneously
- Continue observation if parents agreeable
- Consider surgery if no improvement by age 2-3
- Spontaneous resolution unlikely (10-15%)
- A1 pulley release recommended
- Waiting longer does not improve outcomes
- Delay may lead to fixed contracture
Observation. It suits a child under 3 years, a recent onset, or parents who prefer a conservative approach. Reassess every 3-6 months, measure and document the fixed flexion angle of the IP joint at each visit, and educate the parents about the natural history. An IP flexion contracture greater than 30 degrees resolves in only 2.5% (Hutchinson et al, JHSA 2021, PMID 33436280), so these thumbs are less likely to benefit from observation.
Splinting has limited evidence in paediatric trigger thumb. Unlike adult trigger finger, there is no high-quality data supporting splinting. Most surgeons do not routinely prescribe splints.
When to release. Release is indicated for:
- Persistent triggering beyond age 3
- A developing fixed flexion contracture
- Parental preference for earlier intervention, after discussion
What brings surgery forward. These favour earlier surgery:
- Fixed flexion contracture greater than 30 degrees
- Bilateral involvement, so the procedures can be combined; both thumbs may need release if triggering persists on both sides
- Parental occupational or logistical factors
- A contracture that is progressing despite observation
Surgical Technique
Set-up. General anaesthesia, supine, with the arm on a hand table and the MCP crease and planned incision marked. An upper limb tourniquet may be used or avoided according to surgeon preference; tourniquet time should be minimal, typically less than 20 minutes.
- Incision: transverse, at the MCP crease (10-15mm)
- Dissection: blunt, through the subcutaneous tissue
- Nerve identification: identify and protect the radial and ulnar digital nerves
- Pulley exposure: expose the A1 pulley overlying the FPL tendon
- Release: divide the A1 pulley longitudinally by sharp dissection
- Confirmation: flex and extend the thumb to confirm free FPL gliding
- Inspection: check for complete release and absence of triggering
- Closure: absorbable subcuticular suture (5-0 or 6-0 Monocryl)
Always identify both digital nerves, and see the radial digital nerve crossing palmar to the field, before the pulley is released. Use blunt dissection and loupe magnification, and consider a bloodless field with a tourniquet.
Technical points. The details that matter:
- Keep the dissection superficial to avoid damaging the flexor tendon
- Complete A1 pulley release is essential to prevent recurrence
- Confirm that Notta's node passes freely through the released pulley
- Do not release the oblique pulley, to preserve thumb biomechanics
Complications
- Observation
- 5-10% if observation prolonged
- Surgery
- Rare
- Management
- May require additional soft tissue release
- Observation
- N/A
- Surgery
- less than 1%
- Management
- Microsurgical repair if identified
- Observation
- N/A
- Surgery
- less than 1%
- Management
- Antibiotics, wound care
- Observation
- N/A
- Surgery
- less than 1%
- Management
- Re-release if incomplete
- Observation
- N/A
- Surgery
- 5-10%
- Management
- Scar massage, desensitisation
Nerve injury. Radial digital nerve injury is the most significant complication. Its prevention lies in the technique: careful dissection and direct visualisation of the nerve before the pulley is divided.
Incomplete release. It is recognised by persistent triggering after surgery and is usually due to incomplete division of the A1 pulley. The treatment is re-exploration and complete release.
Postoperative Care
- Soft dressing applied (bulky hand dressing)
- Pain control with oral paracetamol and ibuprofen
- Elevation of hand above heart level
- Ice application for comfort (20 minutes on, 20 off)
- Parent education about wound care and activity restrictions
- Dressing may be removed at 24-48 hours
- Gentle active thumb movement encouraged
- Keep wound clean and dry
- No formal physiotherapy or hand therapy required in uncomplicated cases
- Absorbable sutures do not require removal
- Full active range of motion by 1 week
- Scar massage may begin after 2 weeks
- Follow-up appointment to confirm free thumb extension and no triggering
- Address any parental concerns
- Scar typically fades over 6-12 months
- Discharge from care if uncomplicated
- Timeline
- Immediately
- Notes
- Encourage active flexion and extension
- Timeline
- 2-3 days
- Notes
- When child comfortable, protect from trauma
- Timeline
- 1 week
- Notes
- No restrictions on age-appropriate activities
- Timeline
- 2 weeks
- Notes
- After wound completely healed
- Timeline
- 4 weeks
- Notes
- Protect thumb until scar mature
Unlike some hand procedures, no postoperative splinting is required after paediatric trigger thumb release. Early active movement is encouraged to prevent stiffness and optimise recovery, and splinting may actually delay it.
What the parents can expect. The fixed flexion deformity is relieved immediately, in the operating room. There is mild pain for 2-3 days, easily controlled with oral analgesia, and a small scar at the MCP crease that fades over time. There are no long-term functional limitations, and the recurrence risk is extremely low.
Warning signs. Parents should report:
- Persistent triggering after surgery (suggests incomplete release)
- Numbness or tingling in the thumb (nerve injury)
- Increasing redness, warmth or discharge (infection)
- Inability to move the thumb (unlikely, but requires assessment)
Outcomes and Prognosis
After release. A1 pulley release succeeds in 99%+, and the result is immediate. After successful treatment there is no functional deficit: thumb strength and range of motion are normal, scarring is minimal with proper technique, and children return to normal activities within 2-3 weeks.
Does delay matter? Delayed surgery does not worsen outcomes in terms of final function. Prolonged fixed flexion may, however, lead to an IP joint contracture that requires additional soft tissue release, and surgery by age 3-4 years optimises outcomes.
Residual IP flexion after release. After release for a long-standing fixed IP flexion contracture, the IP joint may not fully extend on the operating table, because of adaptive shortening of the volar plate and FPL.
- In a child the residual contracture usually remodels and improves with continued growth, supplemented by passive stretching and night extension splinting over the following months. Full correction is the norm even when it is not achieved intra-operatively.
- A volar plate / check-rein release (capsulotomy) is rarely required, and is reserved for a persistent, severe contracture that fails to remodel.
- This residual-contracture risk, greatest in thumbs operated very late or with a large fixed deformity, is exactly why timely surgery is preferred once observation has been exhausted, and why a fixed IP flexion contracture over 30° lowers the threshold to operate rather than continue observing.
Guidelines, Registries & Global Practice
Paediatric trigger thumb is managed worldwide along broadly similar lines, but the threshold for surgery and the duration of observation vary by region. The world standard of care is observation in young children with surgical A1 pulley release reserved for persistent cases or fixed contracture.
Global epidemiology (PubMed-verifiable):
- Figure
- 3.3 per 1000 live births
- Source population (PMID)
- Japan, neonatal screening cohort (16632044)
- Figure
- No - none of 1116 neonates affected at birth
- Source population (PMID)
- Japan (16632044)
- Figure
- 16% (29 of 180 children)
- Source population (PMID)
- Hong Kong series (21979473)
- Figure
- 63% at median 48 months
- Source population (PMID)
- Korea (18451388)
- Figure
- 75.9% at minimum 5 years
- Source population (PMID)
- Korea (21629478)
- Figure
- Only 2.5%
- Source population (PMID)
- USA prognostic cohort (33436280)
Major guidance, side by side:
There is no dedicated AAOS, NICE or BOA clinical practice guideline specific to paediatric trigger thumb; guidance is derived from the natural-history and surgical literature and from review syntheses such as the AAOS-affiliated JAAOS review (PMID 22474090). The table below summarises where authoritative sources converge and where genuine practice variation exists.
- Prevailing recommendation
- Observation - high spontaneous resolution
- Evidence basis (PMID)
- 18451388, 21629478, 39534959
- Prevailing recommendation
- Not used in children (used first-line in adult trigger finger)
- Evidence basis (PMID)
- Review consensus (22474090)
- Prevailing recommendation
- Open A1 pulley release (gold standard)
- Evidence basis (PMID)
- 36741041, 21979473
- Prevailing recommendation
- Discouraged - higher recurrence and nerve risk
- Evidence basis (PMID)
- 36741041
- Prevailing recommendation
- Not routinely required
- Evidence basis (PMID)
- Comparative study (40885965)
No national joint registry (NJR, AJRR, AOANJRR, SHAR, NZJR) captures paediatric trigger thumb, as it is a soft-tissue release rather than an implant procedure. The evidence base is therefore drawn from prospective cohorts and surgical case series rather than registry data.
- Observation duration: Asian cohorts (Korea, Singapore) document very high long-term resolution (up to 76%) and favour prolonged observation of 4-5 years (PMIDs 21629478, 39534959). North American practice tends toward earlier surgery, partly reflecting lower observed resolution (32% at 5 years, PMID 33436280) and parental preference for definitive treatment.
- Threshold for surgery: A fixed IP flexion contracture greater than 30 degrees is increasingly used internationally as a trigger for earlier release, because such thumbs rarely resolve (PMID 33436280).
- Resource setting: In limited-resource settings, observation is often favoured by necessity given the benign natural history; open release under general anaesthesia remains the definitive option where theatre access allows.
- Distinction from paediatric trigger FINGER: Unlike the thumb, paediatric trigger finger frequently involves additional flexor-mechanism pathology, has higher recurrence after isolated A1 release, and may require exploration of the FDS/FDP and accessory pulleys (PMID 22474090) - a key examiner discriminator.
MCQ Practice Points
Q: What is the pathognomonic finding in pediatric trigger thumb? A: Notta's node - a palpable nodule of the FPL tendon at the A1 pulley level. This is the key clinical finding that distinguishes trigger thumb from other causes of thumb flexion deformity.
Q: Is pediatric trigger thumb truly congenital? A: No. Despite the name "congenital trigger thumb," the condition is rarely present at birth. It is typically noticed after 6 months of age and is thought to be acquired in early infancy. True congenital conditions are present at birth.
Q: What is the spontaneous resolution rate of pediatric trigger thumb? A: The honest answer names a range and its reason: roughly a third to three-quarters, depending mostly on how long the cohort was followed and how many families chose surgery first. Median time to resolution is about 4 years, and in the longest-followed series no thumb resolved beyond 48 months - so observation for four to five years is defensible, but the common teaching that resolution happens "by age 3" understates the wait. A contracture greater than 30 degrees at presentation is the finding that predicts observation will fail.
Q: What structure is at greatest risk during A1 pulley release for trigger thumb? A: The radial digital nerve of the thumb. It crosses palmar to the A1 pulley and can be injured if not identified and protected during surgical release.
Q: What percentage of pediatric trigger thumb cases are bilateral? A: 16-30%. Always examine the contralateral thumb in any child presenting with trigger thumb.
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“An 18-month-old child is brought by concerned parents who noticed the thumb is always bent. On examination, there is fixed flexion of the IP joint and a palpable nodule at the base of the thumb. How would you manage this?”
“A 4-year-old child was diagnosed with trigger thumb at age 2 and has been observed. The IP joint remains in 30 degrees of fixed flexion. Parents are now asking about treatment options. What would you advise?”
“A 3-year-old child is found to have bilateral trigger thumbs. The right side was diagnosed at 18 months and has not resolved. The left side was just noticed today. How would you approach this?”
DIAGNOSIS
- Notta's node = pathognomonic (palpable FPL nodule at A1 pulley)
- Fixed IP flexion (typically 25-30 degrees)
- NOT truly congenital - acquired after birth
- 16-30% bilateral - always examine both thumbs
KEY NUMBERS
- 0.3-0.5% incidence in children
- Spontaneous resolution a third to three-quarters, median 4 years
- 16-30% bilateral cases
- 99% surgical success rate
MANAGEMENT
- Observe for 4-5 years (a third to three-quarters resolve); contracture over 30 degrees rarely does
- Over 3 years: A1 PULLEY RELEASE
- NO steroid injections in children
- Bilateral surgery at single session is safe
SURGICAL PEARLS
- Transverse incision at MCP crease
- RADIAL digital nerve at GREATEST RISK
- Release A1 pulley longitudinally
- Confirm free FPL tendon glide
DIFFERENTIALS
- Clasped thumb = MCP flexion + adduction (different condition)
- Thumb hypoplasia = underdeveloped structures
- Arthrogryposis = multiple joint involvement
EXAM TRAPS
- Calling it truly congenital (it's acquired)
- Recommending steroid injection (not in children)
- Operating too early (observe under age 3)
- Forgetting bilateral risk (16-30%)
Evidence Base
Kikuchi & Ogino - Incidence and Development (landmark)
- 1116 neonates examined within 14 days of birth - NO trigger thumb present at birth
- Incidence of acquired trigger thumb at 1 year of age was 3.3 per 1000 live births
- Triggering manifested between 8 months and 30 months of age
Baek et al - Natural History (key observation study)
- 71 untreated thumbs prospectively followed (median 48 months)
- 45 of 71 (63%) resolved spontaneously without any treatment
- Flexion deformity improved in 22 of the 26 non-resolved thumbs
Baek & Lee - Long-term Natural History (5+ years)
- 87 untreated thumbs followed for a median of 87 months (5+ years)
- 66 of 87 (75.9%) resolved spontaneously; median time to resolution 49 months
- No further resolution occurred beyond 48 months and no residual deformity
Hutchinson et al - US Natural History (prognostic)
- 93 thumbs (competing-risk analysis) - 32% resolved spontaneously by 5 years
- IP flexion behaves as a CONTINUOUS predictor, which is more useful than the threshold: each additional degree of initial IP flexion reduced the chance of spontaneous resolution by 3% (subdistribution HR 0.97, 95% CI 0.94-0.99)
- IP flexion contracture greater than 30 degrees resolved in only 2.5% of thumbs - but the interval is very wide (95% CI 0.4% to 17%), so this is a strong signal rather than a precise probability
- Bilateral involvement increased the likelihood of surgery (subdistribution HR 2.38)
Ger, Kupcha & Ger - Surgical Management and Timing
- 41 patients with 53 trigger thumbs reviewed
- All eventually required surgical release of the flexor pollicis longus tendon
- Waiting up to 3 years before release did NOT compromise the surgical result
Leung et al - Surgical Release Outcomes (large series)
- 180 children with 209 trigger thumbs; mean age of onset 19 months
- 16% bilateral; only 5% had associated congenital conditions and none a family history
- Over 95% of operated thumbs regained good range of motion; residual flexion in only 4% (mostly operated under age 1)
Farr - Open Release of Pediatric Trigger Thumb (technique)
- Open A1 release restored full range of motion in 95% of children vs 55% with therapy and 67% with splinting
- Open technique complication rate ~3.4%; percutaneous release carried 3.3x higher recurrence and greater neurovascular risk
- Complete A1 division confirmed by the Notta nodule gliding distally into full IP extension
Chew et al - Prospective Natural History (recent)
- 79 thumbs (median age 20.5 months) observed for a mean of 4.2 years
- Spontaneous resolution 37% at 5 years and 50% at 8 years, in 62 patients with 79 thumbs; those that resolved did so at a mean of 3.4 years
- Read those alongside the surgery figures from the same cohort, because the two sum to most of it: 27% had undergone surgery by 5 years and 48% by 8 years
- IP joint angle less than 30 degrees predicted resolution (specificity 0.82)