Second Most Common Carpal Fracture | Dorsal Chip Pattern | FOOSH Mechanism
- Second most common carpal fracture after scaphoid
- Dorsal chip fractures are 93% of all triquetral fractures
- Best seen on lateral radiograph - dorsal cortex avulsion
- FOOSH with ulnar deviation is typical mechanism
- Excellent prognosis with conservative treatment for most
- “Always check lateral view - dorsal chip easily missed on PA
- “Dorsal chip is an impaction injury in extension and ulnar deviation - impactor disputed (hamate or ulnar styloid)
- “Body fractures may indicate perilunate spectrum injury
- “Most dorsal chip fractures heal uneventfully with casting
Overview and Epidemiology
A triquetral fracture is a fracture of the triquetrum, the bone on the ulnar side of the proximal carpal row. The dorsal cortical chip is by far the commonest pattern, over 90% of cases, though body fractures also occur.
How common. Conventionally the triquetrum is the second most common carpal fracture, at 14-20% of all carpal fractures, after the scaphoid at 70-80%. The Swedish Fracture Registry's 6,542 carpal fractures support that ranking, with scaphoid 60% and triquetrum 25%, a share above the 14-20% usually quoted.
The rank depends on how hard you look. A German series in which 91% of patients underwent CT found the triquetrum the commonest carpal fracture of all, ahead of the scaphoid. Only 20% of triquetral fractures are detected on radiographs, so registries built on plain films systematically under-count them while CT-based series do not. Quote "second most common" with that caveat rather than as a fixed fact.
The patients are young to middle-aged adults, with a male predominance.
Anatomy/Biomechanics
The bone. Pyramidal, triangular when viewed from its ulnar aspect, and the third largest bone of the proximal row after the scaphoid and lunate. It forms the ulnar border of the proximal row and articulates on four sides:
- Lunate - on its radial side, as part of the intercalated segment
- Hamate - distally, through the hamate facet, with the proximal pole of the hamate
- Pisiform - on the volar surface, a small sesamoid articulation in the volar groove
- TFCC - proximally, through the ulnocarpal complex
The dorsal surface carries a ridge for ligament attachments, and it is the site of the commonest fracture.
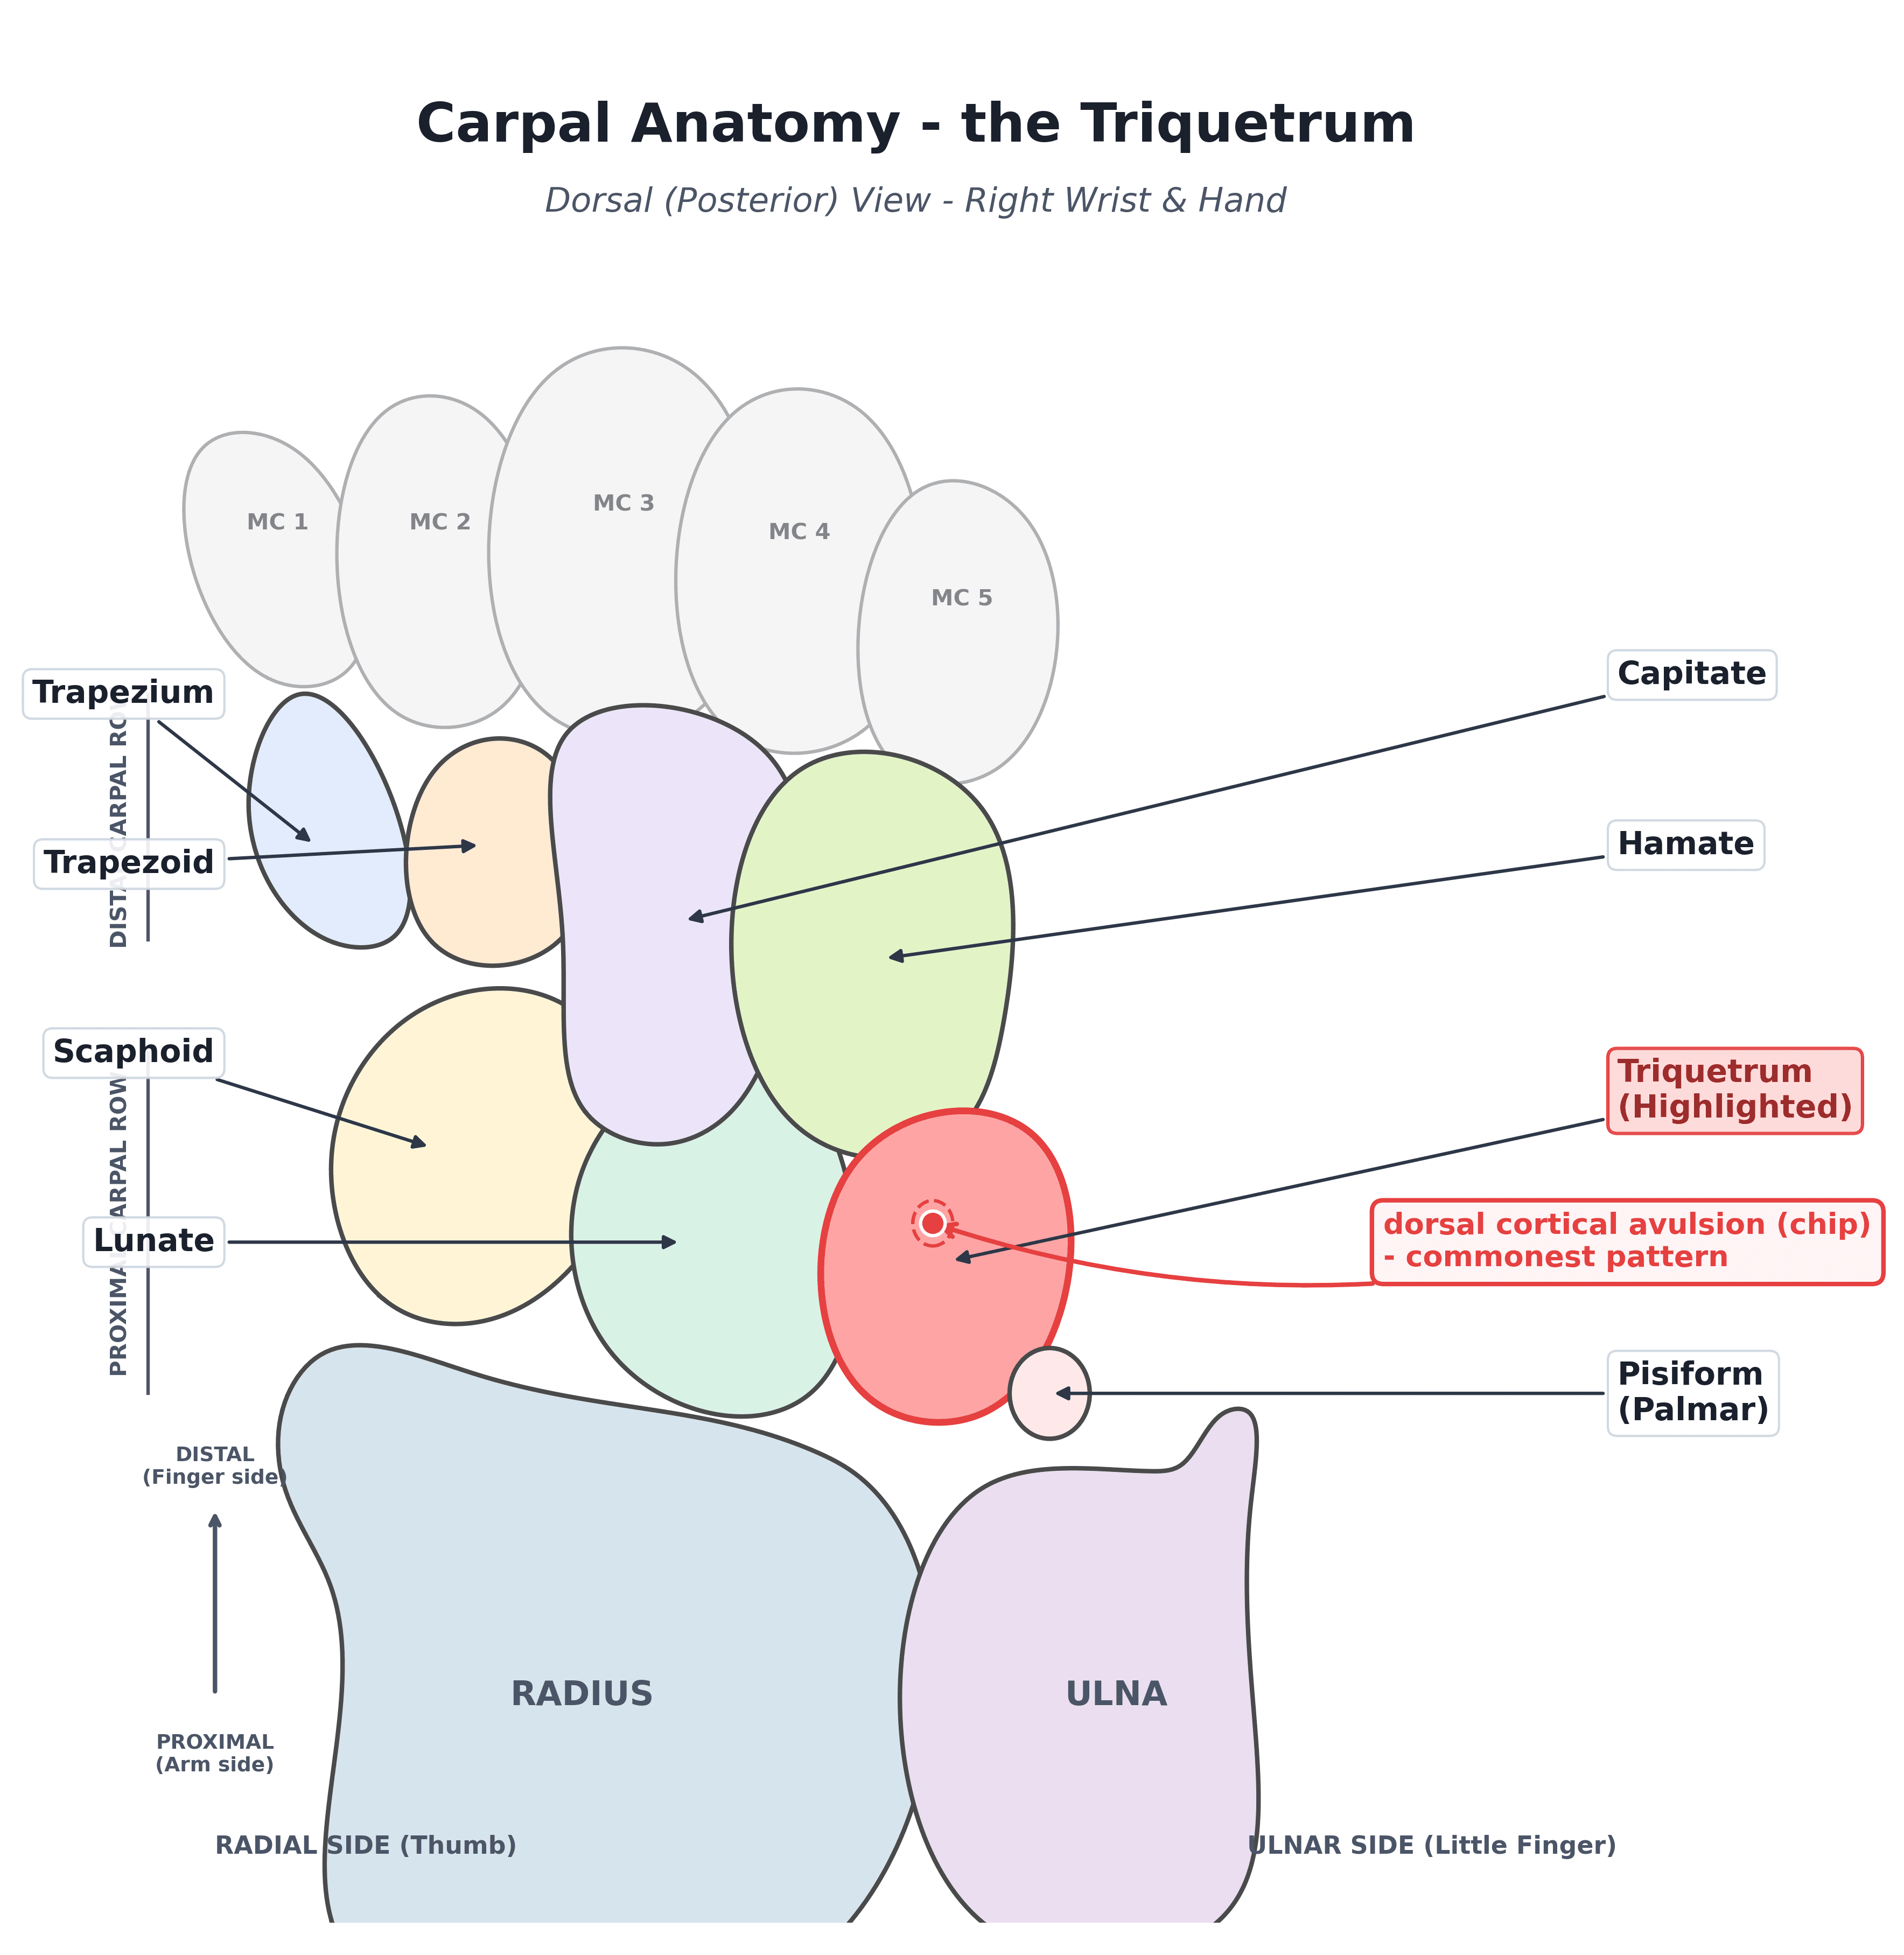
The blood supply. Multiple dorsal and volar nutrient vessels enter the bone: the dorsal surface carries the primary supply, the volar surface secondary vessels, and the other non-articular surfaces add more. No single vessel dominates, unlike the lunate, so the risk of AVN is lower than in other carpals and the healing potential is reliable.
Kinematics. The triquetrum is part of the proximal row "intercalated segment" and moves with the scaphoid and lunate as a functional unit, with limited independent motion. It transmits force from the ulnar carpus, which carries less load than the radial side; the pisiform modifies that transmission, and the hamate comes into contact with it in ulnar deviation.
The mechanism of the dorsal chip. Three explanations compete, and both papers cited on this page reject the one most commonly taught:
- Ligament avulsion (traditional teaching) - the strong radiotriquetral ligament, perhaps with a contribution from the lunotriquetral ligament, pulls off a dorsal flake in traction. It is the most repeated explanation and the weakest.
- Ulnar styloid impaction (Levy) - a cadaveric and radiographic study written specifically to test the avulsion theory disproved it, concluding that a chisel action of the ulnar styloid against the dorsum of the triquetrum causes the chip in a fall onto an outstretched hand held in strong dorsiflexion and ulnar deviation. A prolonged ulnar styloid was noted in every case.
- Hamate impaction (Höcker and Menschik) - a larger series agreed the mechanism is impingement rather than avulsion, but named a different impactor, the dorso-proximal edge of the hamate.
What to say. The dorsal chip is an impaction (chisel) injury in extension and ulnar deviation that shears off the dorsal cortex, with the impactor disputed between ulnar styloid and hamate. Every proposed mechanism produces a similar dorsal flake, so the distinction matters less for treatment than for predicting stability: an impaction mechanism predicts a dorsal cortical flake that does not destabilise the carpus, which is what the outcome data show.
Classification Systems
The anatomical classification is the practical one. It is based on fracture location, and location guides both treatment and prognosis.
- Frequency
- Over 90%
- Stability
- Stable
- Management
- Cast 4-6 weeks; excellent prognosis
- Frequency
- Under 10%
- Stability
- Variable
- Management
- Cast if undisplaced, ORIF if displaced; assess for perilunate injury
- Frequency
- Rare
- Stability
- Usually part of perilunate
- Management
- Address the associated carpal injury
- Frequency
- Very rare
- Stability
- Unstable
- Management
- Complex reconstruction, may need external fixation; poor prognosis
Type I, the dorsal chip. A small cortical avulsion from the dorsal surface, usually under 5mm.
Type II, the body fracture. A fracture through the substance of the triquetrum, which may point to a higher-energy injury. Unlike chips, body fractures may indicate a greater-arc perilunate injury, so always assess for carpal malalignment and associated injuries when one is present.
Type III, the volar avulsion. Rare as an isolated injury. It is of ligamentous origin (pisotriquetral, ulnotriquetral), usually associated with perilunate dislocation as part of the greater-arc pattern, and it requires assessment for carpal instability.
Type IV, the comminuted body. A high-energy injury with significant fragment displacement and a poor soft-tissue envelope.
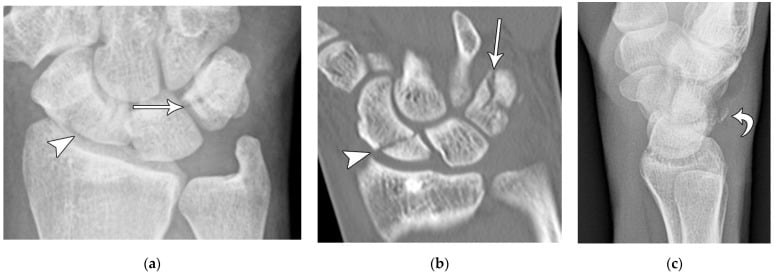
Mechanism predicts the severity of the injury and the associated injuries to look for, and so guides the workup.
- Impaction - extension and ulnar deviation drive the hamate or ulnar styloid into the triquetrum; typically an isolated dorsal chip, low energy, no carpal instability
- Avulsion - ligament traction, which may involve the radiotriquetral or lunotriquetral ligaments; moderate energy, so assess for subtle instability
- Perilunate-associated - a body or volar fracture as part of a greater-arc ligamentous disruption; high energy, and requires comprehensive evaluation
- Direct trauma - a direct blow to the ulnar wrist; a rare, isolated body fracture, which may be comminuted, with variable associated injuries
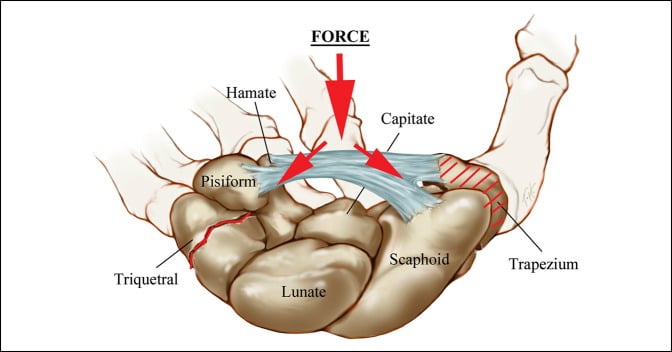
Triquetral body and volar fractures are flagged because they may form part of a perilunate injury. Mayfield's progressive perilunate instability describes a load propagating around the lunate from the radial to the ulnar side: Stage I scapholunate disruption; Stage II capitolunate (midcarpal) disruption; Stage III lunotriquetral disruption (the triquetral-side stage); Stage IV complete volar lunate dislocation (the lunate is extruded while the remaining carpus realigns with the radius). A lesser-arc injury is purely ligamentous (perilunate then lunate dislocation). A greater-arc injury passes through bone — trans-scaphoid, trans-capitate, or trans-triquetral — so a triquetral body fracture with carpal malalignment is a greater-arc perilunate pattern until proven otherwise.
Clinical Assessment
History. The usual mechanism is a fall onto the outstretched hand with ulnar deviation. Less often:
- Direct blow - rare, usually to the dorsum of the wrist
- Sports injury - contact and ball sports
- Motor vehicle accident - dashboard injury
Establish the exact mechanism and wrist position, the energy (height of fall, impact speed), the immediate symptoms and pattern of swelling, any previous wrist injury or symptoms, and hand dominance and occupational demands.
Examination. Swelling over the ulnar wrist may be subtle with a dorsal chip, so compare with the other side, and check the skin. The finding that matters is point tenderness over the triquetrum on the dorsal ulnar wrist. The anatomical snuffbox is negative, which rules out the scaphoid; examine the DRUJ for associated injury, and note that the pisiform may be tender as well.
Motion is limited by pain in the acute setting, ulnar deviation particularly. Assess forearm rotation for DRUJ involvement. Neurovascular function is usually preserved, but check the ulnar nerve and document a baseline for comparison.
Special tests.
- Triquetral shear test - direct pressure on the triquetrum; pain suggests triquetral pathology, and the test is specific for triquetral injury
- Ballottement test - assesses lunotriquetral stability against the other side; a positive test means LT instability
- Watson (scaphoid shift) test - should be negative; if positive, consider an additional carpal injury
- ECU subluxation test - supinate and ulnar deviate the wrist; extensor carpi ulnaris may be injured as well
Ulnar-sided wrist pain after a fall has a broad differential. The triquetral fracture must be distinguished from the conditions below, several of which can coexist with it.
- Distinguishing feature
- Point tenderness dorsal-ulnar; dorsal fragment on lateral film
- Key investigation
- Lateral radiograph (CT if occult)
- Distinguishing feature
- Tenderness at styloid tip; often with distal radius fracture
- Key investigation
- PA radiograph
- Distinguishing feature
- DRUJ pain, positive fovea sign, painful forearm rotation
- Key investigation
- MRI / wrist arthroscopy
- Distinguishing feature
- Positive ballottement test, LT interval changes
- Key investigation
- MRI, dynamic imaging
- Distinguishing feature
- Tenderness over pisiform, pain on pisotriquetral grind
- Key investigation
- Carpal tunnel / 30-degree supinated view
- Distinguishing feature
- Hypothenar pain, tenderness over hook, ulnar nerve symptoms
- Key investigation
- Carpal tunnel view / CT
- Distinguishing feature
- Carpal malalignment, disrupted Gilula arcs, DISI/VISI
- Key investigation
- PA and lateral radiographs, CT
Investigations
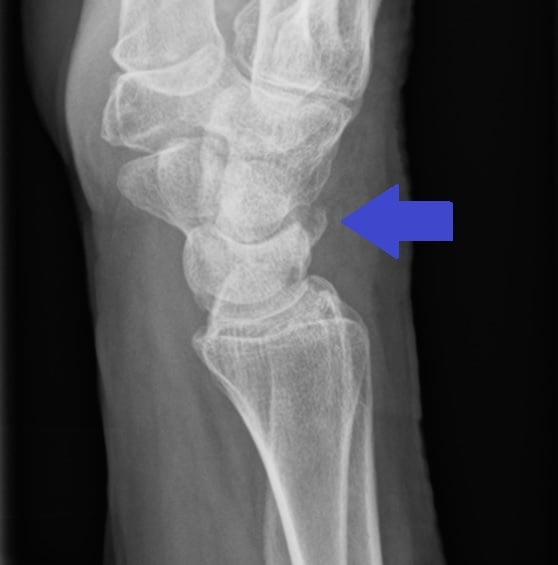
Radiographs. PA, lateral and oblique views. The lateral is the essential view for a dorsal chip, which is often missed on the PA: look for a small osseous fragment dorsal to the carpal silhouette, sitting dorsal to the lunate and usually at the level of the triquetrum. It is best identified with true lateral positioning and may be overlooked if not specifically sought. This is a common exam presentation. The lateral may, in turn, miss a body fracture.
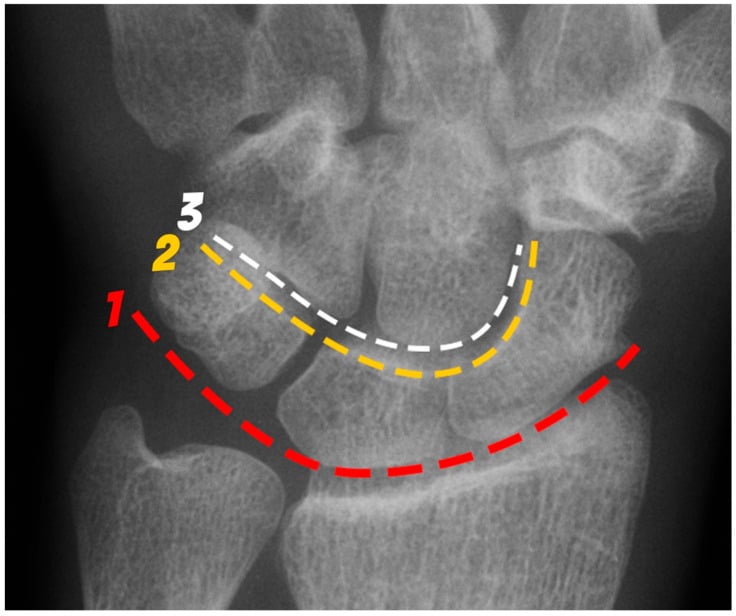
The PA view. Often normal with an isolated dorsal chip, but it may show a body fracture, and it is where carpal alignment and the scapholunate and lunotriquetral intervals are assessed. Signs of an associated injury:
- Scapholunate widening (SL injury)
- LT overlap or widening
- Disruption of the carpal arcs
- A DISI or VISI pattern on the lateral
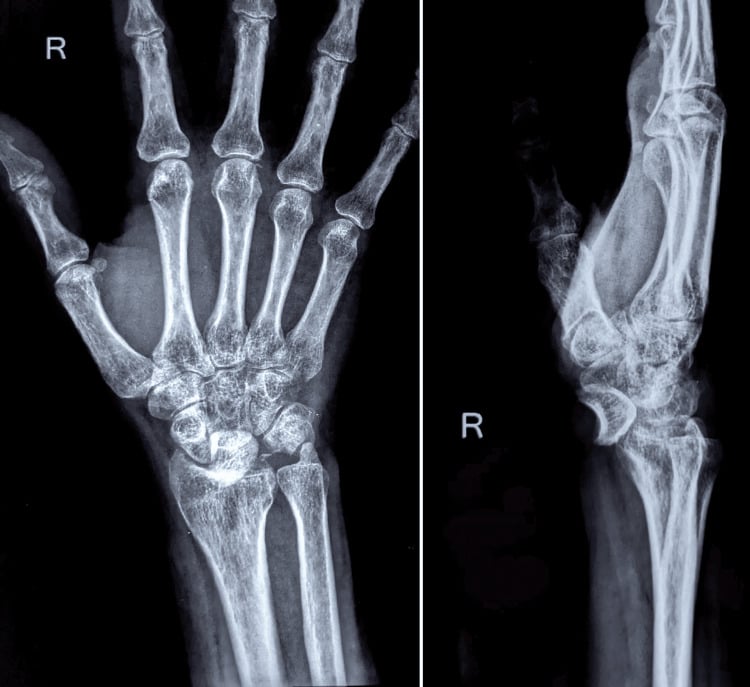
Carpal instability is named for how the lunate tilts on a neutral lateral (normal capitolunate angle near 0 degrees; scapholunate angle 30 to 60 degrees). DISI (dorsal intercalated segment instability) = lunate tilted dorsally, scapholunate angle over 70 degrees — the pattern of scapholunate dissociation and of scaphoid nonunion. VISI (volar intercalated segment instability) = lunate tilted volarly, scapholunate angle under 30 degrees — the pattern of lunotriquetral dissociation, which is the instability relevant to triquetral body fractures and LT ligament injury. A triquetral fracture with a VISI lateral mandates assessment for LT and perilunate disruption.
CT. CT gives fracture detail, at the cost of radiation and expense. Indications:
- A suspected body fracture that is not clear on radiographs
- Surgical planning for a displaced fracture
- Assessment of comminution
- Evaluation for perilunate injury
It shows the orientation of the fracture line, fragment size and displacement, articular involvement and associated carpal injuries.
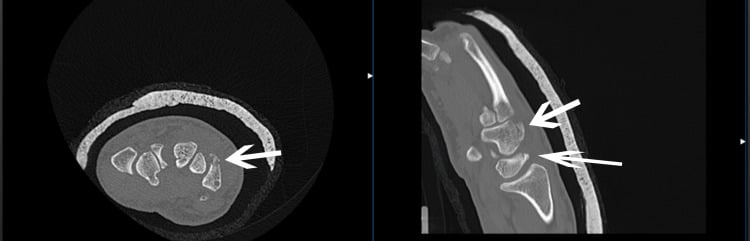
MRI. For a suspected ligamentous injury, the LT ligament and the TFCC, and for an occult fracture not seen on radiographs or CT, which shows as bone marrow oedema. It also shows associated soft-tissue injury; cost and availability limit it.
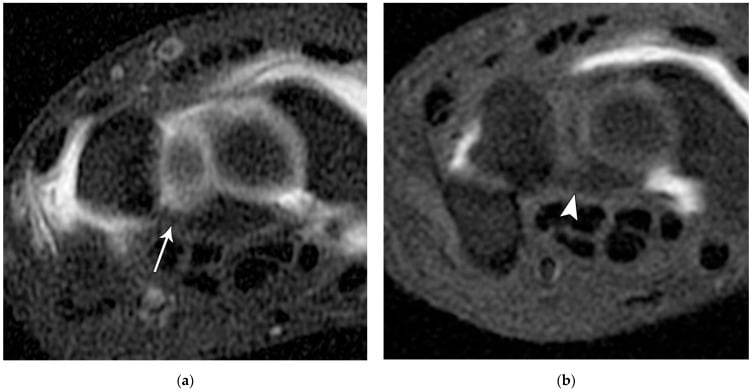
Bone scan. Rarely needed. It may detect an occult fracture but has been superseded by MRI for most indications.
Management Algorithm
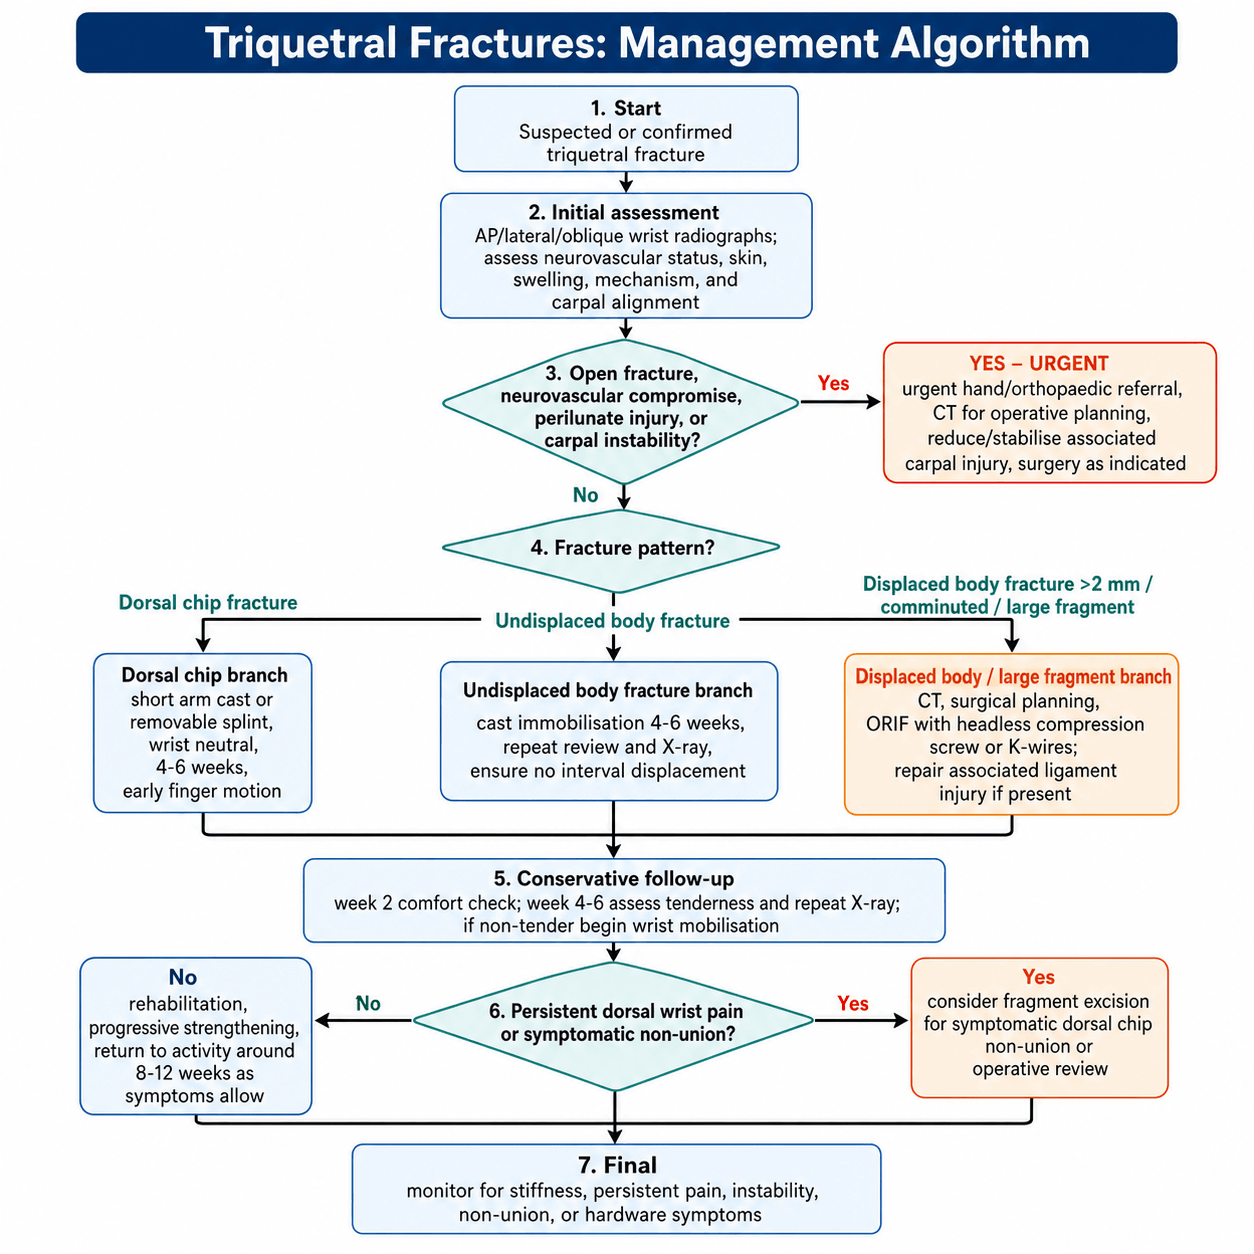
Most triquetral fractures are managed conservatively with excellent results. The decision to operate rests on the fracture pattern and the associated injuries.
Who. All dorsal chip fractures (Type I) and undisplaced body fractures (Type II) without carpal instability, and elderly or low-demand patients.
The cast. A short arm cast or thermoplastic splint with the wrist in neutral for 4-6 weeks. A removable splint may be used for a compliant patient.
The protocol.
- Week 0-2 - immediate finger motion and elevation to reduce swelling; clinical review at 2 weeks as a comfort check
- Week 2-4 - continue immobilisation, switching to a removable splint if compliant; begin gentle finger exercises if not already started
- Week 4-6 - clinical review of tenderness over the triquetrum and a repeat radiograph to confirm position; if non-tender, the splint may be discontinued and mobilisation begins
- Week 6-8 - active wrist range of motion, avoiding resisted activities, progressing as tolerated
- Week 8-12 - progressive strengthening and a return to normal activities, with sport-specific training if applicable
Surgical Technique
Indication. A symptomatic dorsal chip non-union, with persistent pain after 3-6 months of conservative treatment, confirmed by imaging as the source of symptoms.
Set-up. Supine with an arm table and an upper-arm tourniquet, the wrist pronated for dorsal access. A small longitudinal incision of 2-3 cm over the dorsal ulnar wrist, centred on the fragment if it can be palpated.
Steps.
- Incise the extensor retinaculum between EDM and ECU and retract the tendons
- Identify the fragment in the capsule; it is usually embedded in the dorsal ligament complex
- Isolate it carefully and excise it completely with a curette or rongeur, preserving as much ligament as possible
- Debride any fibrous tissue and check for additional fragments
- Repair the retinaculum loosely, close the skin, and apply a soft dressing and splint
Fragment excision is a straightforward procedure with excellent outcomes.
Complications
After a dorsal chip. Symptomatic non-union is the most common complication, presenting as persistent dorsal wrist pain. The fragment may also abrade the overlying extensor tendons, EDC or EDM most commonly, causing tendon pain or snapping. A large fragment can block extension and produce mechanical symptoms with wrist motion (dorsal impingement). Both are treated by excising the fragment.
After a body fracture. Malunion is rare with appropriate treatment, but it may alter carpal kinematics and lead to secondary arthritis. Non-union is more common than with dorsal chips, is associated with inadequate immobilisation, and may require bone grafting.
Post-traumatic arthritis is uncommon with an isolated triquetral fracture, more common with associated injuries, and may require a salvage procedure. Lunotriquetral instability can develop after a body fracture, and the LT ligament may be injured at the time of fracture. It presents with ulnar wrist pain and clicking and is treated by LT repair or fusion.
After surgery.
- Wound - infection (rare), dehiscence, scar sensitivity
- Hardware - screw prominence or K-wire migration, which may require removal
- Tendon - ECU or EDM at risk; usually prevented with careful technique, and repaired if identified intraoperatively
- Frequency
- 5-10% of chips
- Prevention
- Adequate immobilisation
- Management
- Fragment excision
- Frequency
- Rare
- Prevention
- Complete excision
- Management
- Remove fragment
- Frequency
- Rare with body Fx
- Prevention
- Recognise at injury
- Management
- Ligament repair/fusion
- Frequency
- Rare
- Prevention
- Anatomic reduction
- Management
- Activity modification to fusion
Postoperative Care
After fragment excision. A soft dressing and volar splint for 1-2 weeks, with immediate finger motion and elevation. Wrist range of motion begins early, at 2-4 weeks, when the splint may be discontinued and light activities resume. From week 4, full range and strengthening with a return to normal activities without restriction, full activity at 4-6 weeks.
After body fracture ORIF.
- Week 0-2 - volar splint in neutral, immediate finger motion, elevation and wound care; sutures out at 10-14 days
- Week 2-6 - removable splint and gentle wrist range of motion, begun at 2-4 weeks depending on stability; avoid loading and forceful grip
- Week 6-12 - discontinue the splint and begin progressive strengthening; K-wires, if used, are removed at 6 weeks; return to activities at 8-12 weeks
Follow-up.
- Conservative
- Comfort check
- Surgical
- Wound and pain; no imaging
- Conservative
- Radiograph, assess healing
- Surgical
- Radiograph, range of motion and tenderness
- Conservative
- Final review if healed
- Surgical
- Function; final review if healed, imaging as needed
- Conservative
- -
- Surgical
- Final outcome; imaging if symptomatic
- Conservative
- Symptomatic review
- Surgical
- Hardware concerns
Most patients achieve full recovery with straightforward rehabilitation.
Outcomes and Prognosis
Dorsal chips. Over 95% heal with conservative treatment, with union typically at 4-6 weeks, and a fibrous union may be asymptomatic. Range of motion recovers to 95-100% of normal, grip strength returns in full, and patients return to their previous activity level with high satisfaction; persistent symptoms are rare. A symptomatic non-union is easily treated by excision, with excellent results.
Body fractures. Healing is good with appropriate treatment, union typically at 6-8 weeks. Anatomic reduction gives good outcomes, although some residual stiffness may remain; the result depends on the associated injuries, and most return to their previous activity. Perilunate spectrum injuries carry a worse prognosis: LT instability may persist and additional procedures may be required.
Prognostic factors.
- Favourable - dorsal chip pattern, isolated injury, early treatment, compliant patient
- Unfavourable - displaced body fracture, associated perilunate injury, delayed diagnosis, high-energy mechanism
Return to activity after conservative treatment:
- Sedentary work - 1-2 weeks, in the splint
- Light manual work - 6-8 weeks
- Heavy manual work - 8-12 weeks
- Contact sports - 8-12 weeks
After surgery the timelines are similar and may be slightly longer after ORIF of a body fracture; athletes return at 3-4 months.
Guidelines, Registries & Global Practice
Global Epidemiology (Registry & Population Evidence)
There is no dedicated triquetral-fracture trial registry; the strongest evidence comes from national fracture registries and large carpal-fracture series that report relative frequency, demographics and treatment patterns.
- Cohort
- 6542 carpal fractures
- Key finding
- Triquetrum 25% of carpal fractures (2nd after scaphoid 60%); mean age 41, 69% male
- Evidence
- Level IV registry
- Cohort
- 178 ED carpal fractures
- Key finding
- Triquetrum most frequent in cohort; almost all treated conservatively
- Evidence
- Level IV
- Cohort
- 231 triquetral fractures
- Key finding
- Dorsal chip predominates; 3-week immobilisation successful; no AVN/instability
- Evidence
- Level IV
- Cohort
- 61 wrist examinations
- Key finding
- Only 20% of triquetral fractures seen on radiographs; 30% of wrist fractures occult
- Evidence
- Level III
Registry and cohort data are consistent across Europe and North America: the triquetrum is the second most commonly fractured carpal bone, the dorsal cortical (chip) pattern predominates, and the population is skewed towards young adult men. Plain radiographs substantially under-detect these fractures, so persistent clinical suspicion should drive further imaging.
Guideline & Society Positions
No single national society publishes a stand-alone triquetral-fracture guideline; management is governed by general carpal-fracture and wrist-trauma principles. The table below summarises where authoritative guidance is drawn from across major bodies.
- Position relevant to triquetral fracture
- Carpal fractures other than scaphoid managed by general fracture principles; CT for occult or displaced injury
- Evidence basis
- Expert consensus
- Position relevant to triquetral fracture
- Wrist-trauma standards emphasise excluding perilunate injury and dedicated views when radiographs are normal but tenderness persists
- Evidence basis
- Consensus standards
- Position relevant to triquetral fracture
- Isolated stable triquetral fractures: cast immobilisation; ORIF reserved for displaced body fractures and perilunate patterns
- Evidence basis
- Expert consensus
- Position relevant to triquetral fracture
- No specific triquetral guidance; cross-sectional imaging recommended where plain films are non-diagnostic and suspicion remains
- Evidence basis
- Consensus / NG38 fracture principles
Practice Variation
- Consistent across systems: conservative management (short-arm cast or splint, typically 3 to 6 weeks) is standard worldwide for isolated dorsal chip and undisplaced body fractures, reflecting Level IV evidence of reliable union without instability or avascular necrosis.
- Variation: immobilisation duration varies (3 weeks in the Höcker series versus the more commonly quoted 4 to 6 weeks); thresholds for CT after a normal radiograph differ by access and local protocol.
- Surgery: reserved for displaced body fractures, perilunate spectrum injuries and symptomatic dorsal chip non-union (fragment excision) in all systems.
Viva Scenarios
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“A 25-year-old man presents 2 weeks after a fall onto his hand. He has ongoing ulnar wrist pain. PA radiograph was reported as normal. How do you evaluate this patient?”
“A 30-year-old motorcyclist presents after a crash. X-rays show a displaced triquetral body fracture. How do you approach this injury?”
“A patient returns 6 months after a triquetral dorsal chip fracture, still complaining of dorsal wrist pain with gripping. Radiographs confirm non-union. How do you manage this?”
MCQ Practice Points
Q: What is the second most common carpal fracture? A: Triquetral fractures are the second most common carpal fracture (14-20%), after scaphoid fractures which account for 70-80% of all carpal fractures.
Q: What percentage of triquetral fractures are dorsal chip fractures? A: Over 90% of triquetral fractures are dorsal chip (cortical avulsion) fractures. Body fractures account for less than 10%.
Q: Which radiographic view is most important for diagnosing triquetral dorsal chip fractures? A: The lateral radiograph is essential. Dorsal chip fractures are frequently missed on PA views but clearly visible as a small osseous fragment dorsal to the carpus on the lateral.
Q: What is the primary mechanism causing triquetral dorsal chip fractures? A: Hamate impaction - when the wrist falls into extension and ulnar deviation, the hamate dorsal pole impacts the triquetral dorsum, avulsing a fragment of dorsal cortex.
Q: What is the standard treatment for an isolated triquetral dorsal chip fracture? A: Conservative management with short arm cast for 4-6 weeks. Over 95% heal with immobilization, and the prognosis is excellent.
Q: How should symptomatic non-union of a triquetral dorsal chip be treated? A: Surgical fragment excision through a dorsal approach. This is a straightforward procedure with excellent outcomes in over 95% of patients.
Understanding these key concepts will help with exam success.
Key Statistics
- Second most common carpal fracture (14-20%)
- Over 90% are dorsal chip fractures
- Dorsal chip = excellent prognosis
- Body fracture = assess for perilunate
- Non-union rate 5-10% (usually asymptomatic)
Imaging Pearls
- Lateral view ESSENTIAL - chips missed on PA
- Small osseous fragment dorsal to carpus
- PA view: check carpal alignment, Gilula arcs
- CT for body fracture surgical planning
Mechanism
- FOOSH with ulnar deviation
- Hamate impaction on triquetrum
- Ligament avulsion = traditional teaching (disputed)
- Body fracture = higher energy
Treatment Algorithm
- Dorsal chip: Cast 4-6 weeks
- Body undisplaced: Cast 6-8 weeks
- Body displaced: ORIF with screws/K-wires
- Symptomatic non-union: Fragment excision
Body Fracture Red Flags
- May indicate perilunate spectrum
- Assess Gilula arcs
- Check for DISI/VISI on lateral
- CT/MRI for full evaluation
Outcomes
- Over 95% heal with conservative treatment
- Symptomatic non-union easily treated
- Fragment excision has excellent results
- Return to activity 6-12 weeks typical
Evidence Base
Zander MEL et al. Carpal fractures: epidemiology, classification and treatment of 6542 fractures from the Swedish Fracture Registry
- Population registry of 6542 carpal fractures: scaphoid 60%, triquetrum 25%, hamate 5%, trapezium 4%
- Triquetrum is the second most commonly fractured carpal bone
- Mean age at injury 41 years; 69% of patients male
- Carpal fractures had only a small negative effect on hand function and EQ-5D at one year
Höcker K, Menschik A. Chip fractures of the triquetrum. Mechanism, classification and results
- Series of 231 triquetral fractures with 65 followed for a mean of 47 months
- Dorsal chip caused by the chisel action of the dorso-proximal hamate against the extended, ulnar-deviated wrist
- Conservative immobilisation for 3 weeks was successful; fragment union when it occurred took 6 to 8 weeks
- No post-traumatic carpal instability and no avascular necrosis observed; all body fractures united
Levy M, Fischel RE, Stern GM, Goldberg I. Chip fractures of the os triquetrum: the mechanism of injury
- Cadaveric and radiographic study disproving the avulsion-only theory of dorsal chip fractures
- Mechanism is a chisel action of the ulnar styloid on the dorsum of the triquetrum
- A forceful fall in dorsiflexion and ulnar deviation can also fracture the triquetral body
- A prolonged ulnar styloid projecting beyond the ulnar head was consistently noted
Welling RD et al. MDCT and radiography of wrist fractures: radiographic sensitivity and fracture patterns
- Prospective comparison of radiography with CT as the gold standard in 61 wrist examinations
- Only 20% of triquetral fractures were detected prospectively on radiographs
- 30% of all wrist fractures were not diagnosed prospectively on plain films
- CT should be considered after a negative radiograph when clinical suspicion persists
Boeddrich O et al. Epidemiology of carpal fractures: is it only about the scaphoid?
- Retrospective series of 178 emergency carpal fractures over 6 years
- The triquetrum was the most frequently affected bone, ahead of the scaphoid in this cohort
- Almost all triquetral fractures were treated conservatively
- Young men carried the highest risk of carpal fracture and CT was usually required
The evidence supports conservative management for most triquetral fractures with excellent expected outcomes.