ASPSCR1-TFE3 Sarcoma of Young Adults
- ALVEOLAR SOFT PART SARCOMA (ASPS) is a RARE soft-tissue SARCOMA, most often of ADOLESCENTS and YOUNG ADULTS, characterised by a specific genetic abnormality - the ASPSCR1-TFE3 (ASPL-TFE3) GENE FUSION - which produces nuclear TFE3 over-expression that is a hallmark diagnostic marker (confirmed by immunohistochemistry/molecular testing).
- It typically presents as a PAINLESS, SLOW-GROWING, DEEP soft-tissue mass - commonly in the lower limb/thigh in adults (and the head and neck in children) - and is often highly VASCULAR; because it is painless and indolent, it may grow for a long time and is sometimes diagnosed only after METASTASIS is found.
- The defining clinical paradox is that, despite an INDOLENT slow-growing PRIMARY, ASPS has a STRIKING propensity for EARLY HAEMATOGENOUS METASTASIS - to the LUNG (most common), BONE and characteristically the BRAIN - so staging must include the chest and brain, and LATE metastases (years later) occur, mandating long-term surveillance.
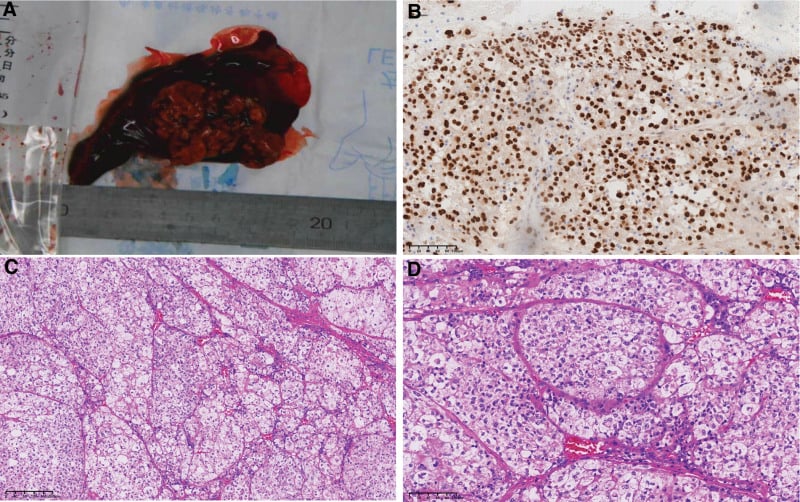
- HISTOLOGY is distinctive: ALVEOLAR/ORGANOID nests of large, polygonal, eosinophilic/granular cells separated by thin-walled sinusoidal vascular channels, with characteristic PAS-POSITIVE, diastase-RESISTANT intracytoplasmic CRYSTALS (rod/rhomboid shaped); the diagnosis is confirmed by nuclear TFE3 immunostaining and/or detection of the ASPSCR1-TFE3 fusion (e.g. on next-generation sequencing).
- DIAGNOSIS and STAGING follow soft-tissue-sarcoma principles: MRI of the primary, a properly PLANNED BIOPSY at the treating sarcoma unit, and STAGING that specifically includes the LUNGS and the BRAIN given the metastatic pattern - an unplanned excision of an undiagnosed deep mass must be avoided.
- MANAGEMENT: WIDE surgical RESECTION of the primary is the mainstay in LOCALISED disease, as ASPS is relatively CHEMO-RESISTANT and doxorubicin-based chemotherapy showed no survival benefit in a 120-patient registry. Metastasectomy is offered for resectable deposits but did NOT improve survival in that registry (a comparison confounded by indication) - so do not promise a survival gain from it. PAZOPANIB was associated with prolonged survival and IMMUNOTHERAPY (checkpoint inhibitors) is also active in advanced disease. LONG-TERM SURVEILLANCE of chest and brain is essential because 45 percent of even localised cases metastasise - all within a specialist sarcoma multidisciplinary team.
- “ASPS = rare soft-tissue sarcoma of YOUNG ADULTS; defining ASPSCR1-TFE3 fusion (nuclear TFE3). Painless, slow-growing, deep, vascular limb mass.
- “Paradox: indolent primary but EARLY HAEMATOGENOUS metastasis (LUNG, bone, BRAIN) - stage the chest AND brain; late metastases occur (long-term surveillance).
- “Histology: alveolar/organoid nests + PAS-positive diastase-resistant crystals; TFE3 nuclear stain. CHEMO-RESISTANT - wide resection (+ metastasectomy); anti-angiogenic TKIs/immunotherapy for advanced disease. Sarcoma-centre care.
Diagnosis, Staging & Management
The indolent appearance of the primary tumour is dangerously misleading. ASPS grows slowly and is painless, so it can be under-estimated, and as with all soft-tissue sarcomas an unplanned excision of an undiagnosed deep mass compromises the oncological outcome.
Work-up. Diagnosis follows soft-tissue-sarcoma principles. A suspicious deep, slow-growing, vascular mass in a young adult should be imaged with MRI, biopsied in a planned way at the treating sarcoma unit, and managed at a specialist sarcoma centre.
Staging. Given the metastatic pattern, staging must specifically include the lungs and the brain.
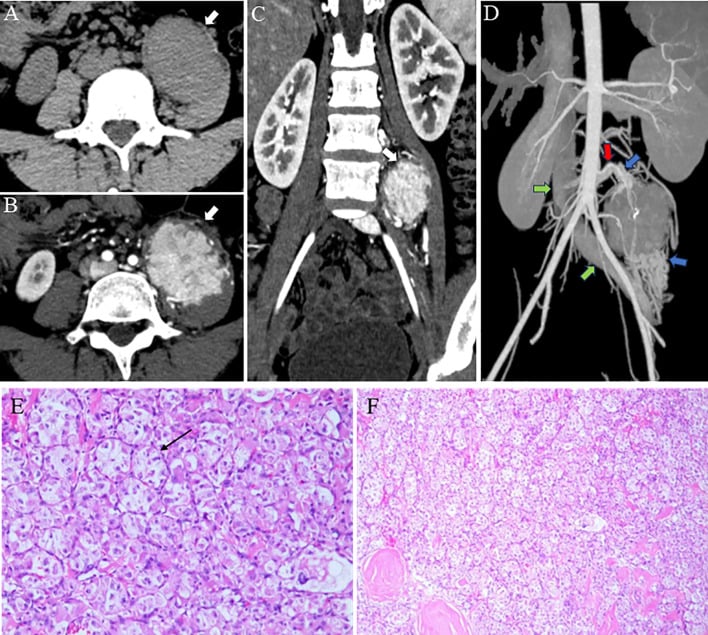
Localised disease. Wide resection of the primary is the mainstay, because ASPS is relatively chemo-resistant. In the registry, adjuvant chemotherapy or radiotherapy did not affect survival in localised disease, and 13 of the 29 followed (45 percent) still developed distant metastases, to lung in 12 (92 percent) and to brain in 2 (15 percent). Adjuvant treatment is therefore no substitute for surveillance.
Metastatic disease. Metastasectomy is offered for resectable deposits, but be careful how it is justified. In the registry, surgery for the primary or for the metastatic site did not affect survival in patients who were already metastatic. That is a retrospective comparison, heavily confounded by indication, because the fittest patients with the most resectable disease get the operation. It is not a reason to withhold an operation from a patient who will benefit symptomatically or from oligometastatic control; it is a reason not to promise a survival gain from metastasectomy that the data do not show, and it argues for honest counselling.
Systemic therapy. ASPS is relatively resistant to conventional cytotoxic chemotherapy. Doxorubicin-based chemotherapy showed no survival benefit in the registry, whereas pazopanib was associated with prolonged survival (p = 0.045). Immune checkpoint inhibitors are also active in advanced disease; no head-to-head comparison against a tyrosine-kinase inhibitor was retrieved.
The case for pazopanib. The rationale for targeting angiogenesis is measured: an angiogenesis oligoarray found 18 angiogenesis-related genes up-regulated in ASPS compared with adjacent normal tissue, with an angiogenic signature the authors described as unique among sarcomas. Disease-specific survival for metastatic disease improved after 2012, when pazopanib became available, from 58 to 65 percent, but the difference was not statistically significant (p = 0.117), so it is a trend and should be quoted as one.
Surveillance. Follow-up is long term and covers the chest and brain, because metastases can appear years later and even localised disease so often metastasises; it is measured in years rather than months. Care sits within a specialist sarcoma multidisciplinary team throughout.
Presentation and Behaviour
Alveolar soft part sarcoma (ASPS) is a rare soft-tissue sarcoma, most often of adolescents and young adults, defined by a specific genetic abnormality: the ASPSCR1-TFE3 (ASPL-TFE3) gene fusion. The fusion drives nuclear TFE3 over-expression, which is the hallmark diagnostic marker.
Presentation. It typically presents as a painless, slow-growing, deep soft-tissue mass, commonly in the lower limb or thigh in adults and in the head and neck in children, and it is often highly vascular. Because it is painless and indolent it may grow for a long time, and it is sometimes diagnosed only after a metastasis has been found.
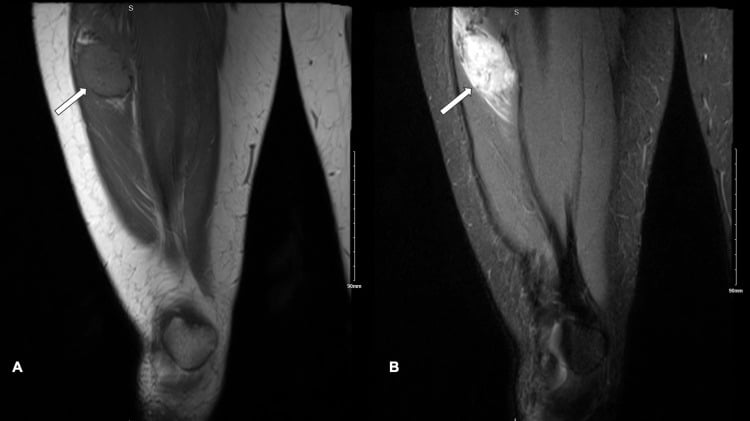
The paradox. Despite the indolent primary, ASPS has a striking propensity for early haematogenous metastasis: to the lung (the commonest site), to bone and, characteristically, to the brain. Late metastases, years later, also occur.
How often it has already spread. "A striking propensity for early metastasis" understates it. In a national registry of 120 newly diagnosed patients, only 34 (28 percent) had localised disease and 86 (72 percent) were already metastatic at presentation. Metastases were already present more often in patients over 25 years (80 percent), with deep-seated tumours (75 percent) and with tumours larger than 5 cm (81 percent), so the "young adult" framing should not lower suspicion in an older patient with a large deep mass.
Survival. The survival figures are more favourable than that proportion implies. Five-year disease-specific survival in the registry was 68 percent overall, 86 percent for localised and 62 percent for metastatic disease, and a separate institutional series reported 74 percent at 5 years and 51 percent at 10. The course is indolent, and treatment-resistant metastases drive the eventual mortality.
Prognosis. Metastasis at presentation was the only adverse prognostic factor in the registry (hazard ratio 7.65).
The Translocation and the TFE3 (Xp11) Family
The translocation. ASPS is defined by an unbalanced translocation, der(17)t(X;17)(p11.2;q25), which fuses ASPSCR1 (ASPL) on chromosome 17q25 to TFE3 on chromosome Xp11.2. The chimeric protein acts as an aberrant transcription factor that up-regulates MET signalling and angiogenesis, which is why the tumour is so vascular (and why anti-angiogenic TKIs work).
The diagnostic marker. Because the fusion drives strong TFE3 expression, the tumour shows strong nuclear TFE3 immunostaining. The stain is sensitive but not fully specific, since other TFE3-rearranged tumours also stain, so FISH or next-generation sequencing for the fusion confirms the diagnosis.
The TFE3/Xp11 family. The same TFE3 (Xp11.2) locus is rearranged in the Xp11 translocation renal cell carcinomas and in a TFE3-rearranged PEComa group, all of them nuclear-TFE3-positive. A TFE3-positive tumour must therefore be placed in its clinical and morphological context.
What the PAS Crystals Are, and the Histological Differential
The pattern. The histology is distinctive: alveolar or organoid nests of large, polygonal, eosinophilic or granular cells, separated by thin-walled sinusoidal vascular channels.
The crystals. The cells contain the pathognomonic PAS-positive, diastase-resistant intracytoplasmic crystals, rod- or rhomboid-shaped. They are membrane-bound crystalline aggregates of the monocarboxylate transporter MCT1 and its chaperone CD147 (EMMPRIN), and they are the specific morphological clue to ASPS.
The mimics. The organoid nests of large granular or eosinophilic cells mimic several tumours, which immunostains separate:
- Metastatic renal cell carcinoma (clear or granular): keratin- and PAX8-positive, whereas ASPS is keratin-negative
- Paraganglioma: chromogranin- and synaptophysin-positive (neuroendocrine), whereas ASPS is negative
- Granular cell tumour: S100-positive, whereas ASPS is S100-negative
- PEComa and melanoma: HMB45- and Melan-A-positive, whereas ASPS is negative
- Adrenal cortical carcinoma: inhibin- and SF1-positive
The clincher. ASPS is characteristically negative for keratin, S100, chromogranin and melanocytic markers and positive for nuclear TFE3. Together with the PAS-positive crystals and the ASPSCR1-TFE3 fusion, that profile makes the diagnosis.
Mnemonics & Memory Aids
ALVEOLAR
Hook:ALVEOLAR: ASPSCR1-TFE3, Limb deep mass, Very vascular, Early lung/bone/brain metastasis, Organoid + crystals, Long-term surveillance, Anti-angiogenic/immunotherapy, Resect widely (chemo-resistant).
LBBMetastatic Pattern - LBB
Hook:Lung, Bone, Brain - and they can arrive YEARS late, so surveillance is measured in years.
KSCHThe Mimics - What ASPS Does NOT Stain For
Hook:Negative for all four, POSITIVE for nuclear TFE3 with PAS-positive diastase-resistant crystals - that combination clinches ASPS.
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“A young adult has a slow-growing, painless, vascular thigh mass, and biopsy shows an alveolar pattern with PAS-positive crystals. What is the diagnosis, and what is critical in management?”
What it is
- Rare soft-tissue sarcoma of adolescents/young adults
- Defining ASPSCR1-TFE3 (ASPL-TFE3) gene fusion driving nuclear TFE3
- Painless, slow-growing, deep, vascular mass (thigh in adults; head/neck in children)
Behaviour
- Indolent primary BUT early haematogenous metastasis
- Lung (most common), bone, and characteristically the brain
- Late metastases occur - long-term surveillance
Diagnosis
- Alveolar/organoid nests; PAS-positive, diastase-resistant crystals
- Nuclear TFE3 immunostain; ASPSCR1-TFE3 fusion (NGS)
- MRI primary + planned biopsy; stage chest AND brain
Management
- Chemo-resistant - wide resection of the primary is the mainstay (localised disease)
- PAZOPANIB had a survival signal; doxorubicin did not. Checkpoint inhibitors also active
- Metastasectomy for resectable deposits did NOT improve survival in registry data (confounded) - counsel honestly
- 72% metastatic at presentation; 5-yr DSS 68% (86% localised / 62% metastatic), 10-yr ~51%
- 45% of localised cases still metastasise - long-term chest AND brain surveillance; sarcoma MDT
Evidence & Key Studies
The der(17)t(X;17)(p11;q25) fuses TFE3 to ASPL - the defining fusion
- The discovery paper for the defining genetics: the non-reciprocal der(17)t(X;17)(p11.2;q25) fuses ASPL (ASPSCR1), a novel gene at 17q25, in-frame to the TFE3 transcription factor gene at Xp11.2.
- An ASPL-TFE3 fusion transcript was detected in ALL 12 ASPS cases tested (9 type 1 fusions joining ASPL to TFE3 exon 4, 3 type 2 to exon 3), establishing the RT-PCR assay as a diagnostic test.
- The reciprocal TFE3-ASPL transcript was found in only 1 of 12 cases, consistent with the non-reciprocal nature of the translocation and identifying ASPL-TFE3 as the oncogenically significant product.
- The fusion retains the TFE3 DNA-binding domain, implicating transcriptional deregulation as the mechanism - the molecular basis for the nuclear TFE3 immunostain used in diagnosis.
Primary pulmonary alveolar soft part sarcoma with ASPSCR1-TFE3 gene fusion (case report)
- Alveolar soft part sarcoma is an extremely rare disease characterised by the specific ASPSCR1-TFE3 gene fusion, confirmed in this case by next-generation sequencing.
- Histology showed the characteristic tumour cells - polygonal cells with abundant eosinophilic or transparent cytoplasm arranged in nests (the alveolar/organoid pattern).
- Management centred on surgical resection with close follow-up, reflecting the importance of detailed diagnosis, prompt treatment and monitoring in ASPS.
National registry of 120 patients: 72 percent metastatic at presentation, and what did not change survival
- 120 newly diagnosed patients from the Bone and Soft-Tissue Tumor Registry in Japan, 2006 to 2017, analysed retrospectively: 34 (28 percent) localised and 86 (72 percent) metastatic AT PRESENTATION.
- Five-year disease-specific survival was 68 percent overall - 86 percent for localised and 62 percent for metastatic disease (p = 0.019).
- Metastasis at presentation was the ONLY adverse prognostic factor (hazard ratio 7.65, p = 0.048); metastases were commoner in patients over 25, with deep-seated tumours and with tumours over 5 cm.
- In localised disease, adjuvant chemotherapy or radiotherapy did NOT affect survival, and 45 percent still developed distant metastases (lung 92 percent, brain 15 percent).
- In metastatic disease, surgery for the primary or the metastatic site did NOT affect survival; pazopanib was associated with prolonged survival (p = 0.045) whereas doxorubicin-based chemotherapy was not.
- Disease-specific survival for metastatic disease rose from 58 to 65 percent after 2012 when pazopanib was approved, but the difference was NOT significant (p = 0.117).
- Retrospective national registry from a single country; the surgical comparisons are confounded by indication and cannot be read as evidence against operating.
Angiogenic gene signature and long-term survival in 71 patients
- Records of 71 patients treated at a single cancer centre between 1986 and 2005, with 33 having tissue available for molecular study.
- Actuarial survival was 74 percent at 5 years and 51 percent at 10 years despite frequent metastasis - the authors describe a highly vascular and metastatic tumour with a surprisingly favourable outcome, in which therapeutically resistant metastases drive mortality.
- The ASPSCR1-TFE3 fusion transcript was identified in 16 of 18 samples tested.
- An angiogenesis oligoarray found 18 angiogenesis-related genes up-regulated in tumour compared with adjacent normal tissue, confirmed for jag-1, midkine and angiogenin, with a signature the authors judged unique among sarcomas - the measured basis for targeting angiogenesis.
- Single-centre retrospective series spanning two decades, with molecular work on only three frozen samples for the array.
The defining ASPSCR1-TFE3 gene fusion (confirmed by next-generation sequencing), the characteristic alveolar/organoid histology (polygonal eosinophilic cells in nests), and the central role of surgical resection with close follow-up come from the cited Hu report. The young-adult demographic, the painless vascular deep-mass presentation, the PAS-positive diastase-resistant crystals and nuclear TFE3 marker, the striking early haematogenous metastasis to lung/bone/brain (with late metastases and long-term surveillance), the chemo-resistance, and the activity of anti-angiogenic TKIs and immunotherapy in advanced disease are standard, well-established teaching. The proportion metastatic at presentation, the survival figures, the hazard ratio for metastasis at presentation, the pazopanib signal and the three negative findings (no survival effect from adjuvant therapy in localised disease, from surgery in metastatic disease, or from doxorubicin) come from the cited Fujiwara national registry - a retrospective, single-country series whose surgical comparisons are confounded by indication. The 5- and 10-year survival figures and the measured angiogenic gene signature come from the cited Lazar series, a single centre spanning 1986 to 2005 with array work on only three frozen samples. No randomised trial in this disease was retrieved, and no evidence-based surveillance interval or duration specific to alveolar soft part sarcoma was found - so the recommendation for prolonged chest and brain imaging is given on the metastatic pattern rather than on a validated schedule, and intervals should follow local sarcoma protocol. See also soft-tissue masses and sarcoma referral and biopsy principles and techniques; the library has no dedicated metastasectomy topic.