Seronegative Spondyloarthropathy | HLA-B27 | Axial Skeleton Involvement
- HLA-B27 positive in 90-95% of patients - but not diagnostic alone
- Sacroiliitis is the hallmark - bilateral symmetric involvement
- Inflammatory back pain: Morning stiffness greater than 30 min, improves with exercise, worse with rest
- Bamboo spine - complete fusion creates high fracture risk from minor trauma
- Spinal fractures - all 3 columns at risk, treat as unstable, high neurological risk
- “Schober test measures lumbar flexion - less than 5cm increase is abnormal
- “Romanus lesion (shiny corner sign) = vertebral body corner erosion
- “Fractures: Assume unstable, image entire spine, CT is gold standard
- “Cervical osteotomy: C7-T1 preferred level for kyphosis correction
Overview and Epidemiology
Ankylosing spondylitis (AS) is a chronic inflammatory disease that primarily affects the axial skeleton and leads to progressive spinal fusion. It is the prototypical seronegative spondyloarthropathy, characterised by sacroiliitis and enthesitis.
Who gets it. Prevalence is 0.1-0.5% in Caucasian populations. Men outnumber women 2-3:1, although the historically higher ratios reflect underdiagnosis in women. Onset peaks at 20-30 years and the disease rarely presents after the age of 45. First-degree relatives carry a 10-20 times increased risk.
Risk factors. HLA-B27 positivity is the major genetic risk factor, and there is strong familial aggregation. Male sex brings higher prevalence and more severe disease, and smoking is associated with worse outcomes and progression.
HLA-B27 in perspective. 90-95% of patients are positive, but the antigen is present in approximately 8% of the general Caucasian population and only 5-10% of HLA-B27 positive individuals develop AS. It is a risk factor, not a diagnostic test. A negative result does not exclude the disease, since approximately 5-10% of AS patients are HLA-B27 negative, and the diagnosis is made on clinical features plus imaging, sacroiliitis on MRI or radiograph.
Pathophysiology
The disease is an aberrant immune response at the entheses, which leads to inflammation and then to new bone formation. Understanding that sequence is what makes both the diagnosis and the management make sense.
HLA-B27. An MHC class I molecule expressed on cell surfaces. How it causes disease is not fully understood; the theories are arthritogenic peptide presentation, protein misfolding and cell-surface homodimer formation. There are over 100 HLA-B27 subtypes, of which B*27:05 and B*27:02 are the most associated with AS.
Non-HLA genes. The named ones are ERAP1, an aminopeptidase involved in peptide processing, and IL-23R, which points to the importance of the IL-23/IL-17 axis in pathogenesis; genome-wide association studies have identified multiple other loci.
Enthesitis. The primary site of inflammation is the enthesis, where tendon or ligament attaches to bone, and the entheses at the sacroiliac joints and spine are particularly affected. The inflammatory infiltrate carries TNF-alpha, IL-17 and IL-23.
From inflammation to bone. The paradox of the disease is that an erosive inflammatory process ends in ossification:
- Erosive inflammation at the entheses
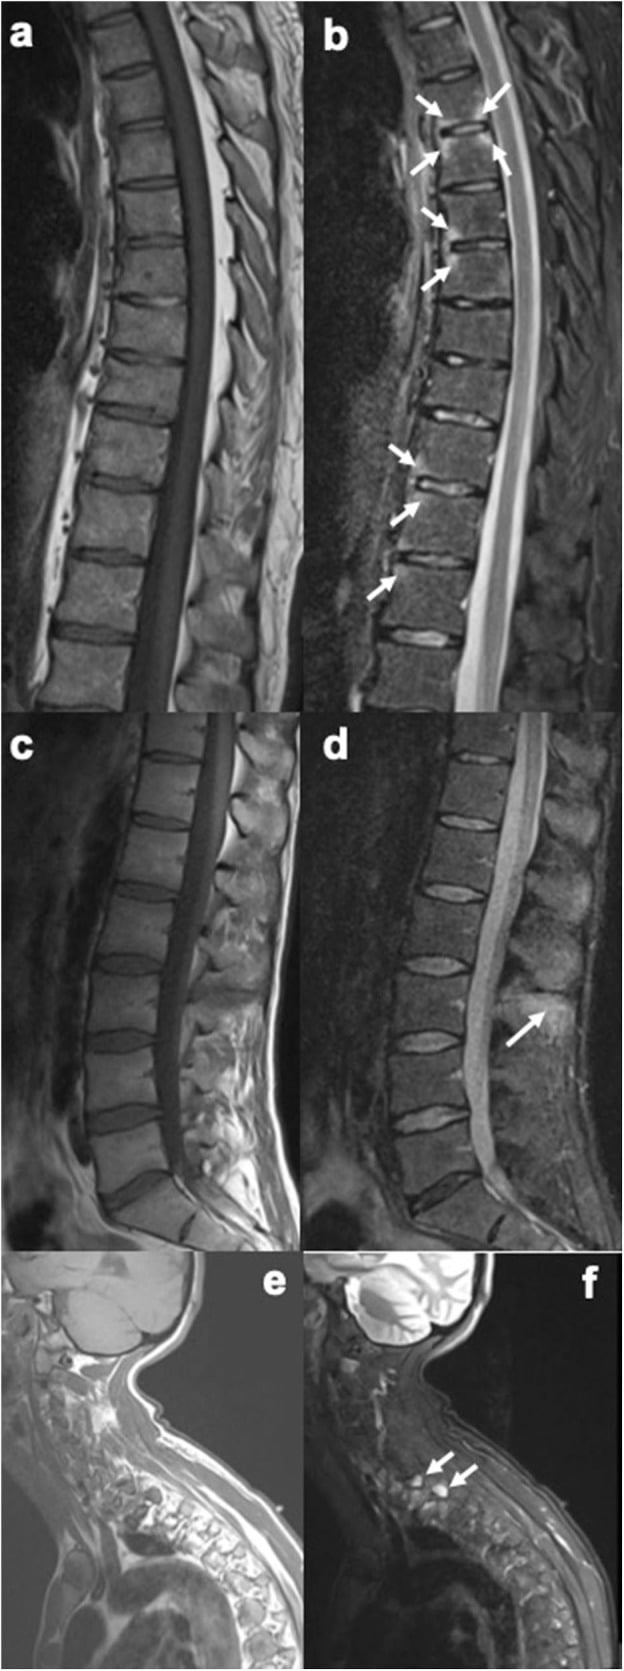
- Bone marrow oedema, visible on MRI
- TNF and IL-17 drive the inflammation
- The repair response forms new bone, the syndesmophytes
- Eventually, complete fusion
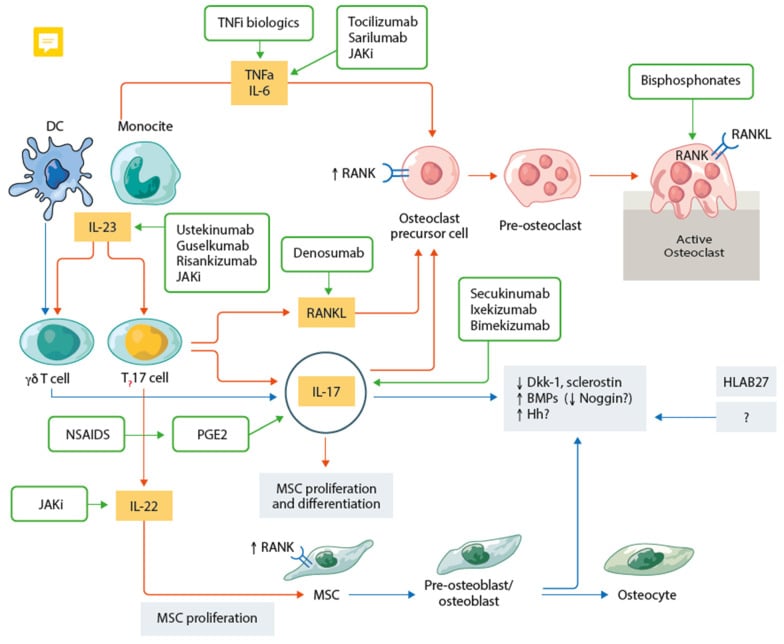
Anti-TNF therapy controls inflammation effectively but may not prevent radiographic progression, the new bone formation. This disconnect between inflammation and ossification matters when counselling patients and is a common exam discussion point.
Sacroiliac joints. The earliest site of involvement. Subchondral bone erosions appear, with sclerosis and widening of the joint initially, and then fusion.
Spine. Erosion at the vertebral body margins produces the Romanus lesion, a corner erosion. Repair produces the syndesmophyte, a vertical bony bridge between vertebrae. The vertebral bodies square, and complete fusion gives the bamboo spine.
Clinical Presentation
Inflammatory back pain is the cardinal feature, and its pattern is what separates it from mechanical back pain. The features are the five in NIGHT below; alternating buttock pain points to the sacroiliac joints.
NIGHTInflammatory Back Pain Features
Hook:NIGHT pain keeps AS patients awake but MOVEMENT makes it better!
Progressive restriction. As the spine stiffens, the lumbar lordosis is lost and the thoracic kyphosis increases, chest expansion falls, and cervical involvement leaves a fixed forward gaze. In severe cases the neck is fixed in flexion, the chin-on-chest deformity, and the global kyphosis produces the question mark posture.
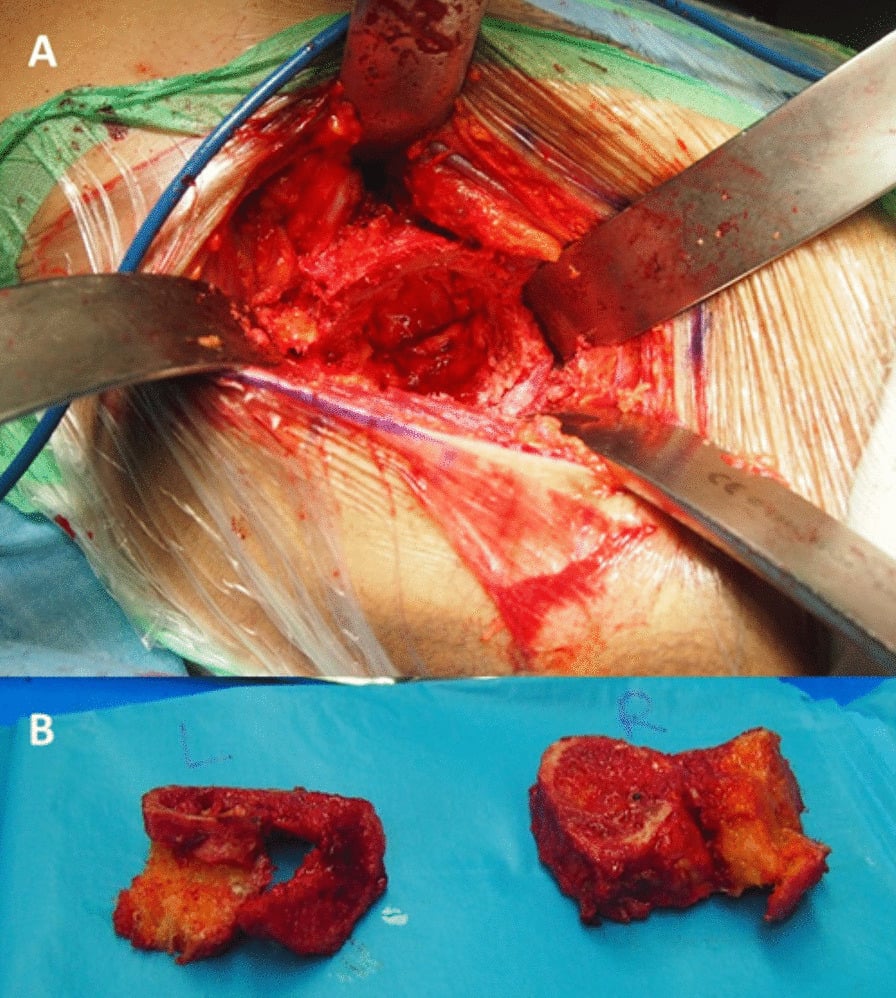
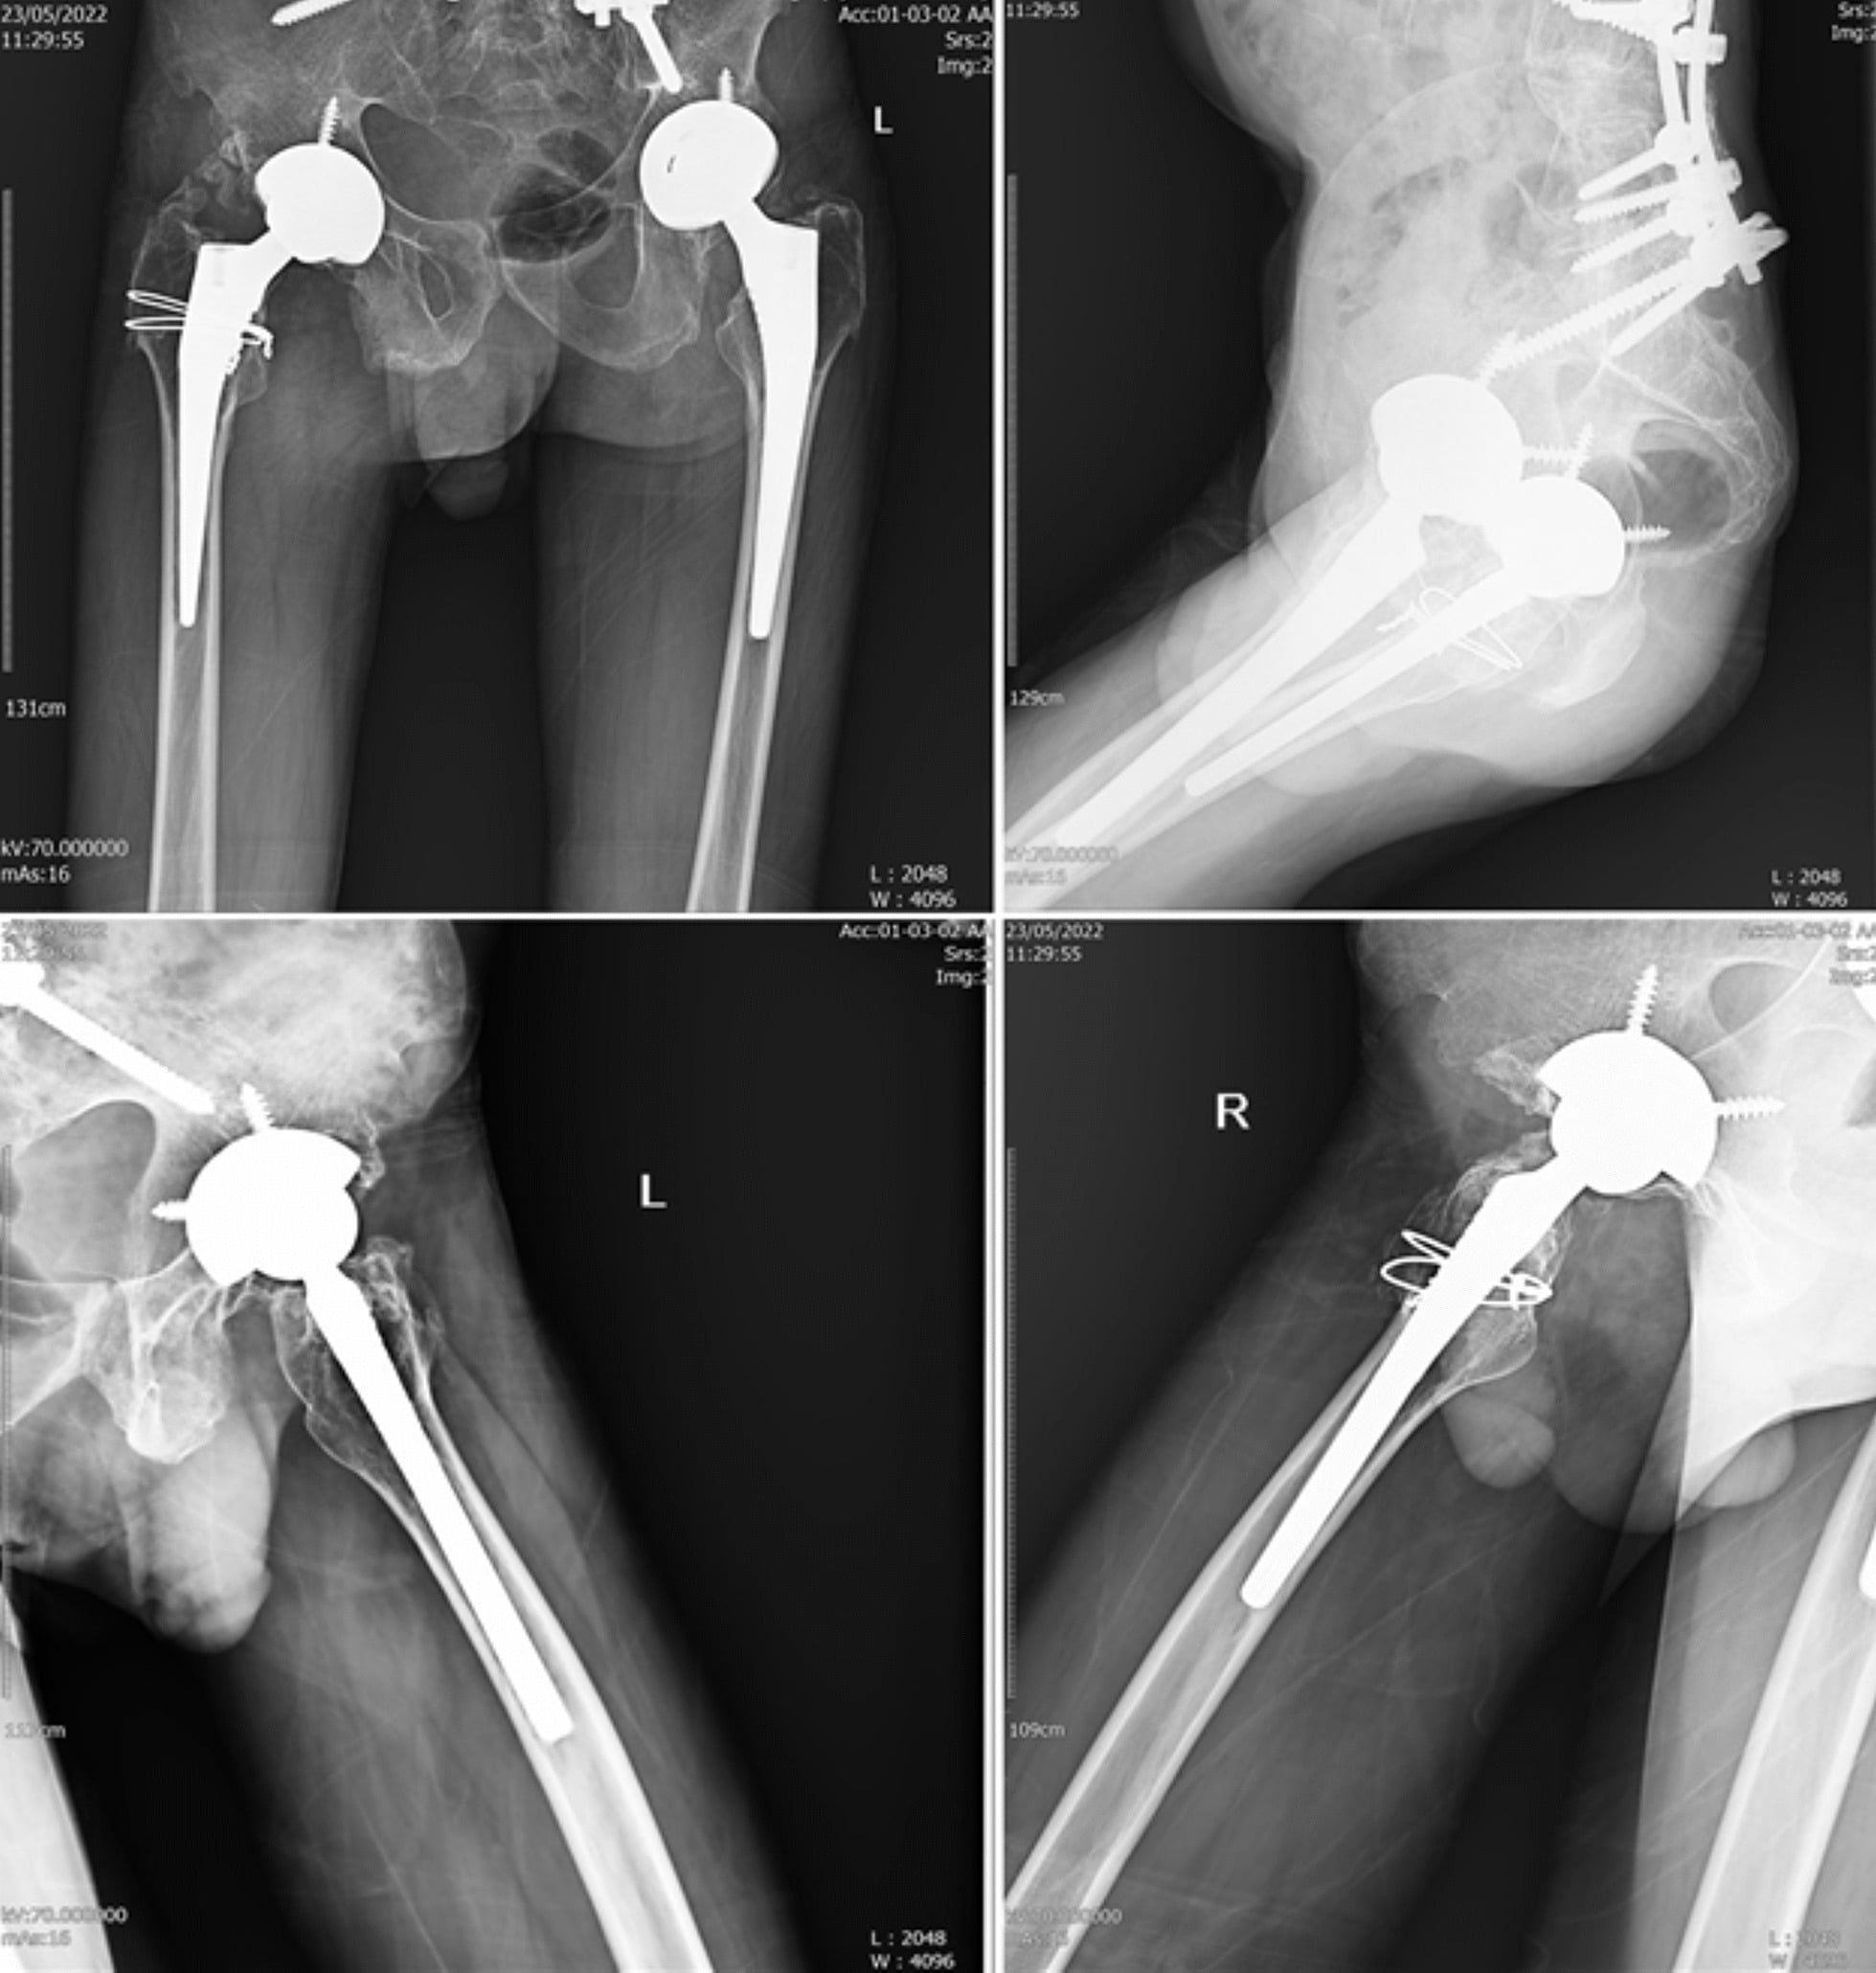
The hips. Involved in 30-50% of patients, often bilaterally, and a major cause of disability. Hip involvement within the first 10 years of the disease carries a worse prognosis.
Other joints. Shoulder involvement is common; the knee and ankle are affected less often. The pattern is an asymmetric oligoarthritis.
Acute anterior uveitis is the most common extra-articular feature, in 25-40% of patients. It is unilateral and recurrent, presents as a painful red eye with photophobia, and is an ophthalmology emergency because it can cause vision loss.
Heart and lungs. The cardiovascular manifestations are aortitis, aortic root dilatation, aortic regurgitation in 1-10% and conduction defects. Apical pulmonary fibrosis is rare; restrictive lung disease follows fusion of the chest wall.
Examination. Inspect the posture first, then measure. The named tests:
- Schober test: mark L5 and a point 10 cm above; on forward flexion an increase of under 5 cm is abnormal
- Modified Schober: marks 5 cm below and 10 cm above the PSIS
- Chest expansion: under 2.5 cm at the nipple line is abnormal
- Occiput-to-wall distance: should be zero; any distance indicates cervical kyphosis
- Tragus-to-wall distance: an alternative measure of cervical mobility
Investigations
Inflammatory markers. ESR and CRP are raised in 50-70%, so normal markers do not exclude AS. They are useful for monitoring disease activity.
HLA-B27 supports the clinical diagnosis rather than making it, and is most useful in early disease when imaging is inconclusive. Rheumatoid factor and anti-CCP are negative, which is what seronegative means, and helps distinguish AS from rheumatoid arthritis.
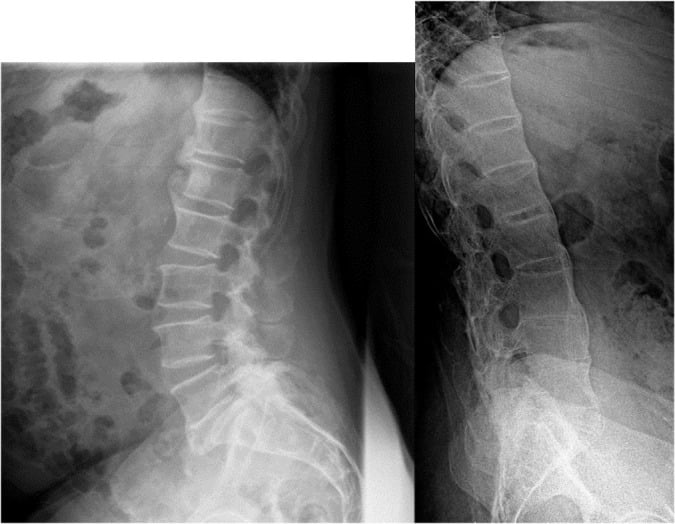
Radiographs. At the sacroiliac joints the picture is bilateral symmetric sacroiliitis: erosions, sclerosis, widening or narrowing of the joint space, and fusion, graded 0-4 by the modified New York criteria. In the spine look for squaring of the vertebral bodies, marginal vertical syndesmophytes, the Romanus lesion (the shiny corner sign), the Andersson lesion (discovertebral destruction) and, at the end, the bamboo spine of complete fusion.
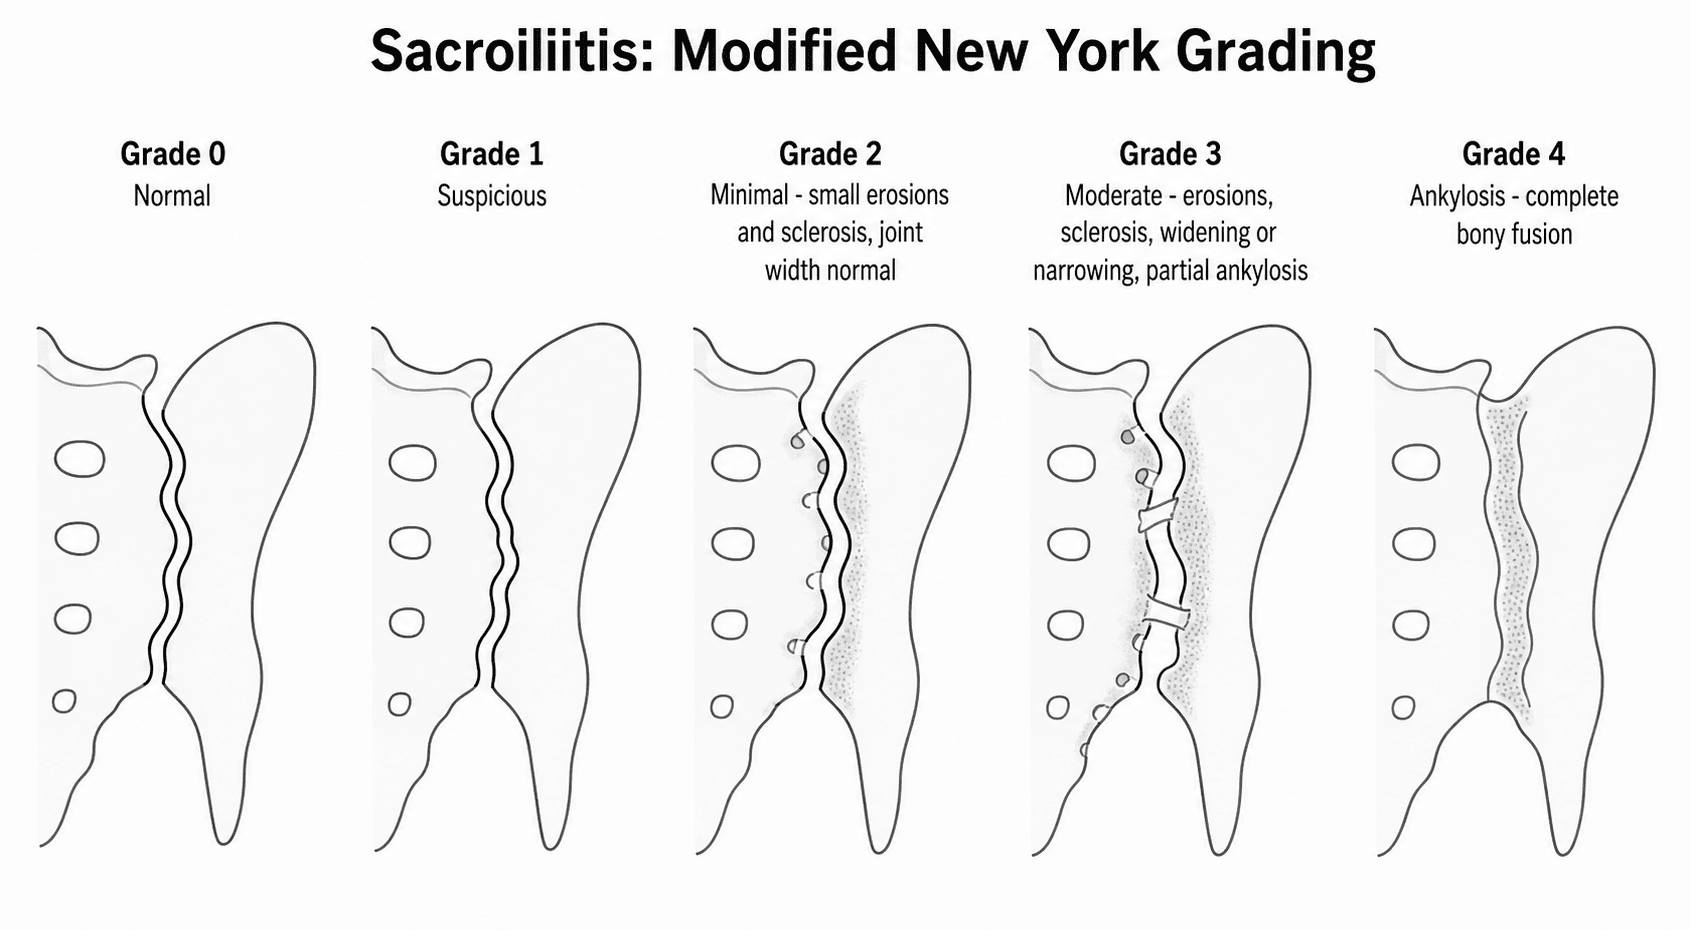
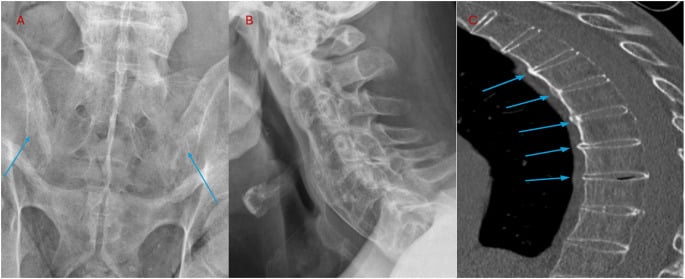
Definite AS requires radiographic sacroiliitis, bilateral grade 2-4 or unilateral grade 3-4, plus at least one clinical criterion: inflammatory back pain, limited lumbar motion or reduced chest expansion. These criteria miss early disease, which is why the ASAS criteria incorporate MRI.
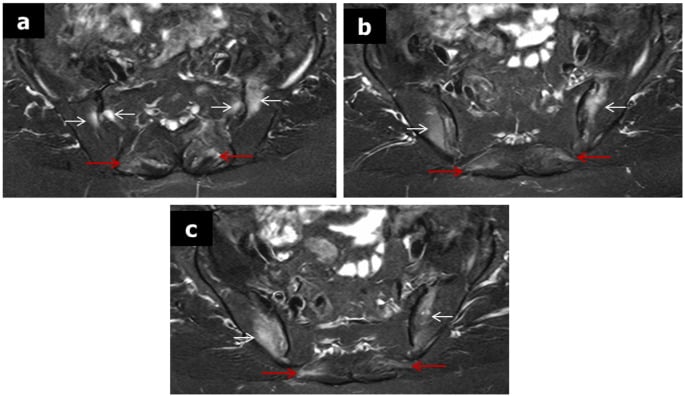
MRI. Bone marrow oedema at the sacroiliac joints is active sacroiliitis, and STIR or T2 fat-saturated sequences show it best. MRI can detect inflammation before any radiographic change and enables diagnosis 5-10 years earlier than radiographs.
CT is the study for fracture in the AS spine. It is superior to radiographs for a fracture through fused segments, and when a fracture is suspected the entire spine is imaged; the fracture pathway is set out under Surgical Management.
Differential Diagnosis
The two highest-yield distinctions are AS versus DISH, both of which ankylose the spine and fracture as long bones, and inflammatory versus mechanical or degenerative back pain.
- Ankylosing Spondylitis
- Onset under 40
- DISH (Forestier)
- Over 50
- Degenerative / Mechanical
- Any, usually older
- Ankylosing Spondylitis
- Bilateral fusion (defining)
- DISH (Forestier)
- Spared (may have bridging only)
- Degenerative / Mechanical
- Degenerative, not fused
- Ankylosing Spondylitis
- Thin marginal syndesmophytes
- DISH (Forestier)
- Flowing 'candle-wax' osteophytes, right-sided thoracic
- Degenerative / Mechanical
- Marginal osteophytes
- Ankylosing Spondylitis
- Disc preserved early
- DISH (Forestier)
- Disc height preserved
- Degenerative / Mechanical
- Disc/facet degeneration
- Ankylosing Spondylitis
- 90-95% positive
- DISH (Forestier)
- Not associated
- Degenerative / Mechanical
- Not associated
- Ankylosing Spondylitis
- Often raised
- DISH (Forestier)
- Normal
- Degenerative / Mechanical
- Normal
- Ankylosing Spondylitis
- Inflammatory (better with movement)
- DISH (Forestier)
- Stiffness, often mild
- Degenerative / Mechanical
- Mechanical (worse with movement)
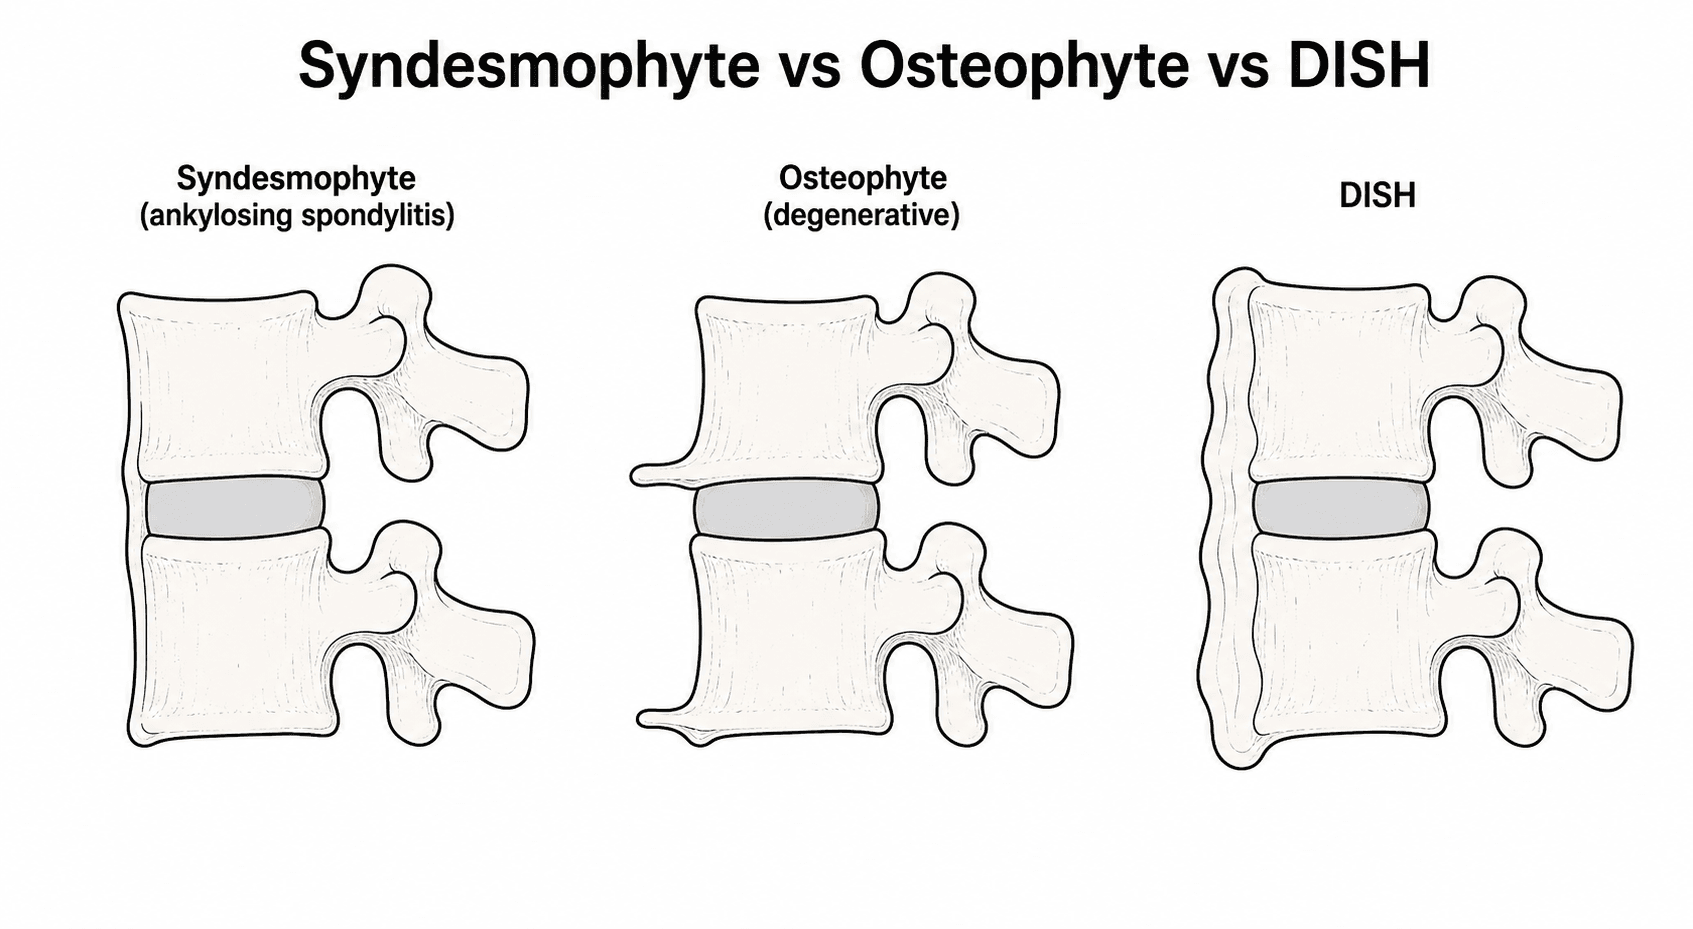
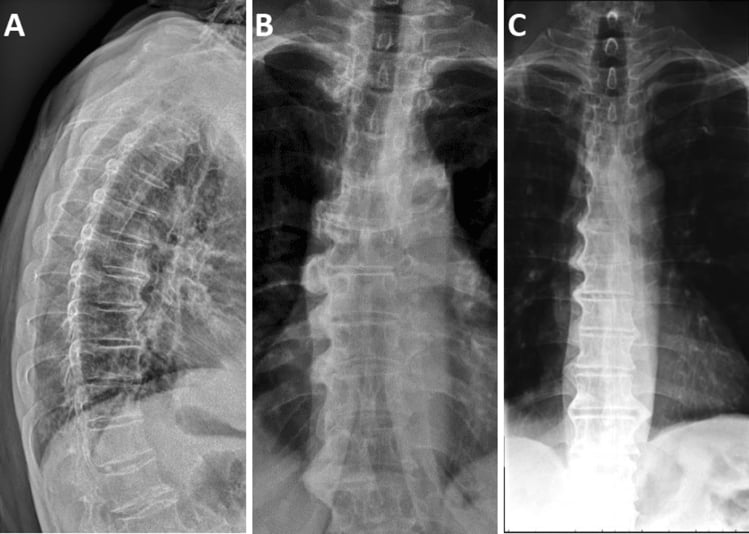
Both AS and DISH create a rigid, long-lever spine that fractures through all columns after trivial trauma and is easily missed on plain films. The orthopaedic management principle (CT whole spine, assume unstable, long-segment fixation) is the same, so do not let the AS-versus-DISH label delay imaging or stabilisation.
- Ankylosing Spondylitis
- 90-95%
- Reactive Arthritis
- 60-80%
- Psoriatic Arthritis
- 40-50%
- Ankylosing Spondylitis
- Always (defining feature)
- Reactive Arthritis
- Common
- Psoriatic Arthritis
- 40% have spondylitis
- Ankylosing Spondylitis
- Uncommon
- Reactive Arthritis
- Predominant
- Psoriatic Arthritis
- Common - DIP, dactylitis
- Ankylosing Spondylitis
- Bilateral symmetric
- Reactive Arthritis
- Asymmetric
- Psoriatic Arthritis
- Asymmetric
- Ankylosing Spondylitis
- Uveitis, aortitis
- Reactive Arthritis
- Conjunctivitis, urethritis
- Psoriatic Arthritis
- Skin, nail changes
- Ankylosing Spondylitis
- Chronic progressive
- Reactive Arthritis
- Often self-limiting
- Psoriatic Arthritis
- Variable
Management
NSAIDs first. Indomethacin, naproxen and etoricoxib are all effective, and continuous dosing is more effective than on-demand dosing. Whether NSAIDs slow radiographic progression is controversial. An NSAID that is effective and tolerated is continued.
When NSAIDs fail. Failure means two agents over four weeks. TNF inhibitors, adalimumab, etanercept, infliximab, golimumab and certolizumab, are highly effective for symptoms and inflammation; most funders require high disease activity on ASDAS or BASDAI plus failure of two NSAIDs. The IL-17 inhibitors secukinumab and ixekizumab are the alternative, and particularly useful after TNF failure.
Other drugs. Sulfasalazine may help peripheral arthritis but has limited axial benefit, and methotrexate is not effective for axial disease. Local corticosteroid injections are useful; long-term systemic corticosteroids are avoided.
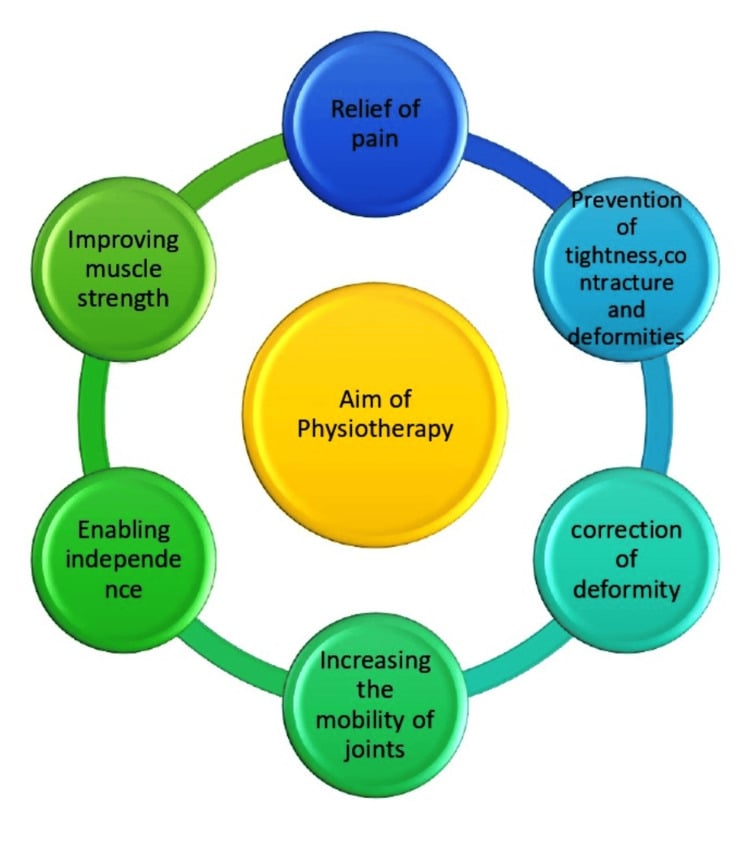
Physiotherapy is essential and a lifelong commitment. Posture and mobility are maintained by regular stretching and strengthening, and hydrotherapy is beneficial.
Surgical Management
Indications for spinal surgery. Four, of which spinal fracture is the most common:
- Spinal fractures
- Kyphosis correction, for a fixed forward gaze and inability to see the horizon
- Spinal stenosis, rare, with cauda equina syndrome
- Pseudarthrosis, an Andersson lesion causing instability
Airway management is critical. A fixed cervical kyphosis limits the options for intubation, and fibreoptic intubation is often required. Position carefully and avoid neck extension; consider positioning the patient awake before induction.
The ankylosed spine functions as a long bone: fractures extend through all three columns, and even minor trauma can cause one. Neurological deficit is present on admission in 67.2% of AS patients in the largest systematic review (345 patients; PMID 18791749), and secondary neurological deterioration occurs frequently. Treat every fracture as unstable until proven otherwise.
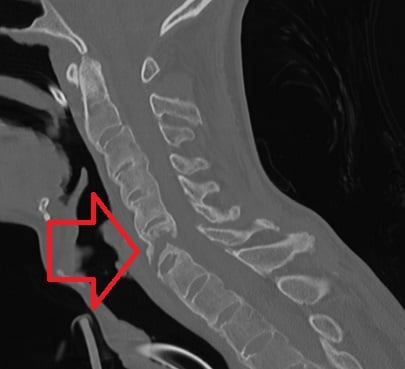
The fractures themselves. In the review most were cervical and followed low-energy impact; the mechanism is commonly hyperextension. Delayed diagnosis was common, from both patient and doctor factors.
Principles.
- Assume unstable: all three columns are involved
- Image the entire spine: non-contiguous fractures occur in 5-10%
- CT is essential: radiographs miss 30% of fractures
- MRI for the cord if there is a neurological deficit
- Immobilise in the position of deformity: do not attempt correction
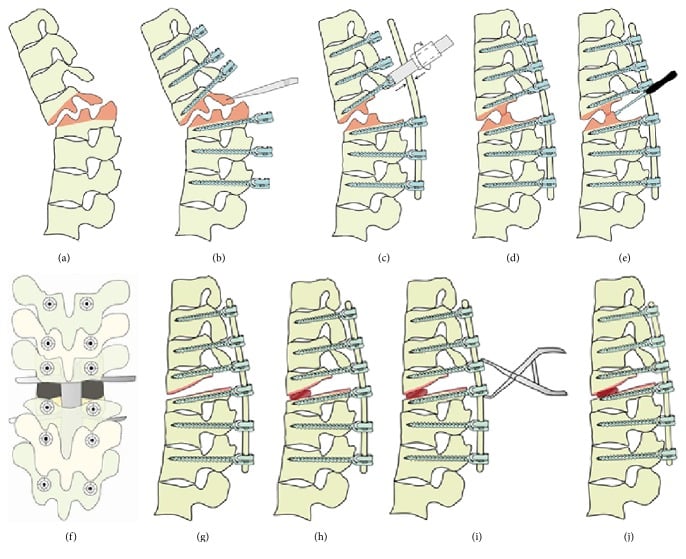
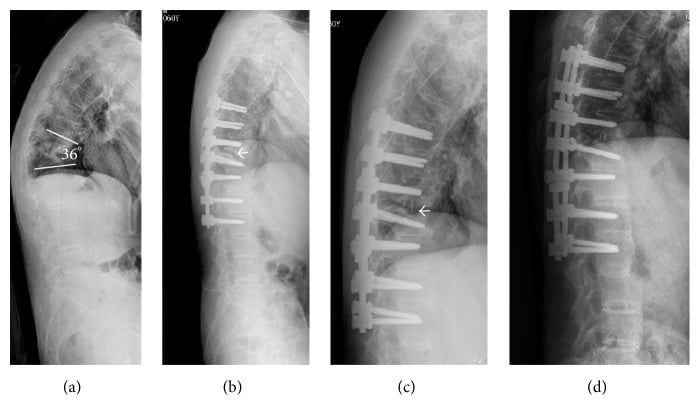
Surgery is usually preferred, and be honest about what it does and does not achieve. Early stabilisation permits mobilisation, nursing and pain control, and avoids the very real problems of external immobilisation in a rigid, deformed spine. The construct is long posterior instrumentation, three or more levels above and below, because the long lever arms of a fused spine load a short construct heavily; anterior support is considered where there is significant kyphosis, and cement augmentation for osteoporotic bone.
What stabilisation does not do. The systematic review's uncomfortable finding was that surgical and non-operative treatment "did not alter the neurological prospective for most patients" (PMID 18791749). Stabilisation is done to control the mechanics, not because it reliably reverses or prevents neurological injury, and that should not be overstated in a viva or to a family.
Conservative management is reserved for undisplaced, stable fractures without neurological deficit. A halo vest or Minerva cast is problematic because the rigid spine and its pre-existing deformity cannot be corrected into the orthosis.
Outcomes. In the 345 pooled AS patients (PMID 18791749), mortality was 17.7% within three months of injury, far higher than in the general trauma population and higher than the 5-15% often quoted, and the overall complication rate was 51.1%. The rate of epidural haematoma was high, and delayed union and pseudarthrosis are risks. For contrast, DISH patients in the same review fared better on neurology (40.0% deficit) and complications (32.7%) but similarly badly on mortality (20.0%).
Andersson Lesion (Discovertebral Lesion and Spinal Pseudarthrosis)
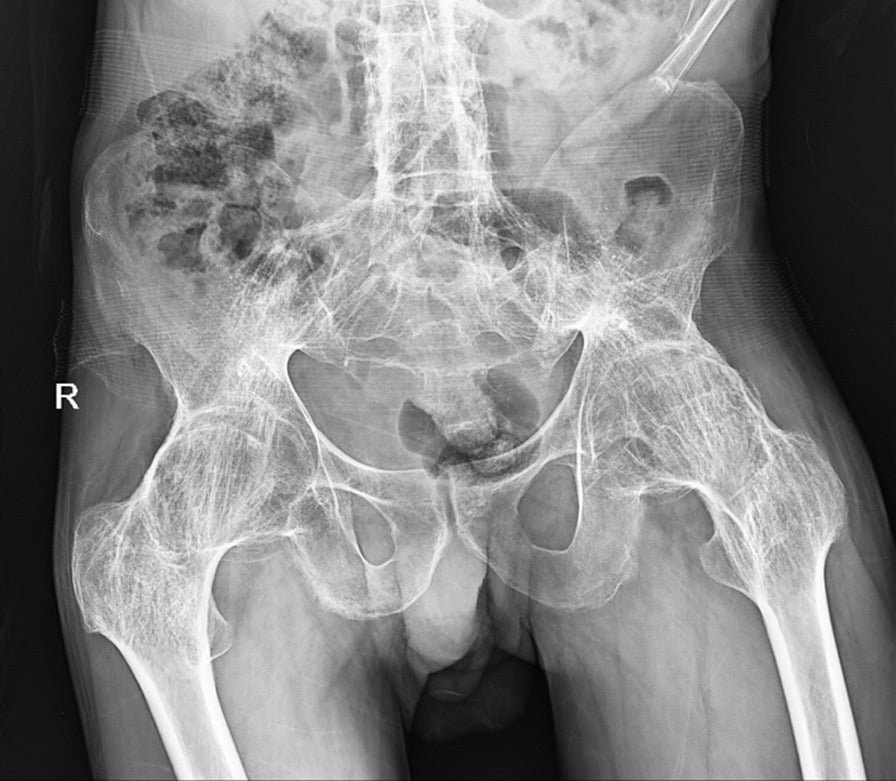
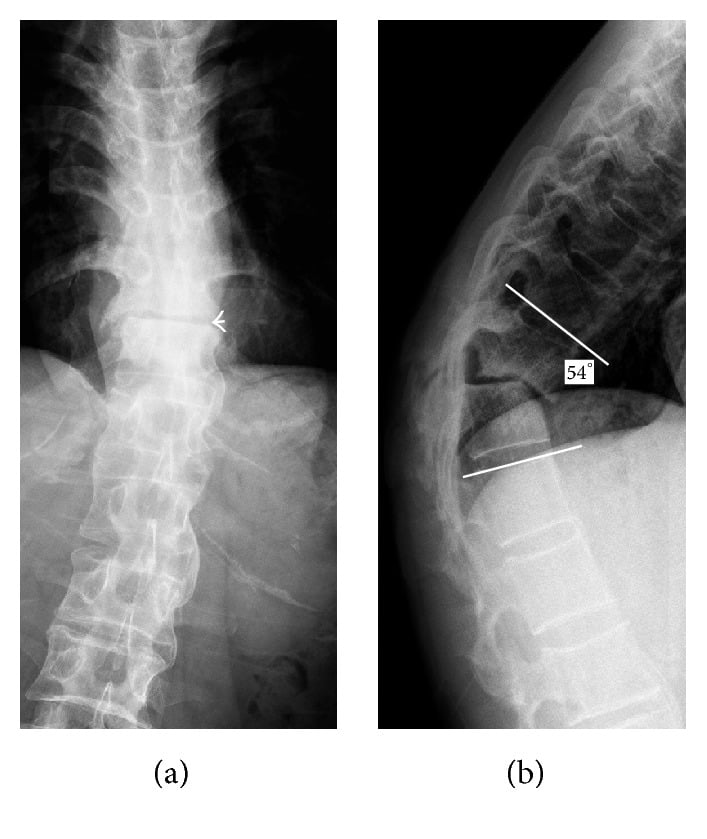
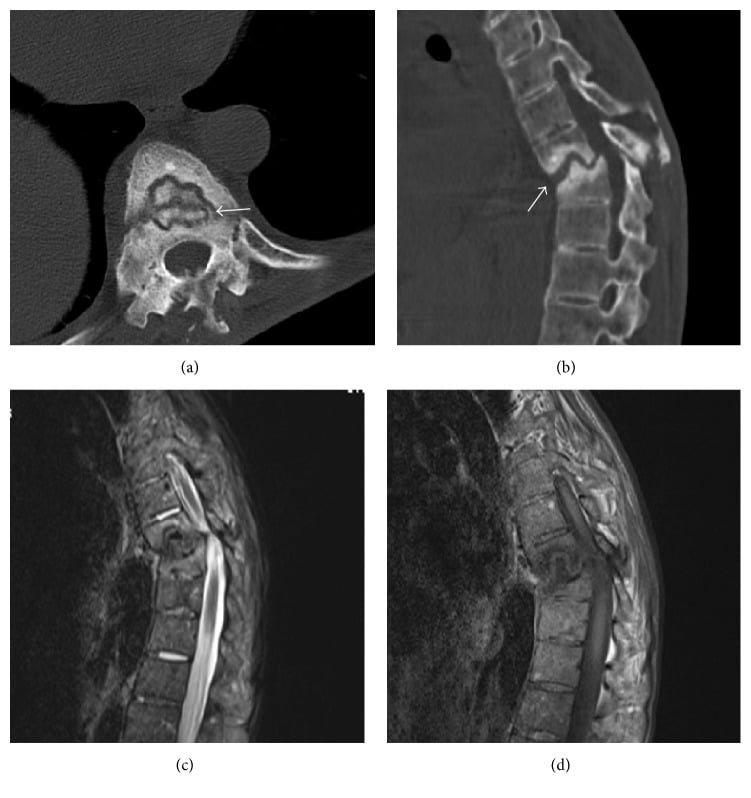
An Andersson lesion, named for Olof Andersson and frequently misspelt with a single "s", is a localised, lucent, destructive lesion of the discovertebral junction in the ankylosed spine. It is both a radiographic finding and, when it destabilises the spine, a surgical indication. Clinically it presents as new, focal pain in an otherwise stiff or fused back, and it has two recognised forms that are managed in opposite ways.
- Inflammatory type
- Active spondylodiscitis-like inflammation of the discovertebral junction
- Mechanical (pseudarthrosis) type
- A stress fracture or established non-union through the rigid fused column with continued micromotion
- Inflammatory type
- Earlier, active inflammatory disease
- Mechanical (pseudarthrosis) type
- Later, in the established bamboo spine
- Inflammatory type
- Erosive discovertebral lesion with marrow oedema on MRI
- Mechanical (pseudarthrosis) type
- Lucent lesion with sclerotic margins and a transdiscal/transvertebral cleft; mobility may be seen on dynamic or flexion-extension films
- Inflammatory type
- Medical control of inflammation
- Mechanical (pseudarthrosis) type
- Surgical stabilisation if there is instability or progressive kyphosis — treat it like a fracture non-union
The mechanical type is the surgical one. It is effectively a non-union through the ankylosed spine, so when it causes instability or progressive deformity it is stabilised with long-segment fixation in the same way as an acute AS fracture.
An Andersson lesion can closely mimic INFECTIVE spondylodiscitis, and occasionally malignancy, on imaging. If infection cannot be confidently excluded, biopsy before attributing the lesion to AS.
Complications
Of the disease. The spinal fracture after minor trauma, the fixed kyphosis and the hip are dealt with above; the rest of the list is what an examiner will expect alongside them.
- Cauda equina syndrome, a late complication of arachnoiditis
- Atlanto-axial subluxation, rare but serious
- Restrictive lung disease from costovertebral fusion
- Aortic regurgitation from aortitis
- Vision loss from untreated uveitis
- Secondary amyloidosis, rare and late
Of surgery. The list to have ready:
- Neurological injury, a high risk with fractures and with osteotomy
- Epidural haematoma, common with AS fractures
- Pseudarthrosis: healing is difficult, especially at osteotomy sites
- Implant failure in osteoporotic bone with long lever arms
- Dural tear, because ossified dura may be encountered
- Heterotopic ossification after hip surgery
Disease Activity and Outcome Measures
Biologic eligibility and treat-to-target monitoring are expressed in indices, and the management and guideline sections quote them. Knowing what each one measures is high-yield.
- What it measures
- Patient-reported disease ACTIVITY — six items (fatigue, spinal pain, peripheral pain/swelling, enthesitis, plus morning-stiffness severity and duration), scored 0 to 10
- Key point
- A score of at least 4 conventionally defines active disease and is the classic biologic-eligibility threshold; entirely subjective, with no objective inflammation captured
- What it measures
- Disease activity COMBINING patient-reported items with an acute-phase reactant (CRP preferred)
- Key point
- Validated states: inactive under 1.3, low 1.3 to 2.1, high 2.1 to 3.5, very high over 3.5; preferred for treat-to-target because it adds objective CRP
- What it measures
- Patient-reported FUNCTION — ten items on daily activities, scored 0 to 10
- Key point
- Tracks disability and complements the activity scores; does not measure inflammation
- What it measures
- Clinician-measured spinal MOBILITY (tragus-to-wall, cervical rotation, lumbar flexion/Schober, lumbar side-flexion, intermalleolar distance)
- Key point
- Objective measure of mobility loss and accumulating structural restriction
- What it measures
- Radiographic STRUCTURAL damage and progression — cervical and lumbar vertebral corners on the lateral radiograph
- Key point
- The standard endpoint for radiographic progression (for example the MEASURE 1 result of an mSASSS change under 2 in most patients)
Do not confuse disease ACTIVITY (BASDAI, ASDAS) with FUNCTION (BASFI), MOBILITY (BASMI) or radiographic STRUCTURAL damage (mSASSS). An examiner may ask which index you would use to justify escalating therapy and which to track long-term fusion.
Guidelines, Registries & Global Practice
Global Epidemiology
- Pooled global prevalence of AS is approximately 0.2-0.5%, with the strongest determinant being background HLA-B27 frequency. AS is rare where HLA-B27 is rare (e.g. parts of sub-Saharan Africa, Japan has low prevalence) and more common where HLA-B27 is high (e.g. some Northern European and Indigenous Arctic/First Nations populations).
- Historic male predominance (2-3:1) is now recognised as partly artefact - women are diagnosed later and more often have non-radiographic axial SpA.
- Mean diagnostic delay remains 5-10 years globally, driven by attribution to mechanical back pain.
Side-by-Side Guidelines
- Diagnosis emphasis
- ASAS criteria - MRI sacroiliitis for nr-axSpA
- Biologic trigger
- High activity (ASDAS at least 2.1 or BASDAI at least 4) after 2 NSAIDs
- Distinctive point
- Treat-to-target; bDMARD and tsDMARD (JAKi) both endorsed
- Diagnosis emphasis
- Imaging + clinical, MRI for early disease
- Biologic trigger
- TNFi preferred first-line biologic
- Distinctive point
- Strong recommendation for continuous NSAIDs and PT
- Diagnosis emphasis
- Specialist referral for inflammatory back pain
- Biologic trigger
- TNFi or secukinumab if BASDAI at least 4 and spinal pain after 2 NSAIDs
- Distinctive point
- Defined response criteria for continuation funding
- Diagnosis emphasis
- CT whole spine for any suspected fracture
- Biologic trigger
- n/a
- Distinctive point
- Ankylosed-spine fracture = long-bone-type unstable injury
Registry & Practice Variation
- Arthroplasty registries (NJR, AOANJRR, SHAR, NZJR) consistently show AS patients undergoing THA at a younger age than primary OA, with good implant survival but higher heterotopic ossification.
- High-resource settings: early MRI, rapid access to biologics (TNFi, IL-17i, JAK inhibitors), and treat-to-target monitoring with ASDAS.
- Limited-resource settings: diagnosis often at the bamboo-spine/fixed-deformity stage; NSAIDs and physiotherapy remain the mainstay where biologics are unaffordable, so fracture prevention, fall counselling and arthroplasty/osteotomy services carry greater burden.
- Across all settings, rheumatology-orthopaedic co-management is essential because spinal fractures and hip involvement are the principal orthopaedic endpoints of the disease.
Controversies & Areas of Uncertainty
Do NSAIDs slow radiographic progression? Earlier data suggested continuous NSAIDs retard syndesmophyte formation, but the ENRADAS trial did not confirm a structural benefit of continuous over on-demand dosing. Continuous use is justified for symptom control, not proven disease modification.
Do biologics prevent ankylosis? Anti-TNF and IL-17 agents control inflammation, but the link to halting new bone formation is unresolved (the "TNF paradox"). Some long-term cohort and IL-17 data suggest reduced progression, but no agent reliably stops fusion.
TNFi versus IL-17i first-line. Both are effective, and the choice is comorbidity-driven rather than efficacy-driven: TNFi covers concomitant inflammatory bowel disease and uveitis better.
nr-axSpA as a disease entity. Whether non-radiographic axial SpA is early AS or a partly separate entity (with more women and a lower progression rate) remains debated, which affects how aggressively to treat.
Spinopelvic targets for THA. With a stiff fused spine, optimal acetabular orientation is contested; "safe zone" cup targets derived from mobile-spine patients may not apply, and functional or spinopelvic planning is increasingly recommended.
Osteotomy choice. Pedicle subtraction osteotomy gives more correction per level than Smith-Petersen but with higher neurovascular risk; the optimal trade-off and the use of multilevel SPO remain individualised.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 55-year-old man with known ankylosing spondylitis presents after a ground-level fall. He has neck pain and bilateral arm numbness. X-rays are reported as normal.”
“A 28-year-old man presents with 18 months of low back pain. He reports morning stiffness lasting over an hour that improves with exercise. His pain wakes him at night. Examination shows reduced lumbar flexion.”
“A 60-year-old man with longstanding AS has progressive difficulty seeing ahead when walking. He cannot see the horizon and has trouble eating. He has a fixed chin-on-chest deformity.”
“A 45-year-old man with AS has bilateral hip pain limiting walking to 100 metres. X-rays show severe bilateral hip arthritis. He has 30 degrees of fixed thoracolumbar kyphosis.”
Diagnosis
- HLA-B27 positive in 90-95% (not diagnostic alone)
- Bilateral symmetric sacroiliitis on imaging
- MRI detects early sacroiliitis (bone marrow edema)
- Modified New York criteria: sacroiliitis + clinical features
Inflammatory Back Pain
- Age less than 40, insidious onset
- Morning stiffness greater than 30 minutes
- Improves with exercise, worse with rest
- Night pain - wakes in second half of night
Spinal Fractures
- ALL fractures are UNSTABLE (3 columns)
- CT entire spine - X-rays miss 30%
- Immobilize in position of deformity
- Surgical stabilization preferred
Physical Examination
- Schober test: less than 5cm increase abnormal
- Chest expansion: less than 2.5cm abnormal
- Occiput-to-wall: increased with kyphosis
- Question mark posture in advanced disease
Treatment Ladder
- NSAIDs first-line (continuous more effective)
- Physiotherapy essential - lifelong
- TNF inhibitors if NSAID failure
- IL-17 inhibitors alternative biologic
Surgical Considerations
- Airway: fibreoptic intubation often needed
- Positioning: avoid forced positions
- THA: high HO risk - prophylaxis essential
- Osteotomy: C7-T1 for cervical kyphosis
Evidence Base
MEASURE 1 - Secukinumab (IL-17A inhibition) in AS
- ASAS20/40 at week 208 was 79.7%/60.8% (150 mg dose)
- No radiographic progression (mSASSS change under 2) in 79% of patients
- Consistent safety profile - low serious infection and Candida rates
Spinal Fractures in Ankylosing Spinal Disorders (AS/DISH)
- Neurological deficit on admission in 67.2% of AS patients
- Overall complication rate 51.1% in AS; 3-month mortality 17.7%
- Most fractures cervical and from low-energy impact, with frequent delayed diagnosis
Cementless THA for Bony Ankylosis in AS
- Harris Hip Score improved from 49.5 to 82.6; reankylosis rate 0%
- Heterotopic ossification in 12 patients; anterior dislocation in 4.3%
- Survivorship 98.8% at 5 years and 85.8% at 8.5 years (revision endpoint)
ASAS Classification Criteria for Axial SpA
- Active sacroiliitis on MRI strongly associated with axial SpA (OR 45)
- Imaging-arm candidate criteria: sensitivity 97.1%, specificity 94.7%
- Knowledge of MRI changed classification in 21.1% of patients
Defining Active Sacroiliitis on MRI (ASAS/OMERACT)
- Bone marrow oedema/osteitis is the essential lesion for active sacroiliitis
- STIR/T2 fat-saturated sequences best demonstrate inflammation
- Structural lesions alone (sclerosis, erosion, fat) are insufficient for the active definition
ATLAS - Adalimumab (anti-TNF) in AS
- ASAS20 at week 12: 58.2% adalimumab vs 20.6% placebo (p under 0.001)
- ASAS40 and partial remission (22.1% vs 5.6%) significantly higher
- No significant excess of infections versus placebo over 24 weeks