Core Muscle Injury | Rectus–Adductor Aponeurosis | Groin Pain in Athletes
- Athletic pubalgia = core muscle injury at the rectus abdominis–adductor longus aponeurosis of the pubis
- True hernia is absent — the pathology is a tear or attenuation of the aponeurotic plate
- Must differentiate from osteitis pubis (inflammatory), FAI (hip intra-articular), and inguinal hernia
- MRI is the gold standard for imaging — look for rectus tear, adductor tendinopathy, and secondary cleft sign
- Conservative management (6-12 weeks physiotherapy) is first line; surgery reserved for refractory cases
- “Sports hernia = no true hernia on examination — it is a core muscle / aponeurotic injury
- “Pain is groin-based, exertional, improved with rest — differentiates from hip pathology
- “Resisted sit-up or adduction against resistance reproduces pain
- “MRI shows rectus abdominis tear or secondary cleft — do NOT diagnose on ultrasound alone
Overview and Epidemiology
Athletic pubalgia is one of the most common causes of chronic groin pain in athletes, and it is frequently misdiagnosed as a groin strain, osteitis pubis or hip pathology. Up to 30-50% of athletes with chronic groin pain have core muscle injury.
What it is. The term "sports hernia" is misleading, because there is no true hernia. The pathology is a tear or attenuation of the aponeurosis between the rectus abdominis and adductor longus at their pubic attachment. Accurate diagnosis requires MRI and a structured clinical assessment to differentiate it from intra-articular hip pathology, which demands a completely different treatment pathway.
What to call it. The Doha agreement went further than rejecting "sports hernia" alone: it retired "athletic pubalgia" as well, on the grounds that both labels assert a pathology that imaging and surgery frequently fail to confirm, and replaced them with the location the examination can actually establish, inguinal-related, pubic-related, adductor-related and iliopsoas-related groin pain, alongside hip-related and other causes. Quote the Doha entity in an exam and give the older label only as a gloss. Athletic groin pain develops the whole framework, including the iliopsoas- and hip-related entities.
Who. Incidence is 0.5-6% of athletes per year in kicking and cutting sports. Patients are overwhelmingly male, a ratio of approximately 10:1, with a peak at 20-35 years, the competitive sporting years. The sports are soccer, rugby, Australian rules football, ice hockey and tennis. 20-30% of cases are bilateral.
What it costs. The average time lost from sport is 6-12 weeks, and recurrence runs up to 20% without structured rehabilitation. The average delay to the correct diagnosis is 4-8 months. Professional athletes may require surgical intervention, and the cost in professional sport is significant because of the time away from play.
Pathophysiology
The pubic aponeurotic plate. The rectus abdominis and adductor longus share a common aponeurotic attachment on the anterior pubis. The rectus abdominis inserts on the pubic crest and symphysis, and the adductor longus originates from the inferior pubic ramus, so the two structures form a functional unit: the pubic aponeurotic plate.
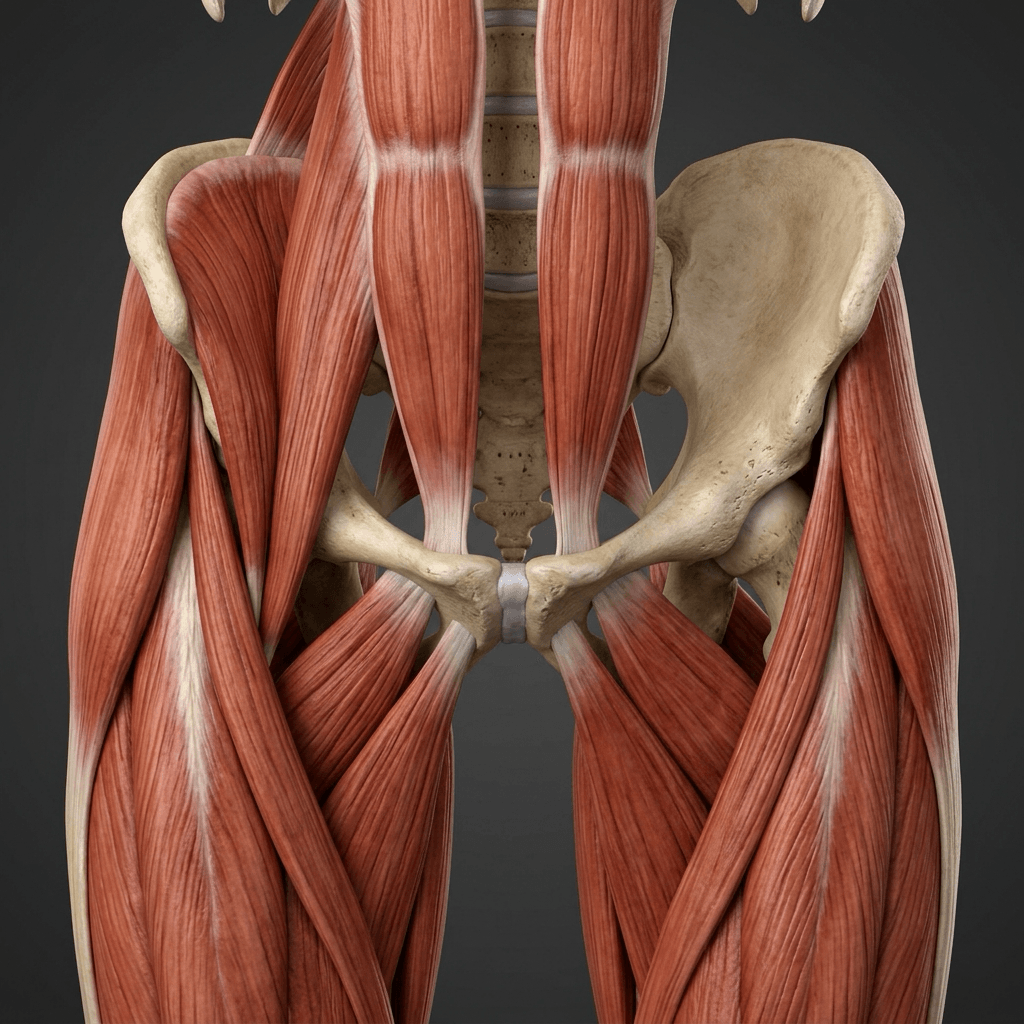
How it fails. Normally the rectus and adductor share a balanced load at the pubic aponeurosis. During twisting, kicking and cutting, opposing forces (the rectus pulling superiorly, the adductor pulling inferiorly) create shear stress at the aponeurosis, and repetitive loading from kicking, twisting and sprinting causes microtears, attenuation or frank disruption at the rectus insertion, the adductor origin, or both. The plate progressively loses integrity, and the result is pain with any activity that loads it: coughing, sit-ups, sprinting.
Why it is not a hernia. The posterior inguinal wall may be weakened, but no visceral structure protrudes. There is no true hernia.
- Attachment to Pubis
- Pubic crest and symphysis anteriorly
- Function
- Trunk flexion, intra-abdominal pressure
- When Injured
- Tear or attenuation at pubic attachment
- Attachment to Pubis
- Inferior pubic ramus origin
- Function
- Hip adduction, stabilisation in running
- When Injured
- Tendinopathy or partial avulsion
- Attachment to Pubis
- Pubic tubercle and pectineal line
- Function
- Posterior wall of inguinal canal
- When Injured
- Attenuation contributes to posterior wall weakness
- Attachment to Pubis
- Contributes to inguinal canal anterior wall
- Function
- Trunk rotation, abdominal wall integrity
- When Injured
- Thinning or tear near superficial ring
Why it mimics other conditions. The pubic symphysis, hip joint and inguinal canal are within centimetres of one another, and athletes often have multiplanar groin pain that is hard to localise. Obturator nerve irritation from adductor pathology refers pain to the medial thigh. FAI or labral pathology and athletic pubalgia can coexist (the proportion, and what it means for surgery, is under Clinical Assessment), and pubic bone marrow oedema can be present in both athletic pubalgia and osteitis pubis.
Classification and Types
There are two ways to classify the injury. By the structure injured, which guides surgical planning: isolated adductor pathology may respond to adductor release, while rectus tears may require direct repair or mesh reinforcement. And by the clinical pattern, which sharpens the differential: an acute adductor strain is sudden in onset and localised to the adductor longus, and osteitis pubis is bilateral, insidious and tender at the pubis.
- Structure Injured
- Inferior rectus at pubic attachment
- MRI Findings
- Rectus oedema or disruption, secondary cleft
- Prevalence
- Most common pattern
- Structure Injured
- Proximal adductor longus tendon
- MRI Findings
- Tendon thickening, peritendinous oedema
- Prevalence
- Very common, often coexists
- Structure Injured
- Both structures at pubic aponeurosis
- MRI Findings
- Bilateral or unilateral multi-structure changes
- Prevalence
- Common in chronic presentations
- Structure Injured
- Conjoint tendon or transversalis fascia
- MRI Findings
- Posterior wall bulge on dynamic ultrasound
- Prevalence
- Less common as isolated finding
Clinical Assessment
History. The mechanism is repetitive overload from twisting, cutting, sprinting and kicking. The pain is deep in the groin and low abdomen, with perineal radiation; it is activity-related, improves with rest and recurs on return to sport. It is typically unilateral, and bilateral pain suggests osteitis pubis. Coughing, sneezing, sit-ups and resisted adduction provoke it; increased intra-abdominal pressure reproduces the pain. Ask about previous treatment: failed courses of physiotherapy, NSAIDs or rest.
Examination. There is no visible swelling and no inguinal lump, which is what separates this from a true hernia. Tenderness sits over the pubic tubercle, the rectus insertion and the adductor origin. The provocation tests are in the table below; the order in which to run them is the protocol.
- Exclude a true hernia. Examine standing and coughing for an inguinal or femoral hernia. A palpable lump is referred to general surgery; it is not athletic pubalgia.
- Assess the adductors. Resisted adduction. Pain localised to the adductor longus origin suggests adductor tendinopathy.
- Assess the rectus abdominis. Resisted bilateral sit-up, and resisted unilateral hip flexion with trunk rotation. Pain at the pubic insertion suggests rectus involvement.
- Assess the hip joint. FADIR (flexion, adduction, internal rotation) for FAI, and FABER for sacroiliac or hip pathology. If positive, order hip-specific imaging.
- Assess the pubic symphysis. Direct palpation. Marked tenderness with bilateral symptoms suggests osteitis pubis.
- Technique
- Supine, resisted trunk flexion from partial sit-up
- Positive Finding
- Pain at pubic insertion of rectus abdominis
- Significance
- Suggests rectus abdominis involvement
- Technique
- Adduction against resistance at 0, 45, and 90 degrees of hip flexion
- Positive Finding
- Pain at adductor longus origin
- Significance
- Suggests adductor pathology
- Technique
- Cough while examiner palpates the inguinal canal
- Positive Finding
- Pain without palpable impulse (no hernia)
- Significance
- Supports posterior wall weakness
- Technique
- Hip flexed 90 degrees, adducted and internally rotated
- Positive Finding
- Deep anterior groin or hip pain
- Significance
- Suggests FAI or labral tear — investigate hip
The differential. Adductor longus strain is the most common athletic groin injury. The intra-articular hip causes are FAI, labral tear and early hip osteoarthritis. Nerve entrapment, obturator or genitofemoral, is the neuropathic cause and is taken separately below.
- Key Features
- Unilateral, exertional groin pain, no hernia
- Discriminating Finding
- Resisted sit-up reproduces pain, no palpable lump
- Imaging
- MRI: rectus tear, secondary cleft sign
- Key Features
- Bilateral pubic pain, insidious onset
- Discriminating Finding
- Direct symphysis tenderness, bilateral symptoms
- Imaging
- MRI: pubic bone marrow oedema, symphyseal sclerosis
- Key Features
- Deep groin pain, prolonged sitting or hip flexion
- Discriminating Finding
- Positive FADIR test, limited internal rotation
- Imaging
- MRI/CT: cam or pincer morphology, labral tear
- Key Features
- Acute onset, localised to adductor longus
- Discriminating Finding
- Sudden injury, tenderness along muscle belly
- Imaging
- MRI: muscle oedema, tear at musculotendinous junction
- Key Features
- Groin lump, cough impulse
- Discriminating Finding
- Palpable reducible mass
- Imaging
- Ultrasound: hernia sac with Valsalva
- Key Features
- Activity-related groin pain, night pain
- Discriminating Finding
- Weight-bearing pain, positive hop test
- Imaging
- MRI: fracture line, periosteal oedema
Up to 25% of athletes with athletic pubalgia have concurrent FAI. A positive FADIR test or limited internal rotation of the hip makes hip-specific imaging (MRI with a hip protocol) mandatory before any groin surgery, because operating on the pubic aponeurosis when the primary pain generator is the hip will fail. The two conditions can coexist and may require sequential treatment: address the intra-articular hip pathology first.
Nerve entrapment is a recognised, examinable cause of athletic groin pain, and it is missed if you think only of muscle, bone and joint.
- Obturator nerve entrapment: classically exercise-induced medial-thigh/groin pain with adductor weakness and medial-thigh paraesthesia that builds with exertion and eases with rest, caused by entrapment of the obturator nerve by a thickened fascia over the adductor brevis. It mimics adductor-related pain but has a neuropathic quality and a sensory component, and is confirmed with EMG/nerve studies; treatment is fascial release/neurolysis of the obturator nerve, not aponeurotic repair.
- Ilioinguinal and iliohypogastric nerve entrapment: neuropathic lower-abdominal/groin (and scrotal/labial) pain, often after prior hernia repair or lower-abdominal surgery (or from a thickened external oblique aponeurosis), with a positive response to a local-anaesthetic nerve block.
- Genitofemoral nerve: neuropathic groin/scrotal/anterior-thigh pain, again often post-surgical.
In the athlete with a neuropathic-quality, dermatomal or sensory groin pain, especially exertional medial-thigh pain with adductor weakness, or pain after previous groin surgery, think nerve entrapment: diagnosed with nerve blocks/EMG and treated by neurolysis, a completely different pathway from core-muscle-injury repair.
Investigations
MRI pelvis, athletic pubalgia protocol. The first-line study: coronal, sagittal and axial T1 and T2 fat-suppressed sequences through the pubic symphysis and hips. Look for a rectus abdominis tear or oedema at the pubic attachment, adductor longus tendinopathy or partial avulsion, the secondary cleft sign (a fluid cleft inferolateral to the symphysis indicating capsular disruption), and the pattern of pubic bone marrow oedema. MRI is the gold standard, with sensitivity reported at 85-95% for core muscle injury.
MRI hip, FAI protocol. Add it for a positive FADIR test, limited hip internal rotation or deep anterior groin pain. Look for cam or pincer morphology, labral tear, chondral damage and ligamentum teres pathology.
Dynamic ultrasound. An adjunct: a Valsalva manoeuvre during real-time scanning of the inguinal canal assesses posterior wall deficiency and a true inguinal hernia. It is operator-dependent and less sensitive than MRI for rectus or adductor pathology; it excludes a true hernia and does not replace MRI for the diagnosis.
CT pelvis. For the patient who cannot have an MRI (pacemaker, metalwork artefact). Soft-tissue detail is poor compared with MRI, so it is less useful for the aponeurosis; its role is to exclude bony pathology, a stress fracture or pubic symphysis sclerosis.
The secondary cleft sign, a curvilinear fluid signal extending inferolaterally from the pubic symphysis where the aponeurotic attachment has torn, is the most useful positive finding, seen in approximately 70-80% of athletes who come to surgery. That figure is a yield in operated patients, not a specificity, and the controlled data are sobering. A 4-year prospective study of 34 elite academy footballers found pubic bone marrow oedema, secondary cleft and capsule/tendon oedema frequently present in asymptomatic players, predicting neither injury nor later symptoms (PMID 24603080; prospective cohort, n=34, MRI scoring kappa 0.84-0.96). A controlled cross-sectional study found positive pelvic MRI findings in up to 71% of asymptomatic soccer players, whose odds of bone marrow oedema, adductor tendinopathy and degenerative change ran 6.3 to 13.3 times those of matched non-soccer athletes (PMID 25512059; n=28 symptomatic, 17 asymptomatic players, 20 controls).
The same study is the reason to grade the oedema rather than record its presence: higher grades of pubic bone marrow oedema separated symptomatic from asymptomatic players, while oedema itself did not, and it cannot separate athletic pubalgia from osteitis pubis in either direction. Treat an abnormal parasymphyseal MRI in a footballer as a description of the anatomy, not a diagnosis. It names the structure that is damaged; the examination, with a targeted diagnostic block where the two disagree, establishes which structure is generating the pain.
The groin packs several potential pain sources within centimetres, and athletic pubalgia, FAI, osteitis pubis and adductor pathology frequently coexist. When MRI shows multiple abnormalities, or symptoms and imaging do not match, image-guided diagnostic local-anaesthetic injections identify the dominant generator before you commit to surgery:
- Intra-articular hip injection: significant (greater than half) pain relief implicates the hip joint (FAI/labrum) as the primary source and predicts a good response to hip arthroscopy. Operate on the hip first.
- Pubic symphysis / secondary-cleft injection: relief localises pain to the pubic aponeurotic plate / symphysis (athletic pubalgia / osteitis pubis).
- Adductor enthesis injection: relief localises to adductor-related pathology.
Each injection should be ultrasound- or fluoroscopy-guided, with pre- and post-injection pain scores documented during a provocative manoeuvre. The principle is treat the source, not the scan: a positive hip injection in a patient with both cam morphology and a rectus tear tells you to address the hip first, and the recorded pain response is the practical safeguard against operating on the wrong source.
Management Algorithm
The decision. Structured rehabilitation comes first for every patient. Surgery is for the athlete who is still in pain after that programme with the injury confirmed on MRI and the hip excluded, and the bilateral, pubic-tender athlete whose plate is intact has osteitis pubis, which is not a surgical condition.
- Diagnosis
- MRI: rectus tear or secondary cleft sign
- Treatment
- Conservative rehab 6-12 weeks first
- Key Pearl
- Most resolve with structured physiotherapy
- Diagnosis
- MRI confirmed core muscle injury, no hip OA
- Treatment
- Surgical repair (laparoscopic mesh or open)
- Key Pearl
- Return to sport in 6-8 weeks post-surgery
- Diagnosis
- MRI: marked symphyseal oedema and sclerosis, aponeurotic plate intact
- Treatment
- Anti-inflammatories, activity modification, rehab
- Key Pearl
- Not a surgical condition — differentiate carefully
The goal is to restore lumbopelvic stability, adductor strength and sport-specific function through structured rehabilitation, and it is first line for all patients.
Rehabilitation Protocol
Control the pain with relative rest from provocative activities, NSAIDs and cryotherapy. Loading is protected: pain-free isometric adductor squeezes, with transversus abdominis and multifidus activation. Manual therapy covers hip joint mobilisation, adductor soft-tissue work and symphysis mobilisation if indicated. The goal is pain reduction and baseline activation of the core musculature.
Progress to isotonic adductor exercises (the Copenhagen adductor programme) and single-leg stability work, and integrate the core with dead bugs, bird dogs and the Pallof press against progressive resistance. Straight-line jogging starts if pain-free. The goal is pain-free activities of daily living and an adductor-to-abductor strength ratio approaching 80-90%.
Sport-specific loading: cutting, twisting and sprinting drills at progressive intensity, change of direction with figure-of-eight running and lateral shuffles, and a progressive kicking programme of distance and power for kicking-sport athletes. The goal is pain-free sport-specific movement at moderate intensity.
Return to full team training, initially non-contact, then to match play once full training is pain-free. The criteria are a pain-free bilateral adductor squeeze test, adductor strength greater than 90% of the contralateral side, and sport-specific functional tests passed. An ongoing adductor and core maintenance programme continues for prevention.
The Copenhagen adductor exercise programme has level 1 evidence for both prevention and treatment of groin problems in athletes: isometric and dynamic adductor exercises performed in a sideline position with progressive loading. Used as a prevention programme it reduces groin injuries by approximately 40%. It is the single most evidence-based intervention for athletic groin injuries.
Complications
- Incidence
- 5-15% of surgical cases
- Risk Factors
- Incorrect diagnosis, concurrent FAI, incomplete repair
- Management
- Reassess for missed hip pathology, repeat MRI, revision surgery rarely
- Incidence
- 15-30% without ongoing prevention
- Risk Factors
- Inadequate rehabilitation, premature return to sport
- Management
- Extended rehab programme, adductor prevention exercises
- Incidence
- Variable, often temporary
- Risk Factors
- Complete tenotomy, inadequate rehab
- Management
- Progressive adductor strengthening, most resolve by 6 months
- Incidence
- 1-3% (surgical cases)
- Risk Factors
- Open technique, obesity, diabetes
- Management
- Standard surgical wound management, antibiotics if indicated
- Incidence
- 2-5% of elite athletes
- Risk Factors
- Multiple failed treatments, incorrect diagnosis, psychological factors
- Management
- Multi-disciplinary pain management, psychological support, career counselling
The most common cause of "failed athletic pubalgia surgery" is that the diagnosis was wrong: the true pain generator was FAI, a labral tear, osteitis pubis or nerve entrapment. Always complete a thorough hip examination and MRI hip protocol before committing to pubic surgery. If any doubt exists about the primary pain source, consider diagnostic injections (hip joint versus pubic symphysis) to differentiate.
Outcomes and Prognosis
- Expected Outcome
- 70-90% resolution of symptoms
- Return to Sport
- 6-12 weeks with criteria-based progression
- Long-term Prognosis
- Excellent if compliance maintained and prevention continued
- Expected Outcome
- 85-95% return to competitive sport
- Return to Sport
- 6-8 weeks post-surgery
- Long-term Prognosis
- Good long-term outcomes with maintained core conditioning
- Expected Outcome
- Variable, depends on hip pathology severity
- Return to Sport
- 3-6 months (longer rehabilitation)
- Long-term Prognosis
- Dependent on hip joint preservation success
- Expected Outcome
- Persistent symptoms, psychological impact
- Return to Sport
- Delayed or absent
- Long-term Prognosis
- Guarded — requires multidisciplinary reassessment
The best prognosis belongs to the acute presentation with an accurate early diagnosis, compliant structured rehabilitation, no concurrent hip pathology and male sex. The prognosis is poor with chronic symptoms of greater than 6 months, multiple previous failed treatments, concurrent FAI or labral pathology, and bilateral symptoms suggesting osteitis pubis.
Guidelines, Registries & Global Practice
- Incidence: 0.5-6% of athletes per year in kicking and cutting sports
- Highest rates: Professional soccer (up to 10-18% career incidence), rugby, ice hockey
- Sex: Overwhelmingly male; female athletic pubalgia is under-recognised and may present differently
- Geographic variation: Higher reported rates in countries with strong football and rugby programmes (UK, Europe, Australia, Scandinavia)
- Economic impact: Significant in professional sport — average 6-12 weeks lost from training and competition
- High-resource: MRI-first diagnostic pathway, structured physiotherapy, surgical options (laparoscopic or open), multidisciplinary team
- Limited-resource: Clinical diagnosis with ultrasound, extended rehabilitation as sole treatment, limited surgical availability
- Universal principle: Structured active rehabilitation is the foundation regardless of resources — the Holmich protocol and Copenhagen programme require no equipment
- Prevention: The Copenhagen adduction programme is free, requires no equipment, and has the strongest evidence for groin injury prevention
- Diagnosis Emphasis
- Clinical examination categorised by anatomical entity; MRI for all persistent cases
- Conservative Treatment
- Minimum 6-12 weeks structured exercise programme before surgical consideration
- Surgical Indication
- Only after failed rehabilitation; multi-disciplinary assessment mandatory
- Diagnosis Emphasis
- MRI pelvis with athletic pubalgia protocol; exclude FAI with hip-specific MRI
- Conservative Treatment
- Physiotherapy-led rehabilitation; Copenhagen programme recommended
- Surgical Indication
- Laparoscopic or open repair in specialist centres
- Diagnosis Emphasis
- MRI pelvis and hip; dynamic ultrasound to exclude true hernia
- Conservative Treatment
- Progressive rehabilitation 6-12 weeks; consider injection therapy
- Surgical Indication
- Open or laparoscopic repair; adductor release if concurrent tendinopathy
- Diagnosis Emphasis
- Assess for bony involvement (pubic ramus stress fracture); MRI essential
- Conservative Treatment
- Rehabilitation first; address biomechanical and training load factors
- Surgical Indication
- Surgical repair principles similar across approaches; expertise matters more than technique
There is no dedicated arthroplasty or implant registry relevant to athletic pubalgia, as the condition involves soft tissue repair without implants. The evidence base is dominated by large case series (Meyers) and a small number of RCTs (Holmich, Haroy). The Doha Agreement (2014) provides the most widely accepted consensus terminology and classification framework, categorising groin pain by anatomical entity: adductor-related, iliopsoas-related, inguinal-related, pubic-related, and hip-related. Athletic pubalgia falls primarily within the inguinal-related and pubic-related categories.
Record in every athlete with groin pain:
- Duration and nature of symptoms (acute vs insidious, unilateral vs bilateral)
- Hernia examination performed (standing, coughing) and result
- Hip examination (FADIR test, internal rotation range) and result
- MRI pelvis findings (rectus tear, secondary cleft, adductor pathology, bone marrow oedema pattern)
- Hip MRI if FADIR positive
- Rehabilitation programme details (duration, compliance, exercises used)
- FADIR test result before any surgical decision
Missed FAI leading to failed athletic pubalgia surgery is a recurring source of poor outcomes and medicolegal claims worldwide.
Controversies & Areas of Uncertainty
No high-quality RCTs directly compare surgical repair with continued conservative management beyond 12 weeks. Surgical evidence comes from large case series with inherent selection bias. The threshold for surgery varies between centres, with some advocating earlier intervention in elite athletes and others insisting on a minimum 6-month rehabilitation trial.
Both techniques report 85-95% return-to-sport rates, but no head-to-head RCTs exist. Laparoscopic repair is preferred by general surgeons (mesh reinforcement of posterior wall), while open repair is preferred by some sports hernia specialists (direct aponeurotic reinforcement). Choice is currently driven by surgeon expertise rather than evidence.
Partial adductor longus release is increasingly favoured over complete tenotomy to minimise post-operative adductor weakness. However, no comparative trials exist, and the long-term functional impact of complete tenotomy in elite athletes remains debated.
The terms "sports hernia," "athletic pubalgia," "core muscle injury," and "inguinal disruption" are used interchangeably, creating confusion. The Doha Agreement (2014) attempted to standardise terminology, but adoption is inconsistent. "Core muscle injury" is increasingly preferred as it accurately describes the pathology without implying a hernia.
MCQ Practice Points
Q: What is athletic pubalgia? A: A core muscle injury involving disruption of the rectus abdominis–adductor longus aponeurotic plate at the pubic symphysis. It is NOT a true hernia — no visceral structure protrudes and no palpable inguinal mass is present. The pathology is a tear or attenuation of the aponeurosis due to repetitive shear forces from twisting and kicking.
Q: What is the gold standard imaging for athletic pubalgia? A: MRI of the pelvis with an athletic pubalgia protocol. Key findings include: rectus abdominis tear or oedema at the pubic attachment, adductor longus tendinopathy or partial avulsion, and the secondary cleft sign (fluid cleft extending inferolaterally from the symphysis). Dynamic ultrasound can exclude true hernia but is less sensitive for core muscle injury.
Q: How do you differentiate athletic pubalgia from osteitis pubis? A: Athletic pubalgia is typically unilateral, with pain reproduced by resisted sit-up or adduction, and MRI shows a rectus tear or secondary cleft sign. Osteitis pubis is typically bilateral, with direct symphysis tenderness, and MRI shows marked pubic bone marrow oedema and symphyseal sclerosis. Osteitis pubis is managed with rest and anti-inflammatories — it is NOT a surgical condition.
Q: What is the first-line treatment for athletic pubalgia? A: Structured physiotherapy for 6-12 weeks comprising: pain control, lumbopelvic stabilisation (transversus abdominis and multifidus), progressive adductor strengthening (Copenhagen adduction programme), and sport-specific functional rehabilitation. The Copenhagen programme has level 1 evidence for treatment and prevention of groin injuries. Surgery is reserved for patients who fail conservative management.
Q: When is surgery indicated for athletic pubalgia? A: Surgery is indicated after failure of a minimum 6-12 weeks of structured, supervised rehabilitation in a compliant athlete with MRI-confirmed core muscle injury and excluded hip pathology. Options include laparoscopic mesh repair, open repair, or combined repair with adductor release. Return-to-sport rates are 85-95% in experienced centres. The number one cause of surgical failure is incorrect diagnosis (missed FAI).
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 24-year-old professional soccer player presents with 8 weeks of progressive left-sided groin pain, worse during kicking and sprinting. He has no palpable inguinal hernia. Resisted sit-ups reproduce his pain. X-rays of the pelvis are normal. What is your diagnosis, investigation, and management plan?”
“A 28-year-old elite rugby player has completed 14 weeks of supervised rehabilitation for MRI-confirmed athletic pubalgia (rectus abdominis tear with secondary cleft sign). He continues to have activity-limiting groin pain. His FADIR test is negative and hip MRI shows no FAI. He is desperate to return to competitive rugby. What are your surgical options and how do you counsel him?”
Key Concept
- Athletic pubalgia = core muscle injury (NOT a true hernia)
- Tear or attenuation of rectus abdominis–adductor longus aponeurosis at pubis
- Repetitive shear forces from twisting, kicking, sprinting in athletes
- Male predominance (10:1), peak age 20-35, kicking and cutting sports
Diagnosis
- MRI pelvis is gold standard — look for rectus tear, secondary cleft sign, adductor tendinopathy
- No palpable inguinal hernia on examination
- Resisted sit-up reproduces pain (rectus involvement)
- Must exclude FAI with FADIR test and hip MRI if positive
Differential Diagnosis
- Osteitis pubis: bilateral, symphysis tenderness, bone marrow oedema — NOT surgical
- FAI: positive FADIR, limited internal rotation, hip MRI changes
- True inguinal hernia: palpable lump on examination
- Adductor strain: acute onset, musculotendinous junction tenderness
Management
- First line: structured rehabilitation 6-12 weeks (Copenhagen programme plus core stabilisation)
- Surgery for refractory cases: laparoscopic mesh or open repair, 85-95% return to sport
- Address concurrent hip pathology BEFORE pubic surgery
- Post-surgical rehabilitation: 6-8 weeks progressive return to sport
Key Exam Traps
- Number one cause of failed surgery = missed FAI
- Secondary cleft is the most useful positive sign — but it occurs in asymptomatic athletes, so correlate with examination
- Osteitis pubis is managed conservatively — never operate for this
- Up to 25% of athletes have both FAI and athletic pubalgia concurrently
Evidence Base and Key Trials
Management of severe lower abdominal or inguinal pain in high-performance athletes. PAIN (Performing Athletes with Abdominal or Inguinal Neuromuscular Pain Study Group)
- Landmark case series establishing the concept of athletic pubalgia as a distinct clinical entity in high-performance athletes
- Identified the rectus abdominis–adductor longus aponeurotic plate as the primary site of injury
- Surgical repair of the identified defect allowed the majority of athletes to return to competitive sport
- Emphasised that the condition is commonly misdiagnosed as a groin strain, hip pathology, or true hernia
Effectiveness of active physical training as treatment for long-standing adductor-related groin pain in athletes: randomised trial
- Randomised controlled trial comparing active training programme (physiotherapy) with passive treatments (massage, stretching, laser)
- Active training group: 79% returned to sport without pain versus 14% in passive treatment group
- The active programme focused on progressive adductor and core strengthening with lumbopelvic stabilisation
- Established structured rehabilitation as first-line treatment for adductor-related groin pain
The Adductor Strengthening Programme prevents groin problems among male football players: a cluster-randomised controlled trial
- Cluster-randomised trial of the Copenhagen adduction exercise programme in professional footballers
- Reduction in groin injury incidence by approximately 40% compared to control
- The programme includes isometric, concentric, and eccentric adductor exercises in a sideline position
- Compliance with greater than 2 sessions per week was associated with the greatest risk reduction
Clinical presentation of femoroacetabular impingement
- Review highlighting that FAI is a frequent cause of groin pain in athletes and often coexists with athletic pubalgia
- Up to 25% of athletes with athletic pubalgia have concurrent FAI
- FADIR test is the most sensitive clinical test for intra-articular hip pathology
- Hip arthroscopy addresses cam and pincer lesions with favourable outcomes in athletes
Athletic groin pain: a systematic review and meta-analysis of surgical versus physical therapy rehabilitation outcomes
- Systematic review and meta-analysis comparing surgical versus physical therapy rehabilitation outcomes for athletic groin pain
- Both surgical and exercise-based rehabilitation showed favourable return-to-sport outcomes
- Physical therapy rehabilitation showed success rates of 70-90% across included studies
- No high-quality RCTs directly comparing surgical versus conservative management exist