Patient Blood Management
- Deformity correction, multilevel fusion and revision bleed most, and spine has the highest transfusion rate of the major orthopaedic procedures (around 15%).
- No single measure suffices: patient blood management is a multimodal, multidisciplinary bundle across all three phases.
- Preoperatively, a low haemoglobin is the strongest independent predictor of transfusion, so find and treat anaemia first.
- Intraoperatively, tranexamic acid is the cornerstone, and prone positioning with a free abdomen decompresses the epidural venous plexus.
- Postoperatively, transfuse restrictively, and target the fullest bundle at the patients at highest risk.
- “Spine (deformity/revision) surgery = high blood loss + the highest transfusion rate in ortho (~15%); epidural venous plexus + cancellous bleeding.
- “Tranexamic acid is the cornerstone agent (reduces bleeding/cell-saver volume/op time; higher weight-based dose more effective in adolescent deformity); absence of TXA predicts transfusion.
- “Multimodal PBM: preop anaemia/iron optimisation; intraop TXA + free-abdomen prone positioning + hypotensive anaesthesia + cell salvage + staging; postop restrictive transfusion.
Overview: Why Spine Bleeds & the Multimodal Bundle
Scope note. This page is the spine-specific layer of patient blood management — the epidural venous plexus, the free-abdomen positioning, the hypotension-versus-cord-perfusion tension, and perioperative visual loss. The general three-pillar PBM framework, the transfusion thresholds and the Jehovah's Witness approach are set out in blood management strategies.
Why spine bleeds. Spine surgery, especially deformity correction, multilevel fusion and revision, loses a great deal of blood. The exposures are large, decorticated and osteotomised cancellous bone bleeds, the operations are long, and the epidural venous plexus lies in the field. It has the highest transfusion rate of the major orthopaedic procedures, reported at around 15% against a few percent for hip and knee arthroplasty.
The answer is a bundle. No single measure suffices, so the modern approach is patient blood management (PBM): a multimodal, multidisciplinary bundle applied before, during and after the operation. The aim is to minimise both the blood lost and the need for allogeneic transfusion, with its risks.
- Measures
- Identify/treat anaemia (iron +/- ESA); manage antiplatelet/anticoagulant; autologous planning
- Goal
- Raise the starting haemoglobin; reduce transfusion need
- Measures
- Tranexamic acid (antifibrinolytic; higher weight-based dose in adolescent deformity)
- Goal
- Reduce bleeding, cell-saver volume, operative time
- Measures
- Free-abdomen prone positioning; hypotensive anaesthesia; meticulous haemostasis; cell salvage; staging
- Goal
- Reduce venous engorgement and surgical blood loss; recycle red cells
- Measures
- Restrictive transfusion thresholds; continue iron; monitor
- Goal
- Limit allogeneic transfusion and its risks
Pathophysiology: Why Freeing the Abdomen Works - The Batson Plexus
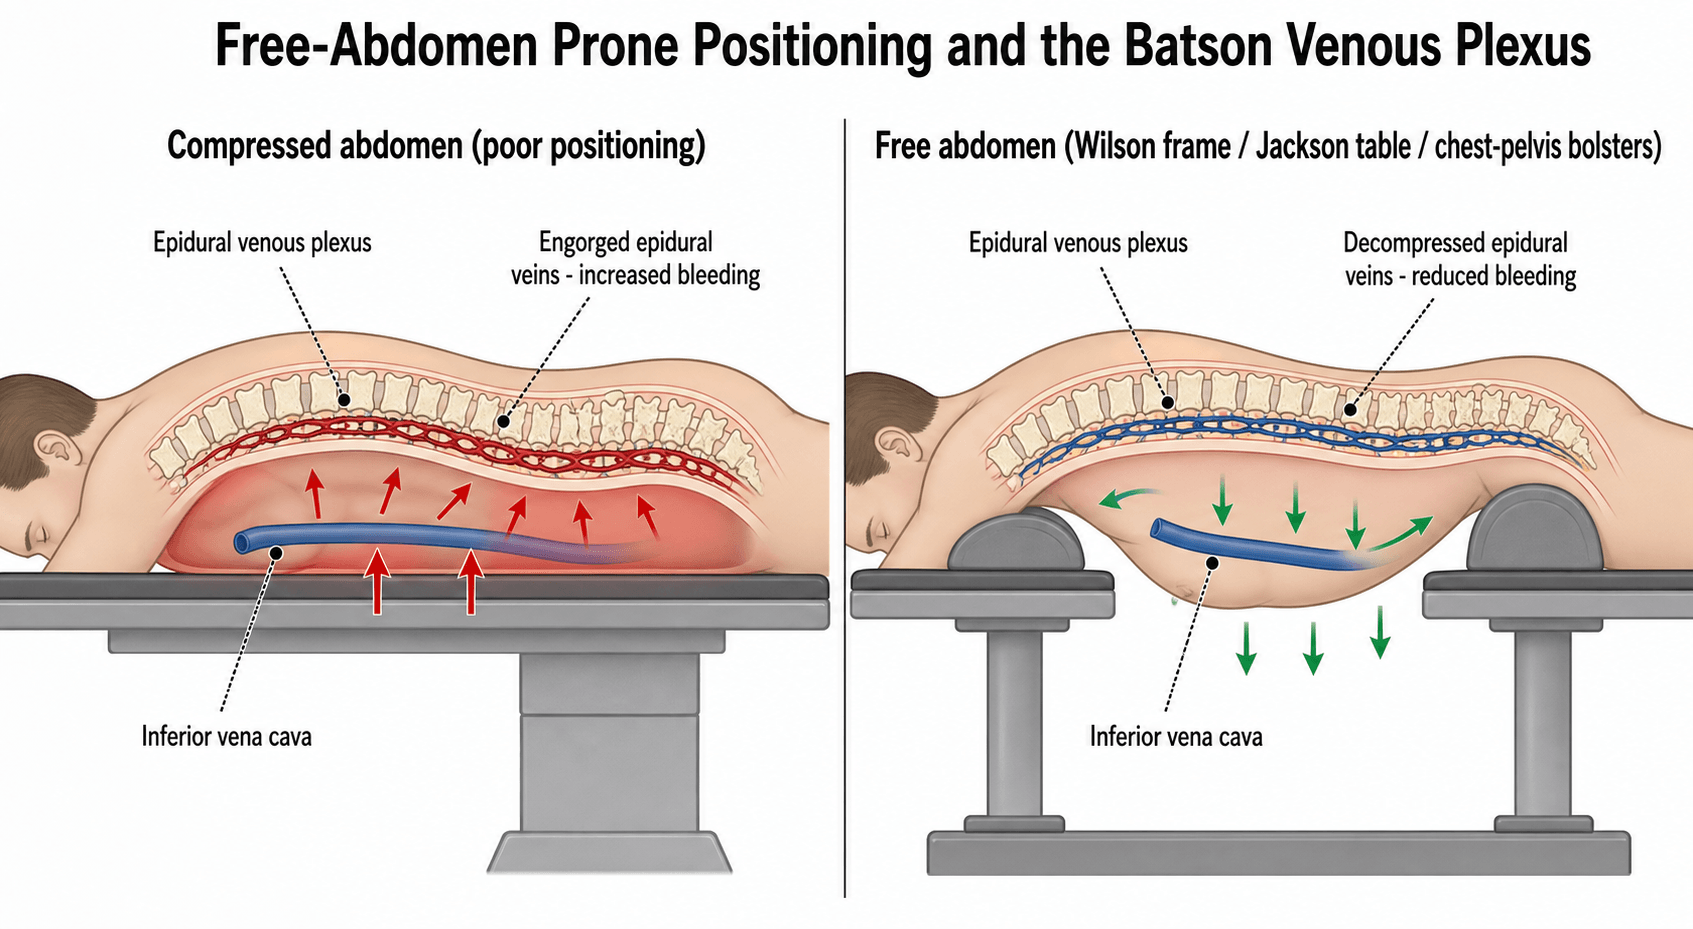
The anatomy. The internal vertebral (epidural) venous plexus is part of the vertebral venous plexus of Batson, a valveless network in the epidural space. It communicates freely with the inferior vena cava, azygos and pelvic venous systems, so pressure passes in both directions with no valves to buffer it.
How a compressed abdomen bleeds. Prone on a compressed abdomen, intra-abdominal and IVC pressure rise. Because the plexus is valveless and connected to the cava, that pressure is transmitted straight into the epidural veins, which engorge and bleed briskly in the surgical field and divert venous return through the plexus.
The fix. Position prone on a Wilson frame, a Jackson or open-frame table, chest rolls, or chest-and-pelvis bolsters, so that the abdomen hangs free. This drops IVC and intra-abdominal pressure, decompresses the epidural plexus and reduces bleeding, and lowers airway pressures too. It is one of the simplest, highest-yield technical measures.
The Wilson frame tension. The frame that frees the abdomen so well is also an independent risk factor for ischaemic optic neuropathy in the case-control data (see the visual-loss section below). The two facts do not conflict: the frame is likely implicated largely through the head-down attitude it is often used in, which raises venous pressure in the head. The resolution is to keep the abdomen free and the head neutral, at or above the level of the heart, rather than to abandon the frame.
The metastatic highway. The same valveless plexus is the route by which pelvic and abdominal tumour and infection spread haematogenously to the spine. The anatomy that drives the bleeding also carries the metastases.
Management: Tranexamic Acid & Positioning
Anaemia first. A low preoperative haemoglobin is the strongest independent predictor of transfusion, which makes anaemia the key modifiable factor. Elective major spine surgery should not proceed until iron-deficiency anaemia has been looked for and treated, with oral or intravenous iron and, in selected cases, an erythropoiesis-stimulating agent. Antiplatelet and anticoagulant agents are managed appropriately.
Tranexamic acid. An antifibrinolytic, and the cornerstone pharmacological measure. It significantly reduces intraoperative bleeding, cell-saver volume and operative time, and is not associated with a clear increase in complications. In adolescent deformity surgery, higher weight-based dosing is more effective. The absence of TXA is itself an independent predictor of transfusion.
A free abdomen. Prone positioning with the abdomen hanging free is a simple, powerful technical measure: it lowers intra-abdominal and caval pressure and reduces epidural venous engorgement and bleeding. The anatomy that makes it work, and the frames that achieve it, are set out in the Batson plexus section below.
The supporting measures. These are added to the three above:
- Controlled hypotensive anaesthesia, kept within safe limits for cord perfusion (see the next section)
- Meticulous haemostasis: bipolar, bone wax and topical haemostatic agents
- Intra-operative cell salvage for high-volume cases
- Staging very large reconstructions
After surgery. Transfuse restrictively, for symptomatic anaemia or at a lower haemoglobin threshold rather than liberally, and continue iron with monitoring. The bundle as a whole reduces exposure to transfusion and its risks.
Who needs it most. A low preoperative haemoglobin, a high-risk procedure, ASA III-IV, no tranexamic acid and older age all raise the risk of transfusion. Target the bundle at the patients who carry them.
Three measures carry most of the benefit and should not be omitted: optimising preoperative anaemia, giving tranexamic acid, and positioning prone with a free abdomen. Combine them with cell salvage, controlled hypotension and a restrictive postoperative threshold, and risk-stratify so the most vulnerable patients receive the fullest bundle.
Hypotension vs Cord Perfusion: The Spine-Specific Tension
Why hypotension helps. Lowering the mean arterial pressure (MAP) reduces capillary and venous oozing and gives a drier field, which is why controlled hypotension is a recognised blood-loss measure. The general technique is covered in our General Anaesthesia topic.
Why it is dangerous in spine. Spinal cord perfusion pressure = MAP minus the local CSF/venous pressure, so a low MAP directly reduces cord perfusion. During deformity correction the cord is stressed at the same time by distraction and correction, and profound hypotension then risks cord ischaemia and iatrogenic spinal cord injury. The cord's blood supply is detailed in our Spinal Cord Blood Supply topic.
The compromise. Intra-operative neuromonitoring guides the pressure (see our Spinal Cord Monitoring topic):
- Use only mild or moderate hypotension, if any, and only during exposure
- Avoid profound hypotension
- Maintain or actively raise the MAP, for example toward around 80 mmHg or higher, during and after the correction manoeuvre
- Do the same whenever SSEP/MEP signals deteriorate
- Patients with poor cord vascular reserve should not be run hypotensive
Cord protection beats blood conservation. Hypotension is the measure you abandon first when the cord is at risk.
Complications: Perioperative Visual Loss - The Complication That Justifies the Whole Bundle
The reason blood loss in prone spine surgery is treated so seriously is perioperative visual loss (POVL), not transfusion cost. POVL is a rare but devastating and usually irreversible complication, and it sits at the intersection of blood loss, prone positioning and hypotension.
Mechanism. Usually ischaemic optic neuropathy (ION) rather than a corneal or retinal problem. Posterior ION, infarction of the retrobulbar optic nerve, which has no collateral supply, is the pattern classically reported after prolonged prone spinal fusion. Central retinal artery occlusion from direct globe pressure is a separate, positioning-specific mechanism, and it is the one that is genuinely preventable by checking that the eyes are free.
Risk factors. The largest case-control work, the ASA Postoperative Visual Loss Study Group analysis of 80 ION cases against 315 controls (Anesthesiology 2012), identified:
- Male sex
- Obesity
- Use of the Wilson frame
- Longer operative time
- Greater blood loss
- A lower colloid-to-crystalloid ratio in non-blood fluid replacement
Patient factors compound them: pre-operative anaemia, intra-operative hypotension, diabetes, hypertension and a small cup-to-disc ratio.
Recognition. Painless visual loss, often noticed on waking, with an afferent pupillary defect. The fundus may look normal in posterior ION, so a normal fundoscopy does not exclude it. Urgent ophthalmology involvement is mandatory, but no treatment is reliably effective, which is why the emphasis falls on prevention.
Prevention. It is the same bundle:
- Keep the operation short and the blood loss down
- Avoid prolonged deliberate hypotension
- Correct anaemia beforehand
- Use colloid as well as crystalloid in replacement
- Stage very long deformity procedures where feasible
- Position with the head neutral and at or above the level of the heart, and the globes demonstrably free of pressure
Consent. In prolonged prone deformity surgery with anticipated major blood loss, visual loss is a recognised risk that should be discussed pre-operatively rather than explained afterwards.
Coagulopathy in the Long Construct
Major deformity surgery loses blood over hours rather than in a single event, and the bleeding changes character as it goes on.
Dilutional coagulopathy. Red cells and crystalloid replace whole blood without replacing clotting factors or platelets. The field stops producing discrete bleeding points and starts oozing diffusely from raw cancellous bone and muscle. Recognise that change as a laboratory event, not a technical one, because more diathermy will not fix it.
Fibrinogen falls first. It is the earliest factor to reach a critical level in dilutional coagulopathy, and the one most often overlooked while attention is on platelets and INR.
Hypothermia and acidosis compound it, both by impairing enzyme function, which is why active warming is a haemostatic measure and not merely a comfort one.
Monitor rather than guess. Serial full blood count, coagulation screen and fibrinogen, with viscoelastic testing (TEG/ROTEM) where available, allow targeted replacement instead of formulaic ratios.
Anticipate it. Expect it in the highest-loss operations: three-column osteotomies (pedicle subtraction osteotomy, vertebral column resection), long multilevel constructs, revision surgery through scar, and tumour resection. Plan cross-matching, cell salvage and blood-product availability before starting rather than during the bleed. The osteotomies themselves are developed in our Three-Column Osteotomies topic.
Mnemonics & Memory Aids
BLOOD
Hook:BLOOD: Bundle (PBM), Low Hb optimise, Offer TXA, Open (free) abdomen prone, Diminish need (cell salvage/hypotension/restrictive).
MAPHypotension vs Cord Perfusion
Hook:MAP: cord perfusion is MAP minus CSF pressure - Avoid deep hypotension, Pump it up when the cord is stressed.
VISIONPOVL (Ischaemic Optic Neuropathy) Risk Factors
Hook:POVL steals VISION: Wilson frame, Increased duration, Sex male, Increased blood loss, Obesity, No colloid (ASA POVL Study Group 2012).
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“How would you minimise blood loss and transfusion in a major deformity spine operation?”
“What is tranexamic acid and what is the evidence in spine surgery?”
Why spine bleeds
- Large exposures, cancellous bone bleeding, long operative times, epidural venous plexus
- Highest transfusion rate in ortho (~15%; vs ~3-4% hip/knee)
- Deformity, multilevel and revision surgery the highest risk
Preoperative
- Identify/treat anaemia (iron +/- ESA) - low Hb is the strongest predictor
- Manage antiplatelet/anticoagulant agents
- Risk-stratify (Hb, procedure, ASA, age)
Intraoperative
- Tranexamic acid (cornerstone; higher weight-based dose in adolescent deformity)
- Free-abdomen prone positioning (reduce epidural venous engorgement)
- Hypotensive anaesthesia (safe for cord), haemostasis, cell salvage, staging
Postoperative
- Restrictive transfusion threshold (symptomatic/low Hb)
- Continue iron; monitor
- Patient blood management reduces transfusion exposure and risk
Evidence & Key Studies
Optimal tranexamic acid dosing for adolescent idiopathic scoliosis surgery (network meta-analysis)
- Tranexamic acid is an antifibrinolytic widely used in spine surgery; in AIS instrumentation, higher weight-based dosing (a 100 mg/kg bolus plus 10 mg/kg/hr infusion) was most effective at reducing intraoperative bleeding, operative time and cell-saver volume.
- Lower doses also helped but less so; there was no difference in complication rates between doses (though not uniformly reported).
- TXA dosing meaningfully affects blood loss in adolescent deformity surgery (network meta-analysis of 1,523 patients across 16 studies).
The role and dosing of tranexamic acid in adolescent deformity surgery (higher weight-based dosing most effective, without a clear increase in complications) come from the cited Lajczak network meta-analysis; the highest-in-orthopaedics spine transfusion rate (about 15%) and the independent transfusion predictors (low preoperative haemoglobin, high-risk procedure, ASA III-IV, absence of TXA, older age) from the cited Ortiz-Gomez cohort. The broader patient-blood-management bundle - preoperative anaemia/iron optimisation, free-abdomen prone positioning to reduce epidural venous engorgement, hypotensive anaesthesia, cell salvage, staging and restrictive postoperative transfusion - is standard, well-established teaching. (See also our Adolescent Idiopathic Scoliosis and Adult Spinal Deformity topics.)