SOX9 Bowing Dysplasia
- CAMPOMELIC (camptomelic) DYSPLASIA is a rare, frequently LETHAL skeletal dysplasia caused by mutation or disruption of SOX9 (autosomal dominant, usually arising de novo); it is one of the recognised skeletal dysplasias of the fetus/infant, and the name means 'bent limb'.
- The SKELETAL HALLMARK is congenital BOWING (camptomelia) of the long bones - characteristically ANTERIOR bowing of the TIBIA (and the femur), often with a SKIN DIMPLE overlying the apex of the bow - together with hypoplastic scapulae, a reduced number of rib pairs, scoliosis, clubfeet and a small/narrow thorax.
- The principal cause of the HIGH MORTALITY is RESPIRATORY COMPROMISE: the small thorax and, importantly, LARYNGOTRACHEOMALACIA (softening of the airway cartilage from the SOX9 chondrogenesis defect) cause airway collapse and restrictive/obstructive respiratory failure, often fatal in the neonatal period - though some milder/longer-surviving cases exist.
- A characteristic NON-skeletal feature is SEX REVERSAL: SOX9 is essential for testis determination, so a large proportion of karyotypically XY (46,XY) individuals have FEMALE or ambiguous external genitalia (XY sex reversal) - a key clue linking the skeletal phenotype to the SOX9 gene.
- OTHER associated anomalies include cleft palate, Pierre Robin sequence (micrognathia/glossoptosis), and cardiac/renal anomalies; the diagnosis is by the clinical/radiographic phenotype (bowed long bones, hypoplastic scapulae) with SOX9 genetic confirmation and karyotype.
- MANAGEMENT is largely SUPPORTIVE/PALLIATIVE given the high mortality from respiratory failure: neonatal RESPIRATORY support (airway management for laryngotracheomalacia), and for survivors, ORTHOPAEDIC management of the limb bowing, scoliosis and foot deformity, plus management of the sex-reversal/endocrine and other anomalies - within a multidisciplinary team with genetic counselling.
- “Camptomelic dysplasia = rare, often LETHAL SOX9 skeletal dysplasia (usually de novo). Hallmark = congenital BOWING (camptomelia) of long bones - ANTERIOR tibial bow + skin DIMPLE at the apex.
- “High mortality from RESPIRATORY compromise: small thorax + LARYNGOTRACHEOMALACIA (airway cartilage softening).
- “SOX9 = testis determination → XY SEX REVERSAL (46,XY females/ambiguous genitalia). Also hypoplastic scapulae, scoliosis, clubfeet, cleft palate/Pierre Robin. Management largely supportive/palliative; orthopaedic care for survivors.
Overview & Epidemiology
Campomelic (camptomelic) dysplasia is a rare, often lethal skeletal dysplasia caused by heterozygous loss of SOX9 function. The name means bent-limbed (Greek campto, bent, and melia, limb), after the congenital bowing of the long bones that is its skeletal hallmark.
Frequency. It is one of the rarest of the named skeletal dysplasias, and no dependable population incidence figure exists in the retrievable literature. Describe it to an examiner as rare and historically lethal rather than attaching a number to it: that answer is honest and cannot be faulted, and a fabricated "1 in X" can.
Inheritance. The condition is autosomal dominant and usually arises de novo. Most patients are sporadic, so the parents are typically unaffected and the recurrence risk is low, but not zero, because germline mosaicism is documented (see genetic counselling under Management).
Ascertainment is bimodal. The severe end is identified antenatally, with bowed long bones and a small thorax on ultrasound, or in the delivery room with respiratory failure. The milder end, including the acampomelic variant, surfaces later, sometimes only when a straight-limbed child with scoliosis and hypoplastic scapulae is sequenced.
Where it sits among the lethal dysplasias. Thanatophoric dysplasia and osteogenesis imperfecta type II together account for roughly half of the fetal and neonatal cases coming to perinatal autopsy in the Jezova series. Campomelic dysplasia is distinctly less common and sits in the next tier, alongside achondrogenesis type 2, short-rib dysplasias and chondrodysplasia punctata.
Pathophysiology: The SOX9 Gene, Locus and Mechanism
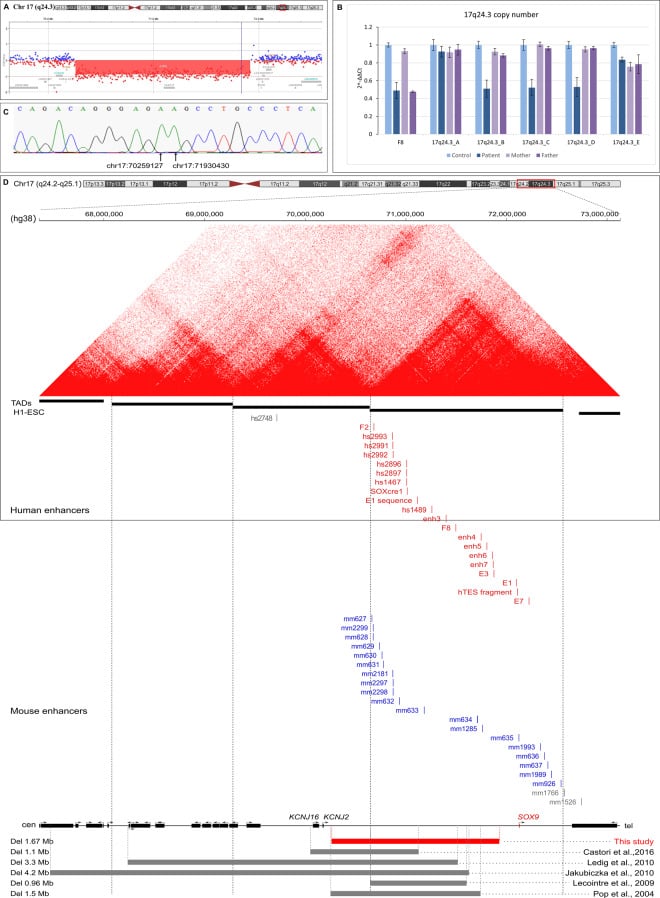
The gene. SOX9, an SRY-box transcription factor on chromosome 17q24.3, is a master regulator of two processes, and between them they explain the whole phenotype. Its role in chondrogenesis, the development of the skeleton and the airway, accounts for the bowing, the small thorax and the laryngotracheomalacia. Its role in testis determination accounts for the XY sex reversal.
Two routes to loss of function. Campomelic dysplasia results from heterozygous loss of SOX9 function by either of two molecular mechanisms:
- Intragenic mutations. Point or truncating mutations within the SOX9 coding region account for the majority of cases, usually arising de novo.
- Upstream chromosomal rearrangements. Translocations, inversions or deletions in the large regulatory region up to about 1 Mb upstream separate SOX9 from its distant tissue-specific enhancers, a position effect or cis-regulatory disruption. These extragenic rearrangements are more often associated with the milder or acampomelic (straight-bone) phenotypes.
Clinical Features
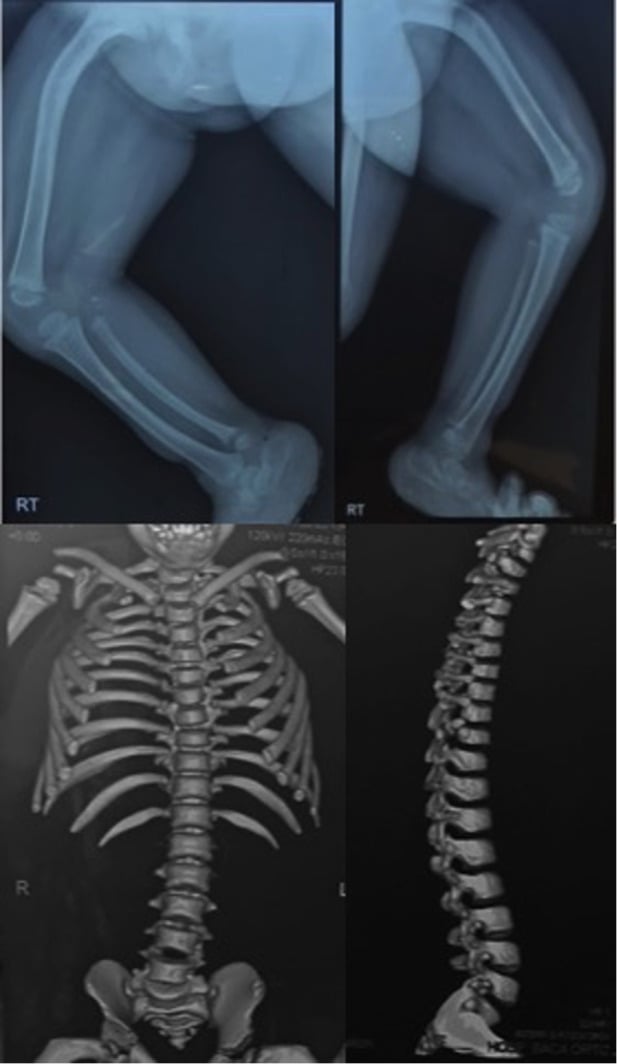
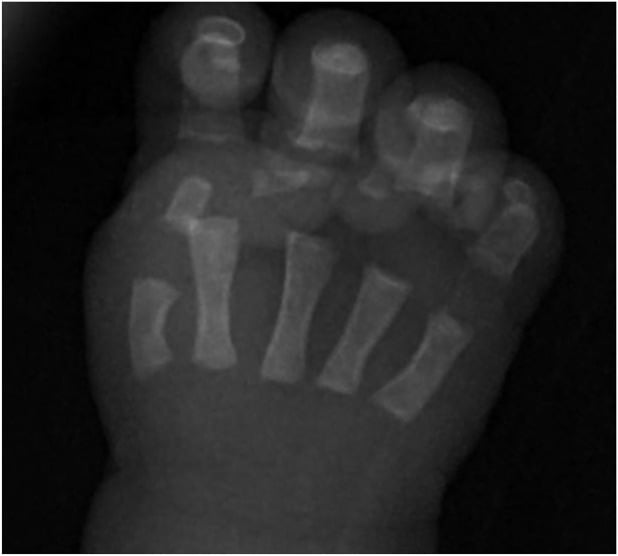
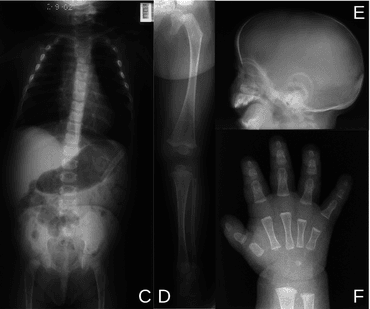
The skeletal hallmark. Congenital bowing of the long bones (camptomelia) is characteristically anterior bowing of the tibia, and of the femur, often with a skin dimple over the apex of the bow. With it come hypoplastic scapulae, 11 pairs of ribs, scoliosis, clubfeet and a small, narrow thorax. The anterior tibial bow with its dimple, together with hypoplastic scapulae, points to the diagnosis.
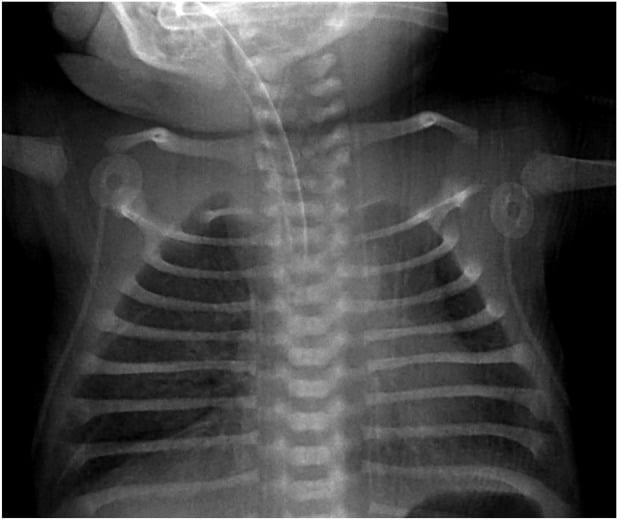
The airway and the thorax. The high mortality is driven by respiratory compromise. The small thorax and laryngotracheomalacia, a softening of the airway cartilage that follows directly from the SOX9 chondrogenesis defect, together cause airway collapse and restrictive and obstructive respiratory failure. It is frequently fatal in the neonatal period, though some milder, longer-surviving cases exist.
Obstruction at several levels. Calling the airway problem laryngotracheomalacia suggests a single lesion to bypass. In practice many patients have airway obstruction at several levels at once: the cartilage defect affects the larynx and trachea together, and the micrognathia and glossoptosis of an associated Pierre Robin sequence add obstruction above them.
Sex reversal. The condition affects both sexes, but because SOX9 is essential for testis determination, a large proportion of karyotypically 46,XY individuals have female or ambiguous external genitalia. It may therefore present as a phenotypic girl with a bowing dysplasia, and the apparent sex may not match the karyotype, which matters for diagnosis and for family counselling. The karyotype is part of the diagnosis, not an afterthought, and the discordance is the clue that links the skeletal phenotype to the SOX9 gene.
Other anomalies. Cleft palate, Pierre Robin sequence, and cardiac and renal anomalies accompany the condition.
The name is misleading in a minority of cases. An acampomelic (straight-bone) variant is well described, in which the femur, tibia and fibula are not bowed and the diagnosis rests on the rest of the phenotype: hypoplastic scapulae, 11 pairs of ribs, scoliosis with undermineralised thoracic pedicles, short ischia, delayed femoral epiphyseal ossification and a cranial vault large relative to the face. Absence of bowing therefore does not exclude the diagnosis, and a neonate with hypoplastic scapulae and a small thorax deserves SOX9 testing even with straight long bones.
Investigations & Prenatal Diagnosis
The most severe and lethal skeletal dysplasias are identifiable before birth, and an increasing proportion are confirmed by genetic testing antenatally, so the diagnosis is often first suspected on a scan rather than in the delivery room.
Antenatal ultrasound. Bowing plus a small thorax is the key pattern:
- Shortened and bowed long bones, especially the femora and tibiae
- A narrow, small thorax with a reduced chest circumference, predicting the lethal pulmonary hypoplasia that drives mortality
- Hypoplastic or absent scapulae
- Sometimes micrognathia or cleft palate
The karyotype clue. Discordance between a 46,XY karyotype and female-appearing genitalia on antenatal assessment strongly suggests the SOX9 diagnosis rather than another lethal dysplasia. The antenatal differential includes thanatophoric dysplasia and osteogenesis imperfecta type II.
Confirmation. Definitive prenatal diagnosis is molecular: SOX9 sequencing and karyotype on chorionic villus sampling or amniocentesis, particularly where there is a suggestive scan or a family history. After birth the diagnosis rests on the clinical and radiographic phenotype (bowed long bones, hypoplastic scapulae), with SOX9 genetic confirmation and karyotype.
Why it matters. Recognising a lethal phenotype prenatally allows honest counselling, the option of termination, and planning of delivery and neonatal care, whether a palliative pathway or active airway and respiratory support.
Management
Management is largely supportive and palliative given the high mortality from respiratory failure, and it is dictated by the airway first and the skeleton second. The honest framing for the family is that this is a historically lethal condition in which survival beyond infancy is now reported but cannot be promised, so airway planning is not futile.
Plan the delivery. When the diagnosis is suspected on scan, deliver at a centre with neonatal intensive care and paediatric ENT and anaesthesia, and agree the ceiling of intervention with the family beforehand. A palliative pathway and an active airway pathway are both legitimate, and the decision should not be made for the first time in the delivery room.
Assess the whole airway. Because obstruction is characteristically multi-level, relieving one level, by intubation past the tongue base or tracheostomy for tracheomalacia, may leave the child still obstructed at another. The Nelson review's two cases argue for evaluation by a team that will scope the entire airway rather than treat the first lesion found, and a child who remains obstructed after intubation or tracheostomy has not been fully assessed.
The thorax compounds the problem. Even with a secured airway, the narrow bell-shaped chest restricts ventilation. Respiratory failure from the combination of restrictive thorax and collapsing airway is the usual mechanism of death.
Feeding and reflux are frequently problematic for the same anatomical reasons and need early speech-and-feeding input.
Complications & Prognosis
Respiratory failure is the dominant early complication and the usual cause of death. Beyond it:
- Progressive kyphoscoliosis in survivors threatens an already small thorax and can worsen restrictive lung disease over time, which is why spinal surveillance continues to skeletal maturity
- Feeding difficulty, failure to thrive and recurrent respiratory infection accompany the airway and palatal anomalies
- Gonadal and psychosocial sequelae of the sex reversal require long-term DSD follow-up
Q: What do you tell the parents?
A: That campomelic dysplasia is historically lethal, that death when it occurs is usually from respiratory failure in the neonatal period, that the airway obstruction is often at several levels and may not be relievable at one, that survival into childhood is reported and changes the conversation towards the orthopaedic, spinal and endocrine issues - and that a precise survival percentage cannot honestly be quoted because none exists in the retrievable literature.
Mnemonics & Memory Aids
BENT
Hook:BENT: Bowed bones (camptomelia), Endocrine sex reversal (SOX9), Narrow thorax (laryngotracheomalacia), Testis gene SOX9.
SOX9
Hook:SOX9: the SRY-box gene that builds cartilage (Osteogenesis) and determines sex (seX) - damage it and you get bowed bones, a collapsing airway, and XY sex reversal in one disease.
DIMPLE
Hook:DIMPLE: the skin Dimple over the tibial bow, de novo Inheritance, Multi-level airway, Palliative framing, Look at the parents, Eleven rib pairs.
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“A neonate has congenital bowing of the long bones with anterior tibial bowing and a skin dimple, hypoplastic scapulae and respiratory distress; the karyotype is 46,XY but the genitalia appear female. What is the diagnosis?”
What it is
- Rare, often lethal skeletal dysplasia; SOX9 mutation (usually de novo)
- 'Camptomelic' = bent-limbed
- Recognised among lethal fetal/neonatal dysplasias
Features
- Congenital long-bone bowing (anterior tibial bow + overlying skin dimple)
- Hypoplastic scapulae, reduced rib pairs, scoliosis, clubfeet, small thorax
- Cleft palate / Pierre Robin sequence; XY sex reversal (SOX9)
Mortality & management
- High mortality from respiratory compromise (small thorax + laryngotracheomalacia)
- Largely supportive/palliative; neonatal airway/respiratory support
- Survivors: orthopaedic care of bowing/scoliosis/feet; endocrine + genetic input
Evidence & Key Studies
SOX9 discovery: campomelic dysplasia and autosomal sex reversal in one gene
- Cloned a translocation breakpoint from a sex-reversed campomelic patient and found the adjacent gene, SOX9, an SRY-related (SRY-box) gene on chromosome 17.
- Mutation analysis implicated SOX9 in BOTH bone formation and control of testis development - one gene explaining the skeletal dysplasia and the XY sex reversal simultaneously.
- Established the molecular route by which a chromosomal rearrangement upstream of a gene (a position effect) can produce the disease.
Skeletal dysplasias of the fetus and infant (including campomelic dysplasia)
- Campomelic (camptomelic) dysplasia is among the recognised genetic skeletal disorders identified in the fetal/neonatal period; the most severe/lethal phenotypes are identifiable prenatally.
- Perinatal autopsy and post-mortem radiographs are crucial for definitive diagnosis, and an increasing number of cases are confirmed by genetic testing.
- Campomelic dysplasia is listed alongside thanatophoric dysplasia, osteogenesis imperfecta, achondroplasia and chondrodysplasia punctata among the dysplasias encountered.
Airway management: obstruction occurs at multiple levels
- Two illustrative children meeting diagnostic criteria, with a review of clinical-molecular correlations in the head and neck - so a case-based review, not a cohort.
- Describes campomelic dysplasia as a rare and HISTORICALLY lethal skeletal dysplasia with a variable but recognisable phenotype - the wording matters, since survival beyond infancy is now described.
- MANY patients have airway obstruction at MULTIPLE LEVELS, so relieving one level may leave the child obstructed.
- Mutations in or around SOX9 account for most patients, with the head and neck anomalies following from the same cartilage defect.
- Two patients: it informs airway strategy and cannot quantify how often multi-level obstruction occurs.
Familial recurrence from maternal germinal mosaicism - and how it was detected
- Most cases are sporadic and de novo; familial campomelic dysplasia is very rare.
- Two siblings with the classic phenotype shared a novel SOX9 frameshift mutation.
- Radiological examination of the apparently healthy MOTHER showed mild skeletal changes, and her somatic mosaicism for the mutation was then confirmed - the first molecularly confirmed maternal germinal mosaicism for SOX9.
- The authors conclude that meticulous clinical examination of superficially healthy parents is needed to avoid overlooking germinal mosaicism.
- A single family: it establishes that mosaic transmission occurs and cannot give a recurrence risk.