Anterolateral Bowing | NF1 Association | Recalcitrant Nonunion
- NF1 mutation drives impaired osteoblast function and poor bone healing
- Anterolateral bowing begins in infancy and fractures early leading to pseudarthrosis
- Crawford classification guides prognosis and timing of intervention
- Union rates remain low despite modern techniques; refracture is common
- Cross-union gives the best pooled results (100% union, 22.5% refracture); combining an IM rod WITH a frame beats either alone; vascularised fibula's PRIMARY union is actually the lowest at 65.3% and it is a defect-bridging/salvage tool
- “Always screen for NF1 stigmata in any anterolateral bow
- “Type IV pseudarthrosis has the worst healing potential
- “Ilizarov with compression-distraction remains gold standard in many centres
- “Amputation is about 16 percent OVERALL, 10-30 percent in refractory cases - quote the right denominator
Overview and Epidemiology
What it is. Congenital pseudarthrosis of the tibia (CPT) is a dysplastic nonunion that develops after pathological fracture through an area of anterolateral bowing. The bow begins in infancy with its apex at the junction of the middle and distal thirds, and the natural history runs from a sclerotic or cystic lesion in the distal third of the tibia, to fracture, to an established pseudarthrosis. It is one of the most challenging conditions in paediatric orthopaedics: union is difficult to achieve and to maintain, and the condition accounts for a disproportionate share of paediatric amputation and repeated surgery worldwide. Early recognition of the bow before fracture, NF1 screening and realistic family counselling are essential.
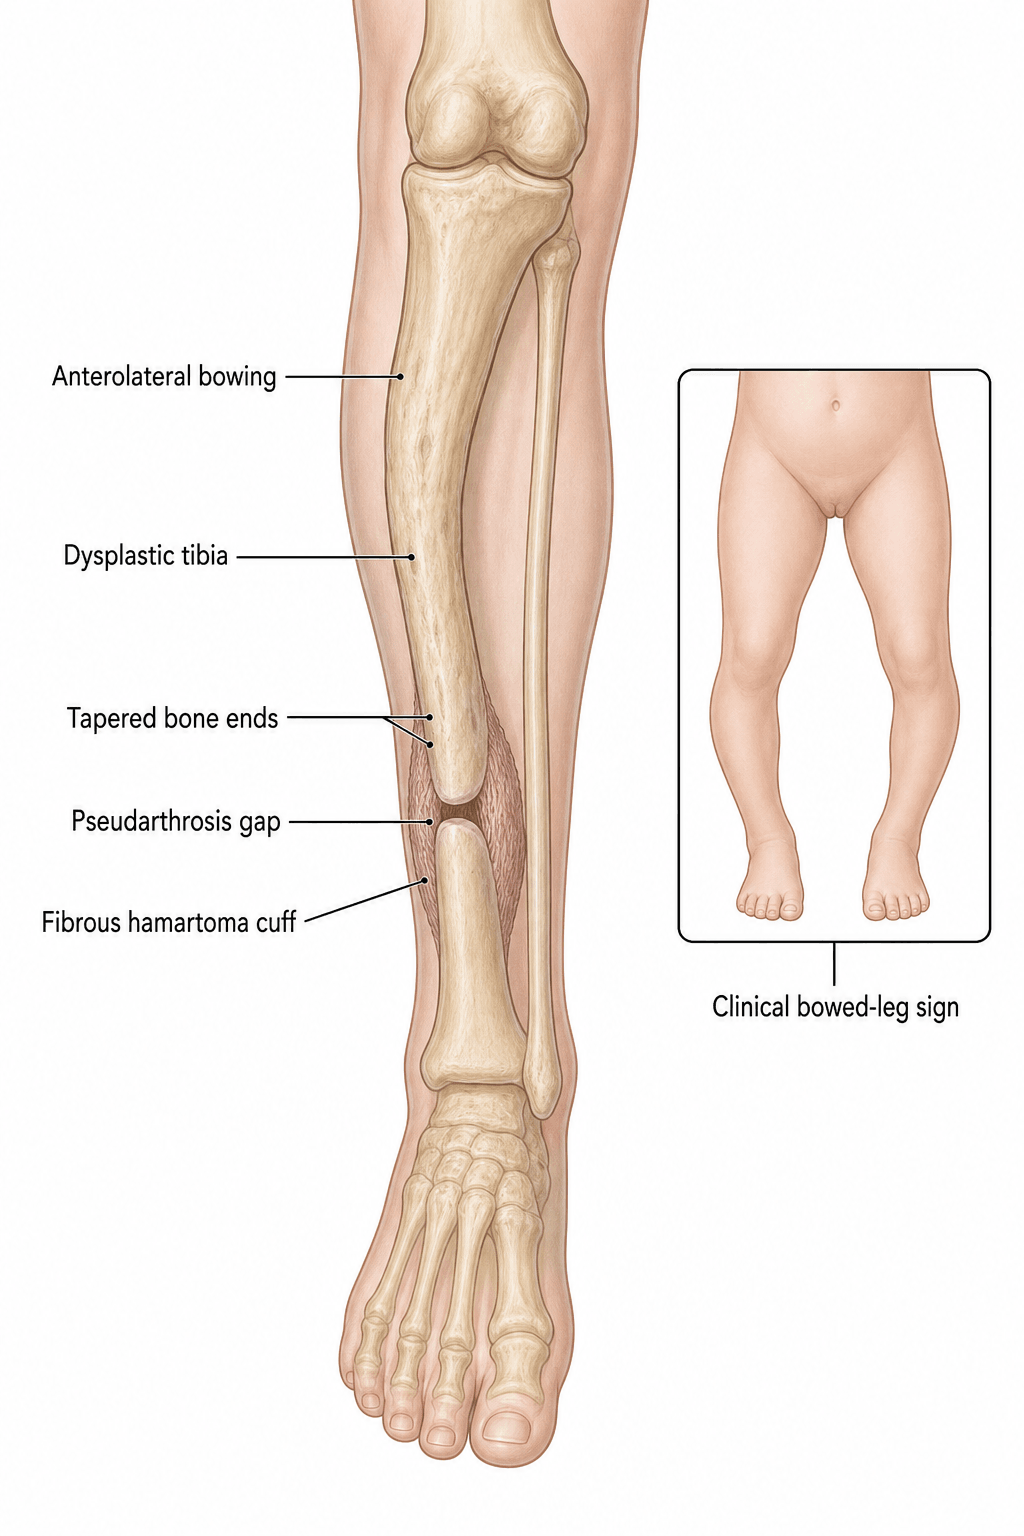
On plain film. Early radiographs show anterolateral bowing without fracture. Later films show atrophic bone ends, sclerosis and eventual pseudarthrosis. The failure is biological, a failure of healing, not a mechanical fracture, not a mechanical fracture.
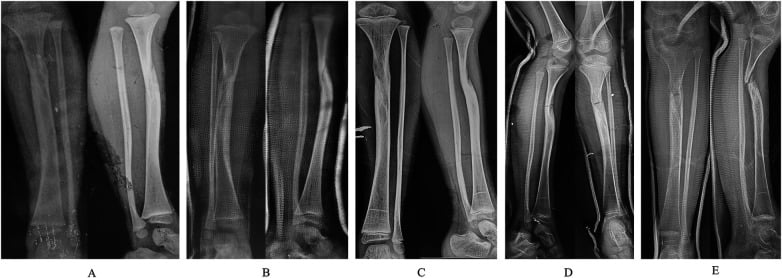
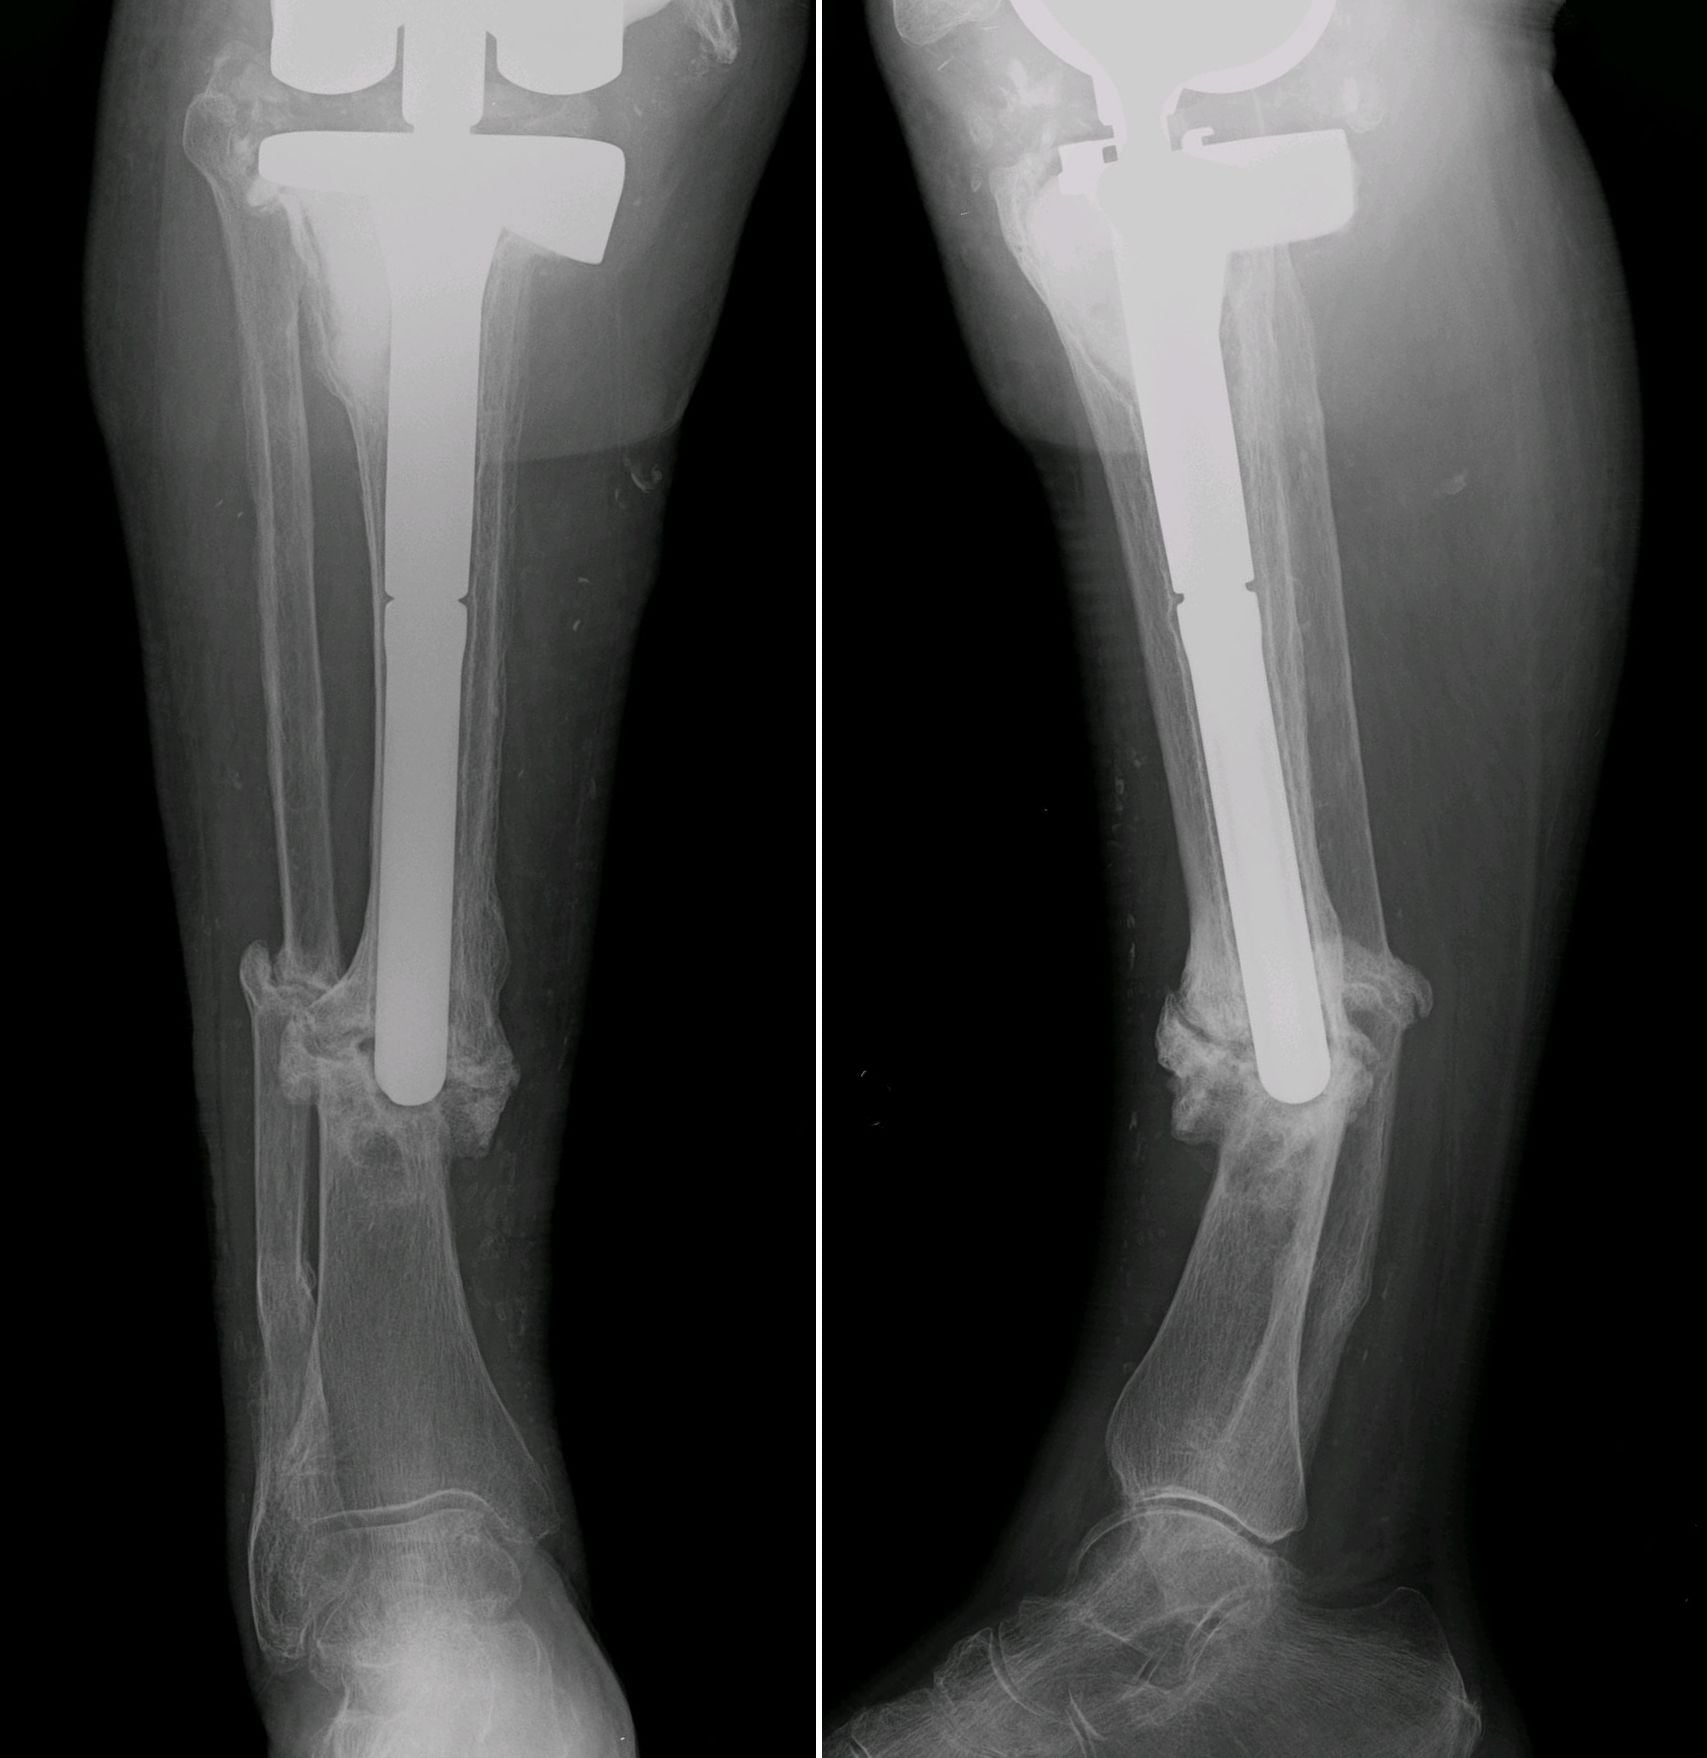
How common. Incidence is 1 in 140,000 to 1 in 250,000 live births. It is unilateral in more than 95 percent, right and left equally.
NF1, in both directions. 50-80 percent of CPT cases have NF1, and NF1 drives the poor bone biology and the higher refracture risk. The reciprocal figure matters more in clinic: only about 5 percent of children with NF1 develop congenital long-bone pseudarthrosis (PMID 10360395). The parents of a child newly diagnosed with NF1 will ask, and the answer is that this complication is uncommon, not expected.
Sex. There is a male predominance, and it is statistically significant: 54 males to 31 females among 85 NF1 patients with pseudarthrosis, against 85:87 in NF1 controls (p = 0.046). Male sex may be a susceptibility factor.
Age at fracture. The bow progresses to fracture by age 2-3 years in most untreated cases, and half of those who fracture do so before age 2 (PMID 10360395). Quote the median, not the mean of 2.5 years: the distribution has a long tail out to age 12, and a mean understates how early the risk is concentrated.
What the disease costs. It has the highest failure rate of any long-bone nonunion. Despite advances in fixation, biology and microsurgery, union rates remain 50-80 percent at best, refracture follows apparent union in more than 50 percent, a limb-length discrepancy of 2-5 cm at skeletal maturity is common, and patients average 3-6 procedures. Amputation is about 16 percent overall (Stevenson series) and 10-30 percent in the refractory subgroup: two different denominators, and they are not interchangeable.
Pathophysiology
The gene. NF1 is caused by loss-of-function mutations in the neurofibromin gene on chromosome 17. Neurofibromin normally inhibits RAS signalling; without it RAS activity is uncontrolled, osteoblast differentiation is impaired, osteoclast activity increases, and a fibrous hamartoma replaces normal bone at the pseudarthrosis site.
The hamartoma. It produces excessive TGF-beta and is poorly vascular, which is why the nonunion is atrophic and why refracture is common even after stable fixation. The disease is in the periosteum: at surgery the pseudarthrosis is encased in a pathologically thickened fibrous cuff, and radical excision of that cuff, rather than simply fixing the bone, is the step that permits union.
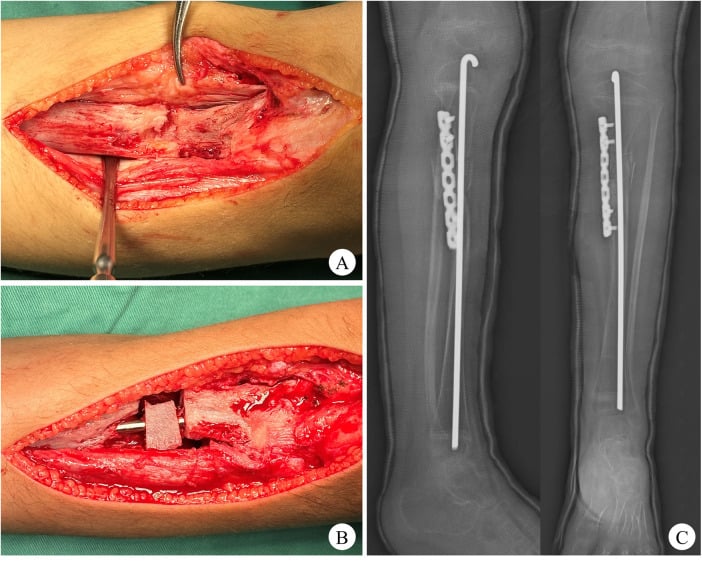
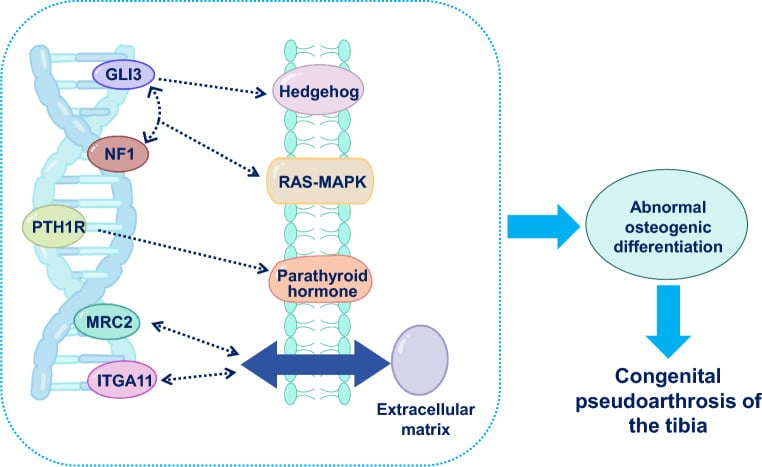
Why healing fails. Four things work against union:
- Biology: deficient osteoprogenitor cells, excessive fibrous tissue and low BMP responsiveness
- Mechanics: a narrow distal fragment with poor purchase for fixation, and high shear at the apex
- Vascularity: the hamartoma is hypovascular, and periosteal stripping during surgery worsens it
- The fibula: fibular pseudarthrosis coexists in 50-75 percent of cases, and untreated it leads to valgus and refracture, so it must be addressed to prevent valgus collapse
Why the bow is anterolateral. Asymmetric physeal growth from NF1 dysplasia disturbs growth, and the fibrous hamartoma tethers the lateral cortex. A weak anterior compartment contributes to the apex-anterior deformity. The lateral bow places the distal tibia in varus, which increases the fracture risk.
The cascade. Untreated, the tibia moves through three stages, each with a radiographic signature and a consequence:
- Pathology
- Periosteal dysplasia, NF1 hamartoma
- Radiograph
- Anterolateral bow, normal canal (Crawford I)
- Risk if Untreated
- Fracture by age 3 years in 70 percent
- Pathology
- Medullary narrowing, sclerosis
- Radiograph
- Type II-III changes, impending fracture
- Risk if Untreated
- Pathologic fracture within months
- Pathology
- Atrophic bone ends, fibrous hamartoma
- Radiograph
- Type IV mobile nonunion +/- fibula
- Risk if Untreated
- Refracture, shortening, deformity
Classification and Types
Crawford's radiographic classification (1986) is the shared language because it correlates directly with the natural history and sets the timing of intervention. Boyd (1982) predates it and is descriptive and aetiologic: it captures where the lesion came from and whether the fibula is involved, which is useful for surgical planning, but it is harder to apply consistently, and reproducibility is why Crawford remains the staging tool of choice. Most centres combine the Crawford type with NF1 status and fibular involvement when they plan.
- Radiographic Features
- Anterolateral bow, normal medullary canal
- Prognosis
- Best; may never fracture
- Treatment Approach
- Observation, prophylactic bracing
- Radiographic Features
- Narrowed canal, cortical sclerosis
- Prognosis
- Good if protected
- Treatment Approach
- Bracing, early surgery if cystic change
- Radiographic Features
- Cystic lesion at apex
- Prognosis
- Moderate; high fracture risk
- Treatment Approach
- Consider prophylactic surgery
- Radiographic Features
- Established pseudarthrosis +/- fibula
- Prognosis
- Poorest; high refracture
- Treatment Approach
- Surgical reconstruction mandatory
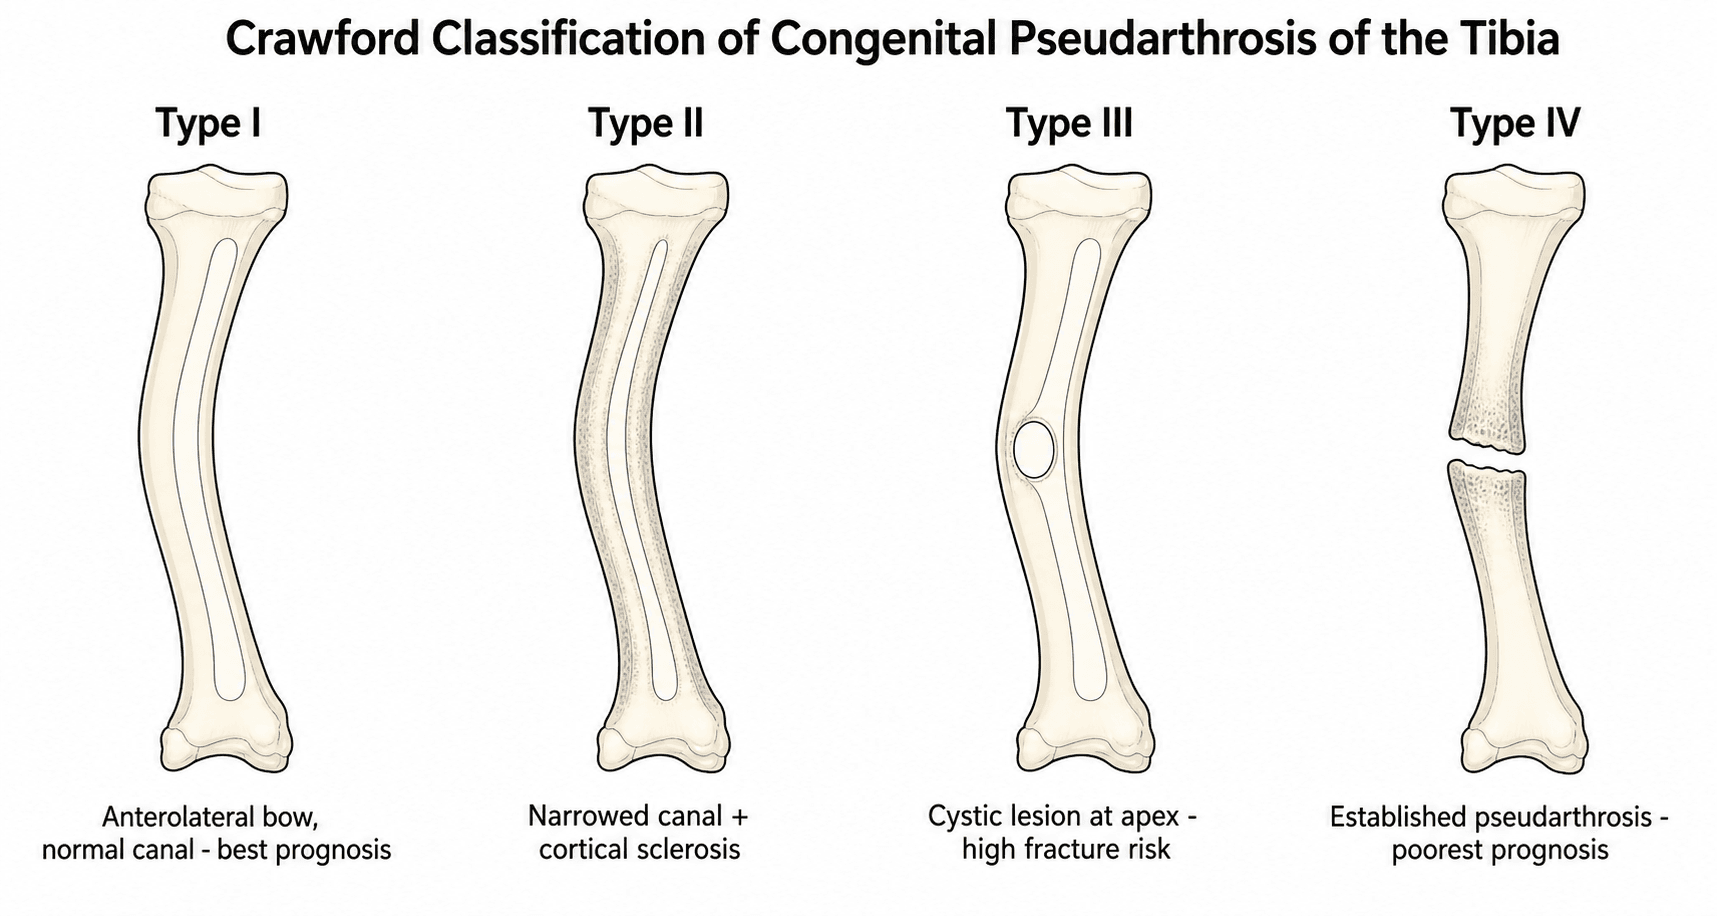
Serial radiographs track the progression from bowing to cystic change to frank nonunion, and the type guides the timing of intervention.
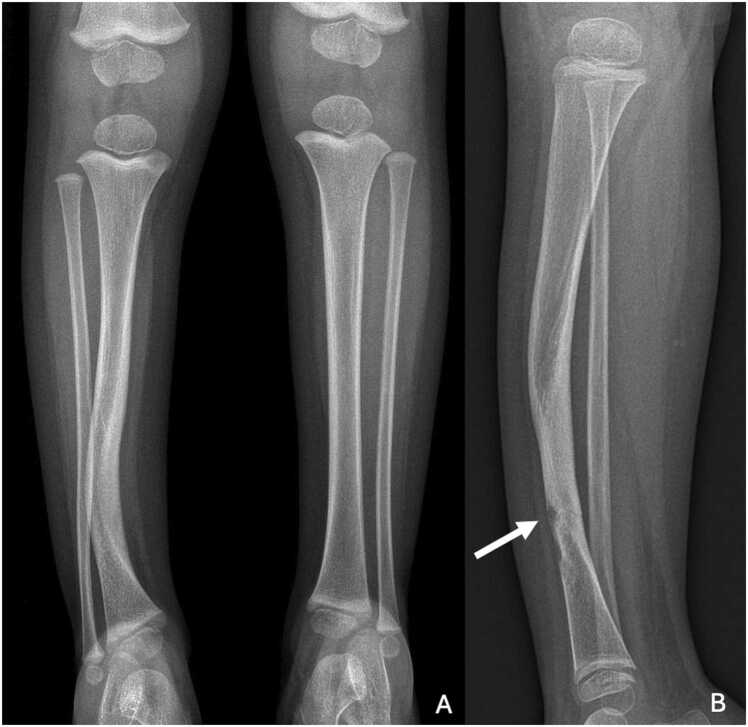
Clinical Assessment
History. The bowing is usually noticed in the first year of life. The answers that change management are these:
- Family history of NF1 in first-degree relatives
- Previous fractures: how many, at what age, and what was tried to heal them
- Functional limitation: pain, limp, problems with shoe wear
- Prior surgery: the number of procedures and their complications
Examination. Inspect for the anterolateral bow, skin dimpling and cafe-au-lait spots. Palpate for a mobile pseudarthrosis, warmth and tenderness. Watch the gait for a short limb, circumduction and a valgus thrust. The neurovascular examination is usually intact, but check for an NF1 neuropathy. Screen the spine for scoliosis and measure the limb-length discrepancy, because deformity and length decide final function as much as union does.
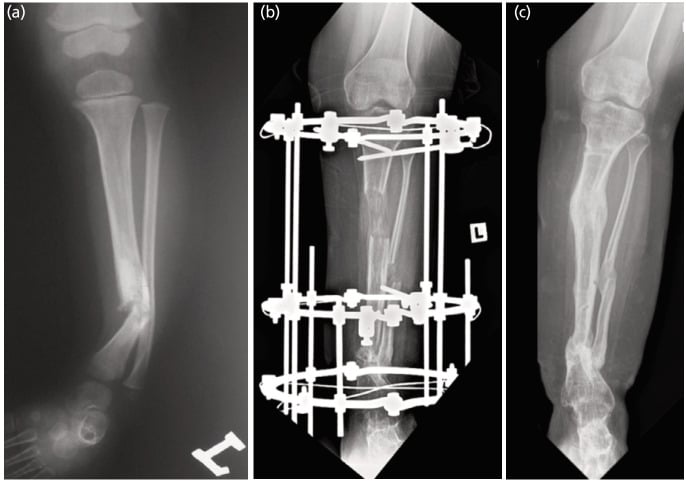
The mimics to separate from a true anterolateral bow: Posteromedial bowing has no NF1 link and no risk of pseudarthrosis, and the bow itself corrects; it is benign for the bone, not for the length, and the persistent shortening is set out in the warning below. Physiologic bowing is symmetric varus that resolves by age 2. Rickets and other metabolic bone disease are bilateral, with metaphyseal changes and biochemical abnormalities, and osteogenesis imperfecta declares itself with multiple fractures, blue sclerae, a family history and a collagen mutation. Obtain full-length standing radiographs and an NF1 clinical screen on every anterolateral bow; the systemic disease is set out in neurofibromatosis.
The direction of the bow is the single most valuable observation you will make in this clinic. Anterolateral means CPT until proven otherwise and carries a poor prognosis; posteromedial is benign and self-correcting. Getting this backwards sends a child either into needless surveillance or, far worse, out of the door without bracing during the two years in which half of all fractures occur.
- Direction
- Anterolateral
- NF1 Link
- 50-80 percent
- Prognosis
- Poor without surgery
- Key Discriminator
- Crawford changes, mobile nonunion
- Direction
- Posteromedial
- NF1 Link
- None
- Prognosis
- Angle resolves; SHORTENING DOES NOT
- Key Discriminator
- Spontaneous correction of the bow, calcaneovalgus foot, but a persistent limb-length discrepancy
- Direction
- Symmetric varus
- NF1 Link
- None
- Prognosis
- Resolves by age 2
- Key Discriminator
- No apex, normal bone quality
- Direction
- Variable
- NF1 Link
- Rare
- Prognosis
- Variable with bisphosphonates
- Key Discriminator
- Multiple fractures, blue sclerae
The row above is the one most often half-remembered. Posteromedial bowing genuinely does not become a pseudarthrosis, it needs no bracing and it must never be osteotomised in infancy - but "it resolves" applies to the angle, not the limb, and reassuring a family that the leg will simply straighten out sets up a discharge that has to be undone years later.
- The bow does remodel, and then stops. In a prospective series of 51 children, the posterior bow remodelled fastest, the rate in the first year of life halved in subsequent years, and minimal remodelling occurred after 4 to 6 years of age (PMID 41239344). What has not corrected by school age will not.
- The shortening only partly resolves. In the same series tibial shortening went from 20 per cent at presentation to 13 per cent at age 6 - better, but permanent.
- A substantial minority need lengthening. Following 22 children from birth to maturity, the bow remodelled satisfactorily in 13 (59 per cent) - and even those had a mean residual discrepancy of 21 mm. Nine of 22 (41 per cent) underwent lengthening, the threshold used being an estimated discrepancy over 40 mm (PMID 36345184).
- You can predict the final discrepancy early. The multiplier method gives an estimate at maturity that does not change significantly once the child is over two years old (PMID 41239344) - so plan from age two rather than watching and waiting.
The practical consequence is to counsel the parents that the shape corrects itself and the length does not, and to keep the child in a limb-length clinic to skeletal maturity rather than discharging them when the leg looks straight.
Two or more of the following criteria confirm NF1; genetic testing confirms but is not required for the diagnosis.
- More than 6 cafe-au-lait macules over 5 mm in a prepubertal child (over 15 mm in an adult)
- Axillary or inguinal freckling (the Crowe sign, highly specific for NF1)
- More than 2 neurofibromas, or 1 plexiform neurofibroma
- Optic glioma
- More than 2 Lisch nodules (iris hamartomas, seen on slit-lamp examination)
- Sphenoid dysplasia or thinning of a long bone
- A first-degree relative with NF1
Macrocephaly is common in NF1, so check the head circumference, and the skeletal dysplasia extends beyond the tibia to scoliosis and sphenoid dysplasia.
Investigations
Radiographs first. Diagnosis and classification are radiographic. Request AP and lateral views of the tibia and fibula, full-length standing films of both legs, and a hand film for bone age if there is a discrepancy. Read them for the Crawford type, the state of the fibula, shortening, ankle valgus and proximal migration of the fibula. In the bowing stage, repeat films every 3-6 months to catch cystic change or fracture.
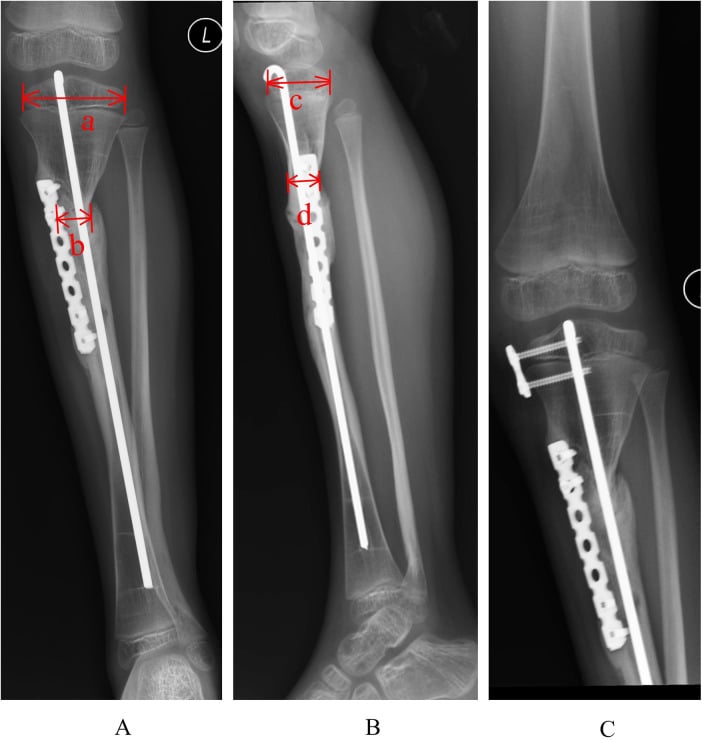
CT characterises the pseudarthrosis before surgery: the atrophic bone ends, the medullary canal diameter, the extent of the hamartoma and any fibular pseudarthrosis. From it come the rod diameter, the Ilizarov ring size and the length of any transport segment.
MRI is for planning a vascularised fibula or a cross-union. It shows the fibrous hamartoma replacing bone, periosteal reaction, muscle quality and the vascular anatomy, and it helps decide between an Ilizarov frame, a vascularised fibula or a combined approach.
Laboratory and genetic. A clinical diagnosis of NF1 is sufficient; genetic confirmation is for family planning or atypical features. Before major reconstruction send a full blood count, coagulation and a type and screen, and check calcium, phosphate, PTH and vitamin D to exclude a metabolic contributor.
MRI and CT are adjuncts for surgical planning only. Do not delay bracing or referral while awaiting advanced imaging in an infant with anterolateral bowing.
Management Algorithm
The goal in Crawford I-III is to prevent fracture, and so pseudarthrosis, by protected weight-bearing and surveillance. Bracing is meant to convert a high-risk Crawford II or III tibia into a Type I that never fractures; it works only with compliance and early application, before the first fracture. Once a fracture occurs the biology changes permanently and union becomes far more difficult.
Management Protocol
A custom total-contact KAFO, or an AFO with an anterior shell, to counteract the bow. Weight-bearing as tolerated, with normal development encouraged. Clinical and radiographic review every 3 months, and the family taught the signs of fracture: pain, swelling, refusal to bear weight.
The decision is prophylactic surgery against continued bracing. Rapid cystic expansion, a canal narrower than 50 percent of normal, and concern about family compliance favour surgery; the options are an intramedullary rod inserted before fracture, or an Ilizarov frame with prophylactic compression. Counsel that even with surgery the fracture risk remains elevated.
- Diagnosis
- Crawford I-II on X-ray, NF1 screen positive
- Treatment
- Prophylactic bracing, serial observation
- Key Pearl
- Prevent fracture before pseudarthrosis develops
- Diagnosis
- Crawford III, cystic lesion at the apex
- Treatment
- Consider early surgery or protected weight-bearing
- Key Pearl
- Pre-pseudarthrosis window for intervention
- Diagnosis
- Crawford IV, atrophic bone ends
- Treatment
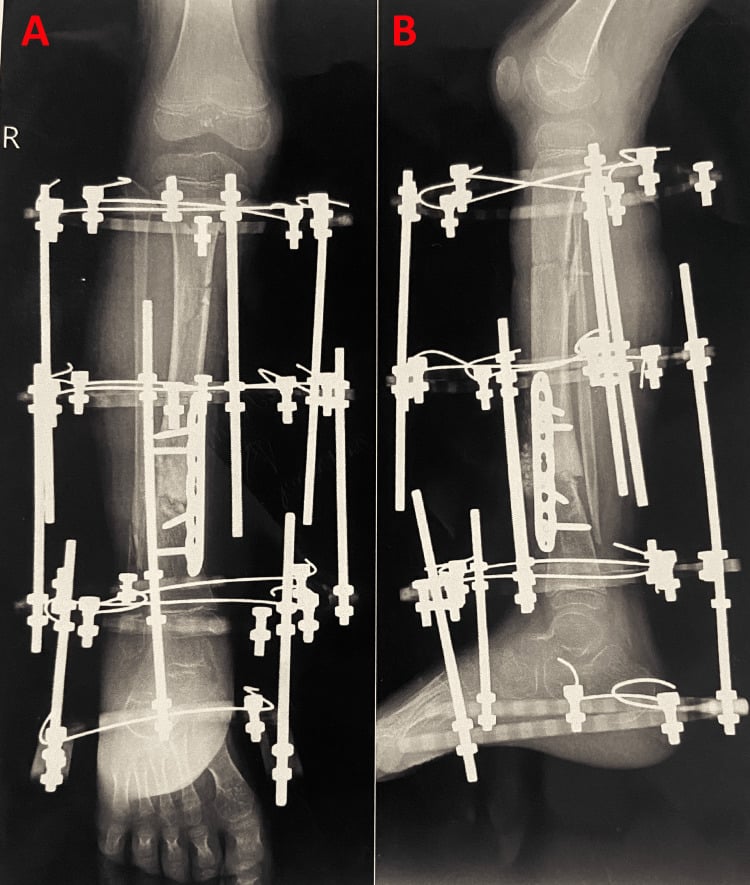
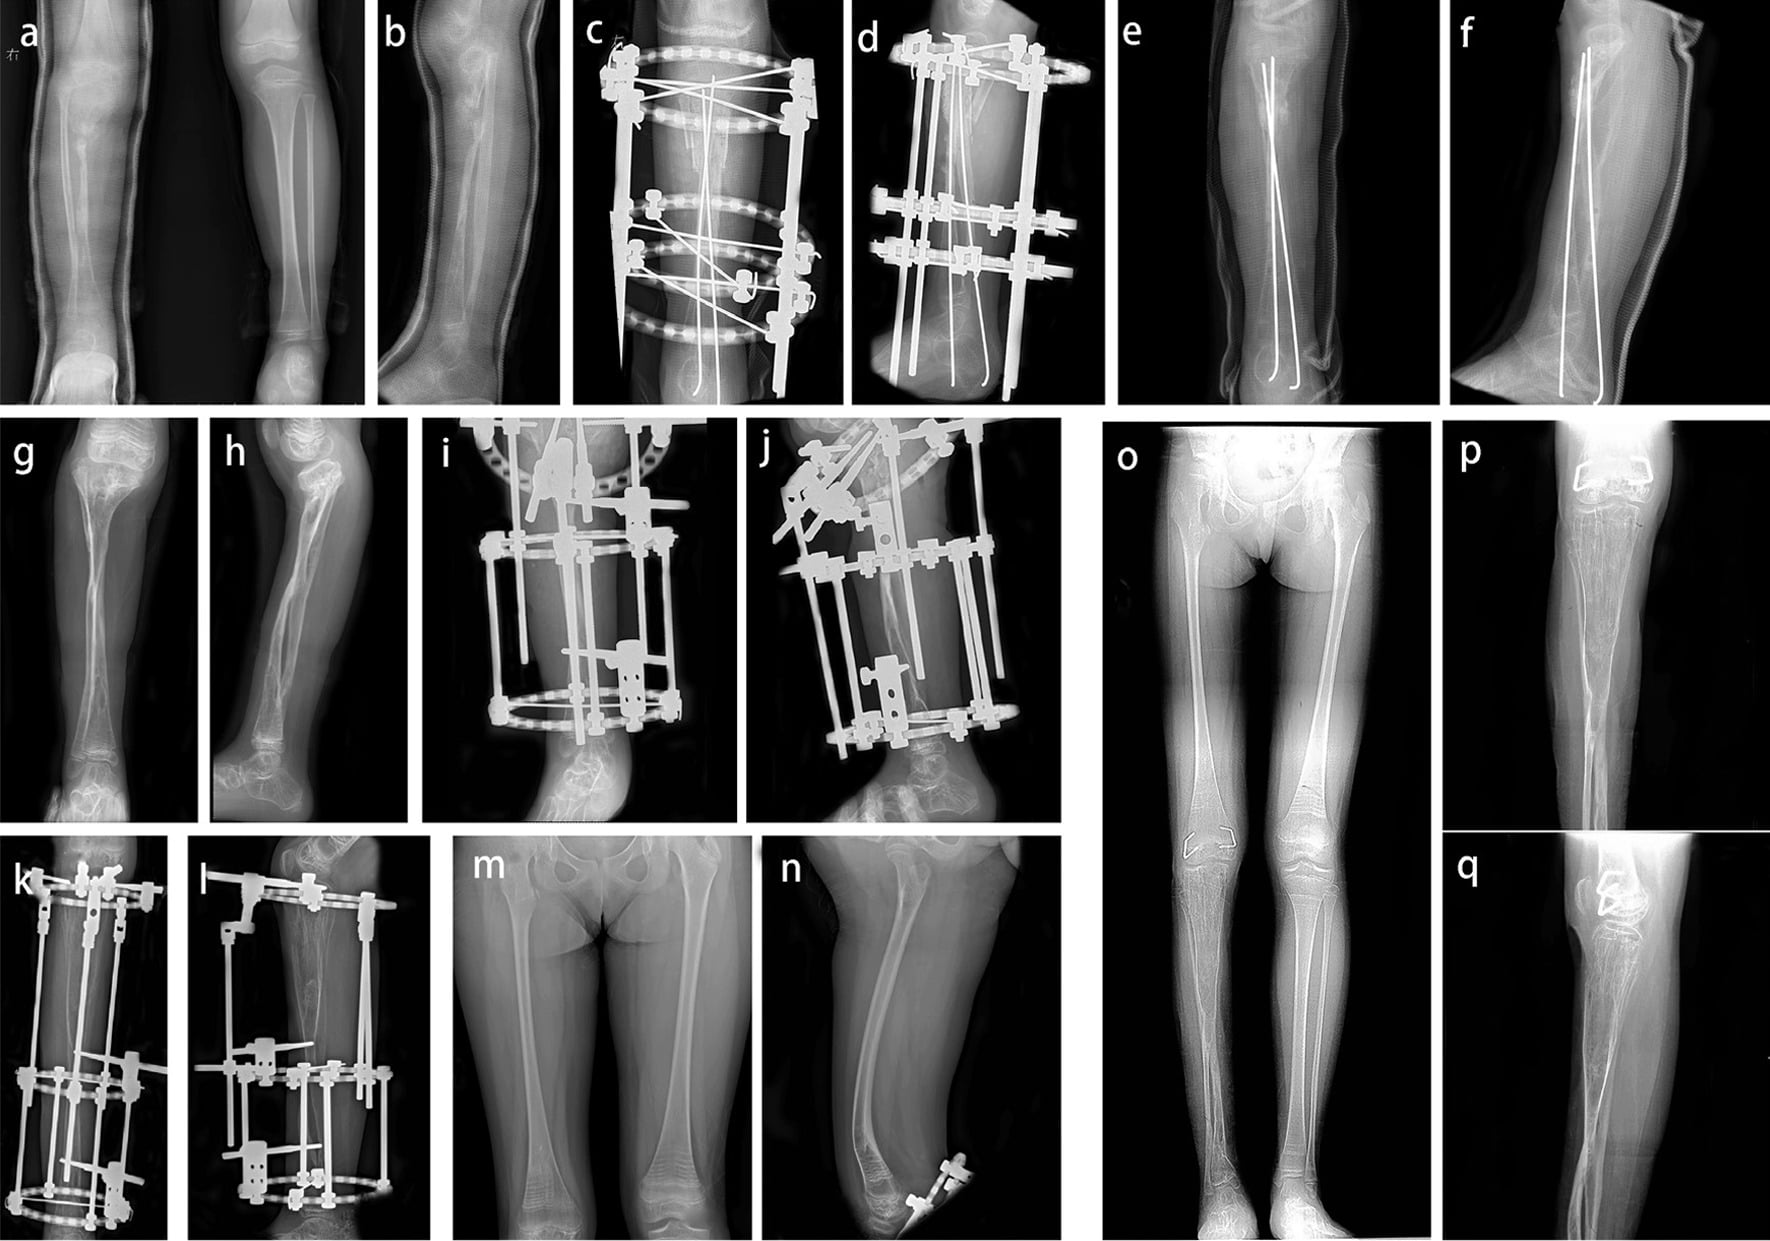
- Surgical reconstruction (Ilizarov, vascular fibula, cross-union)
- Key Pearl
- High refracture risk; counsel family early
Intramedullary Rod Fixation: Transankle and Telescoping Rods
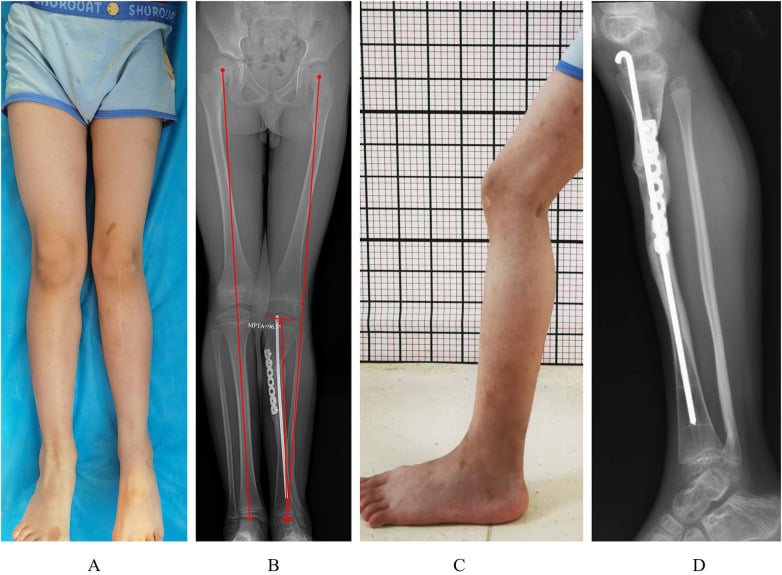
The workhorse. The intramedullary rod is the workhorse of fixation in established CPT, and the choice of rod is a common viva question. The principle is that a rod which spans the pseudarthrosis and crosses the ankle, a transankle or transcalcaneal rod, gives the most durable protection against recurrent angular deformity and refracture through the remaining years of growth. The rod is generally left across the ankle until skeletal maturity; the temporary loss of ankle motion is accepted because distal control matters more, and the ankle remodels.
The distal tibial fragment is short, dysplastic and gives poor purchase. A rod stopping above the ankle leaves it uncontrolled; a transankle rod captures that fragment and the hindfoot and holds alignment until skeletal maturity.
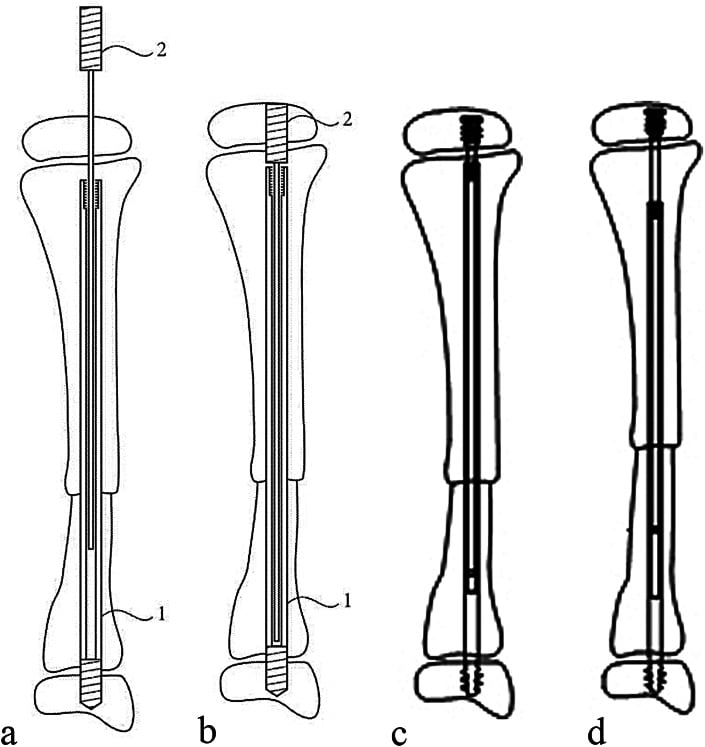
- Williams rod
- Smooth solid (originally a two-part male-female obturator) intramedullary rod
- Telescoping (Fassier-Duval) rod
- Self-elongating two-component rod that telescopes as the bone grows
- Williams rod
- Fixed length; the bone grows off the end so the rod is progressively outgrown
- Telescoping (Fassier-Duval) rod
- Lengthens with the limb, maintaining fixation across the growing segment
- Williams rod
- Planned exchange/re-rodding as the child grows or the rod migrates
- Telescoping (Fassier-Duval) rod
- Fewer planned exchanges; revised mainly for failure, migration or non-telescoping
- Williams rod
- Long-established, widely available, low cost; still effective transankle
- Telescoping (Fassier-Duval) rod
- Adopted from osteogenesis imperfecta practice; favoured where revision burden is a concern
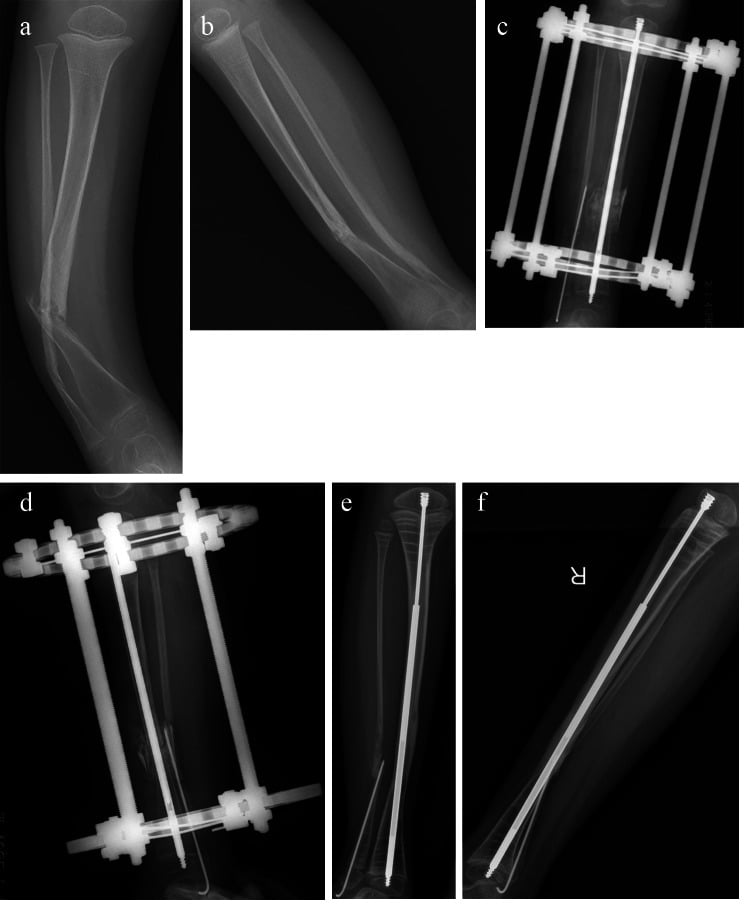
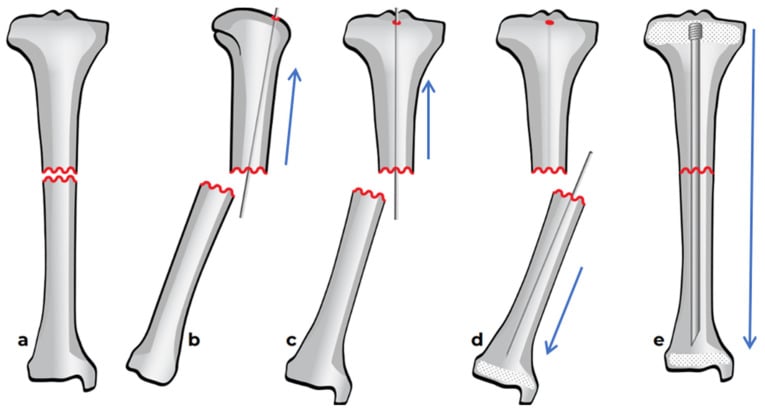
A rod is rarely used alone. Durable union depends on combining stable intramedullary fixation with the biology: radical resection of the fibrous hamartoma, autograft with or without BMP, periosteal grafting, and stabilisation of the fibula or a tibia-fibula cross-union. Rod fixation on its own, without the biology and the fibula, has a high failure rate. The Paley combined ("4-in-1" / cross-union) strategy deliberately pairs a transankle intramedullary rod with cross-union, BMP and a bisphosphonate to attack the mechanics and the poor biology at the same time, which is the rationale for the very low refracture rates reported with that approach.
Complications
- Incidence
- greater than 50 percent overall
- Risk Factors
- NF1, narrow canal, early weight-bearing
- Management
- Re-frame or revise fixation; consider cross-union
- Incidence
- 2-5 cm common at maturity
- Risk Factors
- Multiple surgeries, growth disturbance
- Management
- Epiphysiodesis, lengthening, shoe lift
- Incidence
- 30-50 percent with fibular involvement
- Risk Factors
- Untreated fibular pseudarthrosis
- Management
- Fibular stabilisation or supramalleolar osteotomy
- Incidence
- 10-30 percent after surgery
- Risk Factors
- Atrophic biology, inadequate fixation
- Management
- Revision surgery, vascular fibula, cross-union
- Incidence
- 10-30 percent refractory cases
- Risk Factors
- Multiple failed surgeries, infection, family choice
- Management
- Below-knee amputation with modern prosthetics
Achieving radiographic union is only the first battle. The second, and often harder, battle is maintaining union through skeletal maturity. Protect the leg with bracing or frame for 6-12 months after apparent union, and monitor closely for early refracture. In the pooled series cross-union has the lowest refracture rate, with combined rod-and-frame and vascularised fibula next.
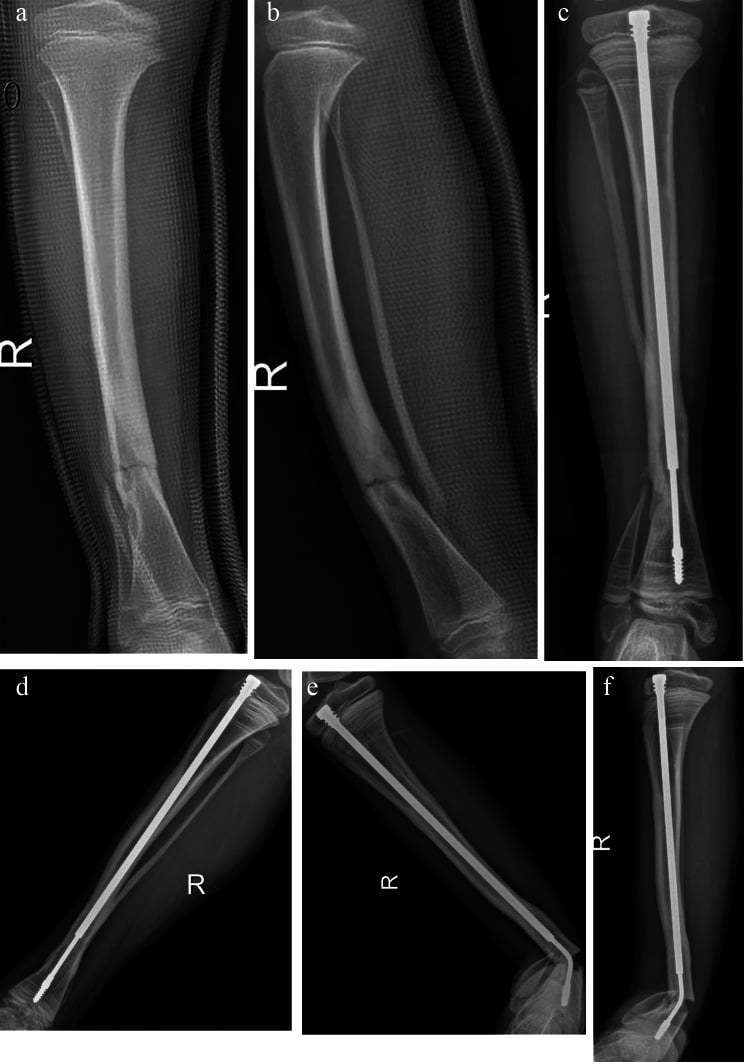
Ankle valgus: why you must treat the fibula, not just the tibia
The fibula is part of the disease. In many cases it is itself dysplastic or carries its own pseudarthrosis, which is graded separately (Dooley). Singer and Johnston showed that reconstructions fixing both tibia and fibula were significantly superior to tibia-only surgery, which produced no excellent results; that is the practical origin of the maxim.
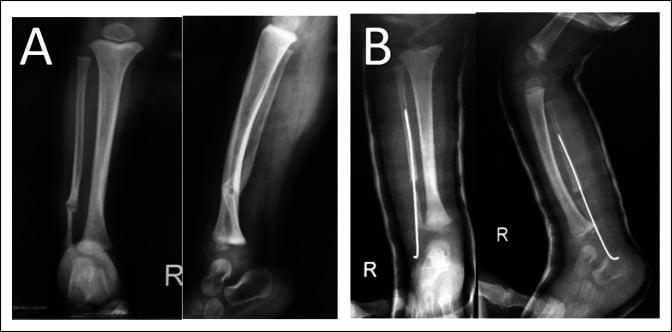
How the valgus develops. A dysplastic or ununited, shortened fibula fails to buttress the lateral ankle. The lateral malleolus migrates proximally, the talus tilts into valgus, and progressive ankle valgus and instability follow, a mean of around 12 degrees despite union in the El-Gammal series. The valgus then compounds any limb-length discrepancy and accelerates degenerative change at the ankle.
How it is managed.
- Achieve fibular union: restoring the lateral column is a major rationale for the cross-union/synostosis strategy, and prevents progression
- Guided growth in the skeletally immature ankle: medial distal tibial hemiepiphysiodesis, for example a medial malleolar screw, corrects the valgus gradually while growth remains
- Distal tibiofibular synostosis (Langenskiöld) stabilises the mortise and prevents proximal fibular migration
- Supramalleolar osteotomy for fixed deformity near or after skeletal maturity
- Surveillance to skeletal maturity, because valgus and instability can recur even after the tibia has united
Outcomes and Prognosis
Use pooled figures, and separate primary from final union. The table below is the systematic review of 57 studies, 1,227 patients and 1,235 tibiae (PMID 35102104), the largest comparison that exists. Primary union is what the index operation achieved; final union is what was achieved after however many revisions it took. Quoting final union as though it were the operation's success rate is how vascularised fibular grafting acquired a reputation the pooled data do not support.
- Primary union
- 67.7 percent
- Final union
- 76.5 percent
- Refracture
- 48.1 percent
- Time to primary union
- 12.6 months
- Overall success probability
- 35.2 percent (lowest)
- Primary union
- 84.2 percent
- Final union
- 81.5 percent
- Refracture
- 47.7 percent
- Time to primary union
- 9.3 months
- Overall success probability
- 44 percent
- Primary union
- 65.3 percent - among the LOWEST, not the highest
- Final union
- 87.1 percent
- Refracture
- 34.6 percent
- Time to primary union
- 9.5 months
- Overall success probability
- 42.7 percent
- Primary union
- 83.7 percent
- Final union
- 92.4 percent (highest final union)
- Refracture
- 33.7 percent
- Time to primary union
- 5.3 months
- Overall success probability
- 55.5 percent
- Primary union
- 100 percent (no non-unions)
- Final union
- 100 percent
- Refracture
- 22.5 percent (lowest)
- Time to primary union
- 4.5 months (fastest)
- Overall success probability
- 77.5 percent (highest)
Vascularised fibula is not the highest union rate. The long-standing teaching that a vascularised fibular graft gives the best union comes from single-surgeon series making unquantified superiority claims about their own technique. In the pooled data its primary union is the lowest of the five strategies, and its good final union is the figure after revision surgery. VFG remains a powerful tool for bridging a large defect or salvaging failed conventional surgery; it is not the default first operation.
Combining fixation beats either alone. Combined IM rod plus Ilizarov reached an overall success probability of 55.5 percent, against 35.2 percent for the rod and 44 percent for the frame used alone, with the shortest time to union of the conventional options. The rod controls the short distal fragment and prevents recurrent deformity through growth; the frame supplies compression and rotational stability. Do not present rod and frame as competing choices: the pooled data favour using both.
The review's own caveat, which you should give with the cross-union figures: "studies on cross-union are few and longer follow-up is lacking." The direction of travel is clear and consistent across three independent series; the durability to skeletal maturity is not yet established.
The best prognosis goes with Crawford I-II caught before fracture, no NF1, good family compliance and access to a specialist paediatric limb reconstruction centre. The poor prognosis goes with NF1, Crawford IV at presentation, fibular pseudarthrosis, prior failed surgery, a short distal fragment and infection. A first fracture before age 3 predicts a worse outcome, and multiple surgeries before age 5 increase the amputation risk.
Guidelines, Registries & Global Practice
- Incidence 1 in 140,000-250,000 worldwide; no clear geographic variation
- NF1 association consistent across populations (50-80 percent)
- Amputation rates higher in low-resource settings due to limited access to Ilizarov and microsurgery
- Specialist centres in high-resource countries report better limb salvage (greater than 85 percent)
- High-resource: Ilizarov, vascular fibula, cross-union, BMP, dedicated limb reconstruction teams
- Limited-resource: IM rod plus autograft, prolonged bracing, higher amputation threshold
- Universal principle: Early bracing before fracture and realistic family counselling are low-cost interventions that improve outcome everywhere
- Surgery: Concentrated in 10-15 global centres with sufficient case volume for expertise
- Diagnosis emphasis
- Crawford classification + NF1 screen on every anterolateral bow
- Surgical strategy
- Ilizarov or vascular fibula at specialist centres; cross-union for salvage
- Long-term protection
- 12 months protected weight-bearing after union; monitor to skeletal maturity
- Diagnosis emphasis
- Early referral to limb reconstruction units before first fracture
- Surgical strategy
- Fibular stabilisation mandatory; cross-union gaining favour
- Long-term protection
- Long-term bracing until growth complete
- Diagnosis emphasis
- Genetic counselling offered for NF1-positive families
- Surgical strategy
- Individualised; IM rod, Ilizarov, or vascular fibula per surgeon preference
- Long-term protection
- Refracture risk discussed; amputation offered after multiple failures
There is no international CPT registry. Evidence is derived from single-centre series and expert consensus. The European Paediatric Orthopaedic Society (EPOS) and POSNA have published treatment algorithms emphasising early referral, fibular management, and prolonged protection. Cross-union is the most recent advance with the lowest published refracture rates.
Record in every anterolateral bowing case:
- Crawford type on initial and serial radiographs
- NF1 clinical criteria met or excluded
- Bracing compliance and family education provided
- Referral to specialist centre documented A missed opportunity to brace before fracture is a recurring source of preventable morbidity worldwide. Always document the bowing direction, NF1 screen, and management plan at the first visit.
Controversies & Areas of Uncertainty
Some centres advocate early rod insertion or Ilizarov compression before fracture in cystic lesions; others continue bracing until fracture occurs. No randomised data exist; decision is individualised by family compliance, canal diameter, and centre expertise.
Off-label BMP-2 or 7 is used by some surgeons to augment biology at the pseudarthrosis site. Small series suggest modest improvement in union rates, but concerns remain about cost, heterotopic ossification, and lack of high-level evidence.
Ilizarov, vascularised fibula, and cross-union all have advocates. No head-to-head trials. Ilizarov is most accessible globally; vascular fibula requires microsurgery; cross-union is emerging as preferred salvage with lowest refracture in recent reports.
After 3-4 failed reconstructions, severe shortening, or infection, many families choose amputation for quality-of-life reasons. Modern below-knee prostheses allow excellent function and sports participation; decision timing and counselling are critical.
MCQ Practice Points
Q: Which Crawford type has the worst prognosis for union? A: Type IV (established pseudarthrosis). Type I has normal canal and best prognosis; Type IV has atrophic bone ends, fibrous hamartoma, and the highest refracture rate despite surgery.
Q: What percentage of congenital pseudarthrosis of the tibia cases are associated with NF1? A: 50-80 percent. Every child with CPT requires full NF1 clinical screening (cafe-au-lait count, axillary freckling, Lisch nodules, family history). NF1-positive cases have worse biology and higher refracture risk.
Q: What is the typical age of first fracture in untreated anterolateral bowing? A: Half of those who fracture do so before age 2 (PMID 10360395) — give the median rather than the commonly quoted mean of 2.5 years, because the range extends to age 12 and the mean is pulled up by that tail, understating how early the risk is concentrated. The practical consequence is that the window for prophylactic bracing is the first two years of life, not the first three. Once fracture occurs, the pseudarthrosis biology is established and healing potential drops dramatically.
Q: Which surgical technique currently reports the lowest refracture rate in refractory CPT? A: Cross-union (tibia-fibula synostosis), performed as a combination protocol with pseudarthrosis resection, autogenous iliac graft, BMP-2 and reliable intramedullary fixation. In 18 patients selected for having already refractured after previous surgery, it produced 100 percent union at a mean 2.96 months with 0 percent refracture at mean 4.3 years (PMID 35297391); a comparative series found 100 percent versus 36.4 percent primary union against rodding and graft alone (PMID 39743526). Add the caveat for full marks: these are Level IV series from expert centres and the follow-up does not yet reach skeletal maturity, which is when refracture has traditionally been judged.
Q: What is the overall amputation rate in congenital pseudarthrosis of the tibia? A: Approximately 16 percent - that is the figure from the largest descriptive series, 75 cases ascertained through NF centre directors (Stevenson, PMID 10360395), and it is an overall rate across all comers. Be careful not to answer this question with the 10 to 30 percent figure: that is a different denominator, describing the refractory subgroup with multiple failed operations, infection or severe shortening. Quoting a refractory-subgroup rate as though it were the whole-cohort rate roughly doubles the risk you present to a family. Where amputation is reached, it is usually below-knee, and prosthetic function is characteristically good - which is why it is a legitimate planned outcome rather than only a failure.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 14-month-old presents with progressive anterolateral bowing of the right tibia noticed since age 6 months. The child has six cafe-au-lait macules greater than 5 mm and axillary freckling. X-rays show Crawford Type II changes with cortical sclerosis and narrowed medullary canal. No fracture has occurred. What is your diagnosis, work-up, and management plan?”
“A 7-year-old with known NF1 and Crawford Type IV congenital pseudarthrosis has undergone three failed attempts at union (two IM rod plus graft, one Ilizarov). The leg is 4 cm short, the pseudarthrosis is mobile with atrophic bone ends, and the fibula is also pseudarthrotic with ankle valgus. The family is desperate to avoid amputation. What surgical strategy would you recommend?”
Key Biology and NF1
- NF1 mutation in 50-80 percent; drives poor osteoblast function and fibrous hamartoma
- Hamartoma produces TGF-beta, is hypovascular, and replaces normal bone at pseudarthrosis site
Crawford Classification
- Type I: anterolateral bow, normal canal - best prognosis, brace
- Type II: narrowed canal, sclerosis - protect, consider early surgery
- Type III: cystic lesion - high fracture risk, surgical threshold
- Type IV: established pseudarthrosis - worst outcome, surgery mandatory
Natural History
- Anterolateral bowing begins in infancy; HALF of those who fracture do so before age 2 (median beats the quoted mean of 2.5 yrs - long tail to age 12)
- Only ~5% of NF1 children develop pseudarthrosis - the reciprocal figure parents actually ask for
- Once fractured, biology changes permanently; refracture greater than 50 percent after union
Surgical Principles
- Debride hamartoma, stabilise (Ilizarov, rod, plate), address fibula
- Cross-union or vascular fibula for lowest refracture; protect 6-12 months post-union
Complications and Endpoints
- Refracture greater than 50 percent, LLD 2-5 cm, ankle valgus, amputation 10-30 percent
- Amputation is realistic endpoint after multiple failures; modern prosthetics give excellent function
Evidence Base and Key Trials
There is no randomised evidence in this condition and there never will be — it affects roughly 1 in 200,000 births. What exists is a small number of series, each answering a different question, grouped below in the order an examiner tends to ask them.
Osseous manifestations of neurofibromatosis in childhood
- Review of the osseous manifestations of neurofibromatosis in childhood, including tibial dysplasia and pseudarthrosis
- Describes the Crawford classification of anterolateral tibial bowing/dysplasia (types I-IV), with established pseudarthrosis the most severe pattern
- Emphasises the strong association of congenital tibial pseudarthrosis with NF1 and its recalcitrant, refracture-prone nature
- Also catalogues spinal (scoliosis/kyphosis, dural ectasia) and other skeletal manifestations of NF in children
Descriptive analysis of tibial pseudarthrosis in patients with neurofibromatosis 1
- Descriptive case-control analysis of 85 NF1 patients with long-bone pseudarthrosis from an international NF database
- ~5% of NF1 individuals have congenital long-bone pseudarthrosis, and 50-80% of congenital pseudarthrosis cases have NF1
- Significant MALE predominance with no parent-of-origin effect, suggesting male gender as a susceptibility factor
- Half of affected children sustained their fracture before age 2, and approximately 16% underwent amputation