Malignant Cartilage Tumor | Second Most Common Primary Bone Malignancy | Variable Biological Behavior
- CONVENTIONAL chondrosarcoma is resistant to chemotherapy and standard-dose radiotherapy - surgery is the only curative treatment. Say 'conventional': dedifferentiated and mesenchymal subtypes DO receive chemotherapy, and mesenchymal also receives radiotherapy
- Histological grade is the most important prognostic factor determining survival
- Distinguishing low-grade chondrosarcoma from enchondroma is challenging clinically and histologically
- Pelvis and proximal femur are most common sites - central (medullary) subtype predominates
- Pain in a previously asymptomatic cartilage lesion suggests malignant transformation
- “Chondrosarcoma is radio-resistant and chemo-resistant - wide surgical resection is mandatory
- “Pathological fracture is rare but indicates aggressive biology
- “Dedifferentiated chondrosarcoma has biphasic pattern: low-grade cartilage plus high-grade sarcoma
- “Pelvic chondrosarcomas have worse prognosis due to late presentation and difficulty achieving wide margins
Overview and Epidemiology
Chondrosarcoma is a malignant tumour whose cells produce cartilaginous matrix. It is the second most common primary malignant bone tumour after osteosarcoma, about 20% of primary bone malignancies, with an annual incidence of roughly 1 per million. Two things make it a different problem from the other bone sarcomas: the conventional form does not respond to chemotherapy or standard-dose radiotherapy, so surgery has to cure it, and at the low-grade end it is hard to tell from a benign enchondroma.
Who. The conventional type peaks at 50-70 years with a male predominance of 2:1. The clear cell and mesenchymal variants arise in younger patients, 20-40 years. Children are rarely affected, under 1% of cases.
Where. The pelvis and the upper femur (proximal femur and femoral shaft) dominate; the flat bones (the ribs, especially the costal cartilage, and the scapula) and the proximal humerus follow. Hands and feet are rare sites, the reverse of enchondroma.
- Frequency
- 30-40%
- Typical Grade
- Grade II-III
- Challenges
- Late presentation, difficult margins, higher recurrence
- Frequency
- 20-30%
- Typical Grade
- Grade I-II
- Challenges
- Reconstruction challenges, risk to neurovascular bundle
- Frequency
- 10-15%
- Typical Grade
- Grade I-II
- Challenges
- Chest wall resection, respiratory compromise
- Frequency
- 10%
- Typical Grade
- Grade I-II
- Challenges
- Brachial plexus proximity, rotator cuff sacrifice
Pathophysiology and Mechanisms
Cartilage biology and treatment resistance. Chondrosarcoma arises from malignant transformation of chondrocytes, and the tissue those cells make explains the treatments that fail. Cartilage matrix is avascular: no blood vessels penetrate it, so drugs reach the tumour cells poorly, the environment is hypoxic, which reduces the efficacy of radiotherapy, and drug-resistance proteins are highly expressed. The cells themselves have a low mitotic rate, especially in grade I lesions, and low metabolic activity, which contributes to the imaging patterns; they produce abundant matrix, proteoglycans and type II collagen, and grow as lobules separated by fibrous septa.
The avascular cartilage matrix is a physical barrier to chemotherapy drug delivery. Even a high-grade dedifferentiated chondrosarcoma receives chemotherapy for its non-cartilaginous high-grade component, not for the cartilage.
Primary and secondary tumours. Central chondrosarcoma arises de novo in previously normal bone in 75% of cases and by malignant transformation of an enchondroma in 25%; transformation of an osteochondroma is rare. Suspect a secondary tumour when a long-standing, asymptomatic cartilage lesion becomes painful or enlarges. Two premalignant settings, one central and one peripheral, must be known.
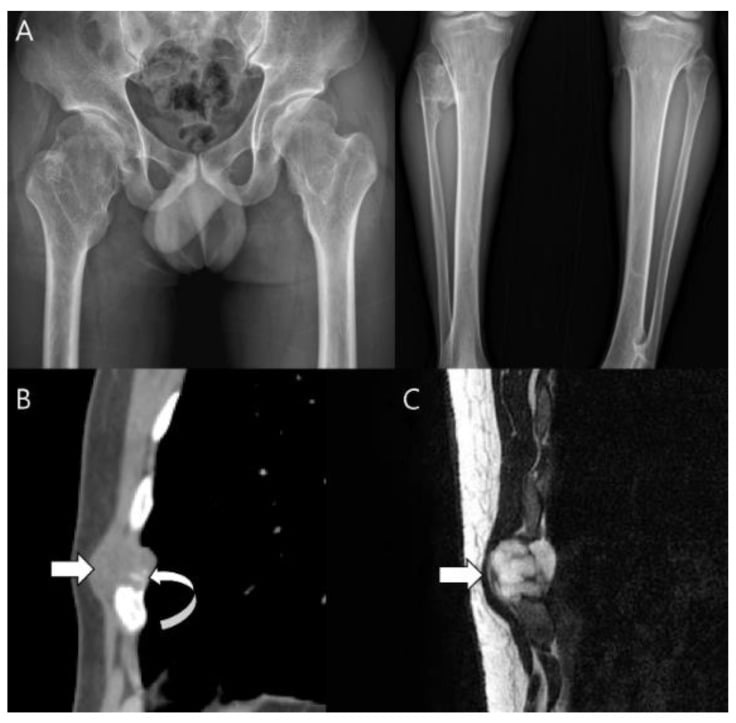
Central chondrosarcoma can arise from an enchondroma, and that risk is dramatically increased in the enchondromatosis syndromes. Ollier disease is multiple enchondromatosis — numerous enchondromas, typically asymmetric and limb-predominant, often causing deformity and limb-length discrepancy. Maffucci syndrome is enchondromatosis plus soft-tissue spindle-cell haemangiomas (look for the bluish subcutaneous nodules and phleboliths). Both are non-hereditary, sporadic conditions caused by somatic mosaic IDH1/IDH2 mutations (the same mutation that defines central cartilage tumours). The crucial point is malignant transformation: the lifetime risk of chondrosarcoma is high in Ollier (around 25-30%, higher with axial/pelvic disease) and even higher in Maffucci, which additionally carries a markedly raised risk of other (visceral, CNS, ovarian) malignancies. These patients therefore need lifelong surveillance, and any enchondroma that becomes painful, enlarges or develops aggressive imaging features must be assumed malignant until proven otherwise.
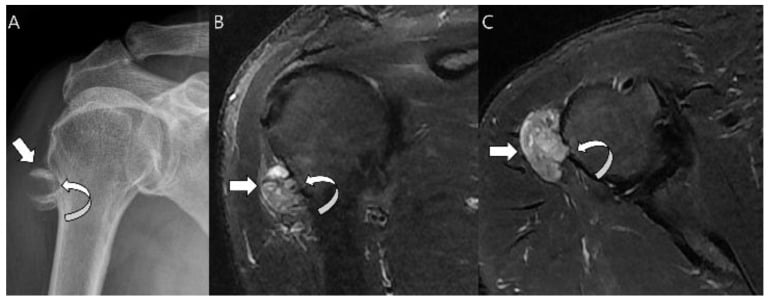
The second route to chondrosarcoma is malignant transformation of an osteochondroma into a secondary peripheral chondrosarcoma (distinct from the central tumours arising from enchondroma). The risk is low for a solitary osteochondroma (under about 1%) but substantially higher in Multiple Hereditary Exostoses (MHE / hereditary multiple osteochondromas, EXT1/EXT2), particularly for central lesions (pelvis, scapula, proximal femur). The single most useful warning sign is the cartilage cap thickness on MRI: a benign cap is thin (a few millimetres in a mature skeleton), whereas a cap thicker than about 1.5-2 cm in a skeletally mature patient strongly suggests transformation — alongside new pain, continued growth after skeletal maturity, and a soft-tissue mass. Biologically these peripheral tumours differ from central chondrosarcoma in that they are IDH-wild-type (the IDH mutation defines central, not peripheral, cartilage tumours). The exam point: in any osteochondroma — especially in MHE — growth or pain after skeletal maturity plus a thick cartilage cap means biopsy/excision, not reassurance.
Classification Systems
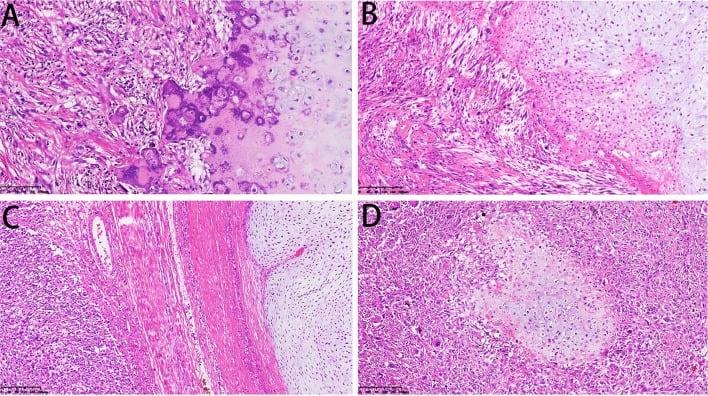
Histological grading. Grade is the most important prognostic factor for chondrosarcoma, correlating directly with survival, metastatic potential and local recurrence. It rests on cellularity, nuclear features and mitotic activity, and it needs adequate tissue and expert pathology: a needle biopsy can sample only the low-grade areas of a heterogeneous tumour, and up to 10% of tumours show grade progression in different areas, which is why the biopsy is aimed at the most aggressive-looking part of the lesion (Investigations).
- Cellularity
- Mildly increased
- Nuclear Features
- Minimal atypia, small nuclei
- Mitoses
- Absent to rare
- Cellularity
- Moderately increased
- Nuclear Features
- Moderate atypia, enlarged nuclei
- Mitoses
- Occasional
- Cellularity
- Markedly increased
- Nuclear Features
- Severe atypia, pleomorphic
- Mitoses
- Frequent
Nomenclature. WHO now calls a grade I lesion in a long bone an atypical cartilaginous tumour (ACT), deliberately reserving "chondrosarcoma grade 1" for the axial skeleton and pelvis, because behaviour differs by site. The treatment consequence of that split is set out under Management.
Subtypes. Central (conventional) chondrosarcoma accounts for 85% of cases; the four variants that follow are rare, and each breaks one of the conventional tumour's rules, of site, age, grade or treatment.
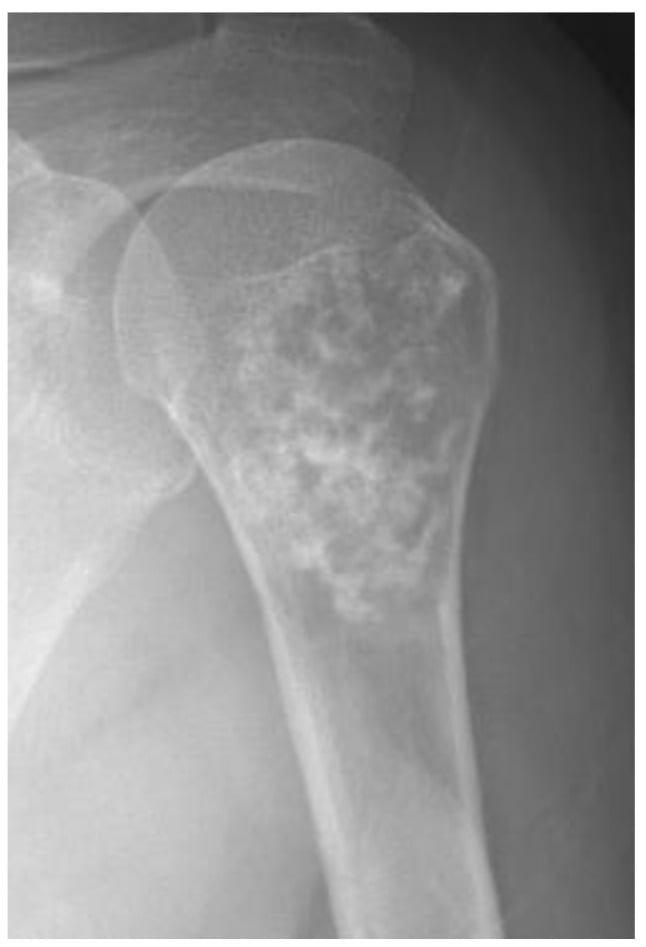
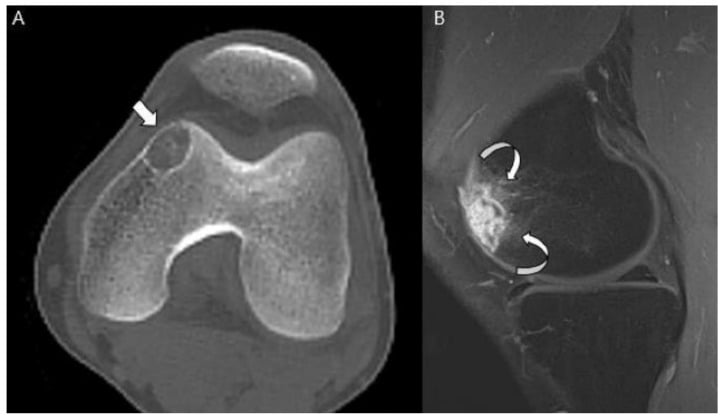
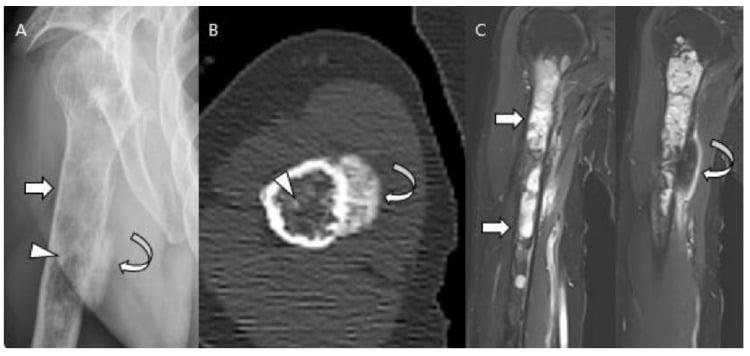
Central (conventional) chondrosarcoma arises in the medullary cavity, peaks at 50-70 years and favours the pelvis and proximal long bones. Histologically it is lobulated hyaline cartilage. On imaging it is a central medullary lesion with rings-and-arcs calcification and endosteal scalloping; a soft-tissue mass appears in the higher grades.
Staging
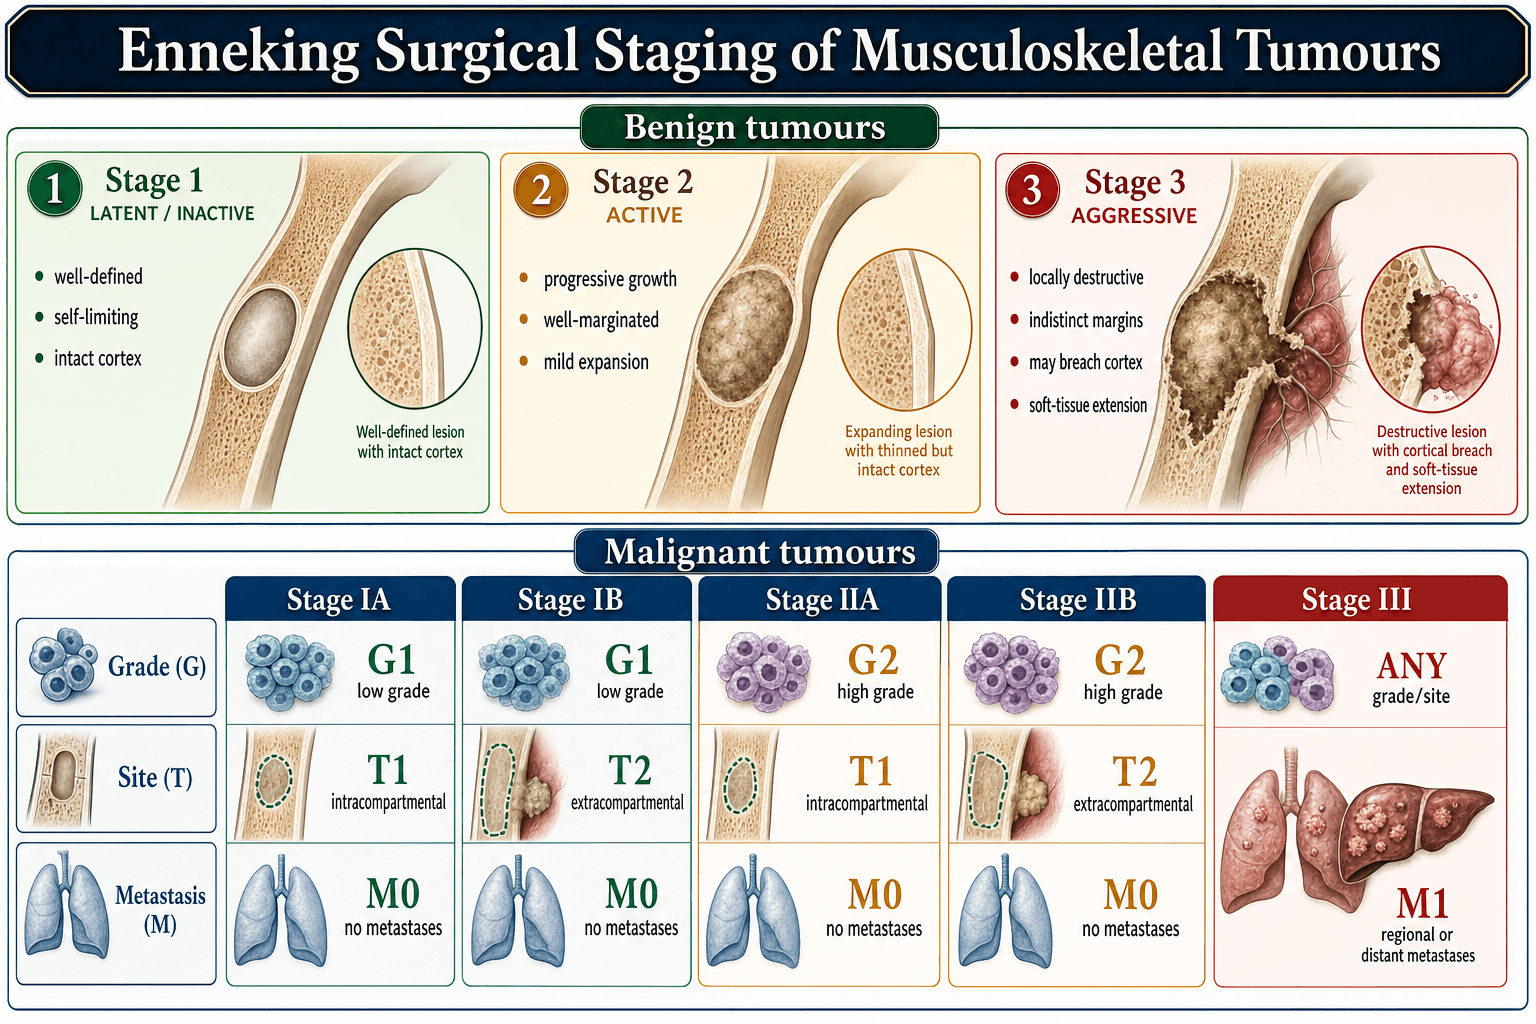
Chondrosarcoma is staged with the Enneking system for musculoskeletal sarcomas, which combines grade, compartment and metastasis into a stage that predicts survival. A tumour is intracompartmental (T1) while it is confined within the cortex or a single anatomic compartment, and extracompartmental (T2) once it extends beyond the cortex into the soft tissues or crosses a major fascial plane.
- Grade
- Low (G1)
- Site
- Intracompartmental (T1)
- Metastases
- None (M0)
- 5-Year Survival
- Greater than 90%
- Grade
- Low (G1)
- Site
- Extracompartmental (T2)
- Metastases
- None (M0)
- 5-Year Survival
- 80-90%
- Grade
- High (G2-G3)
- Site
- Intracompartmental (T1)
- Metastases
- None (M0)
- 5-Year Survival
- 50-70%
- Grade
- High (G2-G3)
- Site
- Extracompartmental (T2)
- Metastases
- None (M0)
- 5-Year Survival
- 30-50%
- Grade
- Any
- Site
- Any
- Metastases
- Present (M1)
- 5-Year Survival
- Under 20%
Clinical Presentation
Symptoms. Pain, dull and aching, is the presenting complaint in 70-80% of patients and a palpable mass in 50%. Pathological fracture is rare, 5-10%, but signals aggressive biology, and some lesions are incidental findings on imaging done for something else. Progression is slow, over months to years; rapid onset of symptoms points to a higher-grade lesion, and pelvic tumours present late because of their deep location.
When a cartilage lesion has turned. New pain in a previously asymptomatic cartilage lesion, or pain that progresses despite conservative treatment, suggests malignant transformation. Age over 40 with a new cartilage lesion, an axial or proximal long-bone site (enchondromas favour the hands) and cortical destruction or a soft-tissue mass all point the same way; the size and scalloping thresholds are under Investigations.
Examination. A mass, when present, is firm, deep and fixed to bone, with tenderness over the lesion; movement may be restricted if the lesion is juxta-articular, and deformity or crepitus mark the rare pathological fracture. The patient is usually systemically well, lymph nodes are not typically involved and metastases are rare at presentation, but examine the chest and record the neurovascular status, assessing for compression.
Investigations and Imaging
Radiographs first. Two orthogonal views of the entire bone. The signs to name:
- Matrix: rings-and-arcs (popcorn) calcification
- Endosteal scalloping: greater than two-thirds of the cortical thickness suggests malignancy
- Cortical destruction in the higher grades
- Soft-tissue mass, mineralised in the higher grades
- Pathological fracture, rare but a marker of aggressive biology
Location helps too: the central type is metaphyseal or diaphyseal, clear cell is epiphyseal.
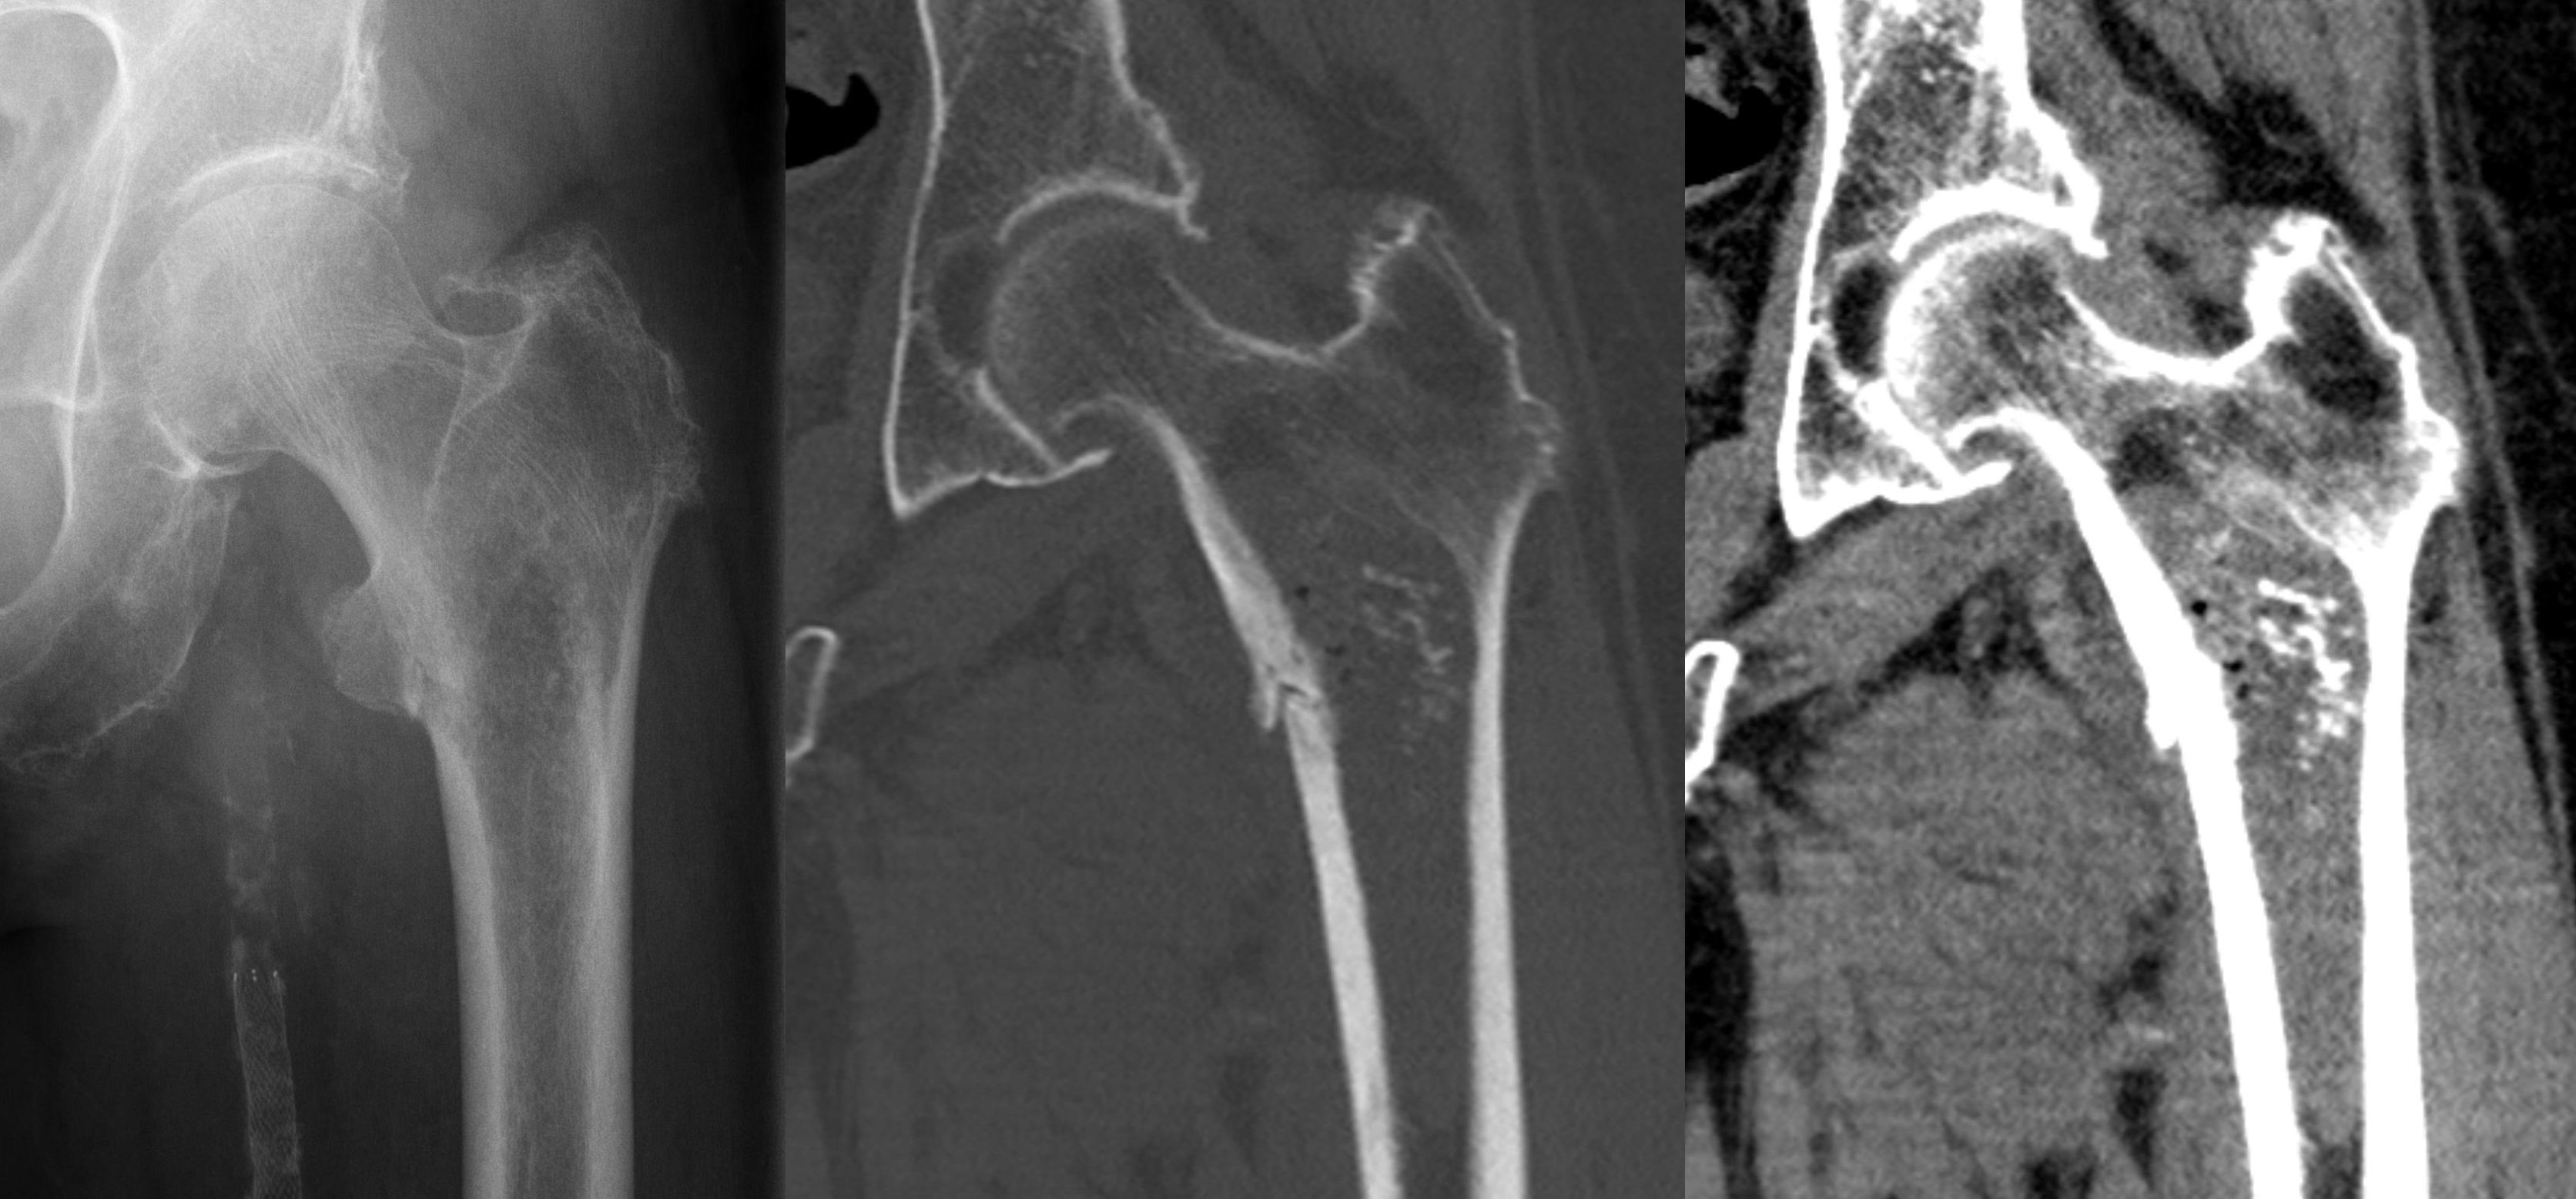
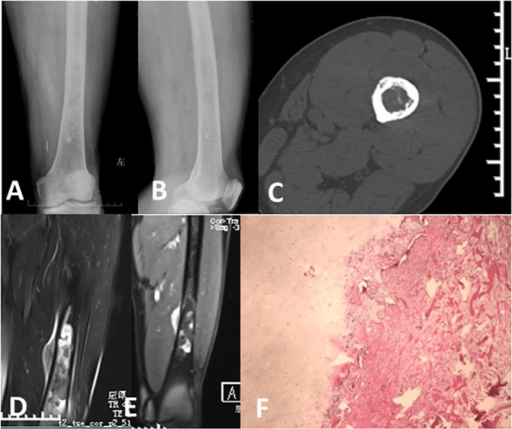
MRI of the whole bone is the gold standard for local staging, with the joint above and below in the field. Cartilage is low signal on T1 and high, lobulated signal on T2 and STIR, with septal and nodular enhancement after contrast. The scan has to answer five questions:
- Extent of medullary involvement
- Cortical destruction and soft-tissue extension
- Neurovascular encasement
- Joint invasion, which contraindicates limb salvage
- Skip lesions, rare in chondrosarcoma
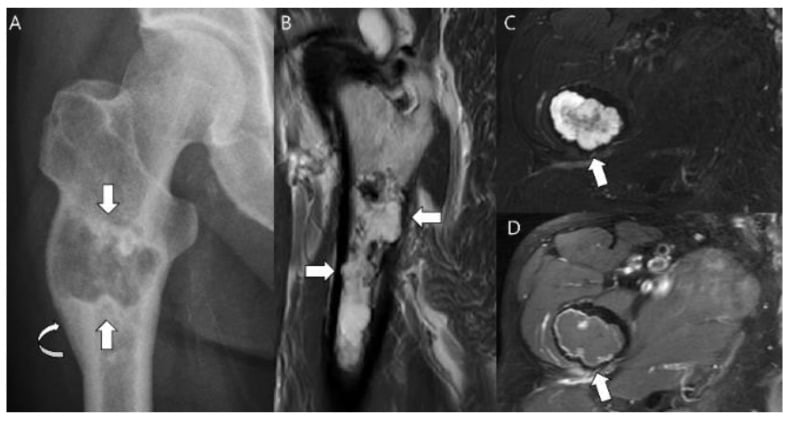
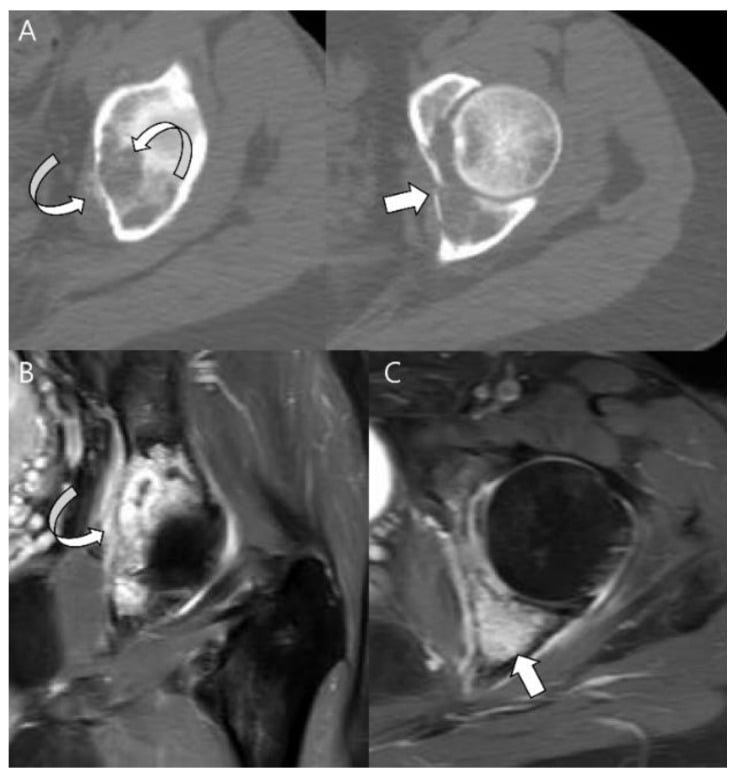
Staging the chest and the skeleton. A high-resolution CT chest looks for lung metastases, the site of 90% of metastases. PET-CT is useful for detecting metastases and for assessing grade, since the SUV is higher in high-grade tumours; a bone scan may show uptake, more commonly in a malignant lesion than in an enchondroma; a skeletal survey is the alternative in paediatric patients.
Biopsy. Core needle biopsy is preferred, performed by or in consultation with the treating surgeon, and it has to obey the rules that protect the later resection:
- Longitudinal approach in line with the definitive incision
- Avoid neurovascular structures
- Sample the most aggressive area, using the imaging to choose it: highest T2 signal, cortical destruction, soft-tissue mass
- Adequate tissue, with multiple cores from different areas if the tumour is heterogeneous
- Frozen section is not reliable for grading chondrosarcoma
The biopsy tract must be excised en bloc with the definitive resection. A poorly planned biopsy can compromise limb salvage surgery, so every biopsy is performed at, or in consultation with, the sarcoma treatment centre.
Imaging Features: Enchondroma vs Chondrosarcoma
- Enchondroma (Benign)
- Hands and feet (60%), asymptomatic
- Chondrosarcoma (Malignant)
- Pelvis, proximal femur, ribs (axial skeleton)
- Enchondroma (Benign)
- Usually under 3-4cm
- Chondrosarcoma (Malignant)
- Often greater than 5cm
- Enchondroma (Benign)
- Absent (unless pathological fracture)
- Chondrosarcoma (Malignant)
- Present in 70-80% (dull, aching)
- Enchondroma (Benign)
- Less than one-third cortical thickness
- Chondrosarcoma (Malignant)
- Greater than two-thirds cortical thickness
- Enchondroma (Benign)
- Intact or mildly thinned
- Chondrosarcoma (Malignant)
- Destroyed or breached (higher grades)
- Enchondroma (Benign)
- Absent
- Chondrosarcoma (Malignant)
- Present in Grade II-III
- Enchondroma (Benign)
- No uptake or minimal
- Chondrosarcoma (Malignant)
- Uptake present (more intense in higher grades)
- Enchondroma (Benign)
- Lobulated high signal, thin septa
- Chondrosarcoma (Malignant)
- Thick irregular septa, nodular soft tissue component
PESTFeatures Suggesting Malignancy (Enchondroma vs Chondrosarcoma)
Hook:When an enchondroma becomes a PEST (painful, eroding, sizable, and tracer-positive), suspect chondrosarcoma!
Differential Diagnosis
- Key Distinguishing Features
- Hands/feet, asymptomatic, small (under 3-4cm), scalloping under one-third cortex, no soft tissue mass
- Discriminator
- Painless, peripheral, IDH-mutant but no aggressive features
- Key Distinguishing Features
- Epiphyseal, skeletally immature patient, painful, fine matrix, H3K36M mutation
- Discriminator
- Younger age and epiphyseal location overlap with clear cell subtype
- Key Distinguishing Features
- Surface lesion, marrow/cortex continuity; cap over 1.5-2cm or growth after skeletal maturity suggests secondary peripheral chondrosarcoma
- Discriminator
- Cartilage cap thickness on MRI is the key alarm sign
- Key Distinguishing Features
- Younger patient, aggressive periosteal reaction, malignant osteoid, more lytic/permeative
- Discriminator
- Tumour osteoid production and IDH wild-type
- Key Distinguishing Features
- Serpentine sclerotic rim, no endosteal scalloping, no soft tissue mass, often asymptomatic
- Discriminator
- Lacks deep scalloping and aggressive features
- Key Distinguishing Features
- Sacrum/clivus, midline, lytic with soft tissue mass, brachyury positive
- Discriminator
- Midline axial location and immunoprofile
Management
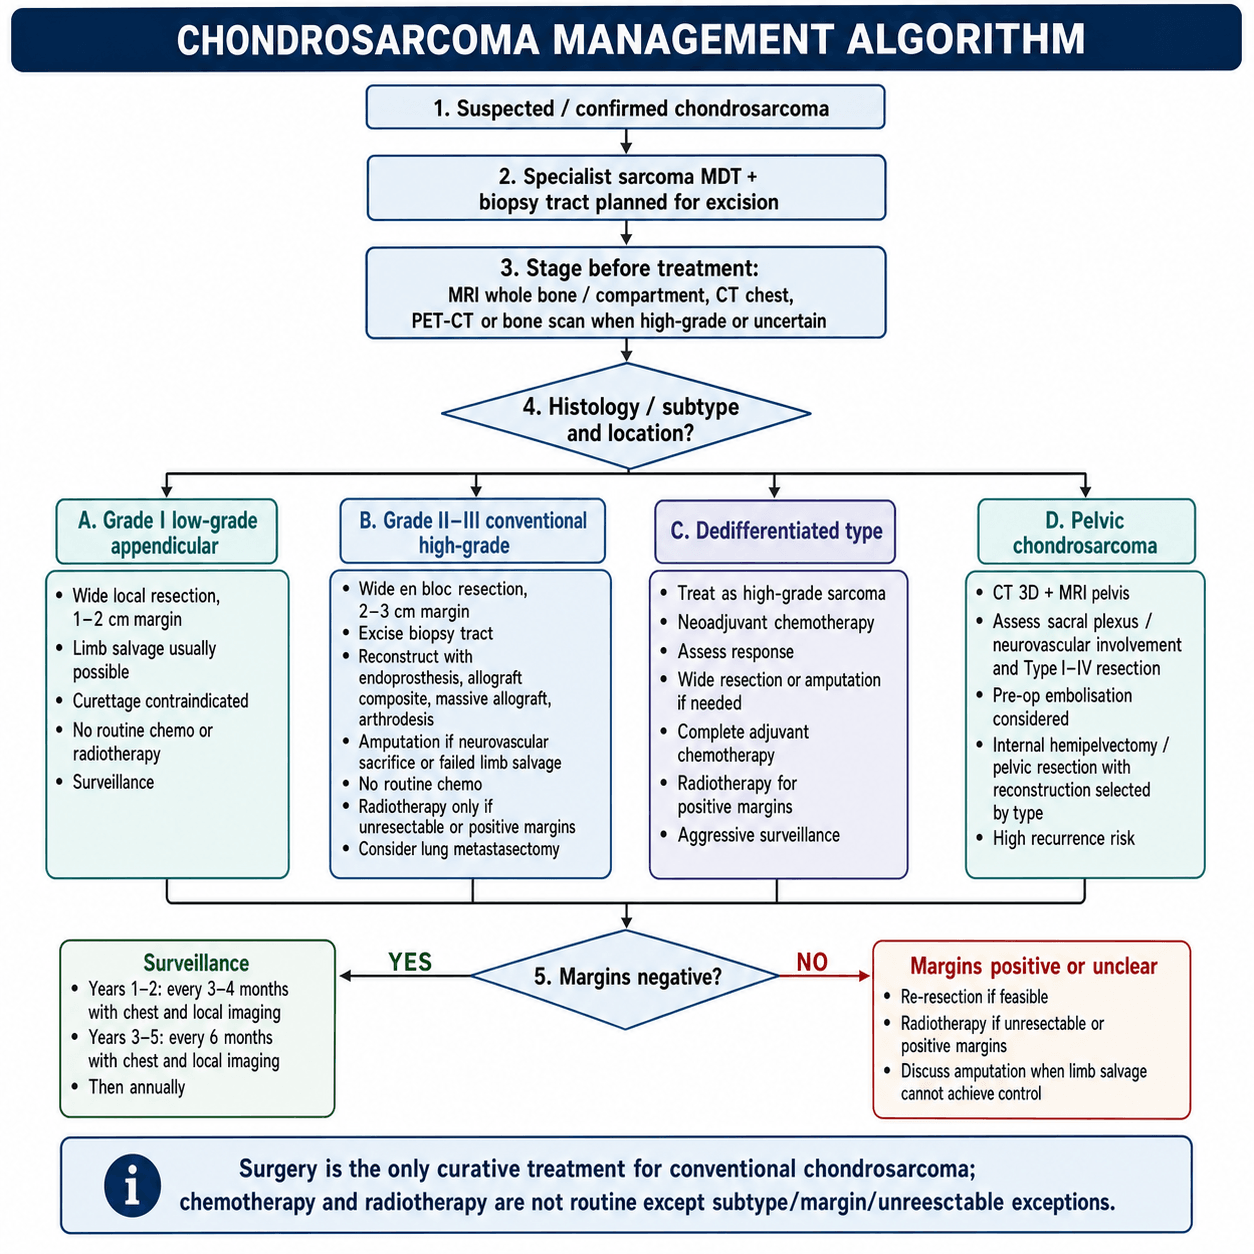
Two subtypes, not one. Conventional chondrosarcoma of any grade does not respond to chemotherapy, so wide resection with negative margins is the treatment - but dedifferentiated AND mesenchymal chondrosarcoma are both treated with it, and it is a mistake to name only the first.
- Dedifferentiated: the high-grade non-cartilaginous component (osteosarcoma, fibrosarcoma or undifferentiated pleomorphic sarcoma) is what may respond, so the regimen is an osteosarcoma-type one directed at that component rather than at the cartilage. Benefit remains modest and the prognosis stays poor.
- Mesenchymal: the small round blue cell tumour with islands of hyaline cartilage and the HEY1-NCOA2 fusion. It is treated with Ewing-type chemotherapy, and series consistently report better outcomes in patients who receive surgery plus chemotherapy. Radiotherapy also has a role in this subtype, which is the other exception to the usual teaching.
Put the exceptions in the same breath as the rule. A candidate who says "chondrosarcoma is chemoresistant" and stops has given an answer that would undertreat the one subtype most likely to benefit.
Treatment by Grade and Location
The goal is cure with negative margins and preserved function, and, for the long-bone lesion, no more surgery than the tumour needs. Stage with MRI of the entire bone and a CT chest, and consider PET-CT if the diagnosis is uncertain.
Where the site decides the operation. A grade I tumour of the axial skeleton or a flat bone, and any lesion with soft-tissue extension, is treated by wide resection with a 1-2cm margin; limb salvage is usually achievable and the defect is reconstructed with an allograft, an endoprosthesis or an arthrodesis. A grade I lesion of a long bone that is confined to bone is an atypical cartilaginous tumour, and for it intralesional curettage with an adjuvant, or observation, is an evidence-supported option, as the warning below sets out. There is no adjuvant treatment: chemotherapy is ineffective, and radiotherapy is reserved for the unresectable tumour with positive margins. Surveillance follows the schedule under Postoperative Care.
The old teaching that every chondrosarcoma, including grade I, needs a wide resection is out of date for the appendicular skeleton, and following it causes real harm - a segmental defect and reconstruction instead of a curettage in a tumour that rarely metastasises. The WHO split between the atypical cartilaginous tumour of a long bone and chondrosarcoma grade 1 of the axial skeleton exists because the evidence follows the same split:
- Long bone, confined to bone (Enneking IA): intralesional curettage with an adjuvant is a safe and reasonable option - 5-year disease-free survival was 97.0% in 37 long-bone lesions treated this way, with a mean MSTS score of 27.9.
- Flat bone (pelvis, scapula, ribs), or any lesion with soft-tissue extension (Enneking IB): this is where curettage fails. Disease-free survival fell to 80.0% in flat bones (p=0.001), and every recurrence in the series had presented with soft-tissue extension. These need wide resection.
Observation is also a legitimate option, not a fringe view. Among 228 patients with radiologically aggressive long-bone cartilage lesions, 153 observed and 75 curetted, MSTS scores were essentially identical (97% versus 96%) but the observed group had significantly FEWER functional limitations - and for lesions over 4.4 cm surgery was significantly worse on both function and pain. The authors concluded that more of these lesions could simply be watched, provided follow-up is guaranteed.
The figure sometimes quoted for recurrence after intralesional treatment of low-grade disease - anything approaching 50% or more - does not match these series, where recurrence after curettage was in the low single figures for long-bone lesions confined to bone. Reserve wide resection for the axial skeleton, flat bones, soft-tissue extension, and any lesion that is not truly low grade.
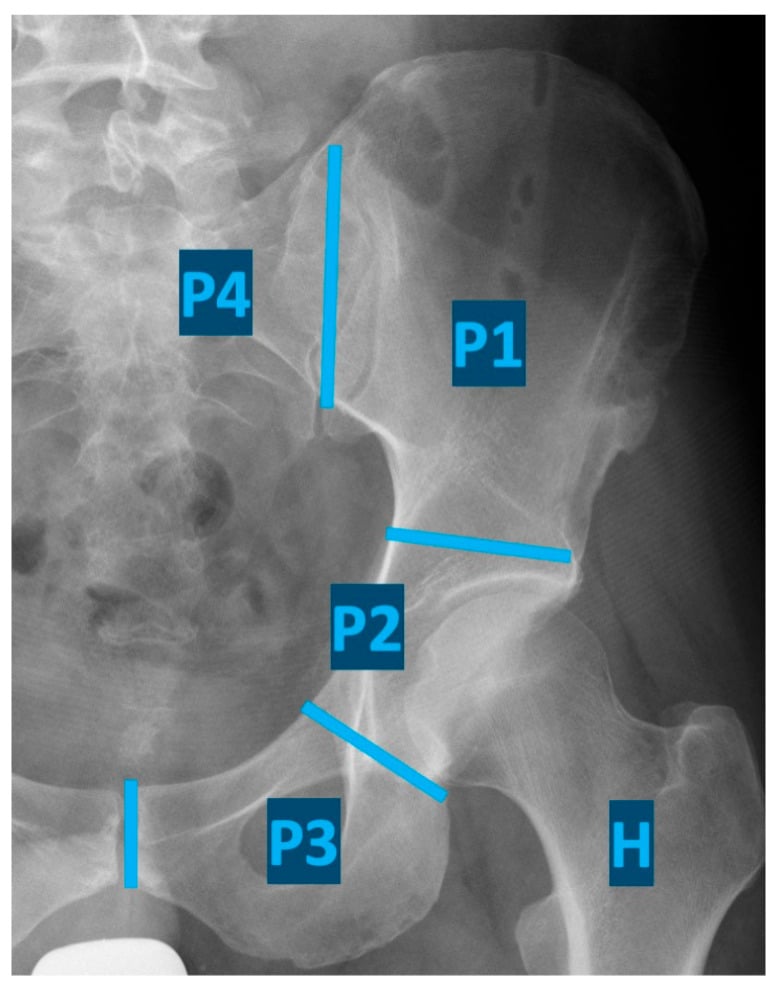
Role of Radiotherapy
Conventional chondrosarcoma does not respond to standard radiation doses, which is the accurate form of the "radio-resistant" claim and the reason radiotherapy is not standard treatment; conventional photon radiotherapy gives local control in under 50%. Where it is used, the dose has to be high: 60-70 Gy with conventional photons, 70-80 CGE with protons. Proton beam therapy is the technique for skull-base lesions, and carbon-ion radiotherapy is emerging.
The indications are therefore few:
- Unresectable tumours (skull base, axial spine), where high-dose proton or carbon-ion therapy achieves control that photons at conventional doses do not
- Positive margins when re-resection is not feasible
- Palliation of metastases
- Mesenchymal chondrosarcoma, the subtype routinely given Ewing-type chemotherapy and radiotherapy rather than surgery alone
State the mesenchymal evidence carefully. Xu's systematic review of 107 patients (PMID 25849226) found that neither anthracycline-based chemotherapy nor radiotherapy was associated with overall survival, and recommended radiotherapy specifically as salvage for a positive margin to improve local control. Radiotherapy for this subtype is standard practice by extrapolation from small round cell biology, not a demonstrated adjuvant survival benefit, and the negative margin remains the part with evidence behind it.
Surgical Technique
Imaging for the plan. The whole-bone MRI defines the extent and the soft-tissue involvement; a CT shows the cortical destruction and sets the osteotomy levels; for pelvic lesions add angiography, with preoperative embolisation in mind, and a 3D reconstruction, which is essential for a complex pelvic resection.
The plan itself. Margins of 1-2cm for grade I and 2-3cm for the higher grades, en bloc excision of the biopsy tract, a reconstruction strategy chosen in advance (endoprosthesis, allograft or arthrodesis), and blood: type and cross 4-6 units, more for a pelvic resection.
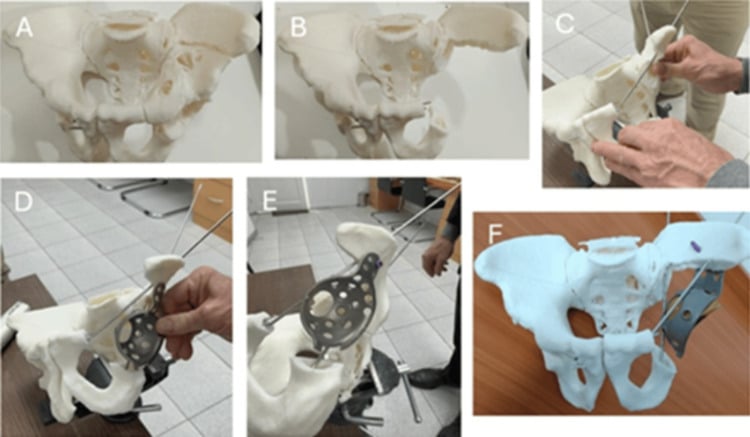
Intraoperative frozen section is UNRELIABLE for assessing margins in chondrosarcoma. Cartilage matrix is difficult to section, and distinguishing normal cartilage from grade I chondrosarcoma is challenging even on permanent sections. Plan adequate margins from the preoperative imaging.
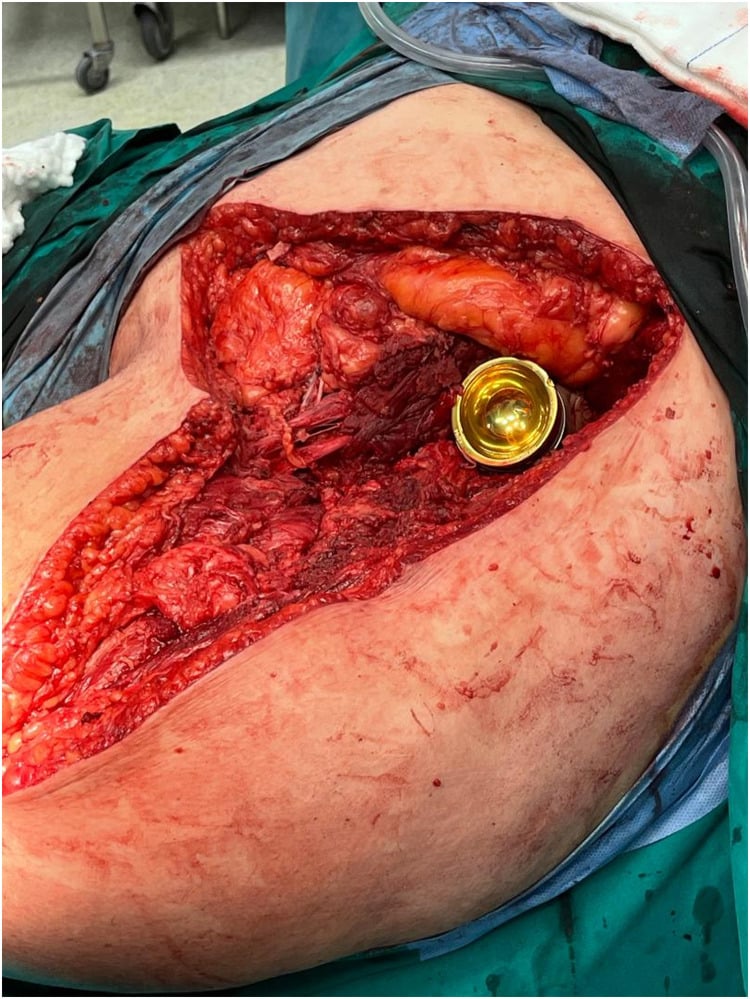
Complications
- Incidence
- Margin-dependent (see Management)
- Risk Factors
- Positive margins, high grade, inadequate resection
- Management
- Re-resection if feasible, amputation for failed limb salvage
- Incidence
- 5-15% (higher for pelvic resections)
- Risk Factors
- Massive reconstruction, pelvic surgery, diabetes
- Management
- Antibiotics, debridement, implant retention if possible
- Incidence
- 5-10%
- Risk Factors
- Pelvic location, tumour encasement
- Management
- Intraoperative recognition and repair, accept deficit if planned sacrifice
- Incidence
- 5-10% for endoprosthesis
- Risk Factors
- Abductor sacrifice, large head size, patient factors
- Management
- Closed reduction, constrained liner, revision if recurrent
- Incidence
- 15-20% at 10 years
- Risk Factors
- High-impact activities, slow incorporation, osteoporosis
- Management
- Protected weight-bearing initially, ORIF if fracture occurs
- Incidence
- Grade-dependent (see Prognosis)
- Risk Factors
- High grade, positive margins, local recurrence
- Management
- Surveillance CT chest, metastasectomy if resectable oligometastatic disease
Local recurrence is the most common cause of treatment failure, and inadequate surgical margins are its primary cause. Most recurrences (70%) occur within the first 3 years, the average time to recurrence being 2-3 years with a range of 6 months to 10 years, but late recurrences beyond 5 years are possible. Re-resection of a positive margin should be strongly considered.
Postoperative Care and Rehabilitation
The two reconstructions rehabilitate differently for one reason: a metal implant is stable the moment it is fixed, whereas an allograft has to incorporate and remodel before it can be loaded. That difference sets the weight-bearing rule in each protocol.
Rehabilitation Timeline
- DVT prophylaxis (LMWH for 6 weeks)
- Wound drain removed when output is under 30ml per 24 hours
- Mobilise on day 1-2 with physiotherapy
- Hip precautions after a proximal femoral replacement (no flexion over 90 degrees)
- Immediate weight-bearing as tolerated: the endoprosthesis is stable at once
- Gait training with walking aids
- Range-of-motion exercises within precautions
- Sutures removed at 2-3 weeks; watch for infection and dislocation
- Wean walking aids as strength improves
- Progressive resistance exercises
- Return to daily activities (driving at 6-8 weeks if safe)
- No high-impact activity (running, jumping), lifelong
- Maintain muscle strength and joint range
- Low-impact activities encouraged (swimming, cycling)
- Lifelong avoidance of high-impact sport
Surveillance Protocol
The schedule. Every visit is a clinical examination, a chest radiograph (PA and lateral) and local imaging (radiograph or MRI), with a CT chest if there is anything concerning. The interval lengthens as the risk falls, but it never reaches zero:
- Years 1-2: every 3 months, the highest-risk period
- Years 3-5: every 6 months
- Beyond 5 years: annually, for life, because late recurrences are possible
The reconstruction is watched too. Annual radiographs look for loosening, wear and subsidence of an endoprosthesis, and for fracture, nonunion and collapse of an allograft, with earlier imaging for pain or functional decline.
Prognosis and Outcomes
Histological grade is the single most important prognostic factor for chondrosarcoma, more important than size or anatomic location: in the 227-patient series, high-grade lesions showed significantly more pathological fracture, metastasis, recurrence and death (all p less than 0.001; PMID 10199270). That is why adequate biopsy tissue for accurate grading matters so much.
On the grade-specific survival percentages: the figures repeated everywhere (roughly 90% for grade I falling to under a third for grade III) trace to Evans' 1977 series, which has no abstract indexed and whose exact numbers differ between sources. Quote them as the classically taught set, not as a measured fact - and if pressed, give the figures that ARE verifiable: 70% survival at 10 years and 63% at 15 years in 153 non-metastatic patients (PMID 11837841), against 24% at 5 years for dedifferentiated disease (PMID 17720491).
- Favourable Prognosis
- Grade I (low-grade)
- Unfavourable Prognosis
- Grade III or dedifferentiated
- Favourable Prognosis
- Appendicular skeleton (extremities)
- Unfavourable Prognosis
- Axial skeleton (pelvis, spine, ribs)
- Favourable Prognosis
- Wide negative margins (greater than 2cm)
- Unfavourable Prognosis
- Intralesional or positive margins
- Favourable Prognosis
- Less than 5cm
- Unfavourable Prognosis
- Greater than 10cm
- Favourable Prognosis
- Under 40 years
- Unfavourable Prognosis
- Over 60 years
- Favourable Prognosis
- None (M0)
- Unfavourable Prognosis
- Present (M1) - lungs, bone
- Favourable Prognosis
- Periosteal or clear cell
- Unfavourable Prognosis
- Dedifferentiated or mesenchymal
Where it spreads. The lungs take 90% of metastases and bone the remaining 10%, the latter especially with the higher grades, and metastases can appear late, 5-10 years after resection. The metastatic rate rises with grade, as the table shows.
- 5-Year Survival
- 90-95%
- 10-Year Survival
- 90%
- Metastatic Rate
- 5-10%
- 5-Year Survival
- 70-85%
- 10-Year Survival
- 81%
- Metastatic Rate
- 25-30%
- 5-Year Survival
- 35-55%
- 10-Year Survival
- 29%
- Metastatic Rate
- 70-75%
- 5-Year Survival
- 10-25%
- 10-Year Survival
- Under 10%
- Metastatic Rate
- Over 90%
The company it keeps, and what it must not be mistaken for. The hardest call in cartilage pathology is grade I chondrosarcoma against enchondroma - the same lesion menu that makes Ollier disease and Maffucci syndrome matter, since both carry a real malignant transformation risk. On the surface of bone the differential is osteochondroma and its secondary chondrosarcoma. At the aggressive end, dedifferentiated chondrosarcoma is effectively a different disease with a different survival curve, and the biopsy that decides all of this must follow biopsy principles - because a badly placed tract contaminates the resection this tumour depends on.
Guidelines, Registries & Global Practice
Global Epidemiology
Chondrosarcoma is the most common primary bone sarcoma in adults and the second most common primary bone malignancy overall (after osteosarcoma), with an annual incidence of roughly 1 per million population worldwide. Population-based registry data (SEER) confirm a steep prognostic gradient by subtype: median survival ranges from around 97 months for juxtacortical lesions down to only about 11 months for dedifferentiated tumours, with metastatic disease at diagnosis the dominant independent predictor of death across all subtypes (Amer et al., J Orthop Res 2020 — PMID 31498474).
- Region
- Europe
- Core Recommendation
- Refer to a bone-sarcoma reference centre before biopsy; en bloc wide resection; no routine chemo/radiotherapy for conventional chondrosarcoma
- Evidence Basis
- Expert consensus, registry and cohort data
- Region
- UK
- Core Recommendation
- Mandatory specialist-centre management and sarcoma MDT; suspected bone tumour referral pathway; surgery is primary treatment
- Evidence Basis
- Guideline + service-configuration evidence
- Region
- USA
- Core Recommendation
- Wide excision for resectable disease; consider particle (proton/carbon-ion) RT for unresectable/axial; chemo only for mesenchymal and dedifferentiated subtypes
- Evidence Basis
- Category 2A consensus
- Region
- Global
- Core Recommendation
- Atypical cartilaginous tumour (ACT) terminology for grade-1 appendicular lesions; reserve 'chondrosarcoma' grade 1 for axial sites
- Evidence Basis
- Molecular + histological consensus
All chondrosarcomas should be managed at a designated bone-sarcoma reference centre and discussed at a sarcoma MDT BEFORE biopsy. This is a near-universal principle across guidelines (ESMO, NICE/BOA, NCCN).
- Poorly planned biopsy contaminates tissue planes and compromises limb salvage
- Reference-centre care is independently associated with better local control and survival
- National sarcoma networks (e.g. UK sarcoma MDTs, European EURACAN/EMSOS centres, US NCI-designated centres) coordinate rare-tumour care
Because chondrosarcoma is rare, most high-quality outcome data come from bone-tumour registries and multi-institutional collaboratives, not RCTs:
- EMSOS (European Musculo-Skeletal Oncology Society) - source of the 337-patient dedifferentiated series
- SEER (USA) - population-level subtype survival benchmarks
- National bone-sarcoma registries contribute to international collaborative trials
Practice Variation
- Variation
- Many centres now use intralesional curettage plus local adjuvant; others retain wide resection
- Rationale
- Low metastatic risk and good local control with curettage in expendable appendicular sites; axial lesions still need wide resection
- Variation
- Available in select European, Japanese and US centres; absent in many regions
- Rationale
- High-dose particle RT improves local control in unresectable skull-base/axial disease but is resource-intensive
- Variation
- Higher rates of amputation and late presentation; limb salvage less available
- Rationale
- Limited access to imaging, endoprostheses, allograft banks and specialist MDTs
Key documentation and consent points:
- Diagnosis delay litigation: Pain in cartilage lesion requires investigation - document imaging and biopsy decisions
- Biopsy tract contamination: Document MDT discussion and biopsy planning by sarcoma surgeon
- Margin status: Intraoperative frozen sections, document decision-making if margins compromised
- Amputation consent: Discuss possibility of amputation before limb salvage surgery if margins cannot be achieved
- Prognosis discussion: Document discussion of grade-specific survival rates
- Surveillance protocol: Provide written follow-up schedule and emphasize importance of compliance
Multidisciplinary Team Composition
Essential members:
- Orthopaedic oncologist (surgeon)
- Medical oncologist
- Radiation oncologist
- Musculoskeletal radiologist
- Musculoskeletal pathologist
- Specialist oncology nurse
- Physiotherapist, occupational therapist
- Psychologist, social worker
MCQ Practice Points
Q: Which statement about chondrosarcoma epidemiology is correct? A: Chondrosarcoma accounts for 20% of primary bone malignancies, making it the second most common after osteosarcoma. Peak age is 50-70 years with male predominance 2:1. Most common sites are pelvis (30-40%) and proximal femur (20-30%).
Q: What is the most important prognostic factor in chondrosarcoma? A: Histological grade is the single most important prognostic factor - more important than size or anatomic location. The classically taught survival set is roughly 90% for grade I, 81% for grade II and under a third for grade III; treat those as traditional teaching (they derive from a 1977 series with no indexed abstract and vary between sources) rather than as measured values. What is verifiable and worth quoting alongside: 70% at 10 years and 63% at 15 years in non-metastatic disease (PMID 11837841), and 24% at 5 years once dedifferentiated (PMID 17720491). Grade is more important than size or anatomic location in determining prognosis.
Q: Why is chemotherapy not used for conventional chondrosarcoma? A: Conventional chondrosarcoma is resistant to both chemotherapy and radiotherapy due to poor vascularity of cartilage matrix and low cell turnover. Wide surgical resection is the ONLY curative treatment. Exception: Dedifferentiated and mesenchymal subtypes receive chemotherapy.
Q: Which chondrosarcoma subtype has the worst prognosis? A: Dedifferentiated chondrosarcoma has the worst prognosis with only 7-24% 5-year survival. It shows biphasic pattern: low-grade cartilage plus high-grade non-cartilaginous sarcoma. Treated with neoadjuvant chemotherapy unlike conventional chondrosarcoma.
Q: What imaging features help distinguish chondrosarcoma from enchondroma? A: Features suggesting malignancy (PEST mnemonic): Pain, Endosteal scalloping greater than two-thirds cortical thickness, Size greater than 5cm, Tracer uptake on bone scan or PET. Also: axial skeleton location, soft tissue mass, and age over 40 years.
Q: What is the local recurrence rate with positive margins after chondrosarcoma resection? A: Positive margins increase local recurrence from under 10% (negative margins) to 40-60% (positive margins). Margin status is the most important surgical factor for local control. Re-resection should be considered if anatomically feasible.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 55-year-old man presents with mild thigh pain for 6 months. X-ray shows a 6cm lobulated lesion in the proximal femoral metaphysis with rings and arcs calcification and endosteal scalloping involving two-thirds of the cortical thickness. What is your assessment and management?”
“A 65-year-old woman presents with severe hip pain and a large palpable mass. Imaging shows a large pelvic mass with two components: a mineralized chondroid lesion in the ilium plus an adjacent non-mineralized aggressive soft tissue mass. Biopsy shows low-grade cartilage with areas of high-grade pleomorphic sarcoma. What is your diagnosis and management?”
“You have resected a Grade II chondrosarcoma of the distal femur with endoprosthetic reconstruction. Final pathology reports positive margins posteriorly where tumor abuts the popliteal vessels. How do you manage this?”
Key Pathology
- Second most common primary bone malignancy (20%)
- Malignant cartilage-forming tumor - rings and arcs calcification
- Histological grade is most important prognostic factor
- Grade I ~90% vs Grade III under a third - classically taught figures; verifiable: 70% at 10yr non-metastatic, 24% at 5yr if dedifferentiated
- Conventional type 85%, dedifferentiated worst prognosis (7-24% 5-year survival)
Clinical Presentation
- Pain in cartilage lesion (70-80%) - key symptom
- Pelvis 30-40%, proximal femur 20-30% - central (medullary) subtype
- Peak age 50-70 years, male predominance 2:1
- PEST features suggest malignancy: Pain, Endosteal scalloping, Size greater than 5cm, Tracer uptake
Imaging Protocol
- X-ray: Rings and arcs calcification, endosteal scalloping greater than two-thirds
- MRI entire bone: T2 high signal lobulated, assess extent and soft tissue invasion
- CT chest: Staging for lung metastases (90% of metastases)
- Core needle biopsy: Adequate tissue from most aggressive area (high T2, cortical destruction)
Treatment Principles
- Surgery is ONLY curative treatment - chemo-resistant and radio-resistant
- Wide resection with 1-2cm margins - intralesional curettage reserved for a long-bone atypical cartilaginous tumour confined to bone
- Positive margins: 40-60% recurrence vs negative margins under 10%
- Dedifferentiated type: ONLY subtype receiving chemotherapy (neoadjuvant)
- Radiotherapy: Only for unresectable or positive margins (60-70 Gy)
Prognostic Factors
- Histological grade: the dominant factor (high grade: more fracture, metastasis, recurrence and death, all p<0.001, PMID 10199270)
- Anatomic site: Pelvic worse than appendicular (30-60% vs 70-90% 5-year survival)
- Margin status: Negative margins essential (positive margins increase recurrence 10% to 40-60%)
- Subtypes: Periosteal best, dedifferentiated worst prognosis
Evidence Base and Key Studies
Prognostic Factors in Chondrosarcoma of Bone: A Clinicopathologic Analysis with Emphasis on Histologic Grading
- Landmark study establishing the 3-tier histological grading system for chondrosarcoma
- Grading based on cellularity, nuclear size, nuclear staining (hyperchromasia) and mitotic activity
- Grade correlated strongly with metastasis and survival across the cohort
- Histological grade emerged as the dominant prognostic factor for chondrosarcoma
Chondrosarcoma of Bone: An Assessment of Outcome
- 227 patients (Massachusetts General Hospital), mean follow-up 6 years (range 3-25 years)
- Most common sites: femur (78), pelvis (51), humerus (39); mean age 47 years
- High-grade lesions older and showed more pathological fracture, metastasis, recurrence and death (all p less than 0.001)
- Predictors of metastasis/death: local recurrence, pelvic location, size over 100cm cubed, aneuploidy, grade 3 and dedifferentiation
- Wide margins (outside reactive zone) gave longer survival than marginal or intralesional resection (p less than 0.04)
Dedifferentiated Chondrosarcoma: Prognostic Factors and Outcome from a European Group
- EMSOS multicentre study of 337 dedifferentiated chondrosarcomas from nine European centres
- Overall 5-year survival only 24%; for the 266 non-metastatic patients, 10-year survival was 28%
- 21% had metastases at diagnosis (median survival 5 months)
- Poor prognostic factors: pathological fracture, pelvic location, increasing age and inadequate margins
- Chemotherapy did NOT significantly improve survival in this series
Risk Factors for Survival and Local Control in Chondrosarcoma of Bone
- 153 patients with non-metastatic chondrosarcoma (52 axial, 101 appendicular), minimum 5-year follow-up
- Cumulative survival 70% at 10 years and 63% at 15 years
- Independent risk factors for death: extracompartmental spread, local recurrence and high histological grade
- Independent risk factors for local recurrence: inadequate surgical margins and size greater than 10cm
- Tumour location, type of surgery and symptom duration were NOT independently prognostic
Clear Cell Chondrosarcoma of Bone: Observations in 47 Cases
- 47 clear cell chondrosarcomas from the Mayo Clinic - the defining series for this subtype
- Low-grade tumour with predilection for the ends of long bones, especially the proximal femur
- Male predominance (2.6:1); most patients in the third and fourth decades
- Frequently mimics benign tumours (e.g. chondroblastoma) causing diagnostic difficulty
- Overall mortality 15%; en bloc resection with a margin of normal bone is the treatment of choice
IDH1 and IDH2 Mutations are Frequent Events in Central Chondrosarcoma and Central/Periosteal Chondromas but Not Other Mesenchymal Tumours
- Screened approximately 1200 mesenchymal tumours including 220 cartilaginous tumours
- IDH1/IDH2 mutations found in at least 56% of central and periosteal cartilaginous tumours
- Mutations span the spectrum from enchondroma through conventional central to dedifferentiated chondrosarcoma
- No IDH mutations in peripheral chondrosarcoma or osteochondroma - a key biological distinction
- The mutations generate the oncometabolite 2-hydroxyglutarate and appear early in tumourigenesis
Survival and Prognosis of Chondrosarcoma Subtypes: SEER Database Analysis
- Population-based SEER analysis of the five non-conventional chondrosarcoma subtypes
- Rate of metastasis at presentation rose across subtypes: juxtacortical 2.1%, clear cell 5.7%, myxoid 7.6%, mesenchymal 10.6%, dedifferentiated 19.8%
- Median survival: juxtacortical 97 months, clear cell 79, myxoid 60, mesenchymal 33.5, dedifferentiated only 11 months
- Metastatic disease at diagnosis was the consistent independent predictor of poorer survival across subtypes
Curettage for low-grade chondrosarcoma: safe in long bones, not in flat bones
- 44 patients with primary low-grade chondrosarcoma treated by intralesional curettage and cryotherapy, split by site: 37 long bone and 7 flat bone
- Five-year disease-free survival was 97.0% in long bones versus 80.0% in flat bones (p=0.001)
- EVERY recurrence, in both groups, had presented with soft-tissue extension (Enneking stage IB) - so it is extraosseous spread rather than grade that predicts failure of intralesional treatment
- Function was also better in the long-bone group (mean MSTS 27.9 versus 21.7, p=0.045)
- The authors conclude curettage with cryotherapy is a safe and reasonable option for lesions CONFINED TO BONE (Enneking stage IA)
Observation versus curettage for enchondroma and atypical cartilaginous tumour of long bones
- 228 consecutive patients with clinically and radiologically aggressive long-bone cartilage lesions not distinguishable as enchondroma or ACT; 153 observed and 75 curetted, mean follow-up 82 months
- Only 3 recurrences after surgery, and 7 complications of which 6 related to the osteosynthesis rather than the tumour
- MSTS scores were essentially identical (97% observed versus 96% operated), but the OBSERVED group had significantly fewer functional limitations
- For lesions larger than 4.4 cm, surgery was significantly WORSE than observation on both function (MSTS 94.0 versus 97.3, p=0.007) and pain (2.3 versus 0.8, p=0.001)
- The authors conclude that more such lesions could simply be observed, provided continuous follow-up is assured