Midtarsal Joint | Talonavicular and Calcaneocuboid
- The Chopart (midtarsal) joint is the talonavicular (TN) and calcaneocuboid (CC) joints together.
- It is critical for foot flexibility, and a missed injury leads to painful arthrosis and flatfoot.
- The mechanism is high-energy (MVA, fall), with forced abduction or adduction of the forefoot.
- Anatomic reduction is essential and ORIF usually required; fusion may be needed if the joint becomes arthritic.
- The nutcracker is lateral column compression: the cuboid is crushed, and bone graft restores length.
- “Chopart joint is the 'transverse tarsal joint' - key for midfoot motion.
- “Talonavicular is the 'keystone' of the medial longitudinal arch.
- “Nutcracker fracture = Cuboid compression. Restore lateral column length.
- “Think of Chopart any time there is significant midfoot swelling/injury.
Overview and Epidemiology
The Chopart, or midtarsal, joint is the talonavicular (TN) and calcaneocuboid (CC) joints taken together, and a Chopart injury involves either or both. The joint is the boundary between the hindfoot and the midfoot. It is critical for foot flexibility: it lets the foot adapt to terrain and is essential for gait.
It is named after François Chopart (1743-1795), a French surgeon who described amputation through this joint.
Epidemiology. Chopart injuries are rare, less common than Lisfranc injuries, and often associated with other foot injuries. The mechanism is high-energy (a motor vehicle or motorcycle accident, a fall from height), and occasionally a low-energy twist.
Chopart versus Lisfranc. The two midfoot joints differ in where they sit, which joint is the keystone, and what the joint does for the foot.
- Chopart (Midtarsal)
- TN + CC
- Lisfranc (Tarsometatarsal)
- TMT 1-5
- Chopart (Midtarsal)
- Midfoot (Transverse Tarsal)
- Lisfranc (Tarsometatarsal)
- Midfoot (Forefoot base)
- Chopart (Midtarsal)
- Talonavicular
- Lisfranc (Tarsometatarsal)
- 2nd TMT
- Chopart (Midtarsal)
- Foot Flexibility/Adaptation
- Lisfranc (Tarsometatarsal)
- Rigid Lever for Push-off
- Chopart (Midtarsal)
- ORIF +/- Fusion
- Lisfranc (Tarsometatarsal)
- ORIF or Primary Fusion
Anatomy and Pathophysiology
The two joints. The talonavicular joint is a ball-and-socket joint, key for inversion and eversion, and the keystone of the medial longitudinal arch. The calcaneocuboid joint is saddle-shaped and less mobile, and it belongs to the lateral column.
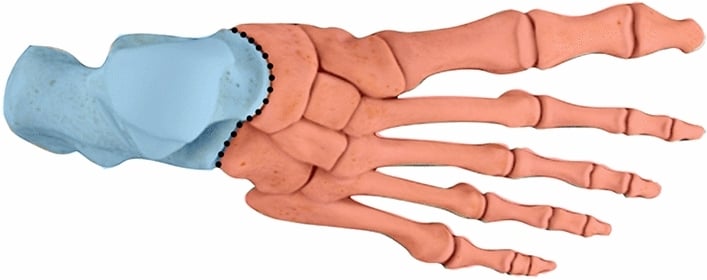
Ligaments. The named restraints:
- Spring ligament (plantar calcaneonavicular)
- Bifurcate ligament, with calcaneonavicular and calcaneocuboid limbs
- Interosseous ligaments
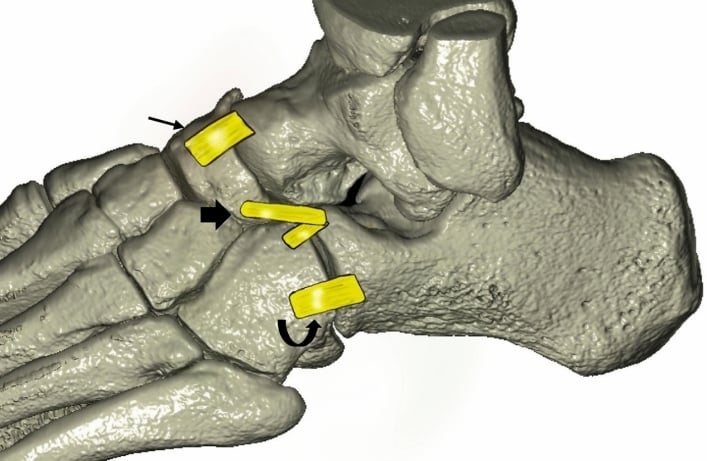
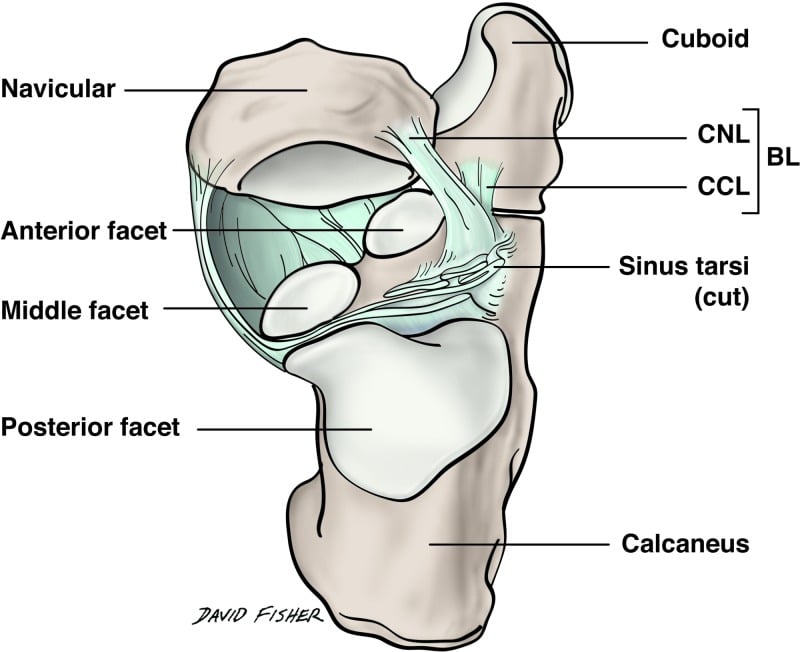
Biomechanics. Together the TN and CC joints form the transverse tarsal joint, which allows midfoot motion. When the subtalar joint is everted, the TN and CC axes are parallel and the foot is flexible. When it is inverted, the axes diverge and the foot becomes rigid for push-off.
How the joint is injured. The injuring forces:
- Forced abduction or adduction: the forefoot is driven laterally or medially on a fixed hindfoot
- Axial load: direct force through the midfoot
- Nutcracker: forced plantarflexion compresses the cuboid between the 4th/5th metatarsal bases and the calcaneus
Classification
Main and Jowett (1975). The name is two surgeons, not the adjective. Main and Jowett described 71 midtarsal injuries and grouped them by the direction of the deforming force, which is why the type names are directions rather than bones. The classification tells you where the force went, and therefore what else to look for, not which bone is broken.
- Injury
- TN Disruption
- Key Feature
- Navicular fracture, TN subluxation
- Injury
- Combined
- Key Feature
- TN + CC disruption
- Injury
- CC Disruption
- Key Feature
- Cuboid fracture, CC subluxation
- Injury
- Nutcracker
- Key Feature
- Cuboid compression
- Injury
- Comminuted
- Key Feature
- High-energy, multiple fragments
Reading the types. Medial and longitudinal types are the commonest, and crush injuries have the worst outcome. Combined patterns are frequent, so read the type as the dominant mechanism rather than an exclusive category. A force large enough to disrupt the midtarsal joint has usually done something else to the foot as well.
The nutcracker fracture. A compression fracture of the cuboid, produced by the plantarflexion mechanism above, and often missed. The crushed cuboid shortens the lateral column, and if length is not restored the result is an abductus deformity.
Clinical Assessment
Suspicion. Midfoot injuries are often missed, so keep a high index of suspicion.
History. Establish the mechanism: a motor vehicle accident, a fall or a twist. The pain is over the dorsal midfoot and worse with walking.
Examination. Look for:
- Significant midfoot swelling
- Tenderness over the TN and/or CC joints
- Deformity: there may be visible abduction or adduction
- Painful midfoot motion
- Neurovascular status: pulses and sensation
Compartments. High-energy Chopart injuries can cause foot compartment syndrome, especially after a crush. Monitor the foot compartments and release them if needed.
Investigations
The imaging sequence. Each study answers a different question:
- Foot radiographs (AP, oblique, lateral): joint widening, subluxation, fractures
- Weight-bearing radiographs, if the patient can tolerate them: better for subtle instability
- CT: essential for surgical planning, to assess comminution and joint congruity
- MRI: rarely needed acutely; for ligamentous assessment when the injury is occult
What to look for. On radiographs and CT:
- TN gap: widening or incongruity of the talonavicular joint
- CC subluxation: malalignment of the calcaneocuboid joint
- Cuboid compression (nutcracker) and lateral column shortening, assessed as in the next section
CT defines the injury. The plain film can understate a mixed injury, and overlapping bones can hide a combined pattern that CT defines. CT then determines both approaches and the fixation sequence.
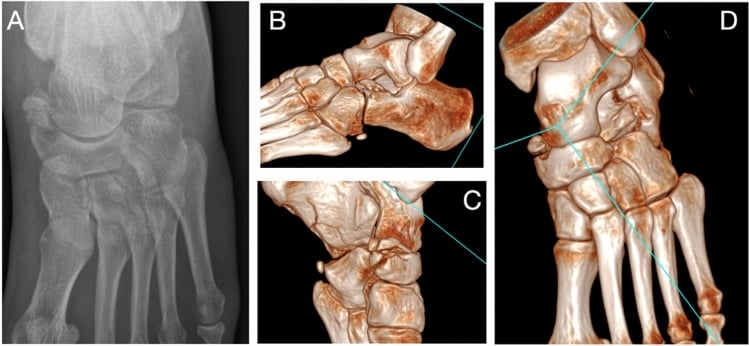
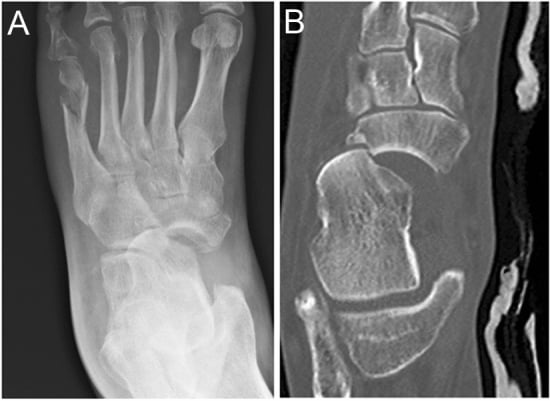
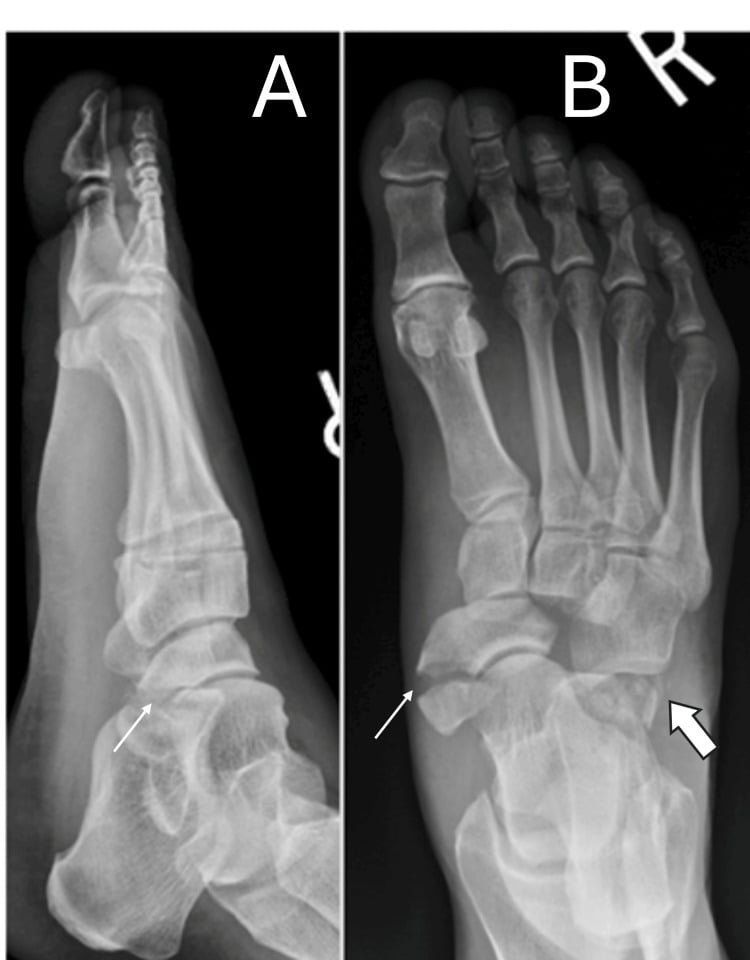
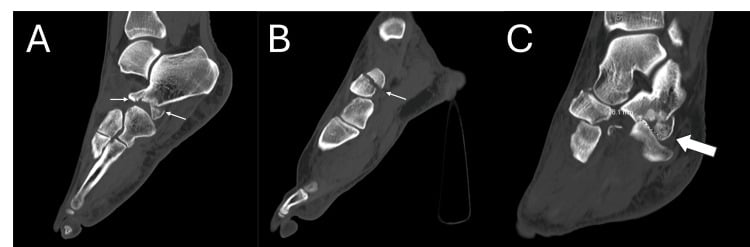
The occult injury. A small avulsion may be the only sign on the radiographs, and the first visible avulsion is a search sign rather than the whole diagnosis. Ongoing focal symptoms after apparently normal films require cross-sectional imaging.
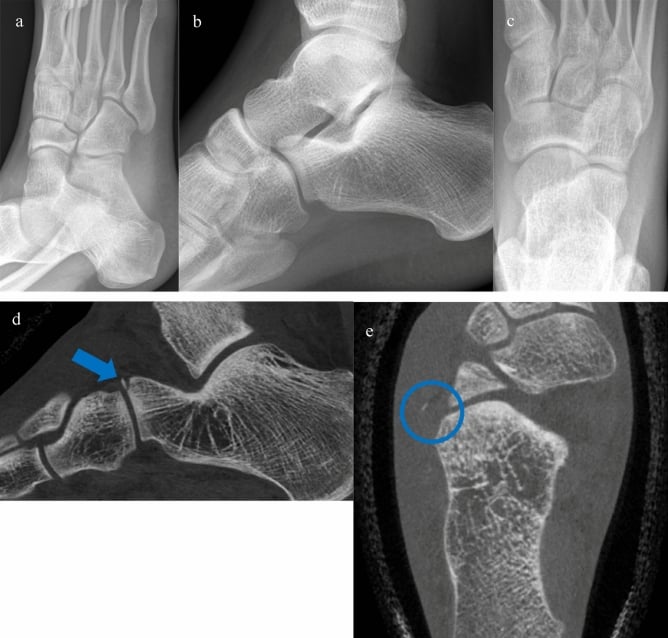
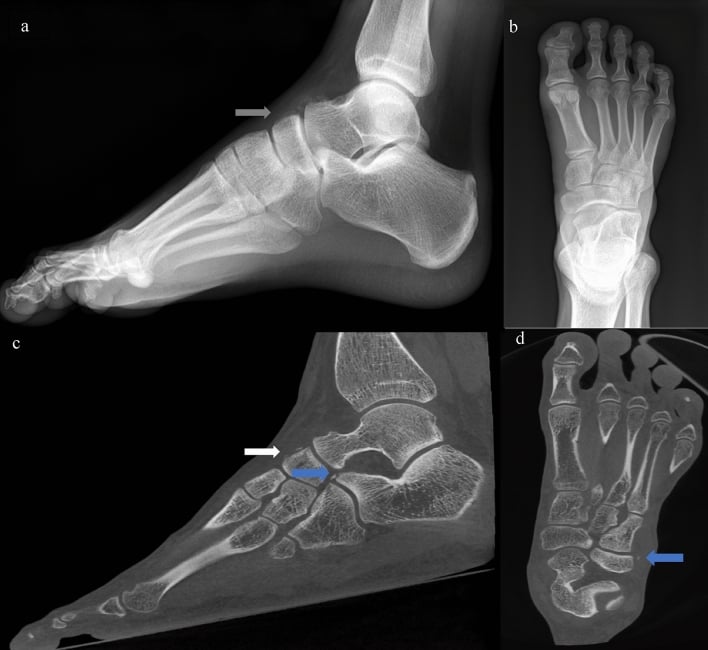
Assessing & Restoring Lateral Column Length
Why length matters. The lateral column (calcaneus, cuboid, 4th/5th metatarsals) must keep its length for a balanced foot. Shortening, typically from a crushed nutcracker cuboid, pulls the forefoot into a fixed abductus, overloads the lateral border, and drives painful gait and calcaneocuboid and midfoot arthrosis.
The operative goal. Restoring length is therefore the central goal of nutcracker repair. Do not simply fix the cuboid: measure and restore its length against the other foot, because residual shortening leaves a fixed forefoot abductus and a poor result.
How to assess it.
- Contralateral comparison: side-by-side standing AP and lateral radiographs are the most practical reference for the patient's own normal length
- Radiographic alignment: on the AP view the lateral column should form a smooth, continuous line, and loss of cuboid length with a forefoot that deviates laterally (abductus) signals shortening; look for loss of cuboid height on the lateral or oblique view
- Intra-operatively: fluoroscopic comparison with the normal side, and direct measurement of restored length after elevating the impacted articular surface; a lamina spreader, distractor or temporary external fixator regains and holds length before grafting and plate fixation
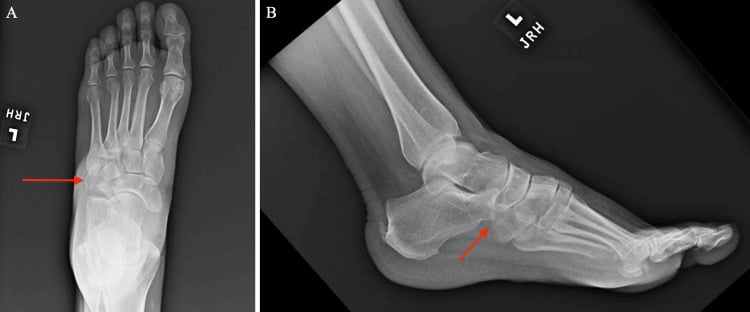
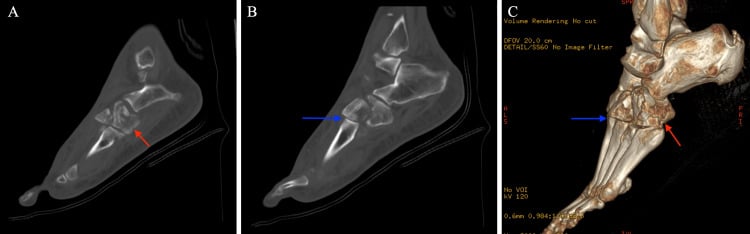
Differential Diagnosis
- Key Discriminators
- Midfoot swelling, TN/CC tenderness, joint widening or column shortening
- Confirming Test
- CT of the foot
- Key Discriminators
- Tenderness/gap at TMT bases, fleck sign, plantar ecchymosis
- Confirming Test
- Weight-bearing or stress radiographs, CT
- Key Discriminators
- Insidious dorsal midfoot pain in an athlete, no acute deformity
- Confirming Test
- MRI or CT (the 'N spot')
- Key Discriminators
- Lateral midfoot tenderness without medial column injury
- Confirming Test
- CT; assess lateral column length
- Key Discriminators
- Localised tenderness, no widening or subluxation on weight-bearing films
- Confirming Test
- Weight-bearing radiographs (stable)
Management Algorithm
Most Chopart injuries need surgery. Non-operative treatment is rare and reserved for truly stable, non-displaced injuries. For the rest, anatomic reduction is essential.
Non-operative. The criteria for it:
- Anatomic alignment
- No subluxation
- Stable on a weight-bearing radiograph
The foot is immobilised non-weight-bearing in a cast or boot for 6-8 weeks, then progressed from partial to full weight-bearing as tolerated. Serial radiographs confirm that nothing displaces.
Operative. ORIF is the standard. The indications:
- Displaced or subluxated TN or CC joint
- Nutcracker (cuboid compression)
- Combined or high-energy injuries
The surgical goals, in order:
- Anatomic reduction of the TN and CC joints
- Restoration of lateral column length (bone graft for the nutcracker)
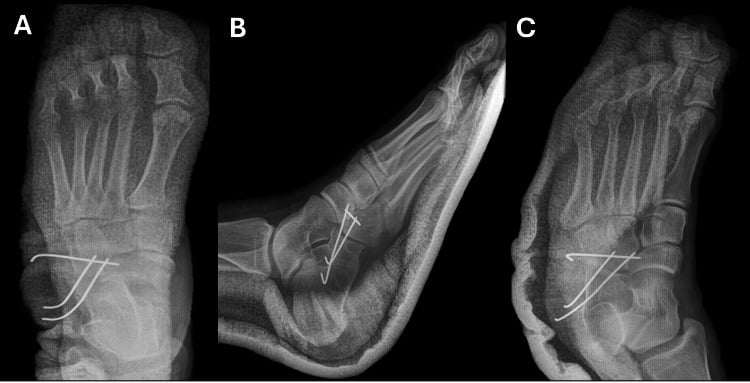
- Stable fixation: screws, plates, bridge plating
Open or closed reduction. Richter's series (Evidence Base) found open reduction better than closed, especially in fracture-dislocations, and supports closed reduction only for pure dislocations that reduce anatomically.
Surgical Technique
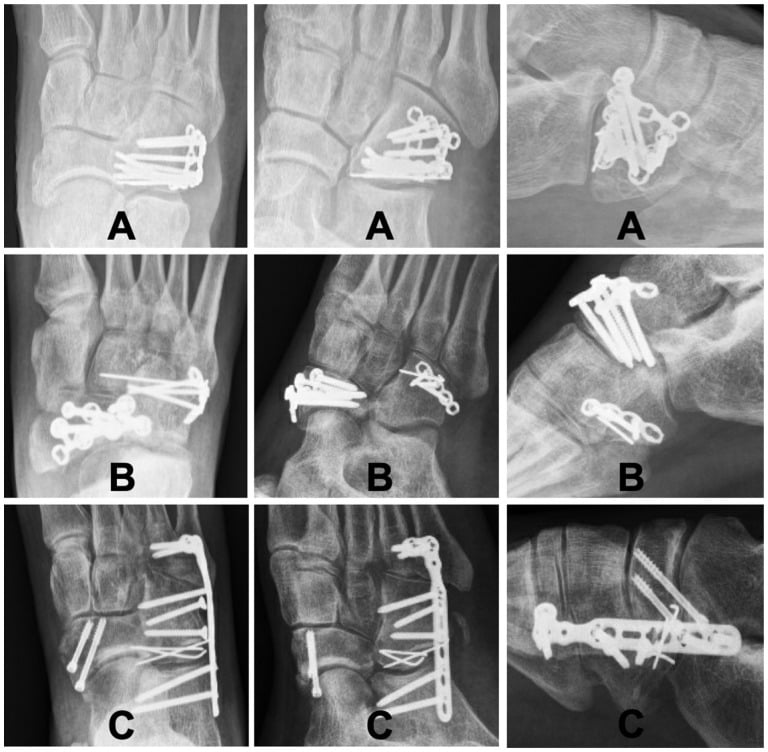
Talonavicular ORIF. TN is the key joint, and its reduction must be anatomic.
- Approach: dorsomedial incision over the TN joint
- Reduction: reduce the TN joint, using a K-wire in the navicular as a joystick
- Fixation: screws (3.5mm cortical or headless) across the TN joint, or a bridge plate if comminuted
- Spring ligament: assess it and repair if disrupted
- Closure: layered
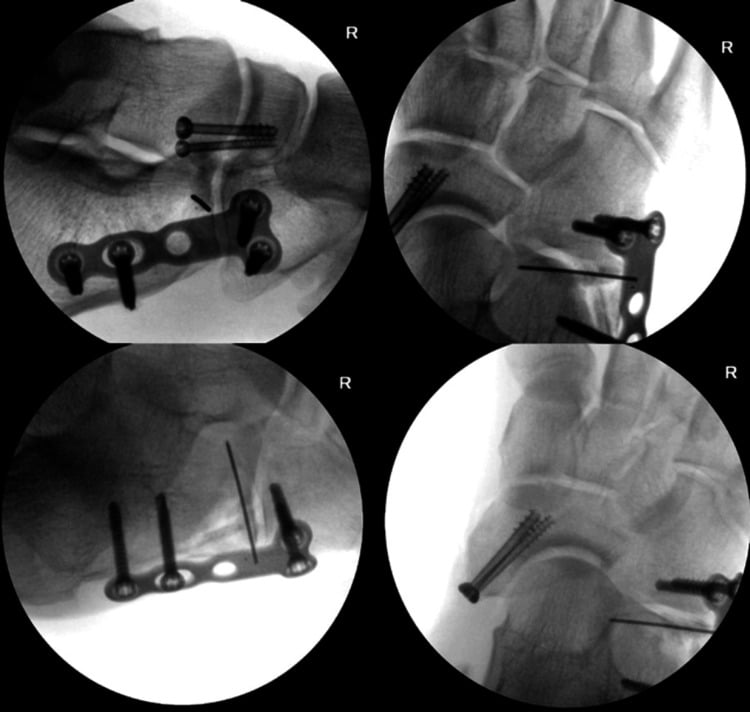
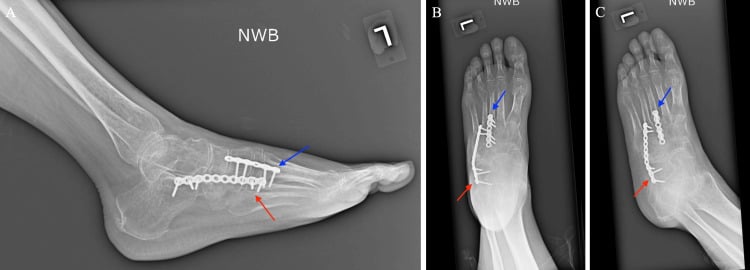
Nutcracker cuboid repair. The aim is to restore lateral column length and so prevent abductus.
- Approach: lateral incision over the cuboid
- Assess: the degree of compression, and measure lateral column length
- Reduction: elevate the articular surface with a bone tamp
- Bone graft: fill the defect with structural graft (iliac crest, allograft or femoral head)
- Fixation: plate with or without screws to hold length
- External fixator: may be needed to maintain length
Complications
- Risk Factor
- Cartilage damage
- Management
- Fusion (TN and/or CC)
- Risk Factor
- Inadequate reduction
- Management
- Osteotomy / Lengthening
- Risk Factor
- High-energy
- Management
- Fasciotomy
- Risk Factor
- Prolonged immobilization
- Management
- Physiotherapy
- Risk Factor
- Swelling
- Management
- Staged surgery if needed
Postoperative Care
After ORIF the foot is kept non-weight-bearing for 6-12 weeks, then moved to protected weight-bearing.
- Non-weight-bearing cast; elevation and swelling control
- Wound and neurovascular surveillance; maintain a low threshold for compartment pressure measurement if pain escalates (Myerson & Manoli)
- Gentle range of motion only when fixation is secure
- Transition from cast to boot as radiographic healing progresses
- Progress partial to full weight-bearing at 8-12 weeks, guided by fixation stability and column-length restoration
- Begin physiotherapy: hindfoot and midfoot mobility within the limits of the construct
- Gait training and progressive strengthening; orthotic support for the lateral column as needed
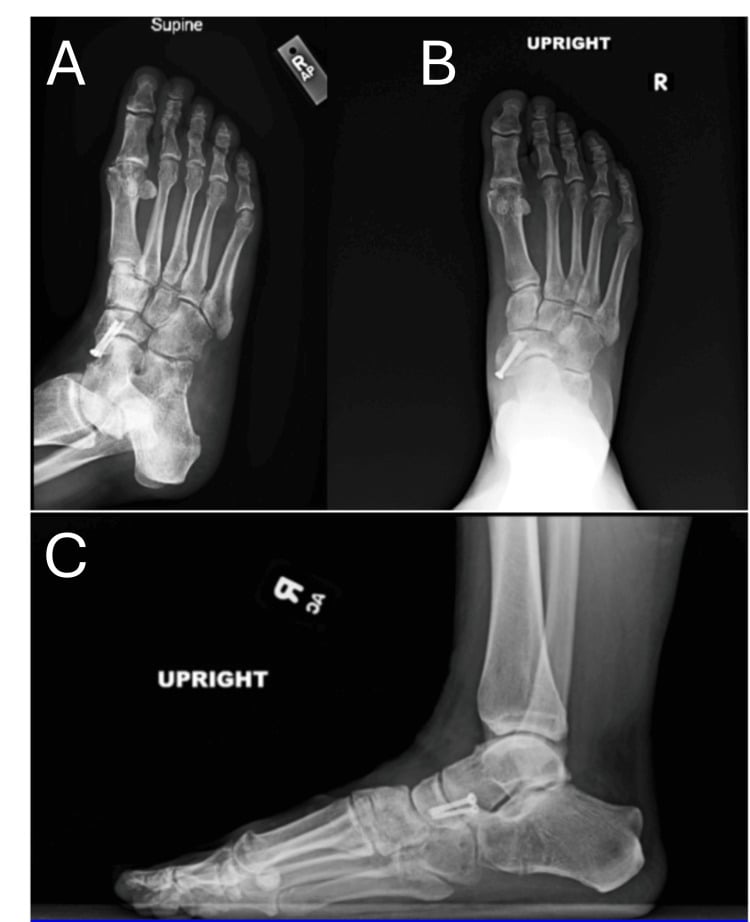
- Monitor for post-traumatic arthrosis at the talonavicular and calcaneocuboid joints
- Counsel with the outcome data below; realistic expectations are part of the follow-up
Outcomes
Reduction drives the result. Good reduction gives better long-term outcomes. Post-traumatic arthrosis is common even after anatomic reduction, and it is the main reason for secondary fusion.
What to tell the patient. The modern series report median AOFAS midfoot scores of 64-76, with quality of life below reference populations after high-energy injuries.
Guidelines, Registries & Global Practice
Global epidemiology
- Chopart injuries are rare, accounting for roughly 0.2 percent of all dislocations; midfoot fracture-dislocations are around five to ten times less common than Lisfranc injuries.
- Most series report a male predominance with a peak in young to middle-aged adults; high-energy mechanisms (road traffic, fall from height, crush) dominate, though a low-energy "twisting" subset exists in athletes.
- Up to a quarter present as combined Chopart-Lisfranc patterns, which carry the worst functional scores.
Side-by-side guidance
- Position on midtarsal injuries
- CT for all suspected midtarsal injuries; anatomic restoration of the medial (TN) and lateral (CC/cuboid) columns; bridge plating or temporary spanning fixation for comminution
- Position on midtarsal injuries
- Early ORIF for displaced fracture-dislocations; column-length restoration with structural graft for nutcracker cuboid; primary fusion reserved for non-reconstructable joints
- Position on midtarsal injuries
- Soft-tissue-led timing, senior decision-making, early CT, and transfer of complex foot trauma to a specialist centre
- Position on midtarsal injuries
- Reflects the Hannover (Richter) evidence: open anatomic reduction superior to closed for fracture-dislocations
Registry and evidence notes
- No dedicated national registry tracks Chopart injuries (they are not implant-arthroplasty procedures); the evidence base is single-centre series and small cohorts, so guidance is consensus- and principle-driven rather than registry-derived.
High- vs limited-resource practice variation
- Well-resourced settings: routine CT, dedicated foot-and-ankle plating systems, cuboid-specific plates, and staged soft-tissue management.
- Limited-resource settings: reliance on plain radiographs and intra-operative fluoroscopy, K-wire and external-fixator constructs to hold column length, and a lower threshold for primary fusion when implants or follow-up are constrained.
Controversies & Areas of Uncertainty
- Primary fusion vs ORIF: For severely comminuted, non-reconstructable Chopart joints (especially the talonavicular keystone), the threshold for primary arthrodesis versus attempted reconstruction is debated; no randomised data exist.
- Spanning (bridge) plate vs internal fixation: Whether to span the midtarsal joint with a temporary bridge plate or external fixator versus rigid internal fixation, and when to remove spanning hardware, remains practice-dependent.
- Nutcracker graft choice: Structural autograft (iliac crest), allograft, and synthetic wedges are all used to restore lateral column length; comparative outcome data are lacking.
- Closed reduction in pure dislocations: Richter's data support closed reduction only when truly anatomic; the durability of this approach versus routine open confirmation is uncertain.
- Weight-bearing protocol: Optimal duration of non-weight-bearing (6 vs 12 weeks) and timing of hardware removal are not standardised.
Viva Scenarios
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“What is your diagnosis and management plan?”
“Explain the key differences.”
“Explain the Nutcracker mechanism.”
MCQ Practice Points
Q: Which joints make up the Chopart (Midtarsal) joint? A: Talonavicular (TN) and Calcaneocuboid (CC).
Q: What is the keystone of the medial longitudinal arch? A: The Talonavicular joint.
Q: What is a Nutcracker fracture? A: Compression fracture of the cuboid, 'nutcracked' between the bases of the 4th/5th metatarsals and the calcaneus.
Q: What is the treatment for Nutcracker fracture? A: ORIF with bone graft to restore lateral column length.
Q: What is the function of the Chopart joint? A: Allows foot flexibility and adaptation to uneven terrain.
Anatomy
- Chopart: TN + CC
- TN: Ball-Socket
- CC: Saddle
- Keystone: TN
Nutcracker
- Cuboid compressed
- Between MT bases + Calc
- Lateral column short
- Bone graft to restore
Treatment
- ORIF standard
- Anatomic reduction
- NWB 8-12 weeks
- Fusion for arthrosis
Pitfalls
- Missed injury
- Compartment syndrome
- Lateral column length
- Post-traumatic arthrosis
Evidence Base
Richter — Open vs Closed Reduction of Chopart Injuries (Landmark)
- 110 Chopart dislocations/fracture-dislocations; 65 followed for a mean of 9 years (range 2-25).
- 25% pure dislocations, 55% fracture-dislocations, 20% combined Chopart-Lisfranc; mean AOFAS midfoot 75.
- Combined Chopart-Lisfranc injuries scored significantly lower than isolated Chopart injuries.
- Initial anatomic reduction was essential for good results; open reduction outperformed closed reduction, especially in fracture-dislocations.
Sangeorzan — Navicular Fracture Classification (Classic)
- 21 displaced tarsal navicular body fractures treated with ORIF; introduced the three-type classification by fracture-line plane and foot displacement.
- Type 1 coronal (no forefoot angulation); Type 2 dorsolateral-to-plantar-medial (forefoot displaced medially); Type 3 comminuted sagittal (forefoot displaced laterally).
- Good results in 67%; both fracture type and accuracy of reduction correlated directly with outcome.
Hermel & Gershon-Cohen — Original Nutcracker Description
- First description of the cuboid 'nutcracker' fracture by indirect violence.
- Cuboid is crushed between the bases of the 4th/5th metatarsals distally and the anterior calcaneus proximally.
- Mechanism produces lateral column shortening.
Engelmann — Cuboid ORIF: Restoring Column Length
- 45 surgically managed cuboid fractures at a level 1 centre; median follow-up 67 months.
- Median AOFAS midfoot 76 (range 34-100); no infections or nonunions; secondary CC fusion in only 2 patients.
- Cuboid plate fixation was independently associated with better AOFAS scores.
van der Vliet — Functional Outcomes of Midfoot Injuries
- 40 patients (45 Lisfranc and/or Chopart injuries) after ORIF; median AOFAS midfoot 64.
- Secondary arthrodesis required in 7 of 45 injuries; higher injury severity predicted worse function.
- EQ-5D quality of life was significantly below the reference population.
Myerson & Manoli — Foot Compartment Syndrome
- Approximately 10% of calcaneal/high-energy foot injuries develop foot compartment syndrome.
- Half of those develop claw toes, stiffness or neurovascular dysfunction; calcaneal-compartment pressures confirm the diagnosis.
- Immediate fasciotomy is recommended, with delayed definitive fixation after wound closure.