Congenital Forefoot Conditions
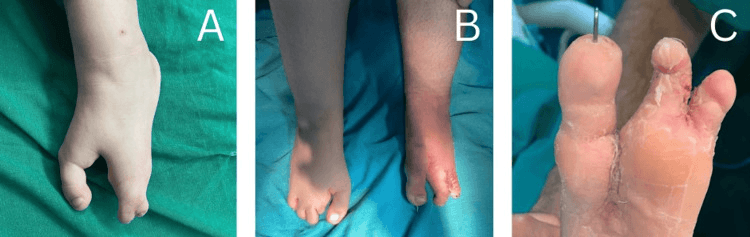
- Cleft foot (split-foot malformation, ectrodactyly, the 'lobster-claw' foot) is a congenital central-ray deficiency: the central metatarsals and phalanges are absent or hypoplastic, with a median cleft and frequently syndactyly of the remaining rays, ranging from a mild central cleft to severe loss of multiple rays.
- It may be isolated or part of a syndrome, most notably ectrodactyly-ectodermal dysplasia-clefting (EEC), and is genetically heterogeneous (SHFM3 is associated with a 10q24 duplication), so genetic counselling and assessment for associated anomalies, including the hands, are important.
- Cleft-foot management is individualised and tailored to function and appearance: many feet function and shoe reasonably well without surgery, and reconstruction is for difficulty with weight-bearing or footwear, or for cosmesis.
- The overlapping (congenital overriding) fifth toe has the proximal phalanx dorsally subluxated and adducted at the fifth MTP joint; in children it often corrects with normal ambulation, so intervention is only for persistent symptomatic deformity.
- The underlapping ('curly') fifth toe has the proximal phalanx in varus and flexion, frequently with rotational malalignment judged by the nailbed; it commonly corrects with reassurance and benign neglect up to about age 6.
- Fifth-toe deformities are treated non-operatively first; surgery is reserved for symptomatic deformity persisting after non-operative measures and is tailored to the pathology, because no single gold-standard procedure exists.
- “Cleft foot = central-ray deficiency (ectrodactyly/split-foot, 'lobster-claw'); isolated or syndromic (EEC; SHFM3/10q24) - genetic counselling + check hands/associations. Surgery tailored to function/cosmesis.
- “Overlapping (overriding) 5th toe = proximal phalanx dorsal + adducted at 5th MTP (overrides 4th); underlapping ('curly') 5th toe = proximal phalanx varus + flexion (rotational).
- “Fifth-toe deformities in children often correct or settle (the curly toe with reassurance up to ~age 6); non-operative care first, surgery (tenotomy, capsulotomy, tendon transfer, osteotomy, phalangectomy) only for persistent symptoms - no gold-standard procedure.
Cleft Foot (Ectrodactyly / Split-Foot Malformation)
What it is. Cleft foot, also called split-foot malformation, ectrodactyly or the 'lobster-claw' foot, is a congenital central-ray deficiency. The central metatarsals and phalanges are absent or hypoplastic, leaving a median cleft, often with syndactyly of the remaining rays.
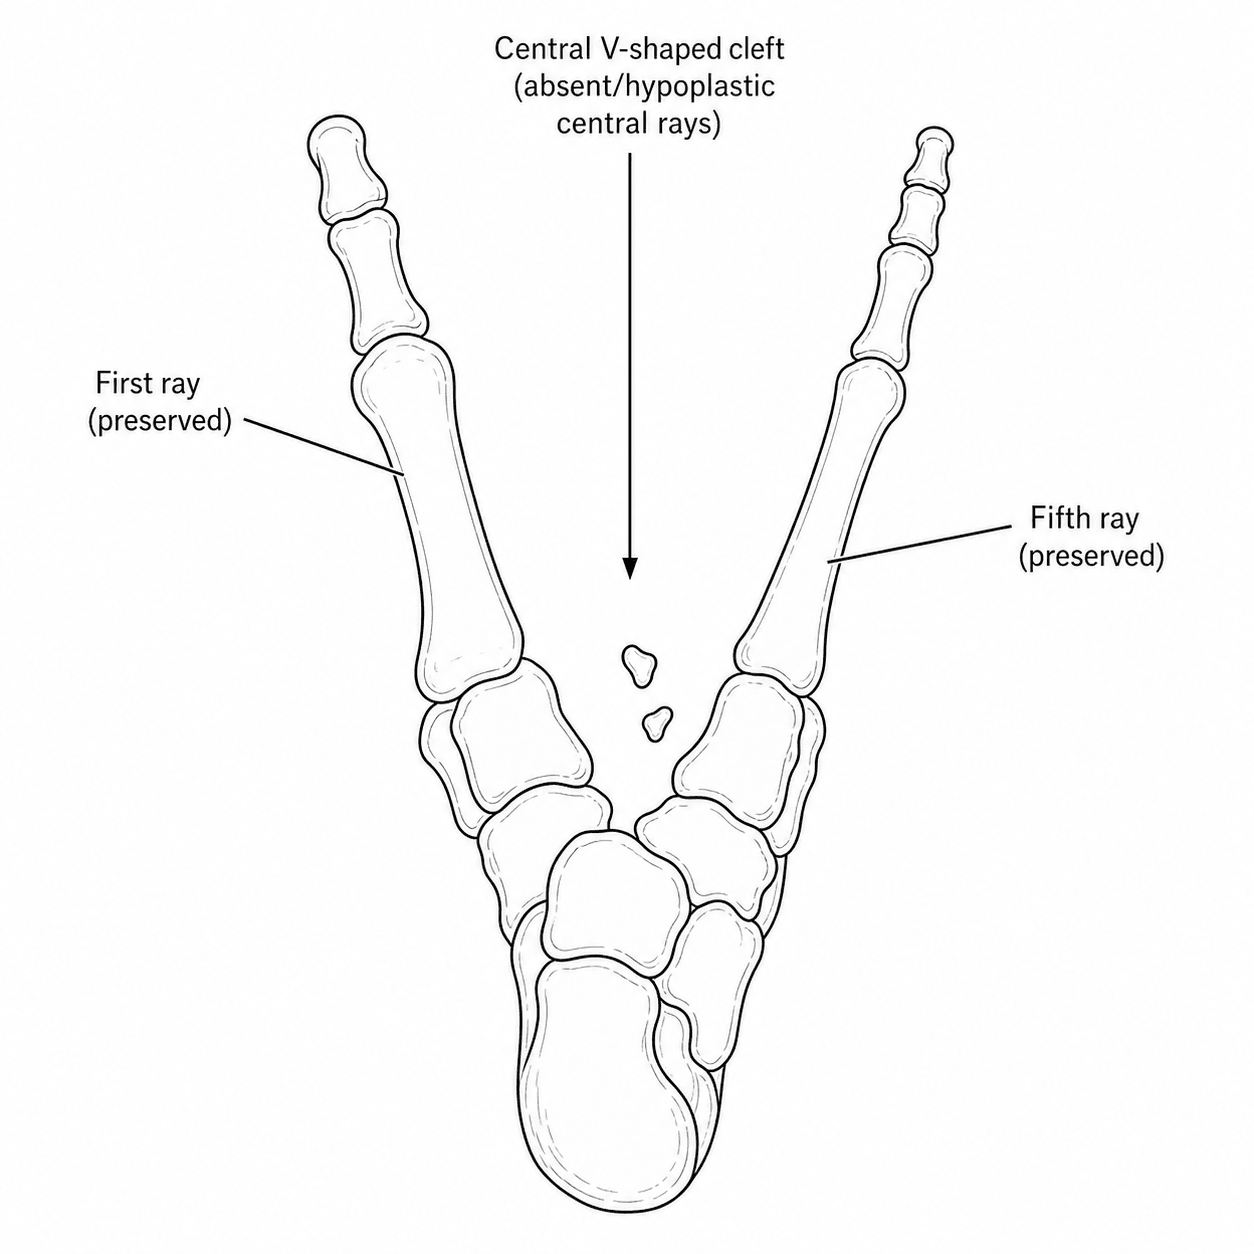
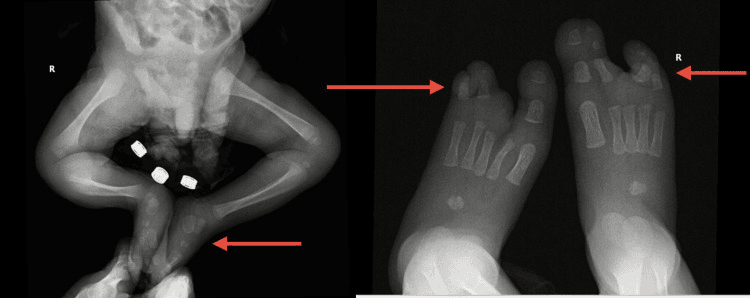
The spectrum. Severity runs from simple toe absence, through a mild central cleft, to a deep cleft reaching the metatarsals with severe loss of multiple rays. The milder forms are easily missed until the foot is examined. A plain radiograph separates toe aplasia from the deeper typical cleft, in which the metatarsals are also absent or fused.
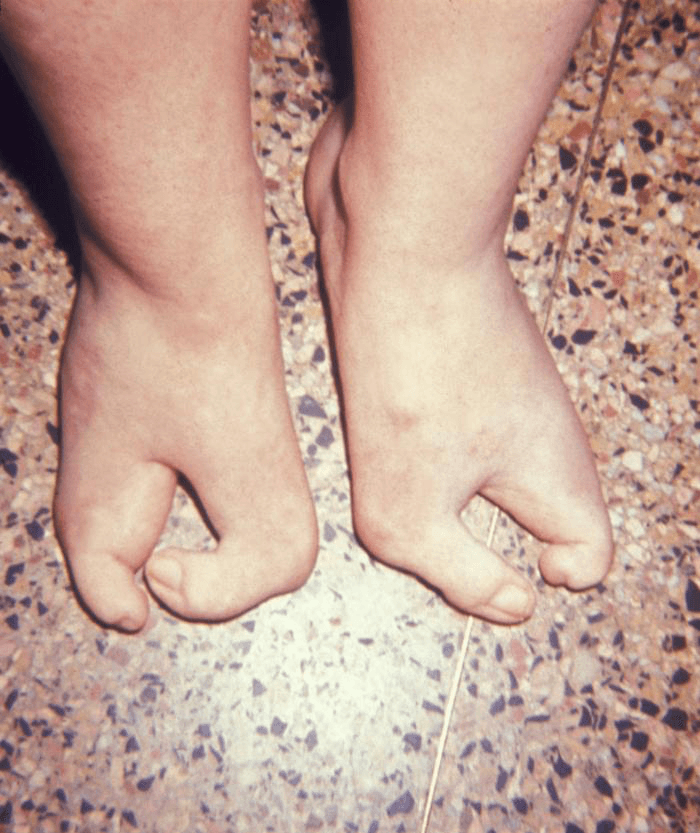
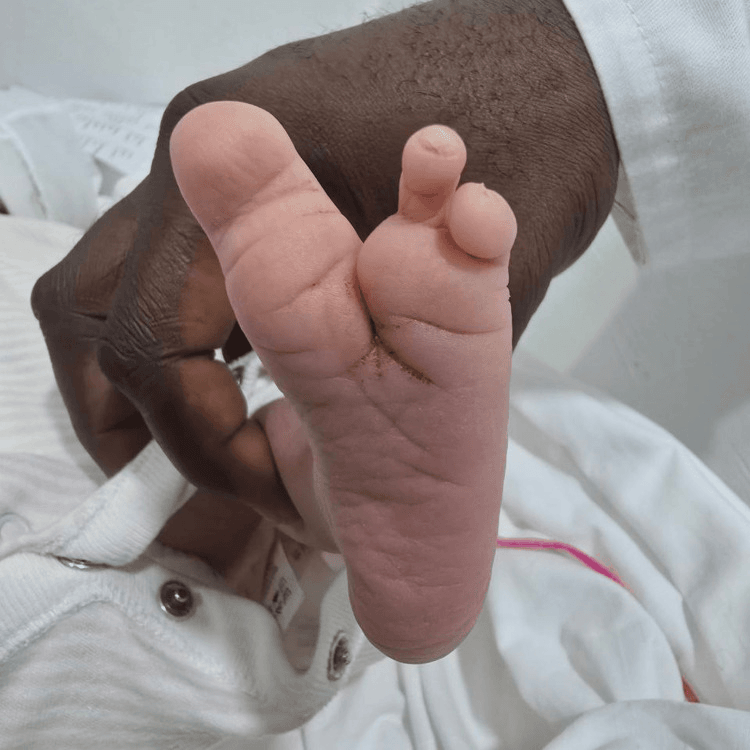
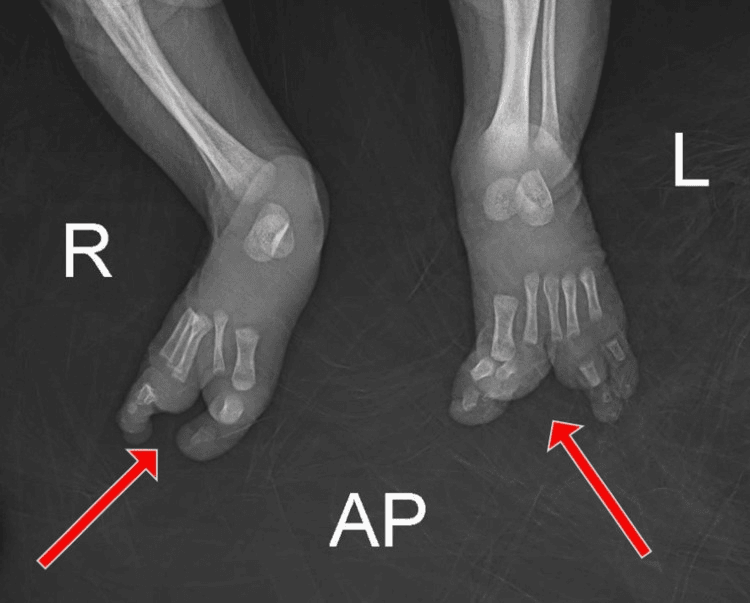
Isolated or syndromic. Cleft foot may occur in isolation or as part of a syndrome, most notably ectrodactyly-ectodermal dysplasia-clefting (EEC) syndrome. It is genetically heterogeneous: SHFM3, for example, is associated with a 10q24 duplication. The foot is therefore not the whole story. Examine the hands in every cleft foot for a split-hand malformation, assess for associated anomalies, and arrange genetic counselling.
Classifying Cleft Foot: Typical vs Atypical
Across the spectrum, the distinction that matters is typical versus atypical, because it carries the inheritance and counselling implications.
- Typical cleft foot (true central-ray deficiency, SHFM). A central, V-shaped cleft from deficiency of the central ray(s), frequently bilateral and often with split-hand involvement. It is commonly familial, autosomal dominant with variable expressivity and incomplete penetrance, so a mildly affected parent may have a severely affected child, and a parent with a trivially abnormal hand may not know they carry it. This is the form linked to the SHFM loci (such as SHFM3/10q24) and to EEC syndrome, and the one for which genetic counselling is most relevant.
- Atypical cleft foot, now usually termed symbrachydactyly. A wider, U-shaped defect with more rays absent, sometimes a near-monodactylous foot. It is typically unilateral and sporadic, not inherited and not part of the SHFM genetic spectrum, so the recurrence risk and counselling differ.
The split-hand counterpart and its Manske classification are covered in the Cleft Hand topic.
Grading the foot. Foot-specific schemes grade severity by the number of remaining rays or metatarsals and the presence of transverse bones. The named scheme is the Blauth and Borisch classification, which grades by the number and morphology of the metatarsals remaining: from a foot with all five metatarsals present and only a soft-tissue cleft, through progressive central metatarsal absence, to a severely monodactylous foot. The count, rather than the appearance of the cleft, is what predicts whether the foot needs nothing more than accommodative footwear or a genuine reconstruction.
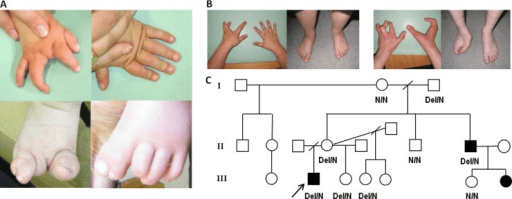
Recognising EEC. EEC is ectrodactyly, ectodermal dysplasia and clefting, most often from a TP63 mutation. "Assess for syndromic features" is only useful if you can name them:
- Ectodermal dysplasia - sparse fine hair, abnormal or absent teeth, dystrophic nails, dry skin and reduced sweating
- Clefting - cleft lip and/or palate
- Lacrimal duct obstruction - characteristic and easily missed, causing chronic tearing and recurrent eye infection; ask about it specifically
- Genitourinary and renal anomalies - warranting a renal ultrasound
- Conductive or sensorineural hearing loss - so arrange a hearing assessment
A cleft foot with cleft lip or palate, urinary anomalies, or skin and hair changes is syndromic until proved otherwise, and that changes the work-up. Refer to clinical genetics.
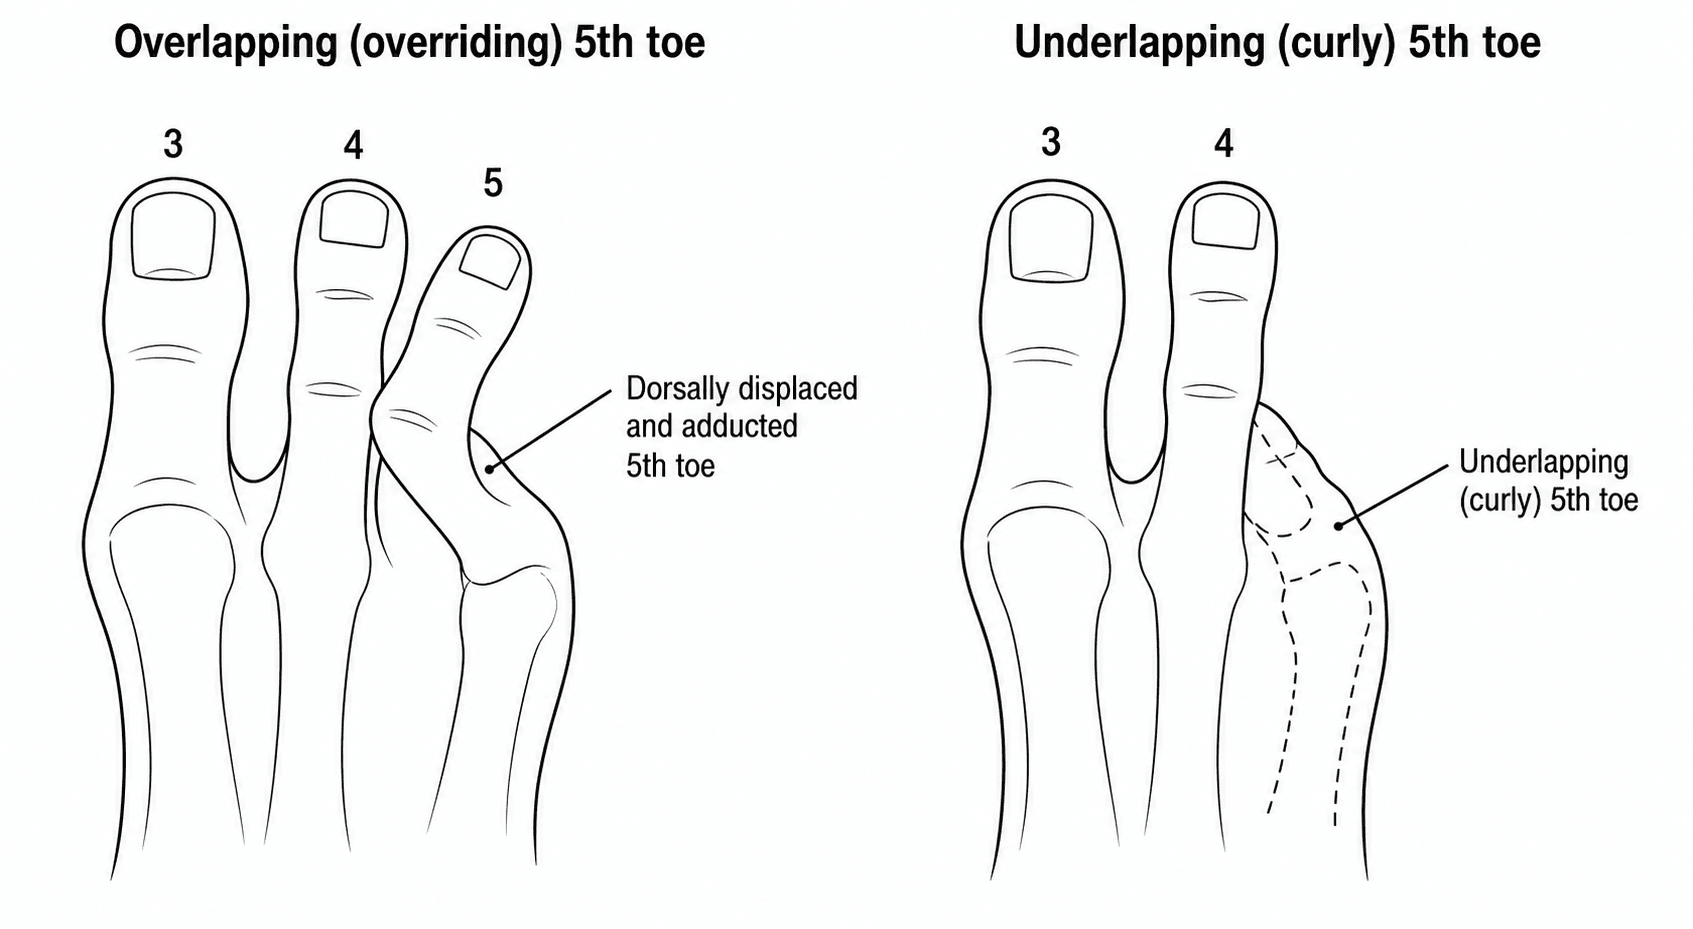
Overlapping & Underlapping Fifth Toe
The overlapping toe. In the overlapping, or congenital overriding, fifth toe the proximal phalanx is dorsally subluxated and adducted at the fifth MTP joint, so the toe rides over the fourth. It may be an asymptomatic parental concern, or painful and disabling with footwear.
The underlapping toe. The underlapping or 'curly' fifth toe has the proximal phalanx in varus and flexion at the MTP joint, frequently with a rotational malalignment (supination or pronation, judged by the nailbed), and it tucks under the adjacent toe. It is usually noticed early in infancy.
Natural history. Both deformities are congenital, and in children both commonly correct or settle. The overlapping toe often corrects with normal ambulation; the curly toe commonly corrects with reassurance and benign neglect up to about age 6. Intervention in either is for persistent pain or footwear difficulty.
Management Principles
Cleft foot. Management is individualised and tailored to function and appearance. Many cleft feet function and shoe reasonably well and need no surgery. Reconstruction is undertaken for difficulty with weight-bearing or footwear, or for cosmesis, and early recognition with tailored intervention optimises outcome. The options:
- Cleft closure
- Syndactyly release
- Ray amputation or realignment
- Removal of ectopic bone
- Correction of associated deformity
Closing the cleft. A diamond (rhomboid) incision is marked around the cleft and opened along the markings, the capsule is repaired and the rays are held with K-wires. Closure converts a splayed forefoot into a plantigrade, shoeable foot. The goal is a narrowed, stable forefoot with preserved function rather than anatomical normality.
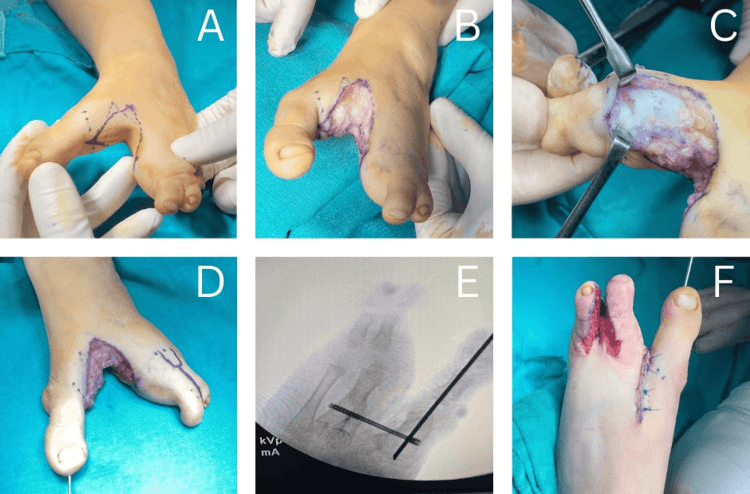
Fifth-toe deformities. Non-operative care comes first: strapping or splinting, accommodative footwear or shoe modification, padding or cushions, and functional modification. Surgery is reserved for deformity that remains painful or causes footwear difficulty after these measures. It is tailored to the specific pathology, because no single operation is the gold standard.
Decide on symptoms and function, not on appearance alone. Intervene for pain and footwear difficulty, and for significant cosmetic or functional concern, not for the radiograph or the look of the foot in isolation.
The Named Operations for the Fifth-Toe Deformities
Match the operation to the pathology. A fixed dorsal-adduction overriding toe needs the soft-tissue release and repositioning of a Butler procedure, whereas a flexible curly toe needs only a flexor tenotomy.
- Butler procedure, the classic operation for the congenital overriding fifth toe. A double racquet-shaped (dorsal and plantar) incision around the base of the toe allows the extensor tendon and the dorsal MTP capsule to be released, the toe is repositioned plantarward into corrected alignment, and the skin closure holds the new position. It corrects the deformity while preserving the toe, in contrast to amputation.
- Percutaneous flexor tenotomy, the simple, effective procedure for the flexible underlapping toe. Dividing the tight flexor digitorum longus (and brevis) through a tiny stab releases the flexion and curl; it works well in children and avoids open surgery.
- Syndactylisation, suturing the fifth toe to the fourth (a Kelikian-type 'buddy' procedure), an option for a recurrent or unstable toe.
- Phalangectomy (removing the proximal phalanx) or a corrective osteotomy, and rarely amputation of the fifth toe, reserved for severe, recalcitrant or salvage situations.
General lesser-toe and curly-toe surgery is covered in the Lesser Toe Deformities and Curly Toes topics.
- Overlapping (overriding)
- Dorsally subluxated + adducted at 5th MTP
- Underlapping ('curly')
- Varus + flexion at MTP (often rotational)
- Overlapping (overriding)
- Rides OVER the 4th toe
- Underlapping ('curly')
- Tucks UNDER the adjacent toe
- Overlapping (overriding)
- Often corrects with ambulation; treat if symptomatic
- Underlapping ('curly')
- Often corrects with reassurance up to ~age 6
- Overlapping (overriding)
- Strapping/splinting, shoe modification
- Underlapping ('curly')
- Accommodative shoes, cushions, functional modification
- Overlapping (overriding)
- Osteoclysis, tenotomy, capsulotomy, syndactylisation, tendon transfer, phalangectomy, amputation
- Underlapping ('curly')
- Flexor tenotomy, capsulotomy, tissue rearrangement, osteotomy, spur removal
Mnemonics & Memory Aids
CLEFT
Hook:CLEFT: Central-ray deficiency, Look for syndrome/split-hand, EEC/genetic counselling, Function/cosmesis-tailored surgery, Toe (5th) deformities mostly non-operative.
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“A child has a 'lobster-claw' foot. What is it, and what is your approach?”
“How do you manage an overlapping and an underlapping fifth toe in a child?”
Cleft foot
- Central-ray deficiency (split-foot malformation / ectrodactyly, 'lobster-claw')
- Isolated or syndromic (EEC); genetically heterogeneous (SHFM3/10q24)
- Check the hands (split-hand) and associated anomalies; genetic counselling
Cleft foot management
- Tailored to function and appearance
- Many shoe/function well → no surgery
- Reconstruction (cleft closure, syndactyly release, ray realignment/amputation) for footwear/weight-bearing/cosmesis
Fifth-toe deformities
- Overlapping (overriding): proximal phalanx dorsal + adducted at 5th MTP (over the 4th)
- Underlapping ('curly'): proximal phalanx varus + flexion (often rotational)
- Children: mostly correct/settle with ambulation + reassurance (curly toe up to ~age 6)
Fifth-toe management
- Non-operative first: strapping/splinting, accommodative footwear, padding
- Surgery for persistent symptoms (tenotomy, capsulotomy, tendon transfer, osteotomy, phalangectomy, amputation)
- No gold-standard procedure - tailor to the pathology
Evidence & Key Studies
Prenatal diagnosis & genetic counselling of split-hand/split-foot malformation (SHFM3, 10q24.3): case report & review
- Split-hand/split-foot malformation (SHFM, ectrodactyly) is a congenital limb malformation affecting the central rays, extending to syndactyly, median clefts of the hands/feet, and aplasia/hypoplasia of phalanges, metacarpals and metatarsals (the 'lobster-claw' appearance).
- It is clinically and genetically heterogeneous (e.g. SHFM3 associated with 10q24 duplication) and may be isolated or syndromic, making prenatal diagnosis and genetic counselling important.
- Genetic counselling helps plan and manage affected pregnancies and families.
Fifth toe deformities: overlapping and underlapping toe
- The overlapping (overriding) fifth toe has the proximal phalanx dorsally subluxated and adducted at the fifth MTP joint; in children it often corrects with normal ambulation, so intervention is only needed for persistent symptomatic deformity, with non-operative measures (strapping, splinting, shoe modification) first.
- The underlapping ('curly') fifth toe has the proximal phalanx in varus and flexion (often with rotational malalignment) and commonly corrects with reassurance up to about age 6; non-operative care is the mainstay.
- Surgery (osteoclysis, percutaneous tenotomy, capsulotomy, syndactylisation, tendon transfer, phalangectomy, amputation) is reserved for persistent pain/footwear difficulty, and no gold-standard approach exists - surgery should be tailored to the specific pathology.
The definition and genetic heterogeneity of cleft foot/split-foot malformation (central-ray deficiency, 'lobster-claw', SHFM3/10q24, isolated vs syndromic) and the importance of genetic counselling come from the cited Lai report (with the cited Raza case report illustrating function-and-cosmesis-tailored surgical management of ectrodactyly, PMID 41013550); the descriptions and management of the overlapping and underlapping fifth-toe deformities (largely non-operative in children with surgery for persistent symptoms, and no gold-standard procedure) from the cited Talusan review. The EEC syndromic association and the assessment of the hands/associated anomalies are standard, well-established teaching. (See also our Polydactyly/Syndactyly and Paediatric Foot Deformities topics.)