Amniotic Band Syndrome | Limb Constriction | Variable Severity | Z-Plasty Release
- Amniotic band syndrome: Fibrous bands constrict developing limbs in utero, causing deformities
- Variable severity: From simple constriction rings to complete amputation
- Patterson classification: Grades 1-4 based on severity and distal changes
- Z-plasty release: Standard surgical technique for constriction bands
- Not hereditary: Sporadic condition, not genetic
- “Viva question: Classify this constriction band using Patterson system
- “Distinguish from other congenital limb deformities (symbrachydactyly, radial club hand)
- “Z-plasty technique: Multiple Z-plasties to lengthen and break up constriction
- “Complications: Recurrence, vascular compromise, need for multiple procedures
- “Modern technique point: EXCISE the band and resurface with continuous opposing flaps - piecemeal Z-plasty leaves an hourglass deformity
- “A dusky digit is an EMERGENCY release, not a days-to-weeks urgent one
Overview and Epidemiology
Congenital constriction bands, also called amniotic band syndrome, constriction ring syndrome, amniotic band sequence or the ADAM complex (Amniotic Deformity, Adhesions, Mutilations), are the deformities left when fibrous bands from a ruptured amnion constrict developing limbs or digits in utero. The result ranges from a simple constriction ring to complete intrauterine amputation, and can cause significant functional impairment as well as cosmetic concern. The word "sequence" is deliberate: the visible bands are one part of a wider pattern.
How common. Reported prevalence varies widely with ascertainment. Australian population-based registries report 2.03 per 10,000 births, about 1 in 4,900 (Bower 1993), while a UK tertiary series cited approximately 1 in 15,000 (Homer 2015). Higher figures, up to about 1 in 1,200, appear in older literature and reflect liveborn-only or less stringent case definitions. There is no sex predilection; registry data show an equal male-to-female distribution.
Sporadic, not inherited. The condition is not hereditary or genetic, and there is essentially no recurrence risk for future pregnancies. That is the key counselling point, and it has to survive the risk-factor data below: those are epidemiological associations in a sporadic condition, not recurrence risks, and a mother who hears "young maternal age is a risk factor" must not be left thinking she caused it.
Risk associations. The Finnish nationwide case-control study of 106 cases against 530 matched controls (Syvanen 2021, PMID 32991492) found young maternal age under 25 years (OR 1.72, 95% CI 1.06-2.80) and primiparity (adjusted OR 2.42, 95% CI 1.52-3.88); the same maternal-age and first-birth associations appear in the Australian registry data (Bower 1993). The Finnish study also reported novel associations with first-trimester maternal beta-blocker and progestogen use, with wide confidence intervals and no replication, and these are not something to present to a mother as a cause. Other cited factors are maternal trauma, infection and drug use (controversial) and multiple gestations (slightly increased risk); most cases have no identifiable risk factor.
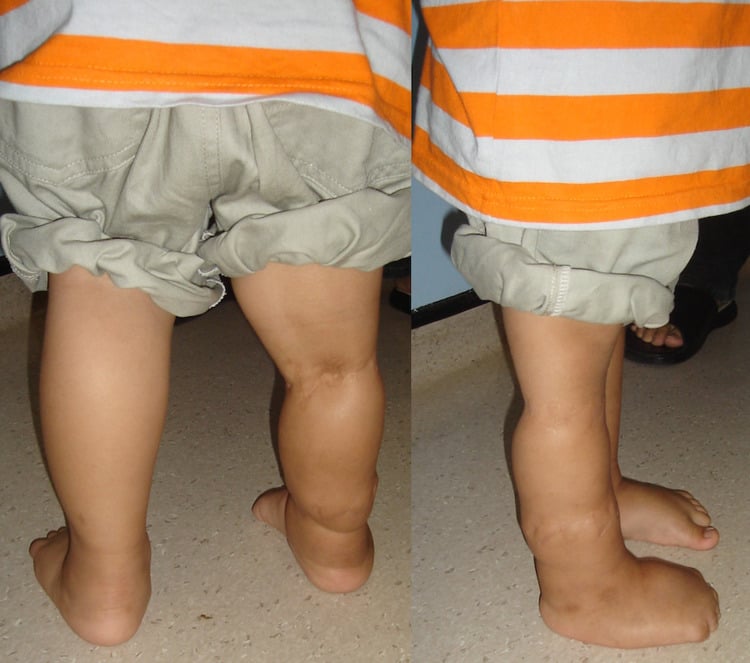
Where the bands are. Bands are frequently multiple and affect more than one limb. They are most common on the fingers, toes, arms and legs, with the upper limb most frequently involved in surgical series, and the pattern is asymmetric and non-anatomical, which is what separates them from the genetic and longitudinal limb-deficiency conditions.
Natural history. What happens without treatment depends on the grade:
- Grade 1: usually stable; may cause cosmetic concern or mild functional limitation
- Grade 2: progressive if not released; the oedema worsens and may lead to tissue loss
- Grade 3: the digits remain fused and need surgical separation
- Grade 4: no progression, since the amputation has already happened; needs prosthetic management
Pathophysiology and Mechanisms
Early rupture of the amnion. The amnion tears early in pregnancy, often in the first trimester. Amniotic fluid leaks and the amnion separates from the chorion; fibrous bands form from the torn amnion, float in the amniotic fluid and can wrap around the developing fetus. The constriction then tightens as the fetus grows.
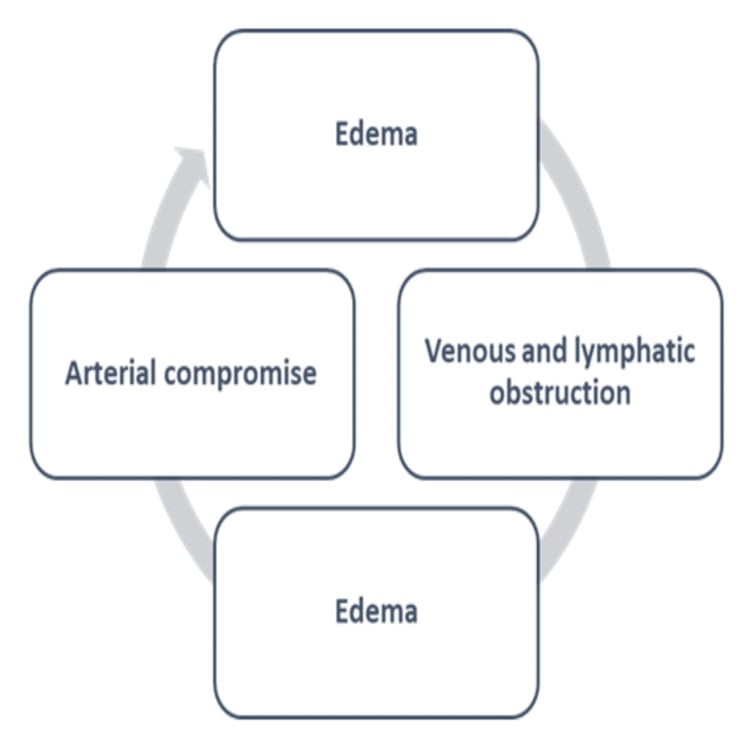
What sets the severity. The timing of the rupture (earlier is more severe), the tightness of the band, its location (digit or limb) and how long the constriction has acted before birth. The consequences run from vascular compromise and lymphatic obstruction to complete amputation, and each structure the band crosses leaves its own sign:
- Consequence
- Obstruction
- Clinical Finding
- Distal lymphoedema (Grade 2)
- Consequence
- Compression
- Clinical Finding
- Venous congestion, swelling
- Consequence
- Severe compression
- Clinical Finding
- Tissue ischaemia, amputation (Grade 4)
- Consequence
- Restriction
- Clinical Finding
- Distal hypoplasia, shortening
- Consequence
- Fusion
- Clinical Finding
- Acrosyndactyly (Grade 3)
Why an untreated ring worsens. The band obstructs lymphatic and venous return first; the resulting oedema tightens the constriction further, and only late does arterial inflow fail. That is why distal swelling is an indication to operate early rather than to observe.
Extrinsic theory (Torpin). The dominant, widely accepted model. Early rupture of the amnion with an intact chorion exposes the fetus to mesodermic fibrous strands floating in the chorionic cavity; these mechanically entangle and constrict developing parts, producing rings, lymphoedema, acrosyndactyly and amputation. It explains the asymmetric, non-anatomical, "anything-anywhere" pattern and the negligible recurrence risk.
Intrinsic theory (Streeter). A primary germ-plasm or developmental defect, an intrinsic abnormality of the embryonic disc or a localised vascular disruption, produces both the bands and the tissue defects, with the bands a by-product rather than the cause. It is invoked for cases with associated internal, visceral and CNS anomalies that are hard to explain by simple constriction. A vascular-disruption mechanism, compromised perfusion of the developing part, is often cited as a unifying contributor.
Lead with the extrinsic (Torpin) amniotic-rupture theory as the accepted explanation for the constriction and limb deformities, be able to contrast it with Streeter's intrinsic theory, which better explains associated internal and CNS defects, and know the synonym ADAM complex.
Classification Systems
Patterson's four grades are the shared language, and they are graded on clinical findings, not imaging. The grade sets both the urgency and the operation, so classify every ring before planning treatment.
- Description
- Simple constriction ring
- Distal Changes
- None - normal distal limb/digit
- Treatment
- Z-plasty if symptomatic, observe if mild
- Urgency
- Elective
- Description
- Constriction with distal lymphoedema
- Distal Changes
- Swelling, venous congestion, may have vascular compromise
- Treatment
- URGENT Z-plasty release
- Urgency
- Urgent
- Description
- Constriction with distal fusion
- Distal Changes
- Acrosyndactyly (digits fused at tips), webbed
- Treatment
- Staged release and digit separation
- Urgency
- Elective but early
- Description
- Intrauterine amputation
- Distal Changes
- Missing distal segment (finger, toe, limb)
- Treatment
- Prosthetic fitting, no surgical release
- Urgency
- N/A
Clinical Assessment
History. The family history is usually negative, because the condition is not genetic. Ask about:
- Prenatal history: maternal trauma, infection or drug use
- Birth history: a normal delivery, and any complications
- Family history of congenital anomalies
- Progression: is the constriction getting worse, which a Grade 2 band may do
- Symptoms: pain, swelling, functional limitation
- Other sites: every limb and digit is checked
Red flags. Four findings change the pace of the assessment:
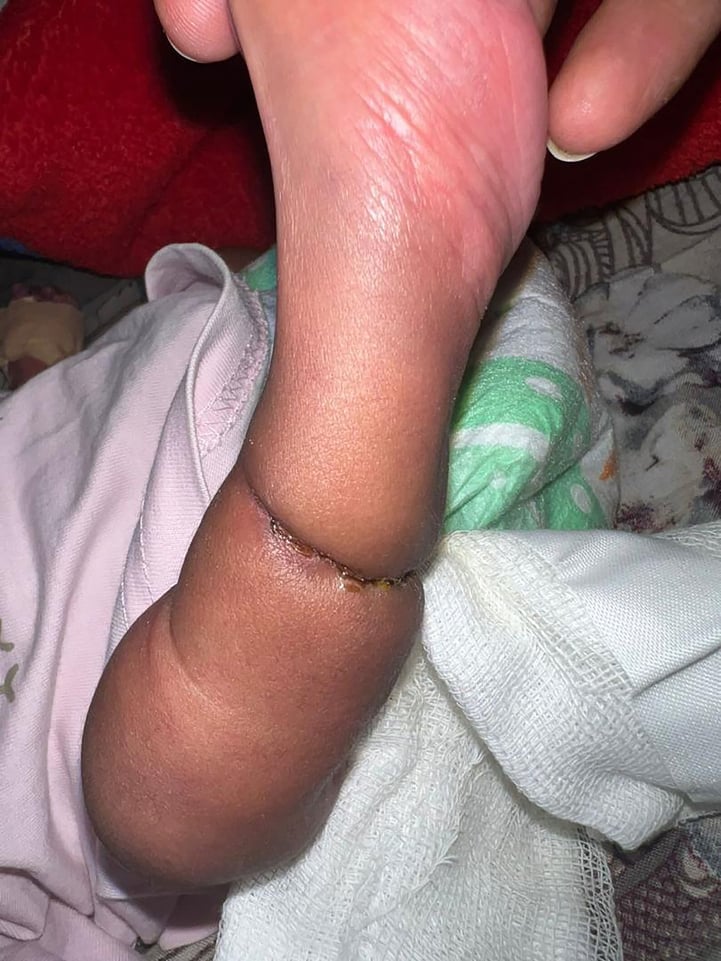
- Distal swelling: a Grade 2 band that needs urgent assessment
- Colour change: blue or purple distal to the band suggests vascular compromise
- Progressive constriction: may indicate active band tightening
- Multiple severe bands: may be part of a more complex syndrome
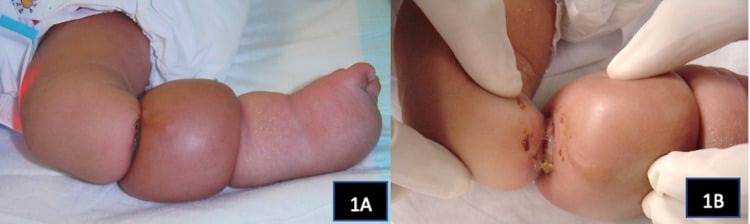
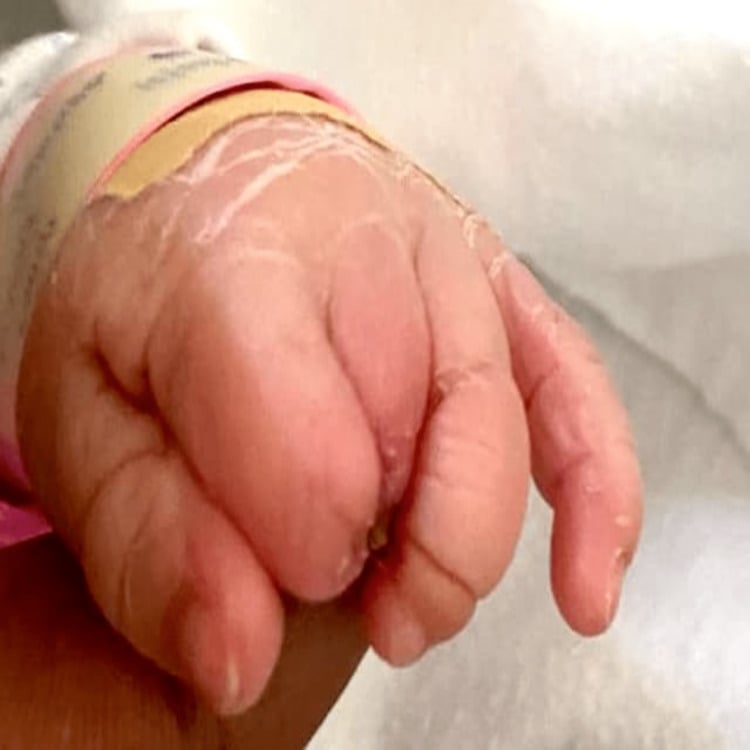
Inspection. Look for the rings themselves, visible grooves or indentations around a limb or digit, and for what lies beyond them: swelling (Grade 2), fusion (Grade 3) or amputation (Grade 4). Note the colour of the distal part, normal, pale or blue-purple, and check every limb, finger and toe, because the asymmetric pattern helps distinguish bands from genetic conditions.
Palpation. Judge the depth of each band, superficial or deep. Distal to a Grade 2 band the pulses may be diminished and the oedema pits; a cool distal part suggests vascular compromise, and sensation may be normal or decreased.
Motion and function. The joints beyond a tight constriction may have limited motion. Assess grip and pinch if fingers are involved and overall limb function if an arm or leg is.
Vascular assessment. Capillary refill should be under 2 seconds; distal pulses may be diminished, and Doppler, if available, assesses arterial flow. If vascular compromise is suspected, the limb needs urgent release, and the two speeds of "urgent" are set out in the Management section.
Amniotic band sequence is a sequence: the band that constricts a limb can entangle or be swallowed by other developing parts, so a complete assessment of the affected newborn looks beyond the obvious ring.
- Atypical (non-anatomical) facial clefts: bands can cause oblique or transverse facial clefts that do not follow the normal embryological cleft-lip and palate lines, a key clue that a cleft is band-related rather than a typical orofacial cleft
- CNS and cranial defects: encephalocele, anencephaly and asymmetric or atypical skull defects can occur when bands involve the head
- Body-wall defects / limb-body-wall complex (LBWC): the severe end of the spectrum, with thoraco-abdominoschisis, scoliosis and short cord, usually lethal and distinct from isolated peripheral bands
- Secondary deformities: bands proximally can produce a secondary (non-idiopathic) clubfoot or other postural deformities distal to the constriction, which behave and are treated differently from idiopathic clubfoot. Expect a stiffer, less Ponseti-responsive foot, and do not counsel the family with idiopathic-clubfoot correction rates
Exam point: in any baby with a constriction band, examine all limbs and the face, skull and trunk. Atypical facial clefts, cranial defects or a body-wall defect both confirm the diagnosis (asymmetric, non-anatomical pattern) and signal a more severe sequence; isolated limb bands carry a far better prognosis than limb-body-wall complex.
Investigations
A clinical diagnosis. A constriction ring, with or without distal changes, is diagnostic, and clinical examination is the primary diagnostic method in every case. Imaging confirms the extent of the problem but is not required to make the diagnosis, and the Patterson grade is assigned on clinical findings.
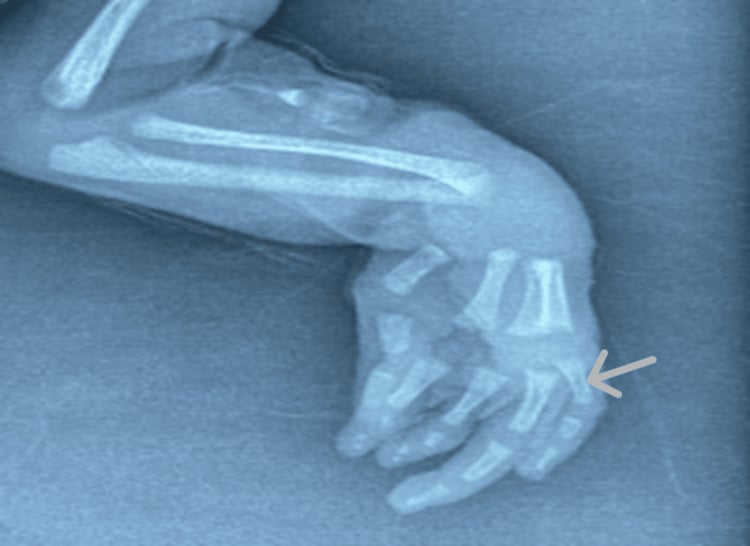
Radiographs. AP and lateral views are taken in all cases to define the bone beneath the ring and any underlying anomaly, and to plan surgery. They may show distal hypoplasia, shortened or underdeveloped bones, and in Grade 3 they may show bony fusion of the digits.
Doppler ultrasound. Reserved for a Grade 2 band with oedema, to assess arterial flow; it may also show dilated lymphatics. It is not routine, because the clinical diagnosis is usually sufficient.
Genetic testing. Considered only when there are multiple anomalies, to rule out a syndrome. The result is usually normal, as expected of a condition that is not genetic.
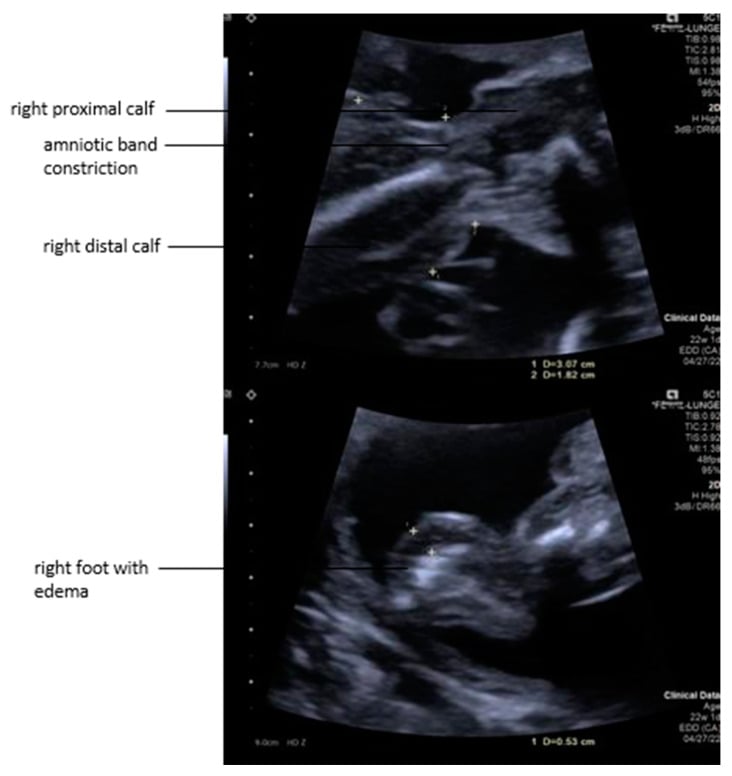
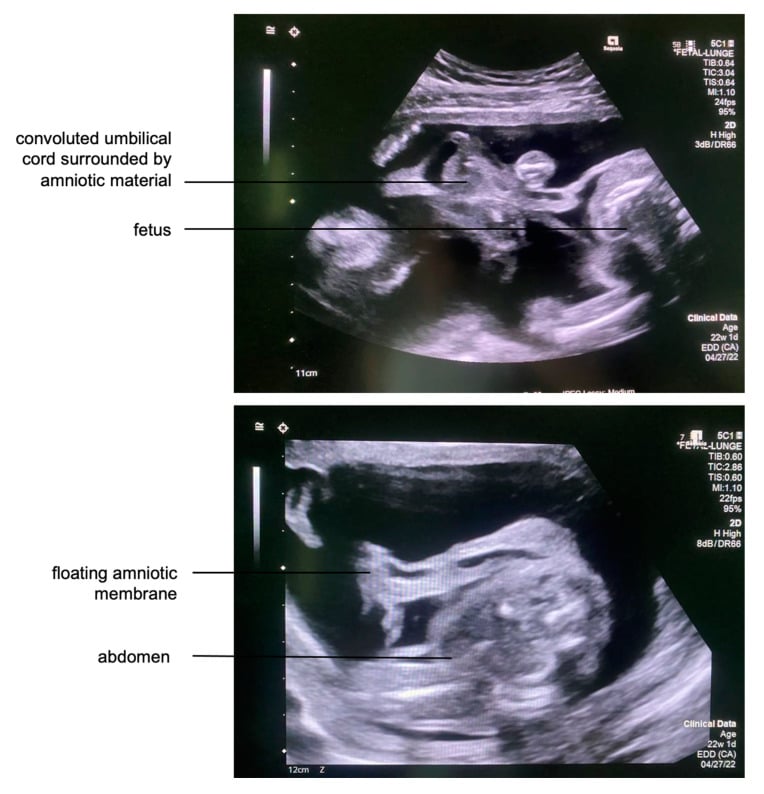
Antenatal imaging. Prenatal ultrasound can show the band itself and, more reliably, its consequence: a step in limb calibre with distal soft-tissue oedema. Serial scans matter because progression of the oedema is what raises the question of in-utero release, and cord involvement is the finding that turns a limb problem into an immediate threat to the fetus and changes obstetric management.
Differential Diagnosis
The defining feature of amniotic band sequence is an acquired, asymmetric, non-anatomical constriction with normal proximal anatomy. Genuine longitudinal and transverse limb deficiencies are intrinsic developmental field defects and follow predictable anatomical patterns: symbrachydactyly has missing central rays, radial club hand a radial deficiency, Poland syndrome an absent pectoralis. Each of the main mimics has its own page, syndactyly, radial longitudinal deficiency, Poland syndrome and thumb hypoplasia, and the field as a whole is set out in the congenital hand overview.
- Key Feature
- Circumferential groove with normal proximal limb
- Symmetry / Pattern
- Asymmetric, non-anatomical, often multiple limbs
- Discriminator from Bands
- Visible ring; distal lymphoedema, acrosyndactyly or amputation; sporadic
- Key Feature
- Short/absent central digits, often nubbins
- Symmetry / Pattern
- Unilateral, follows a developmental gradient
- Discriminator from Bands
- No constriction ring; transverse/central deficiency; Poland-spectrum association
- Key Feature
- Radial deviation, absent/hypoplastic radius and thumb
- Symmetry / Pattern
- May be bilateral; syndromic (VACTERL, TAR, Holt-Oram)
- Discriminator from Bands
- Longitudinal axis deficiency, not a ring; warrants systemic work-up
- Key Feature
- Fusion from the web base distally, normal length
- Symmetry / Pattern
- Often bilateral, familial, web extends proximally
- Discriminator from Bands
- No ring elsewhere on the limb; familial rather than sporadic
- Key Feature
- Cord or trunk involvement, major visceral defects
- Symmetry / Pattern
- Severe, often lethal
- Discriminator from Bands
- Bands extend beyond limbs; not isolated peripheral rings
The classic discriminator examiners probe: acrosyndactyly (Patterson Grade 3) shows distal-tip fusion with a proximal sinus or fenestration that a probe can pass through, reflecting an extrinsic band rather than a failure of separation. True congenital syndactyly fuses from the web space distally with no proximal opening. Constriction rings elsewhere on the limb seal the diagnosis of amniotic band sequence.
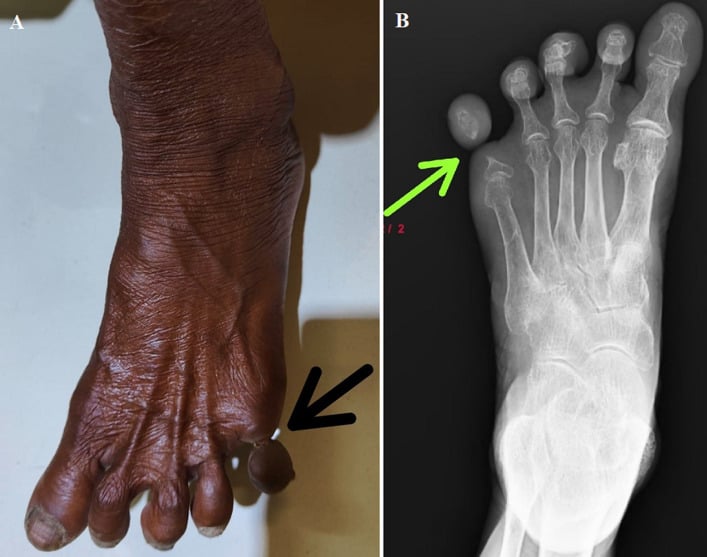
Acquired mimics. Two acquired constrictions can be mistaken for a congenital band.
Management Algorithm
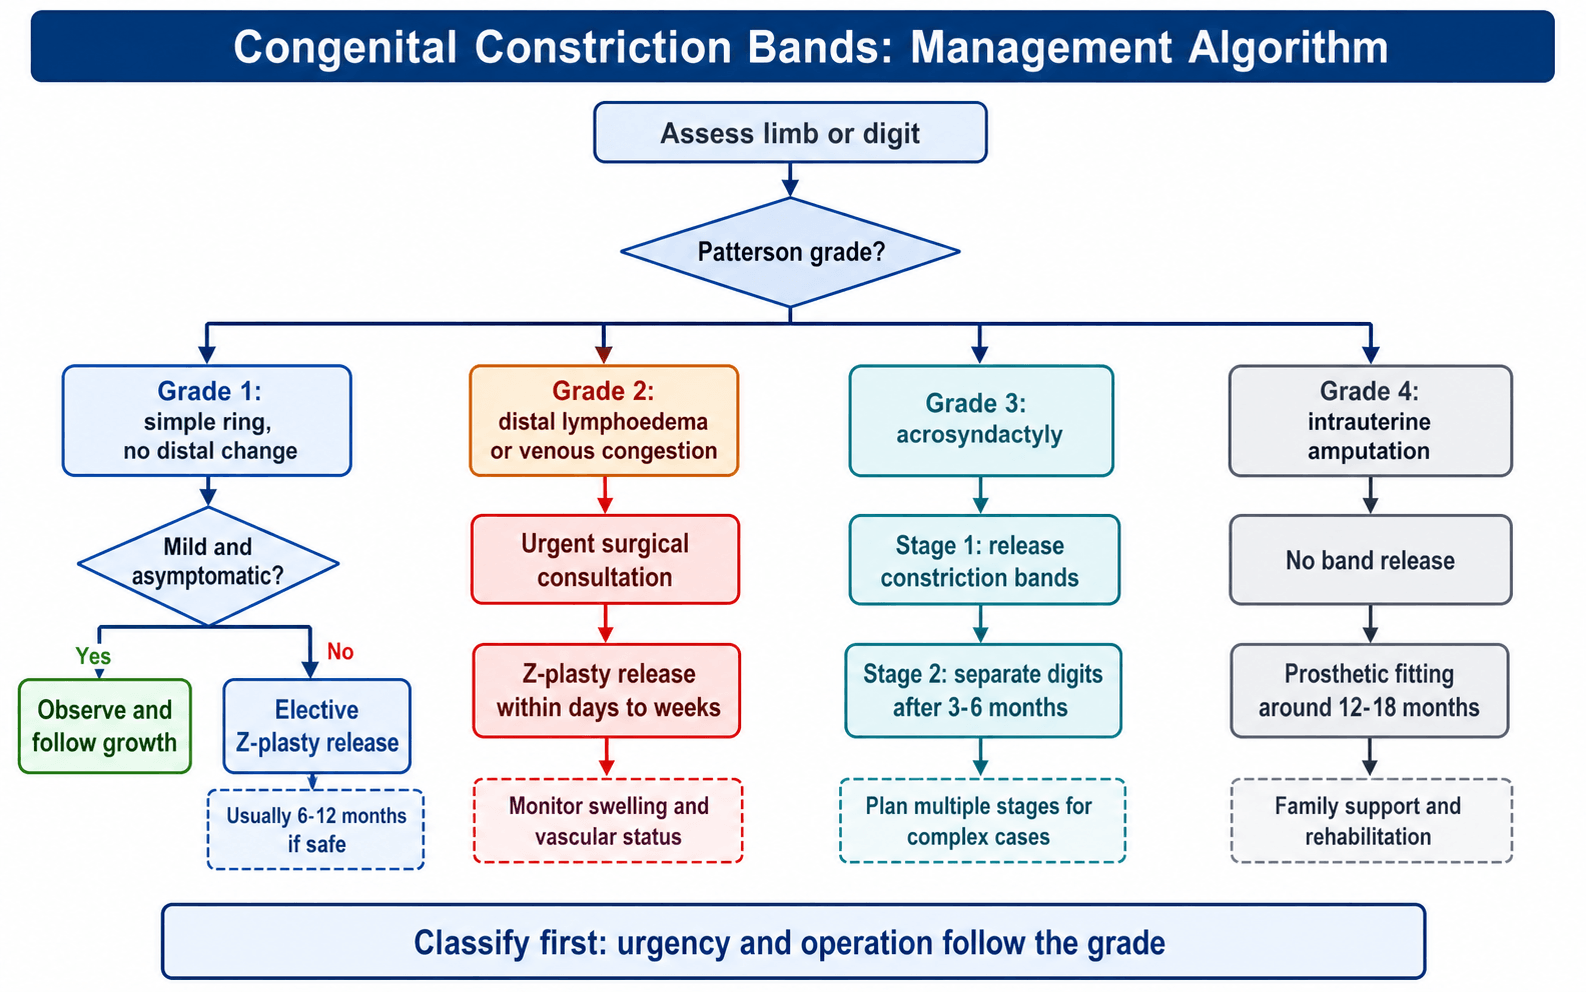
Grade 1. A simple ring with no distal change can be observed if it is mild and asymptomatic. Release is offered where the constriction is deep, symptomatic or a cosmetic concern, and it can wait until the child is 6-12 months old, when anaesthesia is easier; the operation is 2-4 Z-plasties around the circumference to lengthen and break up the ring.
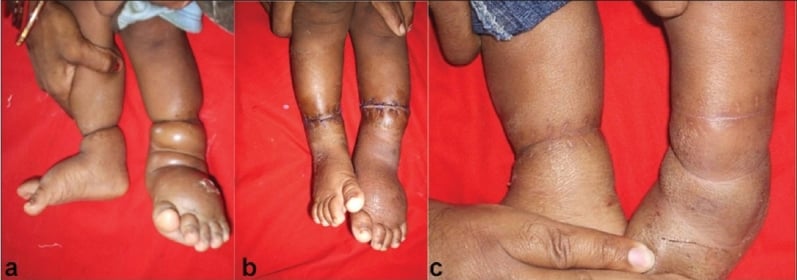
Grade 2. Distal lymphoedema means active obstruction, so release is urgent: within days to weeks, depending on severity, as a complete release with multiple Z-plasties. Afterwards the oedema is watched for resolution, and compression may be needed.
Grade 3. Acrosyndactyly is treated in stages. Stage 1 is Z-plasty release of the constriction bands; Stage 2 is digit separation, usually 3-6 months later, and complex cases may need several stages.
Grade 4. There is nothing to release after an intrauterine amputation. The child is fitted with a prosthesis when ready, usually at 12-18 months; early fitting matters for development and acceptance, and the family is counselled about the prosthetic options.
"Days to weeks" is the timeframe for a swollen but perfused limb. It is not the timeframe for an ischaemic one. Separate the two explicitly, because the examiner's follow-up is almost always "and what if the digit turns blue?":
- Lymphoedematous, warm, pink, capillary refill under 2 seconds: urgent list, days to weeks. The threat is progressive obstruction, not imminent necrosis.
- Dusky, blue or purple, cool, sluggish or absent capillary refill, diminished pulse: this is critical ischaemia in a neonate and an emergency release, not an urgent-list case. Do not wait for a Doppler, an MRI or the next available list; imaging confirms extent and must never delay decompression. The principle is the same one that governs any acutely ischaemic limb, the constricting structure comes off now, and the reconstruction can be planned afterwards.
- Established dense sensory loss distal to the band (an insensate foot or digit): release is still indicated, but counsel the family that the deficit may not reverse and the limb remains at risk. In the one modern technique series, the single amputation was in exactly this child (PMID 35188902).
Non-operative measures. Observation is reasonable only for a mild Grade 1 band, many of which cause no functional problem. Massage and stretching may help a mild constriction, on limited evidence; splinting is not typically helpful and serial casting is not indicated. Most cases will need surgical release for the best outcome, and the indications are:
- Deep constriction causing functional limitation
- Cosmetic concern
- Progressive constriction
- Grade 2 or higher
Antenatal (fetoscopic) release. Where a band is detected antenatally and is progressively constricting a still-perfused limb, or is threatening the umbilical cord, fetoscopic division is offered in a small number of fetal-surgery centres. It is the one point in this topic where an intervention has to be weighed against a substantial risk to the whole pregnancy, so quote the figures rather than the concept. The PRISMA systematic review pooled 17 studies and 37 fetuses, operated at a median of 22 weeks (range 18-29) (PMID 39080813):
- Fetal survival 89.2%
- Limb preserved and functional in 75.7%, which is the benefit being bought
- PPROM in 51.3%: preterm prelabour rupture of membranes in roughly half of cases, and the dominant complication
How to present this in a viva. The strongest indication is cord constriction, where the alternative is fetal death and a 51% PPROM rate is a proportionate trade; the case is weaker for an isolated limb band, where postnatal release of a Grade 1-2 ring is straightforward and the limb is not usually lost. Patient selection remains undefined, the review's own conclusion being that further studies are needed to determine who benefits, so the honest position is that this is a developing option for a narrow group, not an emerging standard. Note also that 37 pooled cases from 17 reports carries the usual publication bias of a small-series literature.
Surgical Technique
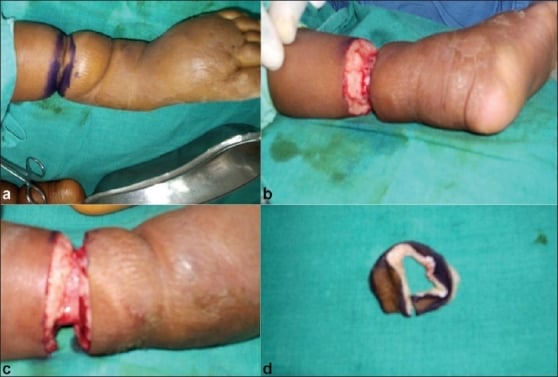
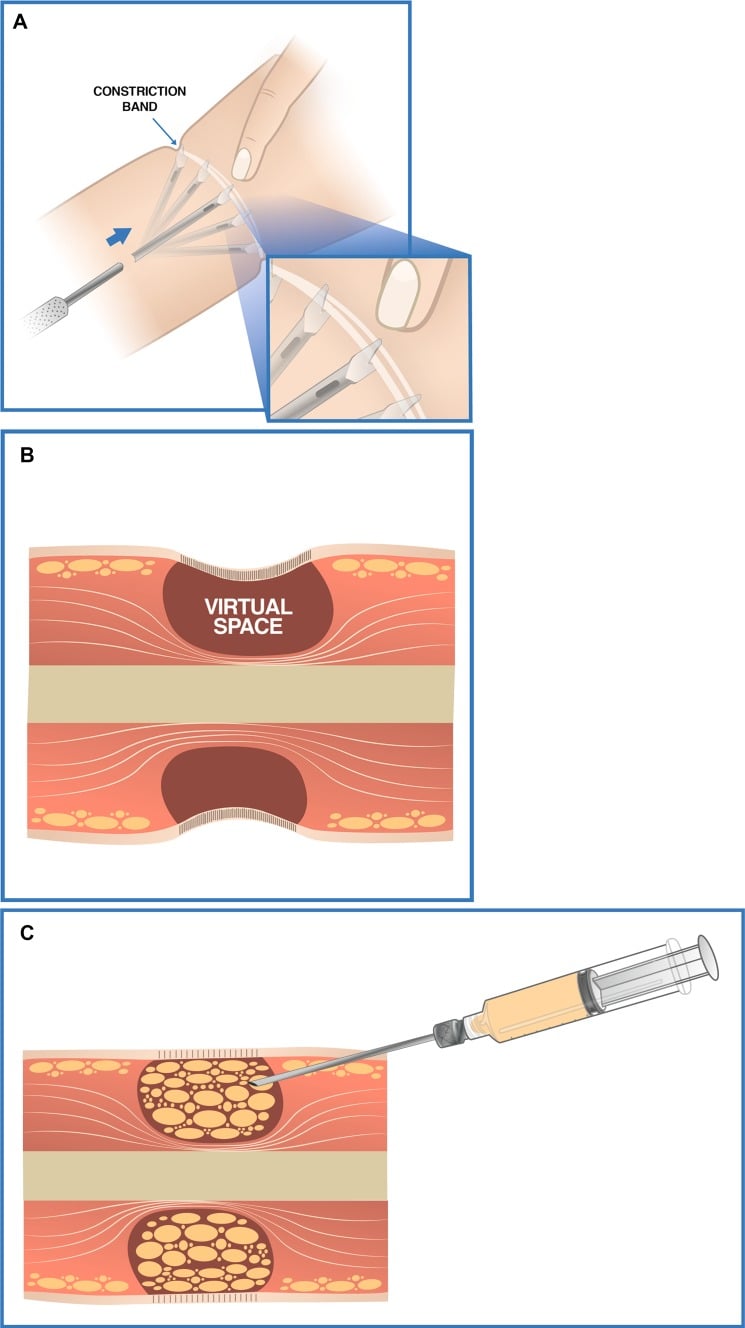
The principle. Multiple Z-plasties around the circumference lengthen the constriction and break up the ring, and a complete release is what prevents recurrence: inadequate release allows the constriction to reform as the child grows.
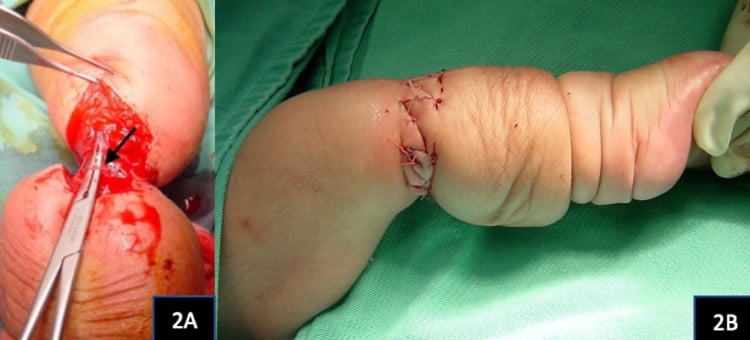
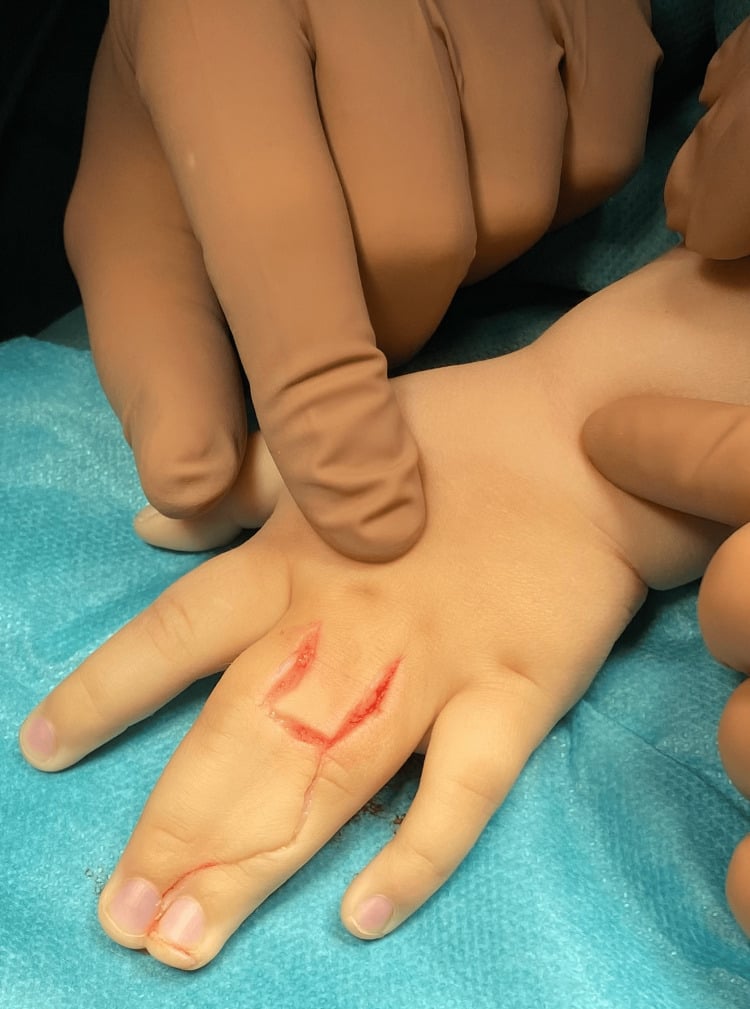
- Plan. Mark the full extent of the ring and design 2-4 Z-plasties around the circumference, with 60-degree angles and limbs of 5-10 mm so that the flaps keep their blood supply.
- Incise and raise the flaps. Cut through the constriction ring and raise skin and subcutaneous tissue as flaps, preserving their vascularity; release the fascia if the constriction is deep.
- Transpose. Interdigitate the flaps, which lengthens the circumference and breaks up the ring, and check that no residual constriction remains.
- Close. Suture the flaps; drains are usually not needed. Apply a non-constrictive dressing that allows for swelling, and a splint may protect the repair.
A Z-plasty lengthens tissue by interdigitating triangular flaps. The theoretical length gain rises with the angle: 30° gives 25%, 45° gives 50%, 60° gives 75%, 75° gives 100%. Theoretical, because skin tension and flap geometry mean the gain achieved in practice is less.
The objection to piecemeal Z-plasty. The "2-4 Z-plasties around the circumference" taught above is the classical answer and remains a correct one, but an examiner who reads the modern literature will push further. The persistent problem after discrete circumferential Z-plasties is a residual hourglass deformity, a visible waist at the level of the old band, because the flaps lengthen the skin envelope without removing the tethering fibrous ring itself. Chan et al. list the deficits that can persist after existing excision techniques as hourglass deformity, lymphoedema, and inadequate band excision with resultant neurovascular compromise, which may lead to revision surgery, including amputation (PMID 35188902).
Excision with continuous opposing flaps. The contemporary principle is therefore excision of the fibrous band plus reconstruction with continuous opposing flaps, in one or two stages, rather than a piecemeal release. Chan's series used multiple continuous opposing Y-to-V-plasties in 7 patients with 10 involved extremities: all achieved primary closure with excellent healing, no infections or scar complications, and no band required revision surgery. Post-operative lymphoedema occurred in two patients and resolved with compression bandaging over several weeks.
Two honest caveats. First, this is a Level IV retrospective series of seven patients with no comparator: a description of a technique that works, not proof that it beats Z-plasty. Second, the one bad outcome in the series was not a technique failure. A child who already had pre-operative sciatic compression neuropathy and an insensate foot from the band went on to chronic calcaneal osteomyelitis and ultimately a Syme amputation. That is the single most useful prognostic point on this page: a band that has already produced a dense neurological deficit distal to it carries a limb-threatening trajectory that releasing the band does not reverse, and it belongs in the consent discussion.
One stage or two, and why the answer has changed. The historical rule was to release only half the circumference at a time, with a second operation months later, on the reasoning that a deep circumferential band leaves marginal venous and lymphatic drainage and dividing the whole ring at once might devascularise the part distal to it. That fear generated the staged operation; it is not what the modern series show. A review of the published experience with one-stage circumferential release concluded plainly that "surgeons may continue the practice to release circumferential [constriction ring syndrome] in one stage" (PMID 25692440), and a 14-patient multicentre series of one-stage circumferential resection with direct circular closure, at a mean age of 13.3 months and mean follow-up of 3.9 years, reported no vascular, neurological or scar-related complications at any point (PMID 33012696). The defensible position is that one stage is the default for most bands, and staging is a judgement call reserved for the deepest circumferential band with genuinely compromised distal perfusion, not a rule to apply reflexively. Be honest about the evidence when you say it: these are small retrospective series, 17 patients across 14 publications in the review and 14 patients in the largest single series, with no randomised comparison of one stage against two, so this is accumulated safe experience rather than proof of equivalence.
The exam answer. Name the Patterson grade, say you would excise the band and resurface with continuous opposing flaps (Y-to-V or Z-plasty) in one or two stages rather than a piecemeal release, and give avoiding the hourglass deformity as your reason.
Complications
The complications of the condition and of its release are listed together, because the two overlap: recurrence and vascular compromise arise from both. The recurrence figure is a conventional teaching estimate rather than a measured rate.
- Incidence
- 5-10% (conventional estimate)
- Cause / Risk Factors
- Incomplete release, inadequate Z-plasties
- Management
- Revision Z-plasty
- Incidence
- Rare
- Cause / Risk Factors
- Poor vascularity, tight closure
- Management
- Debridement, local flaps
- Incidence
- 5%
- Cause / Risk Factors
- Contamination, poor healing
- Management
- Antibiotics, debridement
- Incidence
- 10-15%
- Cause / Risk Factors
- Healing issues, inadequate release
- Management
- Revision, scar management
- Incidence
- Rare but serious
- Cause / Risk Factors
- Tight constriction with delayed release; injury to vessels during release
- Management
- Urgent release or exploration and vascular repair; may need amputation
- Incidence
- Common in Grade 3-4
- Cause / Risk Factors
- Early constriction, growth restriction
- Management
- Accept or lengthening procedures
- Incidence
- Variable
- Cause / Risk Factors
- Severity, location, multiple bands
- Management
- Therapy, adaptive devices
- Incidence
- Common
- Cause / Risk Factors
- Visible constriction rings, amputations
- Management
- Reassurance, revision surgery if severe
Postoperative Care and Rehabilitation
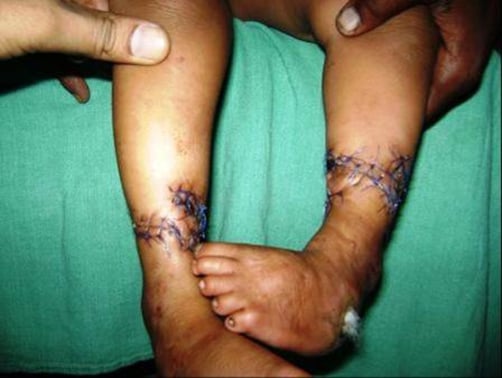
Weeks 0-2. The dressing is non-constrictive and allows for swelling, the limb is elevated to reduce oedema, and the wound is kept clean and dry and watched for infection. A splint may protect the repair.
Weeks 2-6. Sutures come out at 10-14 days. Scar massage begins once the wound has healed, gentle range of motion starts if joints are involved, and the wound and the ring are checked for healing and recurrence.
Months 2-6. Scar management continues, with silicone sheets if needed; occupational or physical therapy is arranged where digits or limbs are affected; growth distal to the release is monitored, and follow-up looks for recurrence.
Long term. Annual review monitors recurrence and growth, assesses function and development, and addresses cosmetic concerns if significant. Further procedures are planned where needed, for Grade 3 separation or for recurrence.
Rehabilitation. Scar management is essential to prevent contracture; functional therapy follows where digits or limbs are affected, adaptive devices may be needed in severe cases, and psychological support matters for children and families.
Outcomes
Long-term outcomes. The percentages below are conventional teaching estimates, not measured rates. This condition has no cohort large enough to generate them: the surgical series on this page number 37 children (Homer) and 7 patients (Chan), and "good to excellent" is nowhere defined as an endpoint. Quote the direction and the mechanism; if pressed on the figures, say plainly that they are customary rather than derived. What the modern series does support is narrower and more useful: primary healing in all 10 extremities with no band revision required after single- or two-stage excision with continuous opposing flaps (PMID 35188902).
- Good to excellent results in 90-95% with appropriate release (conventional estimate; endpoint undefined)
- Recurrence is usually from incomplete release
- Functional outcomes depend on severity and location
- Grade 1: excellent outcomes with release
- Grade 2: good outcomes if released urgently
- Grade 3: variable outcomes, may need multiple procedures
- Grade 4: prosthetic outcomes generally good with early fitting
What predicts the result. Severity, since Grades 1-2 do better than Grades 3-4; timing, since earlier release, especially of a Grade 2 band, does better; completeness of release, since incomplete release leads to recurrence; and location, since fingers and toes generally do better than limbs.
Guidelines, Registries & Global Practice
No formal society guideline (AAOS / BOA / NICE / EFORT) addresses amniotic band sequence specifically — the condition is too rare and heterogeneous for guideline development, and the evidence base is Level III-IV. Practice is therefore guided by classification (Patterson), case-series experience, and registry epidemiology rather than graded recommendations.
Global epidemiology and registry evidence:
- Region
- Australia
- Key Datum
- Prevalence 2.03 per 10,000 births; maternal age under 25 and primiparity associated
- Evidence Level
- III (registry case-control)
- Region
- Europe (Finland)
- Key Datum
- Population case-control; primiparity and first-trimester beta-blocker/progestogen associations
- Evidence Level
- III
- Region
- Europe (multi-country)
- Key Datum
- Surveillance platform tracking limb-reduction and amniotic-band defects across populations
- Evidence Level
- III (surveillance)
- Region
- USA
- Key Datum
- Multi-site case-control; secondhand-smoke association with ABS-limb body wall complex
- Evidence Level
- III
- Region
- UK
- Key Datum
- Tertiary surgical series; ~1 in 15,000; upper-limb predominance
- Evidence Level
- IV (case series)
Practice variation and global access:
- Managed in paediatric orthopaedic/plastic hand units with multidisciplinary limb-deficiency clinics
- Antenatal ultrasound increasingly detects bands and threatened limbs; selected fetoscopic release offered in a few fetal-surgery centres (Cincinnati, European units) for progressive limb or cord constriction
- Microsurgical toe-to-hand transfer and prosthetics available for severe loss
- Frequently diagnosed only postnatally (limited antenatal screening) — case reports from Somalia and Burkina Faso illustrate first documented presentations
- Emphasis on simple band release / Z-plasty under local or topical anaesthesia where theatre access is limited
- Prosthetic provision and staged reconstruction often constrained; early simple release of threatening Grade 2 bands remains the priority intervention
- Patterson classification as the shared language
- Urgent release of bands with distal lymphoedema/vascular threat
- Single- or two-stage circumferential excision with opposing flaps (Z-plasty or Y-to-V) preferred over piecemeal release
- Sporadic aetiology — reassurance regarding negligible recurrence risk
- Patient selection for fetoscopic release (limb salvage vs PPROM risk) is undefined
- Optimal timing of acrosyndactyly separation (early neonatal vs 3-6 months) is debated
- Best technique to avoid residual hourglass deformity after circumferential release
- Whether maternal medication associations are causal or confounded
- Key documentation: Patterson grade, vascular/lymphoedema assessment, timing rationale (urgent vs elective)
- Consent: staged approach for Grade 3, recurrence/hourglass-deformity risk, likely need for multiple procedures
- Common pitfalls: missing the urgency of a distally oedematous band; incomplete release leading to recurrence
Key documentation points:
- Patterson classification (Grade 1-4) clearly documented
- Assessment of urgency (especially Grade 2)
- Discussion of treatment plan and staging if Grade 3
- Family counseling about prognosis and need for multiple procedures
- Timing of surgery (urgent vs elective)
Don't Delay Grade 2: Missing the urgency of Grade 2 constriction bands with distal edema is a serious issue. These require urgent release, and delay may lead to tissue loss or amputation.
MCQ Practice Points
Q: A newborn has a constriction ring around a finger with swelling of the fingertip. What is the Patterson grade and management? A: Grade 2 - constriction with distal lymphedema. This requires URGENT Z-plasty release to prevent progression to tissue loss. The edema indicates active lymphatic obstruction that may worsen if not treated promptly.
Q: How many Z-plasties are typically needed for constriction band release? A: Usually 2-4 Z-plasties around the circumference. Multiple Z-plasties ensure complete release and prevent recurrence. The Z-plasties should have 60-degree angles for optimal length gain (75% theoretical increase; the gain achieved in practice is less). Add the modern qualifier for full marks: piecemeal circumferential Z-plasty is what leaves a residual hourglass deformity, so the contemporary principle is to excise the fibrous band and resurface with continuous opposing flaps (Y-to-V or Z-plasty) in one or two stages.
Q: How do you distinguish constriction bands from symbrachydactyly? A: Constriction bands are asymmetric, irregular, and may affect multiple limbs. Symbrachydactyly is central ray deficiency (missing middle fingers), usually unilateral. Constriction bands have visible constriction rings, while symbrachydactyly has absent rays.
Q: Which Patterson grade requires urgent surgical release? A: Grade 2 (constriction with distal lymphedema) requires urgent release. The edema indicates active lymphatic obstruction that may progress to vascular compromise and tissue loss. Grade 1 can be observed or treated electively, Grade 3 is staged, Grade 4 needs prosthetics.
Q: How do you prevent recurrence after Z-plasty release? A: Complete release with multiple Z-plasties around the entire circumference. Incomplete release allows the constriction to reform as the child grows. Using 2-4 Z-plasties with 60-degree angles ensures adequate lengthening and breaks up the constriction ring completely.
Q: How do you manage Grade 3 constriction bands with acrosyndactyly? A: Staged approach: Stage 1 is Z-plasty release of constriction bands, allowing 3-6 months for healing. Stage 2 is digit separation, creating web spaces and separating fused digits while preserving neurovascular bundles. Multiple procedures may be needed for complex cases.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A newborn is noted to have a constriction ring around the middle finger with swelling of the fingertip. The constriction is deep and the distal finger is edematous.”
“Walk me through the Z-plasty release technique for a constriction band.”
“A 6-month-old has multiple constriction bands affecting several fingers. Some fingers are fused at the tips (acrosyndactyly), and one finger has a constriction ring with distal swelling.”
Patterson Classification
- Grade 1: Simple ring, no distal changes = elective release
- Grade 2: Ring with distal edema = URGENT release
- Grade 3: Ring with acrosyndactyly = staged release and separation
- Grade 4: Intrauterine amputation = prosthetic fitting
Key Clinical Features
- Asymmetric, irregular constriction rings
- Not hereditary - sporadic, negligible recurrence risk (the key counselling point)
- Multiple bands are common: 17 of 37 had BOTH upper- and lower-limb involvement (Alder Hey)
- Examine every limb, and the face, skull and trunk - it is a sequence, not just a ring
- Variable severity from simple ring to amputation
Surgical Technique
- Modern principle: EXCISE the fibrous band, resurface with CONTINUOUS OPPOSING flaps (Y-to-V or Z-plasty), one or two stages - not a piecemeal release
- Reason: piecemeal circumferential Z-plasty leaves a residual HOURGLASS deformity
- Classical Z-plasty release: 2-4 Z-plasties around circumference
- 60-degree angles give a THEORETICAL 75% length gain (45deg = 50%, 75deg = 100%)
- Complete release essential to prevent recurrence
- Preserve flap vascularity
Treatment Urgency
- Grade 1: Elective (6-12 months)
- Grade 2: URGENT (days to weeks)
- Grade 3: Staged (release then separation)
- Grade 4: Prosthetic fitting (12-18 months)
Complications
- Recurrence: 5-10% if incomplete release
- Flap necrosis: Rare but serious
- Wound infection: 5%
- Scar contracture: 10-15%
Evidence Base
The amniotic band sequence literature is dominated by retrospective case series and narrative reviews (Oxford Level III-IV). No randomised trials exist, and is unlikely to, given the rarity and heterogeneity of the condition. The cards below combine the original classification, contemporary surgical-technique series, population-based epidemiology, and the emerging fetal-surgery evidence base.
Congenital ring-constrictions
- Foundational description distinguishing four presentations: simple ring; ring with distal deformity/lymphoedema; ring with distal fusion (acrosyndactyly); intrauterine amputation
- Established that bands and their distal sequelae, not heredity, drive the deformity
- Introduced multiple Z-plasty release as the operative principle
- Framework still in routine clinical and examination use over six decades later
Amniotic Constriction Bands — Case Series and Proposed Classification
- 37 children over 1993-2012 at a single tertiary paediatric centre; 28 underwent surgery, 9 managed non-operatively
- Upper-limb bands were the most common pattern and lower-limb the least; 17 of 37 had combined upper- and lower-limb involvement
- Cited an approximate incidence of 1 in 15,000 live births
- Highlighted lack of consensus nomenclature and proposed an upper-limb scheme incorporating anatomical location and band depth
Multiple Continuous Y-to-V-Plasties for Constriction Band Excision
- 7 patients, 10 involved extremities; band excision with continuous opposing Y-to-V-plasties in one or two stages
- All achieved primary wound healing with no band revision required
- Technique designed to avoid the residual hourglass deformity that can follow simple circumferential Z-plasty
- Post-operative lymphoedema in 2 patients resolved with compression; one neuropathic insensate foot ultimately required Syme amputation
Risk Factors and Prevalence of Amniotic Band-Associated Limb Deficiency
- Nationwide Finnish population-based case-control study, 106 cases versus 530 matched controls (births 1996-2008)
- Young maternal age (less than 25 years) increased risk (OR 1.72, 95% CI 1.06-2.80)
- Primiparity was an independent risk factor (adjusted OR 2.42, 95% CI 1.52-3.88)
- Novel associations with first-trimester maternal beta-blocker and progestogen use
Amniotic Band Syndrome — Australian Population-Based Prevalence
- Two Australian state birth-defect registries (Western and South Australia)
- Prevalence 2.03 per 10,000 births (approximately 1 in 4,900)
- Equal sex distribution; more common with maternal age under 25 years and in first births
- Limb-only defects in 24 cases, limb-body-wall in 4, craniofacial/complex in 12
Fetoscopic Release of Amniotic Bands — Systematic Review
- PRISMA systematic review: 17 studies, 37 fetuses undergoing fetoscopic band release (median 22 weeks)
- Fetal survival 89.2%; limb preserved and functional in 75.7%
- Preterm premature rupture of membranes in 51.3% — the dominant complication
- Strongest rationale where bands threaten the umbilical cord or a still-perfused limb
Prosthetic and Reconstructive Management of Limb Deficiency
- Early prosthetic fitting (around sitting/standing milestones) improves acceptance for congenital amputation
- Toe-to-hand transfer can restore prehension in adactylous constriction-band hands
- Multidisciplinary limb-deficiency clinics optimise function and family support
- Reconstruction is individualised to residual anatomy and functional goals
One-stage circumferential release: the modern default
- Multicentre retrospective series of 14 patients with amniotic band syndrome (mean age 13.3 months) treated by ONE-STAGE circumferential resection of the ring with direct circular skin closure
- Mean follow-up 3.9 years, with assessment of scar quality on both the POSAS and Vancouver scales
- NO scar-related, vascular or neurological complications - either postoperatively or at final follow-up
- This is the direct answer to the historical fear that dividing a deep circumferential band in one sitting would devascularise the part distal to it
Review of the safety of one-stage circumferential ring release
- Systematic search of the English literature 2001-2011 for one-stage circumferential release; 14 publications met criteria, reporting 17 patients with 25 ring constrictions
- Sixteen of the 25 rings (64%) were fully circumferential and 9 (36%) semi-circumferential
- Mean age was 4.8 years for the 14 patients treated in one stage, against 10.5 months for the 3 treated in stages
- The authors' conclusion is explicit: it is confirmed that surgeons may continue the practice of releasing circumferential constriction ring syndrome in one stage
For severe upper-limb amniotic band sequence with multi-digit loss or acrosyndactyly, microsurgical second-toe (and double second-toe) transfer can create a sensate, mobile digit for tip-to-tip pinch. For Grade 4 lower-limb loss the pathway is prosthetic instead — see prosthetic limb components and the congenital lower limb deficiency overview. Series report viable, growing transfers (growth roughly 68-95% of the donor toe) but with mediocre active motion and a near-universal need for secondary procedures, so families must be counselled about staged, long-horizon reconstruction.