O'Driscoll Classification | Elbow Stability Keystone | Terrible Triad Component
- Coronoid is the anterior buttress - prevents posterior subluxation
- LOCATION beats SIZE: every one of 32 terrible triads in Doornberg's series had a fracture UNDER 50% - the 50% rule describes isolated coronoid loss with intact ligaments, not the injured elbow in front of you
- Terrible triad component - dislocation + radial head + coronoid
- Anteromedial facet fractures are often varus-posteromedial pattern
- Never ignore - instability leads to poor outcomes
- “Anteromedial facet fractures have different mechanism - varus stress, not dislocation
- “Coronoid tip fractures in terrible triad may need fixation despite small size
- “Basal fractures always unstable - include brachialis insertion
- “Sublime tubercle involvement means MCL attachment disrupted
Overview and Epidemiology
The coronoid is fractured almost exclusively as part of an elbow instability pattern; an isolated coronoid fracture is rare. Most occur with an elbow dislocation or another fracture pattern, most often the terrible triad, alongside an olecranon fracture or within a Monteggia lesion. The coronoid is critical to elbow stability, so the fracture is read as a clue to the pattern around it.
Mechanism. Each O'Driscoll type has its own mechanism, and the type therefore predicts the injuries that travel with it.
- Posterolateral dislocation, the most common, shears off the coronoid tip as the elbow dislocates: the Type I tip fracture of the terrible triad
- Varus-posteromedial rotational instability, an axial load with a varus stress, produces the Type II anteromedial facet fracture, typically without a frank dislocation
- High-energy direct trauma drives significant force through the ulnohumeral joint and produces the Type III basal fracture
What travels with it. Over 75% occur with an elbow dislocation, and the LCL complex is ruptured whenever the elbow has dislocated. A radial head fracture makes it a terrible triad; an olecranon fracture makes it a transolecranon pattern. With an anteromedial facet fracture the MCL is usually intact, or is avulsed with the sublime tubercle fragment.
Anatomy and Biomechanics
The coronoid. The anterior projection of the proximal ulna, forming the anterior buttress of the greater sigmoid notch. Its attachments matter because each fracture location takes one with it: the anterior capsule attaches to the tip, the anterior bundle of the MCL to the sublime tubercle on the medial side, and brachialis across the anterior surface of the base. The lateral facet articulates with the radial head at the radioulnar joint.
The sublime tubercle. On the ulnar side of the coronoid, it is the insertion of the anterior bundle of the MCL, the most important component of the ligament and its anchor for valgus stability. A fracture through it is a bony avulsion of the MCL, which is why fixing the fragment restores the MCL insertion.
Stability. The coronoid is the primary anterior buttress against posterior subluxation: with the olecranon it is the primary constraint to posterior translation, with the MCL and radial head a secondary valgus stabiliser, and with the radial head it resists axial load. The classic teaching is that loss of more than 50% of coronoid height produces significant instability; smaller fractures can contribute to instability in the presence of ligamentous injury, and what the 50% figure actually measures is set out below.
The 50% figure is quoted throughout the textbooks and is worth knowing. Used as the operative threshold it is wrong, and the two papers cited on this page demonstrate that directly.
- In Doornberg & Ring's consecutive series of 67 surgically treated coronoid fractures, all 32 terrible-triad injuries had small fractures of under 50% (PMID 16443103). The terrible triad is the archetypal unstable elbow; if size were the determinant, none of those 32 elbows would have been unstable.
- In their anteromedial facet series the fragments are by definition small, yet in the six elbows where the facet was not specifically fixed or lost fixation, every one developed varus subluxation, arthrosis and a fair or poor result (PMID 17015599).
- Conversely, 22 of 24 olecranon fracture-dislocations had large coronoid fractures: large fragments cluster with a pattern that is unstable for a different reason.
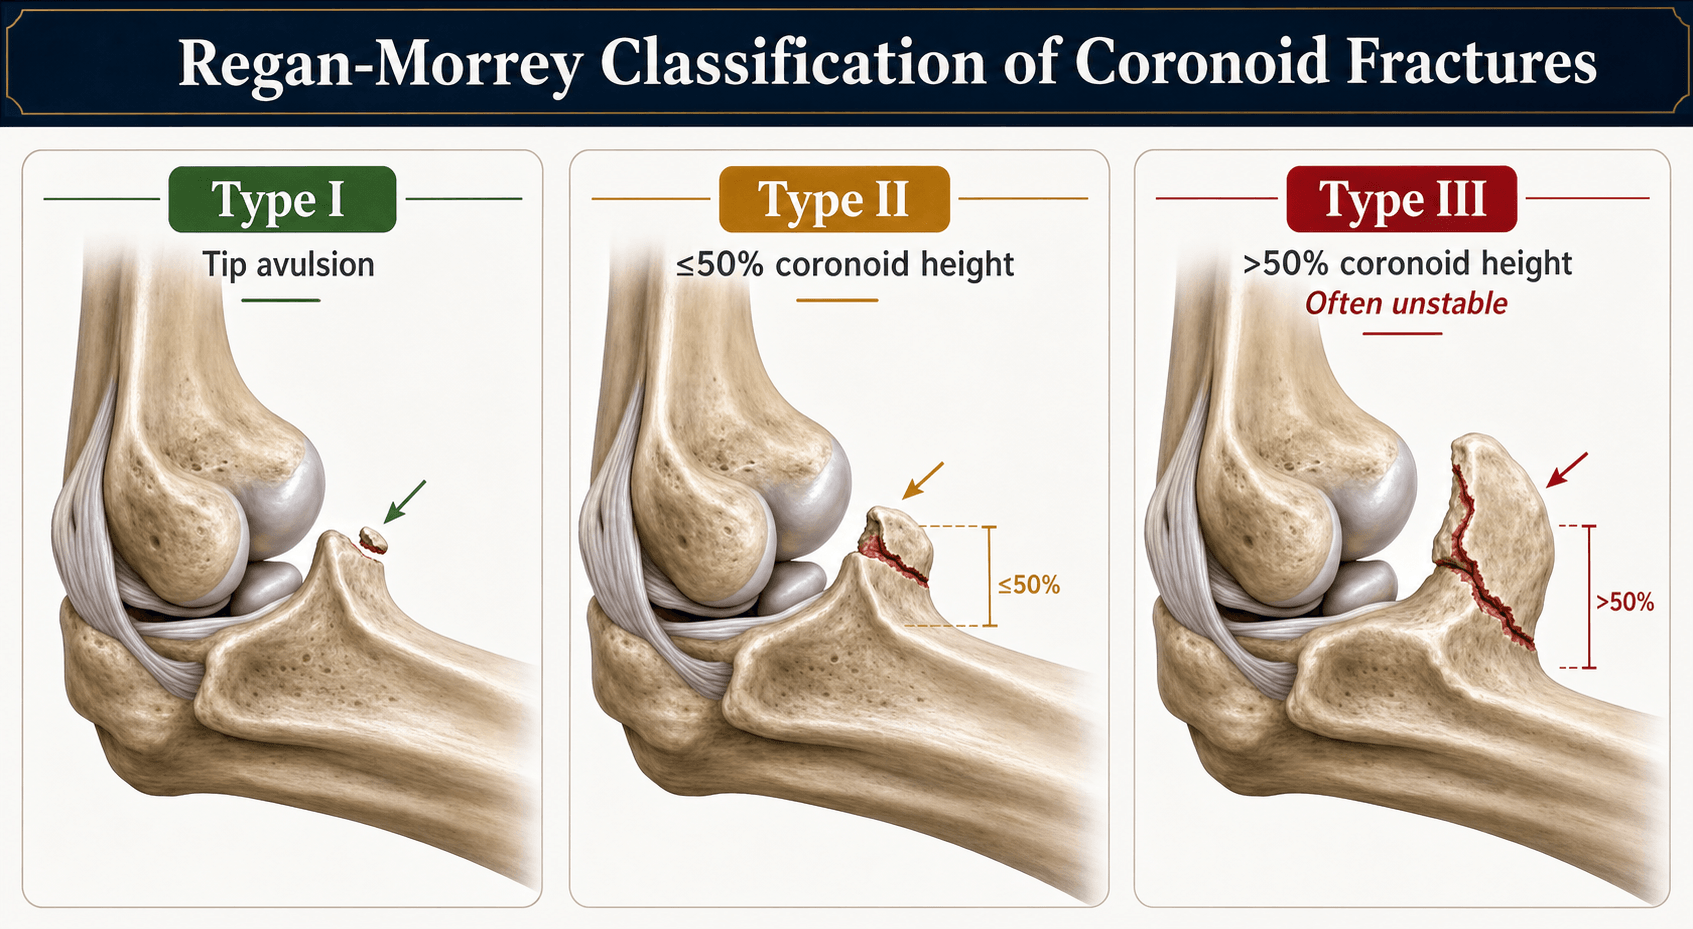
Location, not size, predicts instability, which is why O'Driscoll's location-based classification supplanted the height-based Regan-Morrey system. A 20% anteromedial facet fragment is a surgical problem; a 40% tip fragment in a stable elbow may not be.
How to use the figure honestly. It describes the point at which a coronoid deficiency causes instability in isolation, in the laboratory, with the ligaments intact, a situation that essentially never presents. In the injured elbow the ligaments are not intact, and the operative question is whether the elbow is stable through a functional arc after everything else has been addressed, answered on the table under fluoroscopy rather than with a ruler on the CT.
The exam answer. Quote the 50% rule, then say why you would not decide on it: name the pattern, name the associated injuries, and test stability intra-operatively.
Classification Systems
Two systems are in use. Regan and Morrey classified by fragment height. O'Driscoll classified by location, tip, anteromedial facet or base, because location predicts the mechanism, the associated injuries and the approach, and his is the system most commonly used.
- Subtype
- Tip
- Description
- Tip fracture (less than 2mm)
- Mechanism
- Posterolateral dislocation
- Subtype
- 1
- Description
- Sublime tubercle (medial)
- Mechanism
- Varus-posteromedial
- Subtype
- 2
- Description
- Anteromedial rim
- Mechanism
- Varus-posteromedial
- Subtype
- 3
- Description
- Anteromedial rim + tip
- Mechanism
- Varus-posteromedial
- Subtype
- 1
- Description
- Basal - less than 50%
- Mechanism
- High energy
- Subtype
- 2
- Description
- Basal - more than 50%
- Mechanism
- High energy
Type III.1 is a basal fracture of under 50% height, so "Type III means over 50%", as most revision notes have it, is not true of the whole type. O'Driscoll's system is defined by location, tip, anteromedial facet or base, not by height, which is exactly what distinguishes it from Regan-Morrey; where the two get blended, the height criterion is being imported from the wrong classification.
Treat the subtype numbering with care. The originating source cited on this page (PMID 12690844) states only that coronoid fractures can be classified according to whether the fracture involves the tip, the anteromedial facet, or the base (body); its abstract does not enumerate the subtypes, and published versions of the subtype numbering are not consistent with one another. Be confident about the three types and the mechanism each implies. If an examiner presses, describe the fragment ("an anteromedial rim fracture extending into the sublime tubercle") rather than gambling on "II.1 versus II.3"; describing the anatomy is always safe, and a mis-numbered subtype is not.
A coronoid fracture is also a hallmark of the posterior Monteggia lesion, and missing it changes the whole reconstruction. The pattern is a proximal ulna fracture with posterior dislocation of the radial head, frequently accompanied by a coronoid fracture and a radial head fracture. In Jupiter's sub-classification of Bado II, the type IIA lesion is defined by a fracture at the level of the coronoid/distal trochlear notch, so the coronoid is integral to this pattern, not incidental.
Why it matters. Unlike the terrible triad (a pure dislocation pattern) or varus PMRI (a coronoid plus LCL pattern), the posterior Monteggia is fundamentally a proximal-ulna malalignment problem. The priority is anatomical reconstruction of the proximal ulna, restoring length, alignment and the trochlear notch with a contoured dorsal plate; the coronoid fragment is captured as part of that construct, and only then is the radiocapitellar joint reduced.
The trap. Treating an apparent isolated "coronoid plus radial head fracture" as a terrible triad and approaching it from the lateral side alone misses the posterior ulnar malalignment and leads to recurrent posterior instability and arthrosis. Older patients with osteoporotic comminution at the notch do worst. A coronoid fracture with a posteriorly dislocated radial head and a proximal ulna fracture is a posterior Monteggia (Bado II/Jupiter IIA), see Monteggia fractures, not a terrible triad: reconstruct the proximal ulna first, then the radiocapitellar joint.
Clinical Assessment
History. The answers that shape the plan:
- Mechanism, and the direction of force
- Any sense of instability or dislocation
- Whether the elbow was relocated (self-reduced or reduced)
- Previous elbow problems
- Hand dominance and occupation
Examination. Look for the effusion of an intra-articular injury, then find where it is tender and which way it is unstable.
- Significance
- Intra-articular injury
- Action
- X-ray, CT if fracture suspected
- Significance
- Coronoid/anteromedial facet
- Action
- CT for classification
- Significance
- MCL injury
- Action
- Consider sublime tubercle involvement
- Significance
- LCL injury
- Action
- May have anteromedial facet pattern
- Significance
- PLRI pattern
- Action
- Likely had posterolateral dislocation
- Significance
- Multiple structure involvement
- Action
- Urgent surgical planning
Two instability patterns. In posterolateral rotatory instability (PLRI) the elbow subluxes posterolaterally, and it goes with tip fractures. In varus-posteromedial instability the ulna rotates posteromedially, and it goes with anteromedial facet fractures. The two need different approaches, which is why the examination has to tell them apart:
- Range of motion, looking for a mechanical block
- Valgus stress test for MCL integrity
- Varus stress test for LCL integrity
- Posterolateral rotatory instability test, the pivot shift
- Neurovascular status, especially the ulnar nerve
- Distinguishing features
- Anterior elbow pain, effusion, often part of dislocation; subtle on plain films
- Key discriminator
- Loss of triangular coronoid projection on lateral X-ray; confirm and type on CT
- Distinguishing features
- History of dislocation, gross instability, radial head fracture
- Key discriminator
- All three components present - LCL ruptured by definition
- Distinguishing features
- Lateral pain, painful rotation, no posteromedial tenderness
- Key discriminator
- Coronoid intact on CT; elbow stable through arc
- Distinguishing features
- Posterior wound/pain, large coronoid fragment, dorsal ulna disrupted
- Key discriminator
- Trochlear notch incongruity; ulnohumeral relationship lost through fracture
- Distinguishing features
- Dislocation that reduces and stays stable, no fracture
- Key discriminator
- No bony fragment on CT - purely capsuloligamentous injury
- Distinguishing features
- Fall onto varus-loaded arm, no frank dislocation, medial joint pain
- Key discriminator
- Anteromedial facet fracture plus LCL avulsion - typically no radial head fracture
- Distinguishing features
- Valgus laxity, medial pain, often in throwing athlete
- Key discriminator
- Bony avulsion at MCL anterior bundle insertion on CT/MRI
Investigations
Radiographs. An AP, which may show the fracture, a lateral, and obliques to see the anteromedial facet. The lateral is the best view for coronoid height: look at the anterior projection of the ulna, compare it with the opposite side if needed; loss of the normal triangular projection suggests a coronoid fracture.
CT is essential and is obtained for every suspected coronoid fracture: it types the fracture, measures fragment size and displacement, finds the associated radial head and olecranon injuries and plans the surgery. Read it against a checklist:
- Fragment size, as a percentage of coronoid height
- Fragment location: tip, anteromedial facet or basal
- Sublime tubercle involvement
- Associated radial head fracture
- Articular step-off
3D reconstruction helps with complex patterns, showing the fragment geometry for surgical planning. MRI is rarely indicated acutely; it may assess the ligaments, and is considered when chronic instability is being evaluated.
Management Algorithm
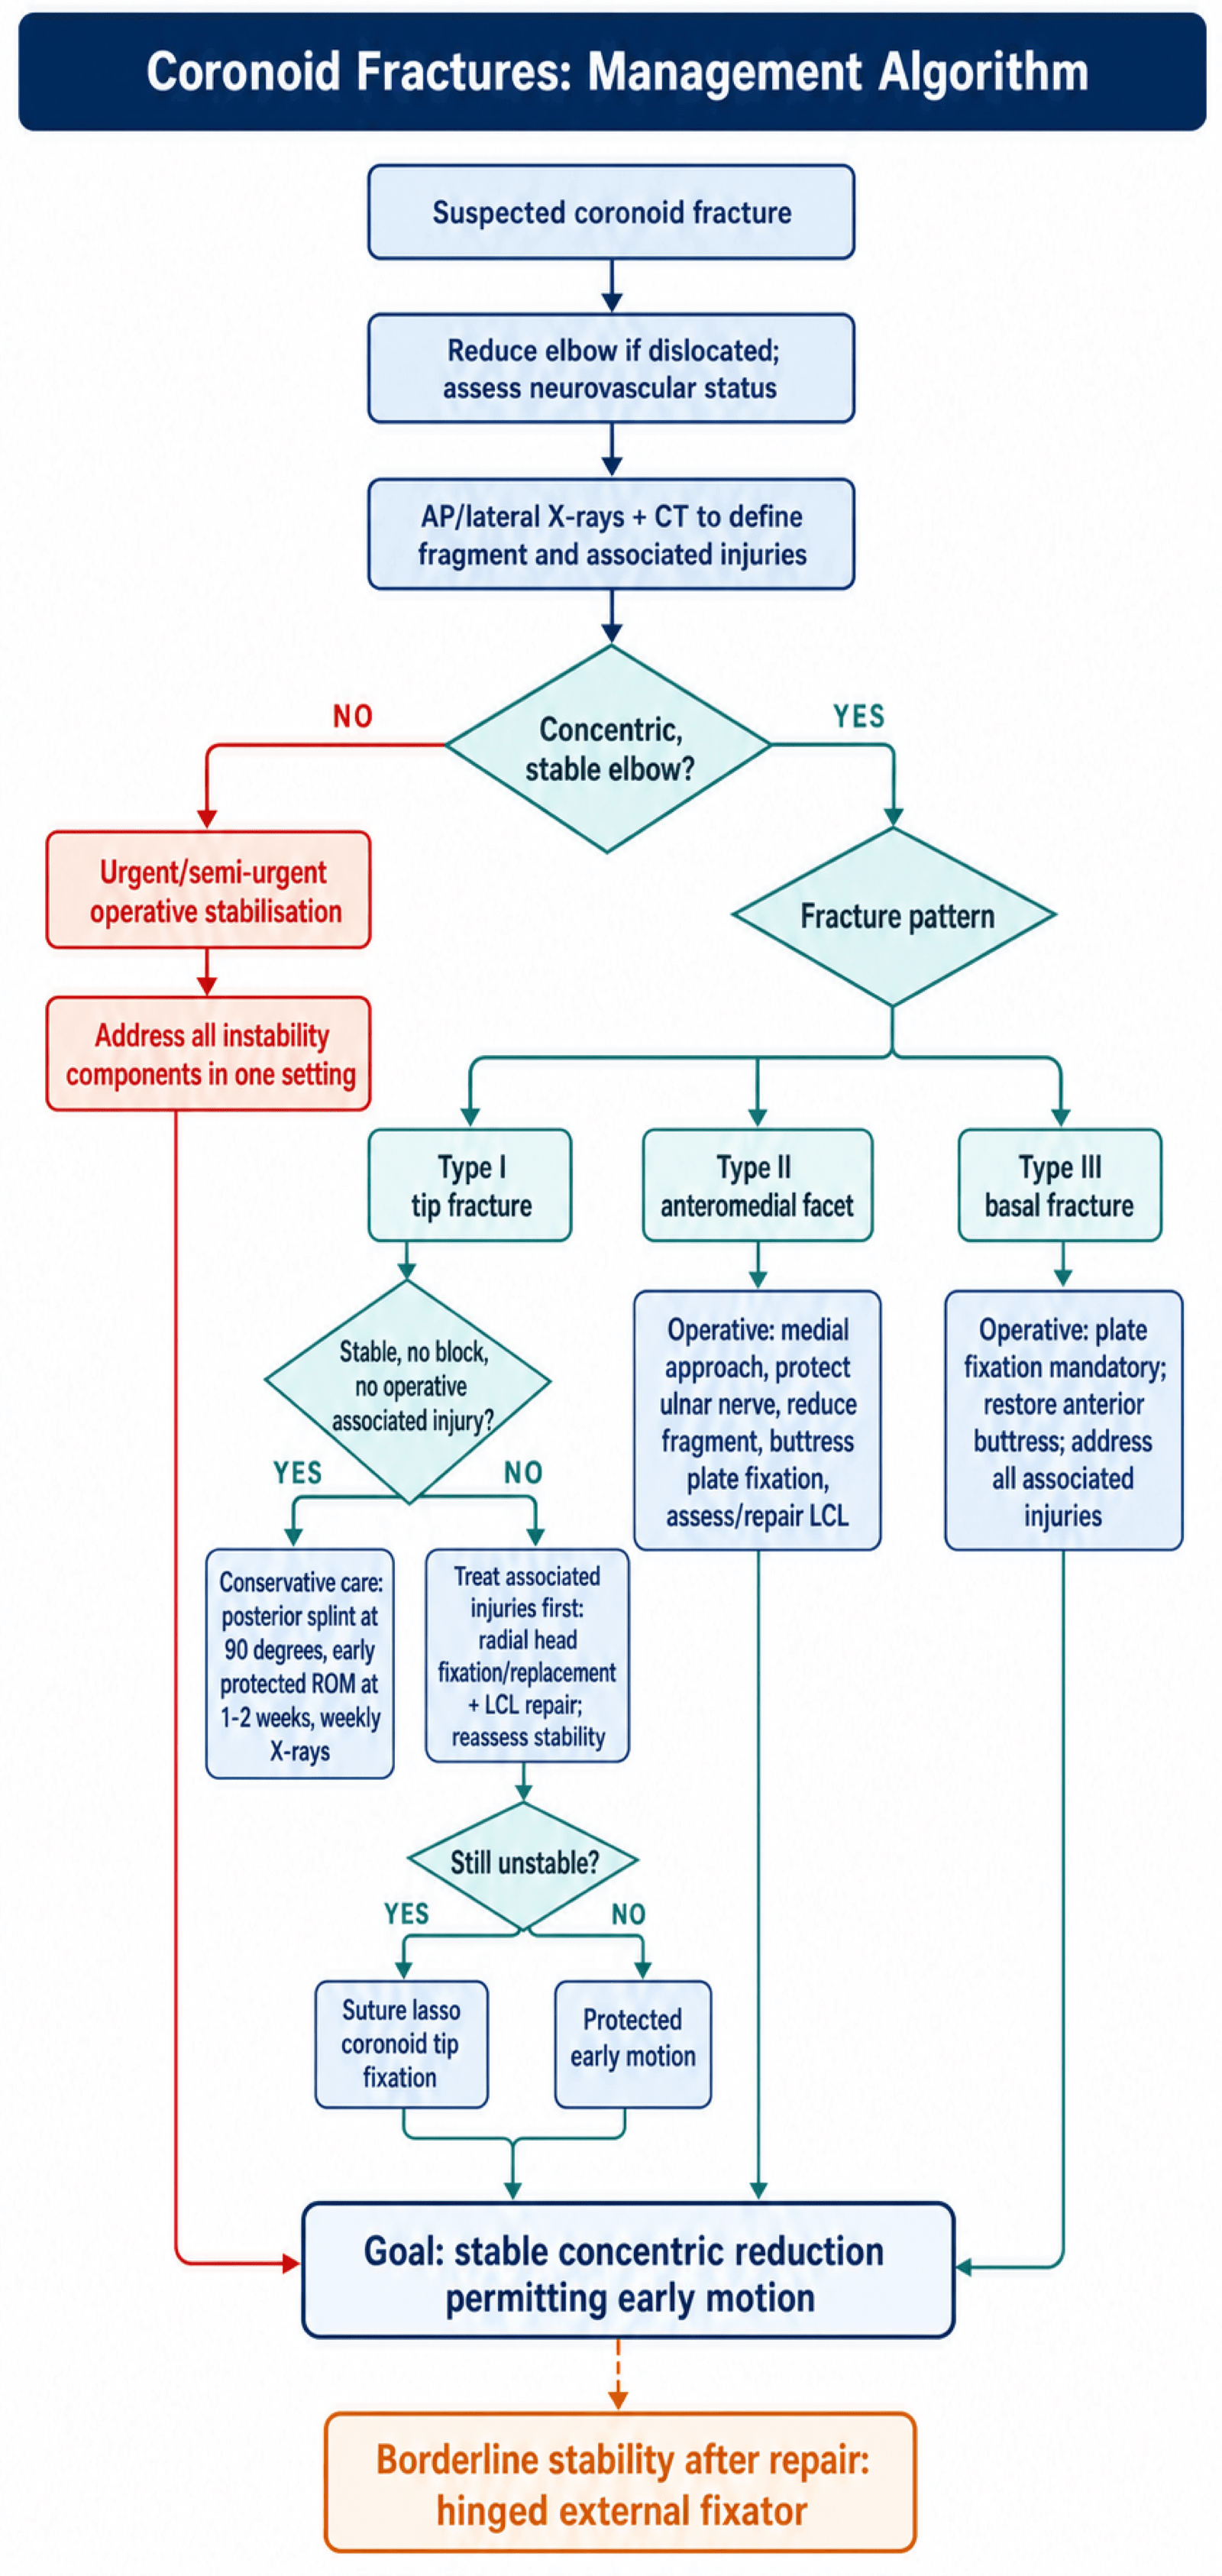
The decision. It is made on the pattern and on stability, not on fragment height. The algorithm and the guide below are the shorthand; the tabs give the detail.
- Key Finding
- Elbow stable after reduction
- Treatment
- Treat associated injuries, no coronoid fixation
- Key Finding
- Part of terrible triad, persistent instability
- Treatment
- Consider suture lasso fixation
- Key Finding
- Less than 50% of facet
- Treatment
- May be stable - assess carefully
- Key Finding
- Medial instability
- Treatment
- Buttress plate via medial approach
- Key Finding
- Always unstable, defined by location
- Treatment
- Plate fixation mandatory
- Key Finding
- MCL attachment involved
- Treatment
- Fix fragment = fixes MCL insertion
Who. Only a Type I tip fracture in a stable, concentrically reduced elbow, with no mechanical block and no associated injury that itself needs surgery. Any instability, incongruency or operative associated injury means the coronoid is fixed.
- Posterior splint at 90 degrees initially
- Begin motion at 1-2 weeks if stable
- Active ROM in flexion-extension arc
- Avoid terminal extension initially
- Progressive motion over 6 weeks
- Weekly X-rays initially
- Assess for subluxation
- Progress motion if maintaining reduction
Surgical Technique
Lateral, for the terrible triad. Kocher or the lateral column approach addresses the radial head and the LCL, and the coronoid can be reached from the lateral side (over-the-top) for a suture lasso of a tip fracture.
Medial, for the anteromedial facet. Splitting FCU, or going over the top of the flexor mass, gives direct access to the anteromedial facet, and the MCL can be assessed and repaired through the same exposure. The ulnar nerve is identified and protected first.
Posterior, for the transolecranon fracture-dislocation. The olecranon fracture itself gives direct visualisation, and the coronoid is fixed from posterior through it.
The fracture pattern and the associated injuries choose the approach.
Plate, screw and suture-lasso fixation all assume a fixable fragment. When the coronoid is comminuted beyond reconstruction, or the patient presents late with chronic coronoid insufficiency, the anterior buttress is rebuilt instead:
- Olecranon tip osteoarticular autograft, the most popular reconstruction: the tip of the olecranon is harvested (it is largely expendable for stability) and fixed to the coronoid base with a screw or plate to rebuild the anterior buttress and the trochlear-notch contour
- Radial head fragment as a graft: when the radial head is being excised or replaced anyway, a suitably sized osteoarticular fragment from the resected head is repurposed to reconstruct the coronoid, "spare-part" surgery
- Iliac crest tricortical graft: a structural autograft contoured to the coronoid base and fixed with a screw, useful when no local articular graft is available
- Other described options: rib osteochondral graft, coronoid prosthesis (rare, salvage) and, in chronic cases, an allograft proximal ulna for major bone loss
The indications are an acute unreconstructable (highly comminuted) coronoid and, more often, chronic post-traumatic coronoid insufficiency presenting with persistent or recurrent instability. The goal is always the same: restore enough anterior height to prevent posterior subluxation, then assess stability and add a hinged fixator if borderline.
Complications
- Incidence
- 5-15%
- Management
- Revision fixation, ligament repair, hinged fixator
- Incidence
- 20-30%
- Management
- Early motion, physio, capsular release if severe
- Incidence
- 15-25%
- Management
- Activity modification, eventual arthroplasty
- Incidence
- 5-15%
- Management
- Prophylaxis, excision if limiting
- Incidence
- 5-10%
- Management
- Often transient, protect during medial approach
- Incidence
- Variable
- Management
- Hardware removal if symptomatic
- Incidence
- Rare
- Management
- Revision fixation, bone graft
Recurrent instability is the most significant complication. It is usually due to inadequate coronoid reconstruction or a missed associated injury, and may need revision surgery or a hinged external fixator.
Stiffness is common after complex elbow trauma. Stable fixation and early motion prevent it; physiotherapy, dynamic splinting and capsular release treat it.
The ulnar nerve is at risk during the medial approach. Options include in-situ protection (preferred for brief procedures) or anterior transposition (for prolonged retraction or if nerve subluxing). Always identify and protect before deep dissection.
Postoperative Care and Rehabilitation
Principles. Early motion is critical to prevent stiffness, and stable fixation is what allows it. Varus and valgus stress are avoided early, and an extension block may be needed initially. If stability is borderline once every injured structure has been addressed, a hinged external fixator allows early motion while protecting the repair: it centres rotation at the elbow axis and prevents subluxation during rehabilitation.
- Posterior splint at 90 degrees
- Elevation, ice
- Finger motion
- Wound check at 5-7 days
- Begin active ROM if stable fixation
- May use hinged brace if borderline stable
- Focus on flexion-extension
- Avoid varus/valgus stress
- Progressive active ROM
- Target functional ROM by 6 weeks
- No resistance until 6 weeks
- Dynamic splinting if stiff
- Begin gentle strengthening
- Progressive loading
- Return to light activities
- Full strengthening
- Return to sport/work
- Final outcome assessment
Outcomes and Prognosis
Prognosis. Outcome is worse with complex patterns: the associated injuries, the quality of the reconstruction, the time to surgery, the patient's compliance and any pre-existing elbow condition all bear on it.
- Good/Excellent
- 80-90%
- Key Factors
- Stable reduction critical
- Good/Excellent
- 70-80%
- Key Factors
- Address all components
- Good/Excellent
- 70-80%
- Key Factors
- Adequate buttress fixation
- Good/Excellent
- 60-75%
- Key Factors
- High energy, complex
The terrible triad has worse outcomes than an isolated coronoid fracture. Even with all three components addressed, expect higher rates of stiffness and residual instability, and counsel patients about a guarded prognosis.
Guidelines, Registries & Global Practice
Global epidemiology. Isolated coronoid fractures are rare; the coronoid is fractured almost exclusively as part of a complex injury pattern. Across consecutive surgical series, the fragment morphology tracks the instability pattern — small transverse tip fractures with terrible-triad injuries, larger fractures with olecranon fracture-dislocations, and anteromedial facet fractures with varus posteromedial rotational instability (Doornberg & Ring, J Hand Surg Am 2006; PMID 16443103). The anteromedial facet is anatomically vulnerable: 3D-CT analysis shows that on average 58% of the facet (range 26-82%) is unsupported by the proximal ulnar metaphysis, explaining why it so often shears off as a discrete fragment (Doornberg et al., J Shoulder Elbow Surg 2007; PMID 17512221). High-energy mechanisms (motorcycle and vehicle trauma, falls from height, occupational falls) predominate for basal patterns, whereas low-energy varus-loading falls produce anteromedial facet injuries.
Guideline & society position (side-by-side). No registry tracks coronoid fractures specifically, and there is no randomised-trial-level guideline; practice is governed by classification-led expert consensus and instructional teaching from the major societies.
- Region
- USA / global
- Position on coronoid fractures
- Pattern-based fixation; restore the anterior buttress; fix coronoid within the terrible-triad sequence after radial head and LCL
- Evidence level
- Expert consensus (Level V)
- Region
- UK
- Position on coronoid fractures
- Complex fracture-dislocations to be managed at units with elbow/upper-limb expertise; early definitive surgery, early mobilisation
- Evidence level
- Consensus standard
- Region
- Europe
- Position on coronoid fractures
- Endorse O'Driscoll typing; anteromedial facet via medial approach with buttress plate; hinged fixator for residual instability
- Evidence level
- Expert consensus (Level V)
- Region
- UK
- Position on coronoid fractures
- Covered under general non-complex/complex fracture pathways; no disease-specific recommendation
- Evidence level
- Not addressed
Registry evidence. Coronoid fractures are not separately captured in arthroplasty or trauma registries (AOANJRR, NJR, AJRR record joint replacement, not elbow fracture fixation), so the evidence base is series- and meta-analysis-driven rather than registry-driven. The best pooled data come from systematic reviews of the terrible triad: comparable functional scores for radial head repair versus replacement (mean MEPS ~88), with an overall complication rate near 65% and reoperation rates of roughly 18% in both groups (Kyriacou et al., Arch Orthop Trauma Surg 2019; PMID 30656475).
Practice variation. Surgical approach is the main area of genuine variation. A meta-analysis found that a combined lateral and anteromedial approach gave significantly greater elbow and forearm motion and a higher MEPS than a lateral-only approach for the terrible triad, at the cost of longer operative time (Meena et al., Bull Emerg Trauma 2020; PMID 32201696). Choice of radial head reconstruction versus replacement, routine versus selective coronoid fixation in tip fractures, and threshold for hinged external fixation differ between centres and surgeon experience.
Be prepared to discuss coronoid classification, recognise the difference between tip and anteromedial facet patterns, understand the sublime tubercle anatomy, and know when plate fixation versus suture lasso is appropriate. Examiners also probe why there is no registry or RCT-level guidance and how you reconcile the high complication rates reported in meta-analyses with the need for early motion. These are common viva topics.
MCQ Practice Points
Q: What defines an O'Driscoll Type II coronoid fracture? A: Anteromedial facet fracture - includes subtypes involving the sublime tubercle (MCL insertion), anteromedial rim, or combination. This pattern results from varus-posteromedial rotational instability, not posterolateral dislocation.
Q: What percentage of coronoid height loss results in elbow instability? A: Greater than 50% — but give the caveat, because the question is testing whether you understand what the figure means. It describes isolated coronoid deficiency with the ligaments intact. In the injured elbow, location and the associated injuries decide stability: in Doornberg's consecutive series every one of the 32 terrible triads had a fragment under 50% (PMID 16443103), and small anteromedial facet fragments left unbuttressed produced varus subluxation and arthrosis in six out of six (PMID 17015599). That is why O'Driscoll classifies by location. The operative decision is made on the pattern and on intra-operative stability testing, not on a percentage.
Q: What structure attaches to the sublime tubercle? A: The MCL (specifically the anterior bundle). The sublime tubercle is the ulnar insertion of the most important stabilizing bundle of the MCL. Fractures involving this area are essentially bony MCL avulsions.
Q: What is the mechanism of anteromedial facet fractures? A: Varus-posteromedial rotational instability - an axial load with varus stress, NOT posterolateral dislocation. This is distinct from tip fractures which occur with posterolateral dislocation.
Q: What approach is required for anteromedial facet fracture fixation? A: Medial approach (FCU splitting or over-the-top). These fractures cannot be adequately visualized or fixed from a lateral approach. Must protect the ulnar nerve.
Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 45-year-old woman falls from a ladder. Her elbow was dislocated and has been reduced. CT shows a comminuted radial head fracture with more than 4 fragments and a small coronoid tip fracture. How do you approach this injury?”
“A 38-year-old man presents after a fall onto his arm. He has no history of dislocation. CT shows an anteromedial facet fracture involving approximately 40% of the coronoid with the sublime tubercle involved. What is your diagnosis and management approach?”
“A 52-year-old man involved in a motorcycle accident has a complex elbow injury. CT shows a basal coronoid fracture involving approximately 60% of the coronoid height. The elbow is grossly unstable. What are your key considerations?”
O'DRISCOLL CLASSIFICATION
- Type I: Tip fracture - posterolateral dislocation mechanism
- Type II: Anteromedial facet - varus-posteromedial mechanism
- Type III: Basal / body - defined by LOCATION (includes fragments under 50%), unstable pattern
- Subtypes: I.1/I.2, II.1/II.2/II.3, III.1/III.2 by fragment size
KEY ANATOMY
- Coronoid = anterior buttress of elbow
- Sublime tubercle = MCL (anterior bundle) insertion
- Brachialis inserts on coronoid base
- 50% rule = ISOLATED coronoid loss with intact ligaments; in the injured elbow LOCATION and associated injuries decide
- ALL 32 terrible triads in Doornberg's series had fragments UNDER 50%
PATTERN RECOGNITION
- Type I tip - part of terrible triad (posterolateral dislocation)
- Type II anteromedial - varus stress mechanism, different approach needed
- Type III basal - always operative, plate fixation
- Isolated Type I can be treated conservatively if elbow stable
SURGICAL APPROACHES
- Tip fractures - lateral approach, suture lasso
- Anteromedial facet - MEDIAL approach, buttress plate
- Basal - medial or posterior, plate fixation
- Protect ulnar nerve on medial approach
FIXATION TECHNIQUES
- Suture lasso - for tip fractures (Type I)
- Screws - for larger single fragments
- Buttress plate - for anteromedial facet (Type II)
- Plate - mandatory for basal (Type III)
TERRIBLE TRIAD PROTOCOL
- 1. Fix/replace radial head
- 2. Repair LCL
- 3. Assess stability - fix coronoid if unstable
- 4. Consider hinged fixator if still borderline
Evidence Base
O'Driscoll et al. — Difficult Elbow Fractures (defining classification)
- Defined the coronoid classification by fracture location — tip, anteromedial facet, and basal (body) — and recognised anteromedial facet fractures as varus posteromedial rotatory fracture-subluxations rather than dislocation-driven injuries. These patterns predict associated injuries, instability and surgical approach.
Doornberg & Ring — Coronoid Fracture Patterns
- In 67 surgically treated coronoid fractures, fracture morphology was strongly associated with the instability pattern: large coronoid fractures with olecranon fracture-dislocations, small transverse tip fractures with terrible-triad injuries, and anteromedial facet fractures with varus posteromedial rotational instability (statistically significant for both classification systems).
Doornberg & Ring — Anteromedial Facet Fractures (landmark series)
- 18 anteromedial facet fractures: all but three had avulsion of the LCL complex from the lateral epicondyle. Six elbows in which the facet was not specifically treated (or lost fixation) developed varus subluxation and arthrosis with fair/poor results; secure medial buttress fixation restored good or excellent function in the remainder.
Liu et al. — Modified Pugh Standard Protocol for Terrible Triad
- 42 terrible-triad elbows treated by a modified Pugh standard protocol (radial head fixation/replacement, LCL repair, coronoid fixation when indicated) achieved a mean Mayo Elbow Performance Score of 88, mean flexion-extension arc of 107 degrees, and 24 excellent plus 16 good results; complications included heterotopic ossification (n=5) and transient nerve palsies, with four reoperations.
Ring et al. — Persistent Instability & Hinged External Fixation
- 13 patients with persistent ulnohumeral instability after elbow fracture-dislocation treated with a protocol of coronoid and radiocapitellar restoration, LCL repair/reconstruction and temporary hinged external fixation regained stability in every case (mean Mayo score 84, mean motion arc 99 degrees), though arthrosis was common.
Kyriacou et al. — Radial Head Replacement vs Reconstruction in Terrible Triad (systematic review/meta-analysis)
- 9 studies, 210 patients: no significant difference in mean MEPS (replacement 88.6 vs reconstruction 88.5) or range of motion. The overall complication rate was 65% and reoperation rates were high in both groups (replacement 18.4%, reconstruction 17.9%).