Electrochemical Degradation | Metal Ion Release | ALVAL | Implant Failure
- Corrosion is electrochemical degradation of metal in physiological environment
- Passivation layer (TiO2, Cr2O3) protects implants - breakdown causes corrosion
- MACC (mechanically-assisted crevice corrosion) is key mechanism at modular junctions
- ALVAL (aseptic lymphocyte-dominated vasculitis-associated lesion) from metal hypersensitivity
- MoM hip failures primarily from taper corrosion, not bearing surface wear
- “Body fluid is corrosive: 0.9% NaCl, pH 7.4, 37°C, proteins
- “Mixed metal couples (CoCr/Ti) have higher galvanic corrosion than matched materials
- “Serum metal ions: Cobalt and chromium levels monitor MoM hips
- “Taper assembly: clean, dry, single impaction reduces fretting corrosion
Overview and Electrochemistry
Corrosion is the electrochemical degradation of a metal in its environment. An orthopaedic implant sits in an aqueous solution of chloride ions (0.9% NaCl) at pH 7.4 and 37°C, surrounded by proteins and other organic molecules, and that combination is aggressive to metal.
The alloys themselves are covered separately — titanium alloys, cobalt-chrome alloys, stainless steel and ceramics — and corrosion should be read alongside wear mechanisms, because the two act together at a taper and are separated only for teaching. The clinical consequences have their own pages: trunnionosis and taper corrosion, metal-on-metal complications and wear-related osteolysis.
Why the body is hostile. Chloride ions, the aggressive anion, attack passivation layers; proteins and amino acids affect the electrochemical reactions; cyclic mechanical loading creates stress and micro-motion; and oxygen gradients develop in crevices and gaps. Each of these reappears below as the driver of a particular type of corrosion.
Why it matters. Metal ion release has four consequences:
- Implant mechanical failure - material loss weakens the structure
- Metal hypersensitivity - Type IV delayed hypersensitivity (ALVAL)
- Local tissue toxicity - soft tissue necrosis and pseudotumour
- Systemic metal elevation - unclear long-term effects
The reaction. Corrosion is an oxidation-reduction reaction. At the anode the metal loses electrons and goes into solution as ions (M → M^n+ + ne^-); that is the corrosion reaction, and metal ion release is what it produces. The electrons flow to the cathode, where oxygen is reduced to hydroxyl ions (O2 + 2H2O + 4e^- → 4OH^-), which completes the circuit.
Passivation. Every orthopaedic metal owes its corrosion resistance to a thin oxide film that keeps the metal out of contact with the electrolyte. Titanium forms TiO2, typically 2-10 nm thick; stainless steel and cobalt-chromium form Cr2O3, which on CoCr is 1-3 nm thick. The film is amorphous, has semiconductor properties, dissolves in an acidic environment and is disrupted by mechanical abrasion. Corrosion occurs when passivation is disrupted, and every section of this topic returns to that one idea.
Why titanium resists corrosion. Titanium is a reactive metal thermodynamically, yet its TiO2 film is tenacious, extremely stable and self-healing: scratched, it reforms in milliseconds in the presence of oxygen. Cobalt-chromium relies on a Cr2O3 film that is less robust.
The polarisation curve. Whether the passive film holds is decided by the anodic polarisation curve, which plots corrosion current against electrode potential:
- Active region - at low potential the bare metal dissolves freely (high current)
- Passive region - as potential rises a protective oxide film forms and the current drops to a very low, near-constant value; the metal is protected across a wide "passive window"
- Breakdown (pitting) potential - above a critical potential the passive film breaks down locally and the current rises sharply again; this is where pitting and crevice corrosion initiate
- Transpassive region - at very high potential the oxide itself dissolves and general corrosion resumes
The wider the passive window and the higher the breakdown potential, the more corrosion-resistant the alloy. Titanium has a very high, self-healing breakdown potential; stainless steel has the lowest, which makes it the most pitting-prone of the implant alloys.
Two modifiers the body imposes. Chloride ions lower the breakdown potential: they adsorb at film defects and prevent re-passivation, so the safe passive window narrows in physiological saline. And when dissimilar metals are coupled, a large cathode driving a small anode, the galvanic area effect, concentrates the entire galvanic current onto a tiny area, so a small de-passivated patch within a taper crevice corrodes very rapidly. A small anode with a large cathode is the worst-case geometry, and between them these two modifiers explain why localised breakdown happens in crevices and at mixed-metal couples.
Principles and Mechanisms of Corrosion
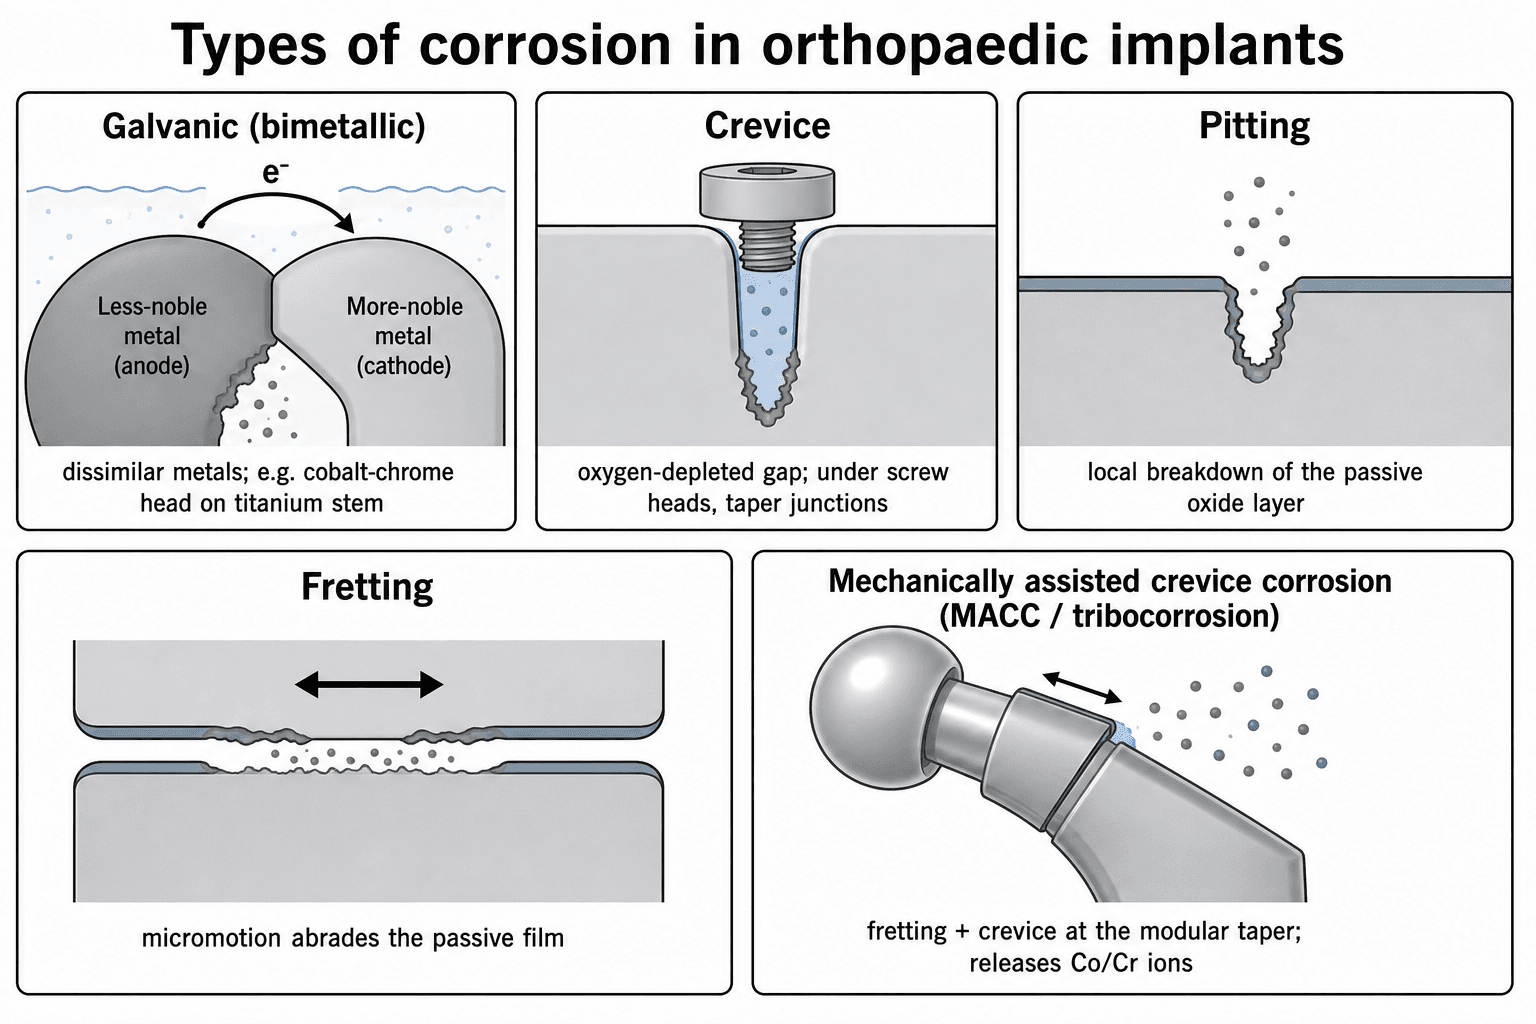
Galvanic Corrosion
Mechanism. Two dissimilar metals in electrical contact in an electrolyte form a cell, and the less noble (more anodic) metal corrodes preferentially. The farther apart the two metals sit in the galvanic series, the larger the potential difference and the faster the anodic metal corrodes.
The galvanic series in physiological saline, most noble to least noble:
- Platinum (most noble, corrodes least)
- Cobalt-chromium alloys
- Titanium alloys
- Stainless steel 316L
- Magnesium (least noble, corrodes most)
- Anode (Corrodes)
- Titanium stem
- Cathode (Protected)
- CoCr head
- Clinical Example
- Modular hip taper junction
- Anode (Corrodes)
- Stainless steel
- Cathode (Protected)
- CoCr
- Clinical Example
- Mixed implants (rare)
- Anode (Corrodes)
- Neither (matched)
- Cathode (Protected)
- Neither (matched)
- Clinical Example
- Preferred combination
The clinical case: a cobalt-chromium head on a titanium stem. CoCr is more noble than titanium in the physiological environment, so at the taper the titanium is the anode and the CoCr head the cathode. Titanium oxidises (Ti → Ti^4+ + 4e^-), micro-motion disrupts its passivation layer, and the galvanic current accelerates the attack; the product is black debris of titanium oxide and chromium oxide at the taper. Retrieval studies show worse corrosion at CoCr/Ti tapers than at CoCr/CoCr tapers, which is why a matched couple is preferred, why the taper is assembled clean, dry and with a single impaction, and why adequate taper engagement to minimise micro-motion matters.
Crevice Corrosion
Definition. Localised corrosion within a shielded area, a crevice or gap, where oxygen is depleted. The crevice starts passive and then turns on itself in a sequence worth being able to recite.
Crevice Corrosion Development
A crevice exists between two surfaces (modular taper, plate-bone interface). Initially it is passive.
Oxygen is consumed, at the entrance and within the crevice, faster than it can diffuse in, so an oxygen gradient develops with low oxygen inside.
Metal oxidation continues (M → M^n+ + ne^-) and the ions hydrolyse (M^n+ + H2O → MOH + H^+), producing H^+ ions. The pH falls to 3-4 inside the crevice.
The low pH dissolves the protective oxide layer. Chloride ions migrate into the crevice for charge balance and proteins denature and deposit; the acidic chloride environment is highly aggressive.
Corrosion accelerates and becomes self-sustaining. Metal ion release increases and the crevice pH stays low.
Where. Modular taper junctions (head-neck and neck-stem), screw-plate and plate-bone interfaces, modular knee tibial tray interfaces, and under a bone cement mantle.
MACC. Superimpose micro-motion on a crevice and the result is mechanically-assisted crevice corrosion. The motion continuously disrupts the passivation layer, fresh metal is exposed to the aggressive crevice environment, mechanical wear debris is added to the corrosion products, and the effect is synergistic: the corrosion rate is much higher than either process alone. MACC is the primary mechanism of modular taper corrosion in hip implants and the leading cause of modular hip taper failures.
What separates MACC from simple fretting corrosion is the crevice. Fretting can happen between any two surfaces; MACC occurs specifically in crevice geometry, where the acidic, chloride-rich, oxygen-depleted environment accelerates passive-layer breakdown once micro-motion is added.
Pitting Corrosion
Definition. A highly localised breakdown of passivation that creates small pits propagating deep into the metal: a small surface opening with deep penetration.
Mechanism. The passivation layer has a microscopic defect, an inclusion or a scratch. Chloride ions adsorb there (Cl^- is a small anion that penetrates the oxide layer and prevents re-passivation), the local breakdown creates a micro-anode, and the pit propagates inward, autocatalytic in the same way as a crevice. The pit can then act as a stress concentration site for fatigue crack initiation.
Clinical relevance. Pitting is less common than fretting and crevice corrosion in orthopaedics, occurs on stainless steel more than on titanium or CoCr, and starts at surface contamination sites. Rough surfaces are more susceptible than polished ones, so surface finishing reduces susceptibility.
Fretting Corrosion
Definition. Combined mechanical wear and corrosion from small-amplitude oscillatory motion between two surfaces, typically less than 100 microns.
Mechanism. The micro-motion abrades the passivation layer away; the fresh metal exposed oxidises rapidly and forms debris; the debris is trapped between the surfaces as third-body wear; and the cycle repeats with each loading cycle, so the degradation is synergistic mechanical and chemical. The characteristic product is black debris of metal oxide particles, which distinguishes fretting from pure wear.
- Pure Wear
- Mechanical removal
- Pure Corrosion
- Chemical dissolution
- Fretting Corrosion
- Synergistic mech + chem
- Pure Wear
- Yes (sliding)
- Pure Corrosion
- No
- Fretting Corrosion
- Yes (micro-motion)
- Pure Wear
- Not relevant
- Pure Corrosion
- Critical
- Fretting Corrosion
- Repeatedly disrupted
- Pure Wear
- Metallic particles
- Pure Corrosion
- Oxide/ions
- Fretting Corrosion
- Oxide particles + ions
- Pure Wear
- Linear with cycles
- Pure Corrosion
- Time-dependent
- Fretting Corrosion
- Accelerated (synergy)
Where. Fretting corrosion is the dominant wear mode at modular tapers. It also occurs between the polyethylene backside and the tibial tray, at screw-plate interfaces where there is micro-motion, and where cerclage wires rub against bone or plate.
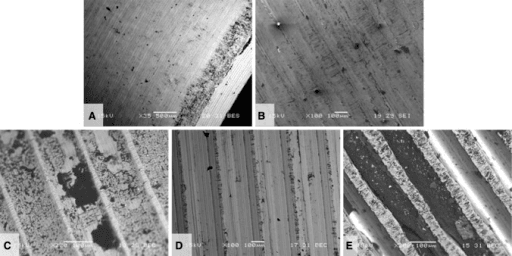
Environmentally-Assisted Cracking: Stress Corrosion Cracking and Corrosion Fatigue
The four types above describe metal loss. A further category describes cracking that occurs when mechanical stress and the corrosive environment act together, and it causes sudden, often brittle, implant fracture rather than gradual material loss.
- Stress corrosion cracking (SCC)
- Sustained (static) tensile stress
- Corrosion fatigue
- Cyclic (fluctuating) stress
- Stress corrosion cracking (SCC)
- Corrosive medium plus stress crack the passive film at a susceptible site
- Corrosion fatigue
- Corrosion removes the fatigue limit - cracks initiate at lower stress and earlier
- Stress corrosion cracking (SCC)
- Branching brittle crack (inter- or transgranular)
- Corrosion fatigue
- Transgranular fatigue crack, often pit-initiated
- Stress corrosion cracking (SCC)
- Historical stainless-steel implant fractures in the chloride environment
- Corrosion fatigue
- Stem/plate fatigue failure accelerated by pitting or crevice attack
Stress corrosion cracking needs three things together: a susceptible alloy, a specific corrosive environment (chloride) and a sustained tensile stress. The crack tip is both mechanically and chemically driven, so failure can occur well below the normal yield strength.
Corrosion fatigue is the synergy of cyclic loading and corrosion. In a corrosive medium a metal loses its true fatigue (endurance) limit, so the S-N curve keeps falling and the implant can fail at a stress that would be safe in air. A corrosion pit or a fretting scar is the stress raiser that initiates the fatigue crack, which is the mechanistic link between localised corrosion and the rare but catastrophic complication of stem, plate or modular-neck fracture. The pure mechanical S-N behaviour and fatigue limit are developed in the fatigue-failure topic.
Metal Ion Release and Biological Effects
Release. When corrosion occurs, metal ions are released into the surrounding tissues and the systemic circulation.
- Normal Serum Level
- Less than 1 ppb
- Threshold for Concern
- 7 ppb (regulatory action level)
- Source of Elevation
- CoCr implant corrosion, MoM bearing
- Normal Serum Level
- Less than 1 ppb
- Threshold for Concern
- 7 ppb (regulatory action level)
- Source of Elevation
- CoCr implant corrosion
- Normal Serum Level
- Less than 5 ppb
- Threshold for Concern
- No established threshold
- Source of Elevation
- Ti implant corrosion (rare)
- Normal Serum Level
- Less than 1 ppb
- Threshold for Concern
- No established implant threshold
- Source of Elevation
- Stainless steel corrosion
ppb and µg/L are the same thing (1 part per billion in serum ≈ 1 microgram per litre), and the numbers are small, which is exactly why an order-of-magnitude slip is easy and consequential. Normal, with no implant, is under 1 ppb: a fraction of a microgram per litre. 7 ppb is the action level in UK regulatory guidance, roughly 119 nmol/L if the laboratory reports in SI units, and a candidate who cannot convert will misread the result in front of them. Above about 20 ppb revision is treated as likely; 50-100 ppb and above is the territory of systemic cobalt toxicity.
A number in the tens or hundreds of ppb is never "normal". Beware any source, including summary boxes and revision cards, that offers a wide "normal range" spanning one to a hundred: that spans the entire distance from a healthy person to cobalt cardiomyopathy. The threshold that changes management is 7; the normal is under 1.
A caution about the 7 ppb figure itself. It is a pragmatic regulatory trigger for further investigation, not a biological cliff-edge and not a revision indication on its own. Trends matter more than absolutes, a rising level in a symptomatic patient outweighs a stable higher one, and the decision to revise is made on symptoms, imaging and trajectory together.
Distribution. Ions and particles travel outward in a predictable order:
- Local tissues - highest concentration, direct toxicity
- Regional lymph nodes - metal particles transported by macrophages
- Systemic circulation - ions absorbed into the bloodstream
- Distant organs - accumulation in liver, spleen and kidney
Local effects. Metal produces four things locally. Metallosis is macroscopic black or grey staining of the tissues. ALVAL is the lymphocyte-dominated reaction described below. A pseudotumour is a soft tissue mass with necrosis, not a true neoplasm. Osteolysis is particle-induced bone resorption. Macrophages engulf the metal particles, ions bind to proteins, the debris accumulates in the pseudocapsule and can extend to bone.
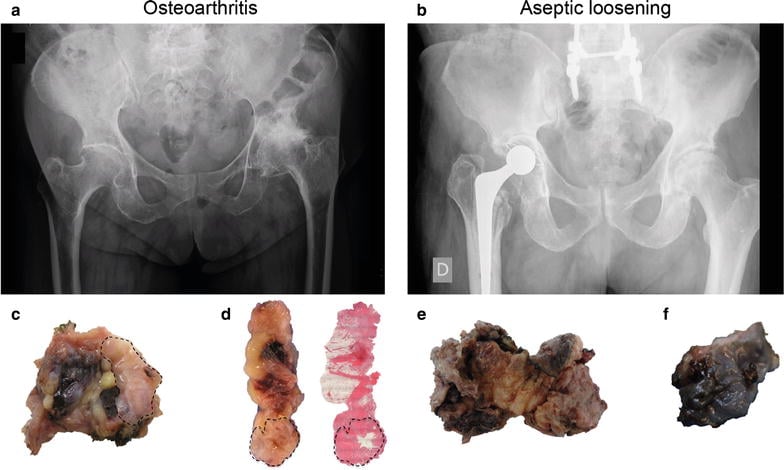
ALVAL. The aseptic lymphocyte-dominated vasculitis-associated lesion is conventionally described as a Type IV delayed hypersensitivity reaction to metal ions, and the sequence below is the mechanism to be able to draw. State it as the leading hypothesis rather than settled fact, because the studies cited in the evidence section do not agree that it is proven, and an examiner who knows the literature will reward the candidate who says so.
For hypersensitivity. Willert's landmark histology found only few metal particles in tissues showing a florid lymphocytic reaction, which argues the response is immune rather than simply proportional to particle volume; and patients re-revised to another MoM articulation had no symptom relief (PMID 15637030).
Against, or at least unresolved. In Langton's ARMD series the lymphocyte transformation tests were negative, leaving the hypersensitivity contribution uncertain, while ARMD patients had significantly higher cobalt and chromium levels and greater bearing wear, a picture more consistent with a dose-dependent toxic reaction (PMID 20044676). Pandit's pseudotumour series concluded the aetiology was probably multifactorial, toxic versus hypersensitivity (PMID 18591590).
The honest synthesis, and a good viva answer. There are almost certainly two overlapping processes: a dose-dependent cytotoxic response to a high particle and ion burden, and a genuine cell-mediated hypersensitivity that can occur at low particle loads in susceptible individuals. That accounts for the clinical paradox that some patients fail catastrophically with modest wear while others tolerate very high ion levels without a reaction, and it explains why serum ions are a useful screening biomarker but a poor predictor in the individual.
The classical hypersensitivity sequence.
ALVAL Development
Corrosion releases Co and Cr ions into the tissues.
Metal ions bind to proteins, creating metal-protein complexes (haptens).
Antigen-presenting cells present the hapten to T-cells, which become sensitised (the priming phase).
Continued metal release re-exposes the sensitised T-cells.
T-cells recruit macrophages and lymphocytes. Perivascular lymphocytic infiltration, tissue destruction and necrosis follow.
Histology. A dense perivascular lymphocytic infiltrate, T-cell predominant, with a diffuse lymphocytic infiltrate, aseptic fibrinoid necrosis, vascular endothelial damage, necrotic tissue containing metal debris, and no infection. Grossly the tissues are stained grey-black, there may be a pseudotumour, and any effusion is sterile.
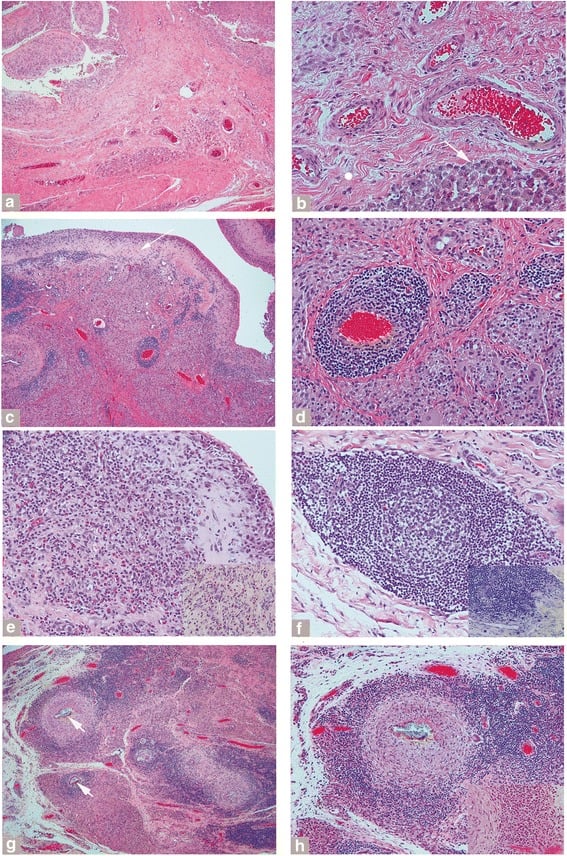
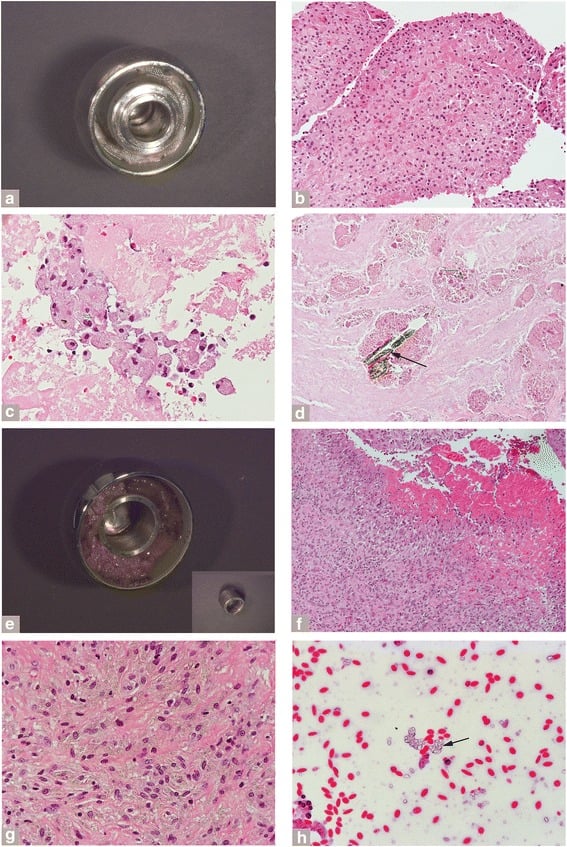
Presentation. Pain is the most common symptom. The others are a soft tissue mass (a pseudotumour on imaging), instability or dislocation from soft tissue destruction, and elevated serum cobalt and chromium.
Systemic effects. The long-term consequences are unclear. Cobalt can cause cardiomyopathy and hypothyroidism at very high levels, and its systemic toxicity is neurological and cardiac; chromium carries a theoretical carcinogenic risk in the Cr^6+ form and accumulates in the kidney; nickel is a known allergen and hypersensitivity to it is common. Most patients with moderate elevation (5-10 ppb) have no systemic symptoms, but the long-term data are limited.
Anatomy of Corrosion Sites
The head-neck taper. The most critical corrosion site in modern THA is the Morse taper between femoral head and stem: a contact area of 50-150 mm² depending on design, a taper angle typically 5°40', and a crevice geometry that is the ideal environment for MACC once micro-motion disrupts the protective oxide layer. Surface roughness affects seating and corrosion, and the material couple (CoCr/Ti) is a critical factor.
Modular necks. A modular neck system adds a second taper at the stem-sleeve junction, for neck angle and offset adjustability, and with it a second corrosion site. Double modular systems produce more corrosion debris and a greater surface area for metal ion release, and their higher failure rates led to some recalls.
- Corrosion Type
- Crevice + fretting (MACC)
- Clinical Significance
- Primary failure site in modular THA
- Corrosion Type
- Crevice + fretting
- Clinical Significance
- Hardware loosening, pain
- Corrosion Type
- Fretting + third-body wear
- Clinical Significance
- Osteolysis, loosening
- Corrosion Type
- Tribocorrosion
- Clinical Significance
- Metal ion release, ALVAL
- Corrosion Type
- Pitting (rare)
- Clinical Significance
- Usually minor clinical impact
Taper design. The design variables that decide how much a taper frets, and why certain implant designs and materials fail preferentially:
- Effect on Corrosion
- Smaller angle = more contact, less micro-motion
- Optimal Design
- 5°40' standard Morse taper
- Effect on Corrosion
- Longer = more contact area, better stability
- Optimal Design
- Longer tapers reduce fretting
- Effect on Corrosion
- Too smooth = poor seating; too rough = fretting
- Optimal Design
- Optimal Ra 0.4-0.8 μm
- Effect on Corrosion
- Matched metals eliminate galvanic component
- Optimal Design
- CoCr on CoCr preferred
- Effect on Corrosion
- Larger head = more taper stress = more fretting
- Optimal Design
- Keep 36mm or less
Classification
Beyond the four mechanisms above, with MACC as the combination that matters clinically, corrosion is classified by the severity of what is found, by the pattern of damage on a retrieved taper, and by which of wear and corrosion drives the other.
Severity. The grade ties the appearance of the taper to the serum ions and to the action taken.
- Visual Appearance
- Minor discolouration, intact taper
- Metal Ion Levels
- Less than 2 ppb Co/Cr
- Clinical Action
- Monitor, annual review
- Visual Appearance
- Black debris, some surface damage
- Metal Ion Levels
- 2-7 ppb Co/Cr
- Clinical Action
- Increase surveillance, imaging
- Visual Appearance
- Gross material loss, deep pitting
- Metal Ion Levels
- 7-20 ppb Co/Cr
- Clinical Action
- Consider revision, MRI for soft tissue
- Visual Appearance
- Taper fracture, massive debris
- Metal Ion Levels
- Greater than 20 ppb Co/Cr
- Clinical Action
- Urgent revision required
Goldberg classification of taper corrosion. Four patterns, in order of material loss:
- Type I - Fretting: a burnished appearance with material transfer between the surfaces and no significant material loss; early-stage corrosion
- Type II - Crevice: black debris deposition, localised pitting and pH-driven dissolution, with moderate material loss
- Type III - Mixed: combined fretting and crevice, which is true MACC; the most common severe pattern, with significant material loss
- Type IV - Etching: generalised surface attack by electrochemical dissolution, with severe material loss and often fatigue failure
Tribocorrosion. The same wear-corrosion synergy is classified by which process drives the other.
- Definition
- Wear-accelerated corrosion
- Primary Site
- MoM bearing surfaces
- Definition
- Corrosion-accelerated wear
- Primary Site
- Polyethylene third-body wear
- Definition
- Synergistic tribocorrosion
- Primary Site
- Modular tapers (MACC)
Investigations
Serum cobalt and chromium. The primary biomarker for MoM monitoring. Under 1 ppb (μg/L) is normal; 2-7 ppb is elevated and calls for increased surveillance; over 7 ppb is concerning and prompts further investigation; over 20 ppb is critical and revision is often indicated. The result is only as good as the sample: a fasting morning sample, because some foods contain metals, drawn into a metal-free trace element tube, avoiding contamination from the needle hub, and run by a laboratory with a validated ICP-MS assay. Recent activity may elevate levels.
When. Annually as a minimum for every MoM hip, at presentation when symptomatic, and at 3 and 12 months after revision.
Imaging. Serum ions and MARS MRI are the cornerstone investigations for suspected corrosion-related pathology; radiographs come first and are the baseline everything else is compared with.
- Findings
- Osteolysis, implant migration, loosening
- Role
- First-line, baseline comparison
- Findings
- Pseudotumour, soft tissue necrosis, fluid collection
- Role
- Gold standard for ALVAL
- Findings
- Fluid collections, pseudotumour
- Role
- Screening, guided aspiration
- Findings
- Bone detail with metal suppression
- Role
- Osteolysis assessment
MARS MRI (Metal Artefact Reduction Sequence) uses specialised pulse sequences and post-processing to reduce metal artefact, so that the periprosthetic soft tissues can be seen and ALVAL, pseudotumour and fluid collections detected.
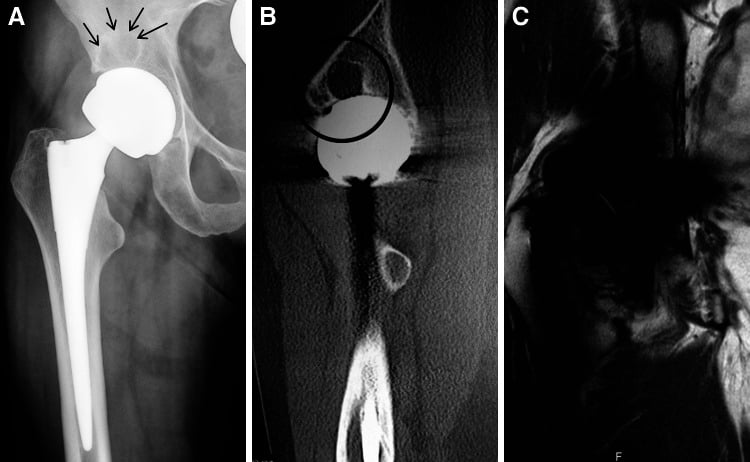
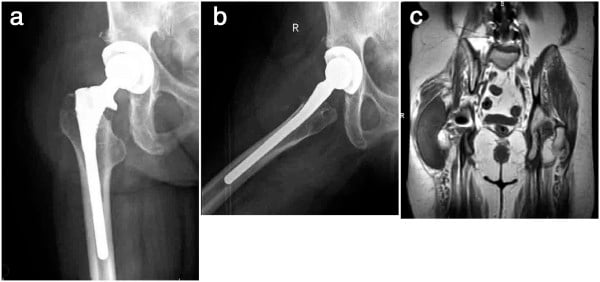
Lymphocyte transformation testing measures T-cell reactivity to metal ions on cobalt, chromium and nickel panels, and a positive result suggests Type IV hypersensitivity. Its use for pre-operative implant selection is controversial, it has a place in persistent symptoms after revision, and it remains a research tool rather than routine practice.
Synovial fluid. Aspirate a turbid grey-black fluid and it is corrosion debris; the metal ion concentration in the fluid is very high. Send it for culture and cell count to rule out infection, and for cytology, where macrophages containing metal particles and a lymphocyte predominance in ALVAL help to differentiate the reaction from infection.
- Discriminating Features
- Groin/buttock pain, soft-tissue mass, elevated Co and Cr, lymphocytic histology
- Key Investigation
- Blood Co/Cr plus MARS MRI
- Discriminating Features
- Rest pain, sinus, raised CRP/ESR, positive aspirate culture, neutrophilic histology
- Key Investigation
- Aspiration (culture, cell count, alpha-defensin)
- Discriminating Features
- Activity-related start-up pain, radiolucent lines, component migration
- Key Investigation
- Serial radiographs
- Discriminating Features
- Anterior groin pain on hip flexion, prominent/oversized cup
- Key Investigation
- Examination plus CT for cup overhang
- Discriminating Features
- Back-dominant pain, radicular signs, normal local hip workup
- Key Investigation
- Spinal examination and imaging
Elevated metal ions point towards ARMD, but infection must always be excluded by aspiration, because the two can coexist and their management differs fundamentally.
Anderson classification of ALVAL on MRI. The MRI appearance of the lesion carries prognostic weight.
- MRI Features
- Thin-walled fluid collection
- Clinical Significance
- May be asymptomatic
- MRI Features
- Solid mass, normal muscle signal
- Clinical Significance
- Often symptomatic, consider revision
- MRI Features
- Solid mass, muscle oedema/atrophy
- Clinical Significance
- Revision indicated, worse prognosis
- MRI Features
- Solid and cystic components
- Clinical Significance
- Variable prognosis
Intraoperative assessment. The retrieved taper is scored visually for corrosion, black debris being the corrosion product, its material loss measured by weight or volume, and photographed for documentation. Tissue goes for histopathology, which grades the ALVAL lymphocyte score, the extent of necrosis and the quantity of metal debris, and for culture and frozen section to rule out infection.
Management
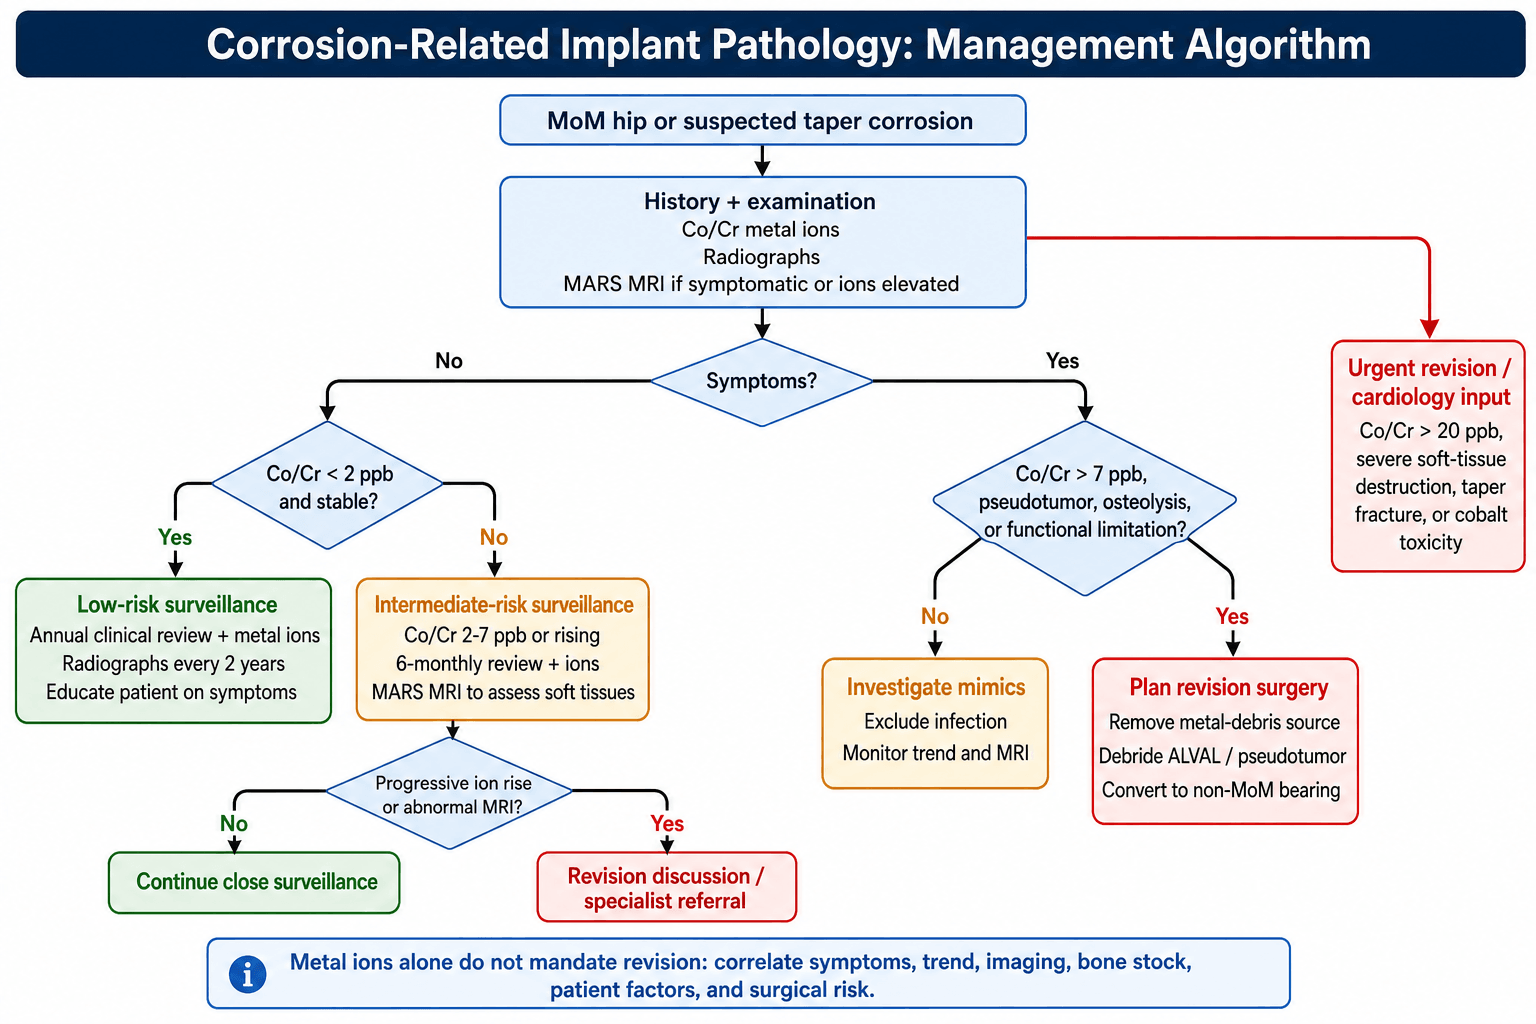
Asymptomatic, ions under 2 ppb and stable. Low-risk surveillance: annual clinical review and metal ion levels, radiographs every 2 years, and patient education on the symptoms to report. Continue indefinitely. Nothing more is needed unless symptoms develop, ions rise progressively or imaging abnormalities appear.
Asymptomatic, ions 2-7 ppb or rising, or an imaging abnormality. Intermediate risk: 6-monthly clinical review and metal ion levels, and MARS MRI to assess the soft tissues, annually. Revision is discussed if the ions rise progressively, imaging shows a pseudotumour, or the patient is high-demand with a long life expectancy.
Symptomatic with ions over 7 ppb, or progressive. High risk: plan revision, with specialist referral and pre-operative optimisation, once infection and the other mimics have been excluded.
- Strength
- Strong
- Timing
- Elective revision planned
- Strength
- Strong
- Timing
- Semi-urgent revision
- Strength
- Strong
- Timing
- Before bone loss worsens
- Strength
- Moderate-strong
- Timing
- Revision recommended
- Strength
- Moderate
- Timing
- Close surveillance vs revision
Delay increases complexity. Early revision before extensive soft tissue or bone destruction improves outcomes. Waiting for severe symptoms often means worse tissue damage.
Non-operative measures. Activity modification, fewer loading cycles and lower-impact activities, may reduce metal ion generation, but the evidence is limited, it does not address the underlying pathology, and it may only delay an inevitable revision. Medical optimisation before revision means cardiac assessment if cobalt is high, neurological assessment if symptomatic, attention to nutritional status and comorbidity management; the cobalt toxicity concerns are cardiomyopathy, thyroid dysfunction, visual and hearing impairment and neurological symptoms.
Deciding. The decision weighs symptoms, the metal ion level and its trend, imaging (pseudotumour, ALVAL), bone stock, patient age and activity, surgical risk and the alternative implant options, through a multidisciplinary approach with shared decision-making. Individualised management balances the risks of revision against the consequences of continued corrosion.
- Favours Revision
- Painful, functional limitation
- Favours Surveillance
- Asymptomatic
- Favours Revision
- Greater than 7 ppb or rising
- Favours Surveillance
- Stable less than 2 ppb
- Favours Revision
- Pseudotumour, osteolysis
- Favours Surveillance
- Normal soft tissues
- Favours Revision
- Young, long life expectancy
- Favours Surveillance
- Elderly, limited life expectancy
- Favours Revision
- High demand
- Favours Surveillance
- Low demand
- Favours Revision
- Low operative risk
- Favours Surveillance
- High medical comorbidities
Elevated metal ions alone do NOT mandate revision. Clinical correlation is essential: assess symptoms, imaging and patient factors. Many patients with moderately elevated levels remain asymptomatic.
Surgical Technique
Head exchange, when the stem is well fixed. Indicated for taper corrosion with a well-fixed stem, good bone stock and no extensive tissue destruction. Dislocate the hip and remove the head, clean the taper thoroughly and dry it, inspect it for damage, and seat a new ceramic head on the clean, dry taper with a single firm impaction. If the taper is damaged, use a sleeve adapter.
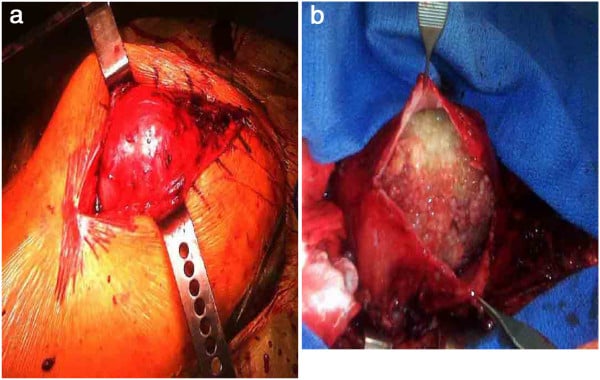
Complete revision. For a loose stem, severe taper damage or fracture, extensive osteolysis, or a pseudotumour with bone destruction. It needs an extended approach for exposure, thorough debridement of necrotic tissue, revision of the acetabulum if affected, a new stem with modular options, and bone grafting where needed.
Approach. Large pseudotumours often extend posteriorly and need to be seen in full for complete excision, so a posterior approach is often the best access. The options are an extended posterior approach, a trochanteric osteotomy if needed, and combined approaches for large pseudotumours.
Tissue handling. Document the tissue appearance with photographs, send tissue for histology (ALVAL score) and for culture to rule out infection, assess abductor integrity and viability, and assess and classify the bone defects.
- Action
- Complete excision
- Rationale
- Remove source of inflammation
- Action
- Thorough debridement
- Rationale
- Remove reactive tissue
- Action
- Lavage, debride what possible
- Rationale
- May not fully remove all staining
- Action
- Debride back to viable tissue
- Rationale
- Document for prognosis
The taper. What is done to it depends on what is found.
- Option
- New ceramic head
- Considerations
- Clean/dry assembly, single impaction
- Option
- Ceramic head with titanium sleeve adapter
- Considerations
- Bypasses damaged taper surface
- Option
- Sleeve adapter mandatory
- Considerations
- Multiple systems available
- Option
- Stem revision required
- Considerations
- No salvage possible
Bearing at revision. Ceramic-on-ceramic eliminates metal ions; ceramic-on-polyethylene (XLPE) has very low wear; metal-on-polyethylene is acceptable if a ceramic taper is used. Avoid another metal-on-metal bearing, a mixed metal taper couple, and large metal heads on modular tapers.
Stability. After ALVAL or a pseudotumour the abductors are often compromised and the dislocation risk is higher, so consider a dual mobility cup, larger head sizes within reason, and a constrained liner if severe; soft tissue repair, tendon transfers for abductor deficiency and an extended rehabilitation protocol may be needed. Revision for corrosion has higher complication rates than routine revision because of the tissue destruction, with dislocation rates of 10-20% in severe ALVAL cases with abductor damage, and the bearing choice and soft tissue management are how that is planned for.
Complications
Local tissue destruction. ALVAL and pseudotumour produce soft tissue necrosis around the implant, a solid or cystic pseudotumour, abductor muscle destruction and, rarely, femoral nerve compression. Bone is involved through debris-driven osteolysis and periprosthetic bone loss, which may compromise fixation at revision.
Systemic cobalt toxicity. Cardiomyopathy, thyroid dysfunction, peripheral neuropathy, and visual and hearing impairment, typically with very high levels, usually over 50-100 ppb. It may be reversible with revision, and cardiac monitoring is recommended.
- Incidence
- 5-30% of MoM hips
- Severity
- Moderate to severe
- Incidence
- 5-15% (corrosion-related)
- Severity
- Moderate
- Incidence
- Less than 1%
- Severity
- Potentially severe
- Incidence
- Less than 1%
- Severity
- Severe - requires revision
- Incidence
- 10-20%
- Severity
- Variable
Complications of the revision itself. Intraoperatively the tissue quality is poor for repair, bone has been lost to osteolysis, exposure is difficult through scarring and inflamed tissue bleeds; the specific risks are nerve injury (femoral, sciatic), fracture of weakened bone and incomplete debridement. The early postoperative complications are dislocation, wound complications, deep vein thrombosis and infection, driven by poor tissue healing capacity, the effect of metallosis on wound healing and abductor deficiency.
- Risk Factors
- Abductor deficiency, large tissue resection
- Management
- Constrained liner, revision, tendon transfer
- Risk Factors
- Incomplete debridement, hypersensitivity
- Management
- Consider metal allergy testing, further revision
- Risk Factors
- Incomplete excision, new corrosion source
- Management
- Re-revision if significant
- Risk Factors
- Abductor weakness, nerve injury
- Management
- Physiotherapy, assistive devices
Cobalt cardiomyopathy. Rare but serious. It presents with dyspnoea, fatigue and oedema, a dilated cardiomyopathy on echocardiography, sometimes as acute heart failure, and the other toxic effects are often present. The diagnosis rests on a high serum cobalt (often over 100 ppb), ECG conduction abnormalities, and the exclusion of other causes of cardiomyopathy.
Treatment is urgent revision with cardiology involvement and standard heart failure management, monitoring the recovery of cardiac function. It is often reversible once the source is removed, improving over weeks to months, though some patients have residual damage.
Postoperative Care
Metal ions after revision. Sample at 3 months (the post-revision baseline), at 12 months (to assess the decline) and then annually until levels normalise. Expect a rapid initial decline over the first 3-6 months and gradual normalisation over 1-2 years; levels may not return to normal in every patient.
Clinical review. At 6 weeks (wound, weight-bearing), 3 months (function), 6 months (metal ions, radiographs), 12 months (comprehensive review) and then annually. At each visit assess hip function (Oxford Hip Score), stability (dislocation precautions) and symptoms (pain, clicking).
- Focus
- Protected weight-bearing, precautions
- Special Considerations
- Extended hip precautions if abductor damage
- Focus
- Strengthening, gait training
- Special Considerations
- Focus on abductor rehabilitation
- Focus
- Progressive loading, function
- Special Considerations
- May need abductor brace if weak
- Focus
- Return to activities
- Special Considerations
- Some permanent limitations expected
Systemic toxicity after revision. If there was cobalt toxicity before revision, obtain a baseline echocardiogram, arrange cardiology follow-up and monitor cardiac function serially: it usually improves after revision, recovery may take 6-12 months, and some patients have residual dysfunction. Document any peripheral neuropathy before revision; it may improve, some sensory loss may persist, and nerve conduction studies are used if severe. Monitor thyroid function, and vision and hearing if affected; most symptoms are reversible.
- Possible Cause
- Incomplete debridement, instability, infection
- Investigation
- MRI, aspiration
- Possible Cause
- Incomplete excision, new corrosion
- Investigation
- MARS MRI, metal ions
- Possible Cause
- Residual debris, new corrosion source
- Investigation
- Imaging review, consider re-revision
- Possible Cause
- Abductor deficiency, component position
- Investigation
- Examination, imaging, consider constrained revision
Long term. Survival of the revision implant is generally good with adequate debridement, may be compromised by bone loss, depends on the component choice, and ceramic bearings reduce the risk of re-corrosion. Pain and function improve but may not return to the pre-failure baseline; abductor weakness is often permanent and some patients have persistent limitations.
Outcomes
Metal ion decline. A mean 50-70% reduction at 12 months, with normalisation (under 2 ppb) in most patients; some have persistent elevation, and the rate of decline varies with the extent of the initial metallosis, the completeness of debridement and the bearing chosen.
Function. The Oxford Hip Score improves significantly, the Harris Hip Score by a mean of 20-30 points, and 70-85% of patients are satisfied. Scores often do not reach primary THA levels, abductor weakness limits function, and some persistent pain is common.
- Better Outcome
- Minimal pseudotumour
- Worse Outcome
- Extensive destruction
- Better Outcome
- Intact abductors
- Worse Outcome
- Necrotic/absent abductors
- Better Outcome
- Minimal osteolysis
- Worse Outcome
- Severe bone loss
- Better Outcome
- Early (before extensive damage)
- Worse Outcome
- Late (symptomatic, severe ALVAL)
- Better Outcome
- Moderately elevated
- Worse Outcome
- Very high (greater than 50 ppb)
Re-revision. Rates at 5 years, by source and by scenario.
- Re-revision Rate
- 10-15% at 5 years
- Notes
- Higher than primary revision rates
- Re-revision Rate
- 12-18% at 5 years
- Notes
- Depends on reason for primary revision
- Re-revision Rate
- 15-25% at 5 years
- Notes
- Abductor damage increases dislocation
- Re-revision Rate
- 5-10% at 5 years
- Notes
- If stem well-fixed, good outcome
Dislocation. 5-10% with minimal abductor damage and 15-25% with significant abductor loss; constrained liners reduce it but do not eliminate it, and the risk is highest in the first 6 months. The risk factors are abductor muscle necrosis, a large tissue resection, previous dislocation and non-compliance with precautions.
Infection. 2-5%, higher than after primary THA, because the tissue is compromised and the surgery prolonged. Prevention is antibiotic prophylaxis, meticulous technique and avoiding excessive tissue handling.
Survivorship. At 1 year most patients have a significant improvement in pain and function, and the metal ions have declined. At 5 years implant survival is 85-90% in most series, function is stable, and some patients need re-revision for instability or other causes. At 10 years the data are limited; results appear comparable to other revision scenarios, and bone stock preserved at the initial revision matters. Outcomes depend heavily on the tissue and bone damage present before revision, which is the case for revising early.
Clinical Implications and Prevention
Failed metal-on-metal hips. In most modern MoM failures the primary failure mode is taper corrosion, not bearing surface wear. Retrievals show severe MACC with debris at the taper while the bearing surfaces are often well preserved; mixed metal couples (CoCr/Ti) show worse corrosion, and a large head diameter increases the mechanical stress on the taper.
Risk factors. The taper corrodes faster with:
- A large femoral head diameter (greater than 36mm), which puts higher torque on the taper
- Increased offset, which raises the moment arm on the taper
- High patient BMI and activity level
- A mixed metal couple (CoCr on Ti)
- Poor taper assembly (contamination, multiple impacts)
Taper assembly. The steps that minimise MACC, and the reason for each:
- Clean and dry - contaminants prevent full seating and increase micro-motion
- Single impaction - multiple impacts damage the taper surface
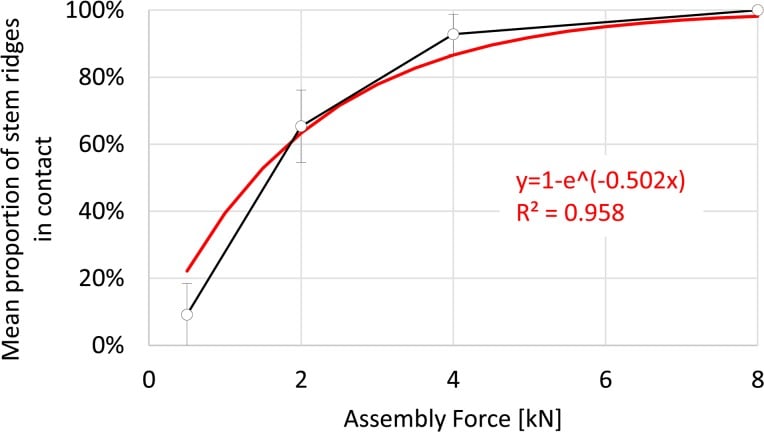
- Adequate force - ensures taper engagement and minimises micro-motion
- Matched materials - CoCr on CoCr eliminates the galvanic component
- Mechanism
- Eliminates metal taper corrosion
- Effectiveness
- Excellent
- Considerations
- Fracture risk (historical concern, rare with modern ceramics)
- Mechanism
- Eliminates galvanic corrosion
- Effectiveness
- Good
- Considerations
- CoCr on CoCr preferred over CoCr on Ti
- Mechanism
- Reduces taper mechanical stress
- Effectiveness
- Good
- Considerations
- Alternative bearing, not directly addressing corrosion
- Mechanism
- Reduces moment arm on taper
- Effectiveness
- Moderate
- Considerations
- May increase dislocation risk in some patients
- Mechanism
- Minimises micro-motion
- Effectiveness
- Essential
- Considerations
- Clean, dry, single impaction - surgeon dependent
Material selection. Titanium stems have excellent corrosion resistance but are the weaker partner at the taper when coupled with CoCr; CoCr stems have a stronger taper but are heavier and stiffer. Ceramic heads eliminate metal taper corrosion at the cost of the historical fracture concern, and a ceramic head on a titanium stem is the popular modern compromise.
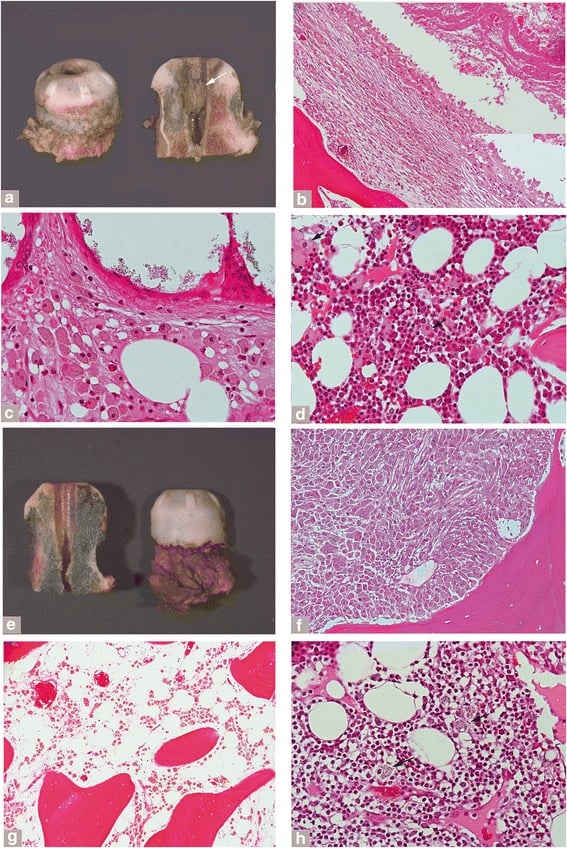
What a ceramic head does not do. The retrieval panels below show the material-related difference between ceramic and cobalt-chromium heads, and they also show that a ceramic head does not make the taper interface immune to fretting or to metal transfer. Use the retrieval score as a descriptor of what was found, not as a validated bedside severity scale.



Guidelines, Registries & Global Practice
Global Epidemiology of Corrosion-Related Failure
Implant corrosion is relevant wherever modular metal hip components are used, which is virtually universal. Two clinical phenotypes dominate: adverse reactions to metal debris (ARMD) from metal-on-metal (MoM) bearings, and head-neck taper corrosion (trunnionosis) in metal-on-polyethylene hips. The National Joint Registry of England and Wales demonstrated that stemmed MoM articulations fail at high rates that rise with head diameter, with young women receiving large-diameter heads at greatest risk.[Smith 2012] Pseudotumour develops in approximately 1% of MoM resurfacing patients within 5 years, with female sex and small components as key risk factors.[Pandit 2008]
What the major joint registries show:
- Stemmed large-head MoM THA has markedly higher revision than ceramic-on-ceramic or ceramic/metal-on-polyethylene
- Revision risk rises with head diameter for MoM (opposite to ceramic-on-ceramic)
- These signals drove global abandonment of large-head MoM by the early 2010s
- MoM bearings now represent a very small fraction of primary THA worldwide
Current global position:
- Higher revision than standard THA overall
- Better in young active men with large femoral heads; poor in women and small components
- Now confined to selected high-volume centres and specific designs
- Registry data (NJR, AOANJRR, NZJR) consistently show sex- and size-dependent outcomes
Surveillance Recommendations - Side by Side
- Core Recommendation
- Annual review of all MoM hips for implant life; blood Co/Cr and MARS MRI if symptomatic or ions elevated
- Evidence Basis
- Registry + retrieval evidence
- Core Recommendation
- Symptom-driven follow-up; metal ion testing and cross-sectional imaging for symptomatic patients
- Evidence Basis
- Expert/regulatory consensus
- Core Recommendation
- Risk-stratified surveillance; lower thresholds for large-head and symptomatic patients
- Evidence Basis
- Consensus, level IV-V
- Core Recommendation
- Co or Cr around 7 ppb (approximately 119 nmol/L) prompts further investigation
- Evidence Basis
- Cohort/registry correlation
Exam Viva Point: "What does registry evidence show about MoM hips?" Answer: National registries (NJR, AOANJRR, others) showed high, head-size-dependent revision rates for stemmed MoM THA, especially in young women with large heads. This evidence drove the global withdrawal of large-head MoM and underpins mandatory surveillance of existing implants.[Smith 2012]
Registry and retrieval evidence converted MoM corrosion from a theoretical concern into a worldwide device-safety issue.
MCQ Practice Points
Q: What provides corrosion resistance to titanium implants? A: TiO2 passivation layer (titanium oxide). This thin (2-10 nm) oxide layer forms spontaneously and is self-healing. It prevents titanium metal from contacting the corrosive environment.
Q: What is MACC and where does it occur? A: Mechanically-Assisted Crevice Corrosion - synergistic combination of micro-motion (disrupts passivation) and crevice environment (low pH, chloride). Primary failure mode at modular hip tapers.
Q: In a CoCr head on Ti stem taper, which metal corrodes? A: Titanium - Ti is less noble than CoCr in the galvanic series, so Ti acts as anode and corrodes preferentially. CoCr acts as cathode and is protected.
Q: What type of hypersensitivity reaction is ALVAL? A: Type IV delayed hypersensitivity (T-cell mediated). Metal ions bind proteins forming haptens, leading to T-cell sensitization and lymphocytic tissue infiltration.
Q: What serum cobalt or chromium level warrants concern in MoM hips? A: 7 ppb (approximately 119 nmol/L) for either metal is the regulatory action level that prompts further investigation. Levels above this threshold are associated with increased corrosion/wear and revision risk. Normal is less than 1 ppb.
Q: What is the pH inside a crevice undergoing crevice corrosion? A: pH 3-4 (highly acidic) - Metal hydrolysis produces H+ ions and oxygen depletion prevents neutralization. This low pH dissolves the passivation layer.
Q: What is the characteristic appearance of fretting corrosion debris? A: Black debris - mixture of metal oxide particles (FeO, TiO2, Cr2O3) from repeated disruption of passivation and oxidation. Distinguishes fretting from pure wear.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“Examiner asks: Describe the four main types of corrosion in orthopaedic implants and give a clinical example of each.”
“Patient with painful MoM hip has serum cobalt 45 ppb, chromium 38 ppb, and MRI shows large pseudotumor. Examiner asks about pathophysiology and management.”
“Examiner asks: You are performing primary THA with a CoCr head on titanium stem. Describe your taper assembly technique and explain the rationale.”
Electrochemistry Basics
- Corrosion = electrochemical degradation (oxidation-reduction)
- Anode: M → M^n+ + e^- (metal oxidizes, goes into solution)
- Cathode: O2 + 2H2O + 4e^- → 4OH^- (reduction)
- Passivation layer (TiO2, Cr2O3) prevents corrosion
- Body fluid aggressive: 0.9% NaCl, pH 7.4, chloride ions
Four Types of Corrosion
- GALVANIC: Dissimilar metals (CoCr/Ti) - less noble corrodes (Ti)
- CREVICE: Oxygen depletion → pH 3-4 → passivation dissolved
- PITTING: Localized chloride attack → small hole, deep penetration
- FRETTING: Micro-motion disrupts passivation + corrosion (synergy)
- MACC = Mechanically-Assisted Crevice Corrosion (taper failure mode)
ALVAL Pathophysiology
- Aseptic Lymphocyte-dominated Vasculitis-Associated Lesion
- Type IV delayed hypersensitivity to Co and Cr ions
- Metal ions + proteins = haptens → T-cell sensitization
- Perivascular lymphocytic infiltration, tissue necrosis
- Pseudotumor = soft tissue mass with necrosis (not tumor)
- Histology: lymphocytes, no bacteria (NOT infection)
Metal Ion Monitoring
- Normal: Co and Cr less than 1 ppb
- Normal under 1 ppb; action level 7 ppb (~119 nmol/L) either metal - a number in the tens is never normal
- Action threshold: greater than 7 ppb warrants investigation
- Annual surveillance for all MoM hips recommended
- Elevated levels: MRI for pseudotumor, consider revision
- Levels decline 6-12 months after revision (slow)
Taper Assembly (Prevent MACC)
- CLEAN: No debris on tapers
- DRY: No blood/fluid contamination (prevents full seating)
- SINGLE: One firm impaction (multiple damages surface)
- MATCH: CoCr on CoCr better than CoCr on Ti (no galvanic)
- CERAMIC: Ceramic head eliminates taper corrosion risk
Prevention Strategies
- Avoid mixed metals (galvanic corrosion)
- Proper taper assembly critical
- Ceramic heads eliminate metal taper corrosion
- Avoid large heads (reduce taper mechanical stress)
- Polish surfaces (reduce stress concentrations for pitting)
Evidence Base
Goldberg, Gilbert, Jacobs et al - Multicentre Retrieval Study of Modular Taper Interfaces
- Retrieval analysis of 231 modular hip implants attributing in-vivo taper corrosion to mechanically-assisted crevice corrosion (MACC)
- Mixed-alloy couples corroded more than similar-alloy couples: moderate-to-severe head corrosion in 42% of mixed versus 28% of similar-alloy tapers
- Implantation time and neck flexural rigidity were predictors of corrosion and fretting
- Larger-diameter (stiffer) necks may reduce fretting, balanced against range-of-motion loss
Langton et al - Early Failure of Metal-on-Metal Bearings from Adverse Reaction to Metal Debris
- Series of 660 MoM resurfacings/large-head THRs: 3.4% (17 hips, all ASR) revised for adverse reaction to metal debris (ARMD)
- ARMD patients had significantly higher blood and joint chromium and cobalt ion concentrations than asymptomatic patients (all p less than 0.001)
- ARMD associated with smaller components and higher acetabular anteversion
- Explants from ARMD revisions showed greater bearing wear, supporting excess wear as a driver
Willert et al - Metal-on-Metal Bearings and Hypersensitivity (ALVAL)
- Landmark description of a lymphocyte-dominated immunological reaction (ALVAL) in revised second-generation MoM hips
- Histology: diffuse and perivascular T and B lymphocyte infiltrates, high endothelial venules, fibrin exudation, macrophages and necrosis - distinct from infection
- Only few metal particles seen, supporting hypersensitivity rather than purely particle-volume-driven reaction
- Patients re-revised to another MoM articulation had no symptom relief
These three studies establish the electrochemical mechanism (MACC) and the hypersensitivity basis (ALVAL) of corrosion-related implant failure.