Congenital Variant | Snapping Knee in Children | Watanabe / Ahn Classification
- Lateral much greater than medial discoid meniscus in Western populations (reversed in East Asian cohorts)
- Snapping / clicking knee in a child under 10 should raise suspicion
- MRI: 3 or more consecutive sagittal bow-tie slices is the classic diagnostic criterion
- Asymptomatic discoid menisci are observed; saucerisation is reserved for symptoms or instability
- Wrisberg type needs stabilisation, not just reshaping - missing this causes persistent symptoms
- “Wrisberg type = unstable posterior horn = no tear but still symptomatic
- “Saucerisation preserves a 6-8 mm peripheral rim - total meniscectomy is never acceptable in children
- “Often bilateral; image the contralateral knee if a discoid meniscus is found
- “Watanabe and Ahn classifications are complementary - Ahn adds instability subtypes
Overview and Epidemiology
Discoid lateral meniscus is the most common congenital meniscal variant and the leading cause of mechanical snapping knee in children. Most discoid menisci are asymptomatic and discovered incidentally. The symptomatic ones bring clicking, early lateral compartment overload and progressive tearing, and the reason to recognise them early is that rim-preserving surgery protects the lateral compartment from premature osteoarthritis.
Who. Incidence is 3-5% in Western populations and up to 13-17% in East Asian cohorts. The lateral meniscus is affected much more often than the medial in Western practice, where a medial discoid meniscus is rare (1-2% of discoid menisci); the reverse is true in East Asian series. The variant is bilateral in 15-25% of cases, so image the contralateral knee when one is found. Symptoms present at 5-15 years, often first noticed with sport, and most series report a slight male predominance.
What it does to the knee. The snapping knee is the presenting complaint: an audible click with flexion and extension, lateral pain and swelling, an effusion after activity and an intermittent limp. Squatting, kneeling and pivoting sports become difficult, and the long-term cost is premature arthritis of the lateral compartment.
Anatomy and Pathophysiology
The theory that is still taught. The traditional account is that the fetal meniscus is a solid disc which normally undergoes central resorption, and that a discoid meniscus is that disc retained. It is memorable and widely repeated, and fetal morphometry does not support it: no discoid stage has been demonstrated in normal human development, and there is no resorption phase to fail.
What development actually shows. Across 41 human fetuses from 14 to 30 weeks and 14 adults, the proportion of the tibial plateau covered by the meniscus was consistently greater laterally than medially at every stage, and the layered collagen structure matured earlier in the lateral meniscus. The lateral meniscus is therefore normally the larger and the more variable of the two, which is a far better explanation for why discoid morphology is almost exclusively lateral than a resorption that never happens.
The tissue, which is what matters clinically. A discoid meniscus is structurally abnormal, not merely large. Its collagen is disorganised and the normal circumferential fibre architecture is deficient, so it cannot convert axial load into hoop stress properly: it transmits load centrally rather than circumferentially, sends higher contact stress to the lateral cartilage, degenerates within its substance and tears far more readily than a normal meniscus. Tears are found in 70 to 77% of symptomatic cases, and the degenerate central tissue is prone to horizontal cleavage.
Why a disc snaps. Thick central tissue catches between femur and tibia in extension. In the Wrisberg type, which lacks a posterior tibial attachment, the meniscus slides anteriorly and blocks terminal extension, producing the dynamic block and the classical clunk.
Instability is a separate problem from shape. Do not equate instability with the Wrisberg variant. The rim can be detached at its anterior, middle or posterior third, and the site recorded at arthroscopy is the subject of the stability check under Management.
- Normal meniscus
- Crescent, semilunar
- Discoid meniscus
- Disc, covers greater than 50 percent of plateau
- Clinical consequence
- Loss of normal wedge and hoop function
- Normal meniscus
- Firm tibial insertion
- Discoid meniscus
- Wrisberg type lacks tibial attachment
- Clinical consequence
- Hypermobility, snapping, locking
- Normal meniscus
- Approximately 50 percent coverage
- Discoid meniscus
- Greater than 80 percent coverage
- Clinical consequence
- Increased focal cartilage stress
- Normal meniscus
- Longitudinal, radial, flap
- Discoid meniscus
- Horizontal cleavage common, intrasubstance
- Clinical consequence
- Degenerative, often central
The long-term consequences. Chronic overload marks the bone: a cupped lateral tibial plateau and squaring of the femoral condyle, and long-standing cases may develop valgus alignment from lateral compartment collapse. Even an untreated asymptomatic discoid meniscus accelerates lateral compartment wear, though the natural history in the absence of symptoms is usually benign, which is why the incidental finding is observed.
Why the rim heals and the centre does not. The whole rim-preservation and repair strategy rests on meniscal vascularity. Blood reaches the meniscus from the perimeniscal capillary plexus (geniculate branches) only at its periphery, which defines three zones:
- Red-red zone - peripheral, roughly the outer 3 mm, fully vascular; heals well and is ideal for repair
- Red-white zone - middle, junctional vascularity; variable healing
- White-white zone - inner third, avascular, nourished only by synovial diffusion; poor healing, and tears here are generally resected rather than repaired
That is why saucerisation resects the avascular central disc and keeps the vascular periphery as the rim, why a peripheral or Wrisberg-zone tear is repairable while a degenerate central horizontal cleavage usually is not, and why repair is favoured over resection in children, whose meniscus is relatively more vascular than an adult's.
Classification and Types
Watanabe's 1969 system is the original arthroscopic classification and still the most widely cited. Ahn's modification is more clinically directed and adds the instability subtypes that decide whether reshaping alone will do. The two are complementary: Watanabe describes the shape, Ahn describes whether the rim is attached.
- Anatomy
- Disc covers entire tibial plateau, no semilunar shape
- Stability
- Stable, attached peripherally
- Typical management
- Saucerisation if symptomatic
- Anatomy
- Semilunar but broader than normal, partial coverage
- Stability
- Stable, attached peripherally
- Typical management
- Saucerisation if symptomatic
- Anatomy
- Posterior horn attached only by Wrisberg ligament
- Stability
- Unstable, hypermobile
- Typical management
- Saucerisation + stabilisation / repair
The Wrisberg type is the only inherently unstable variant, and distinguishing it is critical because saucerisation alone is insufficient.
The Wrisberg type and the two meniscofemoral ligaments. The Wrisberg type is named after one of the two meniscofemoral ligaments, and the examiner will expect you to name both. They run from the posterior horn of the lateral meniscus to the medial femoral condyle, straddling the PCL: the ligament of Humphrey passes anterior to the PCL and the ligament of Wrisberg passes posterior to it ("Humphrey is in front, Wrisberg is at the rear"). They are accessory stabilisers of the lateral meniscus posterior horn; at least one is present in most knees, both in a minority.
Why reshaping alone fails. In the Wrisberg-variant discoid meniscus the normal posterior tibial (coronary/root) attachment is absent, so the posterior horn is anchored only by the ligament of Wrisberg. That leaves it free to translate anteriorly and snap, which is exactly why saucerisation alone leaves the meniscus hypermobile and posterior-horn reattachment is required.
Clinical Assessment
History. The classic presentation is snapping, clicking or locking in a child aged 5-12. The child, or the parents, describe a knee that snaps, clicks or clunks, usually with flexion and extension, and there is no major trauma in most cases. Ask about:
- Intermittent locking (inability to fully extend) in fixed flexion, which the child may unlock with a twist; locking suggests a peripheral tear or an unstable Wrisberg variant
- Lateral knee pain worse with squatting, pivoting and stairs, and not painful at rest
- Effusion after activity and an intermittent limp
- Giving way, which points to an unstable Wrisberg variant
Examination. The snap is usually audible and may be visible, so watch and listen as the knee flexes and extends while palpating the lateral joint line, and check that the click reproduces the child's symptom. Expect a mild to moderate lateral compartment effusion and tenderness localised to the lateral joint line. Range of motion is usually full; a block to terminal extension suggests a Wrisberg variant or a peripheral tear.
- Technique
- Repeated flexion / extension while palpating lateral joint line
- Positive finding
- Audible / palpable click that reproduces symptoms
- Notes
- Best single clinical clue in a child
- Technique
- Flexion to 90 degrees, internal rotation, varus, then extend
- Positive finding
- Palpable clunk at lateral joint line
- Notes
- Less reliable than in adults; often equivocal
- Technique
- Single-leg stance, flex 20 degrees, rotate body
- Positive finding
- Joint line discomfort or locking
- Notes
- Good sensitivity in older children and adolescents; well tolerated
- Technique
- Attempt passive full extension
- Positive finding
- Mechanical block to terminal extension
- Notes
- Suggests Wrisberg variant or large peripheral tear
A child with an audible snapping knee should be taken seriously, even if the parents describe it as harmless or the child has full range of motion. The most common cause of true snapping knee in a child under 12 is a discoid lateral meniscus, and delayed diagnosis risks progressive tear and early cartilage damage. Document the snap, examine under anaesthesia if needed, and arrange MRI before any arthroscopy.
- Key clue
- Snapping, locking, intermittent
- Discriminating test
- MRI bow-tie greater than 3 slices, posterior horn position
- Typical imaging
- MRI diagnostic
- Key clue
- Acute injury, effusion, joint line tenderness
- Discriminating test
- MRI shows normal shape meniscus with tear
- Typical imaging
- MRI shows tear in normal-sized meniscus
- Key clue
- Insidious lateral pain, intermittent swelling
- Discriminating test
- MRI shows subchondral lesion, may have fragment
- Typical imaging
- MRI or CT diagnostic
- Key clue
- Anterior pain, activity-related, no snap
- Discriminating test
- Negative MRI for meniscal pathology
- Typical imaging
- MRI of patellofemoral joint
- Key clue
- Posterolateral pain, no snap, overuse
- Discriminating test
- Clinical, MRI may show tendon oedema
- Typical imaging
- MRI helpful but not always diagnostic
- Key clue
- Lateral pain with running, no true snap
- Discriminating test
- Ober test, MRI may show ITB oedema
- Typical imaging
- MRI supportive
A discoid meniscus may be present for years without tearing, but when a peripheral tear develops the child often presents acutely with locking and effusion. The combination of a discoid meniscus on MRI plus a high intrasubstance or peripheral signal reaching the articular surface is the strongest predictor that saucerisation alone will fail - add repair.
Investigations
Radiographs. Weight-bearing AP, lateral, skyline and tunnel (notch) views. Their job is to exclude other pathology and record baseline alignment; they occasionally raise suspicion, but they are often normal in early disease, so a normal film does not exclude the diagnosis and any child with mechanical lateral knee symptoms should proceed to MRI. Look for:
- Widened lateral joint space (greater than 5-6 mm)
- Cupping or sloping of the lateral tibial plateau
- Hypoplastic lateral femoral condyle
- Squaring of the lateral femoral condyle in long-standing cases
MRI is the definitive investigation: non-invasive, no radiation, and it defines the anatomy for surgical planning. The protocol is a standard knee MRI with sagittal, coronal and axial PD / T2 fat-saturated sequences. The criteria:
- Bow-tie sign: the meniscus appears as a continuous bow-tie on 3 or more consecutive sagittal slices, against only 2 for a normal meniscus. This is the most reliable criterion and reflects the meniscus wrapping continuously across the lateral compartment. It assumes 5 mm slices, so quote the slice thickness: the rule is really meniscal continuity across more than about 15 mm, and it fails on thin-slice sequences where a normal meniscus will span four or more slices
- Transverse width: minimal meniscal width greater than 15 mm on the coronal slice through the mid-body
- Ratio: meniscal width greater than 20% of the maximal tibial width on the same coronal image; some use meniscal-to-tibial coverage above 75%. Coverage of greater than 50% of the tibial plateau on the coronal view is supportive
- Posterior horn: an absent, truncated or anteriorly translated posterior horn suggests the Wrisberg variant
- Tears: high intrasubstance signal reaching the articular surface, or peripheral signal. Look for one rather than being surprised by it
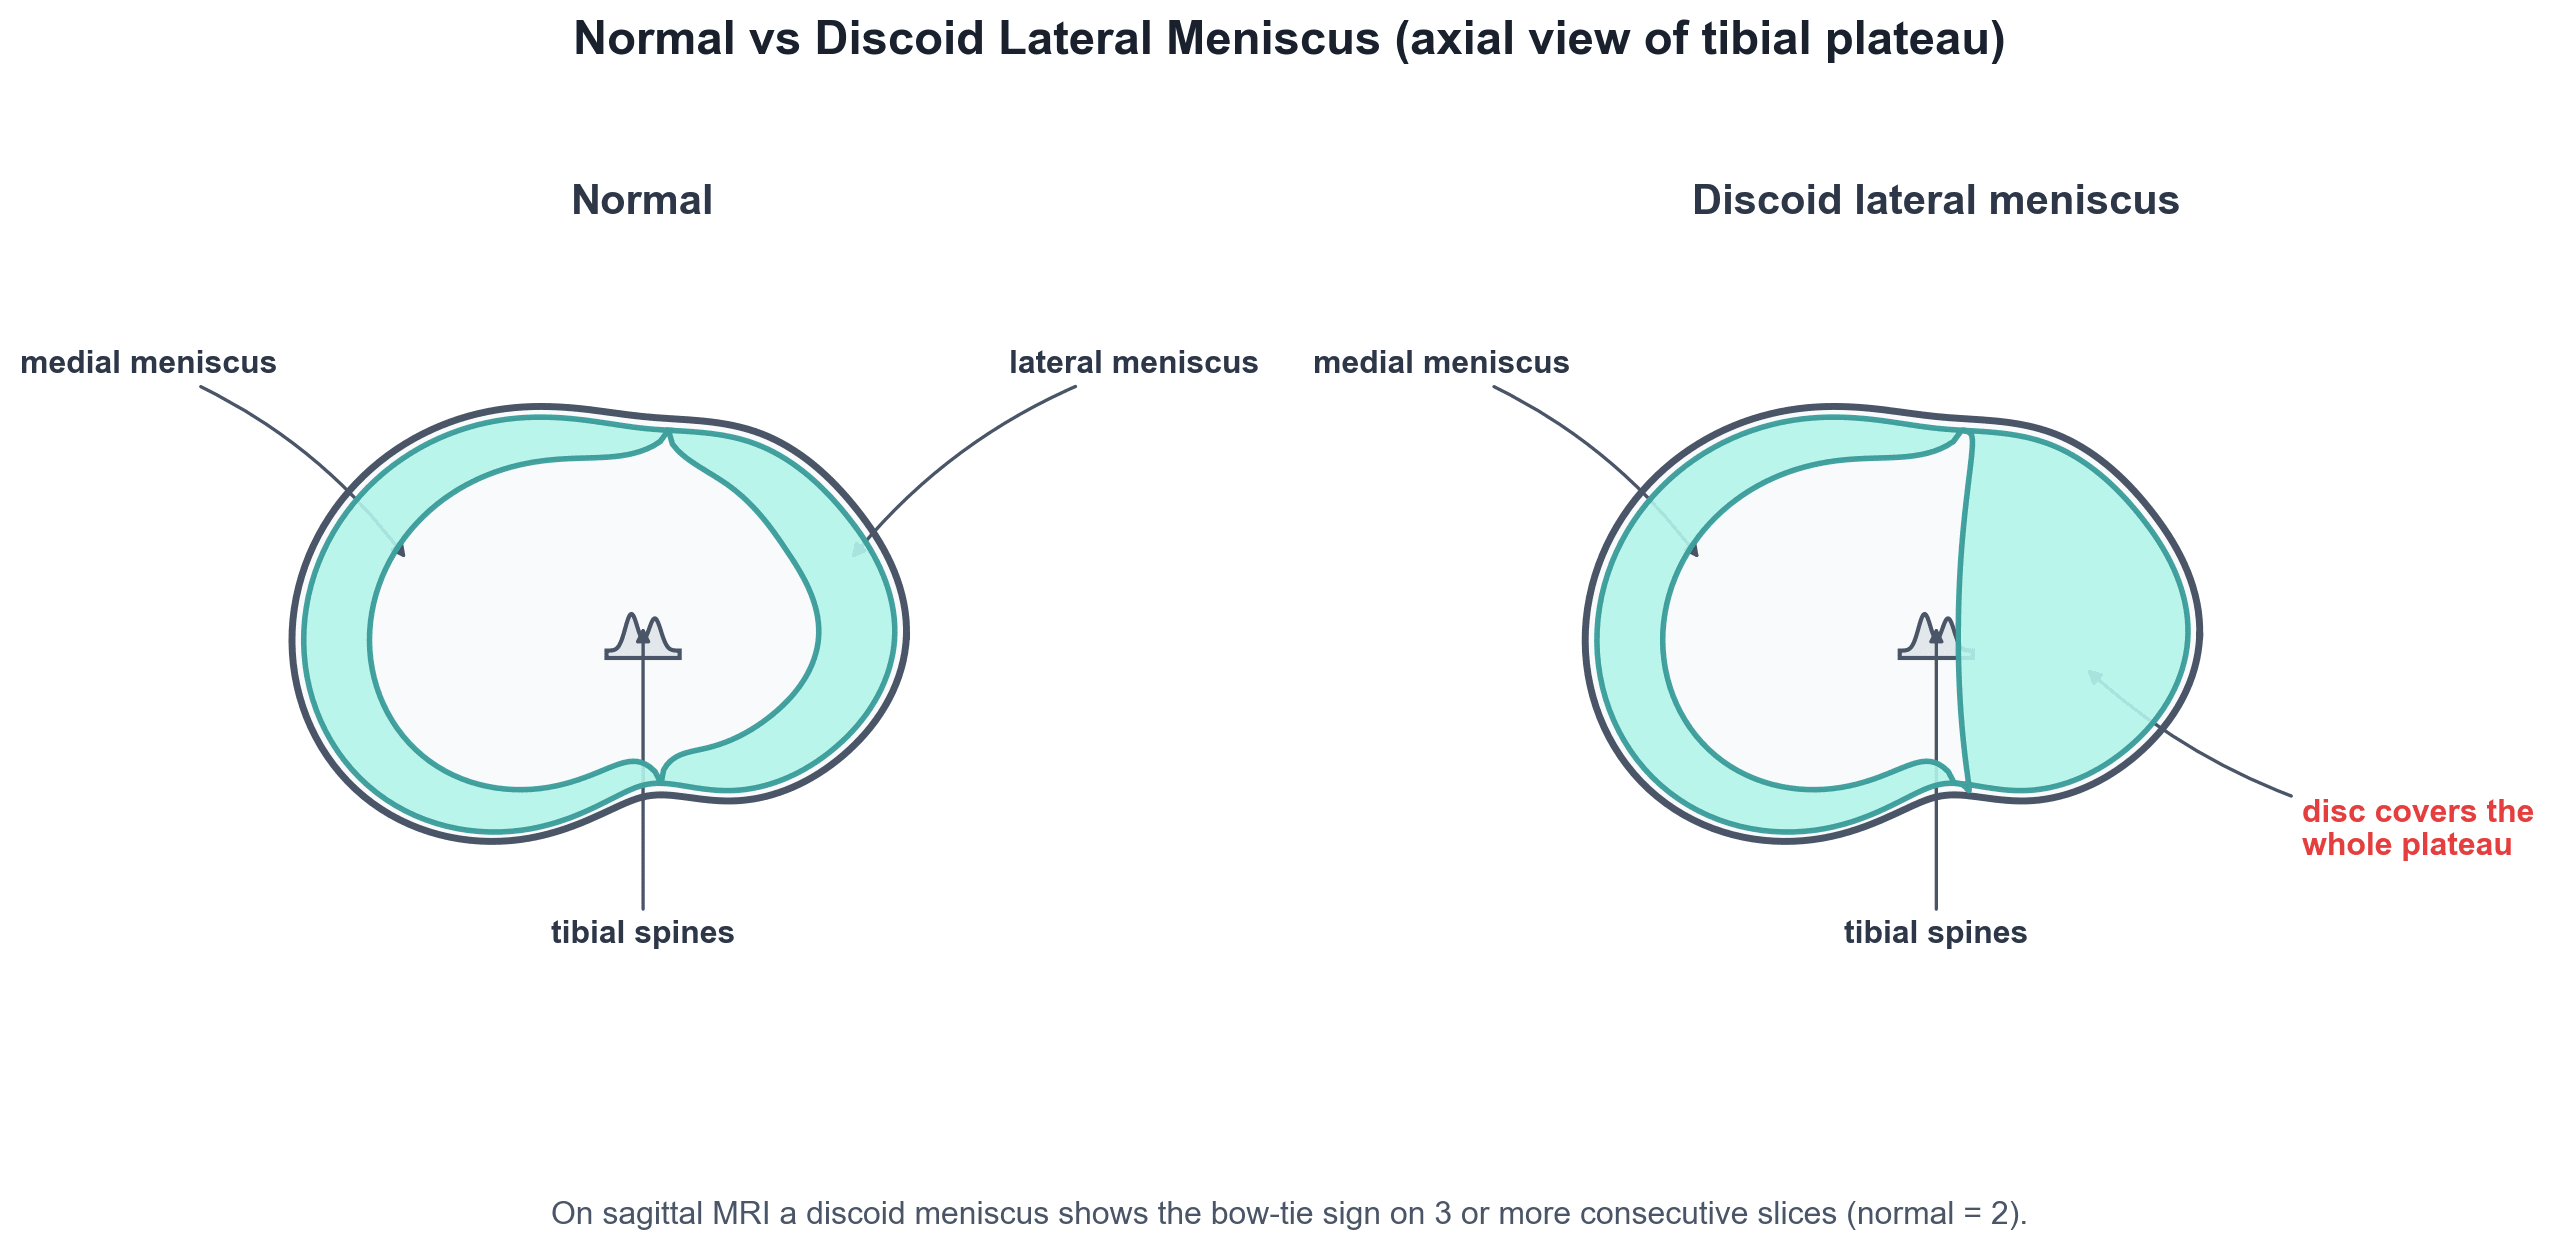
The Wrisberg variant can have an entirely normal-looking shape, and peripheral rim detachment is a dynamic finding. Instability is diagnosed by probing at arthroscopy, not by the scan; under anaesthesia the Wrisberg variant shows anterior translation of the posterior horn.
When the standard scan is equivocal. For a suspected Wrisberg variant or a complex tear, MR arthrography or a repeat MRI looks for anterior translation of the posterior horn and an absent posterior tibial attachment. It confirms the instability subtype and guides the need for stabilisation.
Management Algorithm
Two questions decide the pathway: is the child symptomatic, and is the peripheral rim attached. An incidental discoid meniscus is observed; a symptomatic stable one is reshaped; an unstable one is reshaped and stabilised.
Observe. Most discoid menisci found incidentally never need surgery, and an asymptomatic disc does not need prophylactic surgery. At the first visit reassure the parents and child that incidental discoid menisci are common, avoid restricting sport unless symptoms develop, and encourage normal activity, and document the baseline examination, imaging and counselling. Give return precautions: snapping, locking, pain, swelling or a limp.
Follow-up. Reassess symptoms and function at 6-12 months, with no imaging unless there are new symptoms, and discharge if the child remains asymptomatic and the family understands the return precautions. If symptoms develop at any point, convert to the symptomatic pathway: MRI if not already recent, and arthroscopy for mechanical symptoms or persistent pain.
Total meniscectomy in a child with a discoid meniscus leads to severe, premature lateral compartment osteoarthritis - often within 15-20 years and near-universal by 20 years - and is a recognised cause of early joint replacement in young adults. Even when the meniscus is extensively torn, preserve as much peripheral vascular tissue as possible and combine saucerisation with repair. In unsalvageable cases, meniscal allograft transplantation is a salvage option in skeletally mature adolescents.
Complications
- Incidence
- 5-15 percent in paediatric series
- Risk factors
- Thin rim, vigorous sport, missed instability
- Management
- Revision repair if symptomatic; consider partial regrowth
- Incidence
- 5-10 percent after saucerisation
- Risk factors
- Wrisberg variant unrecognised, inadequate stabilisation
- Management
- Revision with stabilisation if instability confirmed
- Incidence
- 10-30 percent by 20 years
- Risk factors
- Total meniscectomy history, cartilage damage at index surgery
- Management
- Activity modification, cartilage repair, realignment if needed
- Incidence
- Less than 1 percent
- Risk factors
- Posterior horn repair, deep suture passage
- Management
- Careful technique, neurolysis if exposed
- Incidence
- 2-5 percent
- Risk factors
- Prolonged protected rehab, immature patients
- Management
- Aggressive physiotherapy, MUA if persistent
- Incidence
- 10-20 percent in children
- Risk factors
- Higher than adult meniscal surgery
- Management
- Plan for second look if symptoms recur
Associated osteochondritis dissecans. A discoid lateral meniscus is a recognised association of osteochondritis dissecans of the lateral femoral condyle, in contrast to the more common medial-side OCD of the non-discoid knee; the abnormal thickness, poor load distribution and altered contact mechanics of the disc are thought to predispose the underlying condyle to a subchondral lesion. An unrecognised lesion changes the operation, because it may need drilling, fixation or grafting at the same arthroscopy, and its presence worsens the long-term prognosis. Scrutinise the lateral femoral condyle on the pre-operative MRI, and inspect it arthroscopically once the central disc has been saucerised and the condyle is exposed: the lesion is hidden until you lift the disc.
Outcomes and Prognosis
- Treatment
- Saucerisation only
- Expected outcome
- 80-90 percent symptom resolution
- Long-term function
- Good sport return, low reoperation
- Treatment
- Saucerisation + repair
- Expected outcome
- 70-85 percent good outcome
- Long-term function
- Good if instability addressed; better than resection alone
- Treatment
- Saucerisation + repair
- Expected outcome
- 75-90 percent good outcome
- Long-term function
- Good if repair heals; revision possible
- Treatment
- Saucerisation + repair / partial
- Expected outcome
- 60-80 percent good outcome
- Long-term function
- Variable; higher reoperation rate
What predicts a good result. A stable Watanabe I or II meniscus with an isolated central disc, healthy articular cartilage, a motivated child and family, and a single-stage saucerisation.
What predicts a poor one. A Wrisberg variant missed at the index surgery, pre-existing cartilage damage, an unsalvageable circumferential tear, low-compliance rehabilitation, and a return to high-demand pivoting sport before adequate healing. The threshold that matters most is recognising and stabilising the Wrisberg variant at the first operation: missing instability is the commonest cause of reoperation and persistent symptoms.
Guidelines, Registries & Global Practice
- 3-5 percent incidence in Western populations; up to 13-17 percent in East Asian cohorts
- Lateral dominates in Western series; medial discoid is more common in East Asian series
- Bilateral in 15-25 percent of cases - image the contralateral knee when one is identified
- Common age of presentation 5-15 years; symptomatic cases are often sports-related
- Sex: Slight male predominance in most published series
- High-resource: Arthroscopy with rim-preserving saucerisation is the standard; MRI is widely available for diagnosis and planning
- Limited-resource: Clinical diagnosis with X-ray may be the only option; open meniscectomy has been used historically but accelerates OA
- Universal principle: Preserve as much peripheral meniscal tissue as possible; the operation can be done with standard arthroscopy equipment
- Rehabilitation: Hinged bracing and physiotherapy protocols are similar across centres
- Diagnosis emphasis
- Snapping knee in a child, MRI bow-tie greater than 3 slices
- Surgical principle
- Saucerisation preserving 6-8 mm peripheral rim; repair if unstable
- Special notes
- Counsels families on higher reoperation rate than adults
- Diagnosis emphasis
- Watanabe and Ahn classifications, MRI for unstable subtypes
- Surgical principle
- Rim-preserving saucerisation, repair for Wrisberg or peripheral tear
- Special notes
- Strong evidence against total meniscectomy in children
- Diagnosis emphasis
- MRI criteria, classify instability under anaesthesia
- Surgical principle
- Saucerisation with or without repair based on stability
- Special notes
- Return-to-sport criteria based on stability and rehab progression
- Diagnosis emphasis
- Higher prevalence in East Asian cohorts, medial variant more common
- Surgical principle
- Saucerisation principles the same; technical adaptations for medial variant
- Special notes
- Greater emphasis on medial discoid meniscus compared with Western practice
There is no dedicated meniscal registry analogous to the arthroplasty registries. Evidence for discoid meniscus management is dominated by retrospective case series and operative technique descriptions; randomised trials are not feasible because of low incidence and varied subtypes. Major arthroplasty registries (NJR, AJRR, AOANJRR) inform the long-term OA risk of total meniscectomy, which is the primary reason to preserve the rim in children.
Record in every discoid meniscus case:
- Watanabe and Ahn subtype; whether stable or unstable
- Peripheral rim width at end of procedure (6-8 mm target)
- Whether repair was performed; number of sutures; technique
- Status of articular cartilage at index procedure
- Post-operative plan: weight-bearing status, brace, physiotherapy, return-to-sport timeline
A missed Wrisberg variant and a total meniscectomy in a child are recognised sources of complaint and medico-legal claim worldwide. Document instability testing and rim preservation carefully.
Controversies & Areas of Uncertainty
Some authors argue that all complete discoid menisci should be reshaped prophylactically to prevent future tearing and chondral damage. Others observe asymptomatic discoid menisci because the natural history is often benign. There is no level 1 evidence; decisions are typically based on morphology, age, and family preference.
The classic teaching is 6-8 mm of peripheral rim, but the precise minimum is not defined by high-quality trials. Biomechanical studies suggest leaving as much vascularised tissue as possible; some surgeons preserve the entire peripheral zone and resect only degenerate central tissue. Long-term cartilage outcomes are rarely reported.
Inside-out, outside-in, and all-inside techniques all have proponents. Inside-out provides a strong, reliable repair but requires a posterolateral incision and risks peroneal nerve injury. All-inside is faster and avoids the incision but is more expensive and may have lower load to failure in some studies. Choice is often surgeon preference.
Meniscal allograft transplantation is a salvage option in skeletally mature adolescents with unsalvageable discoid menisci or post-meniscectomy syndrome. Outcomes are favourable in selected patients, but the procedure is technically demanding, requires careful sizing, and is not universally available. Long-term outcome data in children are limited.
MCQ Practice Points
Q: What embryological event produces a discoid meniscus? A: The traditional answer is failure of central resorption of the mesenchymal meniscal disc in the fetal knee (around weeks 8-14 of gestation), leaving a disc-shaped meniscus that covers most or all of the tibial plateau. Fetal morphometry does not support it: no discoid stage or resorption phase has been demonstrated, and the lateral meniscus is normally the larger, earlier-maturing and more variable of the two.
Q: Which Watanabe type is inherently unstable and which is the most common? A: Watanabe III (Wrisberg type) is the only inherently unstable type - it lacks a posterior tibial attachment and is restrained only by the Wrisberg meniscofemoral ligament. Watanabe I (complete) is the most common morphological type. Ahn classification adds instability subtypes (3 and 4) that help guide treatment.
Q: What is the most reliable MRI criterion for a discoid meniscus? A: 3 or more consecutive sagittal slices showing a continuous meniscal bow-tie. A normal meniscus shows a bow-tie on only 2 consecutive slices. Coronal coverage of greater than 50 percent of the tibial plateau is supportive. Anterior translation of the posterior horn suggests the Wrisberg variant.
Q: What is the principle of arthroscopic saucerisation and what rim width should be left? A: Reshape the central disc to a normal crescent, leaving a 6-8 mm peripheral rim of stable meniscal tissue. Aim for a wider anterior horn tapering to a thinner posterior horn. Total meniscectomy is contraindicated in children because of premature lateral compartment osteoarthritis. Wrisberg variants require additional stabilisation / repair.
Q: When is stabilisation required in addition to saucerisation? A: Wrisberg variant (Ahn 3) and any peripheral tear (Ahn 2 or 4) require stabilisation. Reshaping alone leaves the meniscus hypermobile and symptoms will persist. Techniques include inside-out, outside-in, and all-inside suture repair of the posterior horn to the tibial footprint.
Q: What is the most important long-term complication of total meniscectomy in a child? A: Premature lateral compartment osteoarthritis, often severe and visible on radiographs within 15-20 years. This is why total meniscectomy is contraindicated in children, and meniscal allograft transplantation may be considered as a salvage option in skeletally mature adolescents.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 9-year-old boy is brought in by his parents because they can hear his right knee clicking when he walks. The clicking has been present for several months, is occasionally painful, and he has begun to limp after football. Examination shows a small effusion, a palpable clunk at the lateral joint line as the knee flexes and extends, and full range of motion. What is the most likely diagnosis, what investigation would you arrange, and what would you tell the parents?”
“A 12-year-old girl had an arthroscopic saucerisation of a discoid lateral meniscus 6 months ago. Her snapping and locking have improved, but she continues to have lateral pain and gives way when pivoting. Examination shows mild effusion, lateral joint line tenderness, and the knee is stable to Lachman and pivot shift. Repeat MRI shows a well-reshaped meniscus, no re-tear, but the posterior horn appears anteriorly translated relative to the original tibial footprint. What has likely been missed, and how would you manage it?”
Key Anatomy and Pathology
- Traditional 'failure of central resorption' account is not supported by fetal morphometry - the lateral meniscus is normally the larger and more variable side
- Lateral much more common than medial in Western populations (reversed in East Asian)
- Often bilateral (15-25 percent); image the contralateral knee
- Wrisberg variant has no posterior tibial attachment - inherently unstable
Watanabe and Ahn Classification
- Watanabe I (complete): disc covers entire plateau, stable
- Watanabe II (incomplete): broader than normal semilunar, stable
- Watanabe III (Wrisberg): no posterior tibial attachment, unstable
- Ahn adds instability subtypes 2 (peripheral tear), 3 (Wrisberg), 4 (circumferential tear)
Clinical Presentation and Diagnosis
- Snapping / clicking / locking lateral knee in a child aged 5-15
- Intermittent pain, effusion, limp; sport-related in many cases
- MRI: 3 or more consecutive sagittal bow-tie slices is diagnostic
- Coronal coverage greater than 50 percent and anteriorly translated posterior horn are supportive
Treatment Algorithm
- Asymptomatic incidental finding: observe, return precautions
- Symptomatic stable: arthroscopic saucerisation, 6-8 mm peripheral rim
- Unstable / Wrisberg: saucerisation + posterior horn reattachment
- Avoid total meniscectomy in children - rim preservation is mandatory
Surgical Pearls
- Probe the posterior horn before and after reshaping - instability must be addressed
- Inside-out sutures are the workhorse for posterior horn reattachment
- Document rim width, stability, cartilage status at end of procedure
- Hinged brace and protected weight-bearing after repair
Complications and Outcomes
- Re-tear 5-15 percent; higher if instability missed
- Persistent symptoms in Wrisberg variant unrecognised at first operation
- Premature lateral compartment OA after total meniscectomy is the worst outcome
- Saucerisation + repair gives 70-90 percent good outcomes at mid-term follow-up
Evidence Base and Key Trials
Development of the Meniscus of the Knee Joint in Human Fetuses
- 41 human fetuses from 14 to 30 weeks of gestation compared morphometrically with 14 adults, measuring meniscal area against tibial plateau area
- The proportion of plateau covered by meniscus was CONTINUOUSLY greater on the lateral side than the medial - at every fetal stage and in adults
- The layered collagen fibre structure matured earlier in the lateral meniscus than in the medial
- No discoid stage was observed in normal development, and no central resorption phase was demonstrated
- The authors attribute discoid morphology to this differential lateral-versus-medial development rather than to a retained fetal disc
Arthroscopic treatment of the discoid lateral meniscus. Technique and long-term results
- 45 patients (49 knees) with torn complete or incomplete discoid lateral menisci treated 1968-1980; 24 knees followed for a mean of 4 years 3 months
- Results by the grading scale this paper introduced - the Ikeuchi grade, still used by every later series: 78% excellent or good, 21% fair, none poor
- READ THE TECHNIQUE CAREFULLY: this was arthroscopic COMPLETE EXCISION of the torn discoid meniscus, refined so that the anterior portion is removed first to improve visualisation and working space
- And the comparison went the way modern practice does not: results after TOTAL meniscectomy were BETTER than after partial meniscectomy in this series
- Three knees had peripheral meniscal repair under arthroscopic control, with long-term results not yet available
Congenital discoid lateral meniscus in children. A follow-up study and evolution of management
- 52 children with 62 discoid lateral menisci, mean age at operation 10.5 years, mean follow-up 5.5 years
- THE DIAGNOSTIC POINT: symptoms were vague and intermittent in most, and the classical clunk was demonstrable in only 39% of knees. The mean delay to diagnosis was 24 months
- Associated osteochondritis dissecans of the lateral femoral condyle in 7 knees - look for it, because the discoid meniscus is not always the only lesion
- 8 knees with intact, asymptomatic discoid menisci were left alone - the incidental discoid is not an operative indication
- Outcomes by Ikeuchi grade: 37% excellent, 47% good, 16% fair, none poor
- Note the era: 48 knees had OPEN TOTAL lateral meniscectomy and only 6 had arthroscopic partial resection, and the authors recommended total meniscectomy for the Wrisberg type with posterior instability
Discoid lateral meniscus: prevalence of peripheral rim instability
- 112 patients (128 knees), mean age 10.0 years, arthroscopically evaluated 1993-2001 - the series that quantified peripheral rim instability
- Of 87 menisci classified at arthroscopy, 62.1% were complete and 37.9% incomplete; an associated tear was present in 69.5% of all knees
- Peripheral rim instability in 28.1% overall
- AND THE LOCATION OVERTURNS THE CLASSICAL TEACHING: of the unstable menisci, 47.2% were unstable at the ANTERIOR third, 38.9% at the posterior third and 11.1% at the middle third. Anterior instability was the commonest, not the posterior Wrisberg pattern
- Instability was significantly commoner in COMPLETE discoid menisci (38.9% vs 18.2%, P = 0.043) and in YOUNGER children (mean 8.2 vs 10.7 years, P = 0.002)
- 31 of the 36 unstable menisci had the peripheral rim attachment repaired