Diathermy Principles & Safety
- Diathermy passes high-frequency alternating current through tissue and generates heat where the current density is high
- A continuous waveform cuts (vaporises); an interrupted waveform coagulates (desiccates); fulguration chars a surface; blend combines cutting with haemostasis
- Monopolar sends current through the patient to a large return electrode; bipolar confines it between the forceps tips and needs no return electrode
- Bipolar is safer near nerves, implants, pacemakers and in digits, but coagulates only a small volume
- Return electrode over well-perfused muscle near the site and never cut down for a child; guard against alternative-site burns, pacemaker/ICD interference, surgical fire and surgical smoke
- The harmonic scalpel is ultrasonic, not bipolar cautery
- About 58% of surveyed surgeons scored unsafe on electrosurgery: a measure of knowledge, not of harm
- “Radiofrequency (about 300 kHz to several MHz) heats without stimulating; at mains 50/60 Hz the current would stimulate nerve and muscle
- “About 60°C coagulates; about 100°C vaporises and cuts
- “Least lateral thermal spread: ultrasonic and advanced bipolar. Most: monopolar
Principles: Frequency, Heat and Waveform
Electrosurgery, or diathermy, passes a high-frequency (radiofrequency) alternating current through tissue and generates heat where the current density is high.
Why the frequency is high. Diathermy runs at about 300 kHz to several MHz, deliberately above the roughly 100 kHz ceiling of neuromuscular and cardiac excitability. At mains frequency (50/60 Hz) the current would stimulate nerve and muscle, the Faradic effect: electrocution and arrhythmia. At radiofrequency the cell membranes cannot depolarise fast enough to follow the current, so it heats tissue without stimulating it.
How the heat is made. The heating is resistive (Joule) heating, proportional to the square of the current density. It therefore concentrates at the small active electrode, where the high density produces intense local heat, and is negligible at the large dispersive pad, where the density is low.
The temperature thresholds. At around 60°C proteins denature and vessels seal, which is coagulation. At around 100°C intracellular water boils and cells explode, which is vaporisation, or cutting. Higher still, tissue chars (fulguration and eschar).
The waveform. The effect depends on the waveform. A continuous waveform cuts by vaporising cells, and an interrupted (damped) waveform coagulates by desiccating and sealing. Fulguration sprays current to char a surface, and blend combines cutting with haemostasis.
Monopolar and Bipolar Diathermy
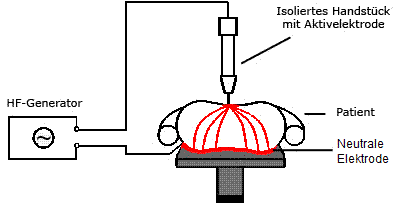
Monopolar. Current flows from a small active electrode through the patient to a large return (dispersive, or 'plate') electrode. The density is high at the small tip, where the surgical effect occurs, and low at the large pad, so the pad does not burn. Monopolar is versatile, cutting and coagulating with a wide effect, but it depends on correct return-electrode application and carries the risks of current passing through the body.
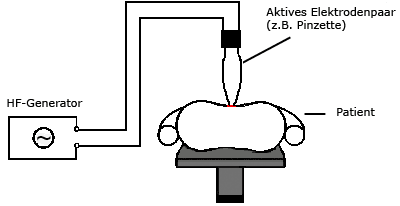
Bipolar. Current passes only between the two tips of the forceps, so no return electrode is needed and no current passes through the rest of the patient. That makes bipolar safer near nerves, near or on implants, in patients with pacemakers, and in digits and other appendages with an end-arterial supply, where monopolar was traditionally avoided (the historic teaching was against monopolar on a digit or the penis). The price is that it coagulates only a small volume.
Safety in Theatre
The return electrode. In monopolar surgery the return electrode is not optional. The dispersive pad must be correctly sized and applied over well-perfused muscle close to the operative site, and poor contact causes a pad-site burn.
Reducing the pad's surface area raises the current density at the pad and risks a pad-site burn. Nearly half of the surgeons in the survey described below said they would do it.
Alternative-site burns. Current diversion can burn the patient away from the pad, at ECG electrodes or other skin contact points, so contact points are kept to a minimum.
Pacemakers and defibrillators. Monopolar diathermy can interfere with cardiac implantable devices, causing inhibition or inappropriate shocks. Bipolar is preferred where possible, bursts are kept short, the return electrode is positioned so the current path avoids the device, and the device team is involved, with a magnet or programming as advised.
Surgical fire. The fire triad is an oxidiser (oxygen), a fuel (drapes, alcohol skin preparation) and an ignition source (the diathermy). Alcohol prep is allowed to dry, oxygen is managed, and the team should know how to handle an operating-room fire.
Fire in limb surgery. Alcohol-based preparation runs downwards and pools beneath a limb, under drapes and beneath a tourniquet cuff, where it neither evaporates nor is visible. The fuel side of the triad is therefore a limb-surgery problem as much as an airway one: the prep must be allowed to dry and pooled fluid removed before the diathermy is switched on.
The current path in a limb. The return electrode should sit so the path does not run along the operated limb through a tourniquet or across a metallic implant, since current concentrating at a small metal contact raises local current density. Around a nerve, an existing prosthesis or a digit, bipolar is the sensible default, because the confined current path removes the question entirely.
Surgical smoke. Smoke is a respiratory and biological hazard and requires smoke evacuation. The related perioperative pages are tourniquet use and surgical site infection prevention.
The measured gap. In one survey, about 58% of surgeons scored at an unsafe level of understanding of electrosurgical devices. The failures were consistent enough to predict both the theatre error and the exam question:
- Most believed the harmonic scalpel was a form of bipolar cautery
- A majority did not know how to handle an operating-room fire
- Other gaps were the correct current mode for coagulating a vessel and where to place the dispersive electrode
This is a single questionnaire study of knowledge, not a measure of how often patients are actually harmed. No study quantifies the incidence of diathermy burns or surgical fires in orthopaedic practice, so no such rate is given here. The survey is why structured training such as the Fundamental Use of Surgical Energy (FUSE) programme is advocated.
Other Energy Devices and Thermal Spread
The ultrasonic (harmonic) scalpel. The harmonic scalpel is an ultrasonic device, not a form of bipolar electrocautery. A piezoelectric transducer vibrates the blade at about 55 kHz: the vibration cuts, and the mechanical friction generates heat that denatures protein and coagulates, so it cuts and coagulates simultaneously, and the coagulation is not electrical. It works at a lower temperature than diathermy, with little lateral thermal spread and no electrical current through the patient, which makes it safe near pacemakers, and it seals vessels up to about 5 mm. Confusing it with bipolar cautery leads to wrong assumptions about safety near pacemakers and implants.
Advanced bipolar vessel sealers. Devices such as LigaSure combine feedback-controlled bipolar radiofrequency with pressure to fuse the collagen and elastin of the vessel wall into a permanent seal, in vessels up to about 7 mm. The generator senses tissue impedance and stops when the seal is complete, which limits thermal spread.
Thermal spread. Ultrasonic and advanced bipolar devices have the least lateral thermal spread and are the safest near nerves; monopolar has the most.
Ablation. Radiofrequency ablation (RFA) and microwave ablation differ in mechanism, and instead destroy a target, such as a tumour or some bone lesions, by heat.
Mnemonics & Memory Aids
DIATHERMY
Hook:DIATHERMY: Density, Interrupted=coag, Alternative-site burns, Two types (mono/bipolar), Harmonic=ultrasonic, Electrode (return), Rhythm devices, Make no fire/smoke, You need training.
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“What is the difference between monopolar and bipolar diathermy, and what are the key safety issues?”
Principles
- High-frequency AC → heat at high current density
- Cut = continuous waveform (vaporise); coagulation = interrupted (desiccate)
- Fulguration = spray/char; blend = cut + haemostasis
Monopolar vs bipolar
- Monopolar: active tip → through patient → large return (dispersive) electrode
- Bipolar: current only between forceps tips; no return electrode
- Bipolar safer near nerves/implants/pacemakers and in digits (small effect only)
Safety
- Return electrode over well-perfused muscle; never cut down for a child
- Alternative-site burns; pacemaker/ICD precautions (prefer bipolar, short bursts)
- Surgical fire triad (oxidiser+fuel+ignition); alcohol prep POOLS under a limb/tourniquet - let it dry
- Route the return so the current path avoids the tourniquet and any metallic implant
- Surgical-smoke evacuation
Other devices / gaps
- Harmonic scalpel = ultrasonic (NOT bipolar cautery)
- Advanced bipolar vessel sealers; RFA and microwave ablation differ in mechanism
- ~58% of surveyed surgeons scored unsafe; ~half would cut a child's pad; most thought harmonic was bipolar → FUSE training
Evidence & Key Studies
Lack of awareness among surgeons regarding safe use of electrosurgery
- In a survey of surgeons, the majority (about 58%) had an unsafe level of understanding of electrosurgical devices; common gaps included the correct mode of current for coagulating vessels, correct placement of the dispersive (return) electrode, and identifying a safe device in patients with a pacemaker.
- Nearly half would inappropriately cut a dispersive electrode to fit a child, and most incorrectly believed the harmonic scalpel was a form of bipolar cautery; a majority did not know how to handle an operating-room fire.
- The findings highlight a high level of ignorance regarding basic electrosurgical equipment and the need for raising awareness and structured training (e.g. surgical-energy curricula).
The evidence that many surgeons have an unsafe understanding of electrosurgery - the 58 percent figure, and the specific gaps in the correct coagulation mode, dispersive (return) electrode placement, the error of cutting the dispersive electrode for a child, identifying pacemaker-safe devices, recognising that the harmonic scalpel is not bipolar cautery, and managing an operating-room fire - comes from the cited Malik survey. The underlying physics (high-frequency AC, cut vs coagulation waveforms), the monopolar/bipolar distinction, alternative-site burns, the fire triad, surgical-smoke hazards, and the ultrasonic mechanism of the harmonic scalpel and the nature of RF/ microwave devices are standard, well-established teaching (formalised in surgical-energy curricula such as FUSE). That survey measured knowledge, not harm: it does not establish how often burns or fires actually occur, and no study gives an incidence of diathermy burns, alternative-site burns or surgical fires specific to orthopaedic surgery, so no such figure is quoted. Nor is there a randomised comparison showing that any one energy device reduces blood loss, operating time or complications in orthopaedic procedures.