Volar-Radial Wrist Tendinopathy
- The FCR runs in its own tight fibro-osseous tunnel against the trapezial ridge and scaphoid tuberosity, beside the trapeziometacarpal and STT joints
- Volar-radial pain and tenderness over the tendon at and just proximal to the wrist crease, worse on resisted flexion and radial deviation
- Usually a degenerative overuse tendinopathy, frequently driven by or accompanied by basal-thumb or STT osteoarthritis
- After the APL hammock suspension arthroplasty a third developed FCR tendinopathy and about a fifth ruptured, every rupture within six months (21 hands)
- Non-operative first; tunnel release and debridement if refractory
- “APL hammock series: tendinopathy 33.3% (7/21), tendinitis 14.3%, rupture 19.0%
- “Manual workers 50% vs 18.2% (OR 4.5) but not significant at n=21 (p=0.18)
- “Post-arthroplasty tendinitis settled with NSAIDs and bracing; all four ruptures needed surgery
- “The FCR inserts on the second (and third) metacarpal base, not the pisiform, which is flexor carpi ulnaris
Anatomy of the FCR Tunnel
Its own canal. The FCR does not run in the carpal tunnel. It has its own fibro-osseous canal, the "FCR tunnel": a groove in the trapezium roofed by a fibrous septum, a split of the flexor retinaculum that attaches to the trapezial ridge and the scaphoid, which separates it from the carpal tunnel contents.
A tight fit with a bend in it. The tendon occupies most of the canal and angulates about 30 degrees around the trapezial ridge before it inserts, which concentrates friction and compression there. Its course runs against the trapezial ridge and the scaphoid tuberosity, immediately adjacent to the trapeziometacarpal and scaphotrapeziotrapezoid (STT) joints. That confined course makes it prone to friction tendinopathy and explains its close association with basal-thumb and STT arthritis.
Insertion and action. The FCR inserts primarily on the base of the second metacarpal, with slips to the third metacarpal base and the trapezial tubercle. It does not insert on the pisiform; that is flexor carpi ulnaris. It flexes and radially deviates the wrist and assists pronation, which is why resisted flexion and radial deviation provoke the pain.
Surgical relations. The neurovascular neighbours are what matter at operation.
- The radial artery lies just radial to the FCR, a useful landmark
- The palmar cutaneous branch of the median nerve runs between FCR and palmaris longus, and is at risk in a volar (FCR) approach
- The median nerve is ulnar and deep
- The superficial radial nerve is dorsal
Pathology: Tendinopathy, Attrition and Rupture
Tendinopathy. FCR tendinitis is usually a degenerative overuse tendinopathy rather than a true acute inflammation. Overuse and repetitive loading provoke it, and it may follow local trauma.
Attrition from the joints next door. Osteophytes from STT and trapeziometacarpal osteoarthritis, and the trapezial ridge itself, project into the tight canal and mechanically abrade the gliding tendon. The result is chronic attrition tendinopathy and, ultimately, attritional rupture. It is directly analogous to the extensor attrition ruptures, EPL over Lister's tubercle or the extensors over the caput ulnae in the Vaughan-Jackson pattern, except that here the FCR frays over trapezial and STT osteophytes.
Causes of rupture.
- Attrition over STT or trapezial osteophytes: spontaneous, in basal-thumb OA, and rare
- A complication of trapeziometacarpal suspension arthroplasty, the abductor pollicis longus "hammock" wrap
- Rarely, acute laceration or trauma
After suspension arthroplasty. FCR tendinopathy, and even rupture, is a recognised complication of trapeziometacarpal suspension arthroplasty, in which tissue is wrapped around the FCR for suspension. After the APL hammock procedure it is common rather than merely recognised. In the Nakai series of 21 hands followed for more than a year, a third developed FCR tendinopathy (7 of 21, 33.3%): tendinitis in 3 (14.3%) and frank rupture in 4 (19.0%).
How far to trust those numbers. With 21 hands, each rupture moves the figure by about 5 percentage points, so the percentages carry wide uncertainty, and they apply to the APL-around-FCR technique rather than to suspension arthroplasty in general. Manual workers had tendinopathy in 50% against 18.2% of non-manual workers, an odds ratio of 4.5, but this did not reach statistical significance (p=0.18). It is a reasonable basis for counselling and postoperative restriction, not an established risk factor.
Presentation and Differential
Symptoms and signs. Volar-radial wrist pain, with tenderness over the FCR tendon at and just proximal to the wrist crease, where the tendon enters its tunnel. The pain is worse on resisted wrist flexion and radial deviation and on direct palpation of the tendon.
Look next door. Because the FCR runs right beside the trapeziometacarpal and STT joints, volar-radial wrist pain attributed to the tendon is frequently driven by, or accompanied by, basal-thumb or STT osteoarthritis. The differential must be worked through and the source localised by examination and imaging.
- Where / sign
- Over the FCR tendon, volar-radial, at the crease
- Discriminator
- Pain on resisted flexion + radial deviation; tender over FCR
- Where / sign
- First dorsal compartment, dorso-radial
- Discriminator
- Positive Finkelstein; APL/EPB tendons
- Where / sign
- Base of thumb / CMC joint
- Discriminator
- Positive grind test; radiographic CMC arthritis
- Where / sign
- Distal scaphoid / trapezium-trapezoid
- Discriminator
- Radiographic STT joint narrowing; tender STT
- Where / sign
- Anatomical snuffbox / scaphoid
- Discriminator
- Snuffbox tenderness; scaphoid imaging
Radial-sided wrist ganglia complete the list. The neighbouring diagnoses have their own pages: the joint that most often drives the pain attributed to this tendon, and whose surgery generates the complication above, is thumb carpometacarpal arthritis; the dorso-radial mimic with the positive Finkelstein test is de Quervain's tenosynovitis.
Investigations
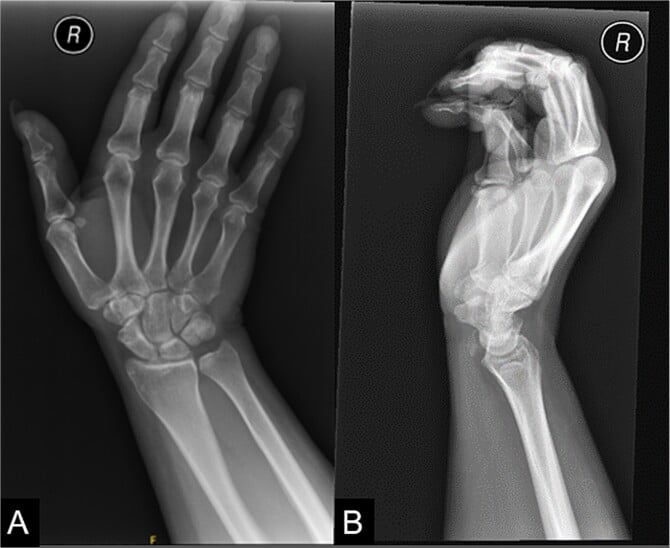
Radiographs, including a basal-thumb/STT view, assess the adjacent joints for osteoarthritis. They can also show calcific tendinosis at the FCR, a recognised cause of FCR-region wrist pain that typically resolves with conservative treatment.
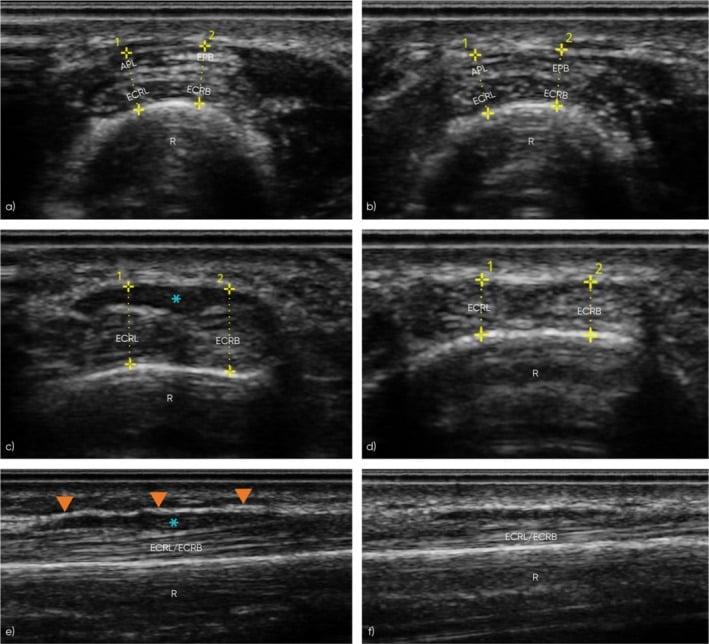
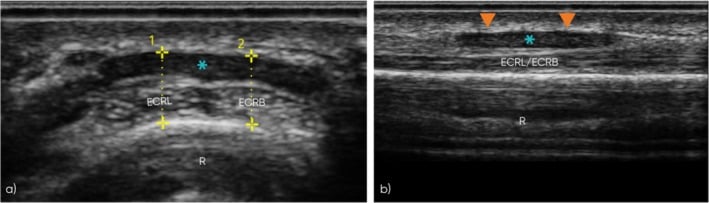
Ultrasound or MRI characterises the tendon itself: tendinopathy, tenosynovitis, partial tear or rupture.
Diagnostic injection. Examination, radiographs and, if needed, an injection into the FCR sheath localise the source. The injection can both confirm the source and treat it.
Management
Non-operative first. Activity modification or rest, a wrist splint (sometimes including the thumb), non-steroidal anti-inflammatories and physiotherapy, with a corticosteroid injection into the FCR tunnel or sheath for refractory symptoms. This is effective for most FCR tendinitis.
Treat the joint as well as the tendon. Do not treat the FCR in isolation. Where basal-thumb or STT osteoarthritis coexists, address it as indicated, including at the time of tunnel release.
Surgery for refractory symptoms. Release or decompression of the FCR fibro-osseous tunnel, with debridement of the diseased tendon.
Rupture. Flexor carpi ulnaris and palmaris longus provide most wrist flexion, so an isolated FCR rupture is frequently well tolerated, and a spontaneous rupture in a low-demand patient may be managed conservatively. A rupture after suspension arthroplasty, which destabilises the reconstruction, and a symptomatic or high-demand rupture require surgery. In the Nakai series all four ruptures did.
New or persistent FCR symptoms after basal-thumb surgery should be taken seriously. After an APL hammock arthroplasty every rupture occurred within six months, often after a wrist-stressing activity, so restrict wrist-stressing activity through that window and review actively through the first postoperative year rather than waiting for the patient to report. The tendinitis settled with anti-inflammatories and bracing in every case.
Mnemonics & Memory Aids
FCR
Hook:FCR: Fibro-osseous tunnel (flexion+radial deviation pain), Check the neighbours (TMC/STT OA, arthroplasty complication), Rest first / Release if refractory.
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“A patient has volar-radial wrist pain over the FCR tendon. How do you assess and manage it?”
Presentation
- Volar-radial wrist pain over the FCR at/just proximal to the wrist crease
- Worse on resisted wrist flexion and radial deviation; tender over the tendon
- FCR runs in a tight tunnel against the trapezial ridge/scaphoid
Associations & differential
- Basal-thumb (trapeziometacarpal) and STT osteoarthritis (adjacent joints)
- After APL hammock arthroplasty: tendinopathy 33.3%, tendinitis 14.3%, RUPTURE 19.0% - all ruptures within 6 months (n=21)
- Differential: de Quervain's (dorso-radial, Finkelstein), scaphoid pathology
Management
- Non-operative first: rest/splint, NSAIDs, physiotherapy, FCR-sheath injection
- Treat coexisting basal-thumb/STT arthritis
- Refractory: FCR tunnel release + debridement; rupture = surgery
Evidence & Key Studies
Flexor carpi radialis tendinopathy after suspension arthroplasty for trapeziometacarpal arthritis
- Retrospective study of 21 hands in 21 patients undergoing the hammock procedure - wrapping the abductor pollicis longus around the FCR - for primary trapeziometacarpal arthritis, with more than one year of follow-up.
- FCR tendinopathy occurred in 7 patients (33.3 percent): tendinitis in 3 (14.3 percent) and tendon rupture in 4 (19.0 percent). Conservative treatment with non-steroidal anti-inflammatories and bracing was effective for the tendinitis; all ruptures required surgery.
- All ruptures occurred within 6 months, often after wrist-stressing activity. Manual workers had a higher incidence (50 versus 18.2 percent, odds ratio 4.5) but this did not reach significance (p=0.1818) in a cohort of 21 - so occupation is a plausible rather than an established risk factor, and the whole rate is specific to the APL hammock technique.
The occurrence of FCR tendinopathy (and rupture) as a complication of trapeziometacarpal suspension arthroplasty, the effectiveness of conservative treatment (non-steroidal anti-inflammatories and bracing) for the tendinitis, the need for surgery for rupture, and the critical first-postoperative-year window come from the cited Nakai series. The anatomy of the FCR fibro-osseous tunnel against the trapezial ridge, its association with basal-thumb/STT osteoarthritis, and the differential with de Quervain's and scaphoid pathology are standard, well-established teaching. That series is a single retrospective cohort of 21 hands, so the percentages carry wide uncertainty and apply to the APL hammock technique rather than to suspension arthroplasty generally. No study gives an incidence of primary (non-operative) FCR tendinopathy in the general population, no trial compares splinting, injection or tunnel release for it, and no threshold or interval for imaging or intervention has been validated - so none is quoted here.