Regenerating Bone, Cartilage and Tendon
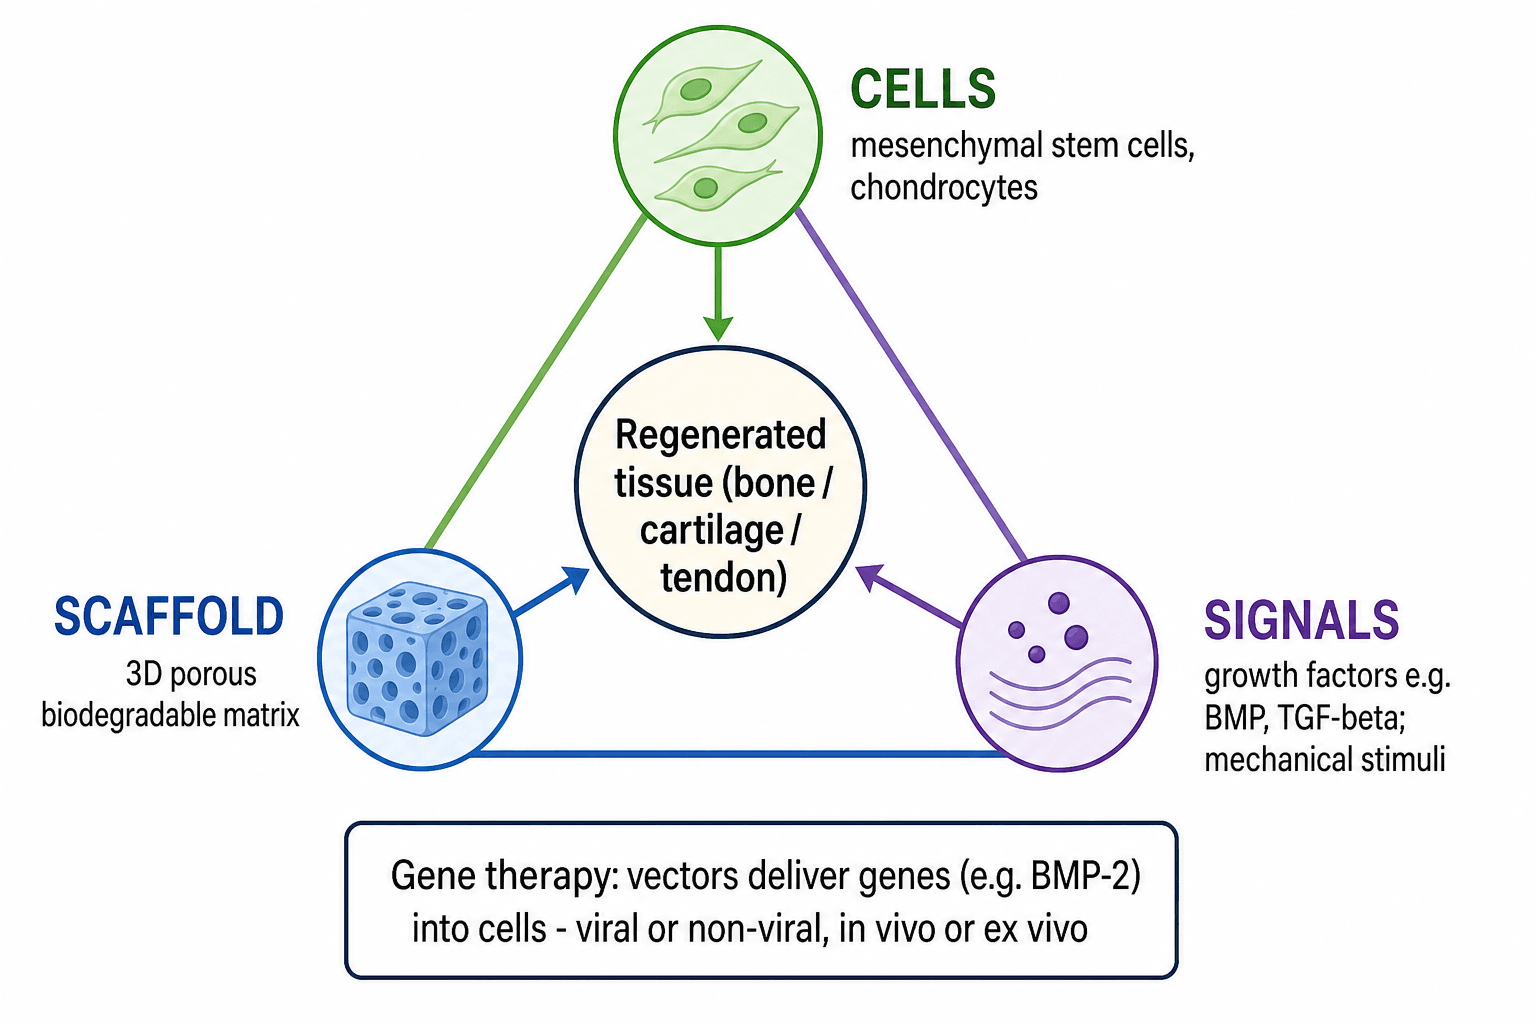
- Tissue engineering regenerates musculoskeletal tissue from a triad, the 'tissue-engineering triangle': cells, a scaffold and signals.
- Autologous chondrocyte implantation (ACI/MACI) is the established clinical example; recombinant BMP-2/BMP-7 on a collagen carrier is used in spinal fusion and tibial nonunion, as recombinant protein, not gene therapy.
- Gene therapy transfers a gene so that cells manufacture the therapeutic protein, giving more sustained local expression than a single dose of recombinant protein.
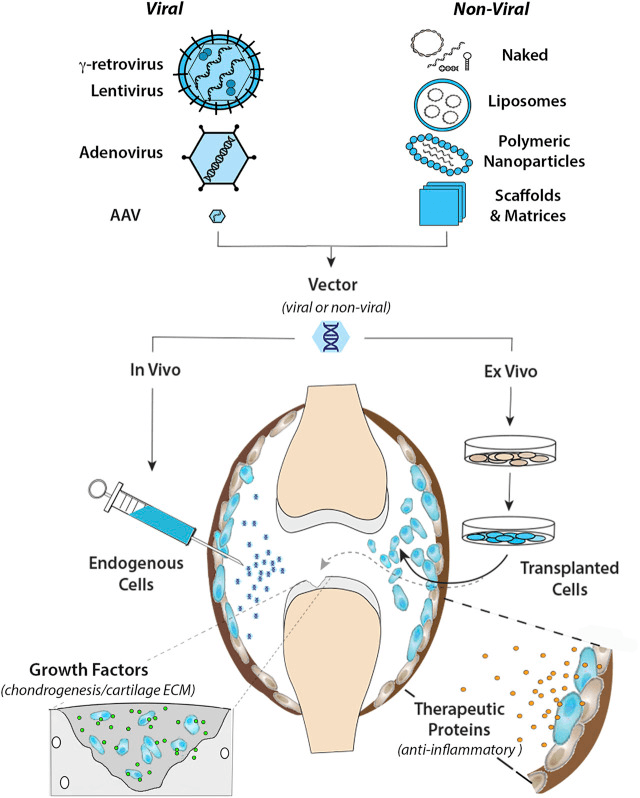
- Viral vectors are efficient but raise immunogenicity and, with integrating retro/lentiviruses, insertional mutagenesis; non-viral vectors are safer but less efficient. Delivery is in vivo (direct to the site) or ex vivo (cells modified then re-implanted, often as a gene-activated matrix).
- Vector safety, vascularisation of large constructs, the cell-scaffold-signal combination, manufacturing, cost and regulation keep most gene therapy and large-scale tissue engineering experimental.
- Regenerative orthopaedics today is a spectrum: ACI/MACI and recombinant BMP carriers in clinical use, orthobiologics (PRP, marrow concentrate) adjunctive, gene therapy and engineered whole-tissue constructs mostly investigational.
- “Tissue-engineering triad = cells (MSCs/chondrocytes) + scaffold (porous biodegradable matrix) + signals (BMP/TGF-beta, mechanical).
- “Established clinical examples: ACI/MACI (cartilage); recombinant BMP-2/7 on collagen carrier (spine fusion, tibial nonunion).
- “Gene therapy: viral (efficient, safety concerns) vs non-viral (safer, less efficient); in vivo vs ex vivo (gene-activated matrix). Mostly experimental - vector safety, vascularisation, cost.
The Tissue-Engineering Triad
Tissue engineering combines three elements to regenerate tissue, often drawn as a triangle: cells, a scaffold and signals. The mechanical environment is itself part of the recipe.
Cells. The cells provide the regenerative capacity. Most often they are mesenchymal stem cells from marrow or adipose tissue, which are multipotent and can become bone, cartilage or fat, or differentiated cells such as chondrocytes and osteoblasts.
Scaffold. A three-dimensional, porous, biodegradable matrix that supports cell attachment and guides the architecture of the new tissue, ideally osteoconductive and resorbing as the new tissue forms. It may be natural (collagen, hyaluronan, hydrogels) or a synthetic polymer or ceramic (PLGA, PCL, calcium phosphates, nanofibres).
Signals. Growth factors instruct the cells: the BMPs are osteoinductive, TGF-beta is chondrogenic, and PDGF and VEGF are others. Mechanical stimulation is part of the signal too, applied in the laboratory with bioreactors.
The hard part. Getting the right combination, and vascularising larger constructs, is the central engineering challenge. Both return below, in the scaffold design requirements and the diffusion limit.
From Bench to Clinic
The loop. A cell-based construct is made by biopsy, cell isolation, cultivation and proliferation, seeding onto a scaffold under growth factors and mechanical stimulus, and implantation.
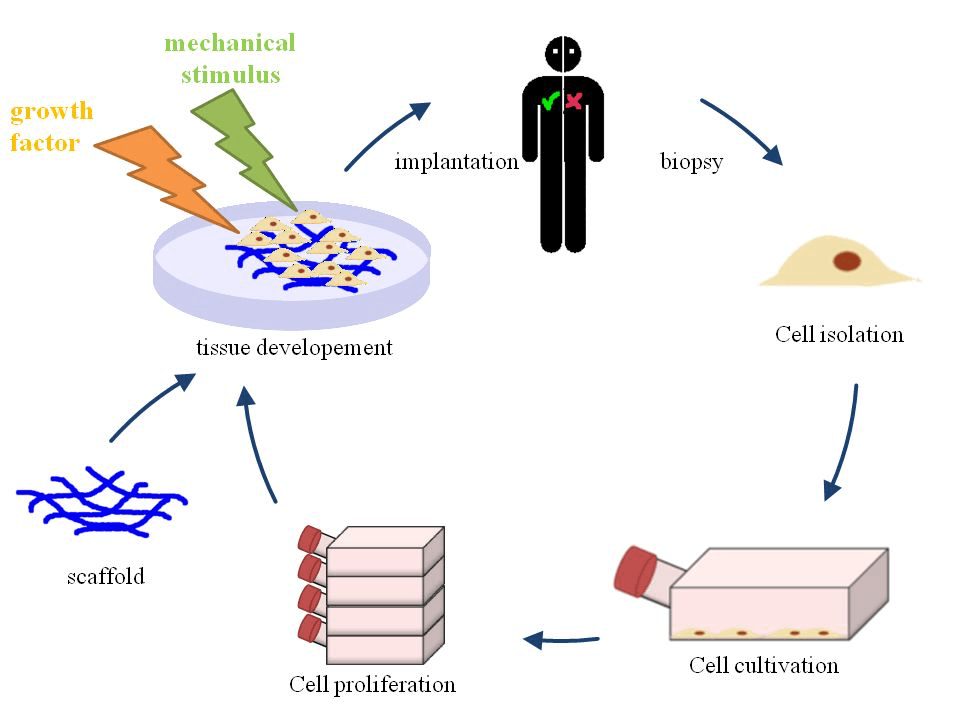
Autologous chondrocyte implantation. The established clinical example of cell-based tissue engineering. The patient's chondrocytes are harvested, expanded and re-implanted into a cartilage defect; in MACI they are seeded on a collagen membrane.
Recombinant BMP. BMP-2 and BMP-7 delivered on a collagen carrier are used clinically for spinal fusion and tibial nonunion. This is a signals-plus-scaffold approach using recombinant protein, not a gene. ACI and recombinant BMP are the clinical products of this field, and they are cell and protein therapies rather than gene therapies.
Orthobiologics. Platelet-rich plasma, bone-marrow aspirate concentrate and demineralised bone matrix are used adjunctively (see the Orthobiologics topic).
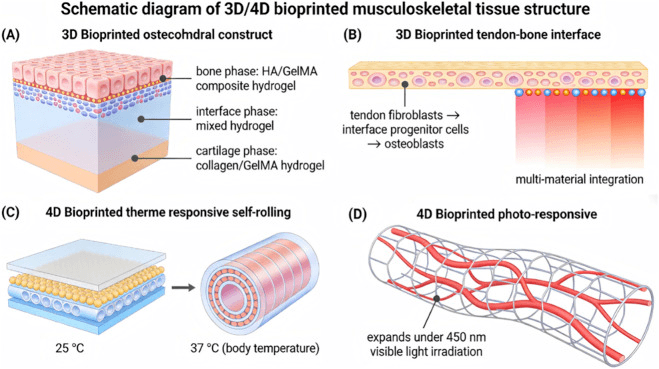
Still investigational. Engineered bone, cartilage, meniscus and tendon constructs, and gene therapy, remain largely preclinical or early-clinical. Bioprinted constructs are bench work with clinical intent: zonal, multi-material printing is how an osteochondral defect gets a matching graft.
Gene Therapy Principles
The idea. Gene therapy delivers a gene encoding a therapeutic protein into cells so that they produce the protein themselves, giving more sustained local expression than a single dose of recombinant protein. Targets include BMP-2/7 for bone, IGF-1/TGF-beta for cartilage and anti-inflammatory genes for osteoarthritis.
Why not load the protein. A protein-loaded scaffold releases a supraphysiological bolus that dissipates within days, which is the criticism levelled at high-dose rhBMP-2. A transfected cell is a dose-controlled source that keeps producing.
Vectors. The first choice is the vehicle, and it trades efficiency against safety:
- Viral (adenovirus, adeno-associated virus, lentivirus/retrovirus): efficient, but with safety concerns, namely immunogenicity and insertional mutagenesis with the integrating retro/lentiviruses
- Non-viral (plasmid DNA, lipofection): safer but less efficient
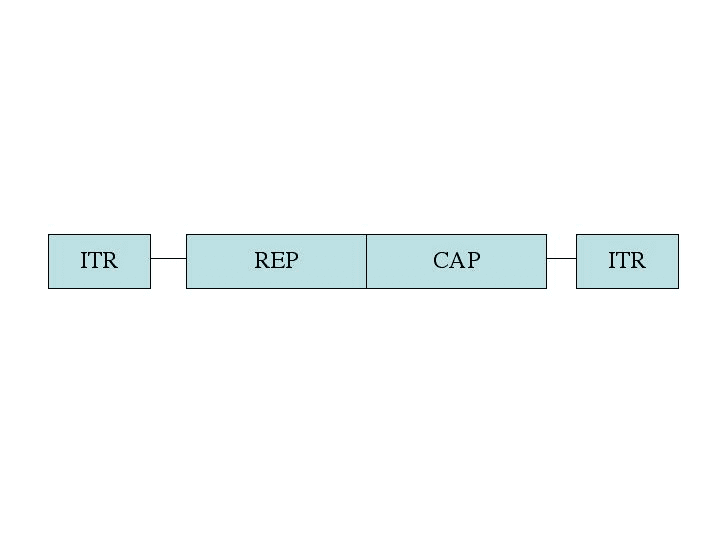
Adeno-associated virus. AAV dominates clinical gene transfer because it is replication-incompetent, weakly immunogenic and gives durable expression. Its genome is a simple cassette, Rep and Cap between two inverted terminal repeats, which makes it easy to engineer: delete Rep and Cap, keep the ITRs, and the vector carries roughly 4.7 kb of therapeutic sequence instead.
Strategy. The second choice is where the gene enters the cell. In vivo delivery applies the vector directly to the target site. Ex vivo delivery harvests the patient's cells, modifies them genetically and re-implants them, often on a scaffold as a gene-activated matrix, which allows quality control at the cost of a two-stage procedure.
The barriers. The biology is not what fails: sustained functional expression in skeletal tissue is well demonstrated. Skeletal tissues are dense matrix with few cells and little blood supply, so there is neither an easy route in nor much to transduce once there.
Translation is limited by vector safety: immune reactions to viral vectors, the risk of insertional mutagenesis with integrating vectors, and achieving controlled, sustained but not uncontrolled expression. It is limited too by the two engineering problems from the triad, selecting the right cell-scaffold-signal combination and vascularising large constructs, and by manufacturing, cost and regulatory hurdles.
Apart from ACI/MACI and recombinant BMP carriers, most gene therapy and whole-tissue engineering in orthopaedics is investigational rather than routine practice, and no gene-activated scaffold has reached clinical use. Know the principles, and describe the delivery problem rather than the list of candidate genes.
What Makes a Good Scaffold: The Design Requirements
A scaffold has to host cells, let vessels in, carry load and then get out of the way. The requirements:
- Biocompatible, with no toxic or excessive immune reaction and non-toxic degradation by-products; this is a recognised weakness of PLGA, whose acidic by-products can cause local inflammation
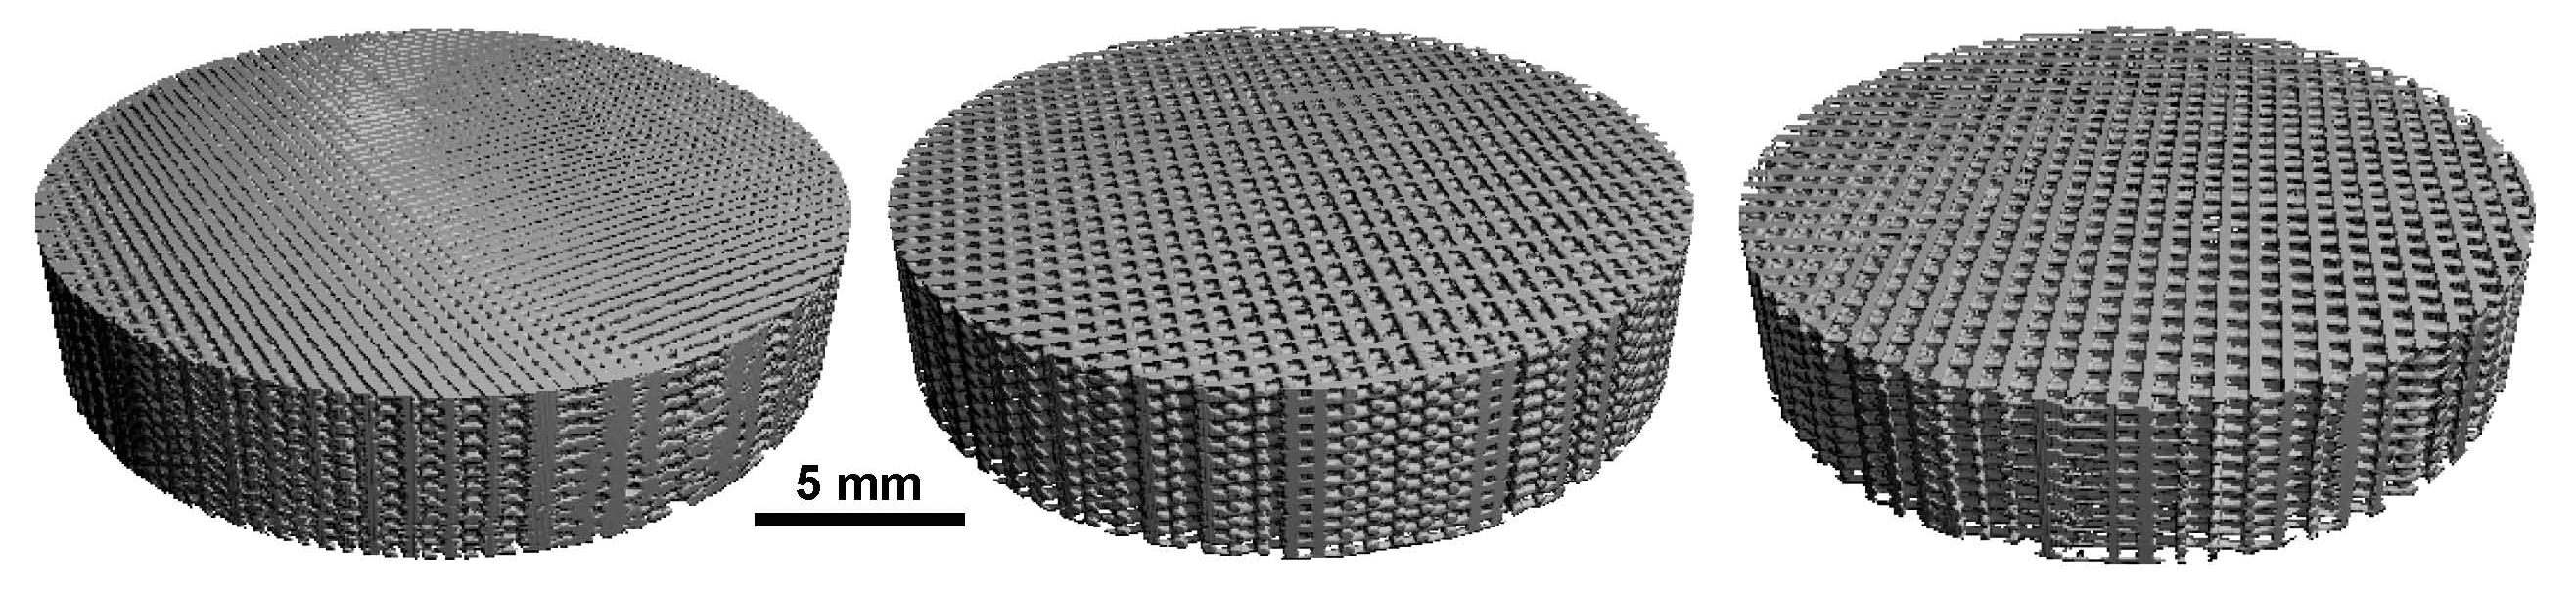
- Highly porous with interconnected pores, broadly around 100 to 500 microns, to allow cell migration, matrix deposition and, critically, vascular ingrowth
- Mechanically matched to the host tissue in stiffness and strength, able to bear or share load during healing without stress-shielding or collapsing
- Degrading at the rate new tissue forms: too fast and it loses support before the tissue matures, too slow and it impedes remodelling
- An osteoconductive surface chemistry and topography for attachment, proliferation and differentiation, ideally functionalised with growth factors or genes (a growth-factor-loaded or gene-activated matrix)
- Manufacturable and reproducible: scalable, sterilisable and increasingly 3D-printed to a patient-specific geometry
Architecture is a trade-off. Pore size, interconnectivity and strut thickness are the design variables that trade mechanical strength against cell ingrowth and vascular access. Regular, fully interconnected porosity is what lets cells colonise the whole construct rather than a surface crust.
The osteoconduction, osteoinduction and osteogenesis framework is developed in the Bone Grafts topic.

The Central Bottleneck: Vascularising the Construct
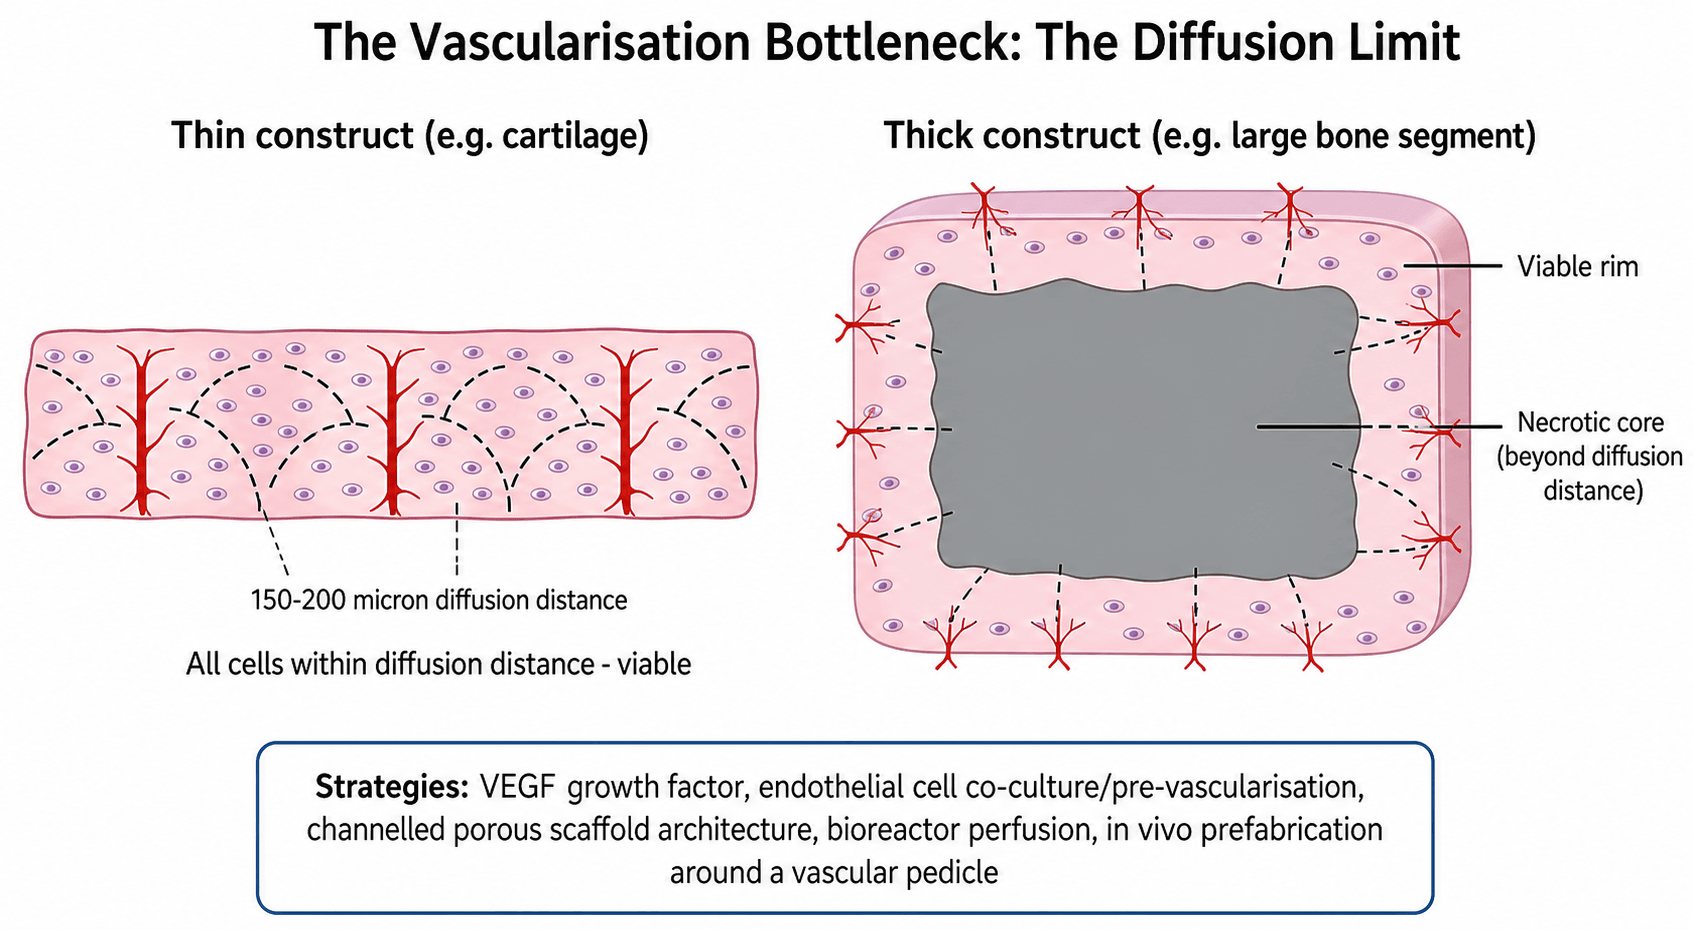
The diffusion limit. Cells survive only within roughly 150 to 200 microns of a capillary, the oxygen and nutrient diffusion distance. Beyond that distance the core of a thick construct becomes hypoxic and necrotic, so large constructs fail without a blood supply.
Which tissues are easier. Thin, relatively avascular tissues such as cartilage are far easier to engineer than thick, vascular ones such as a large bone segment.
Getting vessels in. The strategies to overcome it:
- Load the scaffold with angiogenic growth factors: VEGF, with PDGF for vessel maturation
- Pre-vascularise in vitro by co-culturing endothelial cells to form capillary networks before implantation
- Design the scaffold architecture with channels and high interconnected porosity to invite host-vessel ingrowth
- Use bioreactor perfusion to nourish the construct during culture
- The in vivo "bioreactor" or prefabrication approach: implant the construct around a vascular pedicle, or in a well-vascularised bed, to vascularise it before transfer
- Use a vascularised flap or free transfer surgically
The corollary. Matching the scaffold's pore architecture and angiogenic signalling to the host's capacity to grow vessels in is as important as the cells and the growth factors themselves.
Mnemonics & Memory Aids
CSS
Hook:Tissue engineering = CSS: Cells, Scaffold, Signals.
VECTOR
Hook:Gene therapy choices and challenges = VECTOR.
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“What is the tissue-engineering triad, and what is actually used clinically in orthopaedics?”
“What is gene therapy, how can genes be delivered, and why is it not yet routine in orthopaedics?”
Tissue-engineering triad
- Cells: MSCs (marrow/adipose), chondrocytes, osteoblasts
- Scaffold: 3D porous biodegradable (collagen/hydrogel; PLGA/PCL/ceramic/nanofibre)
- Signals: growth factors (BMP, TGF-beta, PDGF, VEGF) + mechanical stimuli
Clinical reality
- ACI/MACI - established cartilage technique
- Recombinant BMP-2/7 on collagen carrier (spine fusion, tibial nonunion)
- Orthobiologics adjunctive; whole-tissue constructs/gene therapy investigational
Gene therapy
- Deliver gene → cells make protein (sustained local expression)
- Viral (efficient; immunogenicity/insertional mutagenesis) vs non-viral (safer, less efficient)
- In vivo (direct) vs ex vivo (modify cells → re-implant; gene-activated matrix)
Challenges
- Vector safety; controlled, sustained expression
- Vascularising large constructs; cell-scaffold-signal optimisation
- Manufacturing, cost, regulation → mostly experimental
Evidence & Key Studies
Paracrine signals and a gelatin hydrogel scaffold for enthesis (rotator cuff) tissue engineering
- Demonstrates the tissue-engineering triad: mesenchymal stem cells (cells) within a gelatin hydrogel (scaffold) responding to chondrogenic signals (TGF-beta3 and BMP-4) to form fibrocartilage/enthesis tissue.
- Growth-factor and paracrine signals drove enthesis-associated matrix and transcription-factor expression, showing how signals direct differentiation.
- Illustrates a spatially graded biomaterial approach for regenerating the tendon-to-bone enthesis.
Bioactive nanofibrous scaffold for annulus fibrosus repair in disc degeneration
- A biodegradable nanofibrous polyurethane scaffold loaded with a bioactive factor (fucoidan) supported annulus fibrosus repair in intervertebral disc degeneration.
- The bioactive scaffold reduced inflammation and oxidative stress and promoted extracellular-matrix deposition, maintaining disc height and mechanical properties in vivo.
- Highlights both the promise (scaffold + bioactive signal) and a key challenge - the foreign-body reaction and harsh degenerative microenvironment.
Gene therapy in orthopaedics: progress and challenges in pre-clinical development and TRANSLATION
- Reviews gene transfer across the orthopaedic targets - bone, cartilage, ligament, tendon, joint and intervertebral disc - from the group that has led the field clinically.
- The skeletal tissues are a hard target for a specific reason: they are dense extracellular matrix with LOW CELLULARITY and LOW VASCULARITY, so there are few cells to transduce and poor access to them.
- A large body of work shows that transgene expression CAN be sustained at functional levels in skeletal tissue after gene transfer.
- The authors' central statement is the one to carry: clinical use is hindered by the ABSENCE OF PRACTICAL METHODS FOR SAFE, EFFECTIVE DELIVERY - the biology is not the bottleneck, the delivery is.
Gene-activated scaffolds: delivering nucleic-acid nanomedicines on biomaterials for orthopaedic repair
- Reviews the convergence of this page's two halves - a scaffold that also carries the gene, the 'gene-activated scaffold'.
- The rationale is a dosing problem with protein delivery: scaffolds loaded with recombinant PROTEIN release supraphysiological quantities at the defect, causing off-target effects and cytotoxicity, whereas a transfected cell manufactures the protein locally and at a physiological rate.
- Covers RNA interference as well as gene addition - modulating expression down as well as up.
- States plainly that gene-activated scaffolds HAVE NOT REACHED CLINICAL USE.
The single most important thing this page can tell you is the state of translation, so read the cards in that light. The Timmer and Yu studies are benchtop tissue engineering - one entirely in vitro, one in a surgically created animal defect - and neither concerns gene therapy at all; they show what a scaffold plus a signal can do in a laboratory. The gene-therapy half of this topic rests on the Watson-Levings and Raftery reviews, and both say the same thing: the biology largely works and the delivery does not. Skeletal tissues are dense matrix with low cellularity and poor vascularity, so there are few cells to transduce and little access to them, and no gene-activated scaffold has reached clinical use.
So when this comes up, describe the delivery problem rather than listing candidate genes - the list of transgenes that work in animals is long and has been long for two decades.
The tissue-engineering triad, the ACI/MACI and recombinant-BMP clinical examples, and the viral/non-viral, in-vivo/ex-vivo gene-therapy framework with its safety limitations are standard, well-established teaching. (See also our Orthobiologics, Stem Cells (MSC) and Bone Grafts topics.)