Benign Subungual Neuromyoarterial Hamartoma | Classic Pain Triad | Marginal Excision
- Classic triad: paroxysmal pain + pinpoint tenderness + cold sensitivity
- Love test: pinhead pressure on the tender spot causes disproportionate pain
- Hildreth test: tourniquet exsanguination abolishes the pain (highly specific)
- MRI is the imaging gold standard - well-defined T2 hyperintense lesion
- Treatment is marginal surgical excision - cure rate greater than 90 percent
- “Glomus body = arteriovenous anastomosis (Sucquet-Hoyer canal) for thermoregulation
- “Tumour arises from modified smooth muscle cells of the glomus body
- “Subungual lesions may show a faint blue-red spot beneath the nail plate
- “Plain X-ray can show scalloped erosion of the distal phalanx dorsal cortex
- “Always send the specimen for histology - exclude subungual melanoma
Overview and Epidemiology
Glomus tumours of the hand are uncommon, 1 to 5% of all hand tumours, and cause symptoms out of all proportion to their size. The classic triad of paroxysmal pain, pinpoint tenderness and cold sensitivity is so specific that, once recognised, the diagnosis is essentially clinical; when all three features are present the triad is pathognomonic.
Who. The peak is in the third to fifth decades, though the tumour is reported at any age, and women outnumber men by approximately 2-3 to 1. About 10% of patients have multiple lesions, often familial, the glomuvenous malformation described under Clinical Assessment.
Where. 75 to 80% are subungual. The remainder lie in the pulp, the volar finger and the palm.
The delay. The average interval from first symptom to correct diagnosis is around 7 years, because clinicians do not examine the nail bed carefully and do not perform the Love and Hildreth tests. The tumour is tiny (1-5 mm) and often invisible on inspection, the plain radiograph is frequently normal in early disease, and the symptoms are episodic, so the patient is well between attacks. Misdiagnosis is common: neuroma, Raynaud disease, neuropathy, arthritis, complex regional pain syndrome (CRPS) and psychiatric pain.
What it costs the patient. The pain is disabling, paroxysmal and triggered by cold and pressure, so patients avoid typing, writing, tool use and cold weather. Years of undiagnosed pain bring anxiety and sleep disturbance, multiple GP and specialist visits, and unnecessary imaging and treatment.
Pathophysiology
The glomus body. A specialised arteriovenous anastomosis, the Sucquet-Hoyer canal, in the reticular dermis. It is composed of an afferent arteriole, the Sucquet-Hoyer canal itself, an efferent venule and an intraglomerular reticulum of modified smooth muscle cells. Its function is thermoregulation: it shunts blood flow in the skin in response to temperature, particularly in the fingertips, toes and subungual regions, and glomus bodies are most concentrated in the fingertips and subungual region.
The tumour. A glomus tumour is a benign hamartomatous proliferation of these modified smooth muscle cells: a small, well-circumscribed, purple-red nodule that is rich in nerve fibres, hence the exquisite pain. Three components make up the lesion, and each accounts for part of the clinical picture:
- Modified smooth muscle cells - spindle or epithelioid glomus cells around vascular spaces form the bulk of the tumour; positive for SMA and vimentin
- Vascular channels - small, endothelium-lined channels within the lesion; they constrict in the cold, which is what triggers the paroxysmal pain and reflects the thermoregulatory origin of the parent cell
- Non-myelinated nerve fibres - abundant unmyelinated C fibres within and around the tumour; this dense innervation is the source of the pain and accounts for pinpoint tenderness, hyperalgesia, and Love and Hildreth positivity
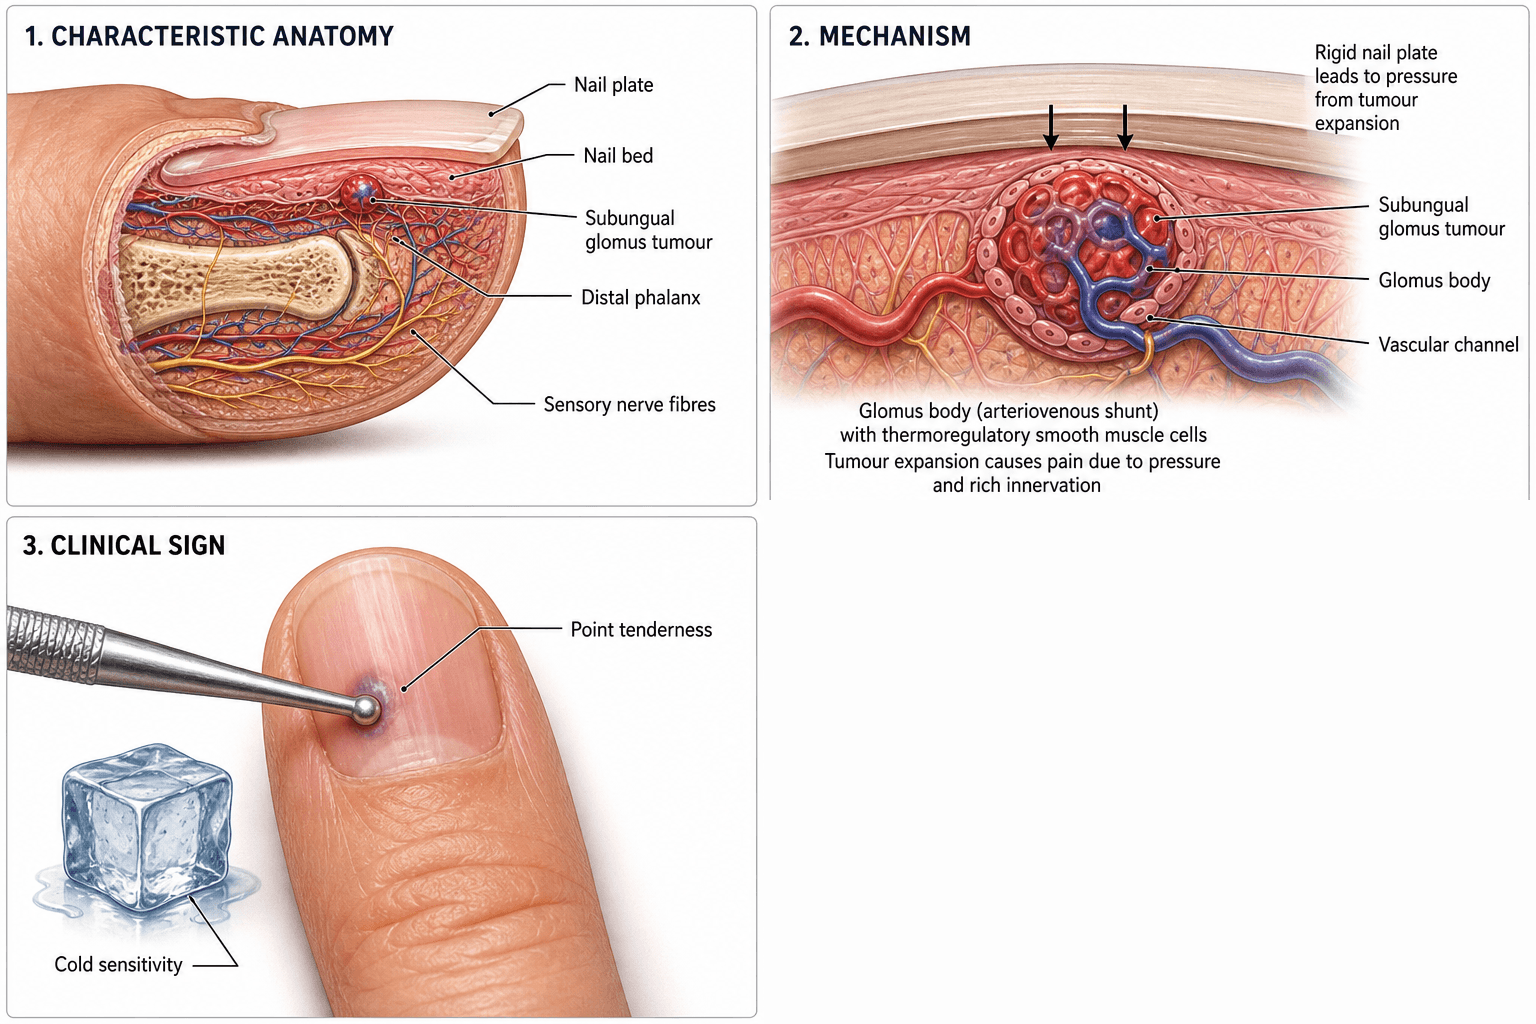
Why pinpoint, and why the tourniquet helps. The nodule is small, discrete, encapsulated and superficial, so the tenderness is confined to a single spot. Exsanguination empties the vascular channels and removes the pressure on the nerve fibres, which is why the Hildreth test abolishes the pain.
Histology. Well-circumscribed nodules of uniform, round, epithelioid glomus cells arranged in nests around small vascular channels. A fibrous pseudocapsule is typical, which supports marginal rather than wide excision. The cells are positive for smooth muscle actin (SMA), vimentin and h-caldesmon and negative for S100, CD31 and cytokeratins, useful in distinguishing them from melanoma, neurofibroma and adnexal tumours.
Classification and Types
Two classifications are in use and they answer different questions. Anatomic location decides the operation; Masson's histological subtype supports the diagnosis on pathology but does not change management, since every variant is treated by marginal excision.
Classification by Anatomic Location
- Frequency
- 75-80 percent
- Typical Sign
- Blue-red spot, nail ridging, possible cortical erosion
- Surgical Approach
- Transungual with partial or total nail avulsion
- Frequency
- 10-15 percent
- Typical Sign
- Small palpable nodule, localised tenderness
- Surgical Approach
- Direct volar marginal excision
- Frequency
- Less than 5 percent
- Typical Sign
- Small bluish nodule visible or palpable
- Surgical Approach
- Direct excision over lesion
- Frequency
- Approximately 10 percent
- Typical Sign
- Several painful bluish nodules; AD inheritance (glomulin gene)
- Surgical Approach
- Selective excision of symptomatic lesions
Subungual lesions are the most common and technically the most demanding.
Could it be malignant? The Folpe classification. The overwhelming majority are benign, but a malignant variant, the glomangiosarcoma (malignant glomus tumour), is rare but real, so "benign" is the rule rather than a guarantee. Malignancy is defined histologically; there is no such thing as "malignant transformation" of a benign glomus tumour. Folpe, from 52 unusual glomus tumours, proposed the four-category scheme the WHO adopted:
- Benign glomus tumour - the ordinary lesion
- Symplastic glomus tumour - high nuclear grade alone, with no other worrying feature; despite the alarming nuclei it behaves benignly
- Uncertain malignant potential (UMP) - one concerning feature only (high mitotic activity in a superficial lesion, or large size (over 2 cm) alone, or deep (subfascial or visceral) location alone) without meeting full malignant criteria
- Malignant glomus tumour (glomangiosarcoma) - deep location and size over 2 cm, or atypical mitotic figures, or moderate-to-high nuclear grade with 5 or more mitoses per 50 high-power fields
Behaviour tracks the category. In Folpe's series metastasis occurred in 38% of tumours meeting malignant criteria and in none classified symplastic, UMP or glomangiomatosis; the drivers of metastatic risk were deep location, size over 2 cm and atypical mitoses. Malignant glomus tumours are far more common in deep or extradigital sites than in the typical superficial subungual location, and they can metastasise (lungs). That is a second reason, beyond excluding melanoma, that every excised specimen goes to histology. A genuinely malignant or uncertain-potential lesion warrants wide excision, sarcoma-service referral and oncological follow-up, not simple marginal excision.
A small, superficial, subungual fingertip lesion is essentially always benign; malignant glomus tumours are typically deep and larger than 2 cm. Reserve concern for a deep, large or histologically atypical tumour, not for the classic painful subungual nodule.
Clinical Assessment
History. The pain is episodic and paroxysmal, sharp or burning, and triggered by cold exposure, light pressure and dependency. The patient points to a single fingertip or subungual spot. The history is typically years long and already carries several of the wrong labels listed in the overview.
Examination. Inspect the nail for a subungual blue-red spot, nail ridging or onycholysis, and palpate for a small, well-defined, exquisitely tender nodule. Then perform the two named tests.
Love test. With the patient seated and the hand rested, apply the tip of a paper clip, ballpoint pen, pencil or cotton-tipped applicator to the suspected spot. A positive test is disproportionate, sharp pain with minimal pressure; the patient typically withdraws the hand. It is easy to perform at the bedside and highly sensitive.
Hildreth (ischaemic) test. Apply a digital tourniquet (a Penrose drain or the finger of a glove) at the base of the affected digit, exsanguinate the digit by wrapping or milking blood proximally, then inflate or tighten the tourniquet. A positive test is complete abolition of the pain, and often of the ability to localise it, while the digit is exsanguinated: the patient who could previously point to a single spot can no longer find it. Release of the tourniquet causes immediate return of the pain.
Why Hildreth matters. It is the most specific bedside test for glomus tumour and helps differentiate it from other causes of fingertip pain, including neuroma and small nerve entrapment. This near-pathognomonic sign, combined with the classic triad, should be sufficient to justify surgery without further imaging, though MRI is still obtained for surgical planning.
Adjuncts. An ice cube or cold water on the digit reproduces the pain; the cold test is helpful but less specific, and positive in Raynaud too. Transillumination with a penlight through the distal phalanx may show a small reddish mass under the nail, a useful adjunct for subungual lesions.
- Discriminating Feature
- Classic triad; small bluish spot; positive Love and Hildreth
- Key Test
- Love and Hildreth
- Imaging
- MRI T2 hyperintense lesion; possible cortical erosion on X-ray
- Discriminating Feature
- Slow-growing firm nodule lifting the nail
- Key Test
- Inspection and X-ray
- Imaging
- X-ray diagnostic: bony outgrowth from distal phalanx
- Discriminating Feature
- Pigmented streak (Hutchinson sign if proximal fold), irregular border
- Key Test
- Biopsy (excisional)
- Imaging
- Dermoscopy; MRI for staging if confirmed
- Discriminating Feature
- Dorsal DIP, ganglion-like, often with degenerative joint
- Key Test
- Inspection and aspiration
- Imaging
- X-ray shows DIP osteophytes; MRI shows cyst
- Discriminating Feature
- Burning pain along nerve distribution, Tinel positive
- Key Test
- Tinel and nerve block
- Imaging
- MRI may show small nerve lesion
- Discriminating Feature
- Bilateral, colour change, cold-induced
- Key Test
- Cold challenge, nailfold capillaroscopy
- Imaging
- Not a focal lesion; X-ray and MRI normal
- Discriminating Feature
- Diffuse hand pain, swelling, vasomotor changes
- Key Test
- Budapest criteria
- Imaging
- Three-phase bone scan (old); clinical diagnosis
GLOMUSDifferential Diagnosis of a Subungual Lesion
Hook:GLOMUS differential: do not miss Glomus, Lentigo/melanoma, Onychomycosis, Mucoid cyst, Underlying exostosis, or SCC - pigmented or painful subungual lesions must be biopsied.
Solitary glomus tumour versus glomuvenous malformation. The familial, multiple "glomus tumours" are a genuinely different entity, the glomuvenous malformation (GVM), and the distinction matters for both the exam and management. A solitary glomus tumour is single, tiny, exquisitely painful with the classic triad, usually subungual, sporadic, and cured by marginal excision. A GVM is multiple, often plaque-like or nodular, bluish and partially compressible, and frequently non-tender or only mildly tender rather than showing the paroxysmal triad. It is inherited autosomal dominant via the GLMN (glomulin) gene with a paradominant, "second-hit" mechanism, hence the patchy distribution and variable penetrance.
Why the distinction changes treatment. GVMs are venous-predominant histologically (the glomangioma pattern) and respond poorly to simple excision; symptomatic or cosmetically troublesome lesions may be treated with sclerotherapy or laser as well as selective excision. The take-home: a painful solitary subungual lesion is a classic glomus tumour, whereas multiple compressible, non-tender bluish lesions with a family history are a glomuvenous malformation, so examine the skin and ask about affected relatives.
The exception: neurofibromatosis type 1. NF1 patients develop multiple true glomus tumours in the digits, often in several fingers and frequently bilateral, and unlike glomuvenous malformations these are the painful kind, with the full triad in each lesion. So "multiple, therefore not painful, therefore a malformation" is a shortcut that fails precisely where the diagnosis is hardest. The mechanism is a genuine tumour-suppressor effect, biallelic inactivation of NF1, with loss of the second allele demonstrated within the glomus cells themselves, which is why these behave as real neoplasms rather than malformations.
Two practical consequences.
- Fingertip pain in a patient with NF1 is a glomus tumour until proven otherwise. These patients endure the longest delays of all, because digital pain is attributed to a neurofibroma or to the neurofibromatosis in general and the small subungual lesion is never sought. Ask specifically about cold sensitivity and pinpoint tenderness, and examine each fingertip with a pen tip.
- Run the inference the other way too. A patient with more than one painful digital glomus tumour, especially bilaterally, should prompt an examination for café-au-lait macules, axillary and inguinal freckling, cutaneous neurofibromas and Lisch nodules, and a family history; the hand may be where an undiagnosed NF1 first declares itself. Warn the patient that further lesions may appear over time, since a new painful digit later is a new tumour rather than a failed operation.
Investigations
Plain radiographs. PA and true lateral views of the affected digit, obtained before MRI in every case to exclude exostosis, bone tumour or significant deformity. Look for a scalloped erosion of the dorsal cortex of the distal phalanx: it is highly suggestive of a long-standing subungual glomus tumour, the slow-growing lesion having remodelled the bone, and a useful pre-operative confirmatory sign when present. The film is normal in many cases, because the tumour is soft tissue and radiographs cannot see it, so a normal X-ray does not exclude a glomus tumour.
Ultrasound. High-resolution ultrasound is a quick, cheap screen in clinic, showing a small, well-defined, hypoechoic, hypervascular nodule. It is operator dependent, and a deeply subungual lesion may be obscured by the nail plate.
MRI. The imaging gold standard, obtained in all suspected glomus tumours before surgery, with a dedicated finger coil:
- T1
- T2 fat-sat or STIR
- Post-gadolinium T1 fat-sat
The lesion is a well-circumscribed, T2 hyperintense, strongly enhancing nodule beneath the nail. MRI localises occult or satellite lesions and guides the surgical approach, and modern high-resolution sequences (3 T with a dedicated surface coil) can identify lesions as small as 1 to 2 mm. Its limitations are cost and that it is not always available urgently.
Histopathology. Always send the excised specimen. Nests of uniform glomus cells around vascular channels, SMA positive and S100 negative, confirm the diagnosis and exclude melanoma or another lesion. It is available only after excision.
Management Algorithm
The operation is a marginal excision, and the approach is chosen by where the lesion sits.
Subungual Glomus Tumour
Goal. Complete marginal excision of the lesion with preservation of the nail matrix and minimum nail dystrophy.
Before theatre. MRI localises the lesion, identifies satellites and plans the approach. Use the Love test to mark the spot immediately before surgery; a regional block can be done first, but the mark should be made before the tissues are distorted. Consent covers recurrence (10-20%), nail dystrophy and persistent pain.
In theatre. Digital block, confirming a positive Hildreth test under the block if feasible, and a finger tourniquet for a bloodless field. Two approaches, chosen by where the lesion lies rather than a one-size-fits-all incision:
- Transungual - partial or total nail plate avulsion, then a longitudinal incision of the nail bed directly over the lesion. Direct midline access, preferred for centrally placed lesions, but a higher risk of nail ridging
- Subungual (Littler) - a lateral subungual incision raising a nail bed flap and preserving the nail plate. Excellent exposure for radial or ulnar subungual lesions, with less post-operative nail dystrophy
The excision itself is sharp dissection around the well-defined, blue-red nodule, taking a 1-2 mm cuff of normal tissue.
Closure. Repair the nail bed with 6-0 or 7-0 absorbable (e.g. polyglactin) interrupted sutures under loupe magnification. Replace the nail plate: it acts as a physiological splint for the repaired nail bed and prevents synechiae. Dress with a soft, non-adherent dressing and the fingertip exposed.
Afterwards. A light protective dressing for 10-14 days. The nail bed heals in 2-3 weeks; the new nail grows at approximately 0.1 mm per day, so a new nail plate takes 6-9 months. Review at 2 weeks for the wound, at 6 weeks, and at 3, 6 and 12 months for recurrence.
Complications
The table gives the figures; the work-up of recurrent pain is in the Management section.
- Incidence
- 10-20 percent
- Risk Factors
- Incomplete excision, missed satellite, multifocal disease
- Management
- MRI and re-excision; histology to confirm
- Incidence
- Up to 20 percent of subungual excisions
- Risk Factors
- Transungual approach, matrix injury, scar contracture
- Management
- Nail bed revision; long-term observation
- Incidence
- Less than 5 percent
- Risk Factors
- Wrong diagnosis, neuroma, CRPS
- Management
- MDT review; targeted nerve block; consider capsaicin
- Incidence
- 5-10 percent
- Risk Factors
- Volar approach in pulp, neuroma
- Management
- Desensitisation therapy; neuroma excision if needed
- Incidence
- Less than 2 percent
- Risk Factors
- Diabetes, poor hygiene, distal location
- Management
- Oral antibiotics; rare surgical drainage
Outcomes and Prognosis
What to expect. Complete excision cures more than 90% of patients with immediate pain relief. The recurrence rate of 10-20% in the complications table usually reflects incomplete excision, a satellite lesion or a second glomus tumour, which is why the two figures are not in conflict.
- Treatment
- Marginal excision with nail bed repair
- Expected Outcome
- Greater than 90 percent immediate pain relief
- Long-term Function
- Excellent return to function, minimal nail dystrophy
- Treatment
- Direct volar marginal excision
- Expected Outcome
- Greater than 90 percent pain relief; small scar
- Long-term Function
- Good function; minor pulp dysaesthesia in some
- Treatment
- Re-excision with wider margin after MRI
- Expected Outcome
- 70-85 percent relief after re-excision
- Long-term Function
- Good function if no further recurrence
- Treatment
- Selective excision of symptomatic lesions
- Expected Outcome
- Variable; depends on number and location
- Long-term Function
- Genetic counselling; long-term surveillance
Prognostic factors. The best prognosis is a single, well-localised subungual lesion treated by an experienced hand surgeon with intra-operative localisation and complete marginal excision. Prognosis is poorer with multifocal disease, an incomplete first excision, misdiagnosis (neuroma, CRPS), or a transungual approach that injures the nail matrix. Most patients are cured with one well-planned operation, and the single biggest predictor of a good outcome is accurate pre-operative localisation, which is why Love testing and MRI before surgery are not optional.
Guidelines, Registries & Global Practice
- Hand tumours: glomus tumours account for 1 to 5 percent of all hand tumours worldwide
- Subungual predilection: 75-80 percent of glomus tumours in the hand are subungual, with a female predominance
- Diagnostic delay: average 7 years from symptom onset to correct diagnosis, regardless of healthcare system
- Familial forms: autosomal dominant inheritance with mutations in the glomulin gene; more common in some populations
- High-resource: MRI with dedicated finger coil is the standard pre-operative localiser; Littler approach or transungual with nail bed repair under loupe magnification
- Limited-resource: clinical diagnosis (triad plus Love and Hildreth tests) with or without plain X-ray is acceptable; transungual excision is inexpensive and effective
- Universal principle: accurate pre-operative localisation (clinical, MRI or both) and complete marginal excision are the keys to cure
- Histology: essential in all healthcare settings - melanoma must be excluded
- Diagnosis emphasis
- Triad plus Love and Hildreth; MRI before surgery
- Treatment emphasis
- Marginal excision with nail bed repair; Littler approach when feasible
- Special notes
- Always send for histology to exclude melanoma
- Diagnosis emphasis
- Clinical diagnosis; MRI for surgical planning
- Treatment emphasis
- Day-case local anaesthetic excision is standard
- Special notes
- Nail bed repair with fine absorbable sutures
- Diagnosis emphasis
- Triad plus imaging (X-ray and MRI)
- Treatment emphasis
- Transungual or subungual approach depending on location
- Special notes
- Wide excision discouraged - marginal is curative
- Diagnosis emphasis
- Triad, bedside tests and ultrasound in resource-limited settings
- Treatment emphasis
- Transungual excision with nail bed repair
- Special notes
- Emphasis on high index of suspicion to reduce delay
There is no dedicated registry for glomus tumours (unlike arthroplasty registries) because the lesion is benign, treated by a small day-case operation, and typically cured. The evidence base is dominated by retrospective surgical series and operative-technique descriptions rather than randomised trials, so guidance is principle-based: recognise the classic triad, perform Love and Hildreth tests, obtain MRI for surgical planning, and excise the lesion completely with a marginal cuff.
Record in every suspected subungual lesion:
- Triad features (paroxysmal pain, pinpoint tenderness, cold sensitivity) - present or absent
- Love test result and Hildreth test result
- Pre-operative MRI findings (location, size, satellites)
- Surgical approach and margin taken
- Histology result and confirmation of complete excision
A missed glomus tumour - particularly one misdiagnosed as CRPS, neuroma or psychiatric pain - is a recurring source of patient dissatisfaction and medico-legal complaint. Always perform and document Love and Hildreth tests on any focal subungual or pulp pain.
Controversies & Areas of Uncertainty
The transungual approach (with partial or total nail avulsion) gives direct midline access but carries a higher risk of nail dystrophy. The Littler lateral subungual approach preserves the nail plate and is associated with less dystrophy, but offers more limited exposure. There is no high-quality comparative trial; choice is dictated by lesion location and surgeon preference.
The classic triad plus positive Love and Hildreth tests is highly specific, and some surgeons proceed to surgery without MRI. However, MRI detects occult satellite lesions and guides the approach. In recurrent cases, MRI is mandatory. The balance between cost and added value remains debated.
Multifocal disease carries a higher risk of recurrence. There is no consensus on the timing of excision of asymptomatic lesions, the value of genetic testing, or surveillance protocols. Selective excision of symptomatic lesions, with genetic counselling, is the current pragmatic approach.
A small number of patients have persistent pain despite complete excision and benign histology. Causes include digital nerve neuroma, scar neuroma, complex regional pain syndrome, or a missed satellite. MDT discussion, diagnostic nerve block, and pain-clinic input are useful; further surgery without a clear target is rarely helpful.
MCQ Practice Points
Q: From which structure does a glomus tumour arise? A: The modified smooth muscle cells of the Sucquet-Hoyer canal, a specialised arteriovenous anastomosis in the reticular dermis. The glomus body is concentrated in the subungual region and fingertip pulp, where it functions in thermoregulation. Tumour cells are positive for smooth muscle actin and negative for S100, which helps distinguish glomus tumour from melanoma and neurofibroma.
Q: What is the classic triad of a glomus tumour? A: Paroxysmal pain + pinpoint tenderness + cold sensitivity. The Love test (pinhead pressure) reproduces the pain, and the Hildreth test (tourniquet exsanguination) abolishes it. When all three features of the triad are present, the diagnosis is essentially clinical, although MRI is used to localise the lesion before surgery.
Q: What is the most useful imaging modality for a suspected glomus tumour? A: MRI with a dedicated surface finger coil and gadolinium enhancement. The lesion appears as a well-circumscribed, T2 hyperintense, strongly enhancing nodule. Plain X-ray may show scalloped erosion of the dorsal cortex of the distal phalanx, but is frequently normal. High-resolution ultrasound can also identify the lesion but is operator dependent.
Q: What is the appropriate surgical margin for a glomus tumour? A: Marginal excision with a 1-2 mm cuff of normal tissue. Wide excision is unnecessary for this benign lesion and risks unnecessary damage to the nail bed and matrix. Histology is mandatory to confirm the diagnosis and exclude melanoma.
Q: A patient has recurrent pain at the same site 12 months after glomus excision. What is the most likely cause? A: Incomplete primary excision or a missed satellite lesion. Obtain an MRI to localise residual disease, re-review the original histology, and offer re-excision with a wider margin. A small number of patients will have a wrong primary diagnosis (e.g. neuroma, CRPS) - re-review of histology and targeted nerve block can clarify.
Q: What is the most important diagnosis not to miss in a subungual lesion? A: Subungual melanoma. Any pigmented streak, non-healing ulcer or atypical subungual lesion must be biopsied and sent for histology. Glomus tumour and melanoma can occasionally coexist, and the absence of pain does not exclude melanoma. When in doubt, biopsy.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 38-year-old woman presents with a 4-year history of severe episodic pain in the right little fingertip. The pain is sharp, paroxysmal, triggered by cold weather and by bumping the fingertip. She has seen two hand surgeons, a neurologist and a pain specialist. She has been trialled on gabapentin, amitriptyline and a stellate ganglion block without benefit. On examination, the nail plate of the little finger shows a faint blue-red spot under the lateral edge, with a subtle longitudinal ridge. Plain X-ray is reported as normal. How would you proceed?”
“A 46-year-old man had a subungual glomus tumour of the right ring finger excised 18 months ago through a transungual approach. The histology confirmed a glomus tumour and he was pain-free for about 9 months. He now returns with identical pain at the same site. The previous surgeon told him the excision was complete. Examination shows a healed nail bed scar with a small bluish spot at its radial edge, and Love test is strongly positive at that spot. How would you manage this?”
Key Anatomy
- Glomus body = specialised arteriovenous anastomosis (Sucquet-Hoyer canal) for thermoregulation
- Tumour arises from modified smooth muscle cells of the glomus body
- Tumour cells are SMA positive and S100 negative (distinguishes from melanoma and neurofibroma)
- Most concentrated in subungual region and fingertip pulp
Classic Triad and Clinical Features
- Classic triad: paroxysmal pain + pinpoint tenderness + cold sensitivity
- Average diagnostic delay of 7 years - high index of suspicion is essential
- Subungual blue-red spot and nail ridging are characteristic
- Female predominance, peak age 30-50 years, 75-80 percent subungual
Bedside Tests
- Love test: pinhead pressure with a paper clip or pencil reproduces the pain
- Hildreth test: exsanguination with a finger tourniquet abolishes the pain
- Cold test: ice cube on the digit reproduces the pain (less specific)
- Transillumination: small reddish nodule visible under the nail
Investigations
- Plain X-ray: PA and lateral - look for scalloped erosion of the distal phalanx dorsal cortex
- MRI with a dedicated finger coil and gadolinium: T2 hyperintense, enhancing nodule
- High-resolution ultrasound: hypoechoic, hypervascular subungual nodule (operator dependent)
- Histology: always send the specimen to confirm glomus tumour and exclude melanoma
Treatment Algorithm
- Marginal (not wide) excision with a 1-2 mm cuff of normal tissue
- Transungual approach for central subungual lesions; Littler lateral subungual approach for eccentric lesions
- Pulp lesions: direct volar marginal excision with nerve preservation
- Nail bed repair with 6-0 or 7-0 absorbable sutures under loupe magnification; replace nail plate as a physiological splint
Outcomes and Complications
- Cure rate greater than 90 percent with complete marginal excision
- Recurrence 10-20 percent - usually incomplete excision or missed satellite
- Nail dystrophy in up to 20 percent of subungual excisions
- Re-excision with wider margin after MRI for recurrent disease
Differential Diagnosis
- Subungual melanoma: pigmented streak, Hutchinson sign, biopsy mandatory
- Subungual exostosis: bony outgrowth, X-ray diagnostic
- Mucoid (myxoid) cyst: dorsal DIP, ganglion-like, often with osteophyte
- Digital neuroma, Raynaud, CRPS: ruled out by bedside tests and MRI
Evidence Base and Key Trials
Glomus tumors of the hand: review of the literature and report of 28 cases
- Classic surgical-pathology series defining the clinical features of glomus tumours of the hand
- Confirms the triad of paroxysmal pain, pinpoint tenderness and cold sensitivity
- Subungual location in the majority of cases; subungual lesions often show bony erosion of the distal phalanx on X-ray
- Marginal surgical excision is curative in the great majority of cases
The ischaemic test for glomus tumour: a new diagnostic test
- Describes the ischaemic (Hildreth) test: a digital tourniquet is applied after exsanguination of the digit
- Positive test is abolition of the pain and of the ability to localise the lesion while the digit is exsanguinated
- Reports high specificity in differentiating glomus tumour from other causes of fingertip pain
Outcomes of the Transungual Approach in 56 Consecutive Digital Subungual Glomus Tumours
- 56 consecutive subungual glomus tumours. ALL 56 (100%) presented with the classic triad - the strongest available argument that this is a clinical diagnosis and that imaging confirms rather than makes it
- WHERE THEY SIT, which is the number that changes the operation: 20% in the sterile matrix, 68% AT THE JUNCTION of sterile and germinal matrix, and 12% in the germinal matrix. Two-thirds are at or beyond the junction, so an exposure that stops short of the germinal matrix is planned to miss most of them
- Average symptom duration before diagnosis was 52.9 MONTHS, range 3 to 204 - over four years, with one patient waiting seventeen
- Longitudinal versus transverse nail bed incision made NO difference to pain or to nail deformity (31 vs 25 patients), so the incision is a matter of exposure and surgeon preference rather than a determinant of the nail result
- One tumour (1.8%) was INTRAOSSEOUS and was only recognised intraoperatively - if the nail bed looks normal at exploration, examine the dorsal cortex of the distal phalanx before closing
- No recurrences. The single patient with persistent pain had a missed SATELLITE lesion in the same digit, which resolved after later excision
The 'shark mouth' flap approach for digital glomus tumours in 24 patients: technique and clinical outcomes
- Describes a novel shark mouth flap approach for digital glomus tumours with good clinical outcomes in 24 patients