Hip Abductor Tears | The Rotator Cuff of the Hip | Repair, Transfer, Reconstruction
- Rotator cuff of the hip - gluteus medius and minimus tears behave like supraspinatus tears, with footprint detachment, retraction and fatty infiltration driving outcome
- A tear is not the same as tendinopathy - this topic is the structural/surgical end of the spectrum; pure tendinopathy and bursitis are covered under greater trochanteric pain syndrome
- MRI is the reference standard - characterises tear thickness, retraction, and muscle fatty infiltration that determines reparability
- Fatty infiltration predicts failure - high-grade atrophy makes direct repair unreliable and pushes towards transfer or reconstruction
- Think abductor tear after THA - persistent limp, Trendelenburg gait or instability after hip replacement may be an iatrogenic or attritional abductor tear
- “Trendelenburg gait plus weak resisted abduction in a middle-aged woman with lateral hip pain points to a tear, not just bursitis
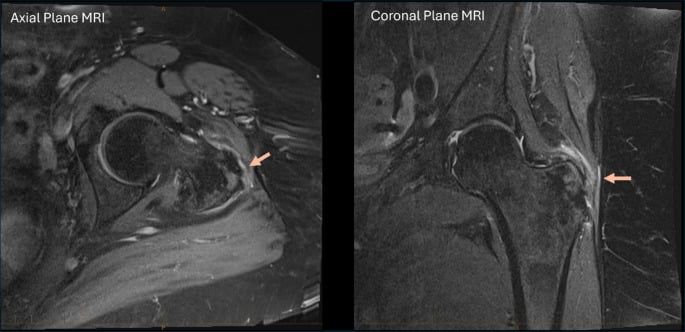
- “A focus of T2 hyperintensity superior to the greater trochanter is the single best MRI sign of an abductor tendon tear
- “Open and endoscopic repair give similar patient-reported outcomes; open techniques report higher complication rates
- “Gluteus maximus transfer is a salvage option for the chronically retracted, fatty, irreparable tendon
Overview and Epidemiology
Gluteal tendon tears are tears of the gluteus medius and/or minimus tendons at their insertion on the greater trochanter. They are increasingly recognised as a discrete cause of chronic lateral hip pain and abductor weakness, distinct from simple bursitis. [1,2]
The rotator cuff of the hip. The gluteus medius and minimus stabilise the pelvis during single-leg stance in the same way the rotator cuff stabilises the glenohumeral joint. Their tears mirror supraspinatus pathology and follow a similar natural history: tendinopathy progressing to partial then full-thickness tearing, with retraction and fatty muscle change. [1,2]
Where this topic sits. A tear is the structural, surgical end of a spectrum whose milder forms, tendinopathy and bursitis, are covered under greater trochanteric pain syndrome. Telling them apart changes management. Tendinopathy and bursitis are managed non-operatively, tendinopathy with loading rehabilitation; a full-thickness tear with weakness and fatty change is a surgical problem, in which the timing of intervention and the reparability of the tendon determine the outcome.
Who. Typically a woman aged 50 to 70. Most surgical series are heavily weighted towards women, frequently around or above a 4:1 ratio, and the wider pelvis increases tendon load. Tears are usually degenerative and insidious rather than acute traumatic events.
How common. Peritrochanteric tendon pathology is common on hip MRI: in a large consecutive imaging series, peritrochanteric lesions, including partial and full-thickness gluteus medius and minimus tears, were found in roughly one in five hips. [3] Isolated trochanteric bursitis without tendon pathology is uncommon, well under 10% of patients with lateral hip pain, which reinforces that structural tendon disease drives most refractory symptoms.
Anatomy
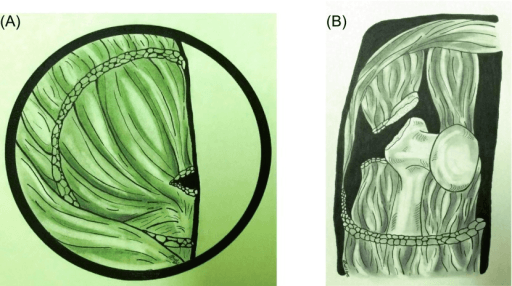
The abductor mechanism. The gluteus medius and gluteus minimus form it, with the iliotibial band and tensor fascia lata contributing to lateral pelvic stability. Both tendons lie deep to the iliotibial band (ITB), and each has its own footprint on the greater trochanter:
- Gluteus medius inserts on the lateral facet (the main, broad insertion) and the superoposterior facet. It is the principal hip abductor and the key pelvic stabiliser in single-leg stance.
- Gluteus minimus inserts more anteriorly, on the anterior facet and the hip capsule. It acts as an abductor and a fine-tuner of femoral head position.
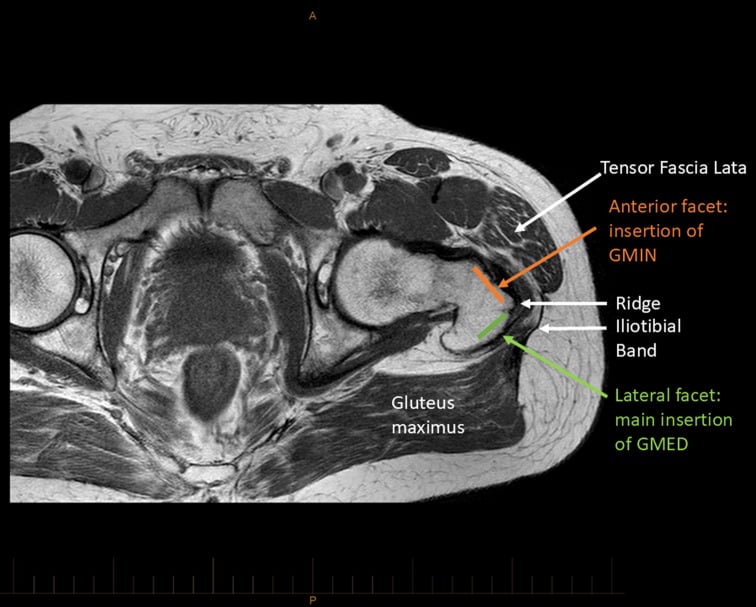
Nerve supply. The superior gluteal nerve supplies both muscles and the tensor fascia lata.
The superior gluteal nerve runs between gluteus medius and minimus, roughly 3 to 5 cm above the tip of the greater trochanter. Both the original lateral approach and any surgical mobilisation or transfer of the abductors can injure it. Iatrogenic superior gluteal nerve palsy produces an abductor lurch that mimics a tendon tear - assess both tendon integrity and nerve function when a patient limps after hip surgery.
Pathophysiology
Degeneration. Most tears are degenerative. Repetitive tensile load during abduction combines with the compressive load the ITB applies against the trochanter, particularly in hip adduction, producing a zone of tendinopathy near the insertion, directly analogous to the "critical zone" of the supraspinatus. Over time the degenerate tendon undergoes:
- Tendinopathy - intratendinous degeneration without a discrete tear
- Partial-thickness tear - undersurface (deep) or interstitial fibre failure with the footprint partly intact
- Full-thickness tear - complete detachment from the facet, with progressive retraction
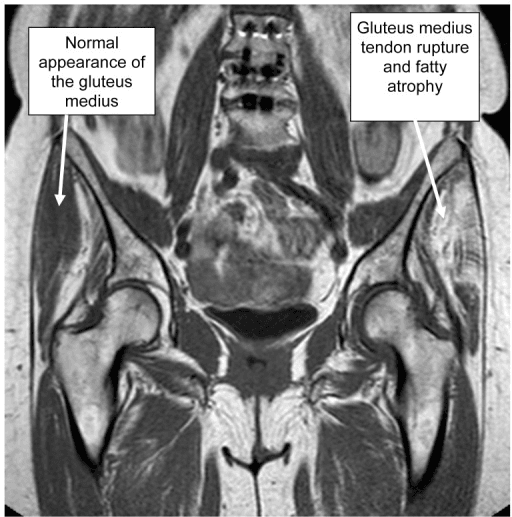
- Muscle change - chronic tears develop fatty infiltration and atrophy of the muscle belly, which is largely irreversible and is the strongest predictor of poor repair
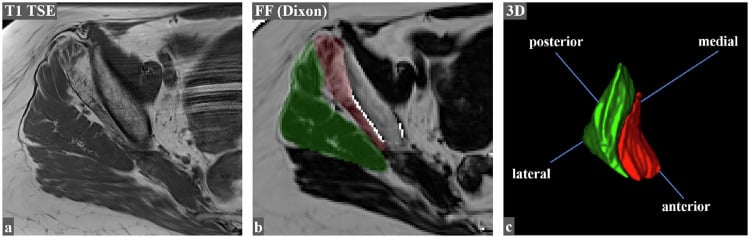
Tensor fascia lata hypertrophy. A recognised compensatory finding. As the gluteus medius fails, the TFL enlarges to maintain abduction, and this hypertrophy on imaging is a useful indirect clue to a significant abductor tear.
The post-arthroplasty abductor. After total hip arthroplasty, especially via a lateral (transgluteal) approach, the abductors can fail by iatrogenic detachment, suture pull-out, attritional wear, or denervation from superior gluteal nerve injury. The result is abductor deficiency, a Trendelenburg gait, and in severe cases recurrent dislocation, because the abductors also contribute to dynamic hip stability. [4] It is a recognised cause of failed THA.
Classification and Grading
There is no single universally adopted classification for gluteal tendon tears, and several descriptive schemes exist, among them a proposed endoscopic anatomical classification. [5] The useful exam framework is to describe the tear by thickness, retraction and muscle fatty infiltration, because these are what guide treatment. Always pair the structural description (thickness, retraction) with the muscle quality description (fatty change): together they determine whether you offer repair, augmentation or transfer.
- Basis
- Footprint involvement on MRI / at surgery
- Categories
- Partial (undersurface or interstitial) vs full-thickness
- Why it matters
- Partial tears may respond to loading; full-thickness usually needs repair
- Basis
- Pattern of insertional involvement
- Categories
- Non-transfixing partial-extension, transfixing partial-extension, transfixing full-extension
- Why it matters
- Transfixing tears are high-grade and carry more fatty infiltration
- Basis
- Distance of tendon from footprint
- Categories
- Minimal vs significant retraction (often around 2 to 2.5 cm threshold)
- Why it matters
- Greater retraction = harder, less reliable repair
- Basis
- Muscle quality on T1 MRI
- Categories
- Low grade vs high grade fat / atrophy
- Why it matters
- High grade predicts irreparability - favour transfer or graft
Retraction. The threshold between minimal and significant retraction is often around 2 to 2.5 cm, and it describes the tear. It is not an agreed threshold for abandoning repair in favour of transfer, which remains a matter of controversy (see below).
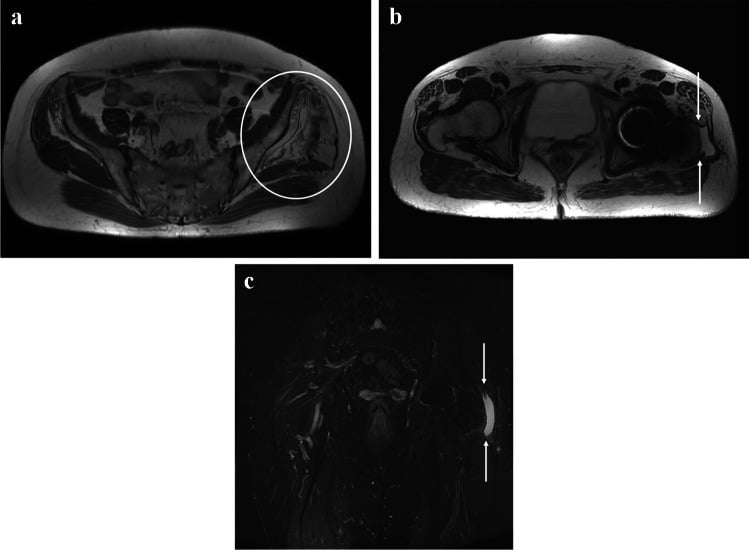
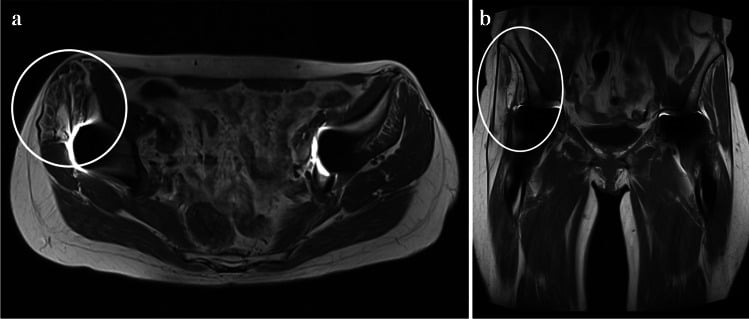
Grading Muscle Fatty Infiltration: the Goutallier Scale
The Goutallier classification was originally described for the rotator-cuff muscles on CT and later adapted to MRI (the Fuchs modification). The same five grades are applied to the gluteus medius and minimus:
- Grade 0 - normal muscle, no fat
- Grade 1 - some fatty streaks within the muscle
- Grade 2 - fatty infiltration present, but muscle bulk still exceeds fat
- Grade 3 - fat and muscle in roughly equal amounts
- Grade 4 - fat exceeds muscle
Why it decides the operation. Low-grade change (grades 0 to 2) behaves like a repairable tendon with viable muscle, so suture-anchor repair to the footprint is reasonable. High-grade change (grades 3 to 4) signals a muscle largely replaced by fat: the change is essentially irreversible, the tendon is functionally irreparable, and direct repair is unreliable, so graft augmentation or gluteus maximus transfer is preferred. Muscle quality, not tear size alone, is the dominant predictor of repair success.
Reading it. Fatty infiltration is best judged on T1-weighted images, where fat is bright. The scale is ordinal and shows only moderate inter-observer agreement, so it guides rather than dictates - a point worth conceding in a viva.
Clinical Presentation and Examination
History. Chronic lateral hip pain over the greater trochanter, often present for months to years, worse with side-lying, stairs and prolonged single-leg loading. Abductor weakness shows as difficulty climbing stairs, getting out of a car or standing on one leg, or a sense of the leg "giving way" laterally. A limp is common, and patients may describe a waddling or lurching gait.
After hip replacement. A new or persistent limp, weakness or instability after hip replacement should raise suspicion of an abductor tear, and is an abductor tear until proven otherwise. Examine gait, abductor power and stability deliberately.
Examination. The findings to look for:
- Gait - Trendelenburg gait (the pelvis drops on the contralateral swing side) or a compensatory abductor lurch (the trunk shifts over the affected hip)
- Trendelenburg test - single-leg stance on the affected side; the contralateral hemipelvis drops, indicating abductor failure
- Resisted abduction - weak and often painful
- Palpation - point tenderness over the greater trochanter
- Hip lag sign (abduction lag) - inability to hold the leg in passively positioned abduction, described as a clinical predictor of significant abductor damage
- Hip range of motion - typically preserved
Weakness is the discriminator. Weakness of resisted abduction, not just pain, and a frank Trendelenburg gait push you towards a structural tear. Pure tendinopathy is painful but usually retains reasonable strength.
Differential diagnosis. Beyond tendinopathy and bursitis, two conditions need separating:
- Hip osteoarthritis - groin pain (C-sign) with restricted, painful internal rotation, where a gluteal tear gives lateral pain with preserved range of motion. The two can coexist.
- Lumbar radiculopathy - radicular pain following a dermatome below the knee, with neurological signs, where a gluteal tear localises to the trochanter with a mechanical pattern and abductor weakness.
Investigations
Radiographs. Plain films are usually normal, and a normal radiograph does not exclude a tear, because the tendon itself is not seen. They are still worth obtaining to:
- exclude hip osteoarthritis, fracture and other bony pathology as alternative causes of pain
- look for calcific deposits at the trochanter (calcific tendinopathy) and for cortical irregularity or enthesophytes at the insertion
- assess implant position in the post-arthroplasty patient
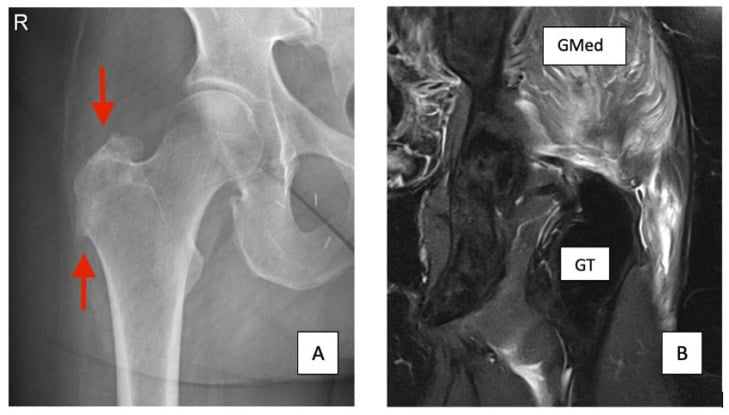
MRI. The reference standard for assessing gluteal tendon integrity and for surgical planning. It defines:
- Tear thickness - partial (undersurface or interstitial) versus full-thickness
- Retraction - the gap between torn tendon and footprint
- Muscle fatty infiltration and atrophy - graded as above, and the key determinant of reparability
- Associated findings - tensor fascia lata hypertrophy and peritrochanteric fluid
The MRI signs. The single best sign of an abductor tendon tear is a focus of T2 hyperintensity superior to the greater trochanter; secondary signs include tendon elongation and discontinuity. 3.0-Tesla MRI detects significantly more tears than 1.5-Tesla. [3] Around an arthroplasty, metal-artefact-reduction (MARS) MRI is generally preferred for soft-tissue assessment.
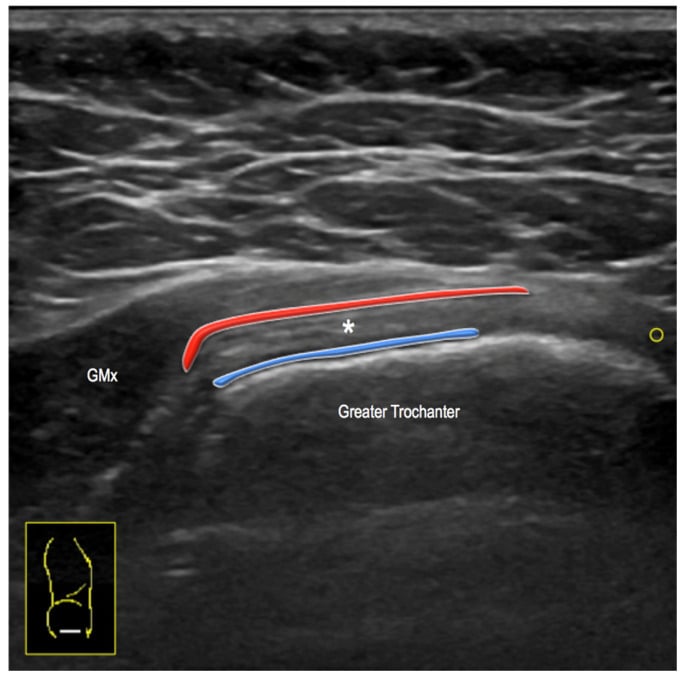
Ultrasound. A useful, dynamic, lower-cost first-line modality where MRI is limited, for example around large arthroplasty implants. It shows tendinopathy, partial and full-thickness tears and peritrochanteric fluid, and allows dynamic assessment and image-guided injection for diagnosis or therapy. It is operator-dependent and less reliable than MRI for grading muscle fatty change.
Other tests. Three further tests have specific uses:
- CT - mainly for bony detail and implant assessment
- Diagnostic injection - local anaesthetic into the peritrochanteric space that abolishes pain supports a peritrochanteric source
- Nerve studies - if superior gluteal nerve injury (denervation rather than tendon tear) is suspected after surgery
Management
Management is staged: structured rehabilitation first for most partial tears, surgery for refractory partial tears and full-thickness tears, and salvage transfer or reconstruction for chronic irreparable disease. Earlier is better, since chronic tears do worse than acute repairs.
Non-operative care. First-line for partial tears and tendinopathy, and overlapping heavily with greater trochanteric pain syndrome:
- Education and load management - reduce compressive ITB loading by avoiding sustained adduction, such as crossing the legs and side-lying on the affected hip
- Progressive abductor loading - isometric then isotonic strengthening, sparing aggressive ITB stretching that can increase trochanteric compression
- Adjuncts - simple analgesia; image-guided corticosteroid injection for short-term pain relief; platelet-rich plasma in tendinopathy without a full-thickness tear, more durable than corticosteroid in tendinopathy but not for established full-thickness tears
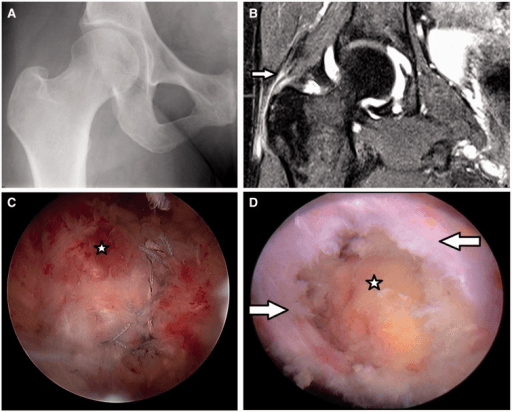
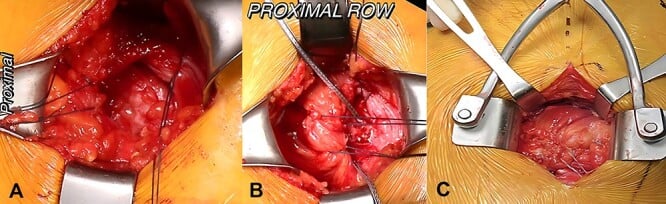
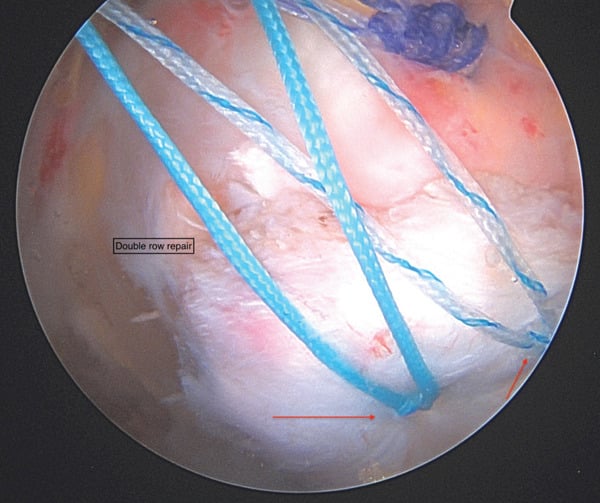
Surgical repair. Indicated for full-thickness tears and for partial tears that fail comprehensive rehabilitation, provided muscle quality is adequate. Endoscopic repair reattaches the tendon to the trochanteric footprint with suture anchors and allows treatment of concomitant intra-articular pathology. Open repair is a direct footprint repair, often with single-row or double-row suture-anchor constructs for anatomical footprint reconstruction.
Open double-row technique. The exposed greater trochanter is mapped, the torn medius and minimus are mobilised, viable tendon is preserved, and a double-row construct compresses the repaired footprint. Traction sutures confirm mobilisation; proximal-row anchors restore the medial footprint and distal anchors complete compression across a four-anchor repair.
Endoscopic technique. Fluoroscopy confirms anterior-lateral and lateral-posterior facet anchor positions, while endoscopy verifies purchase beside the prepared bare footprint. Horizontal-mattress limbs capture the tendon for the proximal row; bites must include sound tissue without strangulating the edge.
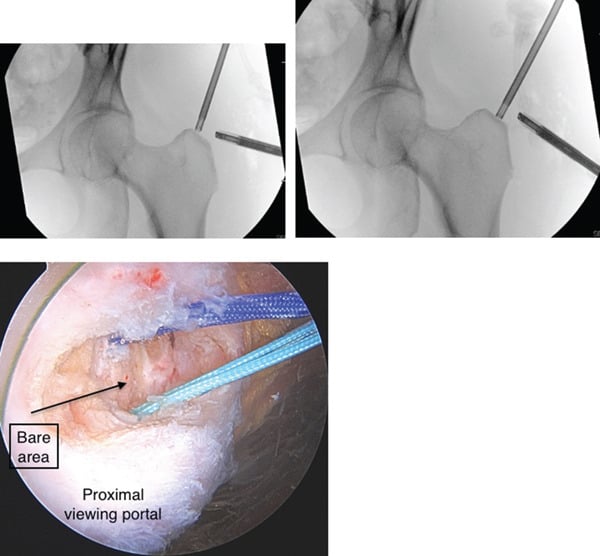
Open or endoscopic. Systematic review evidence shows similar patient-reported outcomes, pain scores and abduction strength, with higher reported complication rates after open surgery. [6] Read that complication difference with care. The endoscopic patients were a different group, 15 of 40 having concomitant intra-articular procedures against none of the 127 open patients; the comparison rests on a handful of level IV series rather than a pooled analysis; and complications were counted as each author reported them.
Results. Both partial and full-thickness tears improve, with low retear rates in appropriately selected patients. [2]
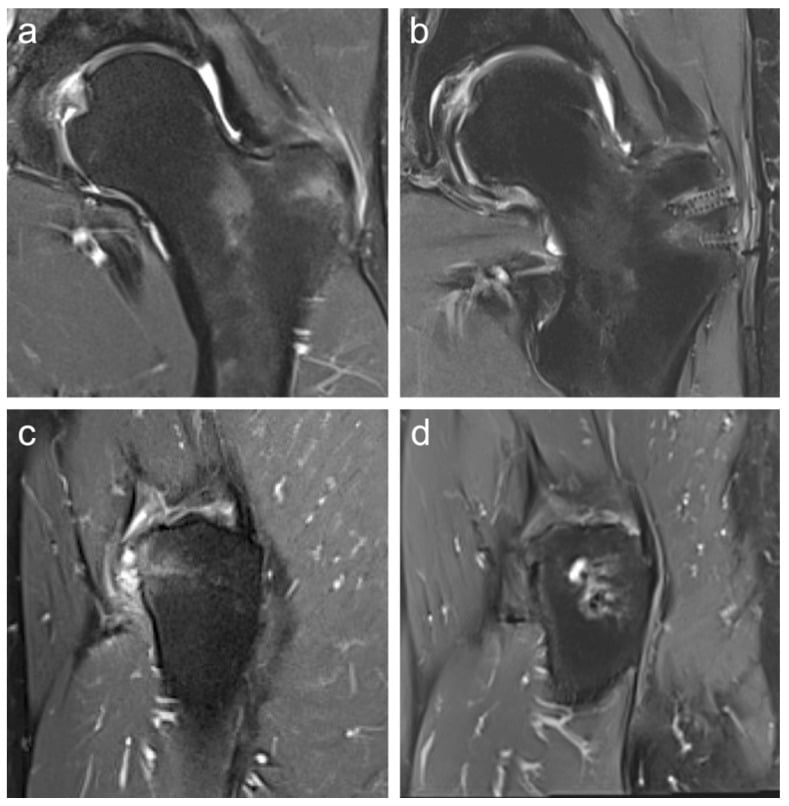
Rehabilitation after repair. Prolonged and protected, because of the high loads acting at the peritrochanteric region. A period of restricted weight-bearing and limited active abduction comes first, then graded abductor strengthening under supervision; premature loading risks repair failure.
Salvage. For chronic, retracted, fatty, irreparable tears, direct repair is unreliable and salvage is required:
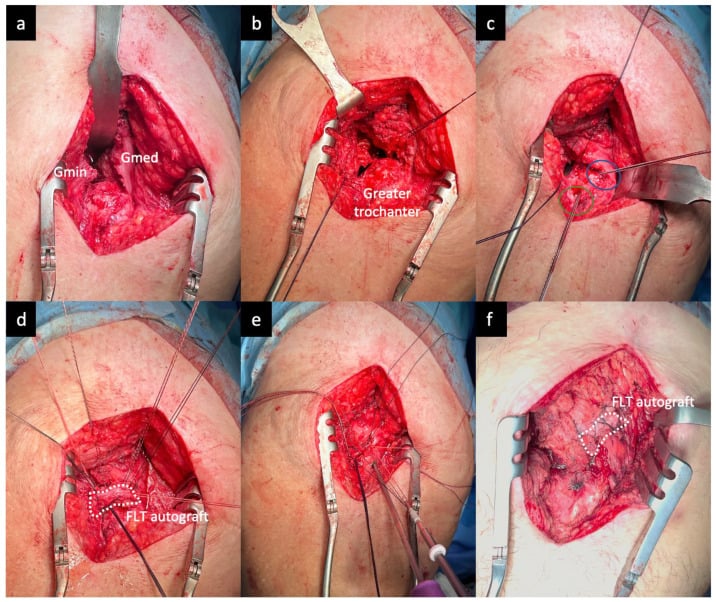
- Graft augmentation / superior gluteal reconstruction - graft or synthetic mesh reinforces a thin, poor-quality tendon. Human dermal allograft incorporated into a double-row construct has shown promising short-term outcomes for massive irreparable tears, including in revision cases. [7]
- Gluteus maximus tendon transfer - the workhorse salvage when the gluteus medius and minimus are severely atrophied or retracted but the gluteus maximus is functioning, alone or combined with the tensor fascia lata in revision arthroplasty (below)
Abductor deficiency after THA. A distinct management track. The goals are pain relief, restoration of abductor function and prevention of recurrent dislocation.
- Direct repair to the greater trochanter is reasonable when instability presents relatively early after primary THA and tissue is adequate. [4]
- Soft-tissue augmentation (acellular dermal allograft) and tendon transfers (gluteus maximus, vastus lateralis, latissimus dorsi in tumour resection) are options for avulsion or chronic deficiency. [4]
Literature quality is limited, but outcomes are generally favourable for pain and stability even when limp persists.
Gluteus Maximus Tendon Transfer: How the Salvage Works
Principle. When the gluteus medius and minimus are functionally lost (high-grade fatty infiltration and retraction) but the gluteus maximus is intact and innervated by the inferior gluteal nerve, part of gluteus maximus is transferred to reconstruct an active abductor pull across the greater trochanter. It is a dynamic, muscle-based reconstruction rather than a repair of the native tendon.
Technique in outline.
- Through a lateral approach, debride the diseased abductor tendon and prepare the greater trochanter to a bleeding bony bed.
- Mobilise the anterior portion (flap) of gluteus maximus on its neurovascular pedicle, preserving the inferior gluteal nerve supply, and advance it anterolaterally over the trochanter.
- Place anchors in the anterior and lateral greater-trochanter facets to reproduce an abductor line of pull, then secure the flap to the trochanter or to the vastus lateralis / residual abductor stump under appropriate tension, with the hip held in abduction so that resting tone helps hold the pelvis level.
- Protect it as for an abductor repair: restricted weight-bearing with the limb supported in slight abduction and limited active abduction, then graded strengthening, because early loading pulls the transfer out.
Variations. The classic Whiteside description uses a gluteus maximus flap alone. Combined constructs add the posterior part of the tensor fascia lata, and the two flaps are wrapped to recreate an abductor sleeve; this has been described to augment abductor reconstruction for severe, irreparable abductor deficiency in revision THA. [8]
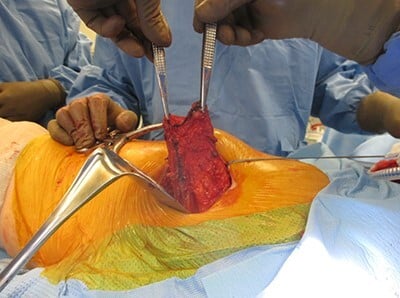
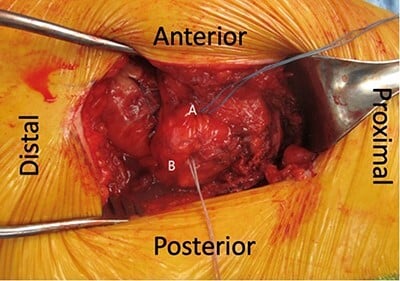
What to warn the patient. Transfer reliably improves pain and stability, but it does not restore normal power. Residual abductor weakness, a persistent Trendelenburg gait or lurch, and continued reliance on a walking aid are common, and the reconstruction can still fail. A more comfortable, more stable hip, but not a normal gait: that honest counselling is exactly what examiners want to hear, and it matches the outcomes reported for salvage transfer.
Complications and Outcomes
Retear and failure of repair. The main concern, especially in chronic tears with high-grade fatty infiltration, large retraction, obesity, and non-compliance with protected rehabilitation.
Other complications. The remaining risks are these:
- Persistent abductor weakness - residual weakness and a degree of Trendelenburg gait can persist even after successful repair or transfer, especially after salvage transfer for irreparable tears
- Superior gluteal nerve injury - meticulous technique and respecting the safe zone above the trochanter reduce the risk of iatrogenic denervation
- Wound and general surgical risks - infection, haematoma and prominent or irritating hardware, with the higher overall complication rate reported for open repair
Prognosis. Appropriately selected partial and full-thickness tears with reasonable muscle quality do well with repair, achieving meaningful pain relief and strength gains by open or endoscopic technique. Chronic, retracted, fatty, irreparable tears do less well and rely on salvage transfer or reconstruction, where pain relief is more reliable than full restoration of strength.
Guidelines, Registries & Global Practice
Global Epidemiology
- Peritrochanteric tendon pathology, including partial and full-thickness gluteus medius/minimus tears, is found in roughly one in five hips on MRI in unselected imaging populations, and is detected more reliably on 3.0-Tesla scanners. [3]
- A strong female predominance and a peak in the sixth and seventh decades are consistent across surgical series worldwide; most tears are degenerative rather than acute.
- Abductor deficiency is a recognised cause of pain, limp and instability after total hip arthroplasty, particularly following lateral (transgluteal) approaches. [4]
Society Guidance Compared
- Diagnosis
- Clinical plus US/MRI for surgical planning
- Repairable tears
- Endoscopic or open suture-anchor repair
- Irreparable / revision
- Graft augmentation or tendon transfer
- Diagnosis
- MRI to grade thickness, retraction, fatty infiltration
- Repairable tears
- Open or endoscopic repair (single/double row)
- Irreparable / revision
- Gluteus maximus transfer, dermal allograft reconstruction
- Diagnosis
- Tendinopathy-to-tear spectrum framing
- Repairable tears
- Repair for full-thickness and refractory partial tears
- Irreparable / revision
- Transfer / reconstruction for chronic retracted tears
- Diagnosis
- MARS MRI / US around implants; exclude nerve injury
- Repairable tears
- Direct abductor repair if early and good tissue
- Irreparable / revision
- Soft-tissue augmentation and tendon transfers
There is broad international agreement that MRI guides surgical decision-making, that repairable tears are treated by open or endoscopic suture-anchor repair with comparable outcomes, and that chronic retracted irreparable tears require salvage transfer or reconstruction. No body endorses a single proven fixation construct.
Registry & Outcome Notes
There is no dedicated gluteal tendon tear registry. Surgical-outcome evidence comes from systematic reviews and case series: open and endoscopic abductor repair give comparable patient-reported outcomes with more complications reported after open surgery [6], and salvage reconstruction with dermal allograft shows promising early results in massive irreparable tears [7]. In the arthroplasty setting, abductor deficiency is an important but under-captured cause of an unhappy hip in registry follow-up, often presenting as persistent limp or instability rather than a discrete revision diagnosis. [4]
High- vs Limited-Resource Practice Variation
- Well-resourced settings: 3.0-T MRI, ultrasound-guided injection, endoscopic and open repair, dermal allograft reconstruction, and tendon-transfer salvage are all available.
- Limited-resource settings: diagnosis leans on clinical assessment (Trendelenburg gait, weak resisted abduction, abduction lag sign) and ultrasound; management emphasises structured abductor loading rehabilitation, with open repair where surgery is available and endoscopic equipment or graft is not. The global priority remains accurate identification of a structural tear so that rehabilitation and surgery are directed appropriately.
Controversies and Areas of Uncertainty
Both achieve similar outcomes, with open surgery carrying higher reported complications - though the compared groups differ (concomitant intra-articular work in the endoscopic series, none in the open) and complications were never adjudicated to a common definition. There is no randomised comparison, so technique selection remains surgeon- and tear-dependent.
The optimal fixation construct and the role of graft augmentation (dermal allograft, synthetic mesh) are not defined by high-quality evidence; practice is extrapolated from rotator cuff surgery.
There is no agreed threshold of fatty infiltration or retraction at which to abandon repair for transfer. Decision-making is individualised on muscle quality and patient demand.
Multiple transfer and reconstruction techniques exist for post-arthroplasty abductor deficiency, but comparative evidence is sparse and persistent limp is common whichever is chosen.
Further uncertainty surrounds the prevalence of asymptomatic abductor tears, the prognostic value of MRI grading for predicting repair success, and the place of biologics in established full-thickness tears.
MCQ Practice Points
Q: What is the single best MRI sign of a hip abductor tendon tear?
A: A focus of T2 hyperintensity superior to the greater trochanter. Secondary signs include tendon elongation and discontinuity. 3.0-Tesla MRI detects more tears than 1.5-Tesla.
Q: Which factor most strongly predicts an irreparable tear or failed repair?
A: High-grade muscle fatty infiltration / atrophy (graded in a Goutallier-type fashion). With high-grade fat, direct repair is unreliable and salvage with transfer or graft is preferred.
Q: How do open and endoscopic gluteal repairs compare?
A: Similar patient-reported outcomes, pain and strength, but open repair has a higher reported complication rate. There is no randomised comparison proving one superior (Chandrasekaran systematic review).
Q: What is the workhorse salvage procedure for a chronic, retracted, fatty, irreparable abductor tear with a functioning gluteus maximus?
A: Gluteus maximus tendon transfer. It improves pain but residual abduction weakness and gait abnormality are common. Dermal allograft superior gluteal reconstruction is an alternative.
Q: What should a persistent limp with recurrent dislocation after a lateral-approach THA make you consider?
A: Abductor deficiency from an iatrogenic or attritional abductor tendon tear (or superior gluteal nerve injury). Options include direct repair, dermal allograft augmentation, and tendon transfers.
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“Classic chronic gluteal tendon tear presentation. The examiner wants a structured work-up that distinguishes a structural tear from tendinopathy and uses imaging to drive management.”
“The examiner is testing conceptual understanding linking shoulder and hip tendon pathology.”
“High-yield post-arthroplasty scenario testing recognition and management of abductor deficiency, including transfer and reconstruction options.”
“Tests knowledge of the comparative evidence and how to apply it.”
KEY CONCEPT
- Rotator cuff of the hip - gluteus medius/minimus tendon tears
- Structural/surgical end of the spectrum (vs tendinopathy/bursitis in GTPS)
- Female predominance, age 50-70, usually degenerative
- Fatty infiltration is the key predictor of reparability
ANATOMY
- Gluteus medius to lateral and superoposterior facets of GT
- Gluteus minimus to anterior facet
- Tendons lie deep to the ITB (compressive load)
- Superior gluteal nerve runs between medius and minimus - at risk
CLINICAL FEATURES
- Chronic lateral hip pain plus abductor WEAKNESS
- Trendelenburg gait and positive Trendelenburg test
- Weak resisted abduction; abduction lag sign
- Preserved hip ROM (helps exclude hip OA)
- Suspect after lateral-approach THA with limp/instability
INVESTIGATIONS
- Radiographs usually normal - exclude OA, calcific deposits, check implant
- MRI is reference standard - grade thickness, retraction, fatty infiltration
- Best MRI sign: T2 hyperintensity superior to greater trochanter
- 3.0-T MRI detects more tears than 1.5-T
- Ultrasound for dynamic assessment and around implants
MANAGEMENT
- Partial tears: load management + progressive abductor rehab first
- Full-thickness / refractory partial: suture-anchor repair
- Open and endoscopic repair give SIMILAR outcomes
- Open repair has higher reported complication rate
- Protected, prolonged rehabilitation after repair
SALVAGE / IRREPARABLE
- Irreparable = high-grade fatty infiltration + retraction
- Dermal allograft superior gluteal reconstruction
- Gluteus maximus tendon transfer (functioning maximus)
- Combined Gmax + TFL transfer in revision THA
- Counsel about residual weakness / limp
Evidence Base
Chandrasekaran S, Lodhia P, Gui C, et al. Outcomes of open versus endoscopic repair of abductor muscle tears of the hip: a systematic review. Arthroscopy. 2015;31(10):2057-2067
- Open and endoscopic repair give similar patient-reported outcomes and strength
- Open repair carries a higher reported complication rate
- No randomised comparison exists to declare one technique superior
Morgan A, Moore M, Derry K, et al. Surgical treatment and outcomes for gluteal tendon tears. Curr Rev Musculoskelet Med. 2024;17(6):157-170
- Repair (open or endoscopic) is first-line surgery for repairable tears
- Gluteus maximus transfer is a salvage option for irreparable tears
- Evidence is still insufficient to mandate a specific fixation construct or graft
Oehler N, Ruby JK, Strahl A, et al. Hip abductor tendon pathology visualized by 1.5 versus 3.0 Tesla MRIs. Arch Orthop Trauma Surg. 2020;140(2):145-153
- About one in five hips show peritrochanteric tendon pathology on MRI
- 3.0-T MRI detects significantly more tears than 1.5-T
- Abductor pathology associates with muscle atrophy and osteoarthritis
Browning RB, Clapp IM, Alter TD, et al. Superior gluteal reconstruction results in promising outcomes for massive abductor tendon tears. Arthrosc Sports Med Rehabil. 2021;3(5):e1321-e1327
- Dermal allograft reconstruction is an option for massive irreparable tears
- Promising short-term outcomes including in revision cases
- Small series and short follow-up limit strength of conclusions
Suggested Reading
- Harrasser N, Banke I, Gollwitzer H, et al. Gluteal insufficiency: pathogenesis, diagnosis and therapy. Z Orthop Unfall. 2016;154(2):140-147. doi:10.1055/s-0041-110812
- Morgan A, Moore M, Derry K, et al. Surgical treatment and outcomes for gluteal tendon tears. Curr Rev Musculoskelet Med. 2024;17(6):157-170. doi:10.1007/s12178-024-09896-w
- Oehler N, Ruby JK, Strahl A, et al. Hip abductor tendon pathology visualized by 1.5 versus 3.0 Tesla MRIs. Arch Orthop Trauma Surg. 2020;140(2):145-153. doi:10.1007/s00402-019-03228-1
- Elbuluk AM, Coxe FR, Schimizzi GV, et al. Abductor deficiency-induced recurrent instability after total hip arthroplasty. JBJS Rev. 2020;8(1):e0164. doi:10.2106/JBJS.RVW.18.00164
- Bitar AC, Guimaraes JB, Marques R, et al. Clinical and radiological results after endoscopic treatment for gluteal tendon injuries with a minimum follow-up of 12 months. Arch Bone Jt Surg. 2023;11(10):641-648. doi:10.22038/ABJS.2023.70495.3304
- Chandrasekaran S, Lodhia P, Gui C, et al. Outcomes of open versus endoscopic repair of abductor muscle tears of the hip: a systematic review. Arthroscopy. 2015;31(10):2057-2067. doi:10.1016/j.arthro.2015.03.042
- Browning RB, Clapp IM, Alter TD, et al. Superior gluteal reconstruction results in promising outcomes for massive abductor tendon tears. Arthrosc Sports Med Rehabil. 2021;3(5):e1321-e1327. doi:10.1016/j.asmr.2021.05.013
- Burns DM, Bornes TD, Al Khalifa A, et al. Surgical technique: abductor reconstruction with gluteus maximus and tensor fascia lata in revision total hip arthroplasty. J Arthroplasty. 2022;37(7S):S628-S635. doi:10.1016/j.arth.2022.03.006
- Lindner D, Shohat N, Botser I, et al. Clinical presentation and imaging results of patients with symptomatic gluteus medius tears. J Hip Preserv Surg. 2015;2(4):310-315. doi:10.1093/jhps/hnv035
- Caviglia H, Cambiaggi G, Vattani N, et al. Lesion of the hip abductor mechanism. SICOT J. 2016;2:29. doi:10.1051/sicotj/2016020