Congenital | Iatrogenic | Traumatic | Flexible vs Rigid | EHL Transfer or Arthrodesis
- Hallux varus is medial deviation of great toe at MTP joint greater than 10 degrees
- Iatrogenic (post-bunion surgery) is most common cause in adults
- Flexible vs rigid determines treatment - test passive correctability
- EHL transfer is first-line surgery for flexible deformity
- Arthrodesis is definitive treatment for rigid, arthritic deformity
- “Always assess flexibility - passive correction test differentiates flexible from rigid
- “Iatrogenic causes: excessive medial eminence resection, overtightening of medial capsule
- “EHL transfer (Johnson procedure) addresses dynamic deforming force
- “First MTP arthrodesis in 10-15° valgus is salvage for rigid deformity
Overview and Epidemiology
Hallux varus is medial deviation of the great toe at the first metatarsophalangeal (MTP) joint, the hallux angulated medially relative to the long axis of the first metatarsal by more than 10 degrees. [1] The normal hallux sits in 5-15 degrees of valgus. [2]
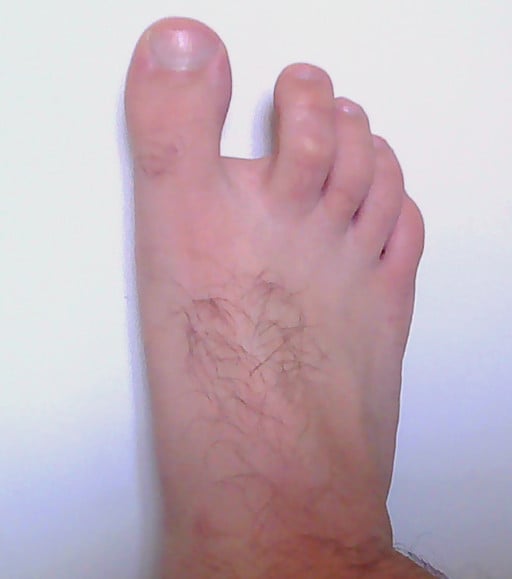
Who gets it. Iatrogenic hallux varus follows approximately 5-15% of hallux valgus corrections, which makes it the most common cause in adults [3]; other series put it at roughly 2-13%, the figure varying with technique and definition. Congenital hallux varus is rare, often associated with metatarsus adductus or part of a polydactyly syndrome [4], and traumatic hallux varus follows crush injuries, burns or medial soft-tissue trauma with subsequent contracture. Iatrogenic cases mirror the demographics of bunion surgery and are predominantly female; congenital cases are equally distributed between the sexes.
Why it matters. The first MTP joint normally bears 40-60% of forefoot weight during terminal stance, and the hallux is the principal contributor to propulsion at that point. A varus hallux contributes less and shifts load laterally onto the lesser metatarsals. [5] The consequences:
- Reduced push-off power and gait inefficiency
- Transfer metatarsalgia, with pain and calluses under the second and third metatarsal heads [17]
- Gait instability, because loss of medial tripod support reduces balance
- Difficulty with shoes, as the varus toe crowds the second toe and creates abnormal pressure points, and the deformity is cosmetically distressing
History. Hallux varus was first described in relation to overcorrection after bunion surgery in the mid-20th century. Early bunion operations often combined aggressive medial eminence resection and medial capsulorrhaphy without balancing the lateral structures, and produced high rates of iatrogenic varus. Modern bunion surgery emphasises preservation of sesamoid balance and judicious soft-tissue release. [6]
Aetiology
Hallux varus falls into three main categories by aetiology: iatrogenic, congenital and traumatic.
Iatrogenic
The most frequent cause in adults is overcorrection during hallux valgus surgery [7], and its flexibility varies from case to case. The technical errors that produce it:
- Excessive medial eminence resection. Removing too much medial bone eliminates the medial buttress, and the unopposed pull of abductor hallucis and extensor hallucis longus (EHL) draws the toe medially. The risk increases if resection extends beyond the sagittal sulcus of the metatarsal head.
- Overtightening of the medial capsule. Aggressive capsulorrhaphy or plication creates excessive medial tension, and with inadequate lateral release the soft-tissue forces are unbalanced. It was common in older McBride-type procedures.
- Fibular sesamoidectomy. The fibular sesamoid acts as a lateral buttress, and removing it allows medial deviation. The risk is higher when it is combined with other medial-sided procedures.
- Disruption of the lateral structures. Injury to the lateral capsule, lateral collateral ligament or adductor hallucis during exposure, or an overzealous lateral release in an attempt to correct a severe bunion.
- Overcorrection with osteotomy. Excessive varus angulation through a distal metatarsal osteotomy (chevron, scarf), or malunion in varus after a proximal osteotomy.
Preventing iatrogenic hallux varus during bunion surgery:
- Limit medial eminence resection to within the sagittal sulcus
- Preserve the fibular sesamoid: no routine sesamoidectomy, and excision only if it is severely diseased
- Balance medial and lateral soft-tissue releases proportionally
- Do not overtighten the medial capsule; plication should restore anatomy, not overcorrect
- Check sesamoid position intraoperatively: the sesamoids should be centred under the metatarsal head
- Aim for slight valgus, 10-15°, not neutral
Congenital
Congenital hallux varus is rare and typically presents in infancy or early childhood. [8] It is present at birth, and the causes include:
- Metatarsus adductus: the first metatarsal is deviated medially, creating a relative hallux varus
- Delta (trapezoid) phalanx: an abnormal wedge-shaped proximal phalanx drives progressive varus angulation
- Polydactyly remnants: incomplete resection, or scarring after excision of a polydactyly
- Congenital contracture of a tight abductor hallucis or the medial capsular structures
Most congenital cases are flexible and may improve with growth, and asymptomatic ones are observed. Rigid cases, and those with a structural bone abnormality, require surgical correction, with soft-tissue release for the rigid toe.
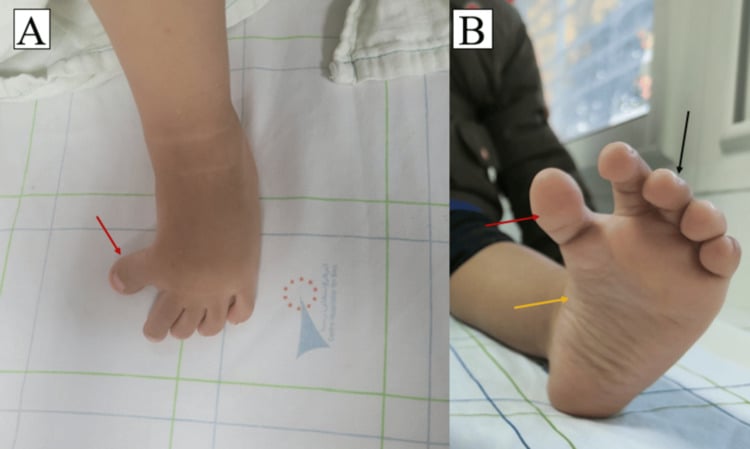
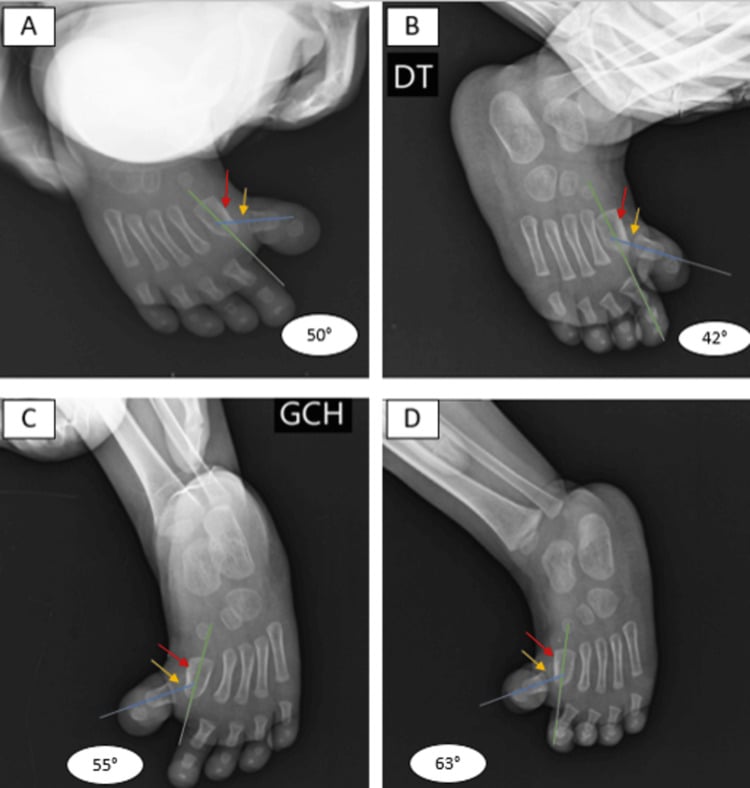
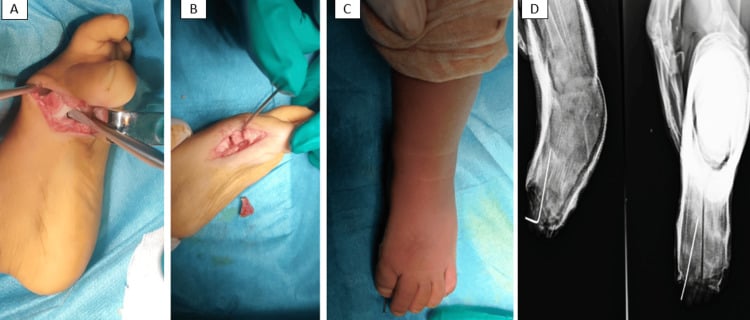
What else to look for. In the congenital case report illustrated below (Manni), plantar inspection also showed associated cavus, inversion and lesser-toe clawing, which must be included in reconstruction planning. Radiographs localised a severe bilateral deformity to the first MTP joints and showed shortened first metatarsals, measurements that influence the need for osteotomy.
Traumatic
Post-traumatic hallux varus comes with a history of trauma and with scarring, and skin quality may be a problem. Treatment releases the contractures, addresses the scarring and reconstructs as needed. The mechanisms:
- Soft-tissue contracture: burns, crush injuries or lacerations causing medial scar contracture
- Disruption of the lateral stabilisers: rupture of the lateral collateral ligament or the adductor hallucis tendon
- Malunion: fractures of the first metatarsal or proximal phalanx healing in varus
- Loss of the fibular sesamoid: traumatic excision or loss in a severe injury
Pathophysiology
The balance. The hallux is held in physiological valgus by opposing forces across the MTP joint:
- Medial, varus-producing: abductor hallucis (inserting on the medial base of the proximal phalanx), the EHL once the toe is in varus, and the medial capsule and collateral ligament
- Lateral, valgus-producing: adductor hallucis (inserting on the lateral base and the fibular sesamoid), flexor hallucis brevis through both sesamoids, the lateral capsule and collateral ligament, and the fibular sesamoid acting as a lateral buttress
Flexible deformity. The medial forces overpower the lateral ones, but the joint remains mobile and passively correctable. The EHL, which normally runs in a straight line, now bowstrings medially and becomes a dynamic deforming force. [9]
Rigid deformity. Chronic imbalance leads to capsular contracture and fibrosis, adaptive shortening of the medial structures and eventually joint stiffness or arthrosis. The deformity becomes fixed and cannot be corrected passively.
Progression Warning: Flexible hallux varus, if left untreated, often progresses to rigid deformity over time as secondary adaptive changes occur. Early intervention in symptomatic flexible cases can prevent progression to arthrodesis requirement.
Clinical Presentation and Assessment
History. Patients complain of the look of the toe, of shoes (the toe rubs on the adjacent toe or the medial side of the shoe), of pain at the MTP joint, especially if it is arthritic, of transfer metatarsalgia, and of difficulty with push-off and sport. The answers that shape management:
- Duration (congenital or acquired), whether it is progressive or stable, and the inciting event: surgery, trauma or insidious onset
- Treatments already tried
- Prior bunion surgery (timing, procedure type, complications), revisions and other foot procedures
- Numbness or tingling, from nerve injury at previous surgery
- Stiffness, which suggests a rigid deformity
Inspection and palpation. Examine standing, measuring the varus angle of the hallux against the first metatarsal, and look at the whole forefoot:
- Skin: scars from surgery or trauma, calluses on the medial hallux or the lateral lesser toes
- Adjacent toes: crossover or crowding of the second toe
- Hindfoot: associated pes planus or cavus
- First MTP joint: tenderness, effusion, and crepitus suggesting arthritis
- Medial eminence: prominence, or deficiency after over-resection
- Sesamoids: plantar tenderness and position
- Lesser metatarsal heads: tenderness suggesting transfer metatarsalgia
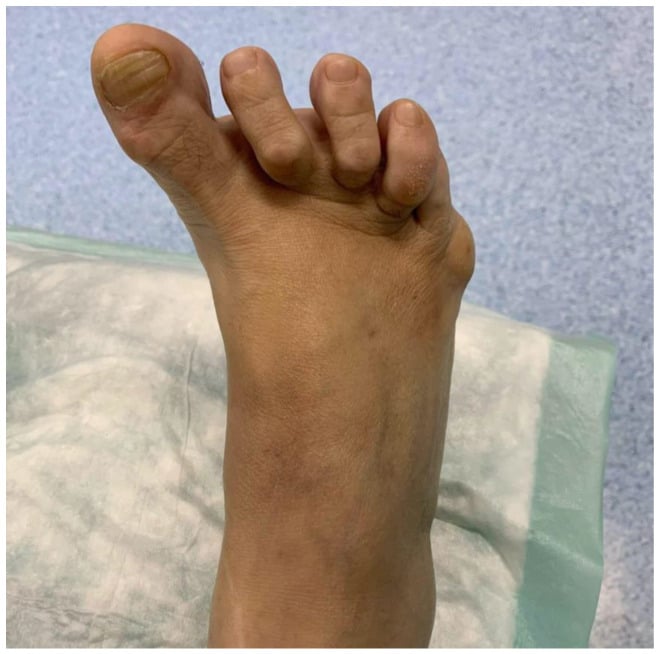
Movement. Normal first MTP motion is 70-80° of dorsiflexion and 20-30° of plantarflexion. Assess IP joint flexion and extension as well; pain or crepitus with motion indicates arthritis.
The passive correction test is the single most important clinical test, and it decides the operation. Grasp the hallux and push it laterally while stabilising the first metatarsal. If the toe readily corrects to neutral or beyond into valgus, the deformity is flexible and amenable to soft-tissue procedures such as EHL transfer; if it does not correct, it is rigid and arthrodesis is usually required. Two further tests identify what the reconstruction must address:
- Technique
- Actively extend hallux IP joint against resistance
- Positive Finding
- EHL tendon visibly bowstrings medially, accentuates varus
- Interpretation
- EHL is dynamic deforming force - consider transfer
- Technique
- Palpate plantar foot for sesamoids
- Positive Finding
- Fibular sesamoid absent or displaced
- Interpretation
- Lateral buttress lost - complicates reconstruction
Neurovascular examination and gait. Check the dorsalis pedis and posterior tibial pulses, sensation in the deep peroneal, medial plantar and saphenous territories, and motor function of EHL, FHL and the intrinsics. In stance, look at weight distribution and any tendency to offload the hallux; at push-off, a diminished hallux contribution and lateral forefoot loading.
Investigations and Imaging
Weight-bearing AP foot. Standard radiographs are essential for diagnosis and surgical planning. The weight-bearing AP shows:
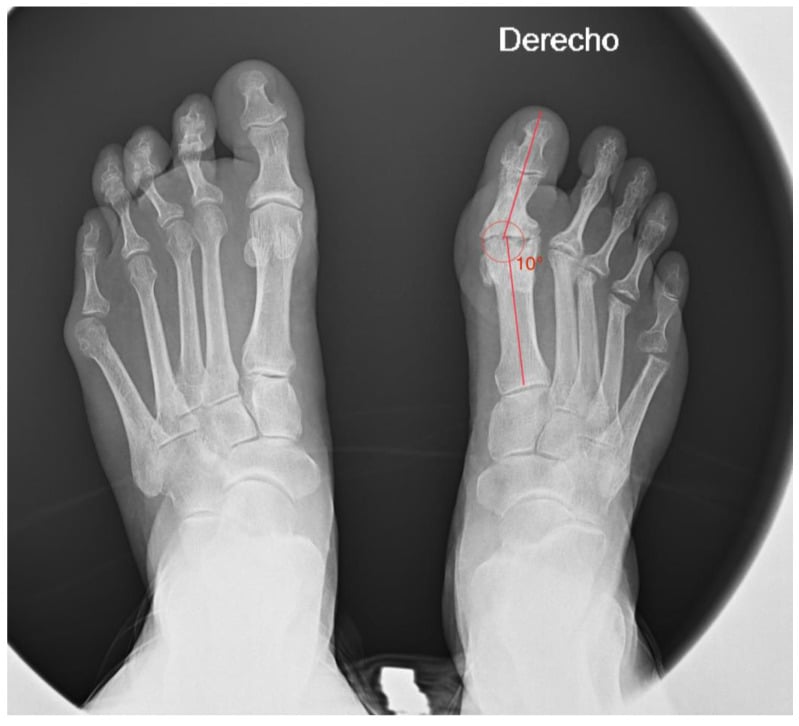
- The hallux varus angle, between the long axis of the first metatarsal and that of the proximal phalanx
- The position of the first metatarsal: metatarsus primus varus, where an increased intermetatarsal angle may predispose to recurrence
- The sesamoids, normally centred beneath the metatarsal head, which shift laterally in varus; look for an absent fibular sesamoid
- The joint space: narrowing, osteophytes or subchondral sclerosis indicate degenerative joint disease
- Evidence of previous surgery: hardware and the pattern of bone resection
- Associated lesser-toe structural abnormalities, which non-weight-bearing films can underestimate
Measuring the angle. Draw a line along the long axis of the first metatarsal shaft and another along the long axis of the proximal phalanx, and measure the angle at their intersection. Medial deviation of more than 10° confirms hallux varus. [11]
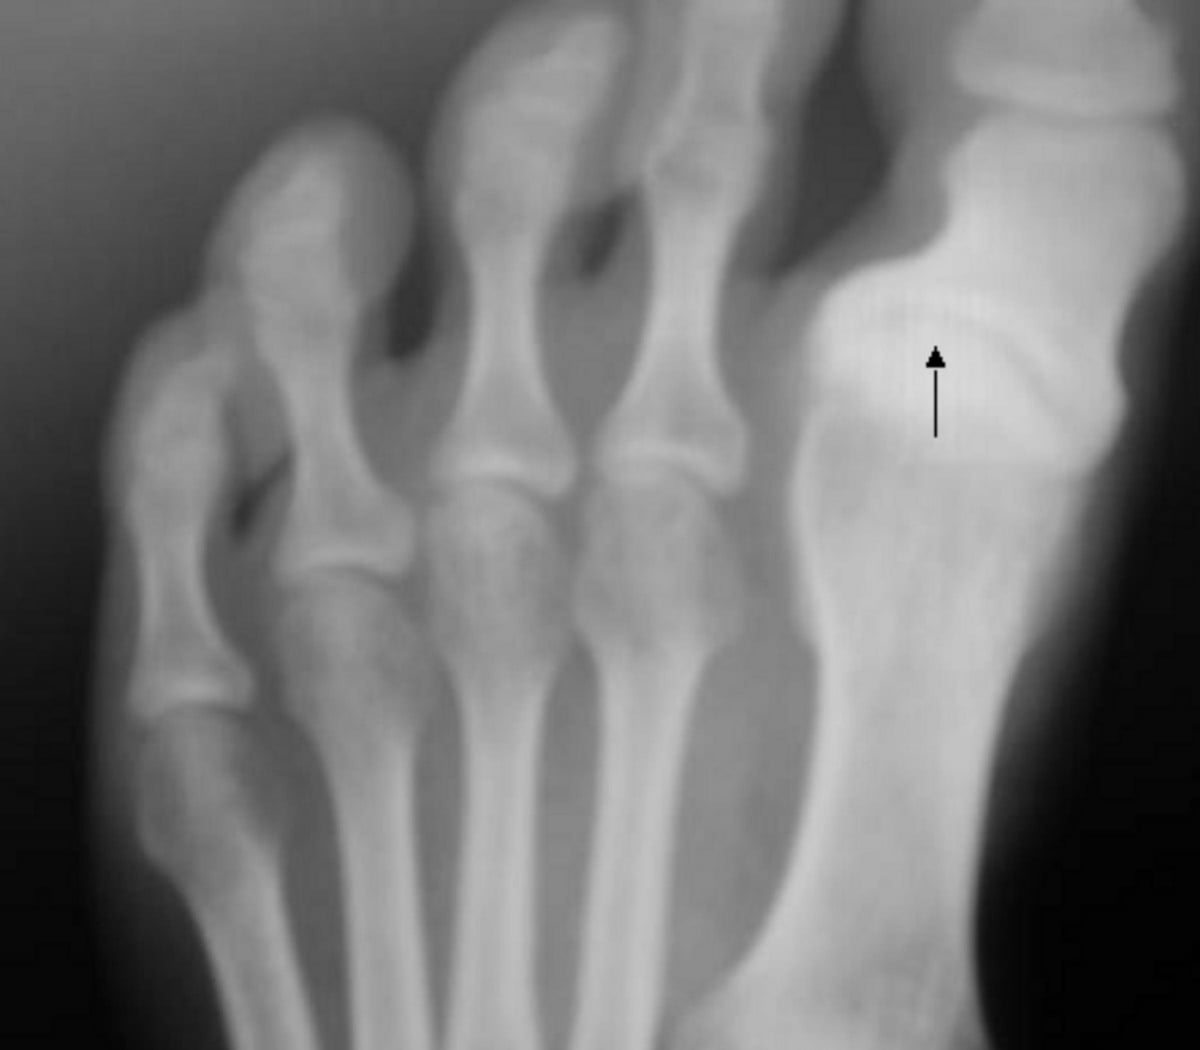
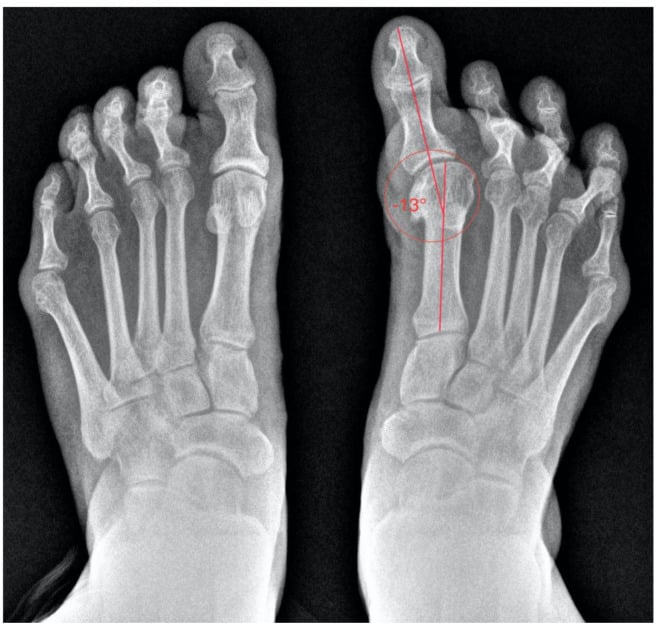
Lateral and oblique views. The weight-bearing lateral shows first MTP congruency and any subluxation, dorsal osteophytes that may limit dorsiflexion, and the declination of the first ray relative to the lesser metatarsals. The oblique view shows the sesamoids and the first MTP articular surfaces better.
MRI is rarely indicated in routine cases. It is useful for the integrity of the lateral soft tissues (adductor hallucis, lateral collateral ligament) in traumatic cases, for occult osteonecrosis of the sesamoids or metatarsal head, and for planning complex revisions.
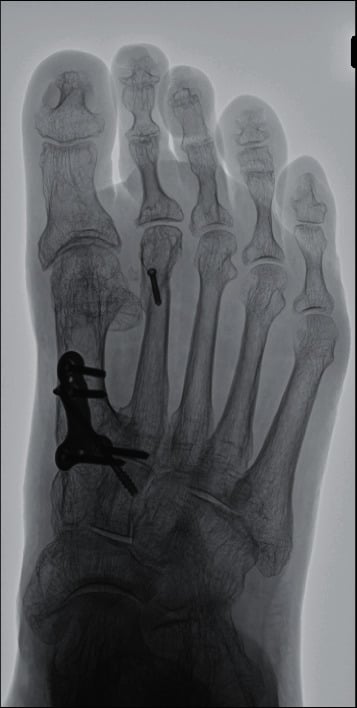
CT is rarely needed. It can assess bone stock and prior screw tracts in the multiply operated foot, and is useful for three-dimensional planning in severe deformity. In the case below, three-dimensional and cross-sectional CT identified an enlarged medial articular surface and a second-toe dislocation, a bony block that had to be corrected along with the soft-tissue imbalance.
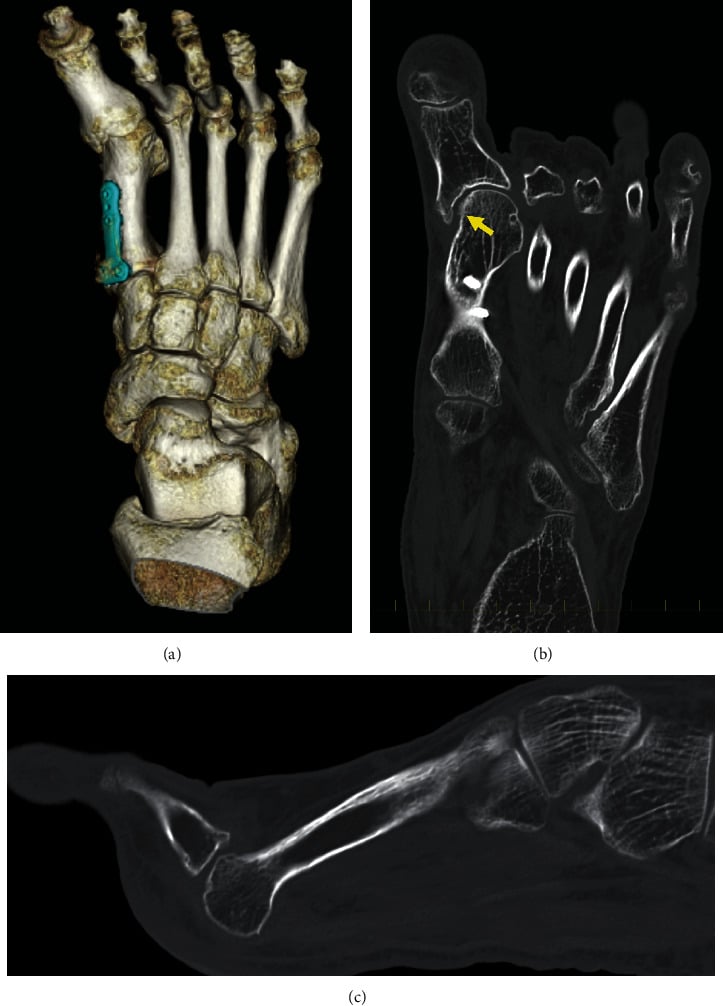
Classification. There is no universally accepted classification. Grouping by aetiology (congenital, iatrogenic, traumatic) and by flexibility is the most useful clinically, and flexibility is what the treatment follows:
- Description
- Passively correctable to neutral or valgus, no fixed contracture
- Clinical Test
- Passive correction test positive
- Treatment
- Soft tissue procedures (EHL transfer, capsular release)
- Description
- Fixed deformity, does not correct, joint space preserved
- Clinical Test
- Passive correction test negative, ROM preserved
- Treatment
- Aggressive soft tissue releases +/- osteotomy, or arthrodesis
- Description
- Fixed deformity with joint degeneration
- Clinical Test
- Crepitus, pain, radiographic arthritis
- Treatment
- First MTP arthrodesis (definitive)
Differential Diagnosis
Medial deviation or a "crooked" great toe has several mimics. The key discriminators are the direction of deviation, the level of deformity, and the history.
- Direction / Level
- Medial deviation at MTP joint
- Key Distinguishing Features
- Hallux angled medially over 10 degrees; often post-bunion surgery; assess flexible vs rigid
- Imaging Clue
- WB AP: hallux medial to first metatarsal axis, sesamoids shifted laterally
- Direction / Level
- Lateral deviation at MTP joint
- Key Distinguishing Features
- Opposite direction - lateral drift; bunion prominence; the deformity surgery was meant to treat
- Imaging Clue
- Increased hallux valgus and intermetatarsal angles
- Direction / Level
- Medial deviation at IP joint of phalanx
- Key Distinguishing Features
- MTP joint aligned; deformity is distal, within the proximal phalanx (delta phalanx, malunion)
- Imaging Clue
- Apex of angulation at phalangeal shaft/IP, not MTP
- Direction / Level
- MTP hyperextension, IP flexion
- Key Distinguishing Features
- Sagittal-plane deformity; may coexist with varus after EHL imbalance
- Imaging Clue
- Lateral radiograph shows dorsiflexed MTP, flexed IP
- Direction / Level
- Variable MTP malalignment
- Key Distinguishing Features
- Polyarticular, synovitis, bilateral, lesser-toe deformities, systemic features
- Imaging Clue
- Erosions, joint destruction, periarticular osteopenia
- Direction / Level
- First ray (metatarsal) medial deviation
- Key Distinguishing Features
- Bone/forefoot is adducted producing relative hallux varus; common congenital association
- Imaging Clue
- Increased intermetatarsal angle, adducted metatarsals
Management Algorithm
Non-operative treatment does not correct the deformity but may reduce symptoms, and a flexible deformity may still progress to a rigid one despite it. Congenital hallux varus is often observed, and surgery is rarely needed. The indications:
- Asymptomatic or minimally symptomatic deformity
- Congenital cases in young children, who have a high rate of spontaneous improvement
- Medical comorbidities precluding surgery
- Patient preference
The options:
- Observation: many congenital cases improve with growth
- Shoe modification: a wide toe box, soft uppers and custom orthotics to accommodate the deformity
- Toe spacers: soft silicone spacers between the hallux and second toe provide a lateral corrective force, with limited efficacy
- Taping or dynamic splinting to hold the toe corrected, which may slow progression in flexible cases
- Activity modification, avoiding what aggravates it
The operative decision. Four questions, in order:
- Is it flexible? Perform the passive correction test, under fluoroscopy if needed.
- Is the joint arthritic? Review the radiographs; an arthritic joint narrows the surgical options to arthrodesis.
- What is deforming it? Look for EHL bowstringing, abductor hallucis contracture, capsular contracture and bone deformity.
- Select the procedure: EHL transfer with or without adjuncts for the flexible, non-arthritic toe; arthrodesis for the rigid or arthritic one; an added osteotomy for bone deformity.
Prognosis. Flexible deformity carries the better prognosis, and does well with appropriate soft-tissue surgery. Arthrodesis for the rigid toe is reliable, at the cost of motion.
- Indication
- Flexible, non-arthritic, EHL bowstringing
- Technique Overview
- Transfer EHL to lateral capsule/proximal phalanx
- Outcomes
- Recurrence 4.4% in a failure-focused systematic review
- Indication
- Medial soft tissue contracture
- Technique Overview
- Release abductor from medial base of proximal phalanx
- Outcomes
- Often combined with EHL transfer
- Indication
- Medial angulation of proximal phalanx
- Technique Overview
- Lateral closing wedge osteotomy of proximal phalanx
- Outcomes
- Adjunct to soft tissue procedures
- Indication
- Rigid, arthritic, salvage for failed soft tissue procedures
- Technique Overview
- Fuse MTP joint in 10-15° valgus, 20-25° dorsiflexion
- Outcomes
- Definitive correction, loss of motion; 93% good or excellent in the cited fusion series (mixed indications)
- Indication
- Metatarsus primus varus component
- Technique Overview
- Correct metatarsal alignment (valgus-producing osteotomy)
- Outcomes
- Rarely needed as isolated procedure
Surgical Techniques
EHL Transfer (Johnson Procedure)
Principle. With the toe in varus, the EHL bowstrings medially and becomes a deforming force. Transferring it to the lateral side of the proximal phalanx removes the medial pull and creates a new lateral stabilising force. [12] What happens to the IP joint depends on whether the whole tendon or half of it is moved, which is set out in the next section.
Indications
- Flexible hallux varus
- Non-arthritic first MTP joint
- EHL bowstringing identified as the dynamic deforming force
- Failed conservative management
Contraindications
- Rigid deformity that does not correct passively
- Arthritic MTP joint
- Severe bone deformity requiring osteotomy
- Poor soft-tissue envelope
Set-up and approach. Supine, with a thigh (or ankle) tourniquet and a bump under the ipsilateral hip to bring the foot flat. A dorsal longitudinal incision of about 4-5 cm, centred over the joint line, runs from the midshaft of the first metatarsal to the midshaft of the proximal phalanx.
Steps
- Incise skin and subcutaneous tissue, preserving the dorsal cutaneous nerves; the EHL lies in the centre of the wound. Open the extensor hood longitudinally over the MTP joint.
- Transect the EHL sharply at the base of the proximal phalanx, distal to the MTP joint, and deliver the proximal stump into the wound with gentle traction; it retracts slightly but remains accessible.
- Retract the tendon medially to expose the lateral capsule, identify the lateral collateral ligament and adductor hallucis insertion, and make a lateral capsulotomy if it is tight (the capsule is often attenuated in chronic varus).
- Drill a 3.5-4 mm tunnel from dorsolateral to plantar-medial through the base of the proximal phalanx.
- Place a heavy non-absorbable suture (e.g. No. 2 FiberWire) in the tendon with a Krackow or whipstitch and pass it through the tunnel from dorsolateral to plantar-medial.
- Hold the hallux corrected, neutral to 5-10° of valgus, and tie the sutures over a button or post on the plantar-medial cortex, tensioning the EHL to the lateral side.
Alternatively, place a suture anchor in the lateral base of the proximal phalanx and suture the EHL to the lateral capsule and periosteum.
Adjuncts. Release abductor hallucis from the medial base of the proximal phalanx, through an extension of the incision or a separate medial one, and release the medial capsule if it is contracted. If significant medial angulation of the proximal phalanx persists after the soft-tissue correction, add a reverse Akin osteotomy.
Closure. Close the extensor hood loosely with absorbable suture, then the subcutaneous layer, and the skin with nylon or an absorbable subcuticular suture. A bulky dressing holds the hallux in slight valgus with gauze between it and the second toe.
Outcomes. None of the sources here gives a pooled success rate for the operation; its recurrence rate and other complications are set out under Complications.
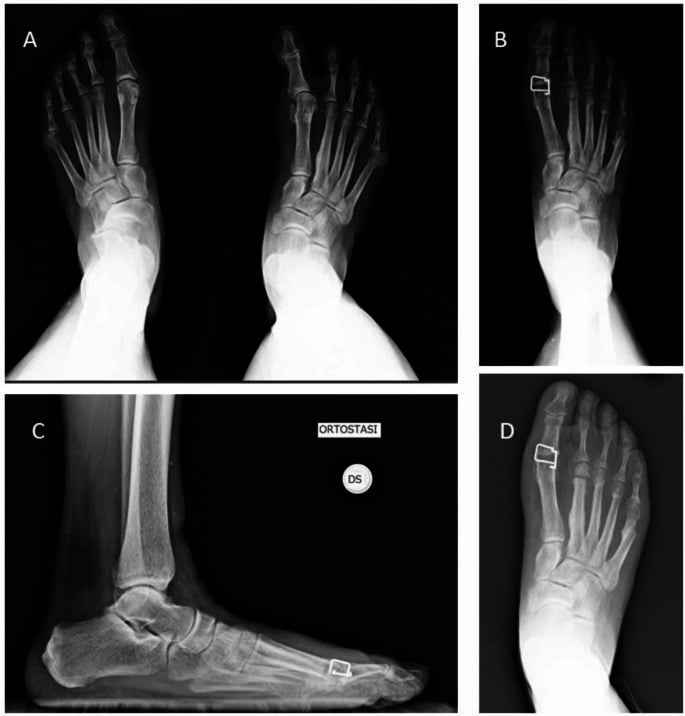
Correcting congenital varus. In the congenital correction illustrated (Manni), a dorsomedial release addressed the tethering abductor hallucis and capsule, and a valgus-producing first-metatarsal osteotomy with temporary MTP K-wire fixation restored alignment.
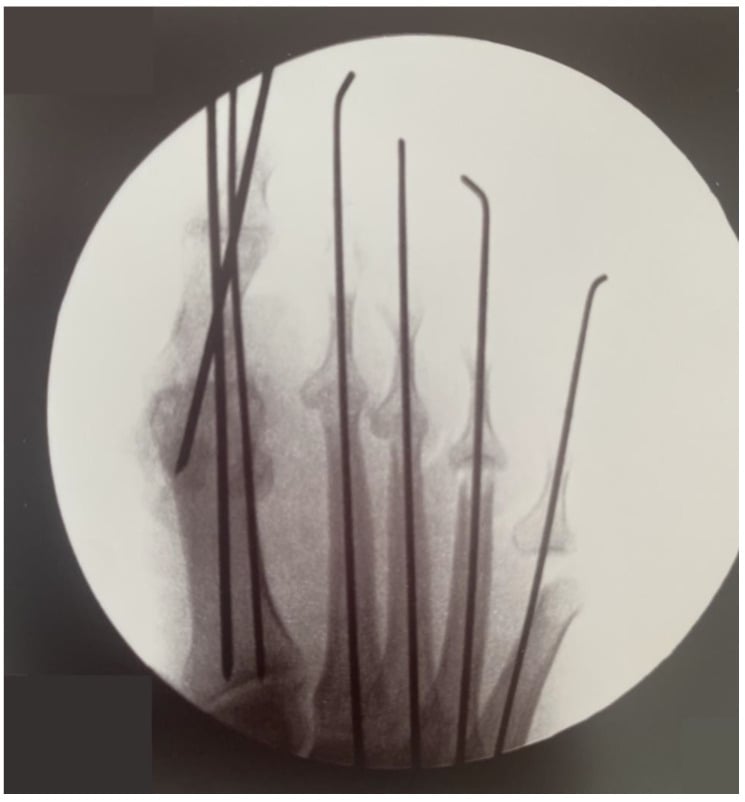
Split EHL Transfer (Modified Johnson)
The original operation. The classic Johnson transfer divides the whole EHL and reroutes it laterally, which removes active extension of the interphalangeal (IP) joint. To prevent the resulting cock-up or claw of the IP joint, Johnson combined it with a first IP arthrodesis, and that fusion is the price of the original operation.
The split modification. Only the lateral half of the EHL is detached and transferred laterally to correct the varus; the medial half is left intact and in continuity to keep extending the IP joint. This avoids the IP arthrodesis and preserves active IP extension, at the cost of a slightly weaker corrective vector from half the tendon. The Skalley series used it.
How to choose. The split transfer is favoured when preserving IP motion matters and the deforming force is not extreme. The complete transfer with IP fusion is kept for a strong dynamic deformity, or for an IP joint that is already stiff or arthritic, whose fusion is no loss. Either way the principle is the same: convert the EHL from a medial deformer into a lateral stabiliser.
Alternative Tendon Transfers and Static Ligamentoplasty
Beyond the Johnson EHL transfer, Plovanich's systematic review and Schwagten's series describe the abductor hallucis (Hawkins), reverse abductor hallucis, extensor hallucis brevis (EHB, Myerson) and first dorsal interosseous (Valtin) transfers:
- Abductor hallucis (Hawkins) transfer, dynamic. Abductor hallucis is itself one of the medial deforming forces, so releasing it from the medial base and transferring it laterally removes a deformer and adds a lateral pull. It is an option when the EHL is not the dominant deformer, and it preserves the EHL entirely.
- Reverse abductor hallucis transfer, a static ligamentoplasty. The abductor hallucis, or a slip of it, becomes a static lateral tether recreating the deficient lateral collateral and adductor buttress. It spares the EHL and the IP joint, but modern long-term data (Schwagten: about 69% satisfaction at a mean of 4 years) show that late loss of correction can occur, and patients must be counselled.
- EHB (Myerson) transfer, dynamic and EHL-sparing. The EHB is transferred laterally as a dynamic corrector while the EHL is left intact, avoiding any loss of IP or MTP extension power.
How to choose. There are no comparative trials, so the choice rests on the dominant deforming force and on whether the EHL and IP joint are to be spared. An EHL-driven bowstring favours an EHL transfer, ideally split; a supple deformity where EHL preservation is wanted favours a reverse abductor ligamentoplasty or an EHB transfer. All are combined with the necessary medial release.
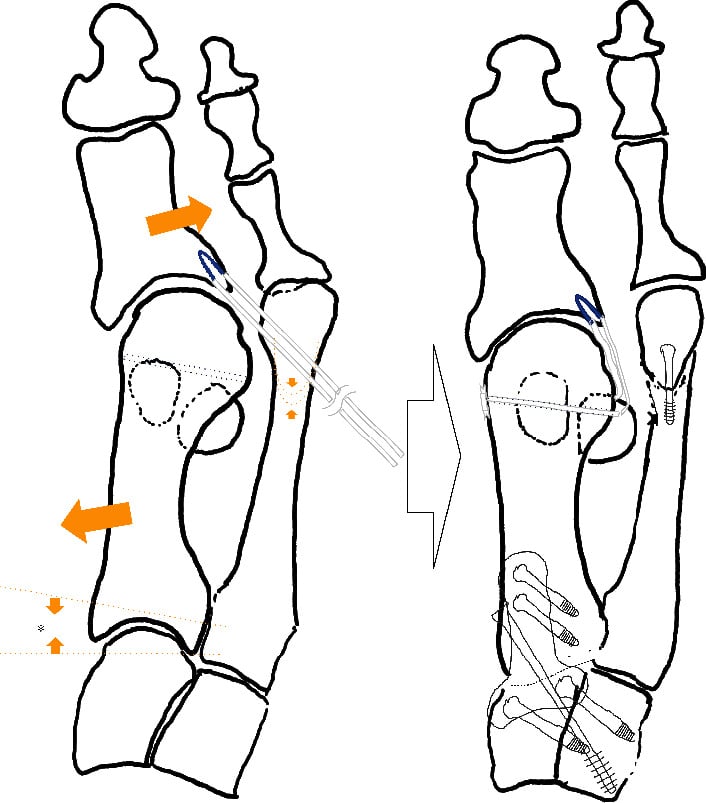
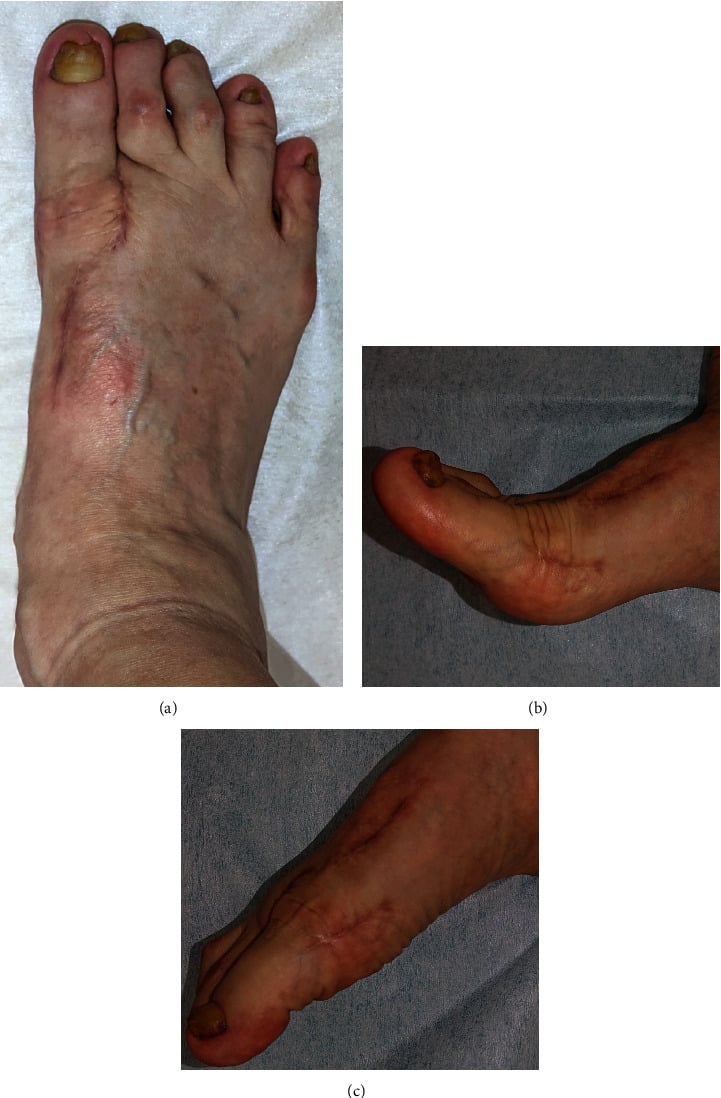
A joint-preserving alternative. The figures below, from one published report (Nekomoto), show reconstruction of the lateral collateral ligament with suture tape. Before surgery, standing views showed a hallux valgus angle of minus 24° with no intermetatarsal divergence, supporting a predominantly capsuloligamentous deformity. The bony medial prominence was reduced and the suture tape recentred the proximal phalanx over the metatarsal head. At one year the hallux valgus angle was 4° and the intermetatarsal angle 8°, with a congruent first MTP joint, maintained alignment and preserved active dorsiflexion and plantarflexion.
Complications
Of the untreated deformity. Left alone, the deformity brings the transfer metatarsalgia, shoe difficulty and reduced push-off described in the Overview, with compensatory gait patterns. Abnormal joint mechanics accelerate degenerative change, and a flexible deformity often becomes rigid through capsular contracture.
General surgical complications
- Infection: 1-3% with standard precautions, higher in revision surgery or compromised soft tissues
- Wound healing problems: the dorsal foot has thin skin and limited vascularity, and the risk rises with multiple prior operations or smoking
- Nerve injury: the dorsal cutaneous nerves are at risk at the incision, causing numbness or a neuroma
- DVT and pulmonary embolism: rare in foot surgery, but consider prophylaxis in the high-risk patient
EHL transfer. Recurrent varus was reported in 4.4% (3 of 68 feet) in a systematic review that deliberately searched for failures, all after Johnson EHL transfer, which was also the commonest procedure in that series. The risk rises with inadequate transfer tension, poor patient selection (a rigid deformity) and failure to address all the deforming forces.
- IP extension weakness: the EHL normally extends the IP joint, so IP extension is weakened, usually well tolerated; transferring the whole tendon removes it altogether, which is why the original operation fused the IP joint and the split modification keeps half the tendon extending it
- Overcorrection to valgus: rare, when the transfer is too tight or combined procedures create excessive valgus force
- Tendon pull-out or failure, when fixation is inadequate; use a strong suture technique and a bone tunnel or solid anchor
- Wound healing issues
Arthrodesis. Roukis pooled 2,818 first MTP arthrodeses across 37 studies: union 94.6%, nonunion 5.4%, and only 32.7% of the nonunions symptomatic, a symptomatic nonunion rate of 1.8%. He states explicitly that the historical figure of about 10% is inaccurate. Nonunion is more likely with smoking, poor bone quality, inadequate fixation or infection. [15]
- Malunion: 6.1%, dorsal in 87% of those; fusion in the wrong position (too much or too little dorsiflexion, persistent varus, rotation) requires revision arthrodesis or osteotomy
- Hardware complications: prominent screws or plates causing irritation, with hardware removal in 8.5%
- Transfer metatarsalgia: loss of MTP motion shifts load to the lesser metatarsals; the mechanism is documented on pedobarography, but none of the sources here quantifies it after arthrodesis for hallux varus
- Hallux IP joint arthritis, from increased stress on the IP joint over time once MTP motion is lost
- Shortening, from excessive bone resection during joint preparation
Reverse Akin osteotomy
- Nonunion: rare in metaphyseal bone
- Malunion: an incorrect wedge size causing under- or overcorrection
- Fracture of the proximal phalanx in osteopenic bone or with trauma
Preventing recurrence after correction
- Select correctly: flexible cases for soft-tissue procedures, rigid ones for arthrodesis.
- Address every deforming force; an EHL transfer alone may fail if medial contractures are not released.
- Fix securely: a strong suture technique for tendon transfers, rigid fixation for osteotomies.
- Protect the correction with splinting while it heals.
Post-operative Care and Rehabilitation
The first two weeks. A bulky compressive dressing with gauze between the hallux and second toe holds the correction, with a posterior splint or CAM boot for protection and the foot elevated above heart level. Keep the dressing clean and dry; the first change, with suture removal, is at 10-14 days. Analgesia is multimodal: paracetamol, NSAIDs if not contraindicated for bone healing, and opioids as needed for the first few days.
Weight-bearing and motion follow the procedure:
- Soft-tissue procedures (EHL transfer, releases)
- Non-weight-bearing in posterior splint or CAM boot, hallux held in valgus with gauze spacer
- First MTP arthrodesis
- Non-weight-bearing in posterior splint after screw fixation; protected weight-bearing may be allowed with rigid plate fixation (surgeon preference)
- Soft-tissue procedures (EHL transfer, releases)
- Protected weight-bearing in stiff-soled shoe or CAM boot; continue toe spacer; gentle IP joint ROM exercises from 2 weeks to prevent stiffness unless the IP joint has been fused; no forceful MTP motion until 6 weeks
- First MTP arthrodesis
- Protected weight-bearing, as tolerated with modern plate fixation, in CAM boot or stiff-soled post-operative shoe; no MTP motion; radiographs at 6 weeks
- Soft-tissue procedures (EHL transfer, releases)
- Progressive return to normal shoe wear; active MTP ROM exercises; strengthening of the intrinsic muscles
- First MTP arthrodesis
- Protected weight-bearing until radiographic union (typically 8-12 weeks), then normal shoe wear
- Soft-tissue procedures (EHL transfer, releases)
- Athletic activities at 10-12 weeks if healing is adequate
- First MTP arthrodesis
- Full activities at 12-16 weeks
After a reverse Akin osteotomy, protected weight-bearing in a stiff-soled shoe for 4-6 weeks, with radiographs at 2 and 6 weeks to assess healing.
Follow-up. Radiographs at 6 weeks, 12 weeks and 6 months check alignment, hardware and, after arthrodesis, union. Assess function (gait analysis, shoe wear, pain, satisfaction) and watch for recurrence, transfer metatarsalgia and hardware prominence.
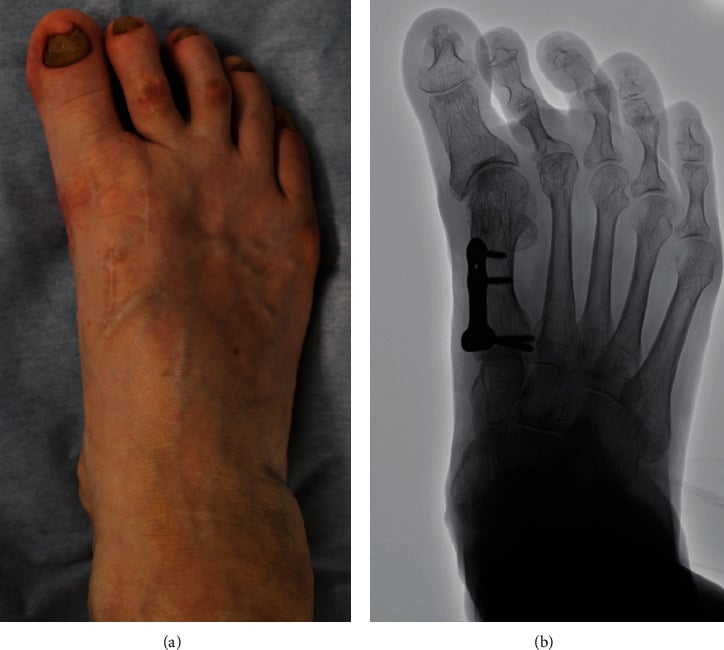
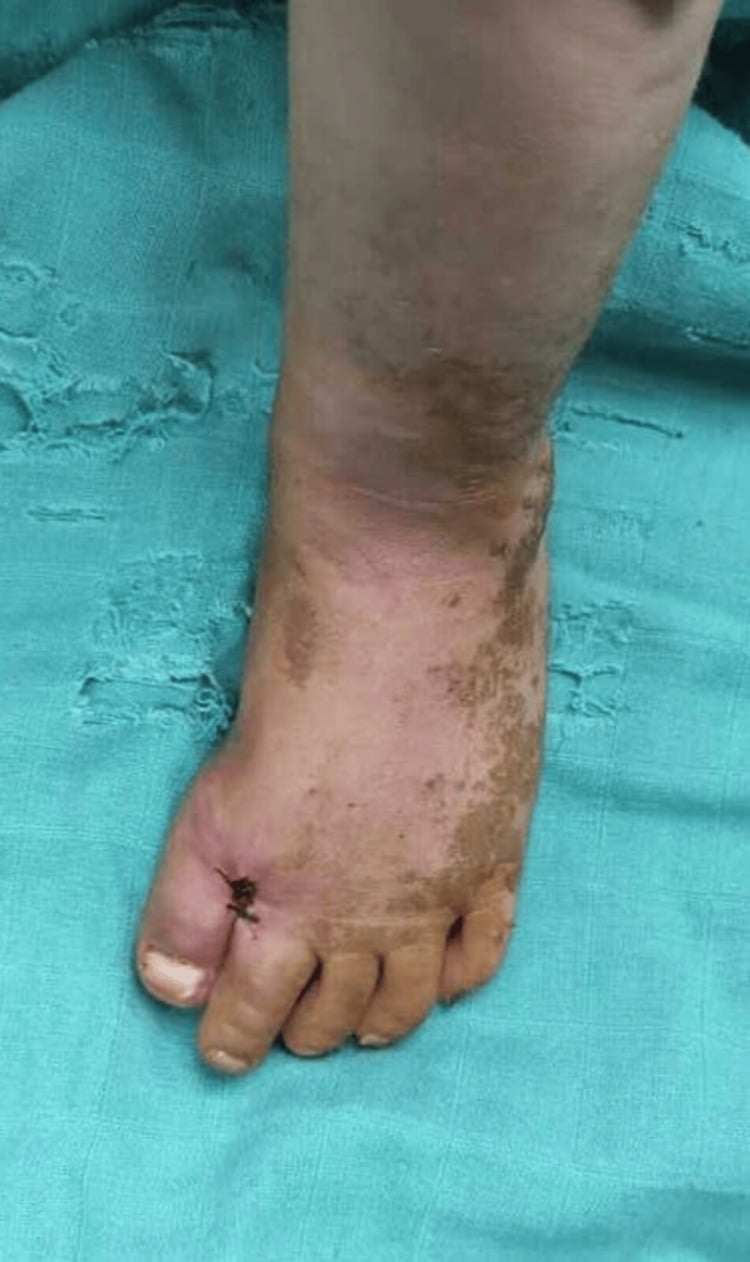
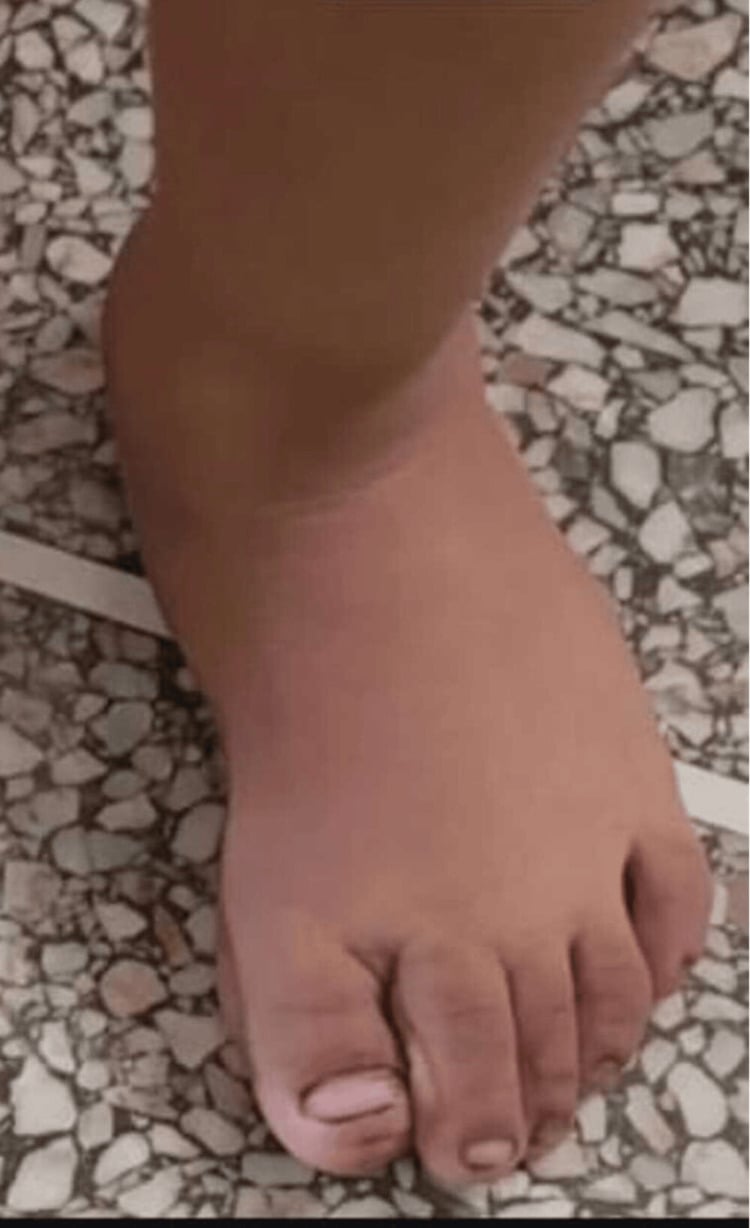
What the illustrated cases show. After congenital correction (Manni), the hallux remained centred at six weeks after temporary stabilisation, when wound condition and maintenance of correction are checked before mobilisation is advanced; at six months it remained aligned without recurrent medial drift, the early clinical goal after release and osteotomy. In the adult case report (Ortiz-Romero), standing alignment remained plantigrade at 48 months, with the hallux centred and the first web space restored under load.
Maintaining the corrected position during the healing phase is critical. A simple gauze or silicone toe spacer between the hallux and second toe provides a gentle lateral force that helps prevent early recurrence as soft tissues heal. Continue for at least 6 weeks post-operatively.
Guidelines, Registries & Global Practice
Global epidemiology:
- Hallux varus is uncommon worldwide; the dominant aetiology in adults is iatrogenic overcorrection after hallux valgus surgery, reported across surgical series at roughly 2-13% depending on technique and definition.
- Reported cohorts are overwhelmingly female, mirroring the demographics of bunion surgery.
- Congenital cases are rare and have equal sex distribution; traumatic/burn-related cases follow injury patterns and are over-represented in lower-resource and high-burn-incidence regions.
Guidance and consensus (no dedicated single-society guideline exists):
- Position relevant to hallux varus
- Algorithm by flexibility and joint status; EHL or abductor transfer for supple non-arthritic deformity, arthrodesis for rigid/arthritic
- Position relevant to hallux varus
- Emphasise prevention during hallux valgus correction (avoid over-resection, preserve fibular sesamoid); reconstruction by foot and ankle specialists
- Position relevant to hallux varus
- First MTP arthrodesis principles: congruent surface preparation, 10-15 degrees valgus and 20-25 degrees dorsiflexion, dorsal plate +/- lag screw
- Position relevant to hallux varus
- Support both dynamic (EHL/EHB) transfers and static (reverse abductor hallucis ligamentoplasty) reconstruction for flexible iatrogenic varus
- Hallux varus is not tracked as a primary outcome in arthroplasty registries (NJR, AJRR, AOANJRR, SHAR). The relevant registry-adjacent evidence is forefoot/first-ray surgery audit data showing that varus is a recognised but infrequent complication of bunion correction, and the largest synthesis of arthrodesis non-union - 2,818 procedures across 37 studies - puts it at 5.4%, with only 1.8% symptomatic, explicitly correcting the historical claim of around 10%.
- Well-resourced settings: weight-bearing radiographs, dorsal locking-plate arthrodesis, anchor/tendon-transfer reconstruction, and access to revision foot-and-ankle fellowship expertise.
- Limited-resource settings: greater reliance on clinical assessment, K-wire or crossed-screw fixation for fusion, and simpler soft-tissue procedures; congenital and burn-contracture varus form a larger share of the caseload.
Controversies & Areas of Uncertainty
No randomised data compare dynamic tendon transfers (Johnson EHL, abductor hallucis/Hawkins, EHB) with static ligamentoplasty (reverse abductor hallucis). Evidence is level IV-V with small, female-predominant cohorts; choice remains surgeon preference and local expertise.
The original Johnson procedure included first IP joint fusion to prevent clawing once the EHL is rerouted. Many surgeons now use split EHL transfer to preserve IP extension and avoid fusion, but comparative evidence for this modification is limited.
There is no universally accepted classification and no consensus threshold angle; values from "any medial deviation" to "over 10-15 degrees" appear in the literature. This hampers pooling of outcome data.
For the rigid but minimally arthritic joint, the role of osteotomy or arthroplasty/implant versus going straight to arthrodesis is unsettled; arthrodesis remains the most reliable but sacrifices motion.
The exact "safe" limits of medial eminence resection and lateral release are not precisely defined; recommendations (stay within the sagittal sulcus, preserve the fibular sesamoid, aim for slight valgus) are consensus-based rather than trial-proven.
Long-term data show meaningful late loss of correction with soft-tissue procedures (e.g. 31% sub-optimal satisfaction at mean 48 months for reverse abductor transfer), so durability and the true recurrence rate over a decade remain uncertain.
MCQ Practice Points
Q: What is the most common cause of hallux varus?
A: Iatrogenic following hallux valgus surgery - most commonly after excessive medial capsular plication, over-resection of medial eminence, over-correction of IMA, or lateral release with fibular sesamoid excision. Disruption of lateral stabilizers (adductor hallucis, lateral capsule, sesamoid complex) leads to medial deviation.
Q: What are the components of the deformity in hallux varus?
A: Medial deviation of proximal phalanx at MTP joint, supination of hallux (rotation), often combined with IPJ flexion (cock-up deformity). May be flexible (correctable passively) or rigid (fixed). Flexible deformity amenable to soft tissue procedures; rigid deformity requires bony procedures or fusion.
Q: What are the surgical options for flexible hallux varus?
A: Soft tissue procedures: EHL transfer (split or complete) to lateral proximal phalanx base, abductor hallucis release, reverse McBride (medial release, lateral repair). Johnson procedure: EHL transfer through P1 base tunnel. For rigid deformity: MTP fusion in 15° valgus, or corrective osteotomy.
Q: What is the reverse McBride procedure for hallux varus?
A: Medial soft tissue release (medial capsulotomy, abductor hallucis release) combined with lateral soft tissue reconstruction (adductor hallucis repair, lateral capsular plication). Essentially reverse of McBride bunionectomy. Effective for mild flexible deformity without MTP arthritis. Often combined with EHL transfer for better correction.
Q: What is the position of MTP fusion for hallux varus?
A: 10-15° valgus relative to first metatarsal, 20-25° dorsiflexion relative to floor (simulating toe-off), neutral rotation. Same fusion position as for hallux rigidus or severe hallux valgus. Preferred treatment for rigid hallux varus with MTP arthritis. Provides pain relief and stable push-off. High union rates with modern fixation.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 52-year-old woman presents 18 months after hallux valgus correction surgery. She complains of medial deviation of her great toe, difficulty with shoe wear, and pain at the first MTP joint. On examination, the hallux is deviated medially approximately 15 degrees. When you grasp the toe and push it laterally, it easily corrects past neutral into slight valgus. Radiographs show no arthritis but the fibular sesamoid appears absent. What is your diagnosis and management plan?”
“A 60-year-old man presents with painful hallux varus that has been progressive over 5 years. He has no history of prior surgery. On examination, the hallux is deviated medially about 20 degrees and when you attempt passive correction, the toe does not move - it is rigid. There is crepitus and pain with attempted MTP joint motion. Radiographs show narrowing of the first MTP joint space with subchondral sclerosis and osteophytes. What is your management?”
“The parents of a 3-year-old boy bring him to clinic concerned about the appearance of his right great toe, which points inward. He was born with this and it has not changed. He is walking well and has no pain. On examination, the right hallux is in about 15 degrees of varus. When you push the toe laterally, it easily corrects to neutral and beyond. There is no skin tightness or scarring. Radiographs show no bone abnormality, normal joint spaces, and the metatarsus is slightly adducted. What do you advise the parents?”
Definition
- Medial deviation of hallux at MTP joint greater than 10° (normal is 5-15° valgus)
- Measure on weight-bearing AP radiograph
- Normal hallux has slight valgus alignment
Etiology (3 Types)
- 1. Congenital: Present at birth, often with metatarsus adductus, usually flexible
- 2. Iatrogenic (MOST COMMON in adults): Post-bunion surgery 5-15% incidence
- - Excessive medial eminence resection (beyond sagittal sulcus)
- - Overtightening medial capsule
- - Fibular sesamoidectomy (loss of lateral buttress)
- - Disruption of lateral structures (LCL, adductor hallucis)
- 3. Traumatic: Burns, crush, medial soft tissue contracture
Classification (Clinical)
- FLEXIBLE: Passively corrects to neutral/valgus - soft tissue imbalance (EHL, abductor)
- RIGID: Does not correct - joint contracture/capsular fibrosis/arthritis
- Flexibility determines treatment approach - TEST PASSIVELY
Clinical Assessment
- History: Prior bunion surgery? Congenital? Trauma? Progressive?
- Exam: Varus angle, PASSIVE CORRECTION TEST (key), EHL bowstringing
- Palpate sesamoids (fibular sesamoid absent?), assess MTP ROM, crepitus
- Radiographs: Weight-bearing AP (measure angle), assess joint space, sesamoid position
Treatment Algorithm
- Conservative: Observation (congenital), shoe mods, toe spacers, splinting
- FLEXIBLE: EHL transfer (Johnson procedure) +/- abductor release +/- reverse Akin
- RIGID: First MTP arthrodesis (10-15° valgus, 20-25° dorsiflexion)
- Arthritis: Arthrodesis is definitive
EHL Transfer (Johnson)
- Indication: Flexible hallux varus, EHL bowstringing, non-arthritic joint
- Technique: Divide EHL at proximal phalanx base, transfer to lateral capsule/bone
- Fixation: Bone tunnel or suture anchor, hold in corrected position
- Outcome: 4.4% recurrence (the 69% long-term satisfaction figure is for the reverse abductor transfer)
- Complication: IP extension weakness (mild); original technique fuses the IP joint
First MTP Arthrodesis
- Indication: Rigid, arthritic, salvage for failed soft tissue procedures
- Position: 10-15° valgus, 20-25° dorsiflexion relative to ground
- Fixation: Dorsal plate (preferred) or crossed screws
- Union: 94.6% pooled (5.4% nonunion, 1.8% symptomatic)
- Outcome: 93% good/excellent in the cited fusion series; MTP motion lost
Prevention (During Bunion Surgery)
- Limit medial eminence resection within sagittal sulcus
- Preserve fibular sesamoid (avoid routine sesamoidectomy)
- Balance soft tissue releases (medial and lateral proportional)
- Avoid overtightening medial capsule
- Target 10-15° valgus, NOT neutral
- Check intraop sesamoid position (should be centered)
Exam Pearls
- Passive correction test = THE key clinical maneuver (flexible vs rigid)
- Iatrogenic is most common cause in adults (5-15% after bunion surgery)
- Congenital cases usually improve with growth - observation first
- EHL transfer for flexible, arthrodesis for rigid - simple algorithm
- Fusion position critical: 20-25° dorsiflexion (too much = heel walk, too little = no heel rise)
Evidence Base
Iatrogenic Hallux Varus - Cause, Prevention, Correction (Classic)
- Foundational paper describing acquired hallux varus as a complication of bunion surgery
- Excessive medial eminence resection, fibular sesamoidectomy and overtight medial capsulorrhaphy identified as causes
- Loss of the fibular sesamoid removes the lateral buttress and predisposes to medial drift
- Hawkins abductor hallucis tendon transfer first described as a correction technique
EHL Transfer for Hallux Varus - Original Description (Johnson)
- Original description of the Johnson EHL transfer for dynamic hallux varus
- Fifteen affected great toes treated; deformity attributed to dynamic tendon imbalance after McBride-type surgery
- EHL routed beneath the intermetatarsal ligament into the base of the proximal phalanx, with first IP joint arthrodesis
- Overall satisfactory correction of the varus deformity reported in the series
First MTP Arthrodesis with Plate Fixation - Outcomes
- 47 patients (58 feet) underwent first MTP fusion with a Vitallium dorsal plate
- 98% (57 of 58 feet) successfully fused; 93% reported good or excellent results
- Cone- or cup-shaped reamers used to create congruous, broadly apposed surfaces
- Plate removal required in only 7%; one nonunion with plate breakage and one delayed union
Congenital Hallux Varus (Classic Description)
- Classic surgical description of congenital hallux varus and its anatomy
- Deformity associated with short, broad first metatarsal, accessory bones and medial soft-tissue tethering
- Surgical correction addresses the medial tether and any duplicated/abnormal osseous structures
- Provides the historical basis for distinguishing congenital from acquired hallux varus
Operative Treatment of Acquired Hallux Varus - Algorithm
- 42 patients (45 feet) with acquired hallux varus; 36 followed prior hallux valgus surgery
- Procedure selection driven by aetiology, age/activity, and the site of primary deformity
- Treatments ranged from soft-tissue release with tendon transfer (17) to arthrodesis (17) and resection arthroplasty (7)
- Pain, shoe-wear difficulty and MTP instability improved across all treatment groups; treatment algorithm proposed
Soft-Tissue Release with Tendon Transfer for Flexible Hallux Varus
- Systematic review of 8 studies, 52 patients (all female), 68 feet treated for flexible iatrogenic hallux varus
- Tendon transfers: Johnson EHL with IP arthrodesis (41 feet), Hawkins abductor (9), reverse Hawkins (7), Valtin (7), Myerson EHB (4)
- Overall complication rate 16.2% (11/68); recurrent varus in only 4.4% (3 feet), all after Johnson EHL transfer
- Sustainable correction achievable with capsular release plus a variety of tendon transfers
Reverse Abductor Hallucis Transfer - Long-Term Results
- Prospective observational study, 16 female patients, 100% follow-up (mean 48 months, range 10-101)
- Success satisfaction rate of 69% (11/16); satisfaction correlated strongly with maintained alignment (r=0.77)
- Coronal/sagittal malalignment were the most disabling complications
- Effective for supple iatrogenic varus but patients must be counselled that late loss of correction can occur
References
-
Mann RA, Coughlin MJ. Hallux varus. In: Mann RA, Coughlin MJ, editors. Surgery of the Foot and Ankle. 6th ed. St. Louis: Mosby; 1993. p. 321-334.
-
Coughlin MJ, Saltzman CL, Anderson RB. Mann's Surgery of the Foot and Ankle. 9th ed. Philadelphia: Elsevier; 2014.
-
Edelman RD. Iatrogenic hallux varus. Foot Ankle Surg. 2015;21(4):223-227. doi:10.1016/j.fas.2015.07.003
-
Farmer AW. Congenital hallux varus. Am J Surg. 1958;95(2):274-278. doi:10.1016/0002-9610(58)90515-4
-
Hutton WC, Dhanendran M. The mechanics of normal and hallux valgus feet: a quantitative study. Clin Orthop Relat Res. 1981;(157):7-13.
-
Hawkins FB. Acquired hallux varus: cause, prevention and correction. Clin Orthop Relat Res. 1971;76:169-176.
-
Skalley TC, Myerson MS. The operative treatment of acquired hallux varus. Clin Orthop Relat Res. 1994;(306):183-191.
-
McElvenny RT. Hallux varus. Q Bull Northwest Univ Med Sch. 1941;15:277-280.
-
Johnson KA, Spiegl PV. Extensor hallucis longus transfer for hallux varus deformity. J Bone Joint Surg Am. 1984;66(5):681-686.
-
Shereff MJ, Bejjani FJ, Kummer FJ. Kinematics of the first metatarsophalangeal joint. J Bone Joint Surg Am. 1986;68(3):392-398.
-
Coughlin MJ, Roger A. Mann Award. Juvenile hallux valgus: etiology and treatment. Foot Ankle Int. 1995;16(11):682-697.
-
Johnson KA, Spiegl PV. Extensor hallucis longus transfer for hallux varus deformity. J Bone Joint Surg Am. 1984;66(5):681-686.
-
Citation unverifiable - do not rely on it. This slot previously read "Chacon YP, Lam T. Extensor hallucis longus transfer for correction of hallux varus: long-term follow-up. J Foot Ankle Surg. 2012;51(6):687-691". No such paper could be found: J Foot Ankle Surg 2012;51(5):687-689 is Sundararajan PP, "Combined arthroscopic and fluoroscopic guidance in the atraumatic treatment of posterior ankle impingement syndrome" (PMID 22766192), an unrelated subject, and the quoted DOI does not resolve to the described article. Every claim that formerly cited this reference has been rewritten to rest on a verified source.
-
Coughlin MJ, Abdo RV. Arthrodesis of the first metatarsophalangeal joint with Vitallium plate fixation. Foot Ankle Int. 1994;15(1):18-28. doi:10.1177/107110079401500105
-
Roukis TS. Nonunion after arthrodesis of the first metatarsophalangeal joint: a systematic review. J Foot Ankle Surg. 2011;50(6):710-713. doi:10.1053/j.jfas.2011.06.010
-
Akin OF. The treatment of hallux valgus: a new operative procedure and its results. Med Sentinel. 1925;33:678-683.
-
Vandeputte G, Dereymaeker G, Steenwerckx A, Peeraer L, Broos P. The Weil osteotomy of the lesser metatarsals: a clinical and pedobarographic follow-up study. Foot Ankle Int. 2000;21(5):370-374. doi:10.1177/107110070002100502
-
Leemrijse T, Hoang B, Maldague P, Docquier PL, Valtin B. A new surgical procedure for iatrogenic hallux varus: reverse transfer of the abductor hallucis tendon. A report of 7 cases. Acta Orthop Belg. 2008;74(2):227-234.
-
Politi J, John H, Njus G, Bennett GL, Kay DB. First metatarsal-phalangeal joint arthrodesis: a biomechanical assessment of stability. Foot Ankle Int. 2003;24(4):332-337. doi:10.1177/107110070302400408