A Viral Fingertip Infection that Must NOT Be Incised
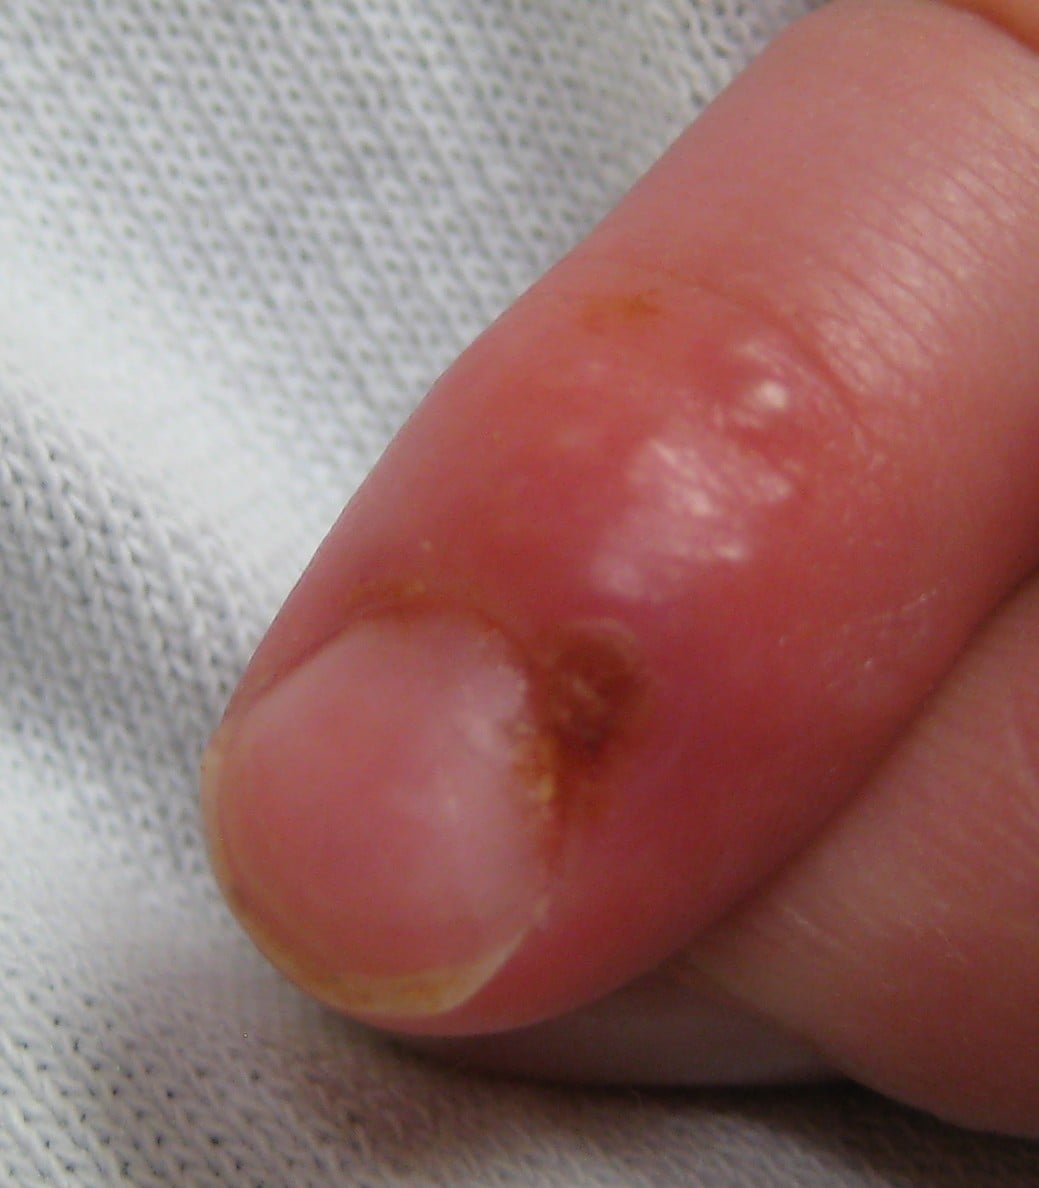
- Herpetic whitlow is a HERPES SIMPLEX VIRUS infection of the FINGERTIP (pulp/periungual skin), caused by HSV-1 or HSV-2; it characteristically produces a PRODROME of pain, tingling or burning followed by GROUPED VESICLES on an ERYTHEMATOUS base, with pain often OUT OF PROPORTION to the modest swelling.
- It classically affects YOUNG CHILDREN (autoinoculation from oral HSV - e.g. thumb-sucking/herpetic gingivostomatitis), HEALTHCARE WORKERS exposed to oral secretions (dentists, anaesthetists, respiratory staff - now much less common with universal glove use), and adults with genital HSV (HSV-2).
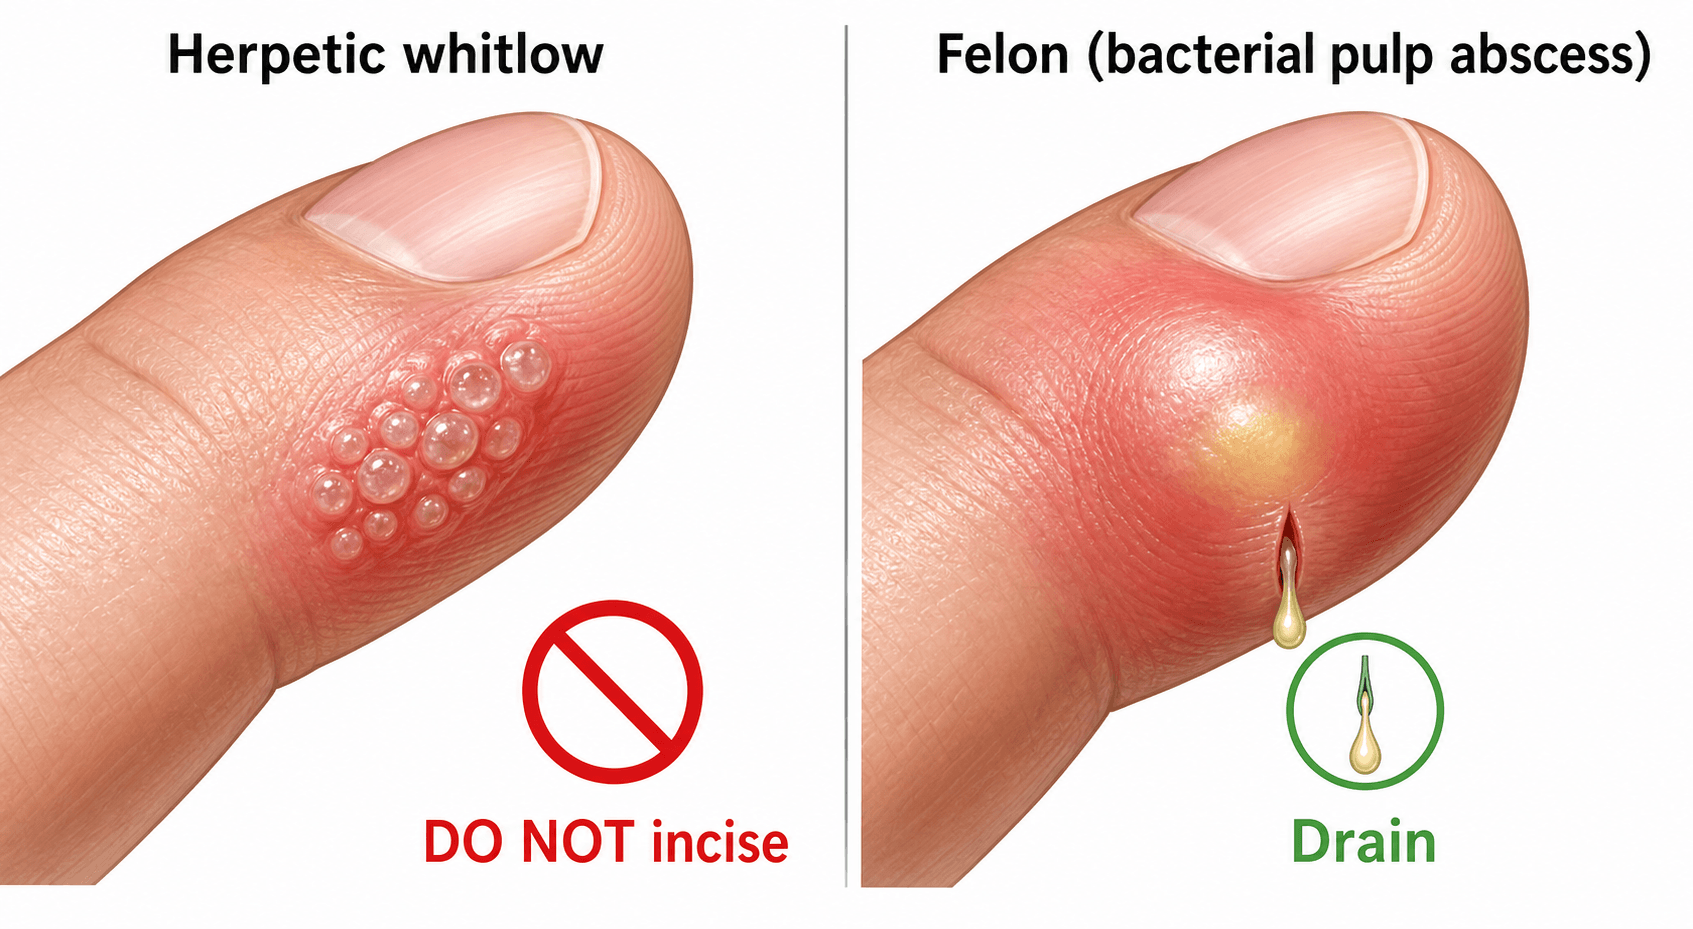
- THE KEY POINT: herpetic whitlow MUST NOT be treated like a felon - it must NOT be INCISED AND DRAINED. The fluid is viral (not pus), and incising it risks BACTERIAL SUPERINFECTION, delayed healing and potentially SYSTEMIC viral spread - a dangerous error, especially in the immunocompromised.
- It is therefore essential to DIFFERENTIATE it from a bacterial FELON (a purulent abscess of the closed pulp space that DOES need incision and drainage) and from acute paronychia: the grouped clear vesicles, the non-purulent vesicular fluid, the prodrome and the relatively soft (non-tense) pulp point to a viral whitlow.
- Diagnosis is usually CLINICAL; it can be confirmed by a TZANCK smear (multinucleated giant cells), HSV PCR (most sensitive/specific), viral culture or direct fluorescent antibody from vesicle fluid - useful when atypical or to avoid an inappropriate incision.
- Management is SUPPORTIVE - analgesia and keeping the lesion clean and COVERED (to prevent autoinoculation/transmission) - and the condition is SELF-LIMITING over about 2-4 weeks; ORAL ANTIVIRALS (aciclovir/valaciclovir) shorten and reduce symptoms, particularly when started EARLY, and are important in severe, recurrent or immunocompromised cases; antibiotics are reserved for proven SECONDARY bacterial infection.
- “Grouped CLEAR vesicles on an erythematous fingertip + pain out of proportion + prodrome = herpetic whitlow (HSV).
- “DO NOT incise & drain (it is viral, not pus) - incision risks superinfection/systemic spread. Felon (purulent pulp abscess) IS drained.
- “Self-limiting (~2-4 weeks); antivirals (aciclovir) help if early/severe/recurrent/immunocompromised; keep covered to prevent autoinoculation.
Aetiology & Presentation
The infection. Herpetic whitlow is inoculation of herpes simplex virus into the skin of the fingertip, the pulp or periungual skin, through a breach. HSV-1 predominates in children and in healthcare workers; HSV-2 affects adults via genital contact.
Who gets it. It classically affects three groups:
- Young children, who autoinoculate from oral herpes, for example by thumb-sucking with herpetic gingivostomatitis
- Healthcare workers exposed to oral or respiratory secretions (dentists, anaesthetists, respiratory therapists): historically a classic occupational infection, now much less common with universal glove use
- Adults with genital HSV (HSV-2)
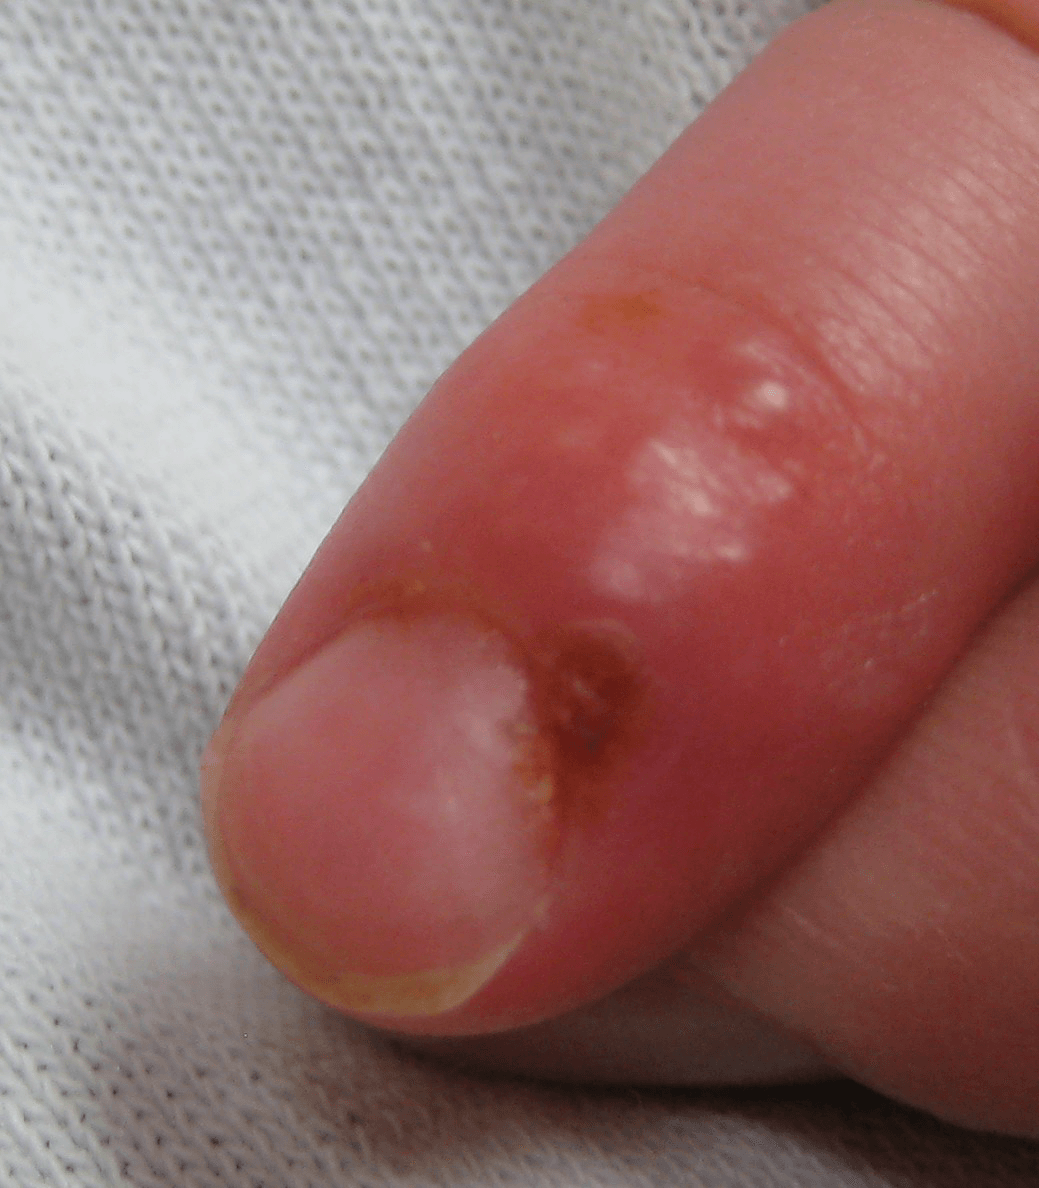
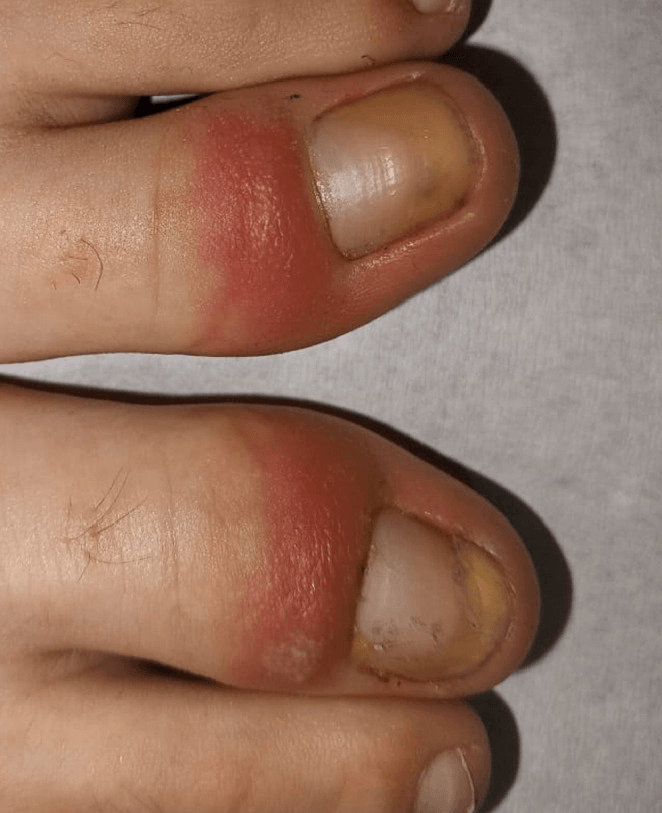
The lesion. A prodrome of localised pain, tingling or burning comes first. Grouped vesicles then appear on an erythematous, oedematous base; their fluid is clear at first and then cloudy, and they may coalesce. The pain is often out of proportion to the modest swelling.
Systemic features. Low-grade fever, lymphangitis and epitrochlear or axillary lymphadenopathy may occur alongside the finger lesion.
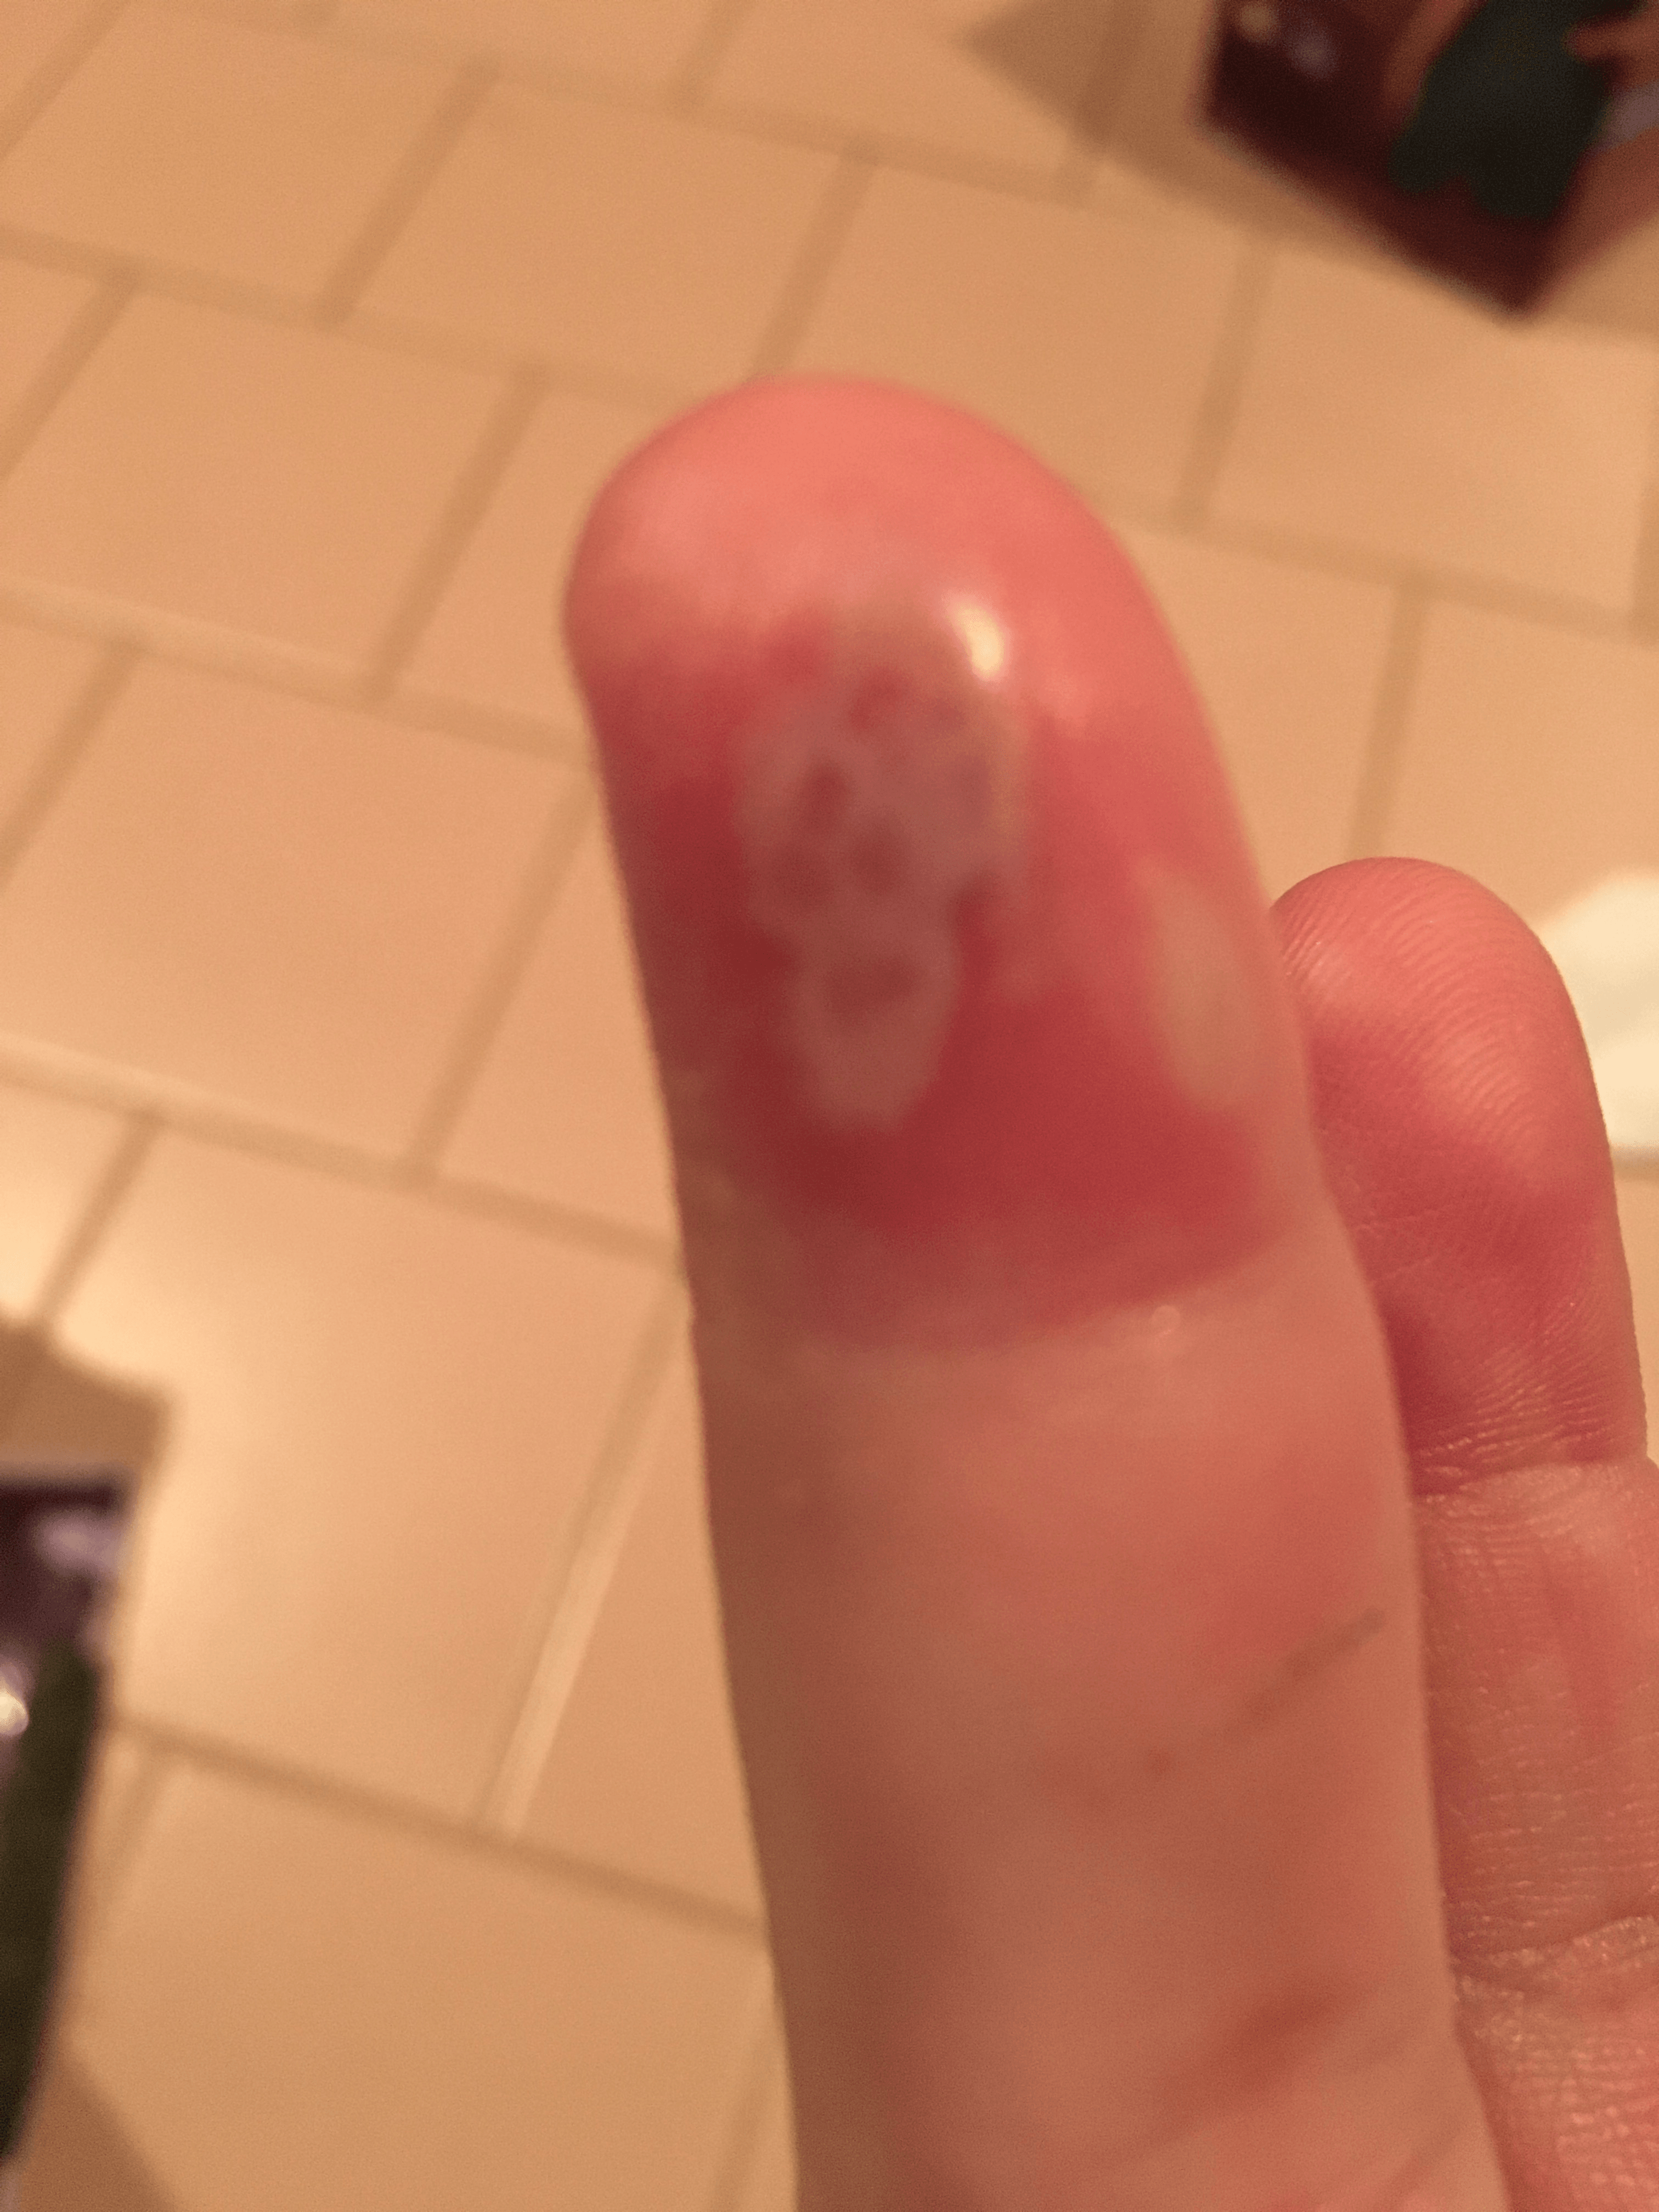
The Natural History: Stages, Timeline and Infectivity
The course. Incubation runs roughly 2 to 20 days (commonly 2 to 7) after inoculation. The whitlow then follows a predictable, self-limiting course:
- Prodrome - localised pain, tingling or burning before any rash
- Vesicular stage - grouped vesicles, clear then cloudy, which may coalesce and ulcerate; this is the most painful and the most infectious phase
- Crusting and healing - the vesicles dry, crust and re-epithelialise
- Resolution - over about 2 to 4 weeks, usually without scarring
The passage from prodrome through vesicle and erosion to crust takes roughly two weeks, and the lesion sheds virus throughout.
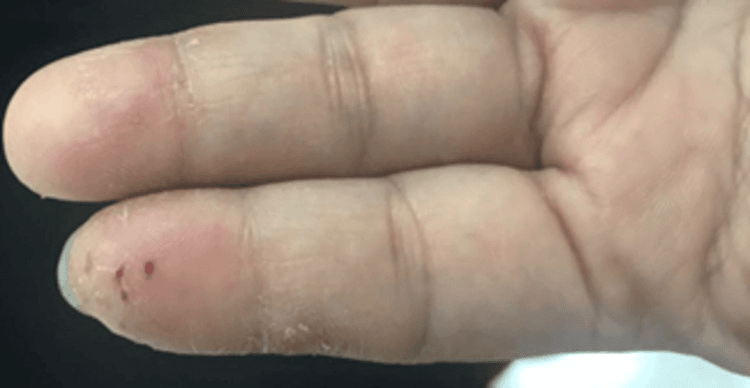
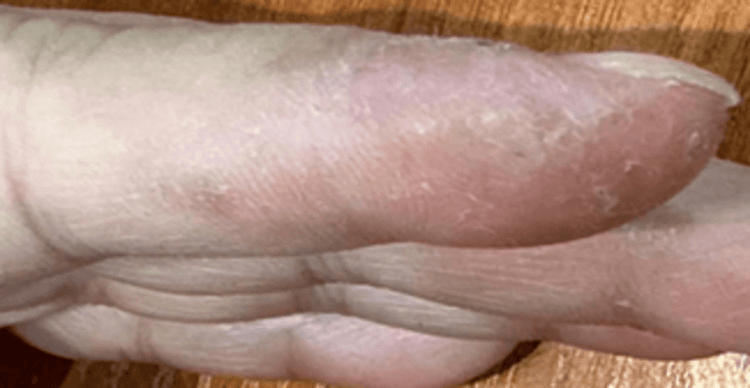
Infectivity and return to work. Lesions are infectious until fully crusted and healed. An affected healthcare worker should avoid direct patient contact, or keep the lesion securely covered with a glove over an occlusive dressing, until healed; the same covering prevents the patient's own autoinoculation.
Latency and recurrence. The virus retreats to the sensory ganglion of that digit and persists there, so recurrence is possible. A substantial minority of patients, reported across series in the region of a fifth to a half, will have at least one further episode. Recurrences are in the same finger and are usually milder and shorter, often heralded by the same prodromal tingle.
Diagnosis & Management
Diagnosis. It is usually clinical, from the grouped vesicles, the prodrome and the non-purulent appearance. When the picture is atypical, or to avoid an inappropriate incision, confirm HSV from vesicle fluid by one of:
- Tzanck smear, a Giemsa-stained smear from the vesicle base showing multinucleated giant cells with nuclear moulding and ground-glass chromatin; the classic rapid confirmation, five minutes with no laboratory wait
- HSV PCR, the most sensitive and specific
- Viral culture
- Direct fluorescent antibody
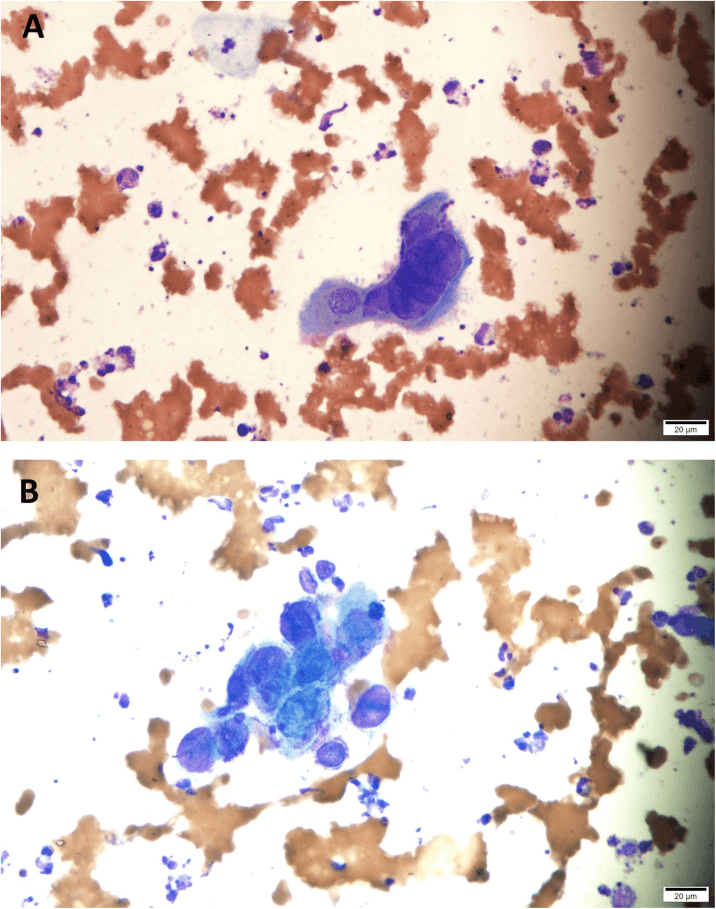
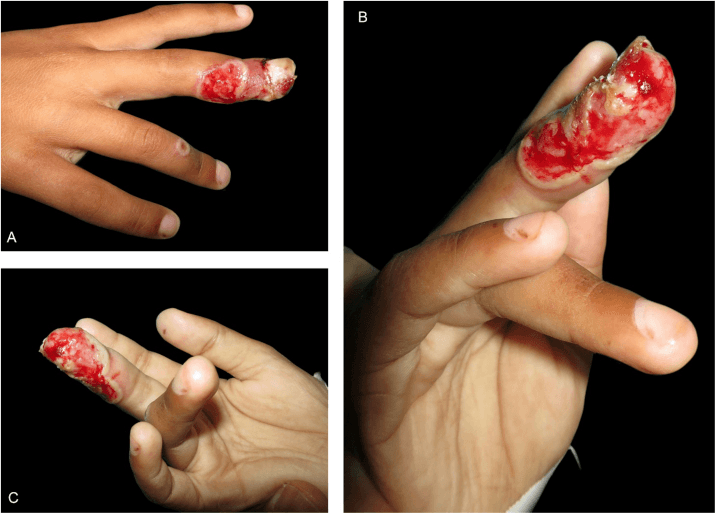
Do not incise and drain: it is the cardinal rule. Incising a herpetic whitlow can cause bacterial superinfection, delayed healing and a risk of systemic viral dissemination, which is dangerous in the immunocompromised. Reports describe the lesion being misdiagnosed as a bacterial whitlow and incised, or, in children, mistaken for non-accidental injury (cigarette burns).
Supportive care. Management is supportive: analgesia, and keeping the lesion clean and covered with a dry dressing. Covering limits autoinoculation, to the eye (herpetic keratitis) and genitals, and transmission to others. Antibiotics are reserved for a proven secondary bacterial infection.
Prescribing the antiviral: dose, window and when it is pointless
What they do. Oral aciclovir or valaciclovir shortens the episode and the symptoms, especially when started early, and is indicated in severe, recurrent or immunocompromised patients.
The window. Aciclovir inhibits viral replication, so it works while the virus is still replicating: within about 48 to 72 hours of symptom onset, and ideally in the prodrome, before the vesicles erupt. Recognising the prodrome is what makes antiviral therapy effective rather than cosmetic. Started at day seven in a crusting lesion it does essentially nothing, and offering it then is treatment for the clinician rather than the patient.
The recurrer. The prodromal tingle that heralds a recurrence is what makes patient-initiated early treatment practical: the patient who knows the sensation can start at the first tingle, inside the effective window, without waiting for an appointment. Counsel for this at the first episode rather than at the second.
Regimens. These are the standard mucocutaneous HSV regimens; check the local formulary.
- Aciclovir 400 mg orally five times daily for around 7 to 10 days is the commonly used course, adjusted for renal impairment, since aciclovir is renally cleared
- Valaciclovir (twice daily) or famciclovir are better-absorbed, less frequent alternatives that suit adherence
- Topical aciclovir alone is not adequate for an established whitlow; it is the systemic drug that matters
- For frequent recurrences, suppression is the approach rather than episodic treatment: continuous lower-dose aciclovir or valaciclovir, reviewed periodically
Escalation. Intravenous aciclovir is for the significantly immunocompromised patient, for extensive or systemic disease, or where there is any suggestion of dissemination. Immunocompromised whitlow runs wider and longer, and this group is the reason the no-incision rule is not merely a technicality.
The Wider Differential of a Vesicular or Blistered Fingertip
The unifying rule. The headline distinction is whitlow against the bacterial pus mimics, felon and paronychia, but a vesicular or blistered fingertip has a wider differential worth knowing. The safe rule is that a vesicular lesion should not be incised as if it were an abscess until HSV is excluded.
Whitlow or felon. The treatments are opposite. A felon is a tense, throbbing, purulent abscess of the closed pulp space that needs incision and drainage plus antibiotics; acute paronychia, pus in the nail fold, needs drainage with or without antibiotics. What points to a viral whitlow is the prodrome, the grouped clear vesicles, the non-purulent fluid and a relatively soft, non-tense pulp.
- Discriminating clue
- Prodrome; grouped CLEAR vesicles on erythema; pain out of proportion; non-purulent
- What it means for management
- DO NOT INCISE - drainage risks bacterial superinfection and prolongs it. Dressing, analgesia and early oral aciclovir; self-limiting
- Discriminating clue
- Tense PURULENT pulp abscess / pus in the nail fold
- What it means for management
- This one DOES need incision and drainage plus antibiotics - a felon left undrained can go on to pulp necrosis or osteomyelitis of the distal phalanx
- Discriminating clue
- Tense superficial blister with PUS over the volar pad, usually in children
- What it means for management
- (bacterial - drain + antibiotics)
- Discriminating clue
- Vesicles on hands AND feet plus oral ulcers; systemic, child
- What it means for management
- (viral - supportive)
- Discriminating clue
- Animal (sheep/cattle) contact; a single papulo-nodule
- What it means for management
- (viral - self-limiting)
- Discriminating clue
- ITCHY not painful, exposure/atopy; or a clear trauma/heat history
- What it means for management
- Neither infective nor surgical - emollients, topical steroid or removal of the irritant; the itch-rather-than-pain history is what redirects you
Mnemonics & Memory Aids
WHITLOW
Hook:Every letter of WHITLOW says: viral, don't cut it, cover it, antivirals.
CLEAR vs PUS
Hook:CLEAR vesicles = leave it (viral); PUS = drain it (felon).
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“A patient presents with a painful, blistered, red fingertip. How do you tell a herpetic whitlow from a felon, and why does it matter?”
“Who gets herpetic whitlow, how would you treat it, and what complications would you warn about?”
What it is
- HSV-1/HSV-2 infection of the fingertip (pulp/periungual)
- Prodrome (pain/tingling) → grouped vesicles on erythema; pain out of proportion
- At risk: children (oral autoinoculation), healthcare workers, adults with genital HSV
Differentiation
- Whitlow: grouped CLEAR vesicles, non-purulent (viral)
- Felon: tense PURULENT closed-pulp abscess (bacterial) - needs I&D
- Confirm HSV if unsure: Tzanck, PCR, culture, DFA
Management
- DO NOT incise & drain (risks superinfection/systemic spread)
- Supportive: analgesia, keep covered (prevent autoinoculation); self-limiting ~2-4 weeks
- Oral aciclovir/valaciclovir if early/severe/recurrent/immunocompromised; antibiotics only for 2ndary infection
Complications
- Autoinoculation (eye - herpetic keratitis; genitals)
- Secondary bacterial infection; systemic spread (immunocompromised)
- Recurrence (latency in sensory ganglion)
Evidence & Key Studies
Paediatric recurrent herpetic whitlow
- A child's recurrent herpetic whitlow was initially mistaken for a bacterial whitlow and treated with incision and drainage, and later misattributed to cigarette burns prompting a child-protection referral.
- Correct diagnosis was made by scraping and viral culture, with recovery after topical and systemic aciclovir; recurrence occurred years later.
- Highlights the danger of incorrect diagnosis and inappropriate incision, the risk of cross-infection, and the importance of recognising HSV - especially to protect immunocompromised contacts.
Herpetic whitlow associated with an eating disorder: a case report
- Herpetic whitlow is a localised cutaneous HSV-1/HSV-2 infection of the fingers that can be recurrent, here linked to autoinoculation behaviour.
- It presented as an eroded group of vesicles on an erythematous base and was diagnosed clinically from history and examination.
- It resolved within a week of topical and systemic aciclovir, illustrating the supportive/antiviral (non-surgical) management.
The danger of misdiagnosis and inappropriate incision (and the diagnosis by viral culture, treatment with aciclovir and tendency to recur) comes from the cited Patel case report, and the HSV-1/HSV-2 aetiology, grouped-vesicle presentation, clinical diagnosis and aciclovir response from the cited Aljehani report. The no-incision rule and the felon/paronychia differentiation are standard hand-surgery teaching, as are the antiviral regimens and treatment window, the escalation to intravenous therapy in the immunocompromised, and the recurrence counselling. (See also Felon, Paronychia and Flexor Tenosynovitis.)