90% Posterior | Reduce within 6 Hours | Sciatic Nerve at Risk
- Posterior dislocation is most common (90%) - mechanism is dashboard injury (knee hitting dashboard = flexed hip)
- Sciatic nerve at risk in posterior dislocation (10-20%) - peroneal division most vulnerable
- 6-hour golden window - AVN risk increases significantly if reduction delayed beyond 6 hours
- Associated fractures common - femoral head (Pipkin), acetabulum (posterior wall), femoral neck
- CT post-reduction mandatory to assess concentric reduction and associated fractures
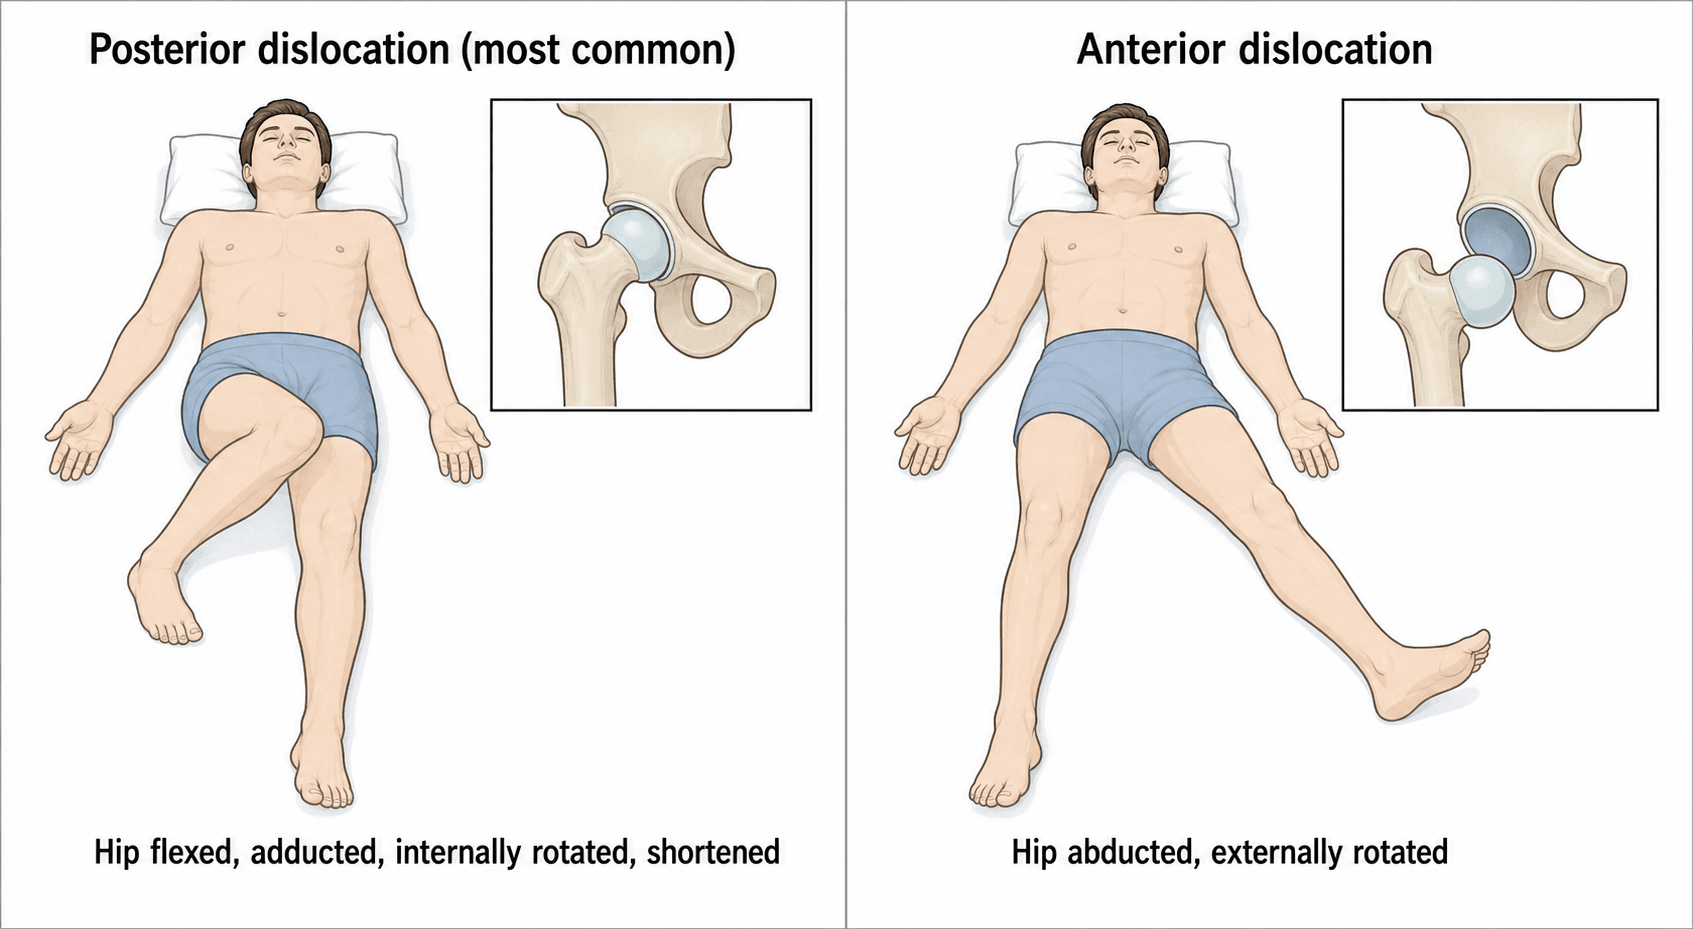
- “Posterior: leg shortened, adducted, internally rotated. Anterior: externally rotated, abducted
- “Sciatic nerve palsy: most recover by 2 years, explore if no recovery by 6 months
- “Pipkin I and II = different - Pipkin I below fovea (ORIF), Pipkin II above fovea (excise if small)
- “Thompson-Epstein classification for posterior; Epstein classification for anterior
Overview and Epidemiology
Traumatic dislocation of a native hip is a true orthopaedic emergency. The femoral head's blood supply is stretched for as long as the head sits out of the socket, the sciatic nerve lies directly behind the joint it has just left, and the energy needed to dislocate a healthy hip commonly injures the femoral head (Pipkin fracture), the acetabulum (posterior wall), the femoral neck (15%) and the knee (PCL, patella) as well. The three things to get right are the time to reduction, the sciatic nerve and the associated injuries, and each is taken in turn below.
Who. Young adults after high-energy trauma, men about twice as often as women (2:1) because of high-risk activities. A healthy native hip rarely dislocates; the far commoner hip dislocation is the prosthetic one, which is a different topic.
Mechanism. The force vector determines the direction of dislocation.
- Motor vehicle accident - the most common, the classic dashboard injury
- High-energy sport - rugby, American football, skiing
- Industrial accidents
- Fall from height
Anatomy and Mechanism
A stable joint. The hip is a ball-and-socket joint that is inherently stable, and it takes significant force to dislocate. Stability comes from bony congruity, the acetabular labrum, the strong capsular ligaments (iliofemoral, pubofemoral and ischiofemoral) and the surrounding muscles.
Blood supply of the femoral head. The retinacular vessels of the medial femoral circumflex artery carry most of it, and they are the vessels a dislocation damages.
- Source
- Profunda femoris
- Contribution
- 80-90% of head
- Clinical Relevance
- Damaged in dislocation - AVN risk
- Source
- Profunda femoris
- Contribution
- Minimal
- Clinical Relevance
- Minor contribution
- Source
- Obturator artery
- Contribution
- 10-20% (variable)
- Clinical Relevance
- More important in children
- Source
- Metaphyseal
- Contribution
- Variable
- Clinical Relevance
- May be compromised
Why dislocation causes AVN. Dislocation stretches or tears the retinacular vessels that supply the femoral head, and for as long as the head stays out the ischaemia continues. The figures that turn this into a rule about time are given with the management algorithm below.
The sciatic nerve. It leaves the pelvis through the greater sciatic foramen below piriformis, passes directly posterior to the hip joint lying on the gemelli and obturator internus, and divides into tibial and peroneal divisions. A posterior dislocation stretches it, and the nerve is injured in 10-20% of posterior dislocations. The peroneal division is injured more than the tibial: it lies more lateral, is tethered at the sciatic notch and at the fibular head, and is less mobile. The clinical picture is a foot drop from weak dorsiflexion, with numbness over the dorsum of the foot and the lateral leg. Document sensation and motor function before and after reduction.
Posterior dislocation (90%). The dashboard injury: knee flexed, hip flexed, the force transmitted along the femur and the head driven out posteriorly. The more adducted the hip, the more superior the exit. The injuries that travel with it are the posterior wall fracture and the sciatic nerve palsy.
Anterior dislocation (10%). Forced abduction with external rotation. With the hip flexed the head comes to lie inferiorly (the obturator type); with the hip extended it lies superiorly (the pubic type). The femoral vessels are at risk, rarely, and the associated bony injury is an impaction fracture of the femoral head.
Classification Systems
Posterior dislocations are graded by Thompson and Epstein, femoral head fractures by Pipkin and anterior dislocations by Epstein. In practice the working split is simpler: a simple dislocation is reduced urgently and a complex dislocation (one with a fracture) is reduced and then fixed definitively, with the post-reduction CT deciding whether the wall or the head needs fixation.
Thompson-Epstein Classification (Posterior)
- Description
- Simple dislocation, no/minimal fracture
- Treatment
- Closed reduction, conservative
- Description
- Posterior wall rim fracture (small)
- Treatment
- Closed reduction, assess stability
- Description
- Large posterior wall fracture (unstable)
- Treatment
- ORIF posterior wall
- Description
- With acetabular floor fracture
- Treatment
- ORIF acetabulum
- Description
- With femoral head fracture (Pipkin)
- Treatment
- Pipkin classification guides treatment
Clinical Assessment
History. The mechanism and its force vector (motor vehicle accident, dashboard, sport), the time of injury because the 6-hour rule runs from it, associated injuries (polytrauma, knee), whether the hip is native or prosthetic, and anticoagulation for the bleeding risk.
Examination. Hip dislocation often occurs in polytrauma, where ATLS takes priority: complete the primary and secondary survey, and log-roll to assess pelvic stability. The deformity is diagnostic and the limb position names the direction, with a leg length discrepancy to match. Record the neurovascular status - the sciatic nerve (peroneal division) behind a posterior dislocation, the femoral nerve and lateral cutaneous nerve in front of an anterior one - and examine the knee for the PCL and patellar injuries of a dashboard strike. An anterior dislocation may leave the hip slightly flexed.
- Posterior
- Shortened, adducted, IR (SAID)
- Anterior
- Abducted, externally rotated
- Posterior
- Flexed
- Anterior
- May be extended
- Posterior
- Not anteriorly (empty)
- Anterior
- Palpable in groin (bulge)
- Posterior
- Sciatic (peroneal)
- Anterior
- Femoral, lateral cutaneous
- Posterior
- 90%
- Anterior
- 10%
SAIDPosterior Hip Dislocation Position
Hook:The patient SAID 'my knee hit the dashboard' - leg is Short, Adducted, Internally rotated, from Dashboard injury!
The single most dangerous differential is a coexisting ipsilateral femoral neck fracture. If the neck is fractured, closed reduction of the dislocation can convert a salvageable injury into a displaced neck fracture with devastating AVN risk. Scrutinise the neck on the pre-reduction film, and if there is any doubt obtain CT or proceed to open reduction.
- Discriminating Features
- Shortened, adducted, internally rotated (SAID); empty acetabulum
- Key Imaging
- AP pelvis: head superolateral, smaller apparent head
- Why It Matters
- Time-critical reduction to limit AVN
- Discriminating Features
- Abducted, externally rotated; head palpable in groin
- Key Imaging
- AP pelvis: head infero/anteromedial, larger apparent head
- Why It Matters
- Different reduction vector; femoral vessel proximity
- Discriminating Features
- Shortened, externally rotated; unable to straight-leg raise
- Key Imaging
- AP/lateral hip; CT if occult
- Why It Matters
- Closed reduction of a coexisting dislocation can displace/comminute the neck - catastrophic
- Discriminating Features
- Shortened, externally rotated; elderly low-energy
- Key Imaging
- AP hip/pelvis radiograph
- Why It Matters
- No dislocation; different fixation pathway
- Discriminating Features
- Pain, reduced weight-bearing; head may be central/subluxed
- Key Imaging
- Judet views + CT
- Why It Matters
- May be central fracture-dislocation; staged reconstruction
- Discriminating Features
- Surgical scar, known arthroplasty, low-energy mechanism
- Key Imaging
- Radiograph shows implant
- Why It Matters
- Prosthetic instability has a separate work-up and reduction risk profile
Investigations
Imaging Protocol
Diagnosis usually obvious. Look for associated fractures: posterior wall, femoral head, femoral neck; check Shenton's line. Do not delay reduction for extensive imaging.
Judet views if stable. Do not delay reduction - X-ray after if unstable patient.
Assess: concentric reduction, incarcerated fragments, femoral head impaction, posterior wall size, occult femoral neck fracture. This dictates further treatment.
Suspected labral pathology, soft tissue incarceration, early AVN assessment. Not urgent.
Reading the AP pelvis. The dislocated head is the wrong size as well as in the wrong place, because its distance from the plate has changed, and Shenton's line is disrupted in both directions.
- Posterior: head superolateral to the acetabulum; smaller apparent head (further from the plate); look for a posterior wall fragment; internal rotation of the lesser trochanter
- Anterior: head inferomedial (obturator) or anteromedial (pubic); larger apparent head (closer to the plate); external rotation makes the lesser trochanter prominent; the head may overlap the obturator foramen
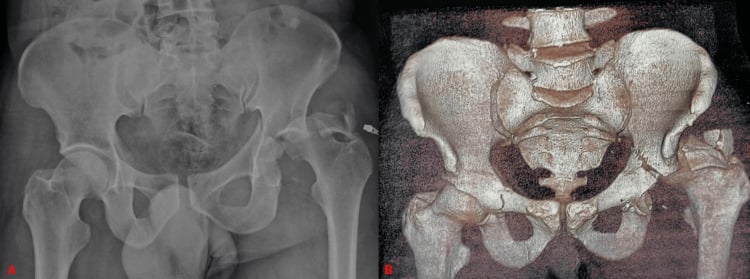
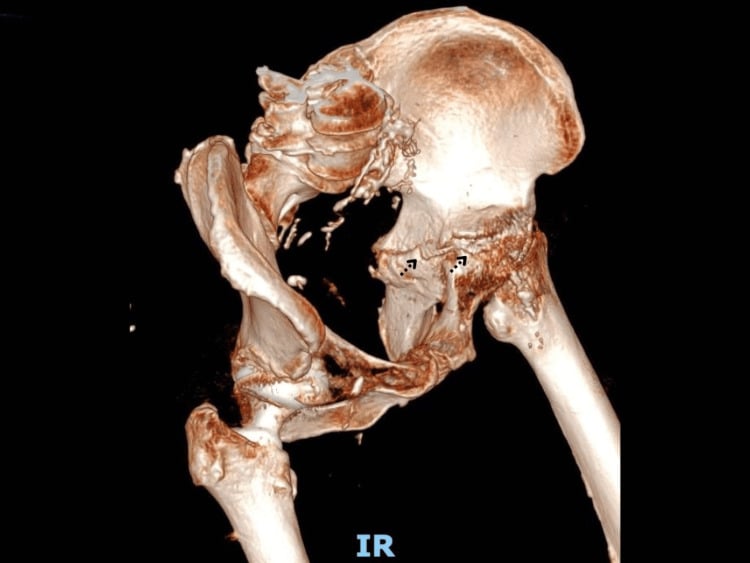
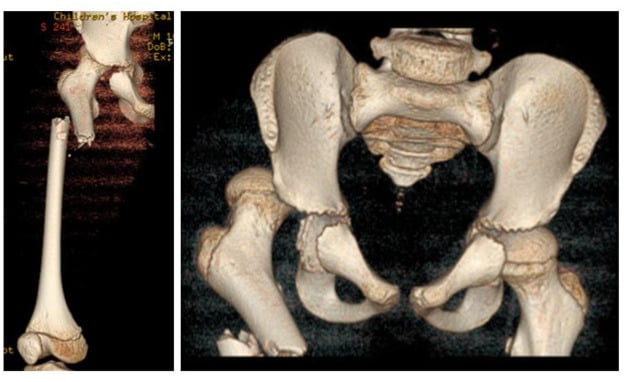
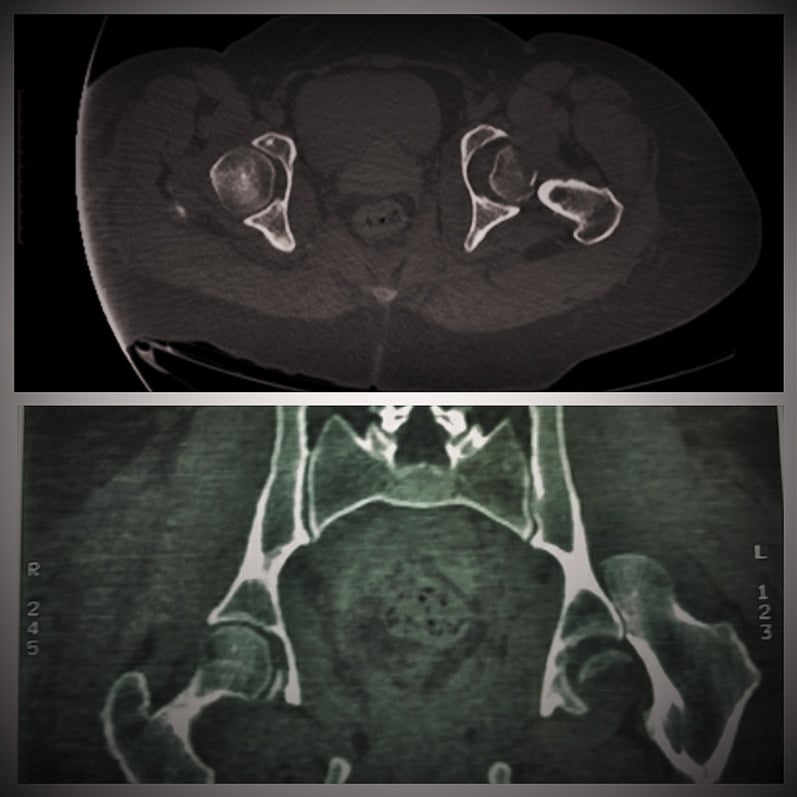
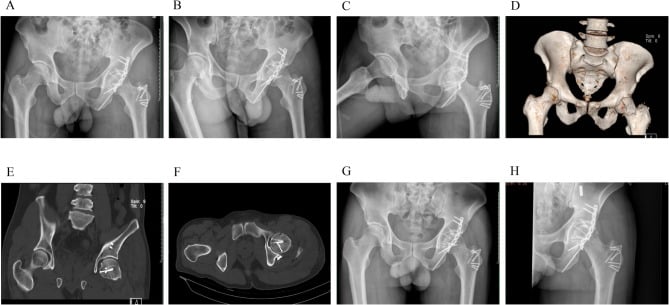
The post-reduction CT. Every reduced hip gets one, and it dictates the rest of the treatment.
- What to Assess
- Joint space equal all around
- Why It Matters
- Non-concentric = incarcerated fragment
- What to Assess
- Size and displacement of fragment
- Why It Matters
- Over 40% wall = unstable, needs ORIF
- What to Assess
- Impaction, osteochondral fragments
- Why It Matters
- Pipkin classification, ORIF planning
- What to Assess
- Occult fracture
- Why It Matters
- Missed neck = complications
- What to Assess
- Associated column fractures
- Why It Matters
- May change surgical approach
- What to Assess
- Intra-articular fragments
- Why It Matters
- Needs arthroscopic or open removal
Non-concentric reduction. An asymmetric joint space on the post-reduction CT means an incarcerated fragment - labrum, bone or capsule - sitting between head and socket. It needs urgent operative removal to prevent AVN and cartilage damage, and a clunk felt at reduction does not exclude it.
Management Algorithm
Reduce as soon as safely possible - the evidence shows a step, not a slope. Hougaard's 100 dislocations: 4.8% AVN reduced within 6 hours, 52.9% beyond it. The meta-analysis (Kellam) found the odds of AVN 5.6 times higher after 12 hours. Those are two different studies with two different thresholds - no study measured the middle band - so do not quote a "5% / 20% / 40%" gradient, which falsely suggests the seventh hour is safer than the data says. Prioritise reduction above imaging, above transfer, above everything except the ABCs.
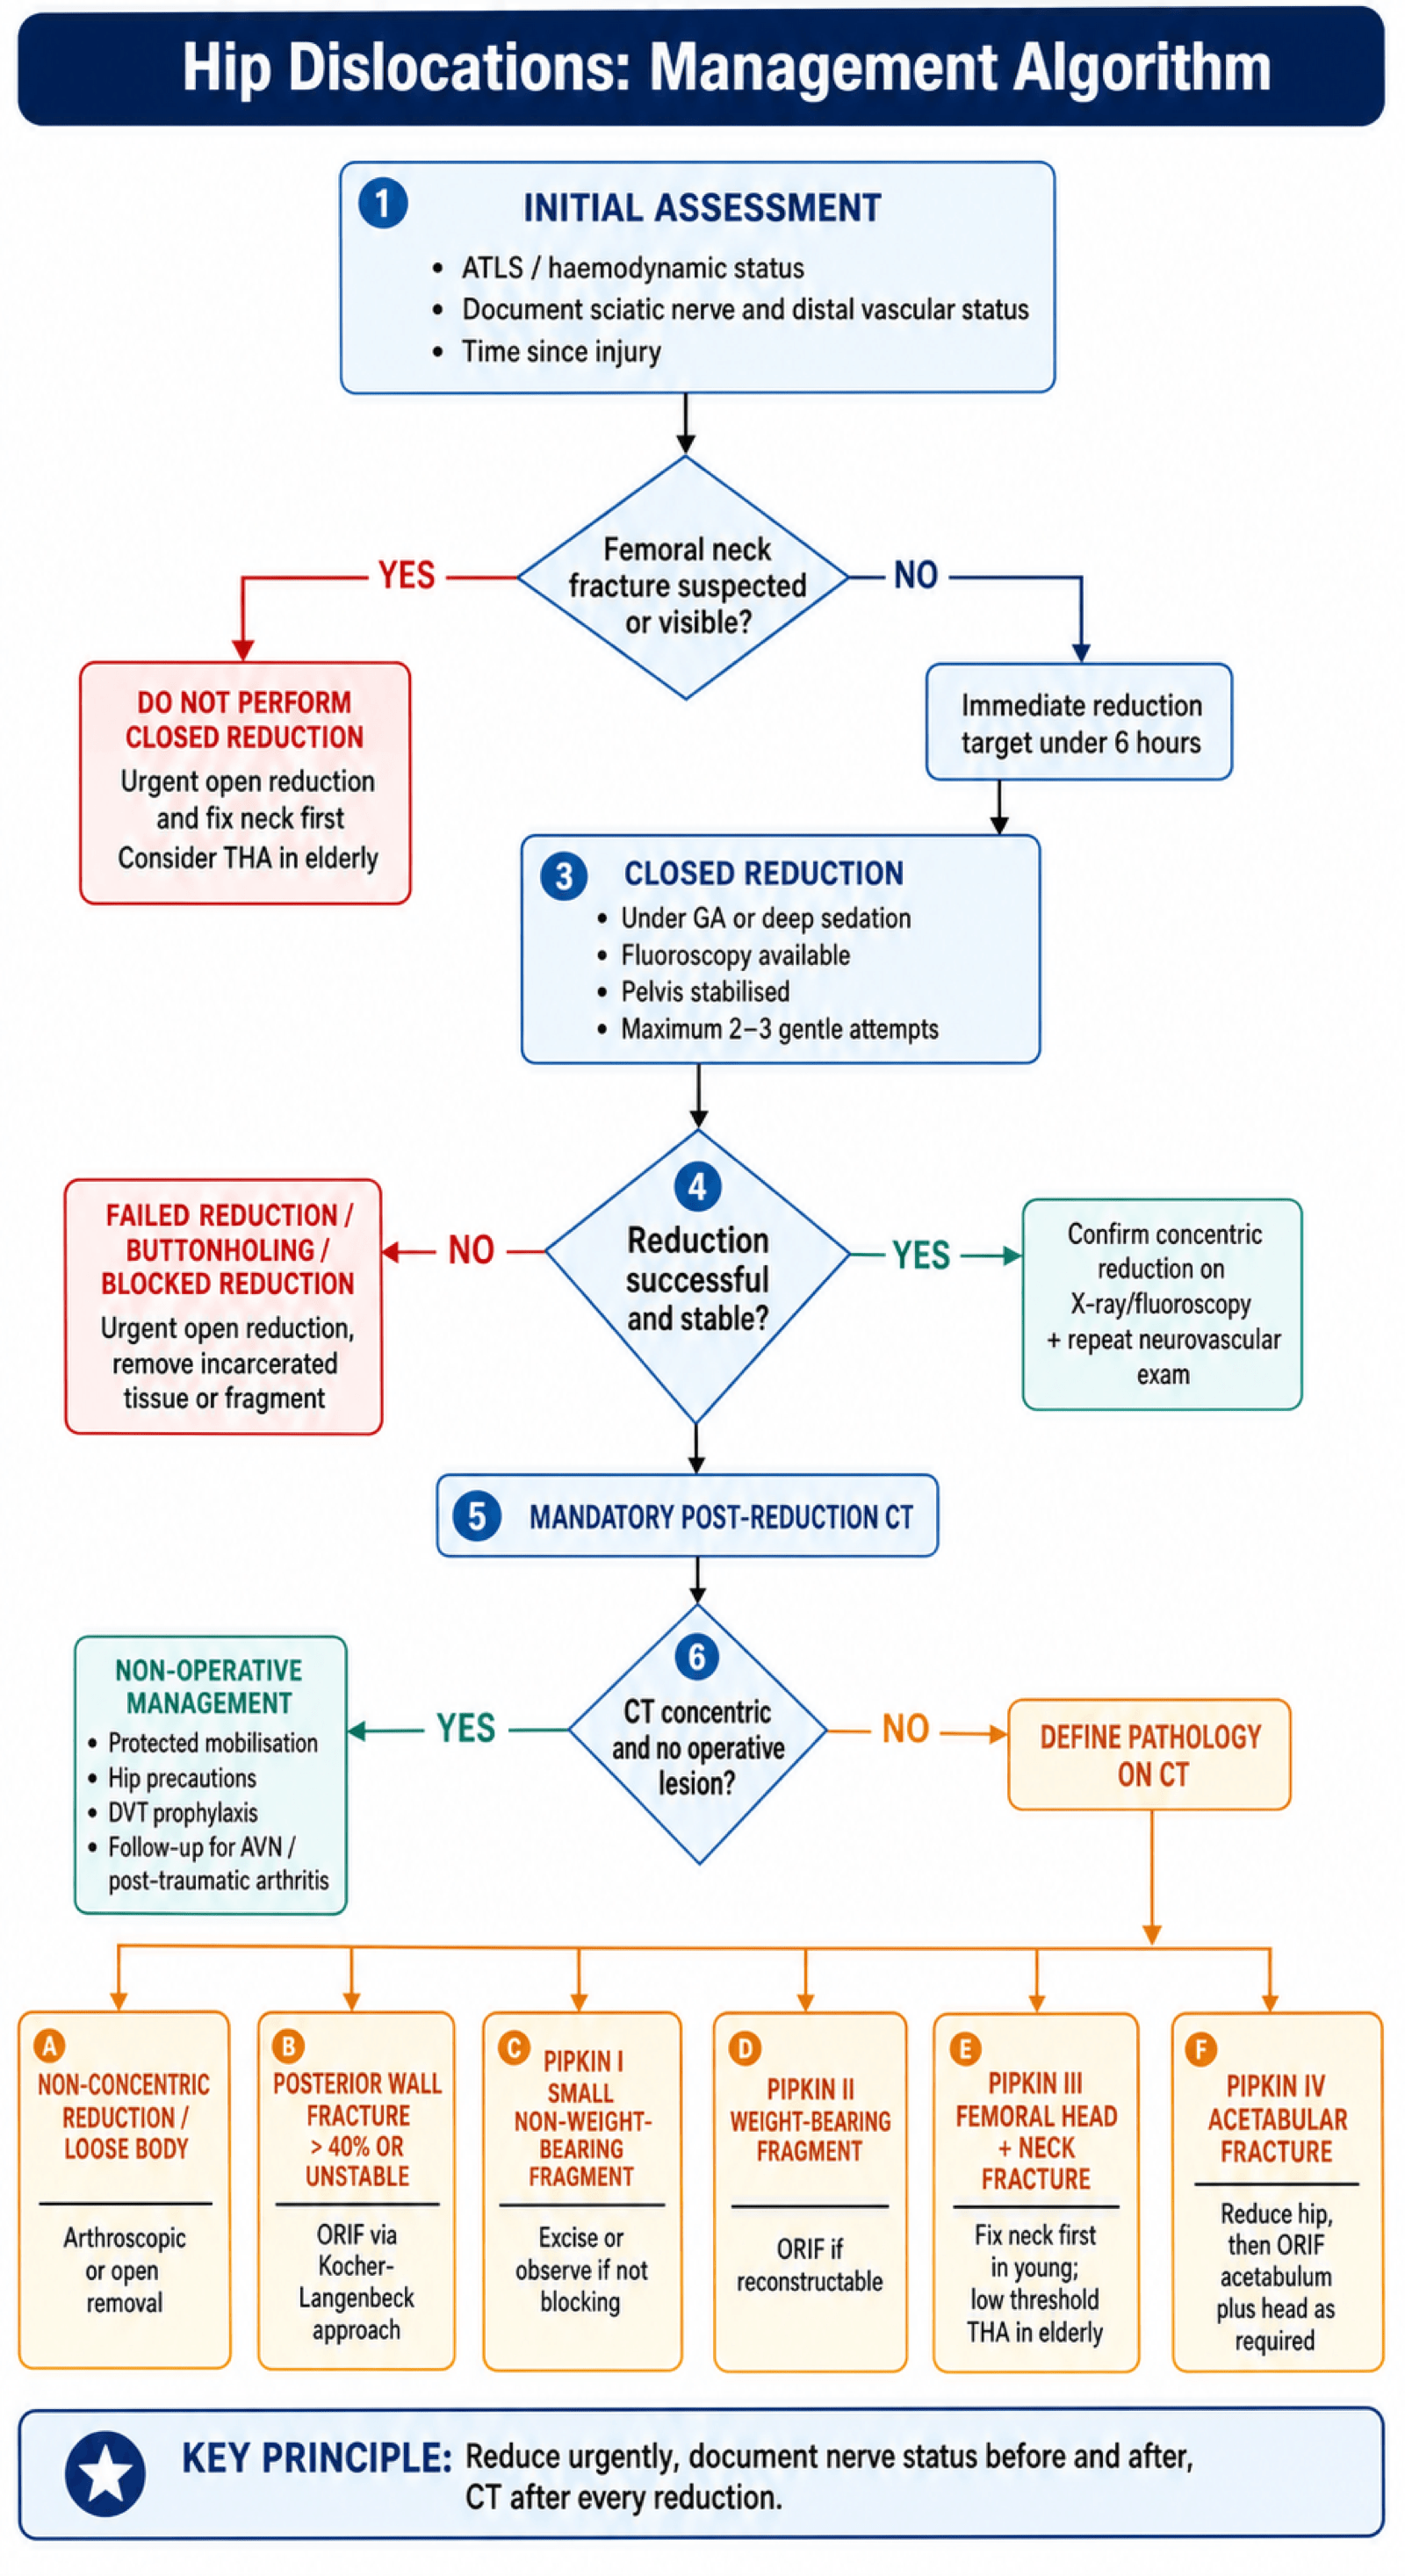
Decision by pattern. Once the hip is in and the CT read, the pattern chooses the treatment.
- Key Finding
- No fracture on X-ray
- Treatment
- Urgent closed reduction, CT after
- Pearl
- 6-hour window - treat as emergency
- Key Finding
- Posterior wall on CT
- Treatment
- Reduce, CT assess wall size, ORIF wall
- Pearl
- Wall over 40% = unstable, needs fixation
- Key Finding
- Femoral head fragment
- Treatment
- Reduce, Pipkin classification guides Rx
- Pearl
- Pipkin I (below fovea) = consider ORIF
- Key Finding
- Femoral neck visible
- Treatment
- Cannot reduce closed - open reduction
- Pearl
- Devastating injury - high AVN risk
- Key Finding
- Leg externally rotated, abducted
- Treatment
- Closed reduction
- Pearl
- Less common (10%), check femoral vessels
The posterior wall threshold. A wall fracture over 40% of the articular surface leaves the hip unstable even after reduction and needs ORIF with buttress plating; under 40% may be stable, and stability is assessed clinically under fluoroscopy. The 40% figure is how CT triages the wall, not the last word on it. In Moed's series walls under 20% were generally stable and walls over 40-50% generally unstable, but static CT measurement was an unreliable predictor across the 20-40% band, where a dynamic fluoroscopic stress examination under general anaesthesia is the recommended test of stability. A wall proved stable on that examination can be managed non-operatively: Grimshaw and Moed's 21 such fractures all scored good to very good at a minimum of 2 years, and every hip assessed radiographically had a congruent joint without post-traumatic arthritis.
Closed Reduction
Before you start. Record the time of injury, because the 6-hour rule runs from it, and examine and document the sciatic nerve before anyone touches the leg: dorsiflexion, toe extension and dorsal foot sensation for the peroneal division, plantarflexion and plantar sensation for the tibial. Consent covers AVN, nerve injury and the possibility of an open procedure.
Setup. General anaesthesia or deep sedation, because muscle relaxation is essential and muscles fighting the reduction defeat it. Theatre, or the emergency department resuscitation bay if the patient is stable; fluoroscopy available to confirm the reduction; a padded table with the patient supine; an assistant to stabilise the pelvis, which is crucial; and a plan for open reduction if closed reduction fails.
The Allis manoeuvre. The preferred technique for a posterior dislocation (Allis or Bigelow), with the assistant providing counter-traction at the pelvis throughout.
Step-by-Step Allis Manoeuvre
Supine on a firm table. The assistant stands at the pelvis with both hands pressing down on the ASIS bilaterally. Without this counterforce you pull the whole patient toward you.
Stand at the side of the table facing the patient's head and flex the hip and knee to 90°. This relaxes the iliofemoral ligament, the strongest ligament in the body, and brings the head to the acetabular opening.
Grasp the proximal tibia at the knee and apply steady, in-line axial traction toward the ceiling with the hip at 90°: sustained force, never a jerk. For a strong patient or a difficult reduction, place the knee in the crook of your elbow, hold the tibia and stand on the table so that your body weight provides the traction - the "Captain Morgan" variation.
While maintaining traction, apply gentle internal and external rotation to the leg to disengage the head from behind the acetabulum and guide it over the rim. Feel for the clunk of reduction; do not use excessive force or rotation.
The leg returns to normal length and alignment. Test the range carefully - the hip should move smoothly through flexion, extension and rotation - and obtain fluoroscopy or a radiograph immediately.
The Stimson manoeuvre. The alternative when Allis fails. The patient lies prone with the injured leg hanging off the end of the table, hip and knee both flexed to 90°, the assistant stabilising the pelvis, and the surgeon applying downward pressure on the calf with gentle rotation. Gravity provides continuous traction and relaxation with less effort from the surgeon, but the price is rolling a polytrauma patient prone, where the face and airway cannot be seen, so it is unsuitable for an unstable patient.
- Likely Cause
- Incarcerated fragment (labrum, osteochondral)
- Solution
- Proceed to open reduction - cannot force closed
- Likely Cause
- Posterior wall fracture (unstable)
- Solution
- Maintain reduction with traction, CT, plan ORIF wall
- Likely Cause
- Inadequate muscle relaxation
- Solution
- Increase sedation/paralysis, ensure full GA
- Likely Cause
- Not actually reduced, head still out
- Solution
- Obtain fluoro immediately, reattempt or open
- Likely Cause
- Incarcerated soft tissue or fragment
- Solution
- Urgent operative removal of incarcerated tissue
Stop closed reduction if: (1) the X-ray shows a femoral neck fracture - closed forces will displace it, (2) more than 2-3 gentle attempts fail - something is blocking reduction, and excessive force risks an iatrogenic fracture, (3) the patient becomes haemodynamically unstable. Proceed to open reduction urgently - the 6-hour window still applies. Do not delay for imaging or wait for a specialist who is not available: reduce first.
The neglected dislocation. A traumatic dislocation that presents late, weeks to months unreduced, is a recognised problem, especially where access to acute care is limited, and it behaves very differently from the acute injury. The femoral head becomes fixed in soft-tissue scar with progressive cartilage loss and capsular contracture, so simple closed reduction is almost never possible and must not be forced, because of the high risk of fracturing the femoral neck or shaft.
Management is staged and depends on age and the state of the cartilage: a period of preliminary skeletal traction to bring the head down gradually, then open reduction with capsulotomy, clearance of the scar and fibrofatty tissue from the acetabulum, and sometimes a femoral shortening osteotomy to allow tension-free relocation and protect the sciatic nerve. In a young patient with preserved cartilage the aim is to relocate and preserve the joint, accepting a high risk of AVN and arthrosis; where the head or cartilage is destroyed, arthrodesis or arthroplasty is chosen by age and demand. Outcomes are guarded, and the patient must be counselled that AVN and post-traumatic arthritis are likely.
Surgical Technique
Reducing an anterior dislocation. Closed reduction of an anterior dislocation is by external rotation, extension and traction; the injury is less common and often requires open reduction. After any reduction, posterior or anterior, confirm a concentric joint on fluoroscopy, take the hip through a full range under the image to assess stability, and send the patient for the CT.
Choosing the approach. The Kocher-Langenbeck posterior approach is the workhorse for posterior dislocations and posterior wall fractures; anterior approaches serve anterior dislocations and anterior column fractures; a surgical hip dislocation serves complex patterns and femoral head fractures. For the femoral head the choice carries a vascular cost: in Stannard's 26 head fractures the Kocher-Langenbeck approach carried 3.2 times the odds of AVN of the Smith-Petersen anterior approach, and 3-mm cannulated screws with washers gave poor results and are contraindicated for head fixation. The Ganz surgical dislocation answers the same problem from the other side: a trochanteric flip osteotomy with anterior dislocation through a posterior approach, in which the external rotators are not divided and obturator externus protects the medial femoral circumflex artery, giving full access to the head and acetabulum; in 213 hips with intra-operative confirmation of head perfusion no subsequent AVN was reported.
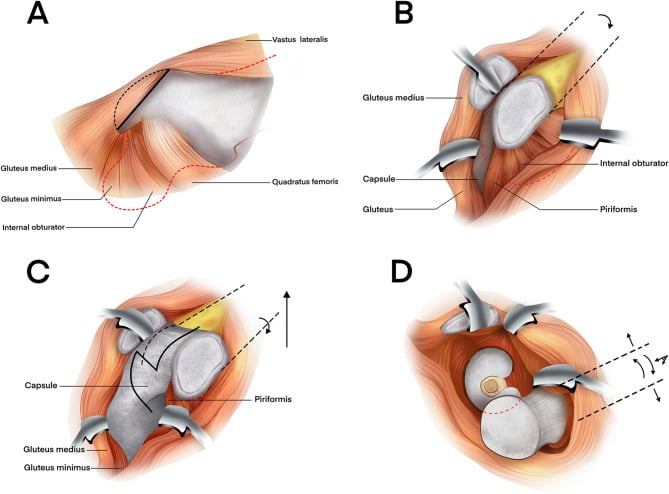
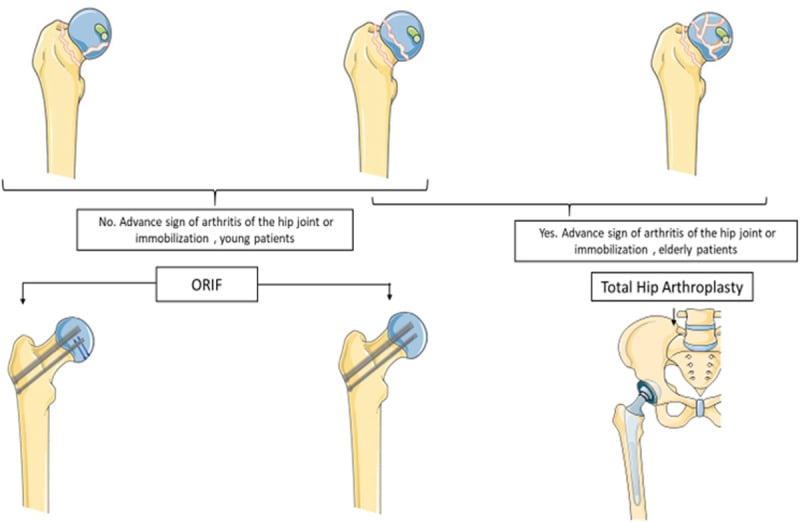
Femoral head fractures by Pipkin type. Femoral head fractures have worse outcomes and higher AVN rates, and the type decides the operation.
Pipkin I (inferior to the fovea). The fragment is usually small and outside the weight-bearing surface. Excise it if it is small and not blocking reduction; fix it if it is larger or involves a weight-bearing portion.
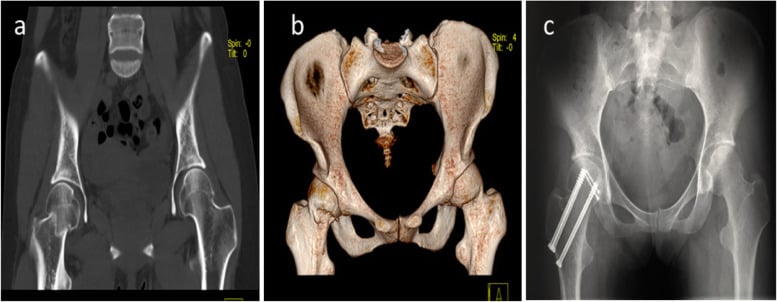
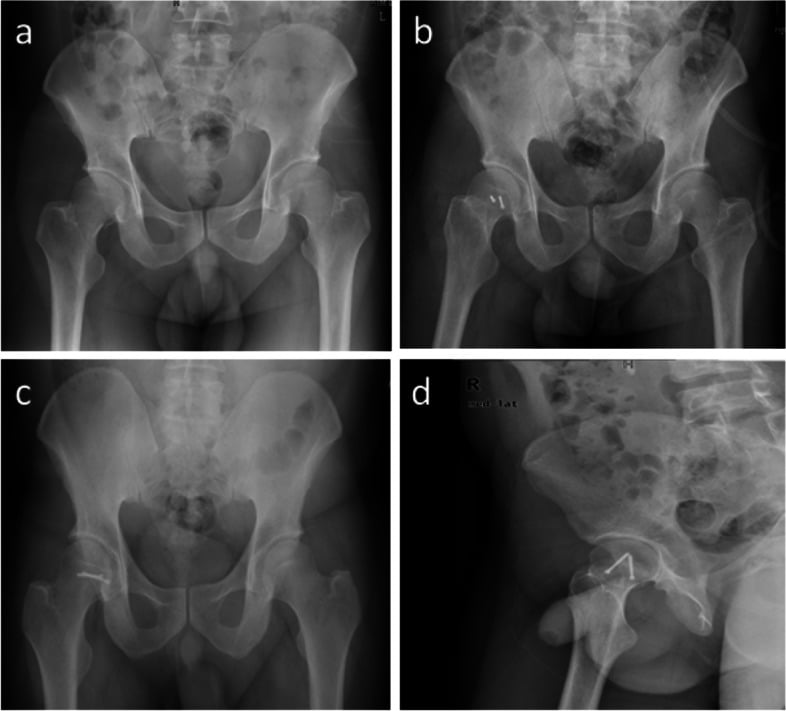
Pipkin II (superior to the fovea). The weight-bearing portion is involved, so ORIF is preferred, with countersunk headless screws, through an anterior approach (Smith-Petersen or Watson-Jones).
Pipkin III (I or II with a femoral neck fracture). An emergency, because both blood supplies are compromised. The neck fracture takes priority: fix it in the young; the elderly often require THA.
Pipkin IV (I or II with an acetabular fracture). Both the acetabulum and the head are addressed, by a sequential or combined approach.
Complications
- Incidence
- 10-40%
- Risk Factors
- Delayed reduction over 6h, repeated attempts
- Management
- Surveillance, THA if symptomatic
- Incidence
- 10-20%
- Risk Factors
- Posterior dislocation, bone fragments
- Management
- Observe, most recover by 2 years
- Incidence
- 20-40%
- Risk Factors
- Cartilage damage, malreduction, AVN
- Management
- Activity modification, THA long-term
- Incidence
- Rare in native hip
- Risk Factors
- Posterior wall deficiency, malreduction
- Management
- Revision ORIF or THA
- Incidence
- 3-5%
- Risk Factors
- Delayed surgery, brain injury
- Management
- Prophylaxis: indomethacin or RT
- Incidence
- Variable
- Risk Factors
- AVN, untreated Pipkin
- Management
- THA
Avascular necrosis. AVN may take 6-24 months to appear on the radiograph, and MRI detects the marrow changes earlier. Follow with radiographs at 6 weeks, 3 months, 6 months, 1 year and 2 years, and treat symptomatic AVN with THA.
Sciatic nerve injury. Most are neuropraxia or axonotmesis, and the early management is to document and wait.
Nerve Recovery Timeline
Document nerve status pre and post reduction. Most are neuropraxia or axonotmesis. Initial foot drop and numbness.
Obtain EMG/NCS to assess severity and prognosis. Look for reinnervation potentials.
Consider nerve exploration if no clinical or electrical recovery. Neuroma excision, nerve grafting.
90% will recover to some degree by 2 years. Peroneal division may have incomplete recovery.
When the foot drop does not recover. The peroneal division recovers worst, so a proportion of patients are left with a permanent foot drop despite the favourable overall prognosis. If recovery has not occurred by around 18-24 months, with EMG showing no reinnervation, the deficit is treated as established. First-line is an ankle-foot orthosis, often all an older or low-demand patient needs to clear the foot in swing and walk safely. For a fit patient who wants to be brace-free, a tibialis posterior tendon transfer, rerouted anteriorly through the interosseous membrane to the dorsum of the foot, restores active dorsiflexion; tendo-Achilles lengthening for a fixed equinus, or ankle arthrodesis for an unstable or arthritic ankle, are added as needed. Keep the early nerve question (document, observe, EMG at 3 months, explore at 6 months) separate from the late functional one (orthosis or tendon transfer once the palsy is permanent).
Postoperative Care and Rehabilitation
Rehabilitation Protocol
Toe-touch or protected weight bearing depending on stability. Bed rest initially. Thromboprophylaxis. ROM exercises.
If stable and no fracture: progress to full weight bearing. If ORIF: protected until fracture healing assessed on X-ray.
Full weight bearing. Progressive strengthening. Gait training. Hip abductor focus.
Return to sport/activity once strength restored. Long-term surveillance for AVN (X-rays).
Weight bearing. The stability of the hip sets the pace. A simple dislocation with a concentric reduction and no fracture may weight bear as tolerated early; after posterior wall ORIF, weight bearing is protected until the wall has healed, at 6-12 weeks; after Pipkin ORIF it depends on the size of the fragment and the fixation.
Outcomes and Prognosis
- Good Outcome Rate
- 70-80%
- Key Factors
- Early reduction, no fracture
- Complications
- AVN 5-10%, OA 15-20%
- Good Outcome Rate
- 50-70%
- Key Factors
- Quality of reduction, wall stability
- Complications
- AVN 10-20%, OA 20-40%
- Good Outcome Rate
- 60-70%
- Key Factors
- Fragment size, excision vs ORIF
- Complications
- AVN 10-20%
- Good Outcome Rate
- 40-60%
- Key Factors
- Articular involvement, reduction quality
- Complications
- AVN 20-30%, OA 30-50%
- Good Outcome Rate
- 20-40%
- Key Factors
- Age, dual blood supply injury
- Complications
- AVN 40-60%, often THA
What decides the result. The favourable hip was reduced within 6 hours, had no fracture, achieved a concentric stable reduction, belongs to a young patient without comorbidities and has an intact sciatic nerve. The unfavourable one was reduced late (over 6-12 hours), carries an acetabular or femoral head fracture, was reduced non-concentrically or remains unstable, has a sciatic nerve injury (particularly of the peroneal component), or endured repeated closed reduction attempts.
In the long term. Most patients with a simple posterior dislocation reduced within 6 hours have a good functional outcome. The determinants of long-term outcome are AVN and post-traumatic osteoarthritis; younger patients may tolerate mild degenerative change better than older patients, and THA remains the salvage procedure for severe AVN or debilitating arthritis.
Guidelines, Registries & Global Practice
- Traumatic native-hip dislocation is uncommon and high-energy worldwide; the great majority (~85-90%) are posterior
- Dominant mechanism globally is road traffic collision (dashboard/front-seat passenger); motorcycle and pedestrian trauma predominate in low- and middle-income settings
- Geographic remoteness and retrieval logistics — not injury energy alone — drive time-to-reduction and therefore AVN risk; rural and low/middle-income settings see the worst delays despite road-safety legislation
- Sport (rugby codes, American football, skiing, soccer) is a recognised cause in young athletes
- In children, posterior dislocation predominates and AVN remains the key long-term adverse event (posterior ~86%, AVN ~15% of associated pathologies in a paediatric systematic review, Baumann 2023, PMID 37947036)
- Most fragility-type hip "dislocations" in the elderly are in fact prosthetic instability - a separate clinical entity
- Where reduction happens varies: many systems reduce in the emergency department under procedural sedation; others mandate theatre/GA - both are defensible if muscle relaxation is adequate
- Time-to-reduction targets differ but the universal principle is "as soon as safely possible"; the historical 6-hour figure is a teaching anchor, not a regulatory threshold
- Stability assessment of intermediate posterior wall fractures varies between CT-only and examination under anaesthesia (EUA), with trauma units increasingly favouring EUA (Moed, PMID 19104298)
- Approach for femoral head fractures varies between anterior (Smith-Petersen), surgical hip dislocation (Ganz) and posterior (Kocher-Langenbeck), with a trend toward vascular-protective approaches
- Position on Hip Dislocation
- Emergent reduction of the dislocated hip; mandatory post-reduction CT; EUA or CT to decide posterior wall stability; ORIF for unstable walls
- Evidence Basis
- Expert consensus + retrospective series (Moed, Grimshaw)
- Position on Hip Dislocation
- Polytrauma hips managed in the ATLS framework within trauma networks; urgent reduction and senior-led decision-making; combined ortho-plastic and pelvic/acetabular referral pathways for associated fractures
- Evidence Basis
- BOAST standards for pelvic/acetabular and open fractures (principle-level)
- Position on Hip Dislocation
- Reduction priority, careful classification (Thompson-Epstein, Pipkin/Brumback), MFCA-protective approaches, anatomic articular reconstruction of wall/head fractures
- Evidence Basis
- AO surgical principles and technique teaching
- Position on Hip Dislocation
- Reinforces prompt reduction, mandatory cross-sectional imaging, and referral of complex fracture-dislocations to specialist acetabular units
- Evidence Basis
- European educational consensus
There is no high-level (NICE-style) clinical guideline specific to traumatic native hip dislocation because the injury is rare and randomised data are lacking. Practice rests on retrospective cohorts and meta-analysis (Hougaard 1986, Kellam & Ostrum 2016) plus expert consensus. In a viva, state this honestly: management is principle-driven (rapid reduction, mandatory post-reduction CT, stability-guided fixation), not protocol-driven.
- There is no dedicated traumatic-dislocation registry; long-term salvage data come from arthroplasty registries
- The AOANJRR, NJR, Nordic and other national joint-replacement registries capture THA performed for post-traumatic osteoarthritis and post-dislocation AVN, which is the common end-point of failed hips
- Post-traumatic / AVN indications are a recognised subgroup with their own revision profile, informing counselling about the possibility of eventual hip replacement
Key documentation: (1) Time of injury AND time of reduction - the 6-hour rule, (2) Sciatic nerve exam before AND after reduction, (3) Consent including AVN and nerve risks, (4) Post-reduction CT performed and reviewed, (5) Follow-up plan for AVN surveillance. Delayed reduction and missed sciatic nerve injury are litigation risks.
MCQ Practice Points
Q: How does time to reduction change the AVN rate after posterior hip dislocation, and what threshold should you quote? A: Quote the two thresholds that were actually measured, and resist inventing the gradient between them. Hougaard's 100 dislocations split at six hours: 4.8% AVN reduced within 6 hours, 52.9% beyond it - roughly a tenfold difference. The 2016 meta-analysis split at twelve hours instead, finding the odds of AVN 5.6 times higher after 12 hours, with posterior-dislocation AVN across pooled series running 10.6% to 43%. Neither study measured a 6-to-12-hour band, so a tidy "5% / 20% / 40%" ladder is interpolation, and it is the dangerous kind: it makes hour seven look like a moderate-risk zone when the only direct evidence puts everything past six hours at over 50%. Reduce as soon as safely possible and treat six hours as the number that changes the prognosis.
Q: Which division of the sciatic nerve is most commonly injured in posterior hip dislocation? A: Peroneal (common peroneal) division. It is more lateral and tethered, making it more vulnerable. Clinically presents as foot drop and dorsal foot numbness.
Q: What is the classic leg position in posterior hip dislocation? A: Shortened, Adducted, Internally Rotated (SAID). The leg appears shorter, is pulled toward midline, with the foot pointing inward. This is the dashboard injury position.
Q: At what percentage of posterior wall involvement does the hip become unstable post-reduction? A: Over 40% posterior wall involvement. This threshold indicates the need for ORIF to prevent redislocation. Assess on CT post-reduction.
Q: What distinguishes Pipkin I from Pipkin II femoral head fractures? A: Pipkin I = below the fovea (infrafoveal), spares weight-bearing surface. Pipkin II = above the fovea (suprafoveal), involves weight-bearing surface and has worse prognosis.
Q: What mandatory imaging is required after closed reduction of a hip dislocation? A: CT scan. Essential to assess: concentric reduction (no incarcerated fragments), posterior wall integrity, femoral head fracture, occult femoral neck fracture, and loose bodies.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 25-year-old male is brought to ED after an MVA. He was an unrestrained front passenger. His left leg is shortened, adducted, and internally rotated. He has no other obvious injuries and is haemodynamically stable. X-ray shows a posterior hip dislocation with no obvious fracture. It is 2 hours since the accident. How would you manage this patient?”
“A 30-year-old female presents after a motorcycle accident with a posterior hip dislocation. You perform closed reduction successfully at 4 hours post-injury. Post-reduction CT shows concentric reduction but a displaced posterior wall fragment involving approximately 50% of the articular surface. She has normal sciatic nerve function. What is your further management?”
“A 35-year-old presents after an MVA with a posterior hip dislocation. You reduce the hip successfully at 5 hours. CT post-reduction shows a femoral head fragment (Pipkin type II - above the fovea involving 30% of the weight-bearing surface). The acetabulum appears intact. There is no sciatic nerve injury. How would you manage this?”
Key Facts
- Posterior 90%, Anterior 10%
- 6-hour rule: reduce early to minimize AVN
- SAID position: Shortened, Adducted, IR (posterior)
- Dashboard injury = posterior dislocation
Sciatic Nerve
- 10-20% injury rate in posterior dislocation
- Peroneal division most vulnerable
- Document BEFORE and AFTER reduction
- 90% recover by 2 years, explore at 6 months if not
Thompson-Epstein
- Type I-II: Simple or small wall fragment
- Type III: Large posterior wall (over 40%) - ORIF
- Type IV: Acetabular floor fracture
- Type V: Femoral head fracture (Pipkin)
Pipkin Classification
- Pipkin I: Below fovea - better prognosis
- Pipkin II: Above fovea - weight-bearing involved
- Pipkin III: With femoral neck - disaster
- Pipkin IV: With acetabular fracture
Post-Reduction CT
- MANDATORY after every reduction
- Check: concentric reduction, wall, fragments
- Non-concentric = incarcerated tissue/bone
- Over 40% wall = needs ORIF
AVN Rates
- Within 6 hours: 4.8% AVN (Hougaard, 100 dislocations)
- Beyond 6 hours: 52.9% - the rise is a step at six hours, not a gradient
- After 12 hours: odds of AVN 5.6x those before 12 hours (meta-analysis)
- Surveillance X-rays for 2 years
Evidence Base and Key Trials
Timing and AVN - Hougaard & Thomsen (origin of the time-to-reduction principle)
- 98 adults with 100 traumatic posterior dislocations, minimum 5-year follow-up
- Avascular necrosis in only 4.8% of hips reduced within 6 hours
- Avascular necrosis in 52.9% of hips reduced more than 6 hours after injury
- Higher AVN incidence with Stewart-Milford grade III and IV dislocations; no benefit demonstrated from skeletal traction or non-weight-bearing
- The AGE of the patient was of no importance - an older patient's head is not inherently more or less likely to survive, so the urgency applies identically at 70 as at 25
AVN & Post-Traumatic OA Meta-Analysis - Kellam & Ostrum
- Systematic review and meta-analysis of AVN and post-traumatic arthritis after traumatic hip dislocation
- Posterior dislocation AVN event rate 10.6-43.0%; PTA event rate 19.4-58.6%
- Odds ratio of AVN 5.6 for reduction after 12 hours versus before 12 hours
- Injury severity (higher Thompson-Epstein grade) correlates with more AVN and PTA
Posterior Wall Stability on CT - Moed
- Walls involving less than 20% are generally stable; greater than 40-50% are generally unstable, leaving an indeterminate middle zone
- Static 2D CT measurement was an unreliable predictor of instability for fragments around 20-40%
- Dynamic fluoroscopic stress examination under general anaesthesia is the recommended gold-standard test of stability
- Small CT wall size does not reliably exclude instability
Non-Operative Posterior Wall after Stable EUA - Grimshaw & Moed
- 21 posterior wall fractures shown to be stable on dynamic stress fluoroscopy under anaesthesia, treated non-operatively
- At minimum 2-year follow-up, modified Merle d'Aubigne scores were good to very good in all
- All radiographically assessed hips had a congruent joint with no post-traumatic arthritis
- Stable EUA reliably predicts a congruent joint and good early outcome without surgery
Femoral Head (Pipkin) Fracture Outcomes & Approach - Stannard
- 26 femoral head fractures associated with hip dislocation - often poor functional outcome
- Kocher-Langenbeck posterior approach carried a 3.2x higher odds of AVN versus the Smith-Petersen anterior approach
- Brumback classification differentiated fracture types better than Pipkin in this series
- 3-mm cannulated screws with washers gave poor results and are contraindicated for head fixation
Vascular-Safe Surgical Dislocation - Ganz Technique
- Trochanteric flip osteotomy with anterior dislocation through a posterior approach, based on detailed MFCA anatomy
- External rotators are not divided and the obturator externus protects the medial femoral circumflex artery
- 213 hips over 7 years with intra-operative confirmation of head perfusion - no subsequent AVN reported in the series
- Gives full access to the femoral head and acetabulum for fixation of head fractures and loose bodies
HO Prophylaxis Caution - Indomethacin & Long-Bone Nonunion (Burd RCT)
- Patients with acetabular fractures randomised to indomethacin or radiation for HO prophylaxis
- Among 112 with a concomitant long-bone fracture, nonunion occurred in 26% of the indomethacin group versus 7% without indomethacin (p=0.004)
- Radiation therapy did not carry the same nonunion penalty
- Companion RCT (Moore 1998, JBJS Br, PMID 9546456) showed indomethacin and single-dose ~800 cGy radiation were equally effective at preventing HO