Dorsal Wrist Overuse Tenosynovitis | 1st Crosses 2nd Compartment | Crepitus and Squeak | Proximal vs Distal
- Friction tenosynovitis where 1st compartment (APL, EPB) crosses over 2nd (ECRL, ECRB)
- Pain and swelling 4-6 cm PROXIMAL to the wrist - not over the radial styloid
- Classic crepitus or audible squeak ('wet leather' sign)
- Key differential is de Quervain (which is at the radial styloid)
- Treatment is conservative - rest, splint, NSAIDs, then injection if needed
- “Proximal intersection is more proximal than de Quervain
- “Rowers, weightlifters, racquet sports, skiers
- “Distal intersection = EPL crossing the radial wrist extensors
- “Surgery is rarely needed
- “Asymptomatic peritendinous fluid is common in elite rowers
Overview and Epidemiology
Intersection syndrome is an overuse tenosynovitis of the dorsal wrist. It arises from friction where the muscle bellies and tendons of the first dorsal compartment, abductor pollicis longus (APL) and extensor pollicis brevis (EPB), cross superficially over the tendons of the second compartment, extensor carpi radialis longus (ECRL) and extensor carpi radialis brevis (ECRB). The crossing lies in the dorsoradial distal forearm, roughly 4-6 cm proximal to the wrist joint (proximal to Lister tubercle), clearly more proximal than de Quervain disease, which sits at the radial styloid.
How common. It is uncommon. A review of more than a thousand hand and wrist ultrasound examinations found intersection syndrome in only about 1.9% of patients evaluated in a specialised setting, and the evidence section below explains why that figure is a floor rather than a prevalence. It is best regarded as a repetitive-strain condition of the active and the athletic rather than a degenerative disease of older patients.
Who. Typically active adults, with a mean age around the fourth to fifth decade and a male predominance reported in imaging series. Rowers are the classic athletes, and the condition is sometimes called "oarsman's wrist"; weightlifters, racquet-sport players, skiers, horse riders and occupations with repetitive wrist extension also feature.
Risk factors. These are the loads to ask about:
- Repetitive resisted wrist extension and radial deviation
- A sudden increase in training load, or a new activity
- Sports with a strong, repeated wrist-extension stroke, such as rowing and weight training
- Repetitive occupational tasks and manual repetitive work
Anatomy and Pathophysiology
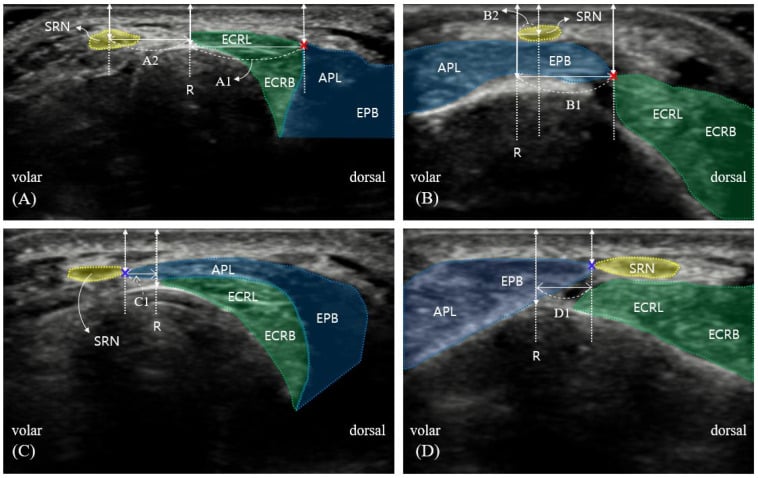
The proximal intersection. The first-compartment muscle bellies and tendons (APL, EPB) pass obliquely over the second-compartment tendons (ECRL, ECRB) through a finite overlap zone. The superficial radial nerve courses nearby and must be considered during palpation and injection.
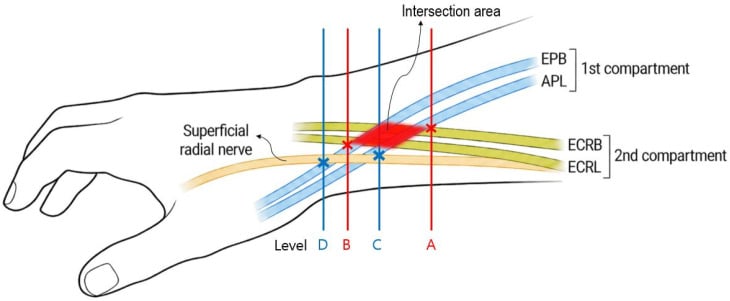
A flat compartment diagram misses the true tendon relationships, which dissection shows.
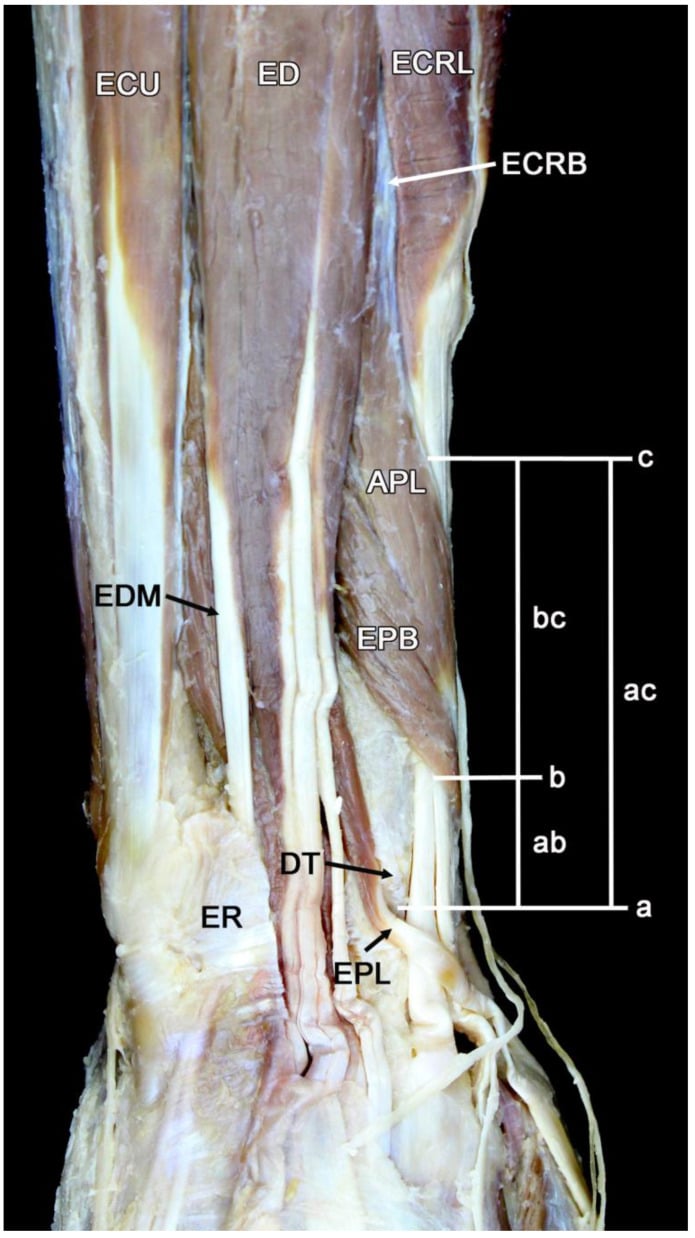
The distal intersection. A separate, rarer entity in which extensor pollicis longus (EPL, the third compartment) crosses over ECRL and ECRB near Lister tubercle. It is closer to the wrist and can be confused with other dorsal wrist pathology. Because EPL hooks around Lister tubercle, attritional change here carries a theoretical risk of tendon damage or rupture.
The six dorsal compartments. Numbering them keeps the two crossings straight: compartment 1 crosses 2 proximally, and compartment 3 crosses 2 distally.
- APL, EPB
- ECRL, ECRB
- EPL
- EDC, EIP (finger extensors)
- EDM (small-finger extensor)
- ECU (ulnar wrist extensor)
Two mechanisms. Repetitive wrist extension produces a tenosynovitis at the crossing, and two mechanisms are described; both result in the same clinical picture.
- Friction. The mobile first-compartment muscle bellies rub across the underlying second-compartment tendons, producing a peritendinous friction tenosynovitis with oedema and fluid.
- Stenosis of the second compartment. ECRL and ECRB become constricted within their sheath as they run deep to the crossing first compartment, a stenosing tenosynovitis analogous to de Quervain but one compartment over and more proximal.
Why the second compartment is the target. Whichever mechanism dominates, the symptomatic, constrained structure is the second compartment. So although the first compartment is the crossing "aggressor", surgery decompresses the second dorsal compartment, a fasciotomy of its sheath with tenosynovectomy that frees ECRL and ECRB; releasing the first compartment is the de Quervain operation.
The injection follows. The same logic sends the corticosteroid injection into the second-compartment sheath or intercompartmental space at the intersection, rather than into the first compartment: treat where the tendons are constrained, not merely where they cross.
The tissue. The dominant change is peritendinous oedema and reactive tenosynovitis rather than intratendinous degeneration. Chronic cases may show synovial proliferation, fluid within the tendon sheaths and adhesions between the crossing tendons. Because the process is largely inflammatory and mechanical, it usually responds well to rest and load reduction.
Classification
Intersection syndrome is classified by which tendons cross. When a question says "intersection syndrome" without qualification it means the proximal type; mention the distal variant to score extra marks.
- Crossing tendons
- 1st (APL, EPB) over 2nd (ECRL, ECRB)
- Location
- 4-6 cm proximal to wrist
- Frequency
- Common (classic)
- Crossing tendons
- 3rd (EPL) over 2nd (ECRL, ECRB)
- Location
- At Lister tubercle
- Frequency
- Rare
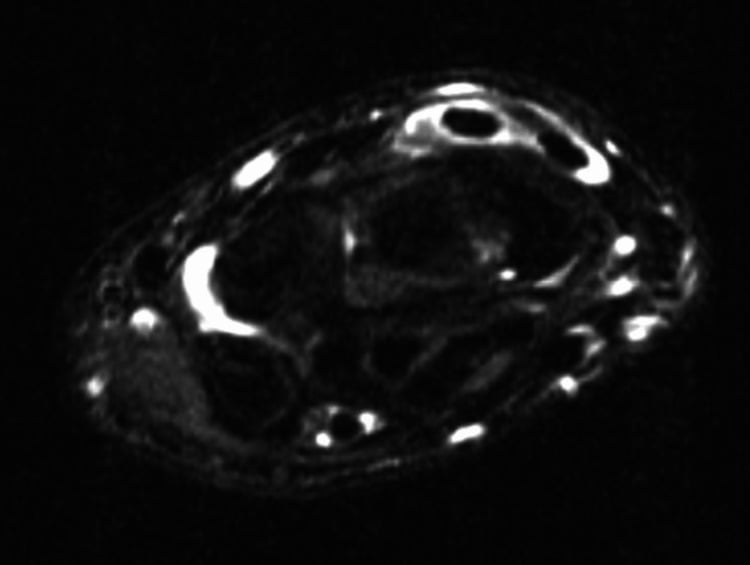
On MRI the distal form shows fluid around ECRL, ECRB and EPL where the third compartment crosses the second near Lister tubercle, which separates it from the proximal APL-EPB crossing.
Chronicity guides escalation rather than changing the diagnosis.
- Features
- Pain, swelling, crepitus after a load spike
- Management emphasis
- Rest, splint, NSAIDs
- Features
- Persistent pain, recurrent on return to sport
- Management emphasis
- Injection, technique/load review, rarely surgery
Clinical Assessment
History. Dorsoradial forearm pain proximal to the wrist, worse with wrist extension and gripping, and a rubbing, squeaking or grating sensation on wrist movement. Always ask about a change in load or a new activity: a recent increase in training or repetitive activity, and an occupation or sport involving repeated wrist extension.
Examination. Locate the point of maximal tenderness carefully; it is the key to the diagnosis.
- Tenderness and swelling over the intersection point, proximal to the radial styloid; the swelling may show as a raised dorsoradial contour
- Crepitus, and sometimes an audible squeak, felt or heard on active wrist flexion and extension: the "wet leather" sign, the classic clinical clue
- Sometimes localised erythema and warmth
- Pain reproduced by resisted wrist extension
- Finkelstein or Eichhoff may be mildly uncomfortable, but the pain is more proximal than in de Quervain
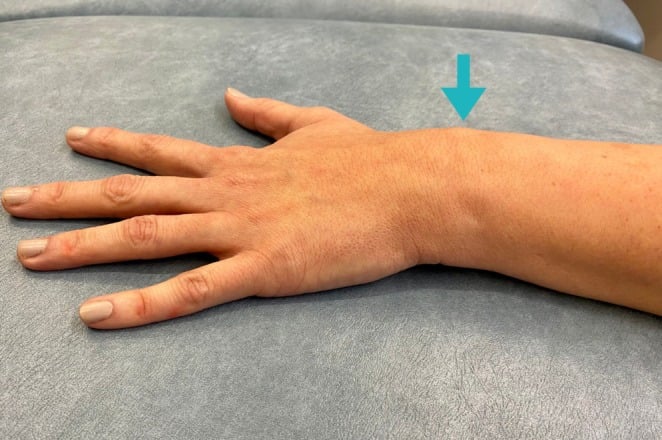
Surface landmarks. Lister tubercle and the bases of the second and third metacarpals orient the examiner to the APL/EPB crossing over ECRL/ECRB and keep palpation proximal to de Quervain territory.
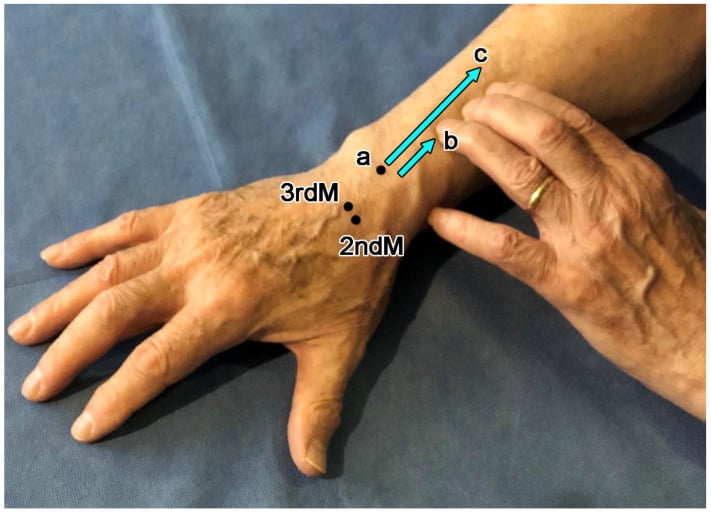
Site of maximal tenderness is everything. Intersection syndrome is proximal to the radial styloid (in the distal forearm); de Quervain is directly over the radial styloid at the first compartment. If you remember one thing, remember the location.
Investigations
A clinical diagnosis. Intersection syndrome is largely diagnosed on the site of pain and crepitus proximal to the wrist. Imaging confirms equivocal cases and excludes alternatives (de Quervain, radial bone stress, compartment syndrome); it is not a routine first step.
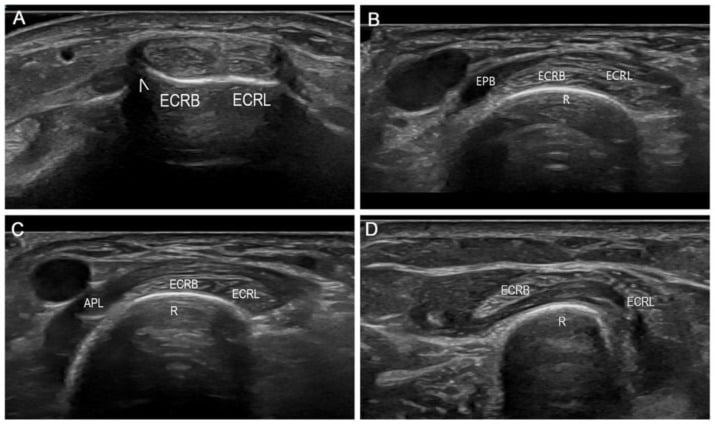
Ultrasound is the first-line imaging test. It is non-invasive, cheap and dynamic, and it can also guide injection. The findings:
- Peritendinous oedema and fluid at the crossing point
- Thickened tendon sheaths
- Sometimes hyperaemia on Doppler
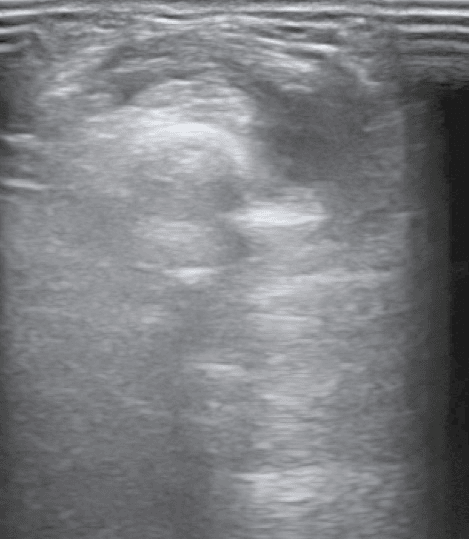
Compare the sides. Side-to-side scanning supports the assessment: the symptomatic crossing shows thicker hypoechoic tissue and altered tendon morphology.
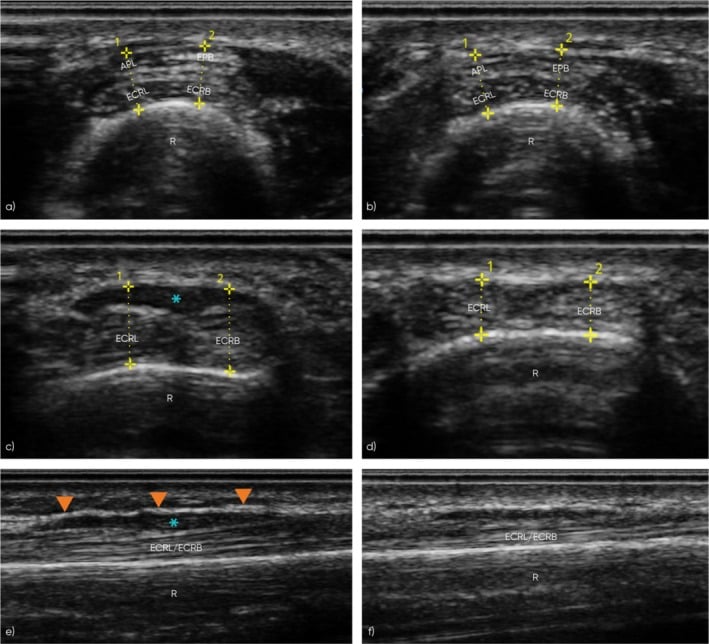
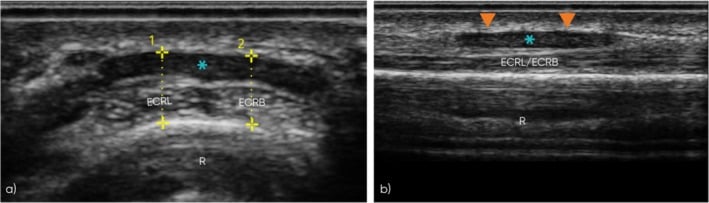
Map before you inject. Identifying the four tendons and the superficial radial nerve on ultrasound before placing a needle prevents tendon misidentification and unsafe needle placement.
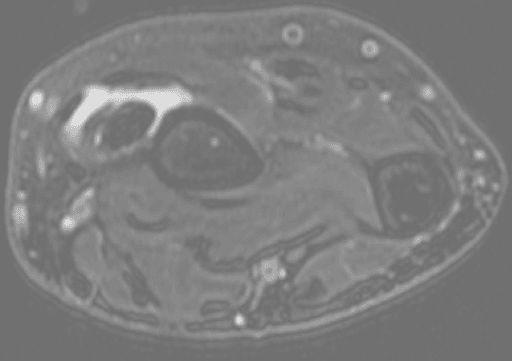
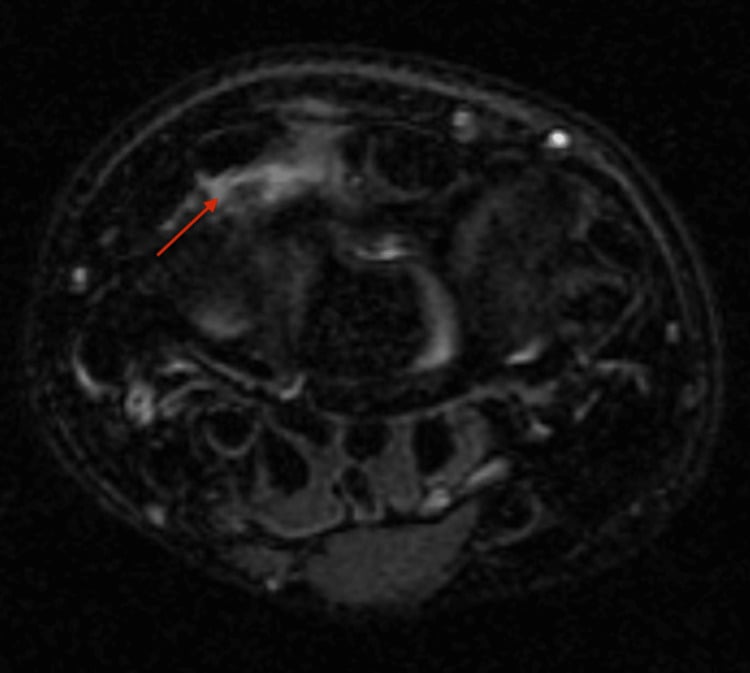
MRI is for problem-solving, reserved for equivocal or refractory cases. Fluid-sensitive sequences show high-signal peritendinous fluid or oedema at the intersection and can separate peritendinous oedema outside the sheath from fluid within it. MRI also helps map proximal versus distal involvement and excludes bone stress or other dorsal pathology.
Radiographs are usually normal and do not show the tenosynovitis itself. They are taken to exclude basal thumb or radial-sided wrist osteoarthritis, bony injury or radial bone stress.
Asymptomatic peritendinous fluid around the radial wrist extensors is common in elite rowers. A positive ultrasound or MRI does not make the diagnosis on its own - it must match localised symptoms and signs.
Differential Diagnosis
- Distinguishing features
- Pain, swelling and crepitus 4-6 cm proximal to the wrist
- Discriminating clue
- Tenderness proximal to the radial styloid; wet-leather squeak
- Distinguishing features
- Pain and tenderness directly over the radial styloid
- Discriminating clue
- Positive Finkelstein/Eichhoff; tenderness at the styloid, not proximal
- Distinguishing features
- Dorsoradial numbness and paraesthesia, no true tendon swelling
- Discriminating clue
- Positive Tinel over the nerve; sensory rather than tendon-stretch pain
- Distinguishing features
- EPL crossing the radial wrist extensors at Lister tubercle
- Discriminating clue
- Pain at Lister tubercle; consider attrition/rupture risk of EPL
- Distinguishing features
- Pain at the thumb base or just distal to the scaphoid
- Discriminating clue
- Grind test; radiographs show joint OA, pain is distal not proximal
- Distinguishing features
- Diffuse exertional forearm pain in endurance athletes
- Discriminating clue
- Pain is diffuse and load-dependent, no localised crepitus
The examiner almost always wants you to contrast intersection syndrome with de Quervain: it is the "not de Quervain" trap for the candidate who reflexively calls any radial wrist pain de Quervain. Lead with location (proximal forearm vs radial styloid), then the crossing tendons (1st over 2nd), then the crepitus sign. Mention Wartenberg syndrome to show breadth.
Management
The ladder has three rungs: conservative care for almost everyone, a corticosteroid injection when that fails, and surgical release of the second compartment for the rare refractory case.
Conservative care. First-line, and most patients settle with it.
- Relative rest and load modification: stop or modify the provoking activity, and correct technique and training-load errors
- A thumb spica or wrist (cock-up) splint with the wrist in slight extension for 2-3 weeks
- NSAIDs and ice for the inflammatory phase
- After 2-3 weeks, progressive stretching and graded strengthening before return to sport
Corticosteroid injection. For symptoms persisting despite adequate conservative treatment. The steroid goes into the second-compartment tendon sheath or peritendinous space at the intersection, and ultrasound guidance improves accuracy and is increasingly preferred.
Safe zones. Mapped safe zones place the treatment between the proximal crossing and the superficial-radial-nerve crossing, with a dorsal or volar trajectory chosen to reach the involved compartment safely.
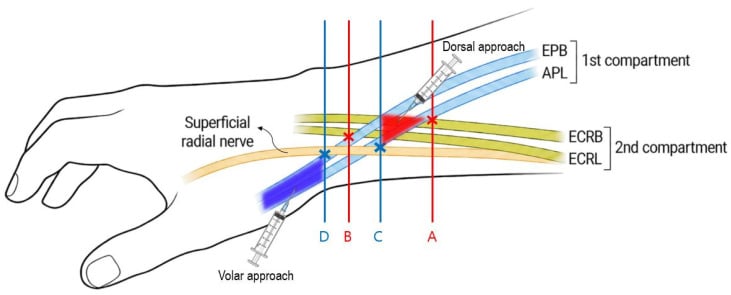
Hydrodissection. Saline hydrodissection at the intercompartmental space has been described as both diagnostic and therapeutic in a refractory case.
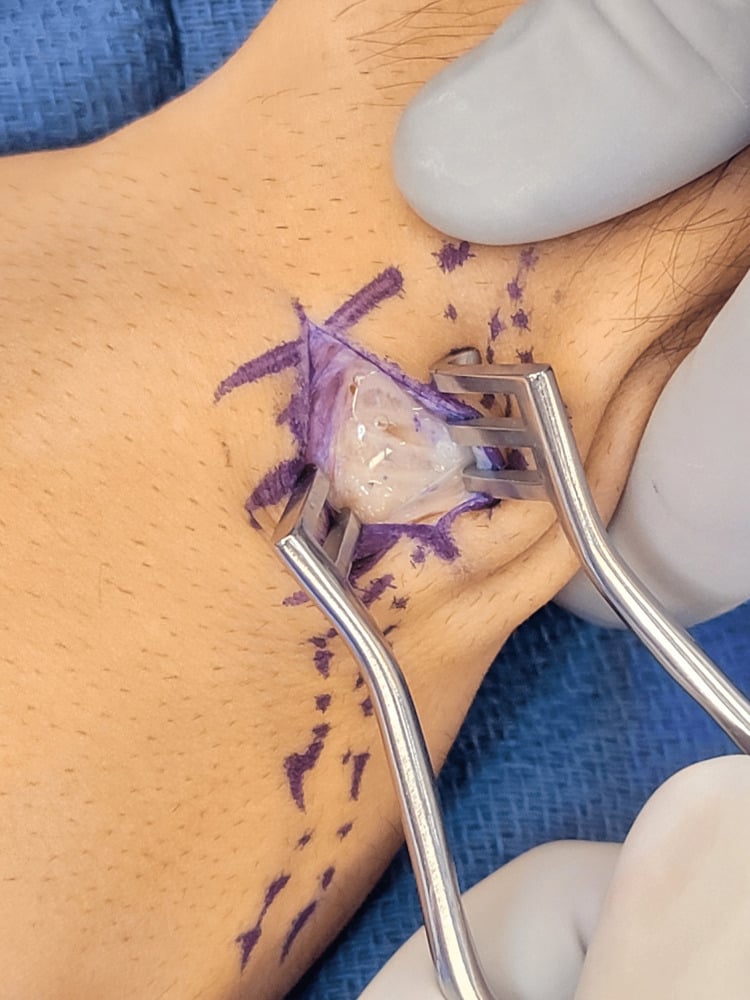
Surgical release. Rare, and reserved for refractory cases that have failed conservative care and injection. The second dorsal compartment is released (fasciotomy) at the intersection, with debridement of inflamed tissue or tenosynovectomy. Protect the superficial radial nerve, which crosses the operative field. In one reported case the exposure revealed a fluid collection and substantial tenosynovitis around ECRL and ECRB.
Return to Sport: Load Management and Technique Correction
The load spike is the cause. Intersection syndrome typically follows a sudden increase in volume or intensity: a pre-season ramp-up, a new training block, or a change of equipment. Recovery without addressing it simply sets up recurrence.
Graded, not calendar-based. After the initial 2-3 week rest and splint phase, advance through three stages only while symptom-free and crepitus-free; a flare means dropping back a stage.
- Pain-free wrist-extension range
- Graded loading
- Sport-specific drills
Objective recovery. A follow-up ultrasound showing restored tendon echogenicity and thickness, without fluid or hyperaemia, is an objective correlate of recovery before full load progression.
Rowing ("oarsman's wrist"). The feathering and squaring action repeatedly loads wrist extension and radial deviation. Coach a more neutral wrist through the drive and feather, review oar-handle size, grip and rigging (gearing, oar length, blade pitch), and discourage over-gripping. Cold, wet conditions and blistered hands worsen the grip and the friction.
Other sports and occupations. The same review applies to whatever the patient does:
- Weightlifting: wrist position and wrist-wrap use in pressing and curling
- Racquet sports: grip size and stroke mechanics
- Manual work: tool ergonomics and task rotation
Periodise the load. Reintroduce training volume incrementally and monitor symptoms. The same load-management logic prevents radial bone stress and forearm compartment syndrome in this rowing population, conditions studied alongside intersection syndrome in the imaging literature.
Complications
- Frequency
- Common if load not corrected
- Prevention / Management
- Graded return, technique and training-load review
- Frequency
- Uncommon
- Prevention / Management
- Injection, structured rehab, occasionally surgery
- Frequency
- Surgical risk
- Prevention / Management
- Careful dissection and nerve protection
- Frequency
- Rare
- Prevention / Management
- Recognise distal intersection; monitor EPL
- Frequency
- Possible
- Prevention / Management
- Counsel patient; avoid superficial injection
Outcomes and Prognosis
The outlook is generally excellent. Most patients recover fully with conservative treatment over a few weeks once the provoking load is removed.
What shifts it. Outcomes are better with early diagnosis, correction of the offending activity and a structured graded return. They are worse with continued overload without rest, delayed diagnosis (the condition is often mislabelled de Quervain) and failure to address sporting technique.
Guidelines, Registries & Global Practice
- Intersection syndrome is uncommon; an imaging series found it in about 1.9 percent of patients undergoing hand and wrist ultrasound in a specialised setting, with a mean age around 45 and a male predominance.
- It is concentrated in athletes and manual workers performing repetitive resisted wrist extension - rowers ("oarsman's wrist"), weightlifters, racquet-sport players and skiers feature repeatedly across reports worldwide.
- Asymptomatic peritendinous fluid around the radial wrist extensors is common in elite rowers, so the true symptomatic prevalence in athletic populations is hard to define.
No orthopaedic society publishes a dedicated, named intersection-syndrome guideline, so practice is anchored by reviews and primary-care guidance rather than a formal guideline document.
- Position
- Rest, thumb spica splint, NSAIDs, then progressive rehab; injection for persistence; surgery if refractory
- Notes
- Most cited treatment ladder for the condition
- Position
- Conservative care first; ultrasound-guided glucocorticoid injection for non-responders
- Notes
- Contemporary primary-care framing
- Position
- Stepwise conservative-to-surgical management of dorsal compartment tenosynovitis
- Notes
- No condition-specific guideline; principles applied
- Position
- Conservative-first, decompression of second compartment reserved for refractory cases
- Notes
- Consistent with the above
Intersection syndrome is a soft-tissue overuse condition managed largely without surgery and is not captured by joint-replacement registries (NJR, AJRR, AOANJRR). Evidence therefore comes from imaging series, small case series and reviews rather than national implant registries.
- In well-resourced settings, ultrasound-guided injection is increasingly standard for non-responders, improving accuracy.
- In limited-resource settings the diagnosis remains clinical (proximal tenderness plus crepitus), and landmark-guided injection or simple conservative care is effective.
- Surgical release is rarely needed and, when performed, is a low-cost day-case procedure - so management is feasible across all resource levels.
Know that intersection syndrome is proximal forearm friction tenosynovitis (1st over 2nd compartment), distinguished from de Quervain by location and crepitus, managed conservatively first with ultrasound-guided injection for non-responders and surgery only for refractory disease.
MCQ Practice Points
Q: Which tendons are involved in proximal intersection syndrome? A: The first compartment (APL and EPB) crossing over the second compartment (ECRL and ECRB).
Q: Where is the pain in intersection syndrome compared with de Quervain? A: About 4-6 cm proximal to the wrist (distal forearm), versus directly over the radial styloid in de Quervain.
Q: What is the classic clinical sign of intersection syndrome? A: Crepitus, often with an audible squeak ("wet leather" sign), over the crossing point on wrist movement.
Q: What is distal intersection syndrome? A: A rarer variant where the EPL (third compartment) crosses over the second compartment (ECRL, ECRB) at Lister tubercle.
Q: What is the first-line treatment for intersection syndrome? A: Conservative care - rest/activity modification, splinting in slight wrist extension, NSAIDs, then graded rehabilitation. Injection if it fails; surgery rarely.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 24-year-old competitive rower presents with a 3-week history of dorsoradial forearm pain about 5 cm proximal to the wrist, with swelling and a squeaking sensation on moving the wrist. There is local crepitus. What is your diagnosis and how would you manage it?”
“An examiner asks you to compare intersection syndrome with de Quervain tenosynovitis. How do you tell them apart and why does it matter?”
“A 38-year-old manual worker has had intersection syndrome for 6 months despite rest, splinting, NSAIDs and one ultrasound-guided corticosteroid injection. He still has pain and crepitus. How would you proceed, and what are the surgical considerations?”
Anatomy
- 1st compartment (APL, EPB) crosses 2nd (ECRL, ECRB)
- Crossing point 4-6 cm proximal to wrist
- Distal variant: EPL crosses 2nd at Lister tubercle
- Superficial radial nerve at risk in surgery
Clinical
- Dorsoradial forearm pain proximal to styloid
- Crepitus / wet-leather squeak
- Rowers, weightlifters, racquet sports
- Worse with resisted wrist extension
Investigations
- Largely clinical diagnosis
- Ultrasound first-line: peritendinous fluid
- MRI for equivocal/refractory cases
- Caution: fluid common in asymptomatic rowers
Management
- Rest and activity modification
- Splint in slight wrist extension + NSAIDs
- Graded rehab before return to sport
- Ultrasound-guided injection if it fails
- Second-compartment release rarely needed
Differentials
- De Quervain (at the styloid)
- Wartenberg syndrome (sensory)
- Distal intersection (EPL)
- Radial bone stress / compartment syndrome
Key Points
- Location proximal = NOT de Quervain
- Crepitus is the classic sign
- Conservative care cures most
- Surgery is a rare last resort
Evidence Base and Key Studies
Balakatounis et al. - Synthesis of Evidence for Treatment
- Intersection syndrome is a rare sports overuse injury caused by friction at the crossing of the first and second dorsal compartments of the forearm
- Differential diagnosis from de Quervain tenosynovitis must be made carefully; clinical examination is central, with MRI and ultrasound as adjuncts
- First-line treatment is rest, thumb spica splinting, analgesia and oral NSAIDs, followed after 2-3 weeks by progressive stretching and strengthening
- Corticosteroid injection adjacent to the injury is useful for persistent symptoms; surgery is reserved for refractory cases
Draghi & Bortolotto - Intersection Syndrome: Ultrasound Imaging
- Re-evaluation of 1,131 hand and wrist ultrasound reports identified 21 patients with intersection syndrome
- Intersection syndrome was found in about 1.9% of patients in a specialised hospital setting
- Mean age 45 years (range 22-60), with both proximal (more common) and distal forms identified
- Ultrasound is a non-invasive, simple and economical method to identify the syndrome, define tendon sheath anatomy and exclude other conditions
Montechiarello et al. - Ultrasound Findings and Diagnostic Value
- Four patients with symptoms suggestive of intersection syndrome (pain, swelling, erythema, oedema of the wrist) were studied with ultrasound
- All four showed peritendinous oedema and synovial fluid within the tendon sheaths at the intersection of the first and second dorsal compartments
- The authors describe these as typical and reliable sonographic signs of the syndrome
- Ultrasound may eliminate the need for more expensive imaging tests
Drew et al. - Normative Imaging in Asymptomatic Elite Rowers
- 19 asymptomatic senior and under-23 elite rowers underwent ultrasound and MRI of the forearms
- Peritendinous fluid of ECRL (53%) or ECRB (32%) was a common finding on ultrasound
- MRI detected these changes at a higher rate than ultrasound
- Imaging findings seen in symptomatic populations were present in asymptomatic elite rowers, so caution is needed when diagnosing intersection syndrome on imaging alone
Skinner - Intersection Syndrome and Saline Hydrodissection
- A 26-year-old pregnant rower with dorsoradial wrist pain and a rubbing/squeaking sensation was initially treated as de Quervain
- Nine months of conservative de Quervain therapy and a landmark-guided corticosteroid injection failed
- In-clinic ultrasound showed tenosynovitis at the intersection of the first and second compartments, confirming intersection syndrome
- Ultrasound-guided saline hydrodissection of the intercompartmental space gave immediate relief and served as both a diagnostic and therapeutic tool
Pujalte et al. - Injections of the Hand and Wrist (Part II)
- Intersection syndrome is described as an overuse injury
- Management involves rest, activity adjustment, bracing, NSAIDs and physical or occupational therapy
- For symptoms not improved by these measures, an ultrasound-guided glucocorticoid injection may be administered
- Discussed alongside de Quervain and carpal tunnel as common injectable wrist conditions
Alter et al. - Distal Intersection Syndrome
- Three cases of distal intersection syndrome (DIS) between the second and third dorsal compartments, a rarer and more distal entity than the classic form
- Diagnosis was confirmed on MRI in all three patients
- Initial treatment was NSAIDs and immobilisation; one patient ultimately required surgical debridement and partial tenosynovectomy
- All patients improved and returned to baseline activity; the authors warn that extensor tendon rupture is possible