Post-surgical stiffness | TKA & ACL | Cyclops lesion | MUA
- Arthrofibrosis is a diagnosis of exclusion - rule out infection, component malposition/oversizing, CRPS and poor rehab first
- Driven by aberrant myofibroblasts depositing type I collagen in a proinflammatory joint; TGF-beta is the best-established pathway
- Manipulation under anaesthesia (MUA) works best early - typically within 6-12 weeks of the index surgery, before scar matures
- Cyclops syndrome = fibrous nodule anterior to the ACL graft causing a painful, springy loss of terminal extension
- Prevention beats cure - good pain control, early range of motion, correct surgical technique and avoiding graft malposition
- “MUA after ~3 months is far less effective and risks fracture/extensor disruption
- “No biopsy and no biomarker confirms arthrofibrosis - it is clinical plus exclusion
- “Cyclops = LOSS OF EXTENSION; global arthrofibrosis = loss of flexion AND extension
- “Patella baja on lateral film suggests infrapatellar contracture - a poor-prognosis pattern
Overview and Epidemiology
Definition. Arthrofibrosis is the formation of excessive scar tissue within and around the knee that mechanically restricts movement, causing stiffness, pain and functional loss. A critical analysis review defines it after total knee arthroplasty (TKA) in the same terms: new formation of excessive scar tissue producing limited range of motion, pain and functional deficits (Ramos et al., JBJS Reviews 2023; DOI).
Arthrofibrosis = pathological scar causing restricted motion AFTER excluding other causes of stiffness. It is a clinical diagnosis of exclusion, not a radiological or histological one.
Why it matters. A stiff knee is one of the most disabling outcomes after otherwise technically sound surgery. Patients cannot manage stairs, get out of chairs or walk normally, and revision for stiffness alone is notoriously unsatisfying: patient satisfaction after it is often modest.
How common. After TKA, clinically significant stiffness requiring manipulation occurs in roughly 2-5% of knees in modern series. After ACL reconstruction, cyclops lesions are seen in up to about 27% of second-look arthroscopies, but symptomatic cyclops syndrome is far less common, around 3-11% depending on the series.
Pathophysiology
Healing that fails to switch off. Arthrofibrosis is fundamentally a dysregulated wound-healing response. Normal healing resolves; arthrofibrosis does not.
The cellular driver. The pathophysiology is multifactorial and centres on aberrant activation and proliferation of myofibroblasts in response to a proinflammatory environment, with transforming growth factor-beta (TGF-beta) signalling the best-established pathway (Ramos et al., JBJS Reviews 2023; DOI). The cascade runs from trigger to tethered joint:
- Surgical or injury trigger - tissue damage and bleeding create a proinflammatory environment.
- Inflammation - cytokines recruit fibroblasts and activate them.
- Myofibroblast transformation - fibroblasts differentiate into contractile myofibroblasts.
- Excess matrix - myofibroblasts deposit large amounts of matrix, primarily type I collagen.
- Contraction and maturation - the scar contracts and cross-links, mechanically tethering the joint.
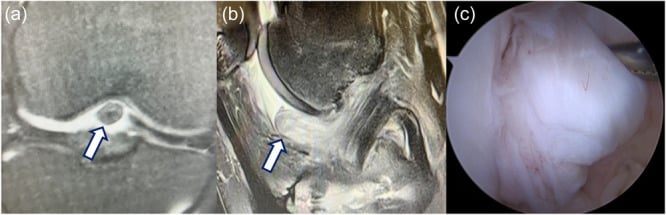
The cyclops lesion. The cyclops lesion is a localised variant. Second-look studies describe it as a fibroproliferative nodule arising from tibial-tunnel drilling debris, ACL stump remnants or broken graft fibres, sometimes from repeated graft impingement on the notch in terminal extension (Delince et al., Arthroscopy 1998; DOI). Its bluish, vascular arthroscopic appearance with surrounding reddish tissue ("eyes") gives it the name.
Contributory factors. Surgery, the patient and the rehabilitation each contribute:
- Surgical - graft malposition or oversizing, notch impingement, retained drilling debris, overstuffed patellofemoral joint, haematoma.
- Patient - tendency to aggressive scarring, prior surgery, diabetes, lower pain threshold.
- Rehabilitation - inadequate pain control and delayed mobilisation allow scar to mature unopposed.
Classification
There is no single universally accepted classification. The most useful exam frameworks are by pattern and by whether a treatable cause is present.
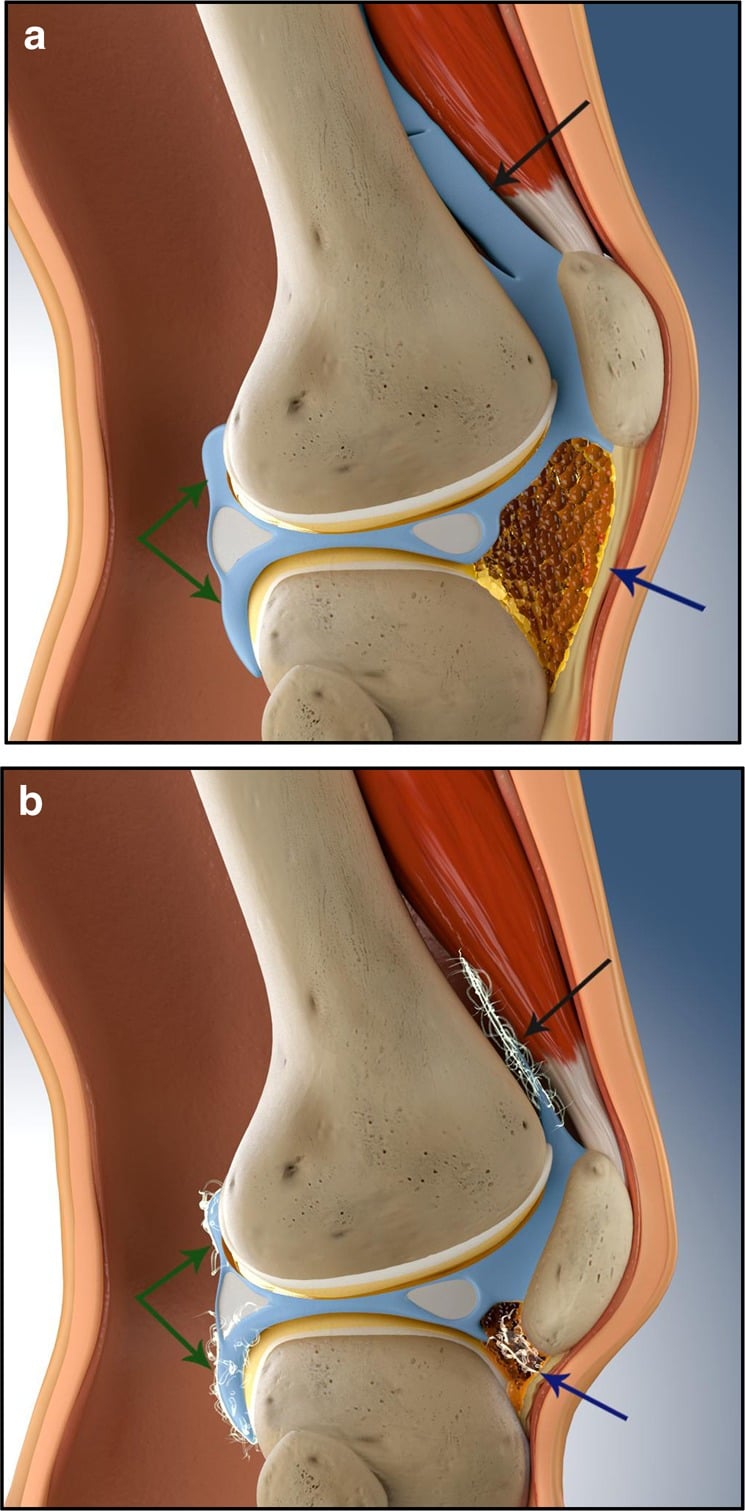
By pattern. Arthrofibrosis is best thought of as a spectrum, from pan-capsular scarring after arthroplasty or major trauma to a discrete nodule after ACL reconstruction.
- Setting and Key Feature
- After TKA or major trauma; pan-capsular scar
- Motion Affected
- Flexion + extension
- First-line Treatment
- Therapy; MUA if early; release if late
- Prognosis
- Variable
- Setting and Key Feature
- After ACL reconstruction; discrete nodule anterior to the graft
- Motion Affected
- Terminal extension
- First-line Treatment
- Arthroscopic excision
- Prognosis
- Good after excision
- Setting and Key Feature
- After major knee surgery; dense scar in the fat pad and patellar tendon, often with patella baja
- Motion Affected
- Flexion mainly
- First-line Treatment
- Stage-dependent: calm early disease, release in the residual stage
- Prognosis
- Poor
- Setting and Key Feature
- Posterior contracture
- Motion Affected
- Extension
- First-line Treatment
- -
- Prognosis
- Variable
Primary or secondary. Primary (idiopathic) arthrofibrosis is an exaggerated fibrotic response with no identifiable mechanical cause. Secondary arthrofibrosis is stiffness driven by a correctable problem: a malpositioned or oversized component, instability, infection, CRPS or poor rehabilitation. It can arise in any setting, the motion lost is variable, and treating the cause comes first. Identifying secondary causes is the single most important step, because they change management completely.
Examiners want to hear you separate primary scar from secondary stiffness. Always say: "First I would exclude a treatable cause before labelling this primary arthrofibrosis."
STIFFExclude Before Diagnosing
Hook:A STIFF knee needs every other cause excluded before you blame scar.
Clinical Presentation
History. The patient has persistent stiffness despite a technically satisfactory operation and appropriate rehabilitation. The pain is often disproportionate and worse at the extremes of motion, and the functional loss shows on stairs, at sit-to-stand and in kneeling. After ACL reconstruction, cyclops syndrome presents as a painful loss of full extension, sometimes with an audible or palpable clunk near terminal extension.
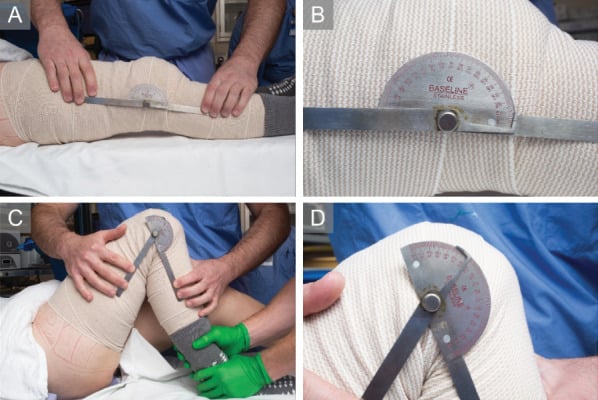
Range of motion. Document active and passive flexion and extension and compare with the other side. Global arthrofibrosis loses both; a cyclops lesion loses terminal extension, with a springy, sometimes clunking end-feel.
Effusion and warmth. A warm, hot or persistently swollen knee should raise suspicion of infection or active inflammation rather than mature scar.
Stability. Assess ligamentous stability. Instability mimics and aggravates stiffness, and an unstable knee will not respond to manipulation.
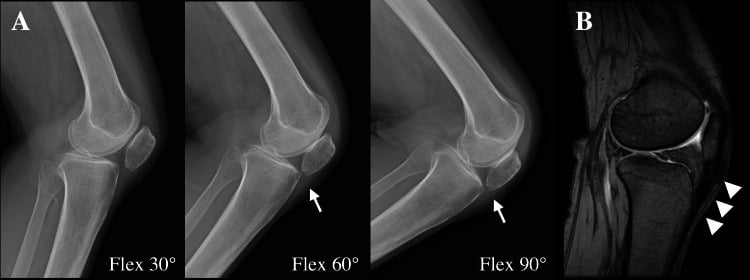
The patella. Check patellar height and tracking. Patella baja suggests infrapatellar contracture, a poor-prognosis pattern.
A hot, swollen, painful knee with raised inflammatory markers may be infected. Never manipulate or release a knee until infection has been excluded - manipulating a septic joint is dangerous and worsens outcomes.
Investigations
What they are for. Investigations serve mainly to exclude other causes; there is no test that proves arthrofibrosis. In the TKA setting the review is explicit that imaging helps rule out specific causes of stiffness, biopsy is not indicated and no biomarkers of arthrofibrosis exist (Ramos et al., JBJS Reviews 2023; DOI).
Bloods and aspiration. CRP, ESR and white cell count screen for periprosthetic or septic joint infection. Consider joint aspiration for cell count, differential and culture if infection is suspected.
Radiographs. Plain films assess component position and size, alignment, patellar height (baja) and loosening. Overstuffing of the patellofemoral joint and malrotation are the key technical mimics to identify.
CT. CT, with rotational protocols after TKA, assesses component rotation and sizing when malposition is suspected, a treatable secondary cause of stiffness.
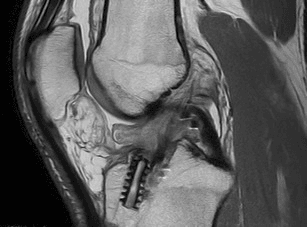
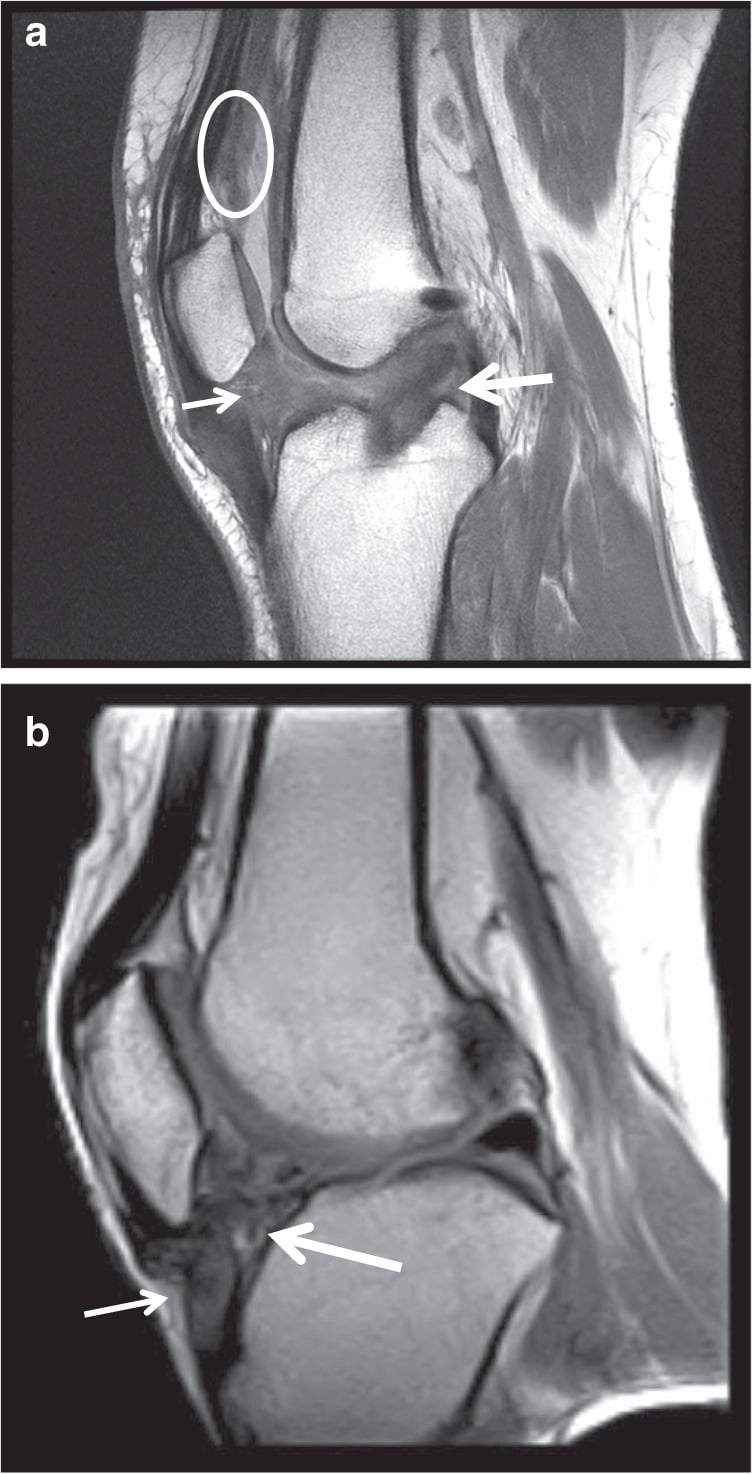
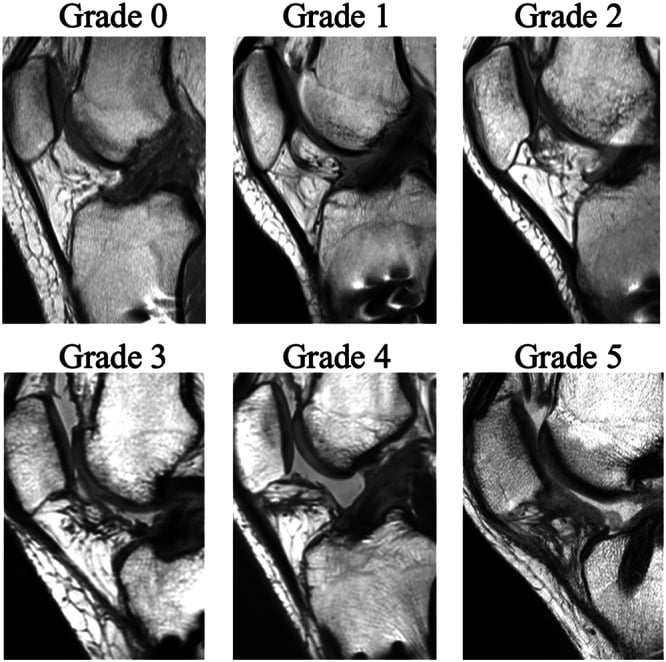
MRI. After ACL reconstruction MRI is the key test for a cyclops lesion, and it also assesses graft position and notch impingement. Metal artefact limits MRI after arthroplasty.
A focal nodule anterior to the ACL graft that is low-to-intermediate signal, in a patient with loss of extension, is the radiological signature of a symptomatic cyclops lesion.
Management
Management is staged and escalating: optimise rehabilitation, then manipulation, then surgical release. Any secondary cause is always treated first.
Prevention and rehabilitation. Multimodal analgesia and early aggressive physiotherapy keep the knee moving while scar is immature. Address swelling, encourage extension as well as flexion, and set range-of-motion milestones. Rehabilitation should be early and consistent, but not violent: uncontrolled loading can damage cartilage and provoke the inflammatory response that sustains fibrosis.
The evidence for prevention. Manipulation rates were 4.75% before and 2.24% after a centre introduced a multimodal pain-management protocol, which is consistent with good analgesia permitting earlier motion - though these are two consecutive eras rather than two randomised arms, and no statistical test was reported (Lavernia et al., J Arthroplasty 2008; DOI). Adjuncts at the index operation have also been explored: autologous platelet gel and fibrin sealant improved early range of motion and reduced the incidence of arthrofibrosis and forced manipulation in one controlled study (Everts et al., Knee Surg Sports Traumatol Arthrosc 2007; DOI).
Manipulation under anaesthesia. MUA is indicated for diffuse stiffness that fails to progress with therapy, ideally early (within ~6-12 weeks). It is performed gently under full muscle relaxation with the hand close to the joint, high on the tibia, to minimise lever-arm forces.
MUA is most effective early while scar is immature. Performed late (after ~3 months) it is less effective and carries a real risk of periprosthetic fracture, patellar tendon avulsion or wound dehiscence.
Arthroscopy. For a cyclops lesion, arthroscopic excision of the nodule, with notchplasty if there is impingement, reliably restores extension. Diffuse arthrofibrosis is treated by arthroscopic lysis of adhesions and selective release, often combined with a gentle manipulation at the same sitting.
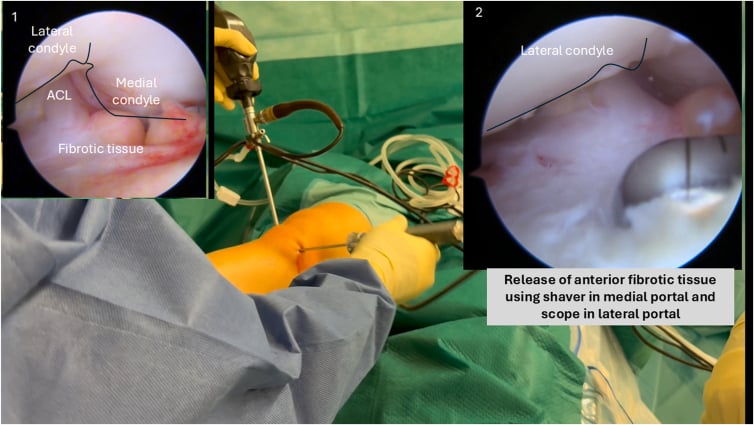
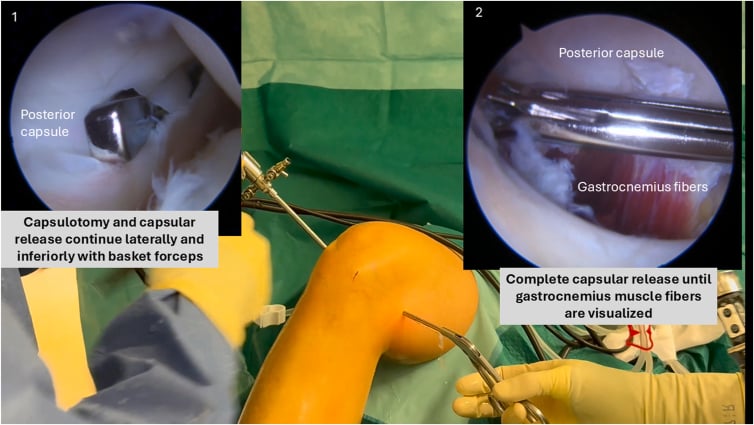
Arthroscopy after TKA. Knee arthroscopy after ipsilateral TKA, commonly for patellar clunk, synovial hyperplasia or arthrofibrosis, was not associated with an elevated risk of periprosthetic joint infection in a registry-matched study, so arthroscopic treatment of post-TKA stiffness is a reasonable option (Wahlig et al., J Arthroplasty 2024; DOI).
Open surgery and revision. Open release or quadricepsplasty is for severe or recurrent diffuse scar resistant to arthroscopic treatment. Revision arthroplasty is reserved for stiffness due to component malposition or oversizing, and is typically a last resort when scar alone is the problem (Ramos et al., JBJS Reviews 2023; DOI).
If stiffness is due to a malpositioned or oversized component, no amount of manipulation or release will help - the implant must be revised. Diagnose this before operating for "arthrofibrosis".
Quadricepsplasty (Judet and Thompson)
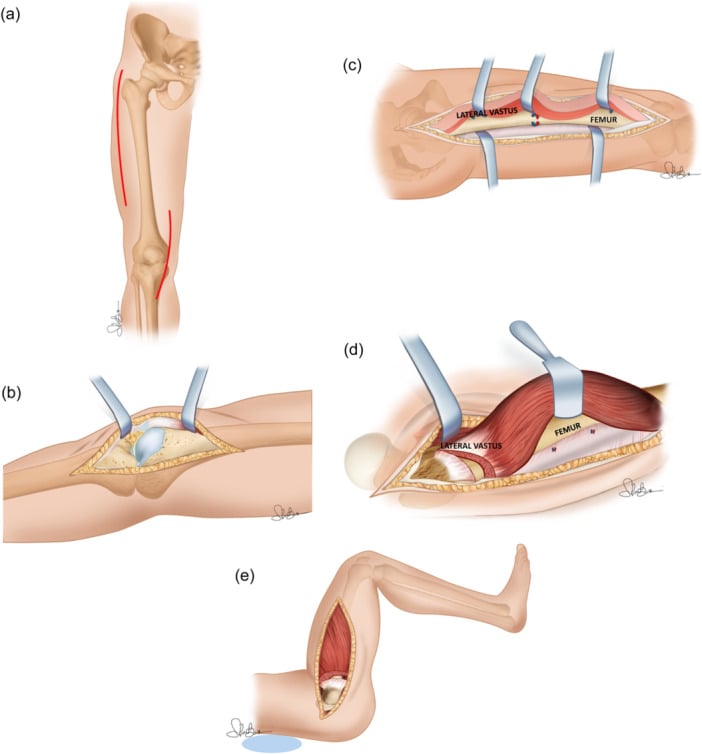
What it is. Quadricepsplasty is the surgical lengthening or release of a scarred, contracted extensor mechanism that mechanically blocks flexion. The typical case is dense extra-articular quadriceps scarring after a distal femoral fracture or prolonged immobilisation, or recalcitrant arthrofibrosis that has failed arthroscopic lysis.
Thompson quadricepsplasty (1944). A single-stage proximal release. Through a midline or lateral approach, free the intra-articular adhesions and the patella, then release the scarred vastus intermedius and rectus from the femur, dividing the patellar retinacula as needed and checking flexion intra-operatively. It is simpler, but splitting the vasti risks devascularising or denervating them and leaving an extension lag.
Judet quadricepsplasty (1959). A more extensive, sequential release performed distal to proximal and tested at each stage:
- Release intra-articular and peripatellar adhesions and mobilise the patella.
- Release the vastus lateralis and the lateral intermuscular septum.
- Free the vastus intermedius off the femur.
- Only if flexion is still inadequate, release the rectus femoris origin.
Flexion is checked after each step and the release stopped once adequate flexion (around 90 to 120 degrees) is reached. That preserves extensor continuity, strength and blood supply better than a single proximal release and leaves less extension lag, at the cost of a larger dissection.
After the release. Protect the extensor mechanism's continuity and vascularity and achieve the gain on the table. Immediate continuous passive motion and aggressive supervised rehabilitation, essential after either operation, hold it. Complications include an extension lag (quadriceps weakness), wound and skin problems, patellar fracture and recurrence. A frank extensor-mechanism rupture is a different problem, covered in the extensor-mechanism-ruptures topic.
Infrapatellar Contracture Syndrome (Paulos)
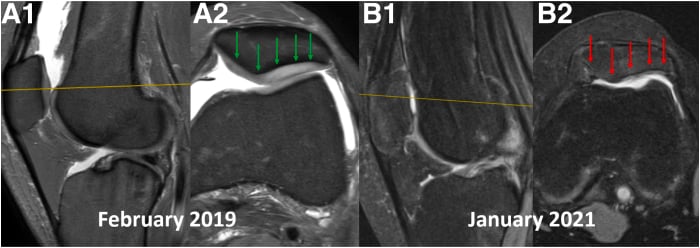
The entity. Infrapatellar contracture syndrome (ICS) is an aggressive, exaggerated fibrotic response centred on the anterior compartment - the infrapatellar fat pad, peripatellar retinaculum and patellar tendon. It "captures" the patella and progressively shortens the extensor mechanism, producing patella baja (infera).
The pathognomonic sign. Patellar mobility is markedly reduced in both the mediolateral and superoinferior directions (patellar entrapment, the "shelf sign"), with painful restriction of flexion and extension and a developing low-riding patella.
Paulos stages.
- Prodromal (roughly 2 to 8 weeks) - painful, decreasing motion, quadriceps shutdown and early loss of patellar mobility. This is the window to intervene with anti-inflammatory measures and gentle, controlled therapy.
- Active (roughly 6 to 20 weeks) - florid scarring, marked global restriction, skin changes and developing patella baja.
- Residual / burnt-out (after several months) - inflammation settles, but a fixed contracture, established patella infera and secondary patellofemoral arthrosis remain.
Management follows the stage. In the prodromal and active inflammatory stages, aggressive manipulation or surgery inflames the process and makes it worse; early disease is calmed, not forcefully manipulated. The residual stage is treated surgically with anterior-interval, medial and lateral retinacular release and fat-pad debridement, with quadricepsplasty for the contracted extensor mechanism. Outcomes are guarded once patella infera and arthrosis are established, and once patella infera is fixed the prognosis is poor.
The detailed measurement of patellar height (Insall-Salvati, Caton-Deschamps, Blackburne-Peel) is developed in the patellar-height-abnormalities topic.
Complications
Recurrence. Scar can re-form, especially after late or repeated intervention. Aggressive post-procedure physiotherapy is essential to hold the gains made.
Manipulation injuries. Forceful or late manipulation can cause the periprosthetic fracture, patellar tendon avulsion and wound dehiscence listed under MUA, and haemarthrosis.
Persistent pain and CRPS. Some patients have ongoing pain out of proportion. Complex regional pain syndrome both mimics and complicates arthrofibrosis.
Guidelines, Registries & Global Practice
Global Epidemiology
- Clinically significant stiffness needing manipulation after TKA occurs in roughly 1.5-5% of knees worldwide; younger, obese and smoking patients are over-represented.
- Cyclops lesions appear in up to ~27% of second-look arthroscopies after ACL reconstruction, but symptomatic cyclops syndrome affects only ~3-11%.
- A narrow intercondylar notch and graft malposition are recognised anatomical/technical risk factors for cyclops formation.
Side-by-Side Guidance
- Stance
- Prevention and staged escalation
- Emphasis
- Early ROM, multimodal analgesia, MUA before scar matures
- Stance
- Optimise rehab pathways
- Emphasis
- Pain control and physiotherapy to prevent stiffness after TKA/ACL
- Stance
- ACL focus
- Emphasis
- Correct graft placement and debris removal to prevent cyclops; arthroscopic excision when symptomatic
- Stance
- Exclude treatable cause first
- Emphasis
- Never label stiffness arthrofibrosis until infection/malposition excluded
Registry and Outcome Data
- Arthroplasty registries (NJR, AJRR, AOANJRR) capture manipulation and reoperation for stiffness as quality indicators, consistently showing higher rates in younger TKA recipients.
- Registry and cohort data confirm stiffness is a leading non-infective reason for early reoperation after TKA.
High- vs Limited-Resource Practice
Multimodal analgesia, rotational CT, MRI for cyclops, and arthroscopic lysis/excision are routinely available, enabling early diagnosis and staged, joint-preserving treatment.
Where MRI and arthroscopy are scarce, diagnosis is clinical and treatment leans on physiotherapy and manipulation. Late presentation with mature scar worsens outcomes, underscoring the value of prevention through good early rehabilitation.
MCQ Practice Points
Q: How is arthrofibrosis diagnosed? A: Clinically and by exclusion. There is no confirmatory biopsy and no biomarker - rule out infection, malposition, instability and CRPS first.
Q: What is the best-established profibrotic pathway? A: TGF-beta signalling, driving myofibroblast activation and type I collagen deposition.
Q: When is manipulation under anaesthesia most effective after TKA? A: Early - within roughly 6 to 12 weeks, before scar matures. Late MUA is less effective and riskier.
Q: What motion does a cyclops lesion typically block? A: Terminal extension. It is a fibrous nodule anterior to the ACL graft, treated by arthroscopic excision.
Q: Which patients are at higher risk of needing MUA after TKA? A: Younger (under 60), obese and smokers. Younger age carries the largest crude relative risk (3.46) - but these are unadjusted single-variable figures from a billing-code database, and the study's own combined stratum shows the factors overlap heavily rather than acting independently.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 58-year-old woman is 10 weeks after a primary TKA. She has poor range of motion (5 to 75 degrees) despite physiotherapy and is in pain. How do you assess and manage her?”
“A 24-year-old man is 4 months after hamstring ACL reconstruction. He cannot fully straighten the knee, has anterior pain and a palpable clunk near terminal extension. What is your diagnosis and management?”
“A 45-year-old man has had two prior knee operations and now has severe stiffness with patella baja on the lateral radiograph. Manipulation has already failed once. How do you proceed?”
Key Concepts
- Pathological scar restricting knee motion
- Diagnosis of exclusion - no biopsy, no biomarker
- Myofibroblast + type I collagen; TGF-beta key pathway
- Spectrum: diffuse (TKA) to localised (cyclops)
Exclude First
- Infection (CRP/ESR/aspirate)
- Component malposition or oversizing
- Instability
- CRPS and inadequate rehabilitation
Cyclops Lesion
- After ACL reconstruction
- Loss of terminal EXTENSION + clunk
- Fibrous nodule anterior to graft on MRI
- Arthroscopic excision (+ notchplasty)
Management Ladder
- Prevention: analgesia + early ROM
- MUA: best within 6-12 weeks
- Arthroscopic lysis of adhesions
- Open release / revision (last resort)
Risk Factors
- Younger age (under 60) - strong
- Obesity, smoking
- Multiple prior surgeries
- Narrow notch (cyclops)
Evidence and Key Studies
Arthrofibrosis After TKA: Critical Analysis Review
- Arthrofibrosis is a clinical diagnosis of exclusion
- No biopsy and no biomarker confirms it
- Myofibroblasts deposit type I collagen; TGF-beta is the key pathway
- Revision arthroplasty is reserved as a last resort
Multimodal Pain Management and Arthrofibrosis
- Manipulation rate fell from 4.75% to 2.24% with multimodal analgesia
- Better early pain control allows earlier mobilisation
- Supports prevention over later intervention
- Recommends multimodal protocols for TKA
Risk Factors for Manipulation After TKA
- Overall MUA rate after TKA was 1.51%
- Younger age (under 60) is a strong risk factor (RR 3.46)
- Obesity and nicotine dependence increase risk
- Diabetes and depression were not significant risk factors
Multifactorial Etiopathogenesis of the Cyclops Lesion
- Cyclops is a fibroproliferative nodule, multifactorial in origin
- Drilling debris and stump remnants are key sources
- Graft malposition causing notch impingement contributes
- Arthroscopic resection (plus notchplasty) restores extension
Cyclops Syndrome After Double-Bundle ACL Reconstruction
- Symptomatic cyclops syndrome occurred in 3.61%
- More common with quadriceps than hamstring graft
- Mean extension loss ~6 degrees with early quad dysfunction
- Arthroscopic debridement restored motion in most
Intercondylar Notch Size and Cyclops Formation
- Cyclops lesions in 27.3% but symptomatic in only 10.9%
- Smaller notch in the cyclops group - but 12 of 15 were women, so notch size and sex cannot be separated
- Higher tunnel-to-notch ratio in the cyclops group
- Most cyclops lesions are asymptomatic incidental findings