Valgus Stress | Grade I-III | Usually Conservative | Combined ACL
- sMCL is PRIMARY restraint to valgus at 30 degrees
- Most MCL injuries heal conservatively (90%+)
- Combined MCL/ACL: treat ACL, MCL heals with rehab
- Surgery indicated: chronic instability, Grade III with ACL, multiligament
- Test at 30 degrees flexion to isolate MCL
- “Test at 0 degrees: posteromedial corner involvement if unstable
- “Stener lesion equivalent: sMCL displaces over pes anserinus
- “sMCL femoral attachment lies just proximal-posterior to medial epicondyle
- “POL (posterior oblique ligament) is the key dynamic posteromedial stabiliser
Overview and Epidemiology
The MCL is the most common knee ligament injury and is usually treated without an operation: over 90% heal without surgery, and even a complete tear usually heals with bracing and rehabilitation. Functional bracing and early range of motion are the key.
Why it heals. The ligament is extra-articular and has a good blood supply, so its healing capacity is excellent. That is what separates it from the ACL and PCL.
Who. Males more than females, in the contact sports (football, rugby, hockey) and in skiing, where the combined ACL and MCL injury is common. Injuries are often combined.
Mechanism. Valgus stress is the most common mechanism: a contact blow to the lateral side of the knee, or a non-contact cutting or pivoting movement. External rotation may also injure the ligament, and the same valgus mechanism commonly produces a combined ACL and MCL injury.
Anatomy and Biomechanics
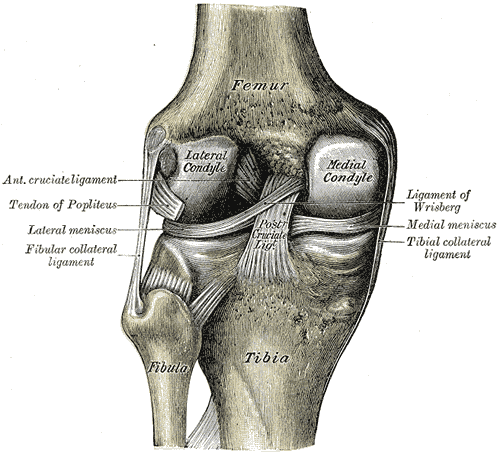
Three static stabilisers. LaPrade's quantitative anatomy describes the medial side as three primary static stabilisers: the superficial MCL (sMCL), the deep MCL (dMCL) and the posterior oblique ligament (POL).
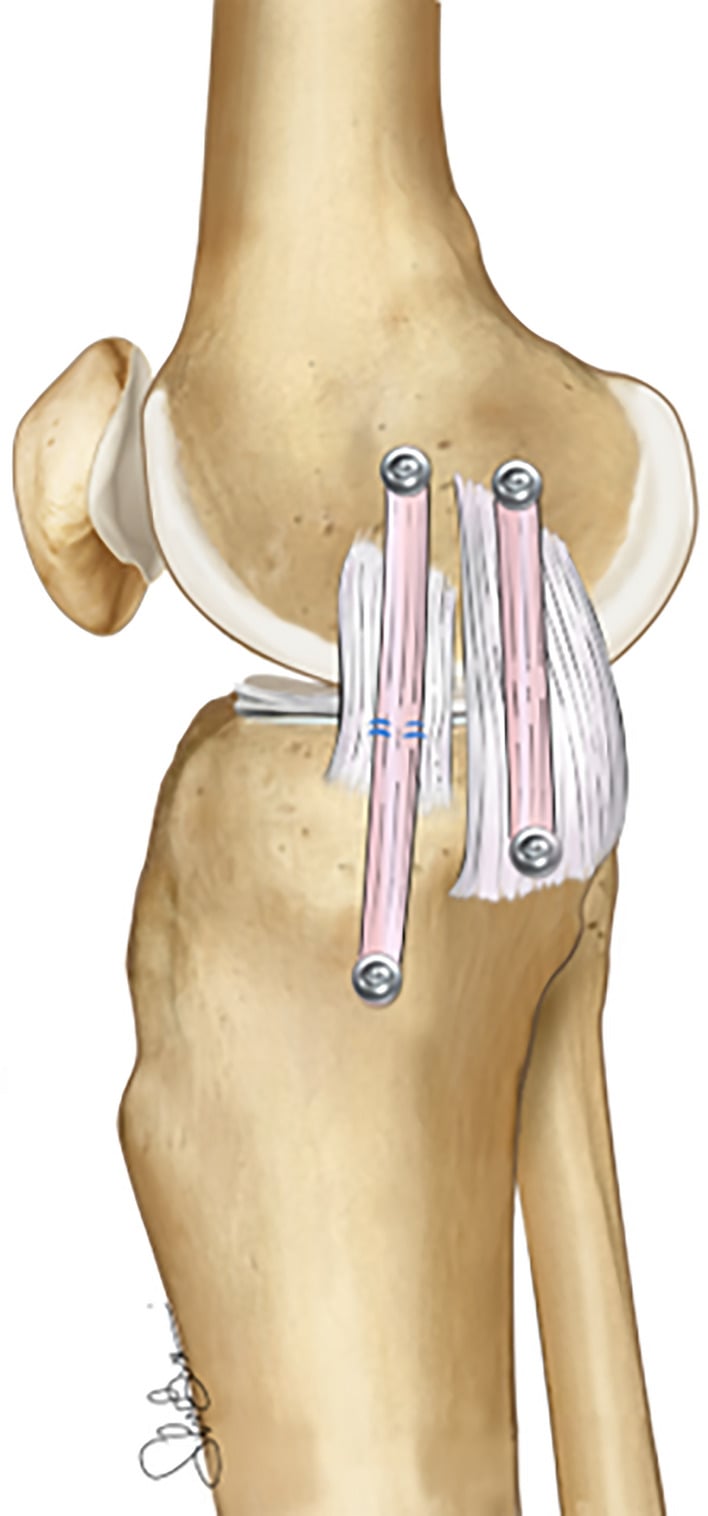
Superficial MCL. The primary static restraint to valgus and a key secondary restraint to external and internal tibial rotation. Its femoral attachment is a small depression just proximal and posterior to the medial epicondyle, on average a few millimetres from it, not several centimetres proximal to the joint. The ligament averages 9 to 10 cm in length and has two tibial attachments: a proximal soft-tissue attachment to the meniscus and a distal, firm bony attachment roughly 6 cm below the joint line, deep to the pes anserinus.
Deep MCL. A capsular thickening with meniscofemoral and meniscotibial components that firmly anchors the body of the medial meniscus. It contributes mainly to anteromedial rotatory restraint.
Posterior oblique ligament. A fan-shaped condensation posterior to the sMCL that blends with the semimembranosus. It is the principal restraint to valgus and rotation near full extension and the key structure in posteromedial corner (PMC) injury.
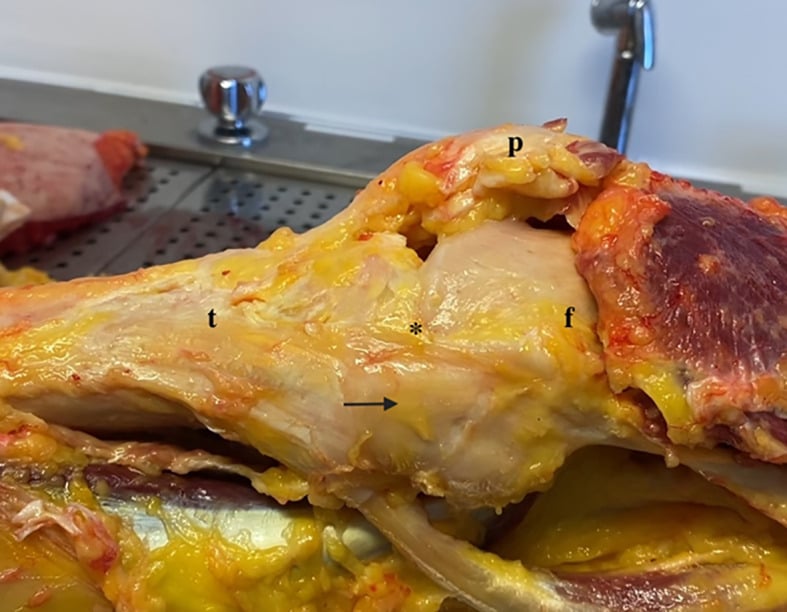
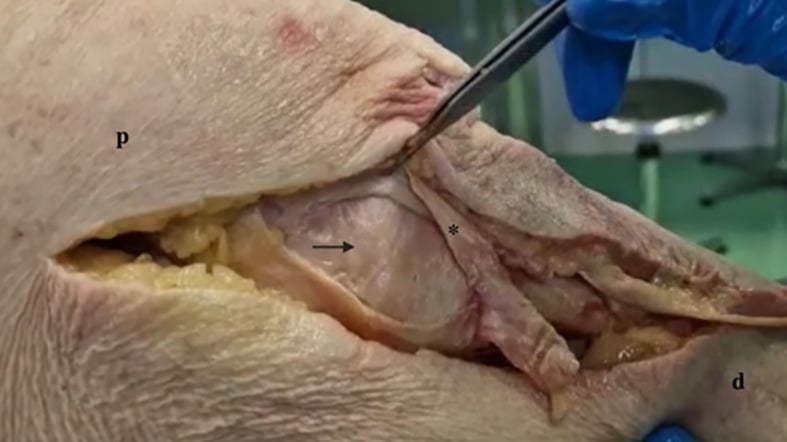
Biomechanics. In the classic Grood and Warren sectioning data the sMCL provides the large majority of valgus restraint at around 25 to 30 degrees of flexion. The proximal division of the sMCL and the POL also restrain external and internal tibial rotation. Their functional lengths change with knee position: the POL tightens in extension, while the sMCL provides its dominant valgus restraint in mid-flexion.
Why the test is done at 30 degrees. At about 30 degrees of flexion the cruciates and the posteromedial capsule are relatively relaxed, so valgus laxity there isolates the sMCL. At 0 degrees the POL, the posteromedial capsule and the cruciates are recruited, so valgus laxity in full extension signals a more extensive injury, involving the PMC and/or a cruciate, not an isolated MCL.
Warren's three layers. The medial side is dissected in three layers, and understanding them matters for surgical exposures:
- Layer 1: sartorius fascia and the investing fascia
- Layer 2: superficial MCL and posterior oblique ligament
- Layer 3: joint capsule, deep MCL and posteromedial capsule
The mnemonic SDP (Superficial, Deep to superficial, Proper capsule) orders them. The pes tendons, sartorius, gracilis and semitendinosus, are the superficial structures of the exposure: the sartorius fascia belongs to layer 1, and the pes lies superficial to the sMCL at its distal tibial attachment.
Classification Systems
Grading. Injuries are graded on valgus stress at 30 degrees, by the amount of opening and whether there is an endpoint. Compare with the other knee, because absolute values vary between individuals.
- Pathology
- Fibre stretch, intact
- Examination
- Tender, firm endpoint
- Laxity
- 0-5mm, no increase
- Pathology
- Partial tear
- Examination
- Lax with endpoint
- Laxity
- 5-10mm increased
- Pathology
- Complete rupture
- Examination
- Lax without endpoint
- Laxity
- Greater than 10mm increased
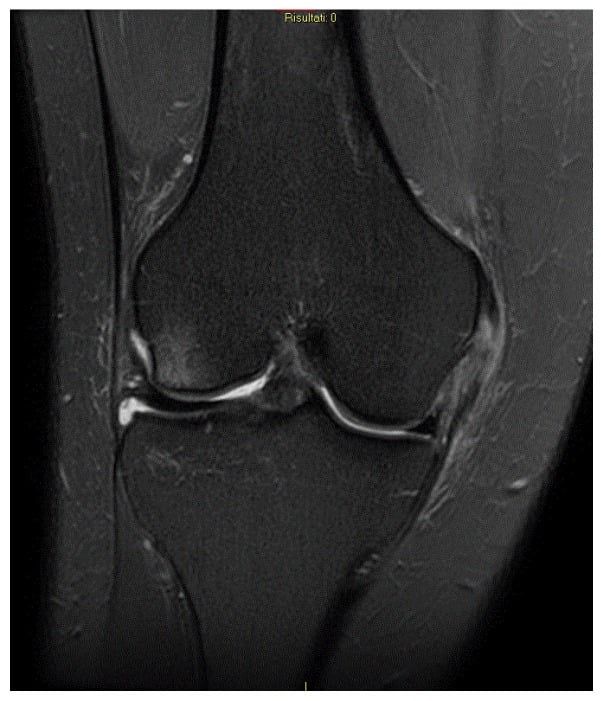
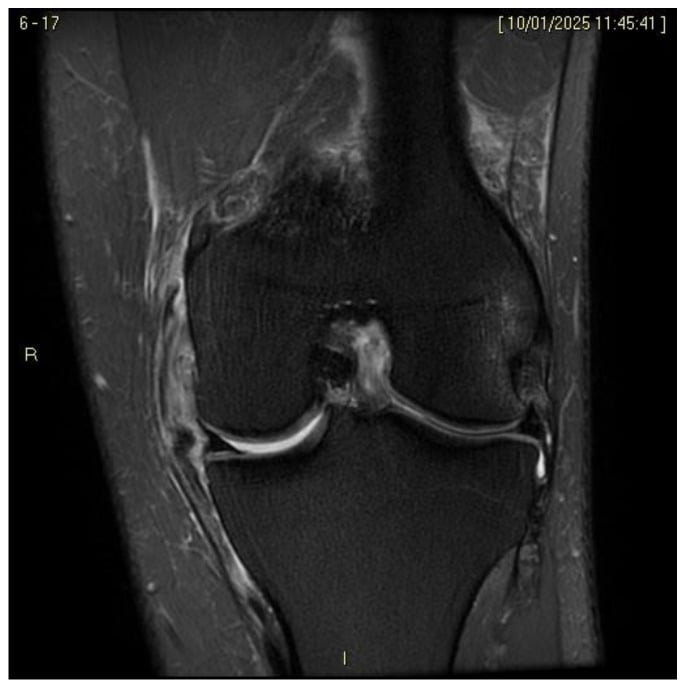
Location. The femoral origin is the most common site and may avulse bone; mid-substance tears are less common. A tear at the tibial insertion can become a Stener equivalent, the sMCL retracting to lie over the pes anserinus. Location affects healing and may influence the surgical approach.
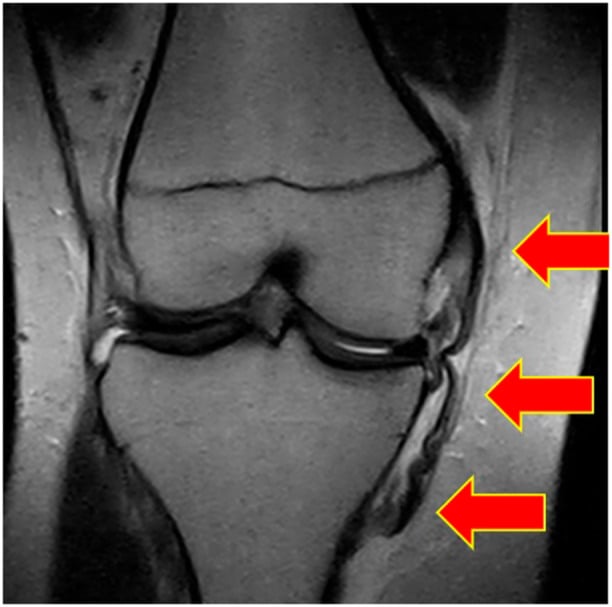
Associated injuries. Always assess for them.
- MCL plus ACL: very common. Address the ACL; the MCL usually heals.
- MCL plus PCL: less common and more severe.
- Multiligament injury: a dislocation pattern.
The unhappy triad. O'Donoghue's triad is classically described as ACL, MCL and medial meniscus, but in practice lateral meniscus tears co-occur with ACL injury more often than medial ones. It is a common exam trap.
Clinical Assessment
History. A valgus blow, usually in contact, with medial knee pain at the time of injury and swelling that is often localised to the medial side. Ask about giving way under valgus load, and about the symptoms of the injuries that travel with it: a pop suggests the ACL, locking suggests the meniscus.
Palpation. Tenderness along the course of the ligament places the injury at the femoral origin, the mid-substance or the tibial insertion.
Valgus stress testing. With the patient supine and the knee at 30 degrees of flexion, stabilise the thigh and apply a valgus force at the ankle, comparing the opening and the endpoint with the other side. Repeat at 0 degrees: laxity in full extension indicates posteromedial corner injury.
The rest of the knee. Always perform a Lachman and a pivot shift, because combined injuries are common, and examine the meniscus with McMurray's test and joint-line palpation.
- Key Distinguishing Feature
- Valgus laxity at 30 degrees, tenderness along MCL course
- Best Test
- Valgus stress at 30 degrees
- Key Distinguishing Feature
- Joint-line tenderness, mechanical locking, effusion
- Best Test
- McMurray, MRI
- Key Distinguishing Feature
- Valgus laxity at 0 degrees plus rotatory instability
- Best Test
- Valgus stress at 0 degrees, MRI
- Key Distinguishing Feature
- Inability to weight bear, bony tenderness
- Best Test
- Radiograph, CT
- Key Distinguishing Feature
- Tenderness over pes insertion, no laxity, often overuse
- Best Test
- Clinical, no valgus laxity
- Key Distinguishing Feature
- Burning medial pain, no laxity, sensory change
- Best Test
- Clinical, Tinel along adductor canal
- Key Distinguishing Feature
- MPFL tenderness, apprehension, haemarthrosis
- Best Test
- Apprehension test, MRI
Anteromedial Rotatory Instability and the Posteromedial Corner
The pattern. An isolated sMCL injury produces straight-plane valgus laxity. When the posteromedial corner (PMC), the posterior oblique ligament, the posteromedial capsule and the semimembranosus expansions, is torn alongside the sMCL, the result is anteromedial rotatory instability (AMRI): the medial tibial plateau rotates anteriorly as the joint opens medially.
How to detect it.
- Valgus laxity at 0 degrees: the POL and posteromedial capsule are the restraints in extension, so opening here, and not just at 30 degrees, signals PMC involvement rather than an isolated sMCL injury
- Anteromedial drawer (Slocum test): an anterior drawer performed with the tibia in roughly 15 degrees of external rotation; increased anteromedial translation indicates AMRI
- MRI confirms injury to the POL, the posteromedial capsule and the semimembranosus
Why it matters. Unlike the isolated sMCL, the PMC heals poorly and is a genuine surgical target. Combined sMCL and POL disruption, and any knee with valgus laxity in full extension, should be evaluated for PMC repair or reconstruction rather than assumed to heal in a brace, especially alongside an ACL reconstruction. Missed AMRI is a recognised cause of failed ACL reconstruction through residual rotatory laxity.
The Skeletally Immature Knee: Physeal Fracture Mimic
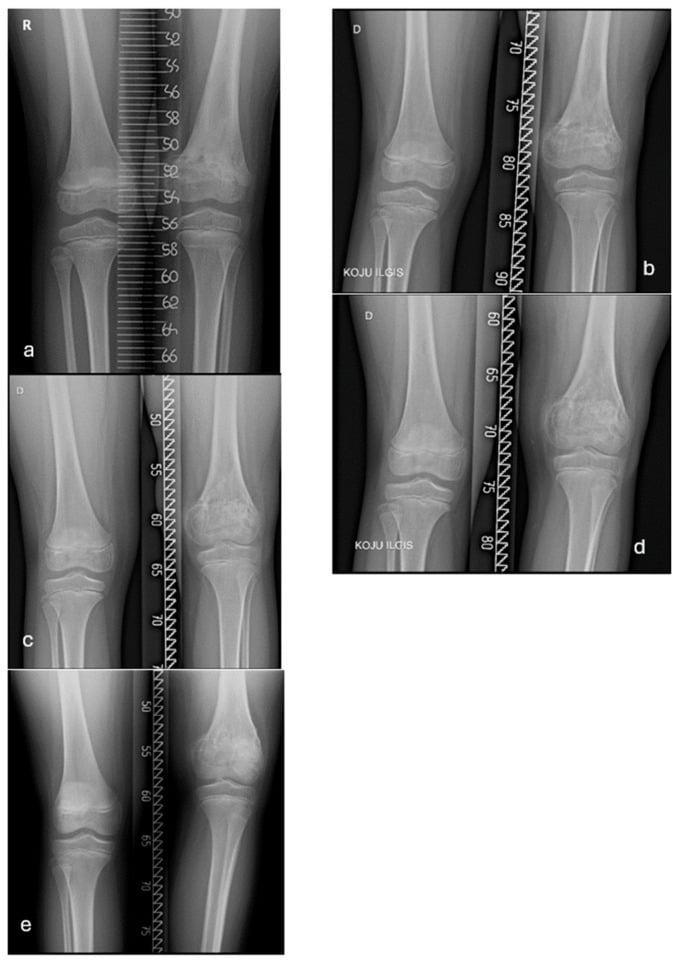
The physis fails first. In a child or adolescent with open physes, the valgus injury that would tear the MCL in an adult more often fails through the distal femoral physis, which is weaker than the collateral ligament. A Salter-Harris fracture of the distal femur can therefore masquerade as an MCL sprain, and apparent valgus laxity on stress testing may be opening through the growth plate rather than through the ligament.
What to do. In a skeletally immature patient with a valgus injury and medial tenderness or instability, scrutinise the physis and obtain plain radiographs; if the examination suggests instability, valgus stress radiographs distinguish physeal opening from true ligamentous laxity. True paediatric MCL injuries do occur and, as in adults, heal well, but the physeal fracture must be excluded first.
Why the label matters. A distal femoral physeal fracture is an anatomical-reduction problem with a real risk of growth arrest and angular deformity, since the distal femoral physis contributes the most growth of any lower-limb physis. Calling it a ligament sprain is a significant error.
Investigations
Radiographs. The standard first step to rule out bony injury; they are usually normal in a pure MCL injury. Look for an avulsion fragment and for the associated fractures of the tibial plateau and femur. In the chronic knee, look for the Pellegrini-Stieda lesion: calcification at the femoral origin of the MCL, representing a chronic injury in which the haematoma has calcified. It is visible on plain films and may be asymptomatic.
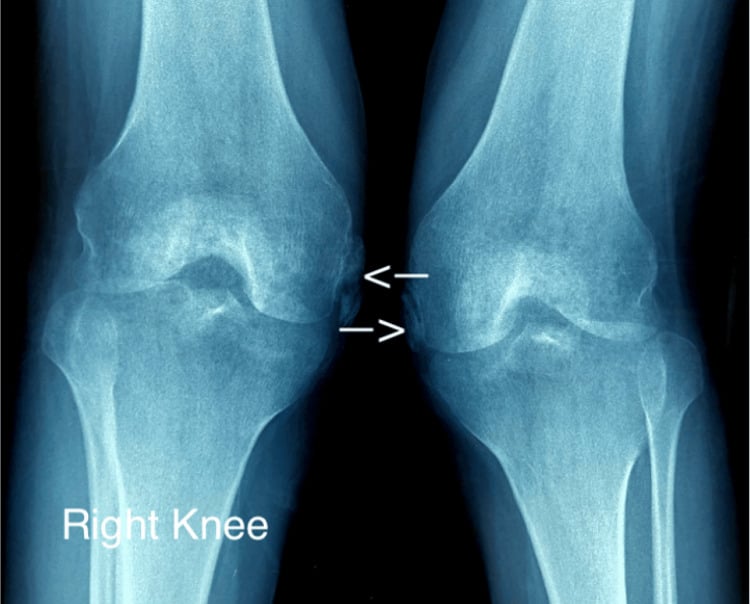
Stress radiographs can document valgus laxity, measured as the side-to-side difference in degrees or millimetres of opening. They are useful in chronic cases, for medicolegal purposes and in research, and are not commonly required in clinical practice.
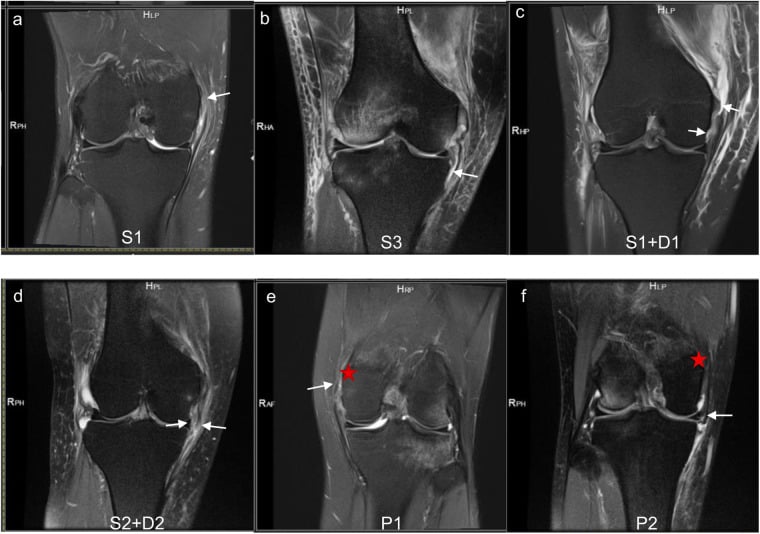
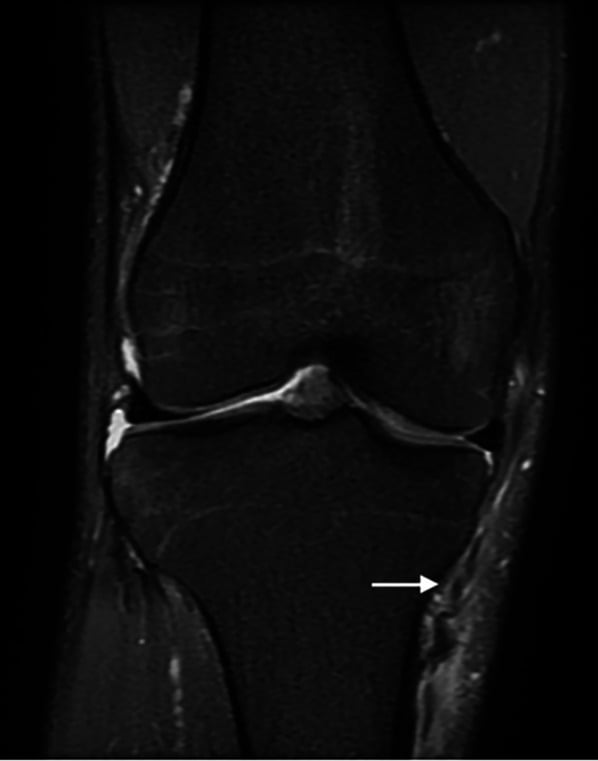
MRI. Sensitivity for MCL injury is excellent. It shows oedema surrounding the ligament, thickening or discontinuity, and the level of the tear (femoral, mid-substance or tibial), together with the associated injuries: ACL, meniscus, cartilage and bone bruise. It is not always required for an isolated MCL injury, but it helps define a Grade III tear and the injuries that accompany it.
Management
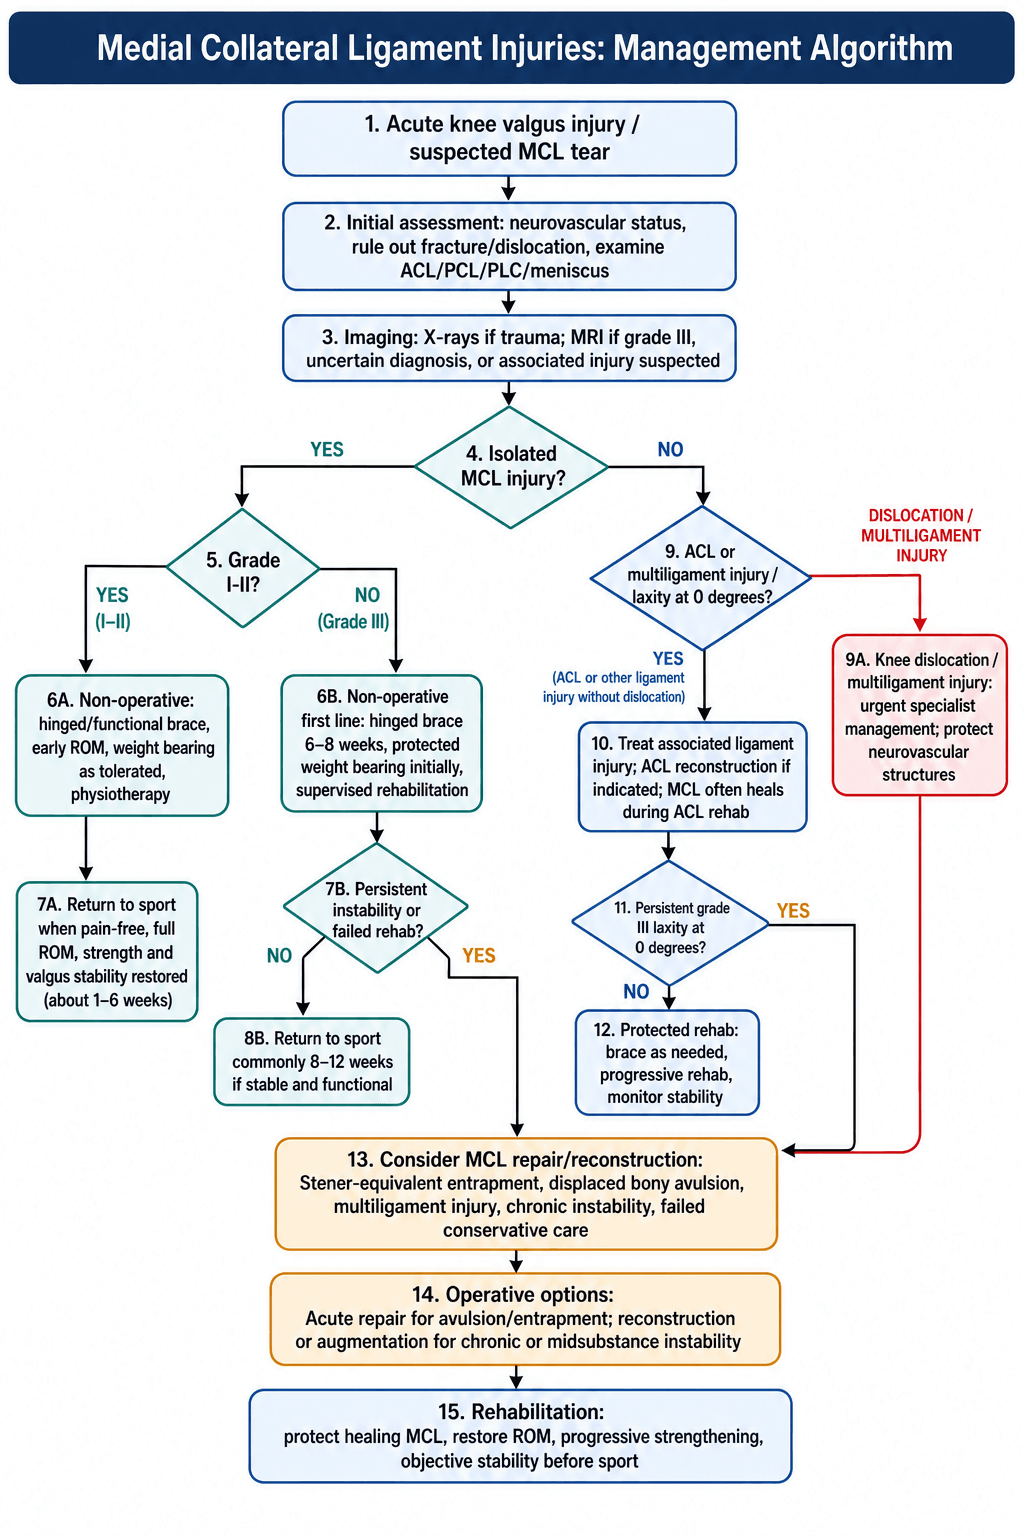
Acutely. RICE and a brace in extension while the knee is examined for associated injuries. Consider MRI if the tear is Grade III or an associated injury is suspected.
Isolated injury. Treatment is non-operative and graded, with weight bearing as tolerated and early physiotherapy for Grades I and II. Healing rates are excellent, and most Grade III tears heal.
- Grade I: functional brace, early range of motion, return to sport at 1-2 weeks
- Grade II: hinged brace for 4-6 weeks, progressive range of motion and strengthening, return to sport at 4-6 weeks
- Grade III: hinged brace for 6-8 weeks, protected weight bearing initially, supervised rehabilitation, return to sport at 8-12 weeks
Combined injury. Reconstruct the ACL if indicated; the MCL usually heals during the ACL recovery. The exception is a Grade III tear with valgus laxity at 0 degrees, which may need MCL surgery at the same time.
Surgery. Uncommon for isolated MCL injuries.
- Primary repair: Stener equivalent with the MCL trapped, bony avulsion with displacement, multiligament injury
- Reconstruction: chronic instability despite rehabilitation, failed conservative treatment, and combined with other ligament surgery if the knee is Grade III at 0 degrees
Surgical Technique
Repair. An acute femoral avulsion is reattached with suture anchors or bone tunnels to restore the origin; an acute tibial avulsion is fixed with a screw and soft-tissue washer; an acute mid-substance tear is repaired primarily with non-absorbable sutures. Augmentation with a graft may be added for severe injuries.
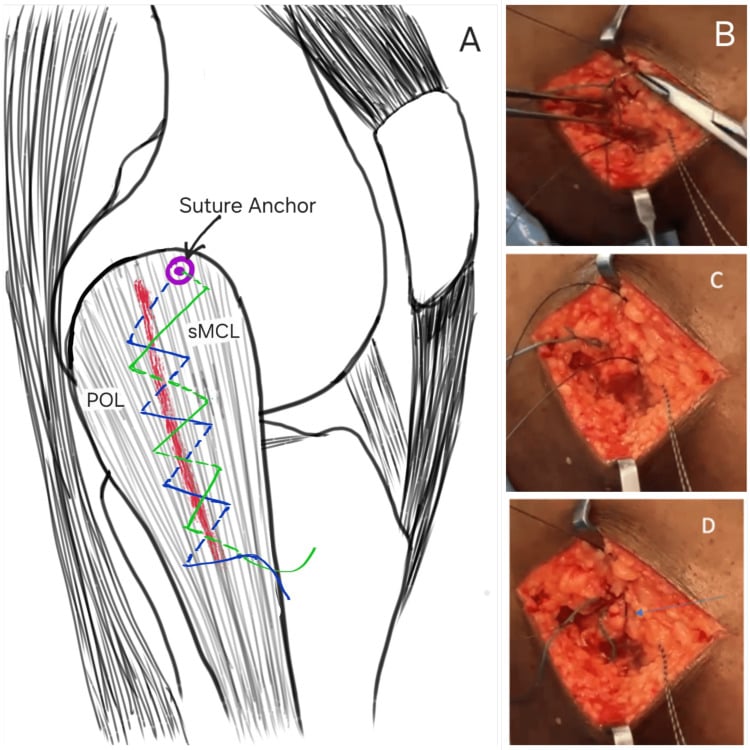
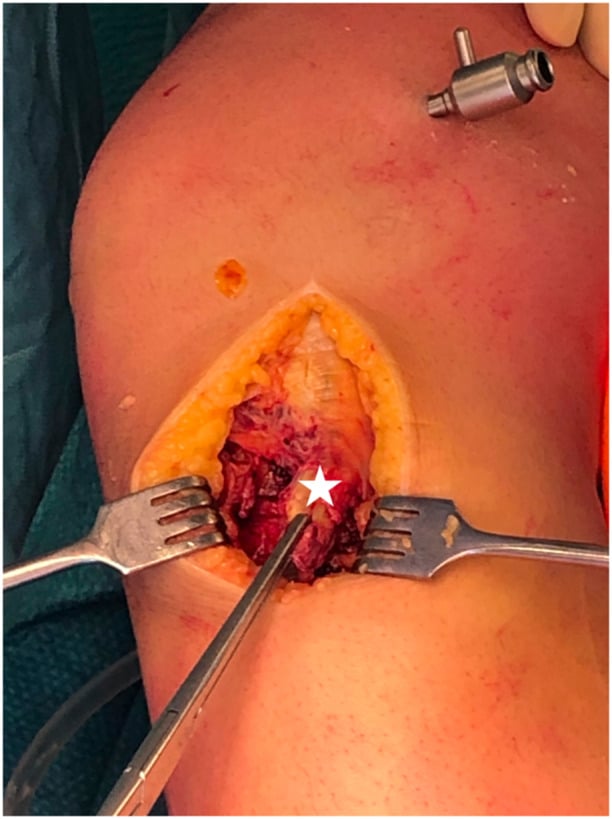
Reconstruction. The graft is a hamstring autograft (semitendinosus) or an allograft (Achilles or tibialis anterior), placed through isometric femoral and tibial tunnels and fixed with interference screws or suture buttons. An anatomic reconstruction restores valgus stability.
When repairing or reconstructing MCL, avoid overtensioning which leads to loss of flexion and lateral compartment overload. Tension at 20-30 degrees flexion with slight valgus.
Combined ACL and MCL surgery. Most Grade III MCL tears heal with ACL reconstruction alone, and the MCL is addressed surgically if the knee is valgus-lax at 0 degrees. The ACL is reconstructed first; the MCL is then repaired or augmented if needed and tensioned with the knee in slight flexion. Postoperative rehabilitation is modified to protect both.
Complications
- Cause
- Prolonged immobilisation
- Prevention
- Early ROM
- Management
- Physiotherapy, MUA if severe
- Cause
- Inadequate healing
- Prevention
- Appropriate bracing duration
- Management
- Late reconstruction
- Cause
- Haematoma
- Prevention
- Early ROM, avoid NSAIDs acutely
- Management
- Usually asymptomatic
- Cause
- Surgery
- Prevention
- Careful dissection
- Management
- Neuroma management
Stiffness is the enemy. Early range of motion is what prevents it, and even Grade III injuries do better in a hinged brace that allows motion than in a cast.
Postoperative Care
Rehabilitation Protocol
Hinged brace locked initially. Toe touch weight bearing. Quad sets, SLR.
Progressive ROM in brace. Increase weight bearing. Gentle strengthening.
Full ROM. Progressive resistance. Proprioception. Wean brace.
Sport-specific training. Functional testing. Full return when stable.
Conservative versus surgical rehabilitation. The conservatively treated knee progresses faster, with early motion encouraged; after reconstruction the knee is more protected initially but reaches a similar final timeline. Both pathways aim for full range of motion and strength before return to sport.
Outcomes and Prognosis
By grade. Grade I injuries have excellent outcomes with minimal long-term sequelae. Grade II injuries do well, and a brace during sport is helpful initially. Most isolated Grade III injuries heal with bracing; some chronic laxity may persist but is often asymptomatic.
Combined injuries. Outcomes depend on addressing all the pathology. ACL reconstruction with the MCL left to heal is the typical course.
Guidelines, Registries & Global Practice
- The MCL is the most commonly injured knee ligament worldwide
- Peak incidence in young, active populations and contact/collision and pivoting sports (football/soccer, rugby, American football, skiing, wrestling)
- Higher reported rates in males, largely reflecting sport-participation patterns
- Skiing classically produces combined valgus-external-rotation ACL/MCL injuries
- Most are low-grade (I to II) and managed entirely in primary or sports-medicine care
- No dedicated national MCL registry exists; isolated MCL injury rarely reaches an implant/arthroplasty registry
- Relevant registry signal is indirect: combined ACL/MCL is captured within national ACL reconstruction registries (Scandinavian, UK NLR, others)
- Those datasets reinforce ACL reconstruction with non-operative MCL care as the dominant combined-injury pathway
- Surgical MCL/POL work concentrates in multiligament and knee-dislocation cohorts
Side-by-Side Guidance (where emphasis differs)
- First-line
- Functional brace and early ROM for isolated injury
- Surgical emphasis
- Selective: chronic instability, distal avulsion, multiligament
- First-line
- Bracing and graded rehab; physiotherapy-led
- Surgical emphasis
- PMC and multiligament patterns to specialist units
- First-line
- Non-operative for isolated; ROM-preserving
- Surgical emphasis
- Repair/augment in dislocation and combined trauma
- First-line
- Conservative isolated MCL; reconstruct chronic laxity
- Surgical emphasis
- Anatomic sMCL/POL reconstruction for failed conservative
High- vs Limited-Resource Practice Variation
- Well-resourced settings: ready access to MRI and hinged functional bracing, supervised physiotherapy and graded return-to-sport testing; specialist reconstruction available for the minority who need it.
- Limited-resource settings: diagnosis relies more on careful clinical valgus stress testing (which is sufficient for most isolated injuries); improvised or non-hinged bracing and home-based rehab are used; MRI and reconstruction are reserved for combined/multiligament injury. Because isolated MCL injury heals well without surgery, clinical-examination-led conservative care travels well across resource settings.
MCL injuries are common viva topics. Know the conservative treatment algorithm, when NOT to operate, how to manage combined injuries, the LaPrade medial-knee anatomy and the grading system.
Controversies and Areas of Uncertainty
Timing of ACL reconstruction in the combined injury. Most surgeons allow the MCL to recover full extension and resolve acute valgus laxity before ACL reconstruction, typically a few weeks, citing the arthrofibrosis risk of very early combined surgery. The optimal window remains debated, and some advocate earlier reconstruction once motion is restored.
Repair versus reconstruction in the acute high-grade injury. For acute distal (tibial-sided, Stener-equivalent) sMCL avulsions and complete posteromedial corner disruption, primary repair has historically had higher failure rates than for lateral-side injuries. There is growing interest in repair with suture augmentation versus primary reconstruction, but high-level comparative data are lacking.
Is the isolated Grade III tear always conservative? Landmark series support non-operative care even for complete isolated tears, yet a subset develops chronic valgus or anteromedial rotatory instability. Identifying which complete tears will fail bracing, for example those that are distally based or involve the POL as well, is unresolved.
Stress radiography and its cut-offs. Side-to-side valgus opening on stress radiographs helps grade severity, but the published cut-offs distinguishing isolated sMCL from combined sMCL and POL injury vary between studies, limiting any single agreed threshold.
MCQ Practice Points
Q: What is the primary function of the sMCL? A: Primary static restraint to valgus stress - in classic sectioning studies the sMCL provides roughly three-quarters of valgus restraint at about 25 degrees of flexion, far more than at full extension.
Q: Why test MCL at 30 degrees flexion? A: Isolates the MCL. At 0 degrees, posteromedial capsule and cruciates also contribute. Laxity at 0 degrees indicates more severe injury.
Q: Why does MCL heal better than ACL? A: Extraarticular location and good blood supply. Not bathed in synovial fluid. Forms healing scar tissue.
Q: How should combined ACL/MCL injury be treated? A: ACL reconstruction, MCL heals conservatively. Exception is Grade III MCL with laxity at 0 degrees may need surgical MCL.
Q: What is Pellegrini-Stieda lesion? A: Calcification at MCL femoral origin from chronic injury with hematoma calcification. Visible on X-ray.
Q: What is the MCL Stener equivalent? A: sMCL displaces over pes anserinus preventing healing. Indication for surgical reduction.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 22-year-old rugby player sustains a valgus blow to his knee during a tackle. He has medial knee pain and swelling. Examination shows Grade II laxity at 30 degrees with a firm endpoint. Lachman is negative. How would you manage this?”
“A 28-year-old skier with a twisting fall presents with a swollen knee. Examination shows Grade III MCL laxity and positive Lachman with pivot shift. MRI confirms ACL rupture and Grade III MCL tear. What is your treatment plan?”
“A 35-year-old presents with ongoing medial knee instability 6 months after an MCL injury that was treated conservatively. He has failed prolonged rehabilitation. Valgus stress shows Grade II laxity at 30 degrees. What would you recommend?”
Grading (Valgus at 30 degrees)
- Grade I: Tender, firm endpoint, no laxity
- Grade II: Laxity with endpoint
- Grade III: Laxity without endpoint
- Compare to contralateral side
Examination Key Points
- Test at 30 degrees: Isolates MCL
- Test at 0 degrees: PMC if unstable here
- Always check ACL (Lachman, pivot)
- Palpate along MCL course
Treatment Algorithm
- Grade I-II: Conservative (90%+ heal)
- Grade III isolated: Usually conservative
- Combined ACL/MCL: ACL surgery, MCL heals
- Surgery: chronic instability, Stener, multilig
Anatomy Pearls
- sMCL: primary valgus restraint
- Femoral origin just proximal-posterior to medial epicondyle (LaPrade)
- dMCL: part of posteromedial capsule
- Warren layers: 3 layers medial knee
Return to Sport
- Grade I: 1-2 weeks
- Grade II: 4-6 weeks
- Grade III: 8-12 weeks
- Protective brace may help initially
Evidence Base and Key Studies
Non-Operative Treatment of Complete (Grade III) Isolated MCL Tears
- Comparative study of operative versus non-operative care of complete isolated MCL tears
- Non-operatively treated knees achieved results comparable to surgically repaired knees
- Functional treatment avoided the morbidity and stiffness of surgery and casting
- Helped establish non-operative care as standard for isolated complete MCL injury
Combined ACL/Grade III MCL: Operative vs Non-Operative MCL (RCT)
- Level 1 RCT: 47 patients with combined ACL + grade III MCL, all had early ACL reconstruction
- MCL treated operatively (n=23) versus non-operatively (n=24)
- No significant difference in stability, ROM, muscle power, Lysholm or IKDC at ~2 years
- AP stability excellent in both groups
Early Operative MCL Repair Slows Recovery (Companion RCT)
- Same RCT cohort analysed for ROM and quadriceps power
- Flexion deficit greater after combined ligament repair at 6, 12 and 36 weeks
- Quadriceps power deficit larger in the repair group at 52 weeks (30.7% vs 20.5%)
- Differences resolved by 104 weeks
Early Functional Rehabilitation of Isolated Grade III MCL in Athletes
- Prospective 5-year follow-up of 35 athletes with isolated grade III MCL sprains
- Treated with lateral hinged brace and early ROM, no immobilisation or surgery
- Mean HSS knee score 45.9 of 50 at mean 5.3 years
- Results comparable to surgery or immobilisation with faster return to sport