Systematic Assessment of Muscles, Tendons, Ligaments, and Soft Tissue Masses
Size: Greater than 5cm
Location: Deep to fascia
Growth: Rapid enlargement
Signal: Heterogeneous, necrosis
Margins: Irregular, infiltrative
Key: Any deep soft tissue mass greater than 5cm requires urgent specialist referral
- Normal tendons and ligaments are dark on all sequences (low signal)
- Increased tendon signal suggests degeneration or tear
- Muscle oedema: high T2/STIR, normal T1
- Fatty infiltration: high T1 signal within muscle
- Soft tissue masses: size greater than 5cm and deep location are red flags
- “Magic angle artefact: 55° orientation causes false tendon signal
- “Complete tear: discontinuity with retraction and haematoma
- “Partial tear: intratendinous signal without complete disruption
- “Goutallier classification for rotator cuff fatty infiltration
- “Lipoma: follows fat signal on all sequences
Overview
Know normal first. Soft tissue MRI interpretation rests on a single principle: knowing what normal looks like on each sequence, so that any deviation can be recognised as pathology. Muscle, tendon, ligament, nerve, fat and the fibrous capsular structures each have a characteristic, predictable signal that reflects their water and collagen content. MRI is the dominant modality for these structures because of its unmatched soft tissue contrast, multiplanar capability and absence of ionising radiation.
Three questions answer most soft tissue MRI problems:
- Is the lesion fluid, fat, fibrous tissue or something more complex, the four basic signal building blocks?
- Where does it sit relative to the deep fascia, and how large is it? Depth and size are the two strongest red flags for a sarcoma.
- Is an apparent abnormality real, or an artefact such as the magic angle phenomenon that mimics tendon degeneration on short-echo sequences?
The four building blocks. Almost every soft tissue lesion can be characterised by comparing it with four reference tissues:
- Fluid - low T1, very high T2/STIR (cysts, oedema, fresh haematoma)
- Fat - high T1, intermediate-high T2, suppresses on fat-saturated and STIR sequences (lipoma, fatty infiltration)
- Fibrous or collagenous tissue - low on all sequences (tendon, ligament, scar, fibroma)
- Cellular or solid tissue - intermediate T1, intermediate-high T2, and it enhances (most tumours, granulation tissue)
Anything that does not fit a single block, heterogeneous, partly necrotic or partly haemorrhagic, should raise concern.
What changes management. A small number of findings do: the gap and retraction that determine whether a tendon is reparable, the Goutallier grade that predicts rotator cuff repair failure, and the depth-and-size combination that mandates referral to a sarcoma unit before any biopsy.
Normal Soft Tissue Signal
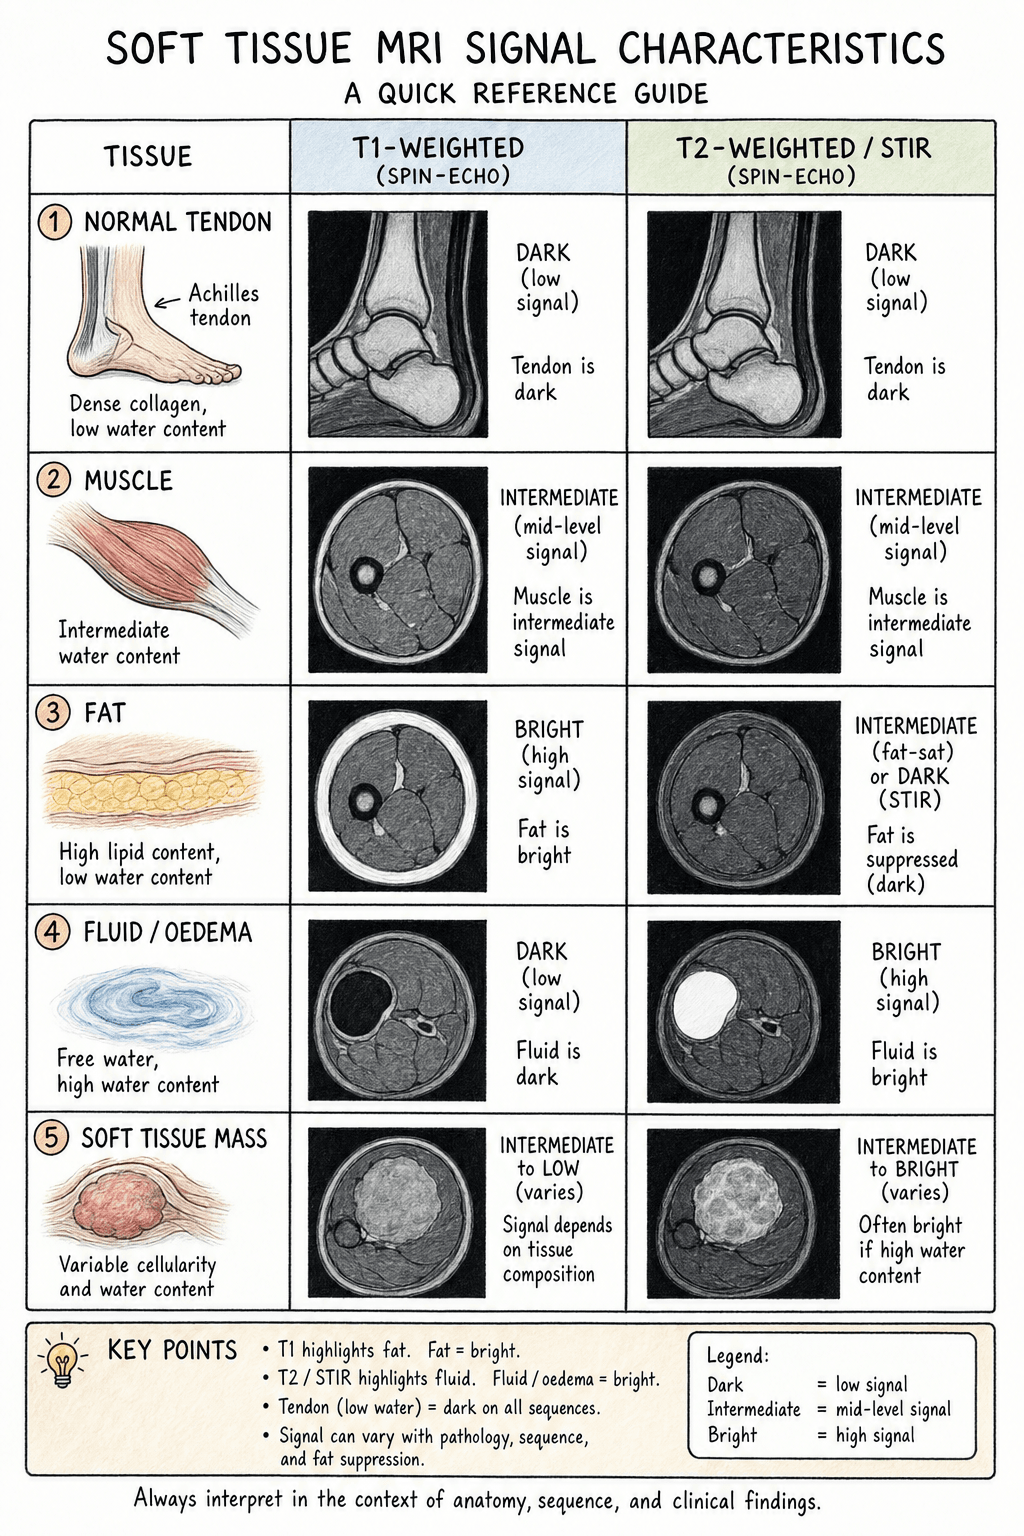
- T1 Signal
- Intermediate
- T2 Signal
- Intermediate to low
- Notes
- Pennate architecture visible
- T1 Signal
- Low (dark)
- T2 Signal
- Low (dark)
- Notes
- Organised collagen fibres
- T1 Signal
- Low (dark)
- T2 Signal
- Low (dark)
- Notes
- Similar to tendon
- T1 Signal
- High
- T2 Signal
- Intermediate to high
- Notes
- Suppresses on STIR/fat-sat
- T1 Signal
- Intermediate
- T2 Signal
- Intermediate to slightly high
- Notes
- Fascicular pattern visible
- T1 Signal
- Signal void
- T2 Signal
- Signal void
- Notes
- Flow-related signal loss
- T1 Signal
- Intermediate
- T2 Signal
- Intermediate
- Notes
- Articular surface assessment
Why tendons are dark. Tendons contain highly organised collagen fibres with few mobile protons and very short T2 relaxation times, so they give low signal on every pulse sequence. Any increased signal within a tendon is abnormal and suggests degeneration, a tear, or the magic angle artefact.
Tendon Pathology
Tendinopathy. Four findings, each with its own meaning:
- MRI Finding
- Enlarged cross-sectional area
- Significance
- Chronic overload response
- MRI Finding
- Increased T1/T2 signal (not fluid bright)
- Significance
- Mucoid degeneration, disorganised collagen
- MRI Finding
- Fluid around tendon
- Significance
- Tenosynovitis or paratendinitis
- MRI Finding
- Signal void within tendon
- Significance
- Calcific tendinopathy
Tears. The classification turns on which surface is breached and whether the tendon is still in continuity:
- MRI Features
- Surface disruption on articular side
- Management Implication
- May progress to full thickness
- MRI Features
- Surface disruption on bursal side
- Management Implication
- Less common than articular
- MRI Features
- Signal within substance, surfaces intact
- Management Implication
- Intratendinous delamination
- MRI Features
- Complete discontinuity, fluid signal gap
- Management Implication
- Surgical consideration
- MRI Features
- Tendon stump retracted, gap present
- Management Implication
- Larger repair required
Reading the full-thickness tear. The fibres are completely discontinuous and fluid signal, bright on T2, fills the gap; the stump may retract. Chronic tears carry atrophy and fatty infiltration of the muscle. Measure the gap for surgical planning.
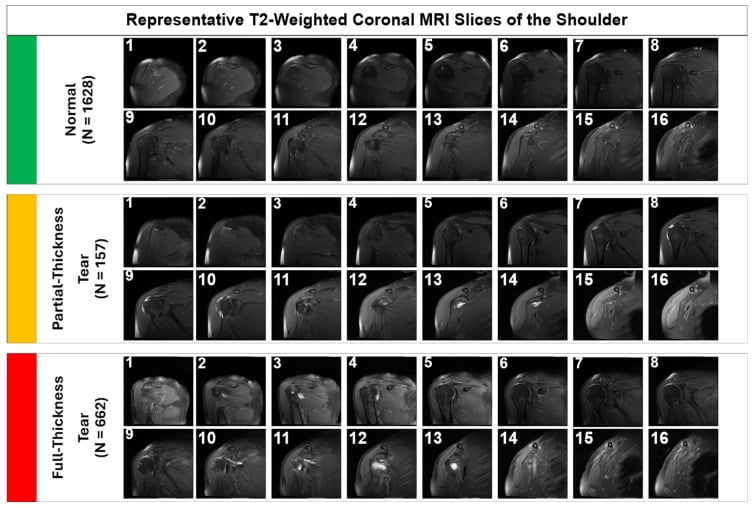
Magic angle artefact. A tendon oriented at 55° to the main magnetic field B0 shows artifactually increased signal on short-TE sequences, T1 and PD, that is not present on true T2-weighted images. The artefact is intermediate at about 45 and 65 degrees and disappears at 0 and 90; the common sites are the rotator cuff and the ankle tendons. If increased tendon signal is seen only on T1 or PD and not on T2, suspect magic angle artefact.
Why "check it on T2" works, and the number behind it. Magic angle signal decays exponentially as echo time lengthens. Once TE exceeds roughly 37ms the signal falls back to what the same tendon shows when it lies parallel to B0: the artefact is abolished while anatomical detail is preserved. That critical TE was independent of the coil used and of field strength, which is what makes the rule portable between scanners rather than a local quirk. So the instruction is not merely to look at another sequence: any adequately T2-weighted sequence is long enough to settle the question, and if increased signal persists on it, the lesion is real.
Muscle Pathology
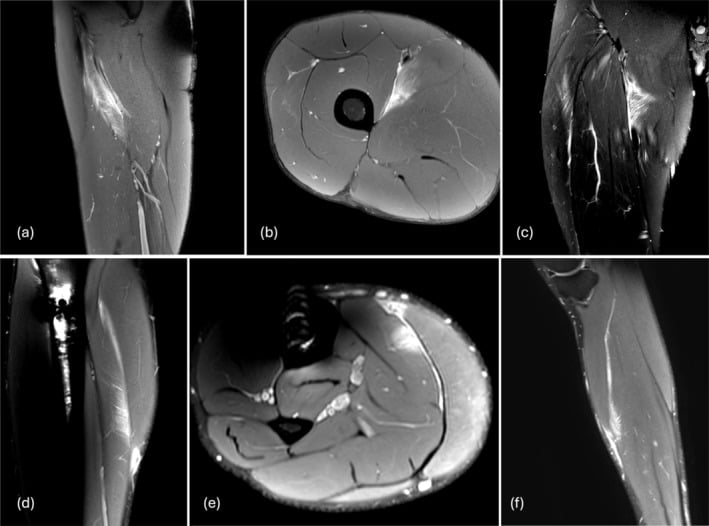
The traditional three grades. Strain, partial tear and complete tear, read from oedema, fibre disruption and haematoma:
- MRI Features
- Feathery oedema, no disruption
- Clinical Correlation
- Mild pain, minimal function loss
- MRI Features
- Partial fibre disruption, haematoma
- Clinical Correlation
- Moderate pain, weakness
- MRI Features
- Complete disruption, retraction, large haematoma
- Clinical Correlation
- Severe, may need surgery
What replaced it. The three-grade scheme is the old system. The British Athletics Muscle Injury Classification (BAMIC) was designed specifically to improve on it, because "grade 2 partial tear" bundles together injuries with very different recovery times. BAMIC grades 0-4 on MRI and then appends a letter for where in the muscle-tendon unit the injury sits, and the letter is the part that carries the prognostic weight.
- Meaning
- Normal MRI despite symptoms
- Why it matters
- Focal neuromuscular pain without structural injury
- Meaning
- Small injury, limited oedema
- Why it matters
- Short recovery
- Meaning
- Moderate injury
- Why it matters
- Intermediate recovery
- Meaning
- Extensive injury
- Why it matters
- Prolonged recovery
- Meaning
- Complete tear
- Why it matters
- Longest recovery; surgical discussion for selected tendon avulsions
- Meaning
- Peripheral, at the muscle margin or fascia
- Why it matters
- Generally the most favourable site within any grade
- Meaning
- At the muscle-tendon junction
- Why it matters
- Intermediate
- Meaning
- Extends into the tendon itself
- Why it matters
- The adverse one — worse and more variable prognosis, and higher re-injury risk, within the SAME numerical grade
Why the letter matters. A report that says "grade 2 hamstring tear" is less useful than "grade 2c": the number and the letter answer different questions, and two athletes with identical grades can have very different timelines if one injury is myofascial and the other intratendinous. The classification has been shown to be reproducible in practice: two radiologists classifying 65 hamstring injuries in 45 elite athletes achieved interrater agreement of kappa 0.80 to 0.88 (85-91% agreement), so it is reliable enough to base decisions on.
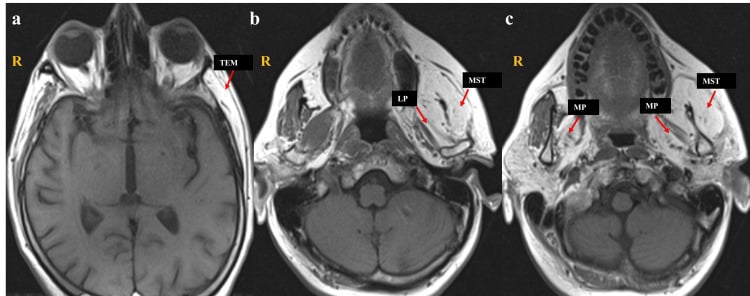
Soft Tissue Masses
Describing a mass. Measure it in three planes and describe it against the seven features below. Heterogeneous signal from haemorrhage or necrosis, irregular or infiltrative margins, infiltrative growth, surrounding oedema and rapid growth on serial imaging all count against it.
- Benign Indicators
- Less than 5cm
- Malignant Indicators
- Greater than 5cm
- Benign Indicators
- Superficial to fascia
- Malignant Indicators
- Deep to fascia
- Benign Indicators
- Well-defined, smooth
- Malignant Indicators
- Irregular, infiltrative
- Benign Indicators
- Homogeneous
- Malignant Indicators
- Heterogeneous
- Benign Indicators
- Uniform
- Malignant Indicators
- Necrosis, haemorrhage
- Benign Indicators
- None or uniform
- Malignant Indicators
- Peripheral, irregular
- Benign Indicators
- Stable
- Malignant Indicators
- Rapid enlargement
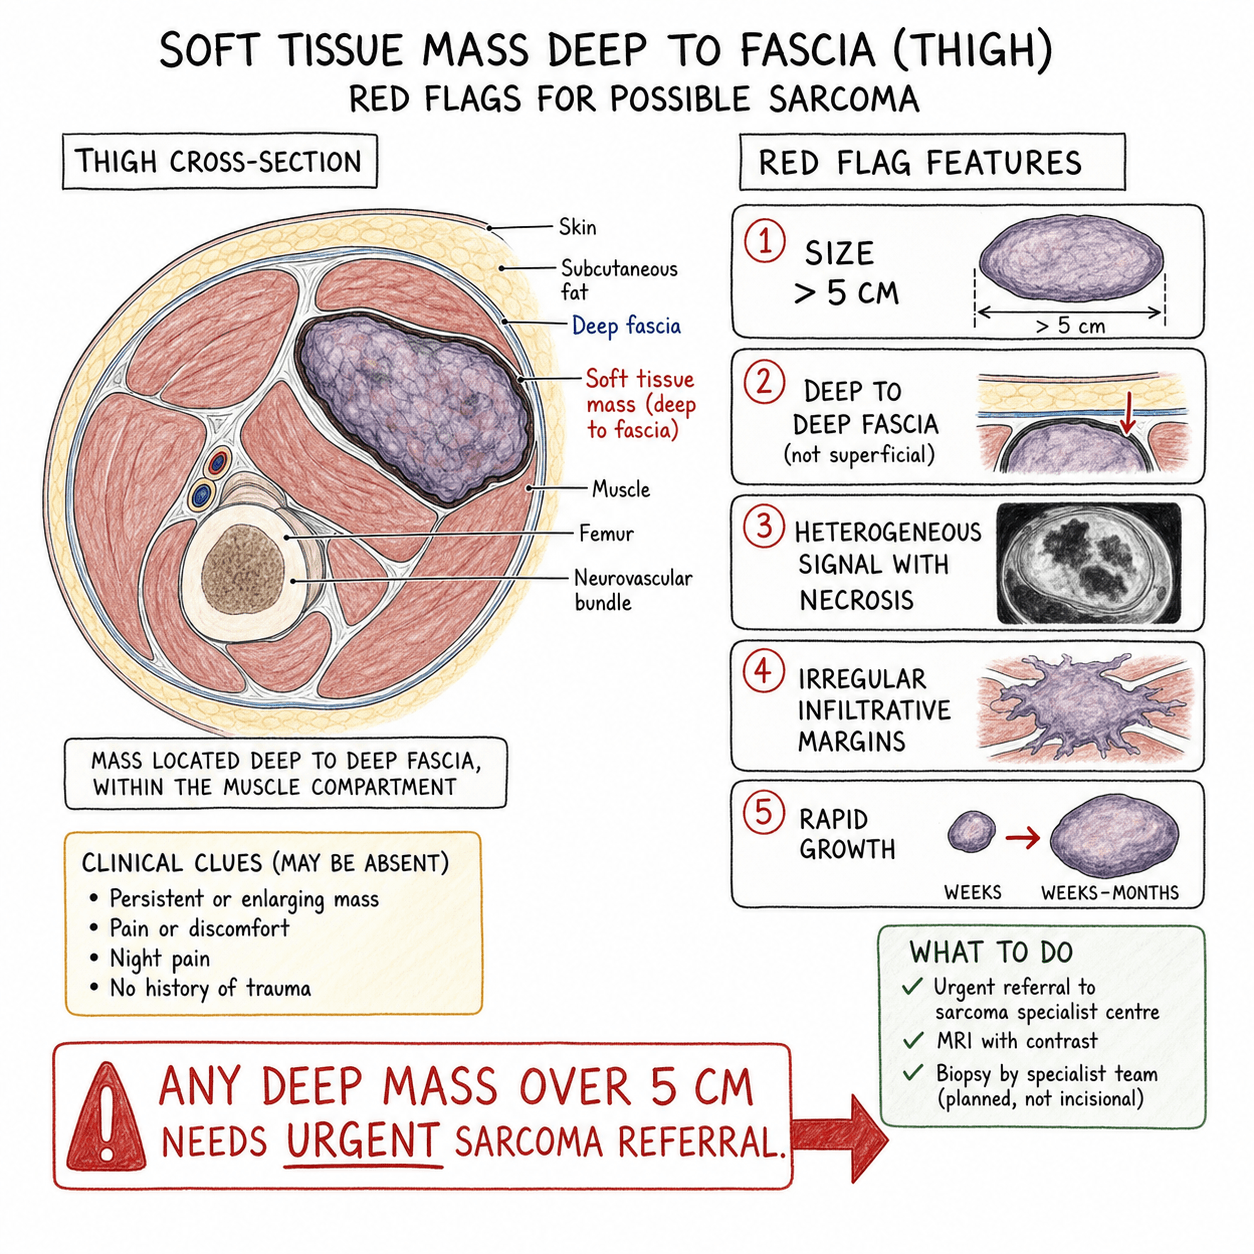
Referral before biopsy. Any deep mass greater than 5cm, or any heterogeneous or enhancing lesion, should be referred to a sarcoma unit before biopsy or excision. Local staging is MRI of the entire compartment, with CT chest for pulmonary metastases. The biopsy is planned in consultation with the tumour surgeon so that the track can be excised at definitive surgery.
Common benign masses. The signal signature and the key feature of each:
- T1 Signal
- High (fat)
- T2 Signal
- High (fat)
- Key Feature
- Follows fat on all sequences, thin septae OK
- T1 Signal
- Low
- T2 Signal
- Very high (fluid)
- Key Feature
- Well-defined, connects to joint
- T1 Signal
- Intermediate
- T2 Signal
- Very high
- Key Feature
- Serpiginous vessels, may have phleboliths
- T1 Signal
- Low to intermediate
- T2 Signal
- High
- Key Feature
- Target sign, fusiform, along nerve
- T1 Signal
- Low
- T2 Signal
- Very high
- Key Feature
- Intramuscular, well-defined, fluid-like signal
Lipoma versus well-differentiated liposarcoma. Both follow fat signal. The features that concern for liposarcoma are size greater than 10cm, thick septae (greater than 2mm), nodular non-fat components and deep location. If any is present, biopsy or excision is recommended.
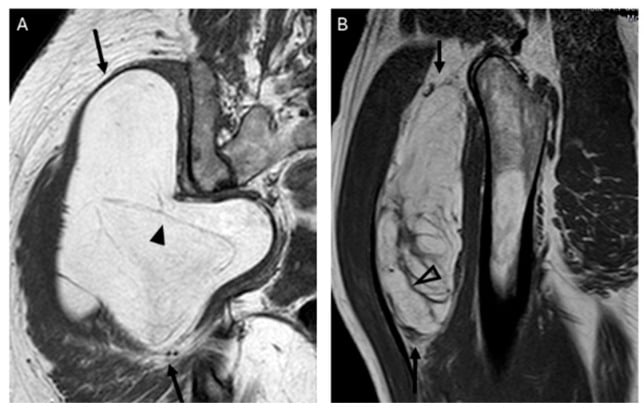
Myxoid tumours. Myxoid matrix is characteristically very bright on fluid-sensitive sequences and can appear deceptively cyst-like.
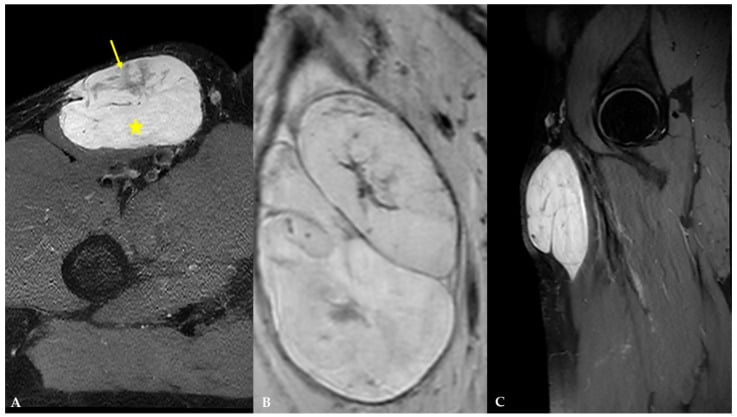
The haematoma that mimics a tumour. A subacute haematoma can be intrinsically bright on T1 (methaemoglobin) and may have an enhancing wall, so knowing how blood signal evolves over time is essential before calling such a lesion a tumour. The signal changes predictably with the oxidation state of haemoglobin:
- Haemoglobin form
- Oxyhaemoglobin (intracellular)
- T1 signal
- Iso/low
- T2 signal
- High
- Haemoglobin form
- Deoxyhaemoglobin (intracellular)
- T1 signal
- Iso/low
- T2 signal
- Low
- Haemoglobin form
- Methaemoglobin (intracellular)
- T1 signal
- High
- T2 signal
- Low
- Haemoglobin form
- Methaemoglobin (extracellular)
- T1 signal
- High
- T2 signal
- High
- Haemoglobin form
- Haemosiderin (rim)
- T1 signal
- Low rim
- T2 signal
- Low rim (blooms on gradient echo)
The discriminators between a resolving haematoma and a haemorrhagic tumour are: a haematoma should evolve and shrink on serial MRI, has no nodular internal enhancement (only a thin rim), and usually a fitting history of trauma/anticoagulation. Any solid enhancing nodule, lack of evolution, or growth means treat it as a tumour and refer - some sarcomas present with intratumoural haemorrhage that masquerades as a simple haematoma.
Fat, Blood, Protein, Melanin, ContrastWhat Is Bright on T1?
Hook:Most soft tissue pathology is LOW on T1; intrinsic high T1 signal narrows the differential sharply — fat suppression confirms fat, while a haematoma evolves over serial scans.
Functional Sequences: Diffusion-Weighted and Dynamic Contrast MRI
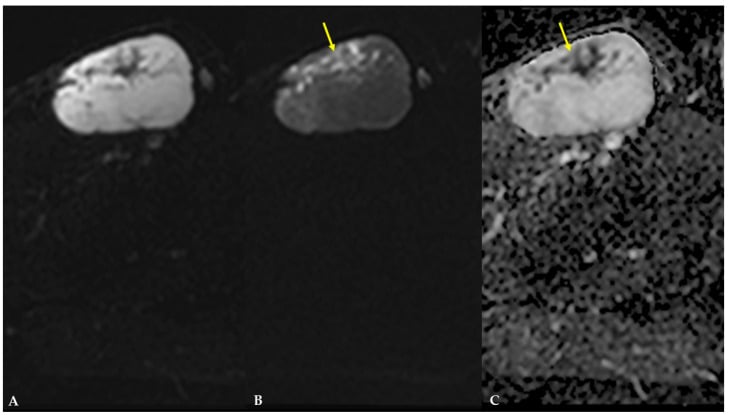
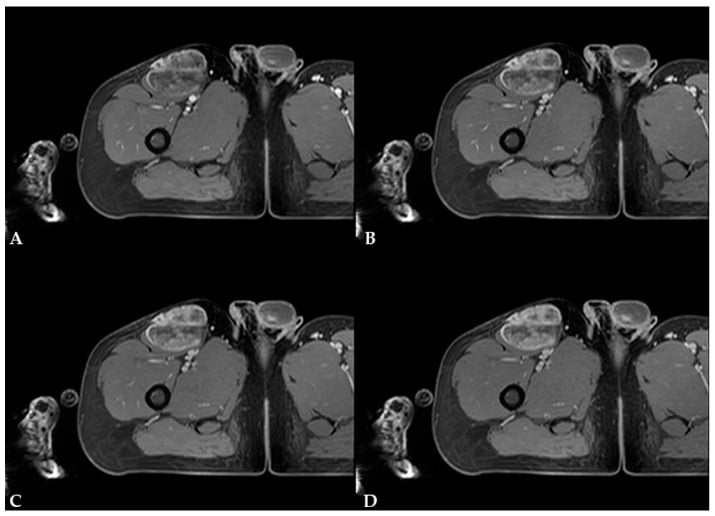
Two techniques beyond the conventional sequences increasingly support soft-tissue mass characterisation, biopsy targeting and treatment-response assessment.
- What it measures
- Restriction of water (Brownian) motion - a surrogate for cellularity
- Typical pattern and caveat
- Highly cellular tumours tend to restrict (low ADC), but overlap is large: myxoid tumours have HIGH ADC and can shine through, while some benign lesions (cellular schwannoma, fibromatosis) restrict. Best for response assessment (ADC rises with necrosis) and detecting recurrence.
- What it measures
- Rate and pattern of gadolinium uptake over time (the time-intensity curve)
- Typical pattern and caveat
- Malignant lesions tend to enhance early and rapidly (steep wash-in, washout-type curve); benign lesions enhance more slowly. Most useful to TARGET biopsy to the most enhancing (viable) region and to separate viable tumour from necrosis or post-treatment change.
Adjuncts, not arbiters. Neither technique reliably separates benign from malignant on its own because of major overlap, so they supplement, and do not replace, conventional multiplanar MRI and sarcoma-MDT review. Their highest-value uses are directing the biopsy to viable tissue and monitoring treatment response, where a rising ADC and falling enhancement suggest necrosis or response.
Specific Structures
Five things to report on a cuff tear. Type, size, retraction, atrophy and fatty infiltration:
- Assessment
- Partial vs full thickness
- Reporting
- Articular, bursal, or interstitial
- Assessment
- AP dimension on coronal
- Reporting
- Small less than 1cm, medium 1-3cm, large 3-5cm, massive greater than 5cm
- Assessment
- Distance from footprint
- Reporting
- Affects repair tension
- Assessment
- Tangent sign (supraspinatus)
- Reporting
- Muscle below scapular spine line
- Assessment
- Goutallier grade
- Reporting
- Affects repair outcome
Peripheral Nerve Sheath Tumours and MR Neurography
A mass on a nerve declares itself. A mass arising from a peripheral nerve has a characteristic constellation of signs, and recognising it both makes the diagnosis and warns against an ill-judged biopsy through a functioning nerve. The combination of an entering/exiting nerve, split-fat sign, target sign and fascicular sign identifies a benign nerve sheath tumour.
- What it is
- A nerve runs into and out of the fusiform lesion
- Meaning
- The lesion is neurogenic and follows a nerve course
- What it is
- A thin rim of fat surrounding the lesion
- Meaning
- It sits within the fat-containing neurovascular bundle (intermuscular)
- What it is
- Central low T2 (fibrocollagenous) with peripheral high T2 (myxoid)
- Meaning
- Classic of a benign nerve sheath tumour, especially neurofibroma
- What it is
- Multiple small ring-like fascicles within the lesion
- Meaning
- Reflects the internal nerve-fascicle architecture
- What it is
- Tapered ends continuous with the nerve
- Meaning
- Confirms the lesion lies along the nerve
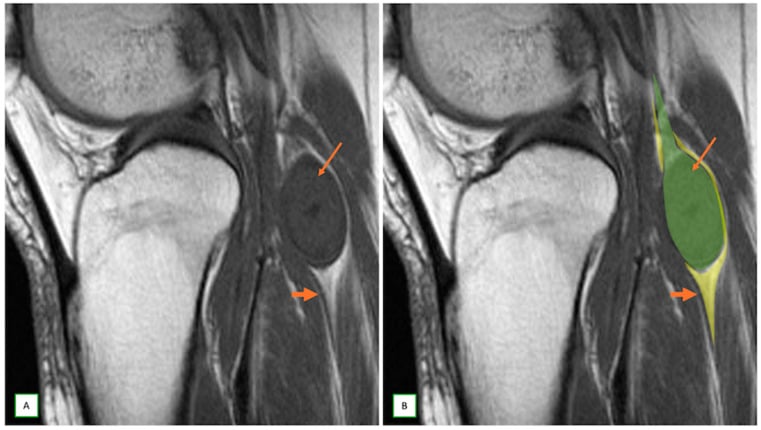
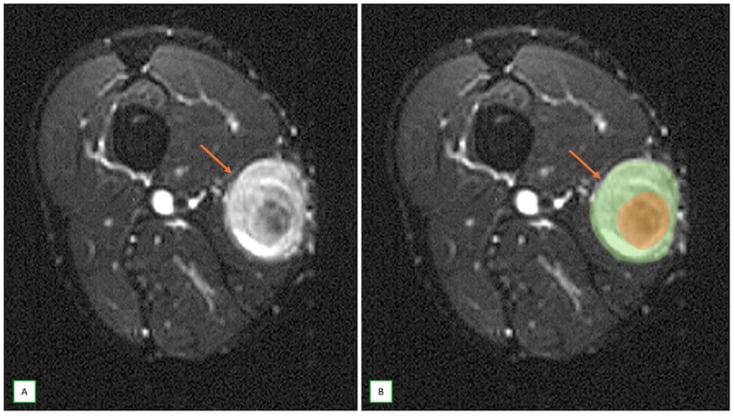
Schwannoma, neurofibroma and the malignant one. A schwannoma typically sits eccentric to the nerve, so it can sometimes be shelled out, whereas a neurofibroma is fusiform with the nerve passing through it and is harder to separate. The major concern is the malignant peripheral nerve sheath tumour (MPNST): suspect it when a nerve lesion is large (over about 5 cm), rapidly enlarging, heterogeneous with necrosis, ill-defined, or has peritumoral oedema, especially in a patient with neurofibromatosis type 1. Loss of the target sign with rapid growth, large size and heterogeneity in an NF1 patient should raise the alarm for malignant transformation and prompt sarcoma referral rather than local excision. Imaging cannot always separate an atypical neurofibroma from an MPNST, so FDG-PET and image-guided biopsy planned with the sarcoma team are used.
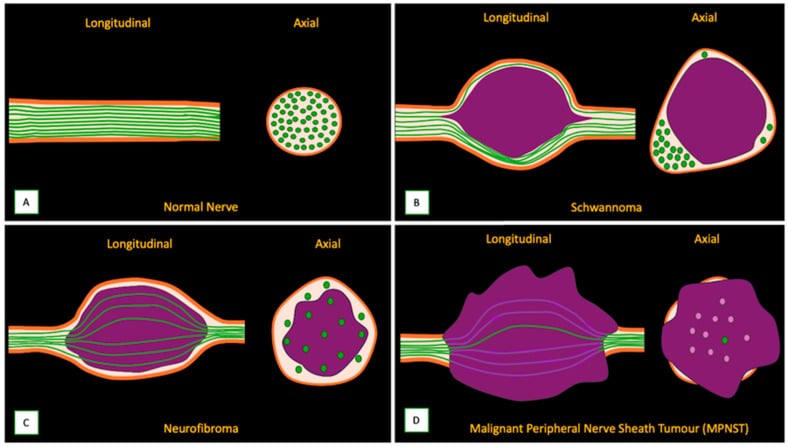
Systematic Approach to the Soft Tissue MRI
A fixed search pattern. A reproducible search pattern prevents the two classic errors: satisfaction of search, stopping after the obvious finding, and over-calling artefact as disease. The seven steps below work for any soft tissue study and are the order in which to present a film.
- Action
- Confirm region, side, sequences and planes
- Key question
- Do I have fluid-sensitive AND anatomical sequences?
- Action
- Identify muscle, tendon, ligament, fat, nerve, vessel
- Key question
- Is each structure the expected signal and calibre?
- Action
- Trace each from origin to insertion
- Key question
- Continuity, thickness, intrasubstance signal?
- Action
- Assess bulk, oedema (T2) and fat (T1)
- Key question
- Oedema, fatty infiltration, or both?
- Action
- Characterise any focal lesion
- Key question
- Fluid, fat, fibrous or solid? Depth and size?
- Action
- Re-examine suspicious signal
- Key question
- Magic angle, partial volume, failed fat-sat?
- Action
- State the finding that changes management
- Key question
- Reparable tear? Red-flag mass? Benign and dischargeable?
Differential Diagnosis by MRI Pattern
Start from the pattern, not the suspicion. Soft tissue lesions are best approached by their dominant MRI signal pattern rather than by clinical suspicion alone. The table groups the common differentials by the pattern that first catches the eye, with the discriminating feature that separates them.
- Differentials
- Lipoma; atypical lipomatous tumour / well-differentiated liposarcoma
- Discriminating feature
- Thick septae (over 2mm), nodular non-fat areas, size over 10cm, deep location favour ALT/WD-liposarcoma
- Differentials
- Ganglion/cyst; myxoma; myxoid sarcoma
- Discriminating feature
- True cyst is non-enhancing and joint-related; myxoid tumours show internal/septal enhancement
- Differentials
- Strain; denervation oedema; myositis; early infection
- Discriminating feature
- Distribution: focal at musculotendinous junction (strain) vs whole nerve territory (denervation) vs symmetric proximal (myositis)
- Differentials
- Chronic fatty infiltration; intramuscular lipoma; subacute haematoma (methaemoglobin)
- Discriminating feature
- Fatty infiltration follows muscle architecture; haematoma is focal with a fluid level and evolves over time
- Differentials
- Tendon/ligament; fibroma; PVNS/GCT-TS (haemosiderin); calcification
- Discriminating feature
- Blooming on gradient echo suggests haemosiderin (PVNS); CT confirms calcification
- Differentials
- Haemangioma / vascular malformation
- Discriminating feature
- Flow voids, fat overgrowth and rounded phleboliths are characteristic and reassuring
The most dangerous trap is calling a deep, large or heterogeneous mass "benign" on signal alone. Even a lesion that follows fat can be a well-differentiated liposarcoma, and some sarcomas (myxoid, synovial) mimic a cyst. When the pattern and the red flags disagree, the red flags win — refer before biopsy.
Guidelines, Registries & Global Practice
Soft tissue MRI interpretation is broadly consistent worldwide because it rests on physics-based signal characteristics, but referral pathways, access and protocol emphasis vary by health system and resource setting.
- Region
- UK
- Key recommendation
- Refer any unexplained lump deep to fascia, fixed, or larger than ~5cm urgently; MRI first-line; biopsy only within a sarcoma service
- Region
- Europe
- Key recommendation
- MRI for local staging of the whole compartment + chest CT for staging; planned biopsy by the sarcoma MDT before any excision
- Region
- US
- Key recommendation
- Image suspicious masses with MRI before any intervention; refer to an orthopaedic oncologist; avoid unplanned excision
- Region
- US
- Key recommendation
- MRI with and without contrast is the preferred study for a soft tissue mass of indeterminate nature
- Region
- Global
- Key recommendation
- MRI grading (e.g. BAMIC) to support return-to-play decisions in muscle injury, integrated with clinical assessment
Controversies & Areas of Uncertainty
The 5cm and depth thresholds. Size over 5cm and depth to fascia are the classic sarcoma red flags, but they are sensitive rather than specific: most deep lesions over 5cm are still benign (a lipoma, a haematoma). They define who needs specialist review, not who has cancer. Khan et al. found that even established imaging red flags performed modestly for lipomatous tumours, which reinforces MDT review over any single sign.
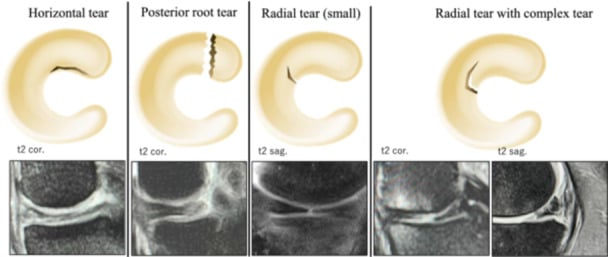
Meniscal grade 2 versus grade 3. The distinction between intrasubstance signal and signal reaching the articular surface underpins MRI meniscal reporting, but interobserver agreement at the surface is imperfect, and signal can persist for years after repair without re-tear. MR arthrography is more reliable in the post-operative knee.
Does MRI grade predict return to play? Higher BAMIC grade broadly predicts longer recovery, but considerable overlap exists, and intratendinous ('c') injuries within a grade carry a worse, more variable prognosis. MRI informs but does not replace serial clinical assessment when timing an athlete's return.
Clinical Imaging
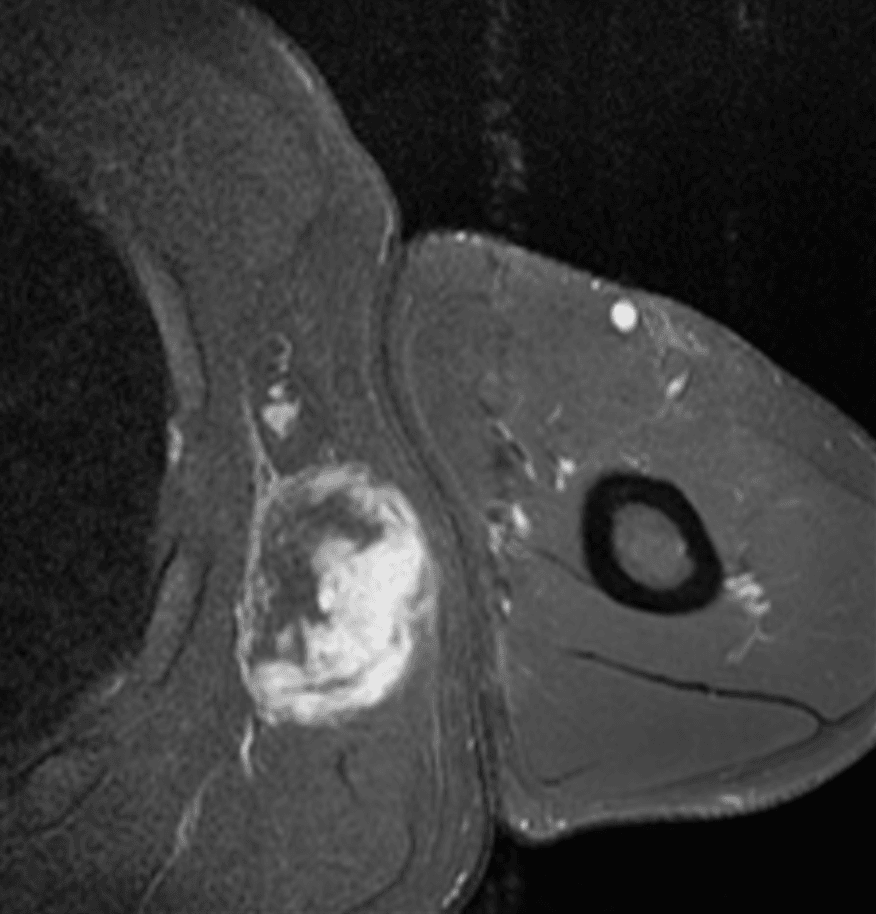
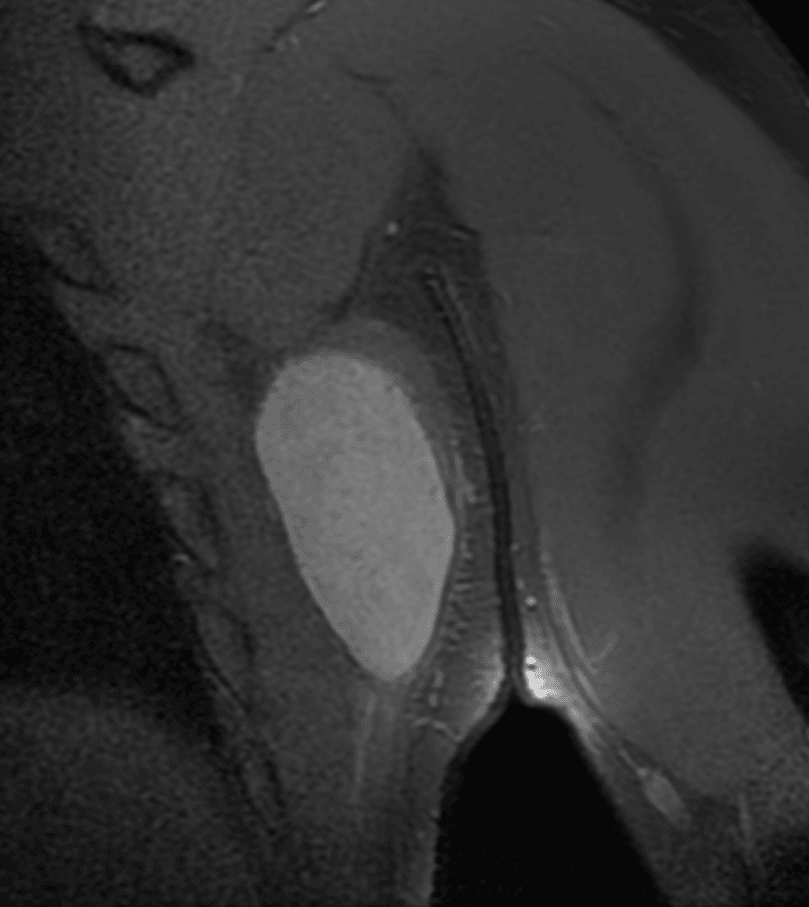
Match the protocol to the question. MRI is the workhorse for soft tissue assessment, but the protocol must be matched to the clinical question. A combination of fluid-sensitive and anatomical sequences in orthogonal planes is essential: for a mass, the second plane confirms the deep (subfascial) location, defines the craniocaudal extent and the relationship to the neurovascular bundle, and is part of every soft-tissue-mass protocol before biopsy.
- What it shows
- Anatomy, fat (bright), marrow
- Best for
- Fatty infiltration, fat in a mass, marrow assessment
- What it shows
- Fluid and oedema (bright), suppresses fat
- Best for
- Tendon tears, muscle oedema, cyst vs solid
- What it shows
- Robust fat suppression, oedema-sensitive
- Best for
- Marrow/muscle oedema, large field of view, off-isocentre
- What it shows
- Enhancing (vascular/solid) tissue
- Best for
- Solid vs cystic mass, abscess wall, tumour viability
- What it shows
- Susceptibility, cartilage
- Best for
- Calcification/haemosiderin (but prone to magic angle)
Setting up the study. Image the whole compartment, and for a mass include both the lesion and the adjacent joint. Use a small field of view and a surface coil for tendons. Check the fat suppression for uniformity, because failed fat-sat can mimic or hide oedema. For a suspected soft tissue mass a non-fat-saturated T1 sequence is mandatory to detect intralesional fat, and post-contrast imaging distinguishes a solid enhancing tumour from a non-enhancing cyst or a necrotic centre.
Prove it before you report it. A finding seen on only one plane or one sequence should always be scrutinised before it is called pathology. A "lesion" seen on one slice only may be partial volume averaging or a normal structure, a vessel or a normal muscle slip.
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“A 55-year-old presents with chronic shoulder pain. MRI shows a full-thickness supraspinatus tear with the tendon stump retracted to the level of the glenoid. T1 sagittal shows high signal within the supraspinatus fossa.”
“A 45-year-old presents with a painless thigh mass that has slowly enlarged over 6 months. MRI shows a 12cm well-defined intramuscular mass that follows fat signal on all sequences but has thick internal septae measuring 3-4mm.”
“A 28-year-old runner presents with progressive calf pain. MRI shows diffuse high T2/STIR signal throughout the gastrocnemius and soleus muscles with no discrete mass. T1 signal is normal.”
Normal Signal
- Tendon/ligament: Dark on all sequences
- Muscle: Intermediate T1 and T2
- Fat: High T1, intermediate T2
- Nerve: Intermediate, fascicular pattern
Tendon Pathology
- Increased signal = degeneration or tear
- Magic angle at 55° (false signal on short TE)
- Full tear: discontinuity + fluid gap
- Measure gap and retraction for surgery
Muscle Assessment
- Oedema: High T2, normal T1
- Fatty infiltration: High T1 (Goutallier 0-4)
- Goutallier 3-4: Poor surgical outcome
- Denervation: Follows nerve territory
Soft Tissue Mass Red Flags
- Size greater than 5cm
- Deep to fascia
- Heterogeneous signal
- Rapid growth
- Irregular margins
Evidence Base
The interpretive frameworks used in soft tissue MRI are underpinned by classification and validation studies. The following are the landmark and supporting references.
Goutallier et al. Fatty muscle degeneration in cuff ruptures
- Original five-stage (0-4) classification of rotator cuff muscle fatty degeneration on CT, derived from 63 patients undergoing cuff repair (57 re-evaluated at mean 17.7 months). Infraspinatus degeneration correlated with impaired active external rotation and had a strongly negative influence on the outcome of supraspinatus repairs; supraspinatus re-tear occurred in 25%. The authors concluded wide tears should be repaired before irreversible muscular damage occurs.
Fuchs et al. Fatty degeneration: CT versus MRI
- Prospective comparison in 41 surgical shoulders. Interobserver reproducibility of fatty-degeneration grading was good-to-excellent for both CT and MRI, but the correlation between MRI and CT was only fair-to-moderate and remained unsatisfactory even when simplified to a 3-grade scale. The degree of fatty degeneration correlated significantly with muscle atrophy.
Pollock et al. British Athletics Muscle Injury Classification
- Proposed an evidence-informed muscle injury grading system (BAMIC). Injuries are graded 0-4 on MRI features, with grades 1-4 carrying a suffix 'a' (myofascial), 'b' (musculotendinous) or 'c' (intratendinous) to capture the site of injury, which had been shown to influence prognosis. Designed to improve diagnostic accuracy and prognostication over the traditional three-grade system.
Patel et al. BAMIC reliability study
- Two radiologists classified 65 hamstring injuries in 45 elite athletes at two timepoints. Interrater agreement was substantial-to-almost perfect (kappa 0.80 then 0.88; 85-91% agreement) and intrarater agreement substantial (mean kappa 0.71). The system was judged straightforward and reproducible.