Benign Fibrous Metaphyseal Lesion | Fibrous Cortical Defect | Paediatric Incidental Finding
- NOF is a very common benign developmental fibrous lesion in children and adolescents
- Classic X-ray: eccentric, cortically based, well-defined metaphyseal lucency with a scalloped sclerotic rim
- Most are incidental, asymptomatic, and ossify or disappear with skeletal maturity
- Fracture risk increases when the lesion occupies greater than 50 percent of the bone diameter or is longer than 33 mm
- Differentiate from fibrous dysplasia: central intramedullary lesion with ground-glass matrix
- “Do not biopsy a classic incidental NOF in the right age group
- “Large distal tibial lesions are the fracture-risk scenario examiners like
- “Pain at the lesion, cortical thinning, or a limp should trigger fracture-risk imaging review
- “Multiple NOFs plus cafe-au-lait macules should prompt syndromic assessment
Overview and Epidemiology
Non-ossifying fibroma is one of the commonest benign bone lesions in the growing skeleton: a developmental fibrous defect of the metaphyseal cortex whose radiographic pattern is usually diagnostic on its own.
The clinical skill is not making an exotic diagnosis. It is recognising the classic benign pattern, avoiding unnecessary biopsy, identifying the small subgroup at fracture risk, and knowing when multiple lesions imply a syndromic diagnosis.
Who. A child or adolescent with open physes, usually with no symptoms at all. The lesion is found on radiographs taken for something else: trauma, a limp, alignment assessment, or knee pain unrelated to it.
Where. The metaphyses of the long bones, often around the knee: distal femur, proximal tibia, distal tibia, proximal humerus, and other long-bone metaphyses.
Natural history. The lesion is active during growth and then ossifies as skeletal maturity approaches. It appears to migrate away from the physis, but it does not move: it stays at its original metaphyseal site while longitudinal growth carries the physis away from it, a benign natural-history clue rather than aggressive spread. It becomes sclerotic and usually disappears or leaves a healed cortical scar.
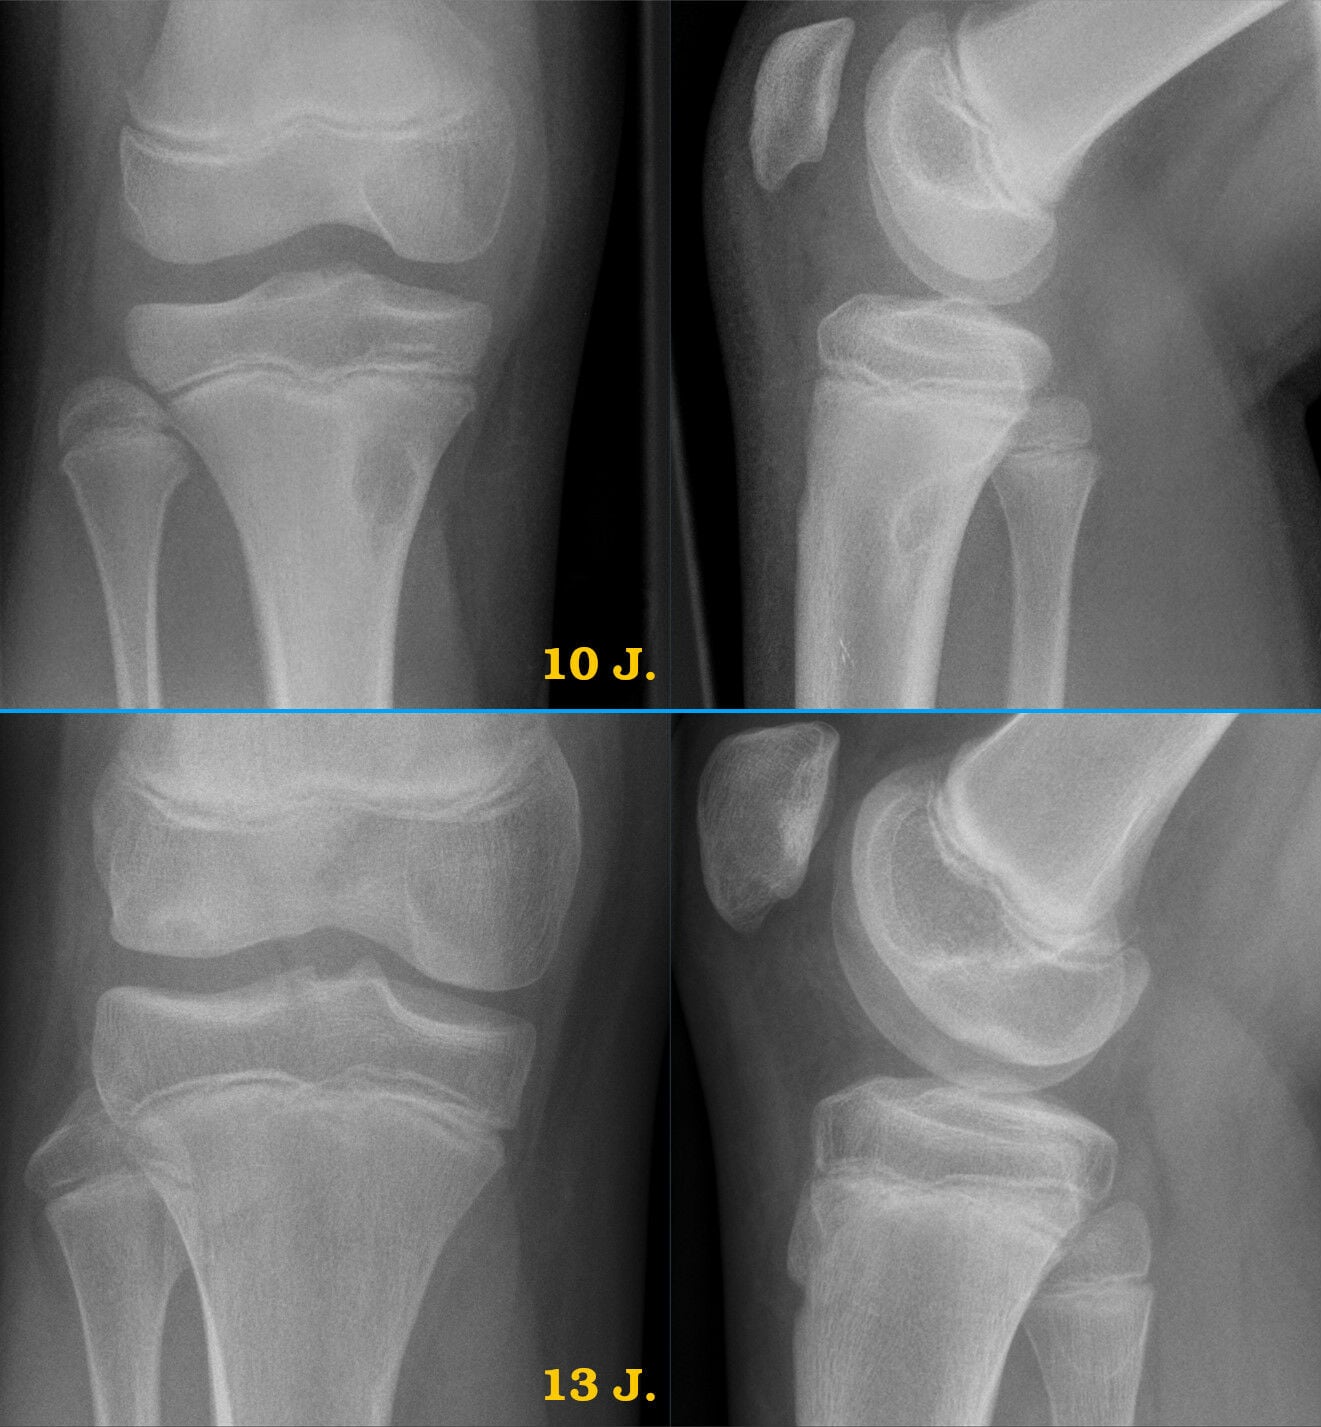
Why it matters. Most lesions require explanation rather than intervention, and an unnecessary biopsy can create anxiety and morbidity. Two things change that: a large lesion in a weight-bearing bone can weaken the cortex, and multiple lesions may be associated with a Jaffe-Campanacci phenotype or neurofibromatosis type 1 features.
Pathophysiology
A developmental defect, not an aggressive tumour. NOF is best understood clinically as a benign developmental fibrous defect of metaphyseal cortex. Histology shows fibroblastic spindle cells in a whorled or storiform stroma, collagen, foamy histiocytes, haemosiderin-laden histiocytes and osteoclast-like giant cells, but biopsy is rarely required because the radiographic pattern is usually diagnostic.
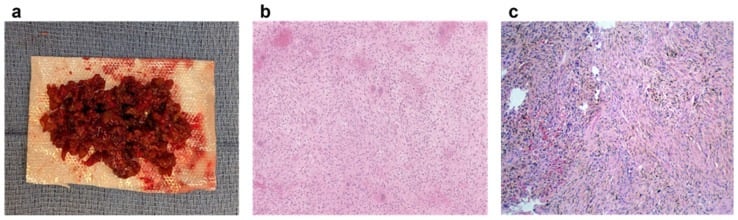
The molecular driver. "Developmental defect" describes the lesion without explaining it. NOFs are driven by activating variants in the RAS-MAPK pathway, with mosaic KRAS variants identified as the principal molecular cause.
Mosaic means the mutation is post-zygotic: it arises in one cell during development, so only that cell's descendants carry it.
Why one clone explains the whole clinical pattern. A late, small mutant clone produces one solitary lesion, which is the ordinary incidental NOF. An earlier or more widely distributed clone seeds several skeletal sites at once, which is the multifocal or polyostotic presentation, and it explains why multiple lesions cluster with extraskeletal findings rather than appearing as isolated bone disease. Because the mutation is mosaic rather than germline, these lesions are typically not inherited, which is a reasonable thing to be able to tell a parent.
The overlap with NF1. NF1 protein is a RAS GTPase-activating protein, so losing it and activating KRAS both drive the same downstream pathway. The two conditions are not coincidentally similar; they converge on one signalling axis.
Why the lesion looks scalloped. Slow growth lets the surrounding bone form a thin sclerotic margin, and the lobulated fibrous tissue produces a scalloped or multiloculated contour rather than a permeative aggressive pattern.
Why it heals with maturity. With physeal closure and remodelling, the fibrous focus progressively ossifies. The lesion may become densely sclerotic, shrink, or become invisible on later radiographs.
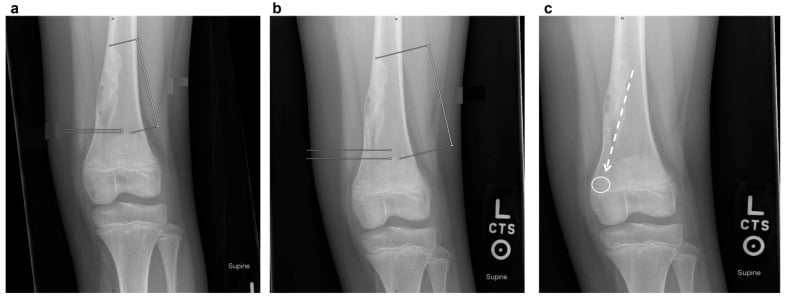
The mechanical spectrum. The same biology produces three clinical situations:
- Fibrous cortical defect: a small focus of fibrous tissue in the cortex, usually less than 2 cm, incidental, mechanically insignificant and self-resolving
- Non-ossifying fibroma: a larger eccentric fibrous metaphyseal lesion that can thin and expand the cortex, so size and cortical support are assessed in weight-bearing bones
- Pathological fracture: loss of cortical cross-sectional strength presenting as pain, limp, deformity or acute fracture, with risk rising with large diameter and length
Classification and Types
By radiographic maturation. Staging is useful because the active lucent stage is the period when fracture risk is most relevant.
- Radiographic Features
- Eccentric lytic metaphyseal defect with thin rim
- Fracture Relevance
- Risk depends on size and cortex
- Management
- Observe if small and asymptomatic
- Radiographic Features
- Increasing peripheral and internal sclerosis
- Fracture Relevance
- Mechanical risk falling as bone fills in
- Management
- Reassure and reduce follow-up if stable
- Radiographic Features
- Dense cortical or metaphyseal sclerosis
- Fracture Relevance
- Low risk
- Management
- No treatment
Ritschl radiographic staging is the named NOF-specific scheme that formalises this natural history into four stages:
- Stage A: a small, round or oval cortical lucency lying close to the physis (the fibrous cortical defect end of the spectrum)
- Stage B: a larger, polycyclic or multilocular well-marginated lesion that may extend into the medulla as the bone grows
- Stage C: sclerosis begins, typically from the diaphyseal margin, as the lesion migrates away from the physis and starts to heal
- Stage D: complete sclerosis and ossification, the healed and often invisible residual lesion
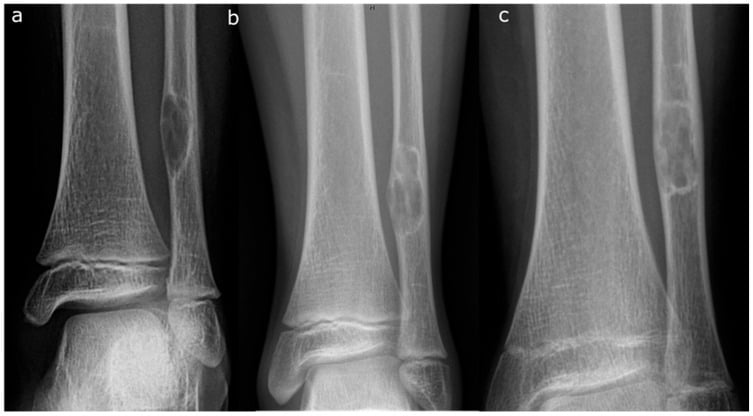
Fibrous cortical defect versus non-ossifying fibroma. Both belong to the same benign developmental spectrum. The NOF is larger and extends from cortex into the medullary cavity, whereas the fibrous cortical defect is smaller and confined to cortex; the terminology should describe morphology without provoking unnecessary biopsy.
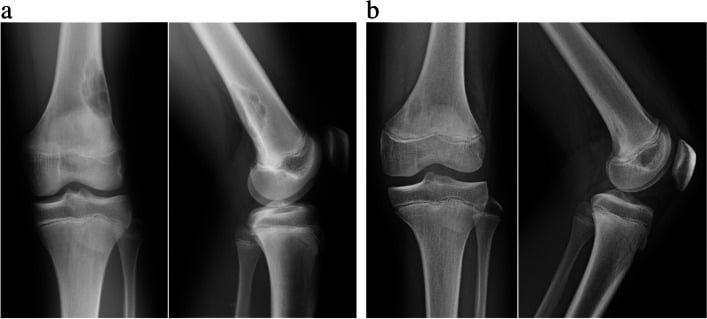
By clinical context. Four settings, each with its own key issue and treatment note.
- Setting
- Child or adolescent imaged for unrelated reason
- Key Issue
- Avoid over-investigation
- Treatment Notes
- Reassure; follow only if large or atypical
- Setting
- Distal tibia, distal femur, or proximal tibia
- Key Issue
- Pathological fracture risk
- Treatment Notes
- Serial radiographs and selective prophylactic surgery
- Setting
- Acute pain after low-energy injury
- Key Issue
- Paediatric fracture management plus lesion assessment
- Treatment Notes
- Cast or fix fracture; curette later if persistent high-risk lesion
- Setting
- Several lesions, cafe-au-lait macules, jaw lesions, endocrine or developmental features
- Key Issue
- Syndromic assessment
- Treatment Notes
- Evaluate for Jaffe-Campanacci / NF1 spectrum
Multiple lesions are not simply "more incidental lesions"; examine the child for syndromic features.
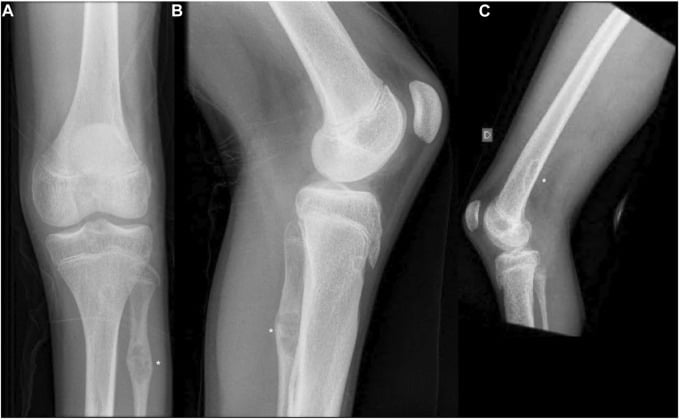
Jaffe-Campanacci syndrome. When multifocal or polyostotic non-ossifying fibromas occur together with café-au-lait macules and extraskeletal anomalies, consider Jaffe-Campanacci syndrome. The recognised features are:
- Multiple NOFs, causing bone fragility and recurrent pathological fractures
- Café-au-lait spots
- A variable combination of intellectual disability, hypogonadism or cryptorchidism, ocular anomalies, and cardiovascular malformations
It overlaps clinically with neurofibromatosis type 1, and both involve RAS-pathway mosaic mutations (see the KRAS evidence), so look specifically for neurofibromas and Lisch nodules and involve genetics and paediatrics. The orthopaedic priority is whole-skeleton fracture-risk assessment, because multiple large lesions weaken several bones at once.
Clinical Assessment
History. Start with why the imaging was done: trauma, knee pain, limp, deformity, or an incidental radiograph. True lesion pain is focal and activity-related, and many children have unrelated anterior knee pain. Sudden pain, inability to weight bear and swelling after low-energy trauma are fracture symptoms. The syndrome screen asks about café-au-lait macules, neurofibromas, developmental delay, jaw swelling, endocrine history, and a family history of NF1.
Examination. Look at limb alignment, swelling, deformity, gait, and the skin for stigmata of NF1. Feel for focal tenderness over the lesion; diffuse joint-line pain suggests another diagnosis. Move the adjacent joint for range, effusion and mechanical symptoms, and screen the hip and spine if pain is poorly localised. Test function with a single-leg hop, a squat, sport tolerance, and weight-bearing ability when safe.
Most NOFs are incidental. If the lesion is small and painless to direct palpation, search for common causes of pain: trauma, osteochondritis dissecans, stress injury, infection, inflammatory arthropathy, hip pathology referred to the knee, or sporting overuse. A classic NOF explains pain mainly when it is large, fractured, or directly tender.
The differential. The table holds the discriminators for a lytic metaphyseal lesion in a child. The NOF-versus-fibrous-dysplasia pair is the common exam trap because both occur in young patients and both are benign fibrous bone lesions.
- Typical Imaging
- Eccentric cortical metaphyseal lucency with sclerotic rim
- Clinical Clue
- Usually asymptomatic
- Discriminating Feature
- Classic scalloped rim, narrow transition zone
- Typical Imaging
- Central intramedullary ground-glass lesion
- Clinical Clue
- May cause deformity or pain
- Discriminating Feature
- Central, expansile, ground-glass matrix rather than cortical NOF
- Typical Imaging
- Expansile eccentric lytic lesion, often blow-out cortex
- Clinical Clue
- Painful, enlarging, sometimes after minor trauma
- Discriminating Feature
- MRI fluid-fluid levels and expansile behaviour
- Typical Imaging
- Central metaphyseal lucency, often proximal humerus or femur
- Clinical Clue
- Fracture presentation common
- Discriminating Feature
- Central lesion; fallen fragment sign after fracture
- Typical Imaging
- Wide transition zone, cortical destruction, periosteal reaction, soft tissue mass
- Clinical Clue
- Night pain, systemic symptoms, progressive pain
- Discriminating Feature
- Aggressive radiographic features; urgent sarcoma referral
Investigations
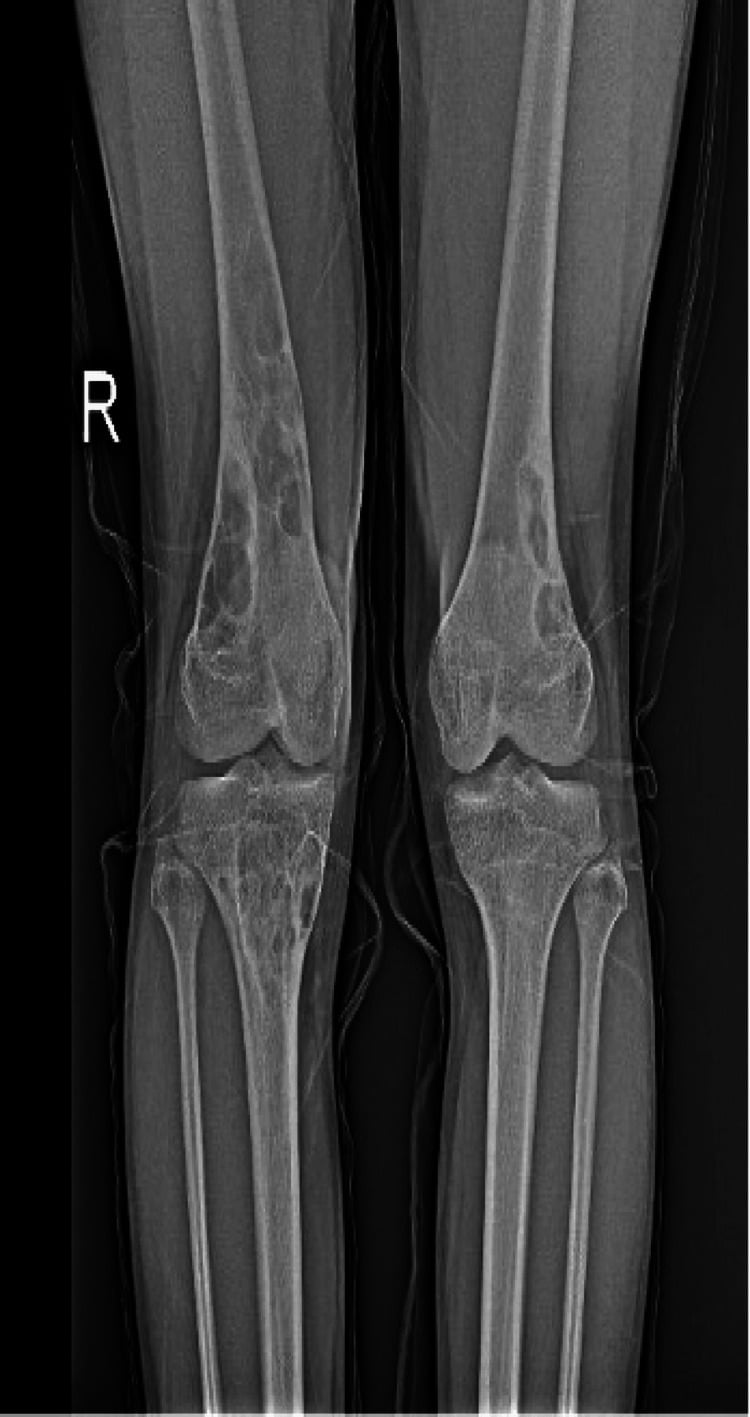
Plain radiographs. Orthogonal AP and lateral views of the involved bone, including the adjacent joints. The classic lesion is eccentric, cortically based, metaphyseal and well circumscribed, with a thin scalloped sclerotic rim and a narrow zone of transition. Its long axis usually parallels the bone, the matrix is lytic and multiloculated without aggressive mineralisation, and a large lesion may expand or thin the cortex.
If the child is pain-free and the pattern is classic, plain films are diagnostic; a ground-glass central matrix suggests fibrous dysplasia instead.
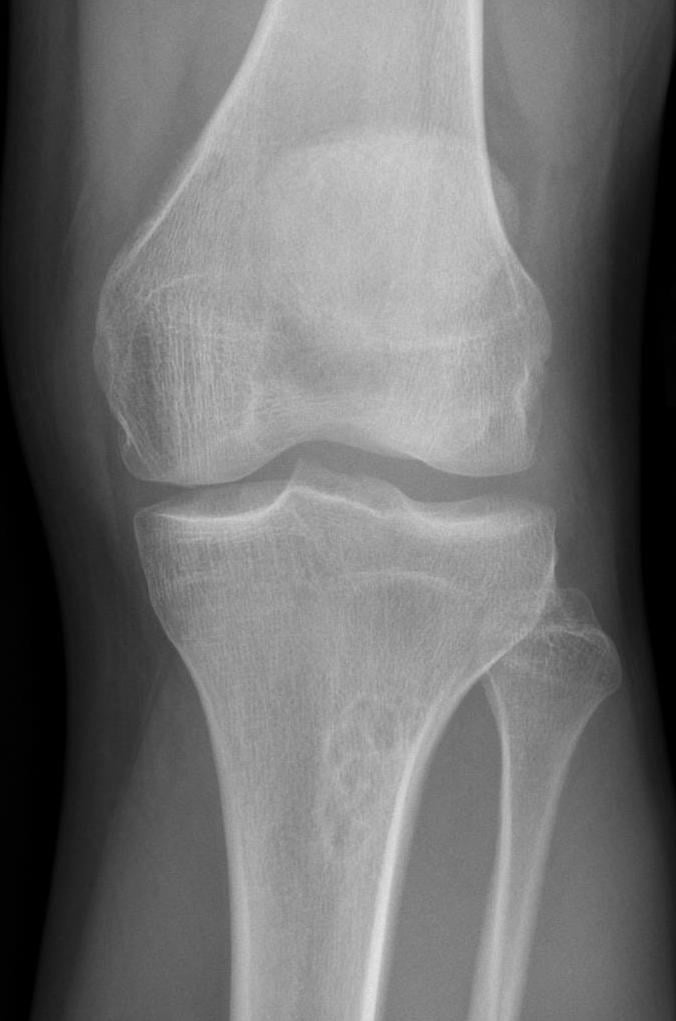
Measuring the lesion. Measure it in two ways: maximum length, and maximum transverse diameter as a proportion of the bone diameter, on both the AP and the lateral view. The classic Drennan / Arata risk flags are length greater than 33 mm and occupation of greater than 50 percent of the bone diameter.
Two precisions usually lost in the retelling. Arata's lesions exceeded 50 percent on both the AP and the lateral film, so a lesion that looks large on one projection alone has not met the criterion, which is exactly why you measure orthogonally. And the 33 mm applied to non-fibular lesions; a long fibular lesion was the stated exception, because the fibula is not carrying the load.
What the numbers are not. Arata described 23 children who had already fractured, with no comparison group of intact lesions, so the flags identify what a fractured NOF looks like and cannot tell you the probability that any particular large lesion will break. Most large NOFs never fracture and never come to surgery. Use the measurements to decide how carefully to look at the cortex and how closely to follow, not as an operative indication standing on its own.
CT. For selected large lesions where cortical support or fracture risk cannot be judged on plain radiographs. It confirms the cortically based nature of the lesion, defines cortical breach, the residual cortical shell and the geometry before prophylactic curettage or fixation, and helps quantify lesion size.
A lesion that breaches or deeply scallops the cortex, leaving a mouth-like defect on the axial slice, is a high-risk feature for pathological fracture and should trigger formal assessment of lesion size and cortical integrity and consideration of activity restriction or prophylactic treatment. Avoid routine CT in classic small lesions; the radiation rarely changes management.
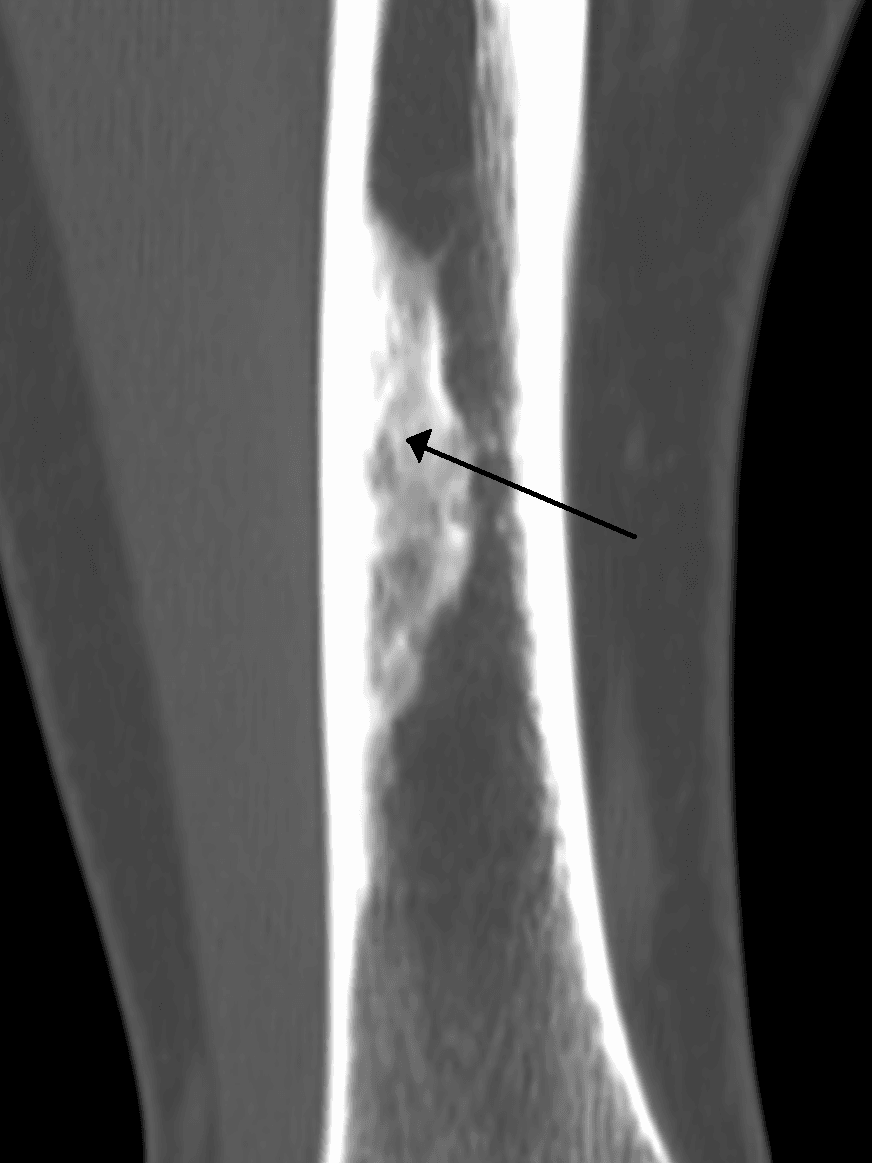
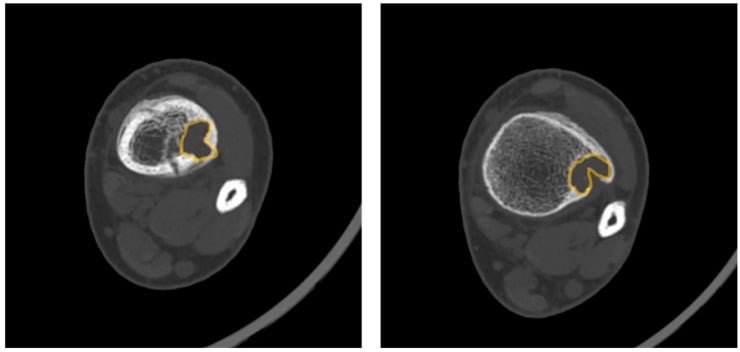
MRI. For atypical margins, aggressive features, persistent unexplained pain, or a possible infection, aneurysmal bone cyst or malignant mimic. NOF can show variable signal and enhancement, so MRI is most useful to exclude alternative diagnoses, not to prove a classic NOF.
A soft tissue mass, marrow oedema out of proportion, cortical destruction, or a wide zone of transition is a referral trigger.
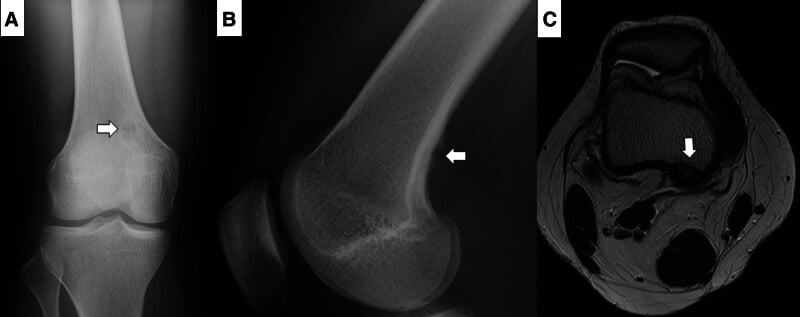
The report. Four questions decide what happens next.
- What to Record
- Age, metaphyseal location, eccentric cortical position, narrow transition zone
- Management Impact
- Classic lesion avoids biopsy and extensive workup
- What to Record
- Length in millimetres and percentage bone width on both views
- Management Impact
- Large lesions need fracture-risk counselling and surveillance
- What to Record
- Subtle cortical break, periosteal reaction, angulation, or displacement
- Management Impact
- Treat fracture according to paediatric fracture principles
- What to Record
- Poorly defined margin, soft tissue mass, aggressive periosteal reaction, epiphyseal extension
- Management Impact
- Urgent tumour referral and advanced imaging
Management Algorithm
The incidental classic lesion. The goal is to reassure the family, avoid unnecessary biopsy, and confirm the lesion is mechanically safe.
At the first visit confirm that the radiographic pattern is classic, explain that this is a benign developmental lesion, not cancer, with no malignant transformation expected and usually resolving with maturity, and assess the risk by measuring width and length and examining for focal tenderness and gait change.
Low-risk lesion. Small, asymptomatic, no cortical breach, and below the fracture-risk thresholds: normal activities, reassurance, no biopsy, no immobilisation. Discharge, or one interval radiograph if diagnostic confidence or family anxiety requires it.
Larger lesion. A lesion approaching greater than 50 percent bone width or greater than 33 mm, particularly in the tibia or femur, is watched.
That "or" is deliberately more cautious than the source, where every fractured lesion exceeded 50 percent on both views and every non-fibular one exceeded 33 mm, so a lesion meeting only one flag sits in a group Arata never described, and is a reason to watch rather than to operate. Modify activity for high-impact sport if the lesion is symptomatic or the cortex is very thin, and repeat radiographs until sclerosis or reduced mechanical concern.
The family needs two clear messages: the lesion is benign and usually self-resolving, but a large lesion can behave like a stress riser. That framing prevents both over-treatment and unsafe dismissal.
The large lesion at risk of fracture. The goal is to prevent avoidable fracture while avoiding prophylactic surgery for lesions that are simply large on a single projection. Stratify in clinic by measuring length, AP width, lateral width, cortical thinning and lesion stage. Focal pain, limp, or pain with loading increases concern, and distal tibial and other lower-limb weight-bearing lesions deserve closer attention.
Non-operative. Asymptomatic, stable, no fracture line, and sufficient cortex despite size: activity advice, avoiding high-risk impact while painful, and radiographic surveillance until progressive sclerosis or skeletal maturity.
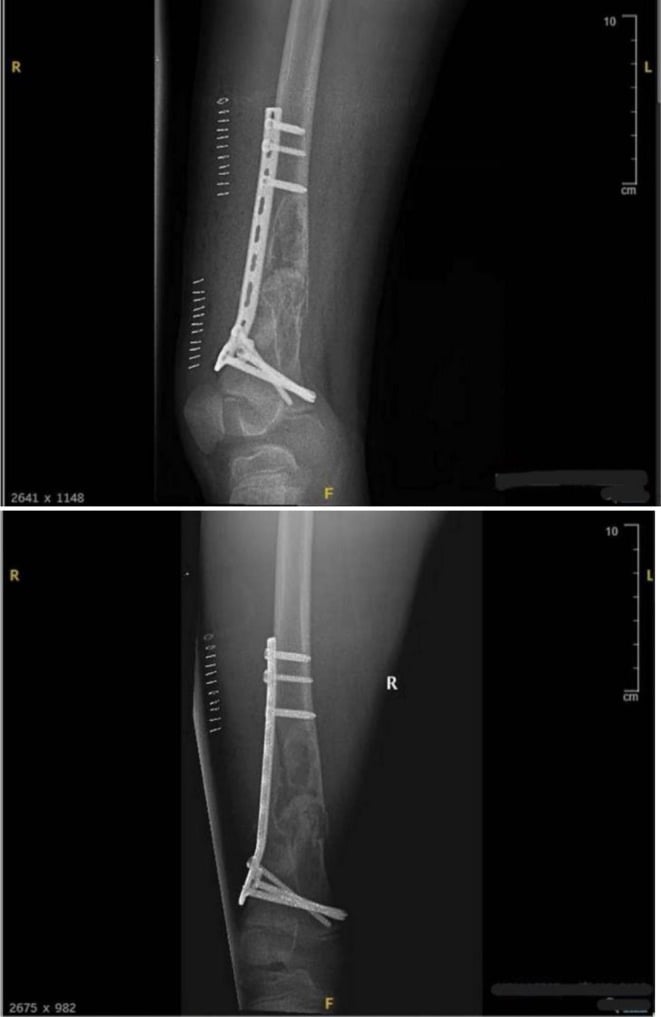
Prophylactic surgery. Selective, for pain, progressive cortical thinning, a very large weight-bearing lesion, impending fracture, or unacceptable activity risk. The operation is curettage through a cortical window, filling of the defect with bone graft or substitute, and fixation only if structural support is inadequate. Counsel that surgery treats mechanical risk, not malignant potential.
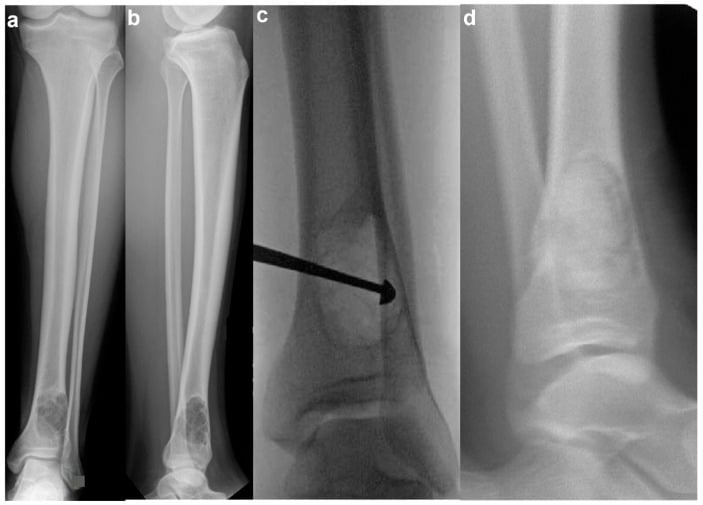
Pathological fracture. The goal is to heal the fracture, maintain alignment, and reassess the lesion after union.
Fix the fracture when the fracture needs fixation; do not operate merely because the background lesion has an alarming name.
- Undisplaced or acceptably aligned: immobilise in a cast or brace according to bone and age, restrict weight bearing until pain and radiographs permit progression, and after union decide whether the residual size still creates risk. Many fractures through NOF heal uneventfully with standard paediatric fracture care.
- Displaced, unstable, or load-bearing: reduction and fixation on standard paediatric fracture principles, curettage and grafting if the lesion compromises stability or remains a large void, and return to sport only after union and adequate cortical restoration.
- Indication
- Acceptably aligned fracture with stable cortex
- Outcome Goal
- Fracture union without surgery
- Complications
- Loss of reduction, delayed weight bearing
- Indication
- Large persistent defect after fracture or impending fracture
- Outcome Goal
- Fill mechanical void and promote ossification
- Complications
- Recurrence is rare; graft resorption or pain possible
- Indication
- Displaced fracture, unstable lower-limb lesion, or inadequate cortical support
- Outcome Goal
- Restore alignment and permit safe healing
- Complications
- Hardware irritation, infection, refracture if return too early
Complications
- Incidence
- Uncommon overall, concentrated in large lesions
- Risk Factors
- Greater than 50 percent bone width, greater than 33 mm length, lower limb, active lucent stage
- Management
- Immobilise or fix fracture; reassess lesion after union
- Incidence
- Avoidable when imaging is classic
- Risk Factors
- Failure to recognise benign radiographic pattern
- Management
- Correlate age, location, margin, and cortical position before referral
- Incidence
- Rare but high consequence
- Risk Factors
- Painful atypical lesion, wide transition zone, soft tissue mass, periosteal reaction
- Management
- Urgent MRI and sarcoma pathway referral
- Incidence
- Rare
- Risk Factors
- Multiple lesions, cafe-au-lait macules, jaw giant-cell lesions, endocrine or developmental features
- Management
- Genetics / paediatric assessment and whole-skeleton risk review
NOF does not become malignant. The reason to follow or treat a large lesion is mechanical weakness, especially in a weight-bearing bone. Explain this clearly: a child may need surveillance or curettage because the cortex is thin, not because the lesion is biologically dangerous.
Outcomes and Prognosis
- Treatment
- Reassurance, no intervention
- Expected Outcome
- Spontaneous sclerosis or resolution with maturity
- Long-term Function
- Normal function and unrestricted activity
- Treatment
- Observation or selective curettage
- Expected Outcome
- Usually stabilises as it ossifies; surgery prevents selected fractures
- Long-term Function
- Excellent if fracture is avoided or healed
- Treatment
- Standard fracture care with or without grafting / fixation
- Expected Outcome
- Union expected in most paediatric patients
- Long-term Function
- Return to sport after union and cortical restoration
Best prognosis: classic incidental lesion, small size, no pain, increasing sclerosis, and approaching skeletal maturity.
Higher-risk prognosis: large active lucent lesion, thin cortex in the distal tibia or femur, focal pain, or a previous pathological fracture.
Key threshold: large size changes fracture risk, not tumour biology.
Guidelines, Registries & Global Practice
- Worldwide lesion: NOF is common in children and adolescents across all health systems
- Detection pattern: most are found incidentally on radiographs taken for trauma or sports symptoms
- Clinical burden: low oncological burden, but large lower-limb lesions create fracture-risk decisions
- Syndromic cases: multiple lesions are uncommon and should prompt a broader clinical examination
- High-resource: MRI or CT may be used for atypical lesions or pre-operative mechanical assessment
- Limited-resource: plain radiographs are usually sufficient for classic lesions and fracture follow-up
- Universal principle: classic, small, asymptomatic NOF needs reassurance, not biopsy
- Referral: atypical imaging or aggressive features should enter a bone-tumour pathway wherever the child is treated
- Diagnosis emphasis
- Benign fibroblastic / histiocytic lesion of growing skeleton
- Observation / follow-up
- Clinical-radiographic diagnosis when classic
- Surgery / referral
- Histology reserved for atypical or uncertain cases
- Diagnosis emphasis
- Do not biopsy classic benign latent lesions unnecessarily
- Observation / follow-up
- Follow only if lesion is symptomatic, large, or atypical
- Surgery / referral
- Refer aggressive features to specialist tumour care
- Diagnosis emphasis
- Assess size, cortex, symptoms, and weight-bearing location
- Observation / follow-up
- Serial radiographs for large active lesions until sclerosis
- Surgery / referral
- Selective curettage / grafting for impending or recurrent fracture risk
- Diagnosis emphasis
- Treat pathological fracture by stability, alignment, age, and bone involved
- Observation / follow-up
- Observe lesion after union if cortical support restores
- Surgery / referral
- Fix unstable fractures and fill defects when structural support is inadequate
There is no implant or arthroplasty registry equivalent for NOF because most lesions are non-operative developmental findings. Evidence is mainly historical descriptions, retrospective fracture series, and observational natural-history studies. The practical global standard is therefore principle-based: recognise the classic benign lesion, measure mechanical risk, and refer atypical or aggressive imaging.
Record in every NOF assessment:
- Why the radiographic appearance is classic or atypical
- Lesion length and percentage bone diameter on AP and lateral views
- Whether there is focal tenderness, limp, fracture line, or cortical breach
- Family counselling: benign natural history, fracture-risk advice if large, and return precautions
Clear documentation prevents two opposite errors: unnecessary tumour anxiety in small classic lesions and unsafe reassurance in large lower-limb lesions.
Controversies & Areas of Uncertainty
Greater than 50 percent bone diameter and greater than 33 mm length are useful classic risk flags, but they are not absolute rules. Symptoms, site, cortical thickness, lesion stage, and child activity level all modify risk. The reason the threshold is uncertain is worth stating plainly, because it is a study-design problem rather than a gap that more experience has failed to close. Both source series - Drennan 1974 and Arata 1981 - assembled patients because they had fractured. Neither followed intact lesions forward, so neither contains a single lesion that met the criteria and did not break. That gives the flags near-total sensitivity by construction and leaves their specificity entirely unmeasured, and since large NOFs are common while pathological fracture through one is rare, the specificity is almost certainly low. No prospective cohort has been done in the fifty years since, and it would be a hard study to run: the event is uncommon, the lesions resolve with maturity, and randomising a child with a thin cortex to observation is difficult to justify. Until then the honest position is that the numbers flag a lesion worth looking at properly, and that the operative decision rests on the cortex, the symptoms and the bone involved.
There is no universally mandated follow-up schedule. Many units discharge small classic lesions, while large active lesions are followed until sclerosis or skeletal maturity reduces risk.
Surgery can prevent fracture in selected large symptomatic lesions, but many large lesions heal without operation. The decision balances fracture probability, sport exposure, lesion site, and family preference.
Multiple NOFs overlap clinically with NF1-spectrum findings. Whether a child has a distinct syndrome or NF1-related manifestation may require genetics and paediatric assessment.
Because the driver is RAS-MAPK activation, the pathway can in principle be blocked. The MEK inhibitor trametinib has been reported to produce radiological reossification of KRAS-driven multifocal NOFs and to stop the recurrent fractures — but the lesions relapsed after the drug was stopped, so this suppresses the disease rather than curing it. Weigh that against the evidence level: this rests on case reports (Level V) with an in-vitro correlate, not trials, and MEK inhibitors carry real toxicity. It is not a treatment for ordinary solitary NOF, where the lesion involutes on its own and surgery is the only question. Its place, if any, is severe polyostotic disease with repeated fractures, decided with paediatric oncology and genetics — but a candidate who can name the mechanism and its limits is answering the "what is new in this field" question well.
MCQ Practice Points
Q: What is the classic radiographic appearance of a non-ossifying fibroma? A: Eccentric, cortically based, metaphyseal, well-defined lytic lesion with a scalloped sclerotic rim in a child or adolescent. The long axis often parallels the bone, and the transition zone is narrow.
Q: Which NOFs are at risk of pathological fracture? A: Large active lesions in weight-bearing bones, especially those occupying greater than 50 percent of the bone diameter or measuring greater than 33 mm in length. Symptoms, cortical thinning, and site matter as much as a single measurement.
Q: How do you distinguish NOF from fibrous dysplasia? A: NOF is eccentric and cortical; fibrous dysplasia is central and ground-glass. Fibrous dysplasia may expand the medullary canal and produce deformity, whereas NOF has a thin sclerotic rim and cortical metaphyseal origin.
Q: What is the treatment for an incidental small NOF? A: Reassurance and observation. No biopsy, curettage, or activity restriction is required when the lesion is classic, asymptomatic, and mechanically low risk.
Q: What should multiple NOFs make you consider? A: Jaffe-Campanacci syndrome or NF1-spectrum features. Look for cafe-au-lait macules, neurofibromas, jaw giant-cell lesions, developmental or endocrine abnormalities, and family history.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 12-year-old footballer has knee radiographs after a twisting injury. The knee injury is improving, but the AP film shows a 22 mm eccentric lytic metaphyseal lesion in the distal femur with a thin scalloped sclerotic rim. He has no focal tenderness over the lesion and no systemic symptoms. How do you manage this?”
“A 10-year-old presents with activity-related distal tibial pain. X-rays show a 45 mm eccentric cortically based metaphyseal lesion with a sclerotic rim. It occupies greater than 50 percent of the tibial diameter on the lateral view, with marked cortical thinning but no fracture line. What is your assessment and management?”
Key Imaging
- Child or adolescent with eccentric cortically based metaphyseal lucency
- Thin scalloped sclerotic rim and narrow zone of transition
- Usually around the knee or distal tibia, but can occur in other long bones
- Fibrous dysplasia is central and ground-glass, not eccentric cortical
Diagnosis
- Plain radiographs diagnose a classic NOF
- No biopsy for an asymptomatic textbook lesion
- MRI only for atypical features, persistent unexplained pain, or aggressive mimic
- Multiple lesions require skin, jaw, endocrine, developmental, and family-history assessment
Fracture Risk
- Large lesion: greater than 50 percent bone diameter or greater than 33 mm length
- Risk highest in lower-limb weight-bearing bones with cortical thinning
- Pain, limp, and active lucent stage increase concern
- Size thresholds are risk flags, not automatic surgery indications
Treatment Algorithm
- Small incidental NOF = reassure, observe, no activity restriction
- Large asymptomatic NOF = measure, counsel, consider surveillance and activity advice
- Symptomatic high-risk NOF = consider curettage and graft / substitute
- Fractured NOF = treat fracture first, then reassess residual lesion
Exam Traps
- Do not call NOF malignant; it is benign and self-limiting
- Do not confuse NOF with central ground-glass fibrous dysplasia
- Do not ignore a large distal tibial lesion because the diagnosis is benign
- Do not miss Jaffe-Campanacci / NF1 features when lesions are multiple
Evidence Base and Key Trials
Pathological Fractures Through Non-Ossifying Fibromas - the Origin of the Size Criteria (Arata, 1981)
- 23 pathological fractures through histologically verified NOF, collected at the Mayo Clinic over 49 years; mean age at fracture 12 years
- All but one fracture was in the lower limb, most often the distal tibia (10 of 23)
- The lesion exceeded 50 per cent of the transverse bone diameter on BOTH the AP AND the lateral radiograph in EVERY patient - not on one view
- Vertical length was always the maximum dimension and exceeded 33 mm in every NON-FIBULAR lesion; fibular lesions were the stated exception
- Treatment was cast immobilisation with later biopsy, simple curettage, curettage with autogenous grafting, or segmental resection of fibular lesions
Fractures Through Large Non-Ossifying Fibromas - the Earlier Series (Drennan, 1974)
- The earlier of the two series that the size criteria are jointly attributed to, predating Arata by seven years
- Established the association between large metaphyseal fibrous defects and pathological fracture in the growing lower limb
- Named alongside Arata whenever the size flags are quoted, so the eponym pair is 'Drennan / Arata' rather than either alone