Sarcomatous Transformation of Paget Disease | Usually Osteosarcoma | Poor Prognosis
- Paget sarcoma is a secondary high-grade bone sarcoma arising in a bone previously affected by Paget disease
- Lifetime risk of sarcomatous transformation in Paget is less than 1% (older series quoted 5-10%, modern estimates lower)
- Osteosarcoma accounts for 50-60%; fibrosarcoma / MFH and chondrosarcoma account for most of the remainder
- Classic clinical pattern: new or worsening pain, a palpable mass or a pathological fracture in a patient with long-standing Paget
- Biopsy must be performed by the musculoskeletal tumour service - core needle, tract planned for later resection
- Prognosis is markedly worse than primary osteosarcoma in adolescents - 5-year survival around 5-25%
- “Paget sarcoma is the prototypical secondary bone sarcoma - elderly patient, girdle bones, no prior radiation required
- “Suspect malignant change when pain in a Paget bone changes character, escalates, becomes constant, or wakes the patient at night
- “A new soft-tissue mass or pathological fracture in Paget bone is malignant until proven otherwise
- “ALP may already be elevated from Paget - a further sustained rise raises suspicion but is not diagnostic
- “Biopsy should be the last investigation, not the first - full imaging first to identify the most representative target
Overview and Epidemiology
Paget sarcoma is a high-grade bone sarcoma arising in a bone affected by Paget disease, and osteosarcoma is its dominant subtype. It is uncommon, but it ties together two of the most heavily examined musculoskeletal topics, Paget disease of bone and the primary malignant bone tumours. Know the risk, the dominant histology and the presentation pattern, and be able to separate Paget sarcoma from a giant cell tumour arising in Paget, which is a separate, often benign entity.
Risk. In modern cohorts fewer than 1% of patients with Paget disease develop sarcomatous transformation. The older literature quoted 5-10%; the true risk is lower, but the absolute number of cases is high because Paget affects 1-2% of adults over 55 in European populations. The sarcoma almost always arises in polyostotic or long-standing Paget: polyostotic disease carries a higher risk than monostotic, and the longer the disease has been active and the more bones involved, the higher the cumulative risk.
Who. The median age is 60-70 years, decades older than in primary osteosarcoma, and there is a slight male predominance.
Where. Pelvic and long-bone sites dominate, above all the pelvis, proximal femur and proximal humerus. In Huvos's series the pelvis accounted for 34%, the humerus 22%, the femur 19% and the craniofacial bones 14%.
The spine is spared. Paget disease has a strong predilection for the axial skeleton and spine, yet pagetic sarcoma conspicuously spares the spine. A vertebra riddled with Paget disease very rarely becomes the site of the sarcoma, while the pelvis and humerus are over-represented relative to their share of pagetic bone, so the distribution of the sarcoma does not simply mirror that of the disease. Nobody has explained this convincingly, and it is a good discriminator to be able to state.
The cost. Five-year overall survival is 5-25%, markedly worse than primary osteosarcoma in adolescents. Lung metastases are present at diagnosis in 10-25%, and most patients need a major resection, often pelvic or proximal femoral, or an amputation.
Asked for the causes of secondary osteosarcoma, lead with Paget and prior radiation, then add the rest:
- Paget disease, the commonest cause of secondary osteosarcoma in the elderly
- Prior radiation (post-radiation osteosarcoma)
- Fibrous dysplasia: rare malignant transformation, higher in polyostotic disease and McCune-Albright
- Bone infarct, for example in sickle-cell disease, caisson disease or steroid-related infarcts
- Chronic osteomyelitis: rare; Marjolin-type squamous change is more classical, but sarcoma is reported
- Genetic predisposition: hereditary retinoblastoma (RB1), Li-Fraumeni (p53), Rothmund-Thomson, though these are arguably "primary" in a predisposed host
For post-radiation sarcoma, know Cahan's criteria:
- The tumour arises within a previously irradiated field
- A latency period of, classically, at least 3-5 years
- It is histologically distinct from, or different in type to, the original irradiated lesion
- There is histological proof of sarcoma
Paget sarcoma needs no prior radiation: the pagetoid bone itself is the substrate.
Pathophysiology
The disease underneath. Paget disease is a disorder of dysregulated bone remodelling driven by abnormal osteoclasts. They contain characteristic nuclear and cytoplasmic inclusions, paramyxovirus-like on electron microscopy and possibly viral in origin, and the disease is associated with somatic mutations in the SQSTM1/p62 gene. The relentless remodelling cycle (lytic, mixed, sclerotic) creates a high bone-turnover state with disordered matrix.
The step to sarcoma. Over years, genomic instability accumulates and a clonal high-grade sarcoma emerges, most often osteosarcoma. The model is stepwise:
- SQSTM1/p62 mutation drives abnormal osteoclast signalling through the NF-kB pathway
- A chronic high-turnover state, with disordered lamellar bone
- Decades of cellular stress, with p53 mutation and chromosomal aneuploidy
- A clonal high-grade sarcoma, its osteoid matrix produced by malignant cells
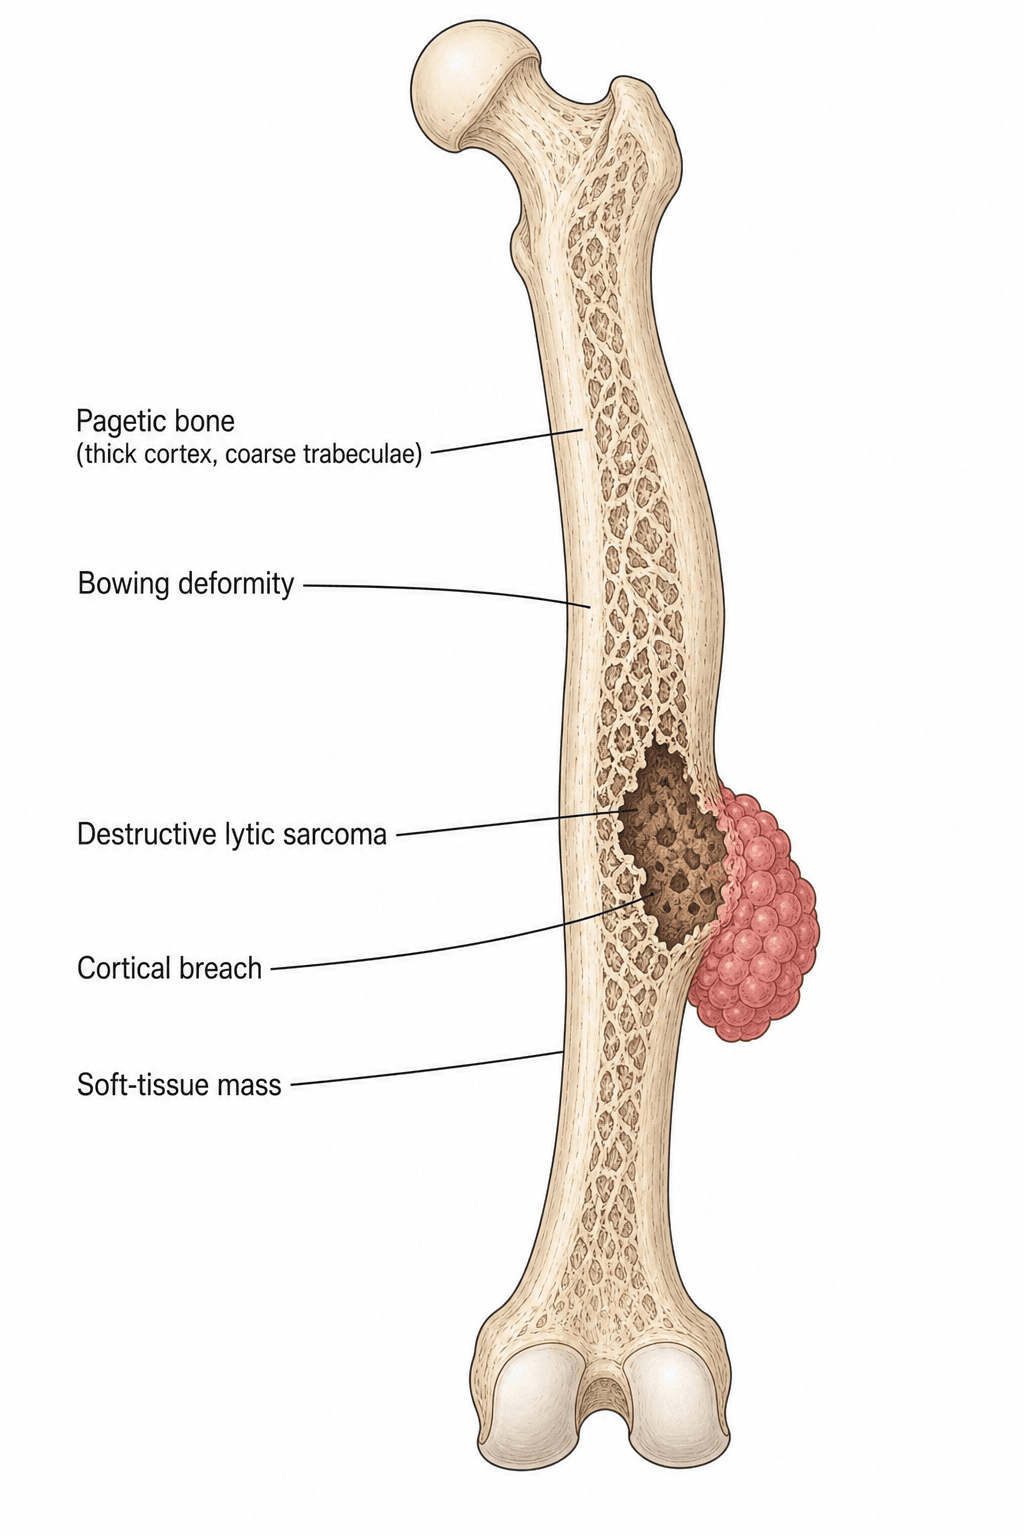
- Paget Disease
- Dysregulated but polyclonal remodelling
- Paget Sarcoma
- Clonal malignant mesenchymal proliferation
- Paget Disease
- SQSTM1/p62 (sequestosome 1) common
- Paget Sarcoma
- p53 loss / mutation frequent in sarcoma
- Paget Disease
- Mosaic pattern of cement lines, large osteoclasts
- Paget Sarcoma
- Pleomorphic spindle cells, malignant osteoid (osteosarcoma)
- Paget Disease
- Benign, controlled by bisphosphonates
- Paget Sarcoma
- Aggressive, metastasises to lungs
Classification and Types
Paget sarcoma is classified three ways: by histology, which drives chemotherapy sensitivity; by site, which governs resectability; and by local extent. Osteosarcoma dominates the histology, and chondrosarcoma is relatively chemo-resistant.
- Frequency
- 50-60% (most common)
- Behaviour
- Aggressive, osteoid producing, lung mets
- Treatment
- Wide resection + multi-agent chemo
- Frequency
- 20-25%
- Behaviour
- Spindle cell, lytic, soft tissue mass
- Treatment
- Wide resection +/- radiotherapy
- Frequency
- 10-15%
- Behaviour
- Cartilaginous matrix, may dedifferentiate
- Treatment
- Wide resection (chemo less effective)
- Frequency
- less than 10%
- Behaviour
- Variable
- Treatment
- Subtype-specific protocols
Clinical Assessment
The history. The background is known Paget disease, often polyostotic and present for many years. The complaint is a change in the pain at a known Paget site: new in onset, escalating, or waking the patient at night. Weight loss and fatigue suggest a high-grade malignancy. Ask about function (a limp, reduced range, inability to weight-bear) and about a pathological fracture after minimal trauma.
The examination. Look for deformity of the Paget bone and for new swelling or asymmetry. Palpate for a hard, often fixed mass with warm overlying skin, and test movement for restricted range and pain at end-range. Rule out nerve or vessel compromise, especially with pelvic lesions; lymphadenopathy is rare, and there may be chest signs if there are lung metastases.
The red flags in a Paget bone are new or worsening pain, a new palpable mass and a pathological fracture. Constant or night pain is malignant until proven otherwise. ALP may already be elevated by the Paget disease, so a rise above the patient's own stable baseline is suspicious but not specific.
New constant pain in a known Paget bone plus a palpable mass plus a rising ALP = malignancy until proven otherwise. Arrange urgent MRI of the painful segment, CT chest and referral to a musculoskeletal tumour service. Do not start bisphosphonates empirically and do not reassure: the earlier Paget sarcoma is biopsied and treated, the better the chance of cure.
CHANGERed Flags in a Paget Bone
Hook:Any CHANGE in a Paget bone - pain, mass, ALP, X-ray, site or extension - must raise suspicion of sarcoma!
The differential. Not every new lesion in a Paget bone is a sarcoma, and the imaging clue and the key test separate the alternatives.
- Discriminating features
- Constant pain, mass, pathological fracture
- Imaging clue
- Cortical destruction, soft tissue mass
- Key test
- Core needle biopsy via tumour service
- Discriminating features
- Pain, lytic lesion
- Imaging clue
- Well-defined lytic lesion, no soft tissue mass
- Key test
- Curettage / histology; often benign
- Discriminating features
- Known primary, weight loss, multiple lesions
- Imaging clue
- Multiple lytic / blastic lesions
- Key test
- Whole-body staging, biopsy of accessible site
- Discriminating features
- Acute pain after fall, deformity, no mass
- Imaging clue
- Fracture line through pagetoid trabeculae
- Key test
- MRI to exclude underlying sarcoma
- Discriminating features
- Fever, raised inflammatory markers
- Imaging clue
- Periosteal reaction, sinus tract, soft tissue oedema
- Key test
- Aspiration, blood cultures, biopsy
A giant cell tumour arising in a bone affected by Paget disease is a separate, usually benign entity. It is histologically identical to conventional GCT, but the patient is older (50-70), the Paget involvement is often polyostotic, and the lesion is most often in the skull, facial bones, pelvis or spine. Do not call every Paget-associated bone tumour "sarcoma": GCT in Paget is curetted, not widely resected.
Investigations
Radiographs first. AP and lateral views of the painful segment, including the whole bone and the joint above and below. Paget disease alone gives a coarsened trabecular pattern, cortical thickening and bone enlargement; sarcoma superimposes a destructive pattern on the pagetoid bone, with cortical lysis, periosteal reaction, a soft-tissue mass or a pathological fracture. Compare with prior films: any change in the Paget appearance is suspicious, and any new finding within a Paget bone is malignant until proven otherwise.
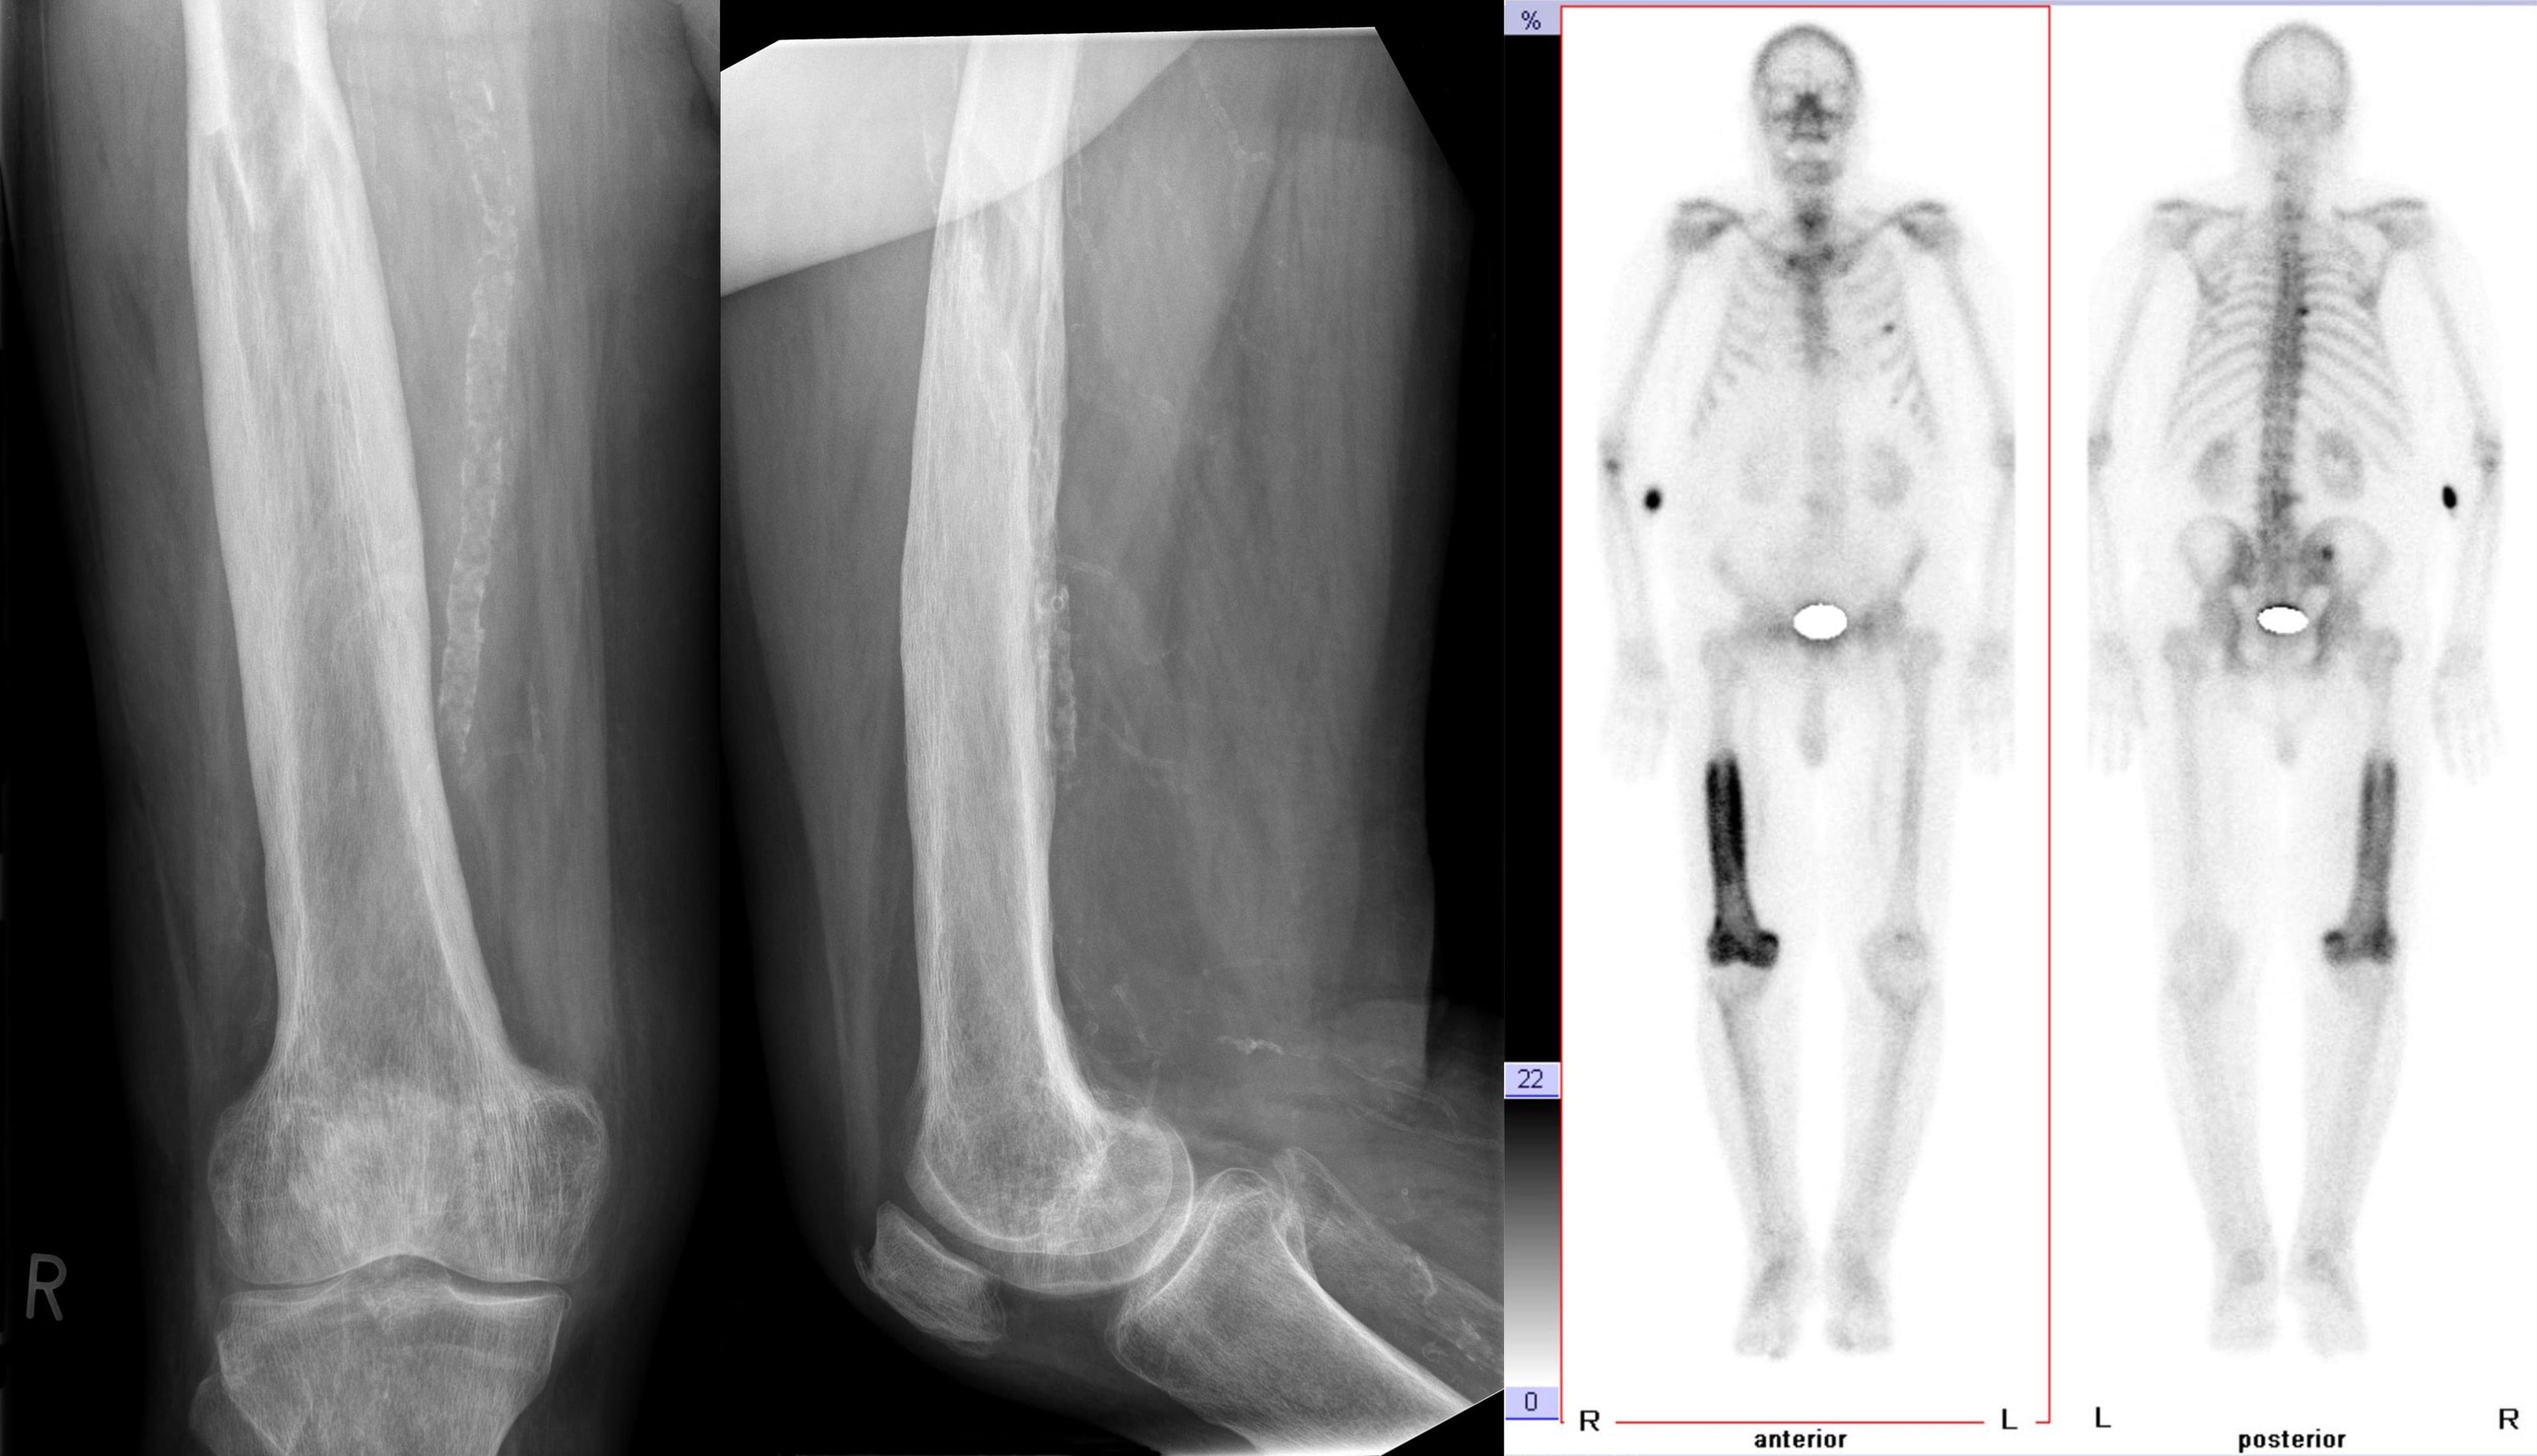
MRI of the whole bone is indicated in every suspected Paget sarcoma and is the best modality for local staging. It defines the intraosseous and extraosseous extent: marrow oedema beyond that expected from Paget, a soft-tissue mass and neurovascular involvement. Sequences are T1, STIR and post-contrast T1 fat-sat, and the study includes the whole bone to catch skip lesions.
CT of the lesion gives better cortical detail than MRI, showing cortical breakthrough, fracture lines and matrix mineralisation. It is the surgical planning study, used for the biopsy trajectory and for endoprosthetic sizing.
Distant staging. CT chest, because the lungs are the first site of metastasis in osteosarcoma, and a bone scan or PET to identify other Paget-involved bones and any skip lesions. Both provide a baseline for post-treatment surveillance.
Primary osteosarcoma is almost always a solitary lesion. Paget sarcoma can be multicentric, synchronous in more than one pagetoid bone, because every bone affected by long-standing Paget carries the same malignant potential; this is a recognised and testable distinction.
- The whole-body bone scan or PET is not just for skip lesions: it is needed to detect a second synchronous sarcoma in another Paget site, which completely changes prognosis and resectability
- A new aggressive lesion in one Paget bone should prompt scrutiny of every other involved bone. A second focus of intense, destructive uptake, distinct from the diffuse uptake of active Paget, is suspicious
- Multicentric Paget sarcoma behaves as disseminated high-grade disease and is generally treated palliatively
Asked how Paget sarcoma is staged differently from a teenager's primary osteosarcoma, say that it may be multifocal, so you image the entire skeleton, not just the symptomatic bone and the chest.
- Paget disease alone
- Coarsened trabeculae, cortical thickening, enlargement
- Paget sarcoma
- Cortical lysis, soft tissue mass, fracture
- Comment
- Most useful single sign is a new finding
- Paget disease alone
- Marrow oedema in active Paget, no soft tissue mass
- Paget sarcoma
- Soft tissue mass, neurovascular involvement
- Comment
- Best modality for local staging
- Paget disease alone
- Increased uptake in active Paget segments
- Paget sarcoma
- New focus of intense uptake, often with photopenic centre
- Comment
- Useful for skip lesions and other Paget sites
- Paget disease alone
- Mild to moderate uptake in active Paget
- Paget sarcoma
- Markedly increased FDG avidity (SUV greater than 5)
- Comment
- Helps pick biopsy target and stage disease
- Paget disease alone
- Often elevated (reflects Paget activity)
- Paget sarcoma
- Sustained rise above patient's own baseline
- Comment
- Trend over months is more useful than single value
- Paget disease alone
- Usually normal
- Paget sarcoma
- Hypercalcaemia uncommon (unlike myeloma / mets)
- Comment
- If raised, look for immobility or concurrent pathology
Biopsy comes last. Full imaging comes first, to identify the most representative target and to plan the tract; never incise or biopsy first. The biopsy is a core needle biopsy by a musculoskeletal radiologist or surgeon from the tumour centre:
- At least 3-4 cores from the solid, viable part of the tumour
- Through a planned tract along the future resection corridor, which will be excised at definitive surgery
- Without contaminating uninvolved compartments or letting haematoma drain away from the resection bed
Management Algorithm
The principle. Wide surgical resection, limb-sparing when oncologically safe, plus multi-agent chemotherapy for the osteosarcoma subtype. Radiotherapy is reserved for unresectable or margin-positive disease, and bisphosphonates or denosumab control ongoing Paget activity. Each pathway below starts with the sarcoma MDT.
- Diagnosis
- X-ray + MRI + core biopsy (tumour service)
- Treatment
- Wide resection + chemotherapy if osteosarcoma
- Key Pearl
- Biopsy is the last investigation
- Diagnosis
- CT chest + bone scan + core biopsy
- Treatment
- Multimodal: surgery + chemo +/- radiotherapy
- Key Pearl
- Prognosis worse than primary osteosarcoma
- Diagnosis
- X-ray + ALP trend, no urgent biopsy
- Treatment
- Optimise bisphosphonate / denosumab for Paget
- Key Pearl
- Most Paget pain is not sarcomatous change
- Diagnosis
- MRI, biopsy, whole-body staging
- Treatment
- Treat the actual lesion (curettage for GCT, etc.)
- Key Pearl
- GCT in Paget is a separate entity, not sarcoma
Proximal femur, humerus or tibia. The goal is a wide (R0) resection with limb-sparing reconstruction when oncologically safe, combined with multi-agent chemotherapy for the osteosarcoma subtype.
Treatment Protocol
Confirm the histology, imaging and fitness for chemotherapy. The team of sarcoma surgeon, medical oncologist, radiologist, pathologist and specialist nurse documents the planned surgical margins, reconstruction and neoadjuvant or adjuvant chemotherapy.
Cisplatin / doxorubicin / high-dose methotrexate, the regimen varying by centre, to downstage the tumour, treat micrometastatic disease and assess the response histologically. Elderly patients often tolerate dose-reduced regimens poorly.
Wide (R0) margins, taking the biopsy tract en bloc. Reconstruction is by endoprosthetic replacement or allograft-prosthetic composite, or amputation if required.
Complete the planned osteosarcoma regimen if tolerated, and consider radiotherapy for positive or close margins or unresectable disease. A bisphosphonate or denosumab controls ongoing Paget activity at other sites.
Chest CT every 3 months for 2 years, then 6-monthly, and MRI of the surgical bed at 3, 6 and 12 months, then as indicated. Functional care is physiotherapy and prosthesis refinement.
Limb salvage. Limb-sparing surgery is achievable in the majority of appendicular Paget sarcomas, but it requires wide margins and proper handling of pagetoid bone. Plan the endoprosthetic reconstruction around the abnormal anatomy, not around a "normal" template. Amputation is reserved for neurovascular involvement, fungation or unreconstructable bone loss.
Paget bone is sclerotic, porotic, vascular and deformed. Drilling produces bone that cuts like wet balsa, then streams blood. Screws strip, plates do not contour, and cement behaves unpredictably. Plan for it: have augmentative fixation strategies ready (intramedullary nails, cemented stems, custom prostheses). Tourniquet time, blood loss and surgical duration are higher than for the same operation in normal bone.
Complications
- Incidence
- 30-50% within 2 years
- Risk Factors
- High grade, axial site, large tumour
- Management
- Pulmonary metastasectomy if resectable; otherwise palliative chemo
- Incidence
- 20-40% (higher axial)
- Risk Factors
- Positive margins, extracompartmental disease
- Management
- Re-resection or radiotherapy for palliation
- Incidence
- 15-25% at presentation
- Risk Factors
- Lytic destruction, proximal femur / humerus
- Management
- Stabilise before chemo; definitive fixation at resection
- Incidence
- 10-20% at 5 years
- Risk Factors
- Paget bone quality, age, weight
- Management
- Revision arthroplasty
- Incidence
- Common in elderly
- Risk Factors
- Renal (methotrexate), cardiac (doxorubicin), marrow
- Management
- Dose reduction, growth factor support
- Incidence
- Common
- Risk Factors
- Polyostotic Paget, ongoing activity
- Management
- Bisphosphonates (zoledronate) or denosumab
Outcomes and Prognosis
Why outcomes are so poor. The patients are older, and comorbidities limit chemotherapy dose-intensity. The tumour is often axial or pelvic, which limits resectability; it is high grade at presentation in the majority, its p53-driven biology is often chemo-resistant, and lung metastases are common at diagnosis. Diagnosis is delayed when symptoms are wrongly attributed to Paget pain.
Stage and resectability dominate. In Longhi's Rizzoli series of patients over 65, stage, tumour volume and surgery were significant prognostic factors on multivariate analysis and Paget disease itself was not. With only 13 Paget sarcomas that null cannot exclude a real effect of pagetic biology, but it points the blame at late presentation and unresectable axial bulk.
- Treatment
- Wide resection + chemo
- Expected Outcome
- 5-year survival 20-30%
- Long-term Function
- Limb preserved in most; functional loss around resection
- Treatment
- Surgery (if feasible) + chemo + RT
- Expected Outcome
- 5-year survival 5-10%
- Long-term Function
- Major functional loss; amputation rate 20-30%
- Treatment
- Palliative chemo + local control
- Expected Outcome
- Median survival under 12 months
- Long-term Function
- Focus on pain control and quality of life
- Treatment
- Re-resection / radiotherapy
- Expected Outcome
- Median survival 12-18 months
- Long-term Function
- High symptom burden - early palliative care
Prognostic factors. The outlook is better with an appendicular site, a small tumour, no pathological fracture, R0 margins and a patient able to tolerate full-dose chemotherapy. It is worse with:
- An axial or pelvic site
- Large size, greater than 8 cm
- Pathological fracture at presentation
- Positive margins; an intralesional margin makes local recurrence inevitable
- Lung metastases at diagnosis
- Poor performance status
The single biggest adverse factor is axial location (pelvis, sacrum, spine), because resectability and chemotherapy tolerance are both compromised. Axial Paget sarcoma has the worst prognosis: late presentation, the technical difficulty of pelvic surgery and high-grade biology together explain a five-year survival often under 10%. Patients with a small, peripheral Paget sarcoma diagnosed early have the best chance of cure.
Guidelines, Registries & Global Practice
- Paget disease is most prevalent in British descent populations (UK, Australia, New Zealand, North America) and least common in Scandinavia, Asia and Africa
- Paget sarcoma therefore clusters in the same populations, peaking in the seventh and eighth decades
- Male:female ratio approximately 1.5:1
- Polyostotic Paget carries a higher sarcomatous transformation risk than monostotic
- High-resource: dedicated musculoskeletal tumour centres with MDT, core-needle biopsy, endoprosthetic reconstruction, multi-agent chemotherapy
- Limited-resource: open incisional biopsy by the resecting surgeon, cement-augmented internal fixation for palliation, single-agent chemotherapy or radiotherapy for symptom control
- Universal principle: biopsy is the LAST investigation, not the first; the tract must be planned with the future surgery in mind
- Paget control: zoledronate 5 mg IV annually is the global standard; denosumab is used in refractory or renal-impaired patients
- Diagnosis emphasis
- MDT review, planned core biopsy, MRI + CT chest staging
- Treatment emphasis
- Wide resection + multi-agent chemo (osteosarcoma regimens)
- Prognosis
- 5-year survival 5-25 percent, registry-dependent
- Diagnosis emphasis
- Referral to designated sarcoma centre before any intervention
- Treatment emphasis
- Surgery in specialist centre, chemo on case-by-case basis
- Prognosis
- Outcomes audited by NHS sarcoma database
- Diagnosis emphasis
- Compare with prior films, MRI whole bone, biopsy by tumour service
- Treatment emphasis
- Limb-sparing when R0 feasible; amputation otherwise
- Prognosis
- Prognosis worse than primary osteosarcoma
- Diagnosis emphasis
- Optimise underlying Paget control with zoledronate
- Treatment emphasis
- Paget control does not prevent sarcoma but reduces fracture risk
- Prognosis
- Advocates research registries for Paget sarcoma
There is no dedicated international Paget sarcoma registry, but Paget cases are captured within national sarcoma registries (NCCN, NHS, SEER). The evidence base for Paget sarcoma is dominated by single-centre retrospective series and histology reviews, with very few prospective trials because the disease is rare. Modern management extrapolates from primary osteosarcoma trials, acknowledging that elderly Paget patients tolerate chemotherapy less well.
Record in every Paget patient with new pain:
- Comparison with prior imaging and ALP trend
- MRI and CT chest performed before biopsy
- Biopsy tract documented on a diagram in the notes
- MDT outcome communicated in writing to the patient and GP
- Prognosis discussed honestly with patient and family
A missed Paget sarcoma - "treated as Paget pain" with a bisphosphonate boost - is a recurring cause of late-stage presentation and complaints worldwide. When in doubt, image the painful segment and refer to the tumour service.
Controversies & Areas of Uncertainty
No high-quality evidence shows that bisphosphonates or denosumab reduce the risk of Paget sarcoma. They control Paget activity (bone turnover, pain, deformity) and reduce fracture risk, but the malignant potential of pagetoid bone is not abolished. The reduction in fracture may even delay detection by making a fracture the presenting sign less common.
Evidence from primary osteosarcoma supports multi-agent chemotherapy in patients able to tolerate it. In Paget sarcoma, the decision is individualised by age, comorbidity, histology and patient preference. Some centres offer dose-modified regimens or single-agent doxorubicin in older patients; others reserve chemo for osteosarcoma subtype only.
Wide (R0) margins are the surgical goal, but Paget bone is poorly defined macroscopically, so margins are technically harder to achieve. Amputation rates in pelvic Paget sarcoma exceed 20 percent. Functional outcomes after limb-sparing surgery are often comparable to amputation in the long term, but immediate morbidity differs.
SQSTM1/p62 and NF-kB pathway biology is under investigation as a targetable driver. Trials of denosumab, immune checkpoint inhibitors and SQSTM1-directed agents are early-phase. Until results are available, multimodal surgery and chemotherapy remain the standard of care.
MCQ Practice Points
Q: What is the approximate lifetime risk of sarcomatous transformation in a patient with Paget disease of bone? A: Less than 1 percent in modern cohorts (older literature quoted 5-10 percent, but contemporary series are lower). The risk is higher in polyostotic Paget and in those with a family history. The ABSOLUTE number of cases remains clinically meaningful because Paget is common in older adults.
Q: What is the most common histological subtype of Paget sarcoma? A: Osteosarcoma, accounting for 50-60 percent. The remainder are mostly fibrosarcoma / malignant fibrous histiocytoma and chondrosarcoma. The histological subtype matters for chemotherapy sensitivity - osteosarcoma is the most chemo-sensitive, chondrosarcoma the least.
Q: What clinical pattern should make you suspect malignant transformation in a Paget bone? A: A change in pain character - new onset, escalating or constant pain, night pain - in a bone with known Paget disease, especially when accompanied by a palpable mass or pathological fracture. A rising ALP above the patient's own baseline is supportive but not specific.
Q: Why must biopsy be the last investigation in a suspected Paget sarcoma? A: Because the biopsy tract must lie within the planned surgical resection corridor. An improperly placed biopsy contaminates uninvolved compartments and can convert a limb-sparing operation into an amputation. Biopsy should be performed by the musculoskeletal tumour service that will do the definitive surgery.
Q: What is the cornerstone of treatment for resectable Paget sarcoma? A: Wide (R0) surgical resection combined with multi-agent chemotherapy for osteosarcoma subtype. Limb-sparing surgery is preferred when oncologically safe; amputation is reserved for neurovascular involvement or unreconstructable bone loss. Radiotherapy is added for positive margins or unresectable disease.
Q: Why is the prognosis of Paget sarcoma worse than primary osteosarcoma? A: Patient age (60-70 years) limits chemotherapy dose-intensity, axial sites (pelvis, sacrum) are commonly involved and difficult to resect, lung metastases are common at presentation, and the underlying biology (p53-driven) is often chemo-resistant. Five-year overall survival is 5-25 percent compared with greater than 60 percent for primary extremity osteosarcoma in adolescents.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 72-year-old man with known polyostotic Paget disease of the pelvis and proximal femur presents with 6 weeks of escalating pain in the right ilium, waking him at night. On examination there is a firm, fixed mass over the right iliac fossa. His ALP has risen from a stable baseline of 450 to 980 U/L. X-ray shows cortical destruction and a soft tissue mass arising from the ilium. How would you manage this?”
“A 68-year-old woman with known Paget disease of the proximal femur presents with acute pain in the right hip after tripping on a rug. X-ray shows a pathological fracture through a lytic lesion in the subtrochanteric femur. There is no prior imaging for comparison. How do you proceed?”
Definition and Risk
- Paget sarcoma = high-grade bone sarcoma arising in a bone affected by Paget disease
- Lifetime risk less than 1 percent in modern cohorts (older 5-10 percent estimates are too high)
- Risk rises with polyostotic Paget, family history, and duration of disease activity
- Median age 60-70 years, slight male predominance
Pathology
- Osteosarcoma accounts for 50-60 percent - the dominant subtype
- Fibrosarcoma / MFH and chondrosarcoma account for most of the remainder
- SQSTM1/p62 mutation drives Paget; p53 loss is enriched in Paget sarcoma
- Biology is high-grade, often chemo-resistant, lung-seeking
Sites and Presentation
- Pelvis 34%, humerus 22%, femur 19% - and note the discordance: Paget favours the SPINE, pagetic sarcoma SPARES it
- Pelvic and sacral lesions have the worst prognosis because of resectability
- New constant pain, night pain, palpable mass or pathological fracture are the red flags
- Rising ALP above the patient's own baseline is supportive but not specific
Imaging and Staging
- Plain X-ray of the painful segment plus the joint above and below - compare with priors
- MRI of the WHOLE bone for local staging and soft tissue extent
- CT chest for lung metastases (most common distant site)
- Bone scan or PET to identify other Paget-involved bones and skip lesions
Biopsy Rules
- Biopsy is the LAST investigation, not the first - image first
- Core needle biopsy by the musculoskeletal tumour service
- Biopsy tract placed along the planned future resection corridor
- Multiple cores from the SOLID, VIABLE part of the tumour - 3-4 cores minimum
Treatment
- Resectable appendicular disease: wide R0 resection + multi-agent chemo (osteosarcoma regimens)
- Pelvic / axial disease: combined surgery + chemo + radiotherapy, often unresectable
- Unresectable / metastatic: palliative chemo, radiotherapy, surgical stabilisation
- Paget activity elsewhere: control with zoledronate or denosumab
Prognosis
- 5-year overall survival 5-25 percent - markedly worse than primary osteosarcoma
- Median survival under 12 months in metastatic disease
- Single biggest adverse factor: axial / pelvic location
- Lung metastases at presentation in 10-25 percent
Avoid the Traps
- Treating new pain in a Paget bone as Paget pain without imaging - the commonest error
- Biopsy through a tract that contaminates uninvolved compartments
- Internal fixation of a pathological fracture through a Paget bone before excluding malignancy
- Underestimating blood loss and technical difficulty in pagetoid bone
Evidence Base and Key Trials
Osteogenic sarcoma associated with Paget's disease of bone. A clinicopathologic study of 65 patients
- 65 of 1,177 osteogenic sarcoma patients at Memorial Hospital (5.5 PER CENT) arose in monostotic or polyostotic Paget disease; median age 64 years, range 39-82
- Osteosarcoma was the dominant subtype; in almost half the cases histology was fibrohistiocytomatous or osteoblastic
- Site distribution: PELVIS 34 per cent, HUMERUS 22 per cent, FEMUR 19 per cent, craniofacial 14 per cent
- Unrelenting pain and tender swelling were the presenting features in 85 PER CENT, with pathological fracture in 14 patients (22 per cent); two-thirds appeared as a LYTIC DESTRUCTIVE lesion radiographically
- THE SURVIVAL FIGURE IN ITS ORIGINAL FORM: despite radical amputations, ONLY THREE OF THE 65 PATIENTS SURVIVED BEYOND 5 YEARS - and the authors state the prognosis is significantly worse than de novo osteosarcoma IN PATIENTS OF COMPARABLE AGE, which is the fair comparison
Osteosarcoma in Paget's disease of bone
- Review of the molecular pathogenesis of Paget sarcoma
- SQSTM1/p62 mutations are common in familial and sporadic Paget disease
- p62 / sequestosome-1 activates NF-kB signalling, driving osteoclast activity
- p53 mutations are enriched in Paget sarcoma compared with Paget disease alone - a stepwise model: SQSTM1 driver, p53 second hit for malignant transformation
Paget's osteosarcoma and post-radiation osteosarcoma: secondary osteosarcoma at Middlemore Hospital, New Zealand
- Single-institution series of secondary osteosarcoma including Paget osteosarcoma and post-radiation osteosarcoma
- Paget osteosarcoma presents at significantly older age than primary osteosarcoma and is overwhelmingly axial/pelvic
- Wide surgical margins were achievable in appendicular cases but pelvic lesions had high positive-margin rates
- Outcome is markedly worse than primary osteosarcoma - confirming the high-grade biology of Paget sarcoma