Instability, meniscal preservation and growth-plate-respecting treatment
- A rapid effusion after a pivoting or landing injury is an intra-articular injury until proven otherwise.
- Younger children may sustain a tibial spine avulsion rather than a midsubstance ACL tear; X-rays are therefore not optional.
- MRI should be read for the ACL, tibial spine, meniscus, cartilage, bone bruising, collateral injury and physeal maturity.
- Repeated giving way increases the risk of secondary meniscal and chondral damage.
- Technique choice depends on growth remaining: non-operative surveillance, tibial spine fixation, physeal-sparing, all-epiphyseal, hybrid or carefully planned transphyseal reconstruction.
- “Lachman is usually more useful than forcing a pivot shift in an acutely painful child.
- “A locked knee after ACL injury is urgent because a bucket-handle meniscal tear or displaced tibial spine fragment may block extension.
- “Non-operative care is selected active surveillance with activity modification and rehabilitation, not permission to keep pivoting on an unstable knee.
- “Return to sport is based on motion, strength, neuromuscular control, hop testing, confidence and graded sport exposure, not a date alone.
Overview and Epidemiology
Paediatric ACL injury has become more common with year-round youth sport, early specialisation and high-volume pivoting activities. The injury may be a midsubstance ACL rupture, a partial tear, a tibial spine avulsion, or a combined injury with meniscal, chondral, collateral or osteochondral damage.
Two risks at once. The decision differs from an adult ACL tear because two risks have to be managed at the same time. Repeated giving way can damage the meniscus and cartilage in a knee that should last for decades, while adult-style reconstruction through open physes can rarely cause a limb-length difference or angular deformity. The key clinical issue is whether ongoing instability is converting a reconstructable ligament problem into a meniscal and chondral preservation problem.
Delay is the larger risk. Pooling 9 studies and 1353 patients, medial meniscal injury occurred in 26% of early-reconstruction knees against 47% of delayed ones (RR 0.49, 95% CI 0.36-0.65), roughly halved by operating earlier, with reduced chondral damage across multiple compartments as well. In a separate pooled analysis, delay beyond about 12 weeks was where the risk of meniscal injury, including irreparable tears, rose.
Growth disturbance is uncommon. Across 100 studies, limb-length discrepancy exceeding 10 mm occurred in 2.1%. Only about a third of those studies followed patients to skeletal maturity, and few assessed skeletal age or standing alignment consistently, so 2.1% is the best available estimate rather than a precise one.
The asymmetry is the argument. A one-in-fifty risk of a clinically meaningful leg-length difference does not justify accepting a doubling of meniscal injury in a child who keeps giving way. The growth figure is a reason to monitor growth after reconstruction, not a reason to relax about it.
Waiting is no longer the default. Current evidence no longer supports simply waiting until skeletal maturity for every child. Non-operative care can be appropriate for selected stable injuries and low-demand children, but an unstable pivoting athlete with recurrent giving way or a repairable meniscal tear needs timely specialist treatment. The aim is to avoid both physeal injury and instability-related meniscal damage, not to avoid surgery at any cost, and the plan must be individualised to the child, maturity, sport demands, instability episodes, family goals and local expertise.
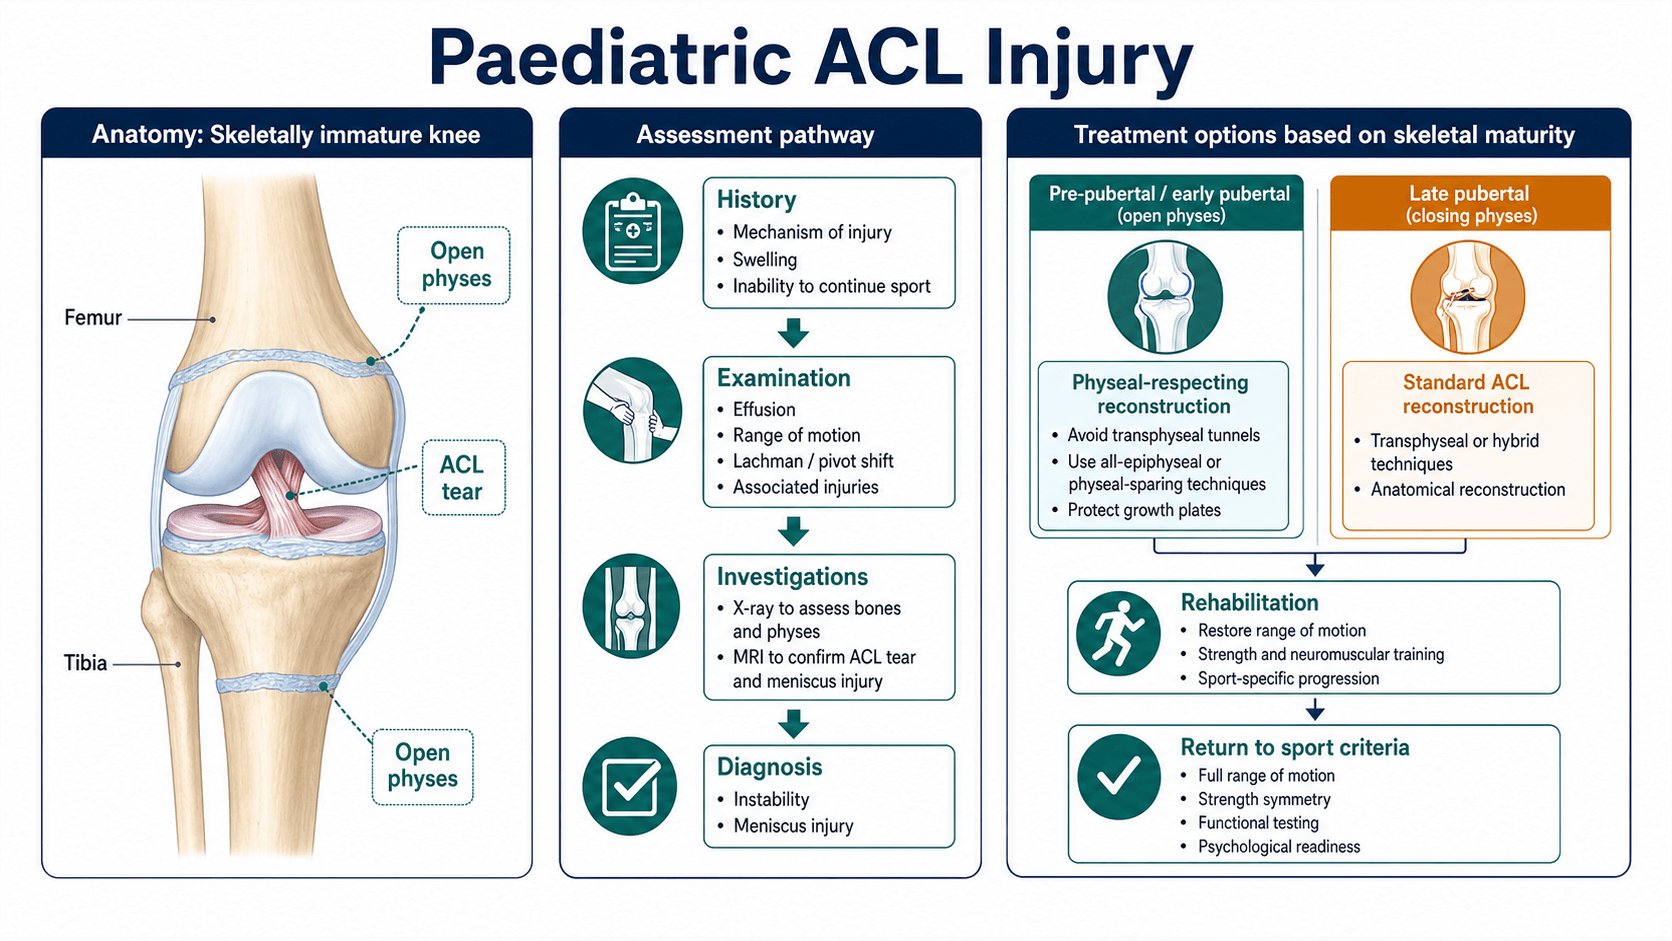
Pathophysiology and Anatomy
The ligament and the mechanism. The ACL restrains anterior tibial translation and contributes to rotational stability. It is vulnerable during non-contact pivoting, cutting, deceleration or landing, commonly with the knee near extension and loaded in valgus and rotation.
How the child differs. In younger children the ACL may avulse bone from the intercondylar eminence rather than tear in the ligament substance. The distal femoral and proximal tibial physes are open, and can be affected by tunnels, fixation, bone blocks, thermal damage or repeated drill passes.
Haemarthrosis. An acute haemarthrosis occurs because the ACL is intra-articular but extrasynovial and vascular.
Associated injury. The pivot-shift mechanism may also injure the meniscus, articular cartilage and subchondral bone. Lateral meniscal injury and bone bruising are common in acute pivot injuries; medial meniscal tears and chondral injury become increasingly important with recurrent instability and delay.
The paediatric meniscus. The paediatric meniscus is highly vascular, and that vascularity supports repair potential in the growing knee.
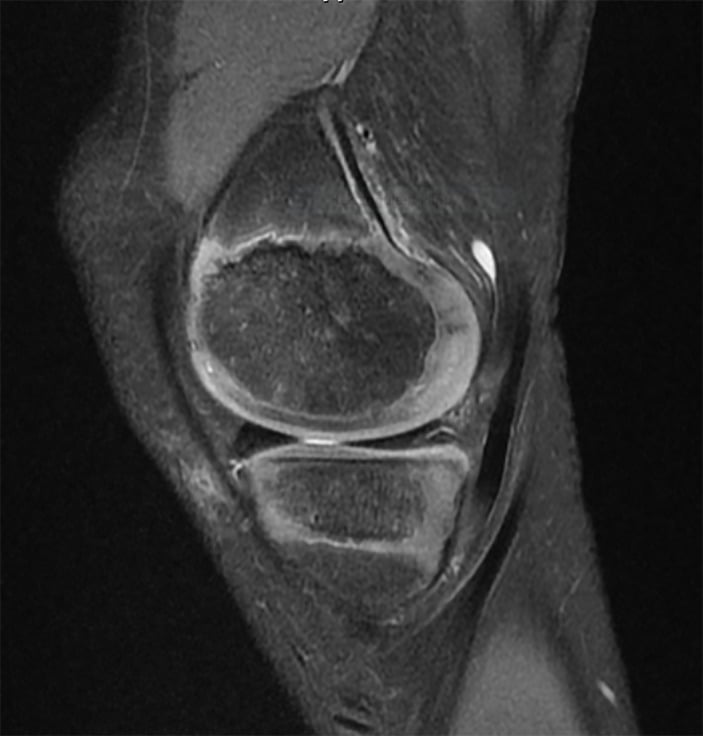
Classification
Classification should describe the injury pattern, bony attachment, associated pathology and skeletal maturity.
- Complete midsubstance tear - functionally unstable in many active children and adolescents.
- Partial tear - may be stable or unstable. Lachman and pivot, symptoms and sport demand decide treatment rather than the MRI wording alone, and a partial tear that gives way is not benign.
- Tibial spine avulsion - the bony ACL-equivalent injury, in which the ACL attachment avulses from the intercondylar eminence.
- Combined injury - ACL plus meniscal, chondral, collateral, posterolateral, osteochondral or patellar instability pathology. The associated pathology often changes the urgency and the operative plan.
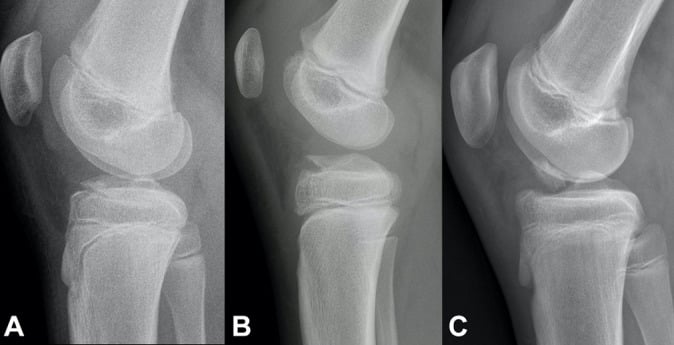
Clinical Presentation
History. The classic presentation is a pivoting or landing injury with a pop, immediate pain, rapid swelling and inability to continue sport. Some children describe instability immediately; others mainly describe swelling, apprehension and inability to fully trust the knee. Ask specifically about:
- The mechanism: pivot, sidestep, deceleration, landing, tackle, hyperextension or direct contact
- Pop, immediate pain and rapid effusion
- Ability to continue sport and to weight bear
- Giving way, recurrent instability or fear of pivoting
- Locking, catching or inability to fully extend
- Previous patellar dislocation, prior knee injury and contralateral ACL injury
- Sport level, season timing, position, training volume and willingness to modify activity
- Growth history, pubertal stage and menarche history where clinically appropriate
Rapid swelling after pivoting is an intra-articular injury until proven otherwise. A child with a pop, rapid effusion, giving way or loss of extension after a pivoting injury needs X-rays for tibial spine avulsion and MRI assessment for ACL, meniscus and cartilage injury. Missing the diagnosis delays activity restriction and increases the risk of secondary injury.
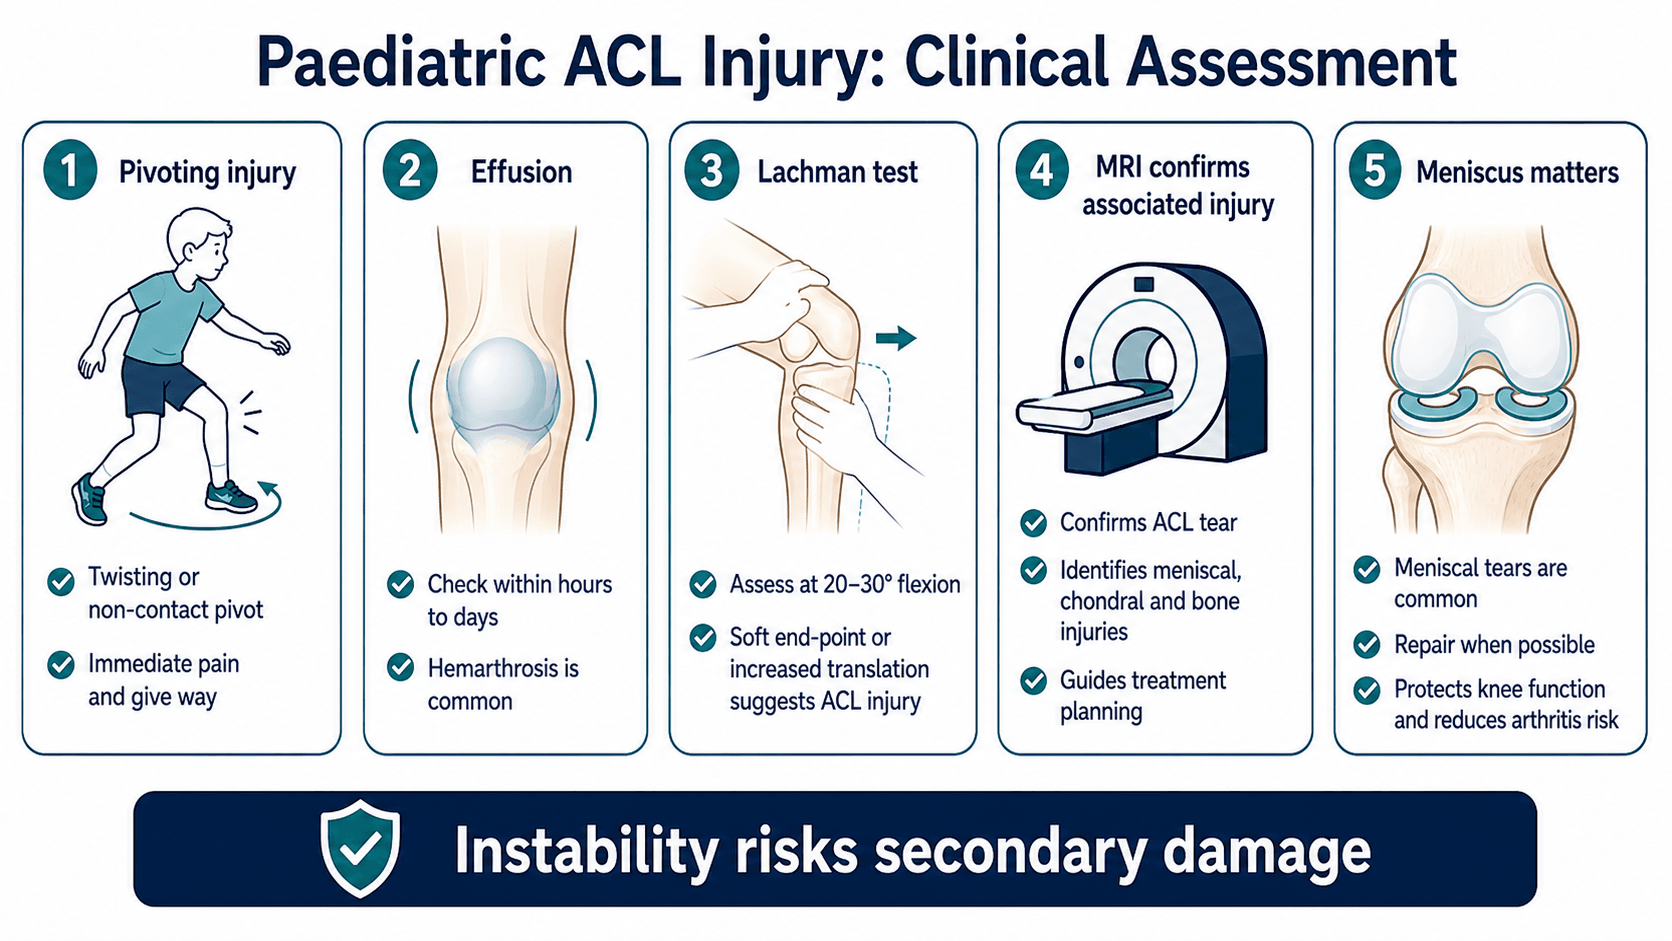
Examination. The acute knee may be painful and guarded. Start with effusion, range of motion and the ability to achieve full extension, comparing with the opposite knee. Then assess:
- Effusion or tense haemarthrosis
- Extension loss or a true mechanical block
- Lachman test and endpoint, when tolerated
- Joint-line tenderness, McMurray symptoms and meniscal locking
- Collateral ligaments and posterolateral corner in higher-energy injuries
- Patellar apprehension and osteochondral injury clues
- Distal neurovascular status
- Limb alignment, generalised laxity, gait and functional squat or landing control when appropriate
Test the pivot shift later, under anaesthetic, or when pain settles; do not force it in an acutely painful child. A dramatic pivot shift is not required to diagnose a clinically suspicious paediatric ACL injury, and in the acute setting effusion, extension loss, Lachman, X-ray and MRI are usually more useful.
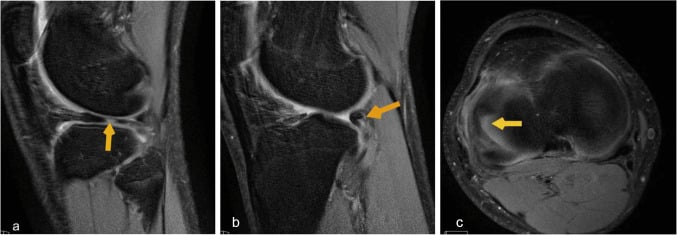
Investigations
Radiographs first. Obtain AP and lateral knee radiographs, adding notch, tunnel or sunrise views when clinically relevant. In a child the films are taken to identify tibial spine avulsion, osteochondral fracture, Segond-type injury, patellar dislocation sequelae or physeal injury, not just to exclude a fracture. MRI is essential, but X-rays are the first step because tibial spine avulsion and osteochondral fracture change management.
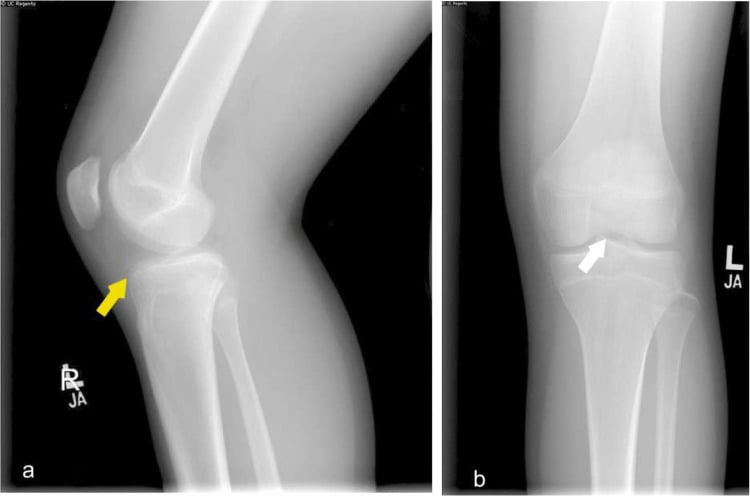
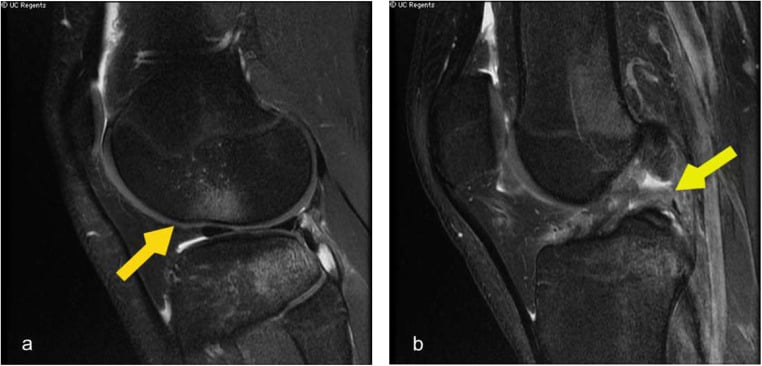
MRI. MRI confirms the ACL pattern and has to be reviewed actively, reporting the ligament alongside everything around it:
- ACL continuity, fibre orientation and stump position
- Tibial spine fragment or bony avulsion
- Meniscal tear, bucket-handle tear and ramp lesion, with tear morphology, vascular zone and repairability
- Chondral or osteochondral injury
- Bone bruising pattern
- Collateral ligament or posterolateral injury
- Physeal status and safe tunnel anatomy
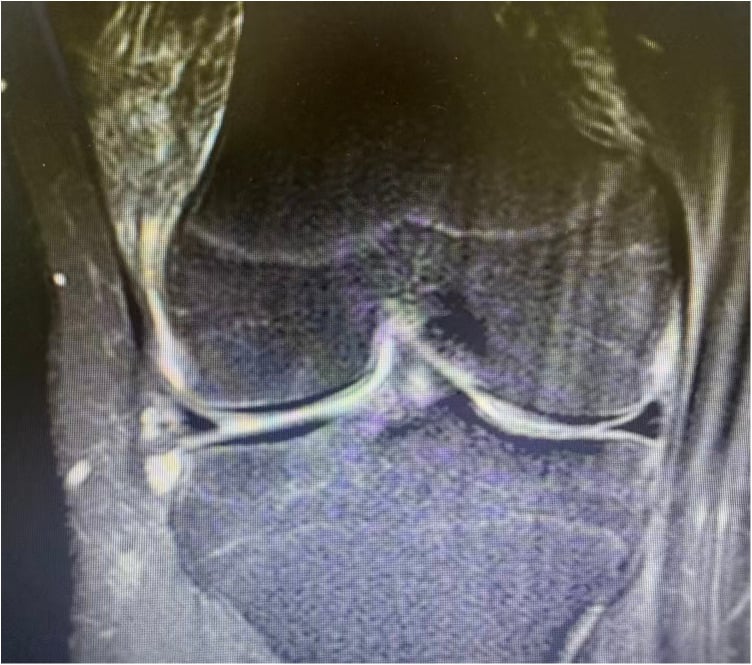
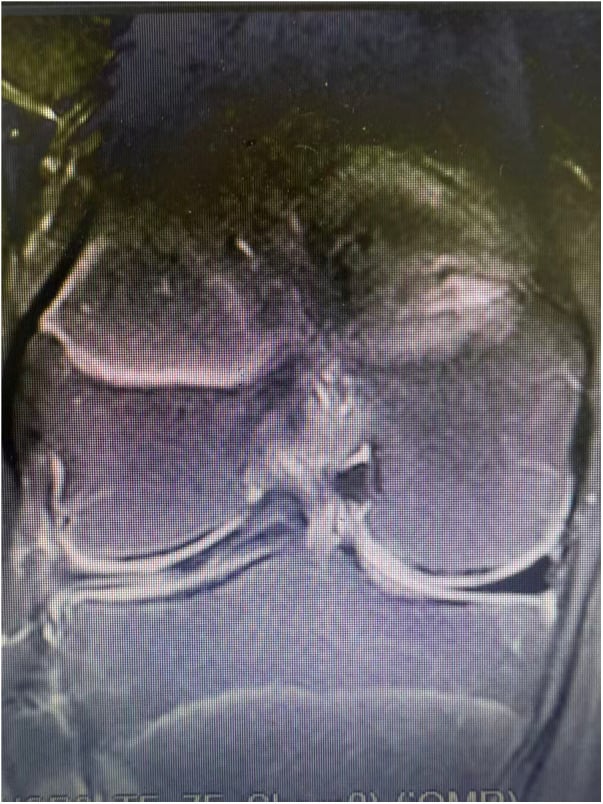
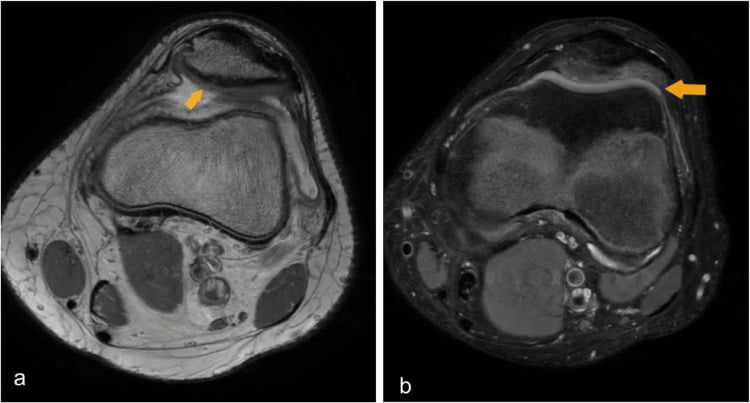
Maturity assessment. Skeletal maturity assessment is required when the reconstruction technique depends on growth remaining, and chronological age alone is insufficient. Use a combination of growth history, growth velocity, pubertal (Tanner) stage, menarche history, knee radiographs, hand bone age, standing hip-to-ankle radiographs or local maturity protocols where appropriate.
The practical toolkit has three parts:
- Tanner stage 1-5 (sexual maturity): 1-2 prepubescent, 3 pubescent, 4-5 post-pubescent
- Bone age by the Greulich-Pyle hand-wrist atlas or the Sanders hand skeletal-maturity stages
- Growth history and menarche: in girls, growth largely completes about 2 years after menarche
The unifying concept is peak height velocity (PHV), the growth spurt, at about 11.5-12 years in girls and 13.5-14 years in boys. Around and before PHV the physes are most active and most growth remains, so growth-disturbance risk is highest and physeal-sparing is favoured. After PHV, with Tanner 4-5 and closing physes, most growth is complete and carefully planned transphyseal reconstruction may be appropriate. When the decision is close, estimate growth remaining by multiplier methods or standing alignment.
Differential Diagnosis
The swollen paediatric sports knee has important mimics and associated injuries:
- Tibial spine avulsion
- Patellar dislocation with osteochondral fracture
- Bucket-handle meniscal tear
- Isolated meniscal tear
- Collateral ligament injury
- Posterolateral corner injury after a high-energy mechanism
- Distal femoral or proximal tibial physeal fracture
- Osteochondritis dissecans presenting after a minor episode
- Acute haemarthrosis from a bleeding disorder in the right clinical context
Management
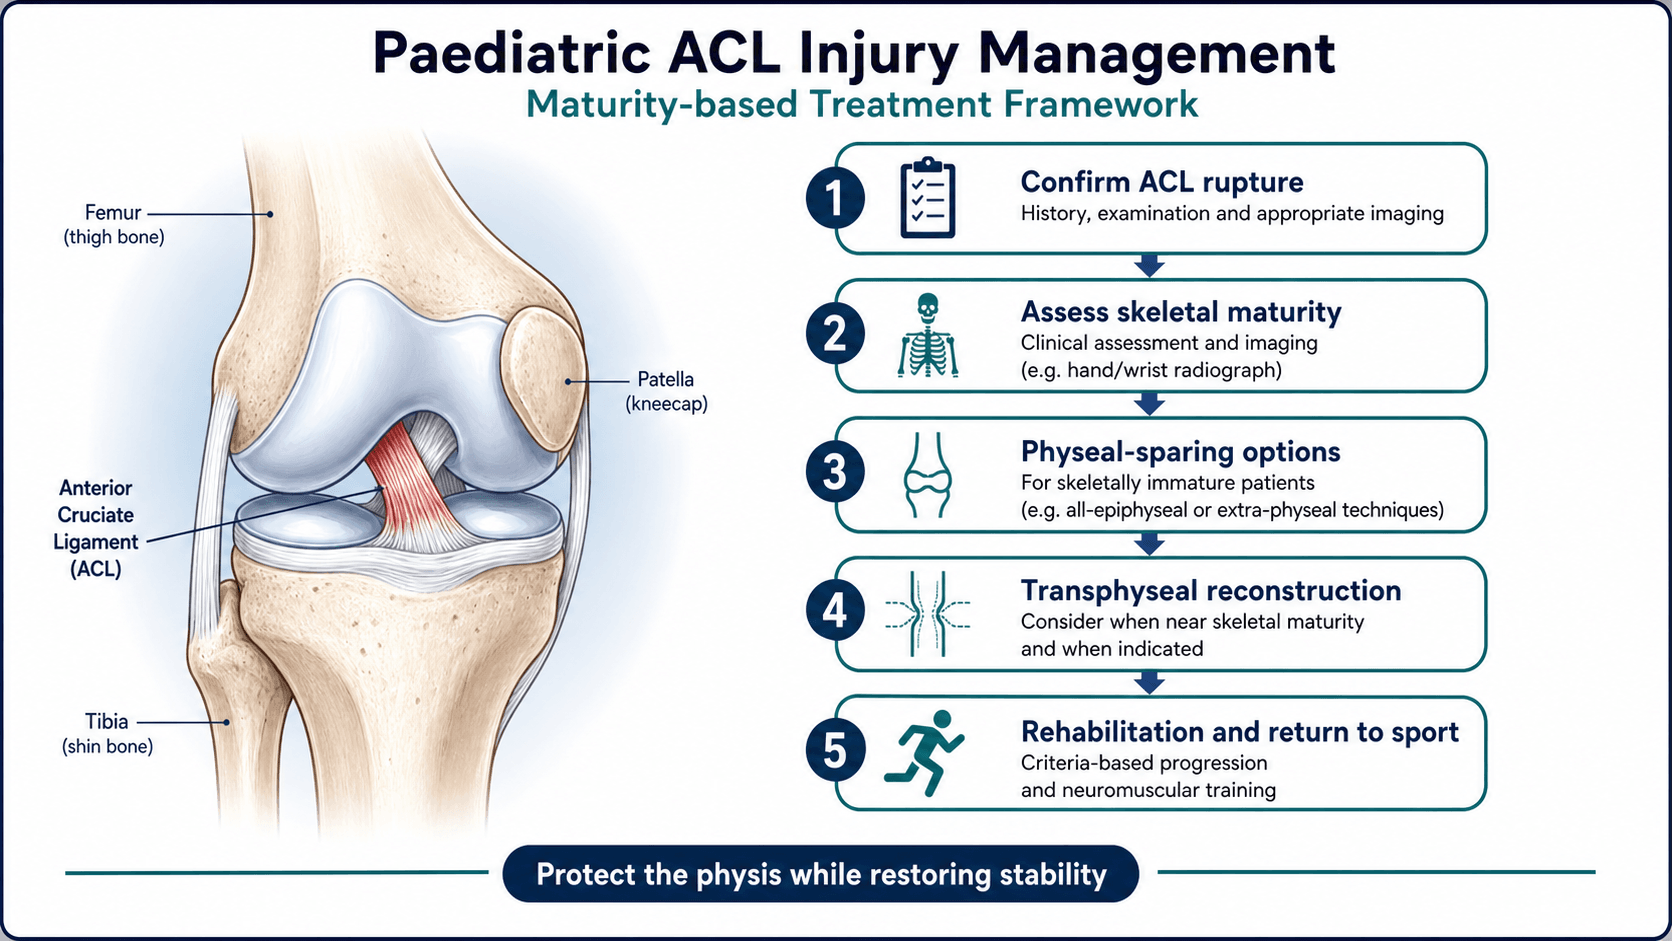
The sequence. Six questions, asked in order, run from recognition to clearance:
- Clinical question
- Is this an intra-articular knee injury?
- Decision impact
- Rapid effusion after pivoting triggers ACL, meniscus and tibial spine workup
- Clinical question
- Is there a tibial spine fracture or osteochondral injury?
- Decision impact
- X-ray changes urgency and treatment
- Clinical question
- What does MRI show beyond the ACL?
- Decision impact
- Meniscus, cartilage, ramp lesion and bone bruise affect the plan
- Clinical question
- How much growth remains?
- Decision impact
- Guides physeal-sparing, hybrid or transphyseal reconstruction
- Clinical question
- Is the knee stable enough for selected rehabilitation?
- Decision impact
- Prevents repeated instability while avoiding unnecessary physeal risk
- Clinical question
- Has the child passed functional, psychological and sport-specific criteria?
- Decision impact
- Reduces graft and contralateral injury risk
Acute care aims to control swelling, restore extension and define the injury.
- Analgesia, ice, compression and protected weight bearing
- Early restoration of full extension as pain allows
- No premature return to pivoting or cutting
- Urgent review for a locked knee, displaced tibial spine avulsion, osteochondral fracture or suspected bucket-handle meniscus
Prolonged immobilisation is avoided unless a fracture pattern requires it, because stiffness and quadriceps shutdown complicate recovery.
- Reasonable direction
- Structured rehabilitation, activity modification and close review
- Avoid
- Unsupervised return to pivoting sport
- Reasonable direction
- Maturity-specific ACL reconstruction
- Avoid
- Repeated giving way while waiting for maturity
- Reasonable direction
- Arthroscopic reduction and fixation when extension or stability is compromised
- Avoid
- Missing interposed meniscus or accepting residual extension block
- Reasonable direction
- Physeal-sparing or all-epiphyseal strategy when reconstruction is needed
- Avoid
- Adult-style tunnels and fixation without maturity assessment
- Reasonable direction
- Carefully planned transphyseal reconstruction may be appropriate
- Avoid
- Overstating physeal risk when instability is damaging the meniscus
- Reasonable direction
- Stabilise the knee and repair the meniscus where possible
- Avoid
- Partial meniscectomy by default
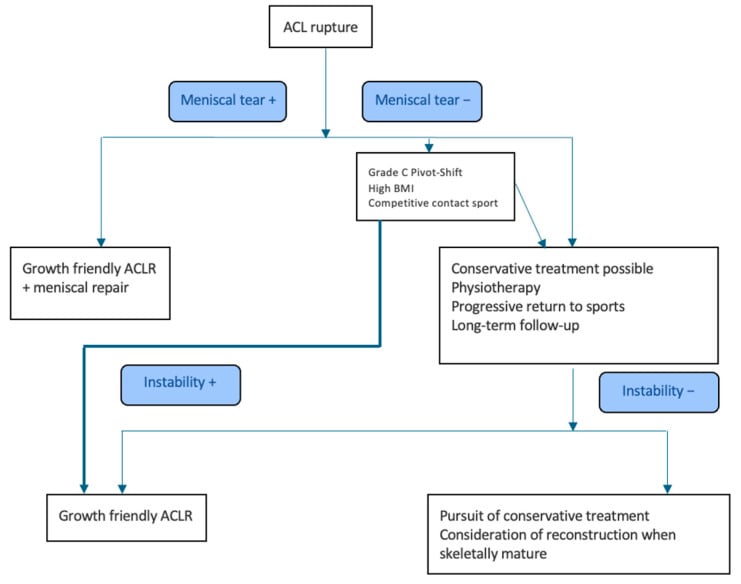
Graft and Technique Principles
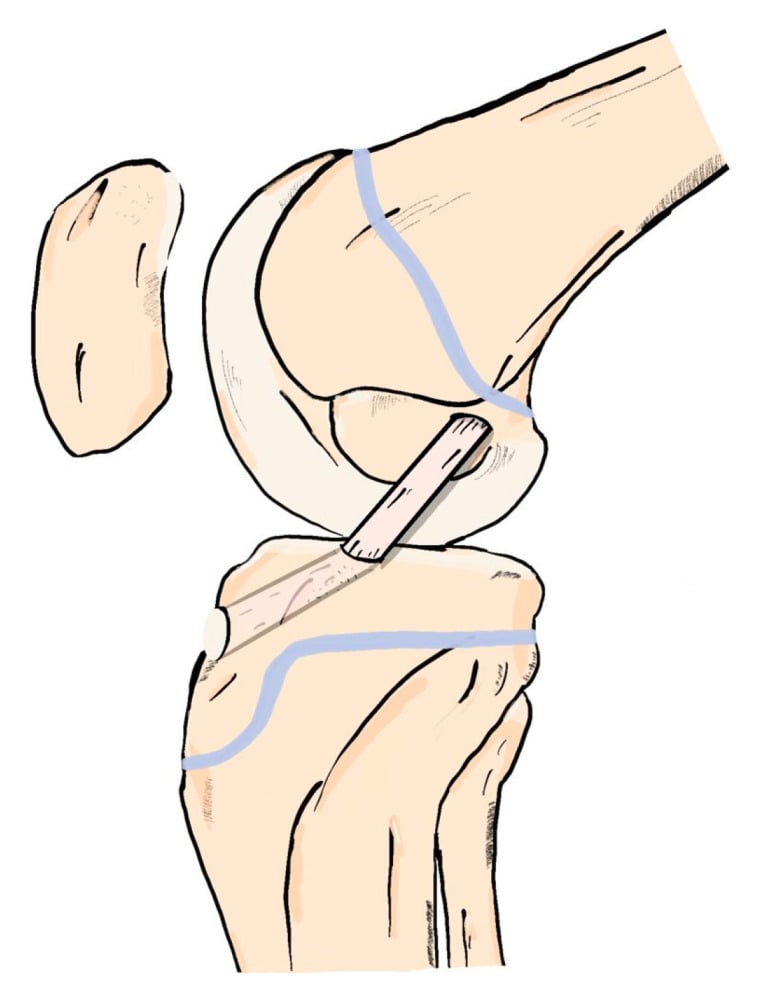
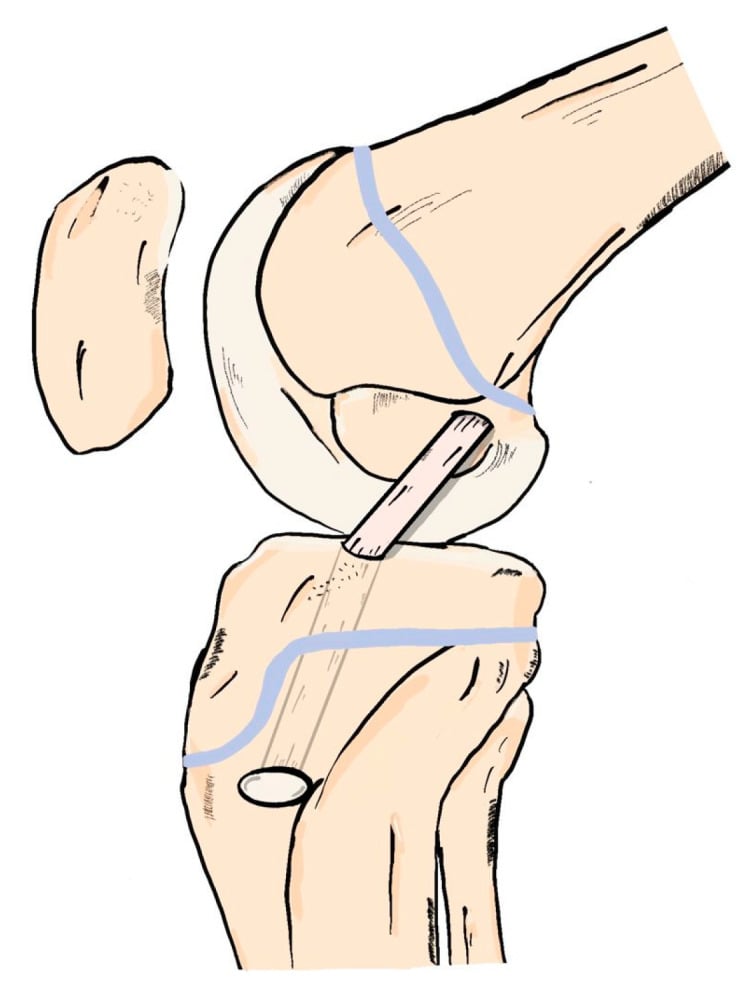
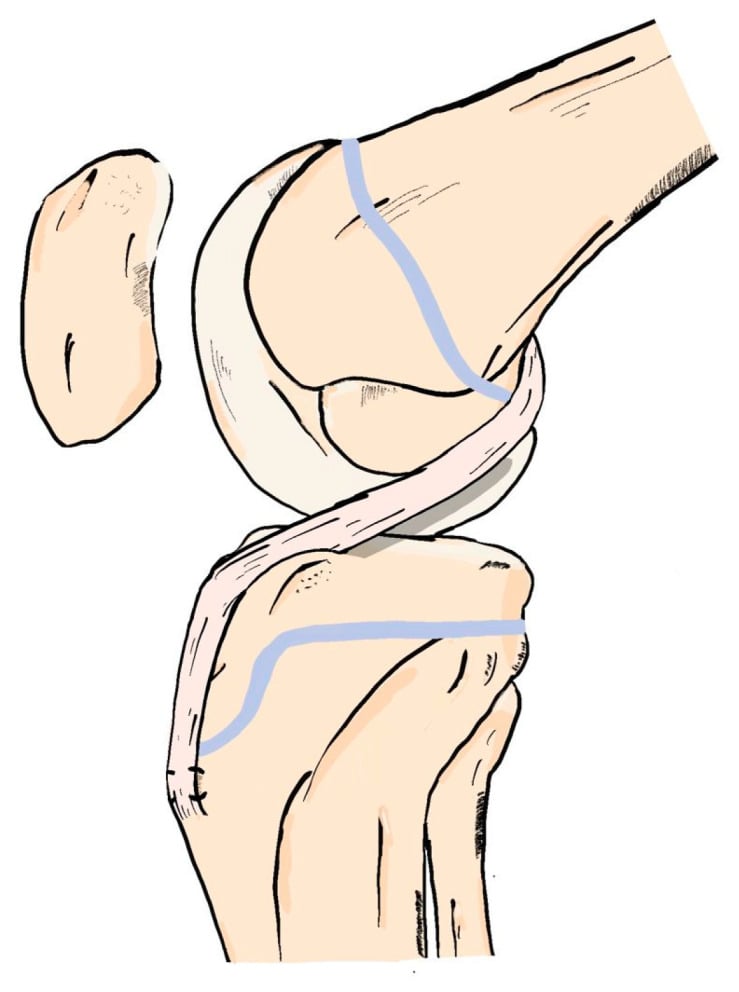
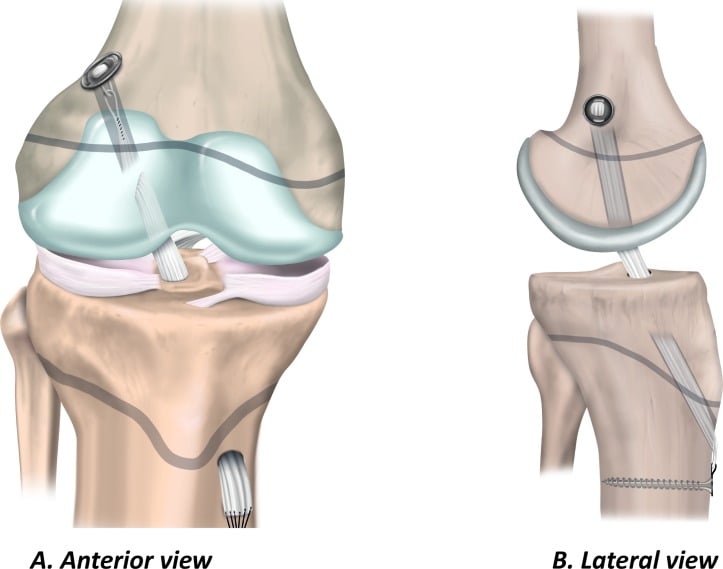
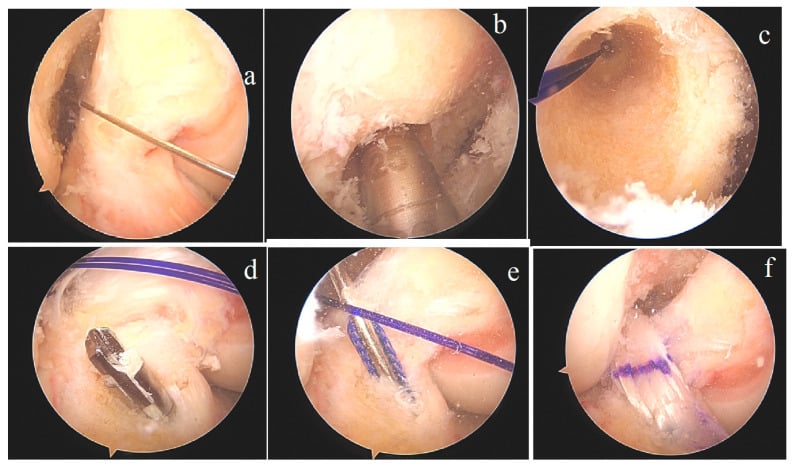
Choosing graft and technique. The best graft is not the same for every child. Graft and technique are chosen according to skeletal maturity, sport, tunnel plan, graft size, donor-site morbidity, revision risk and surgeon experience.
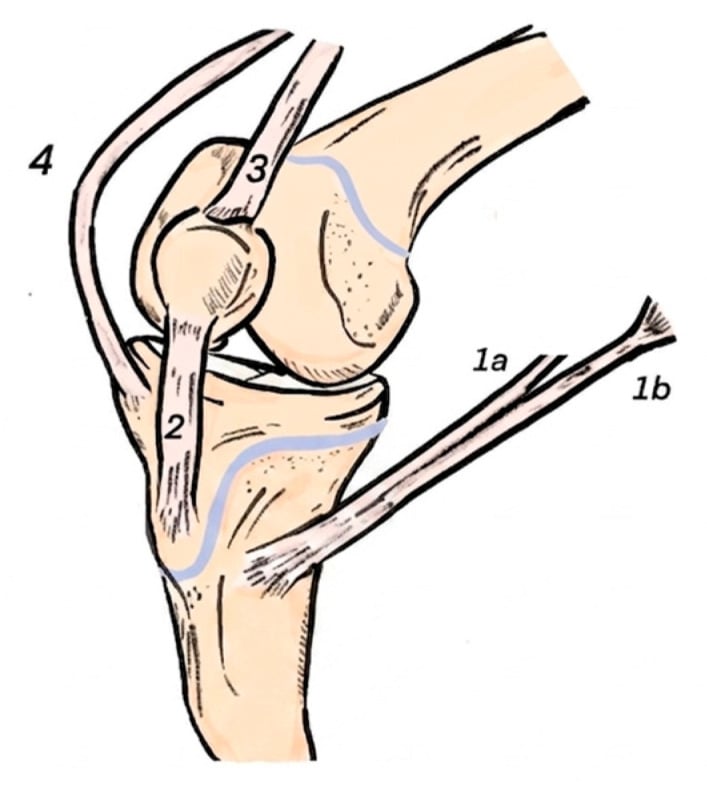
Named techniques. The maturity stages map onto specific named operations that examiners expect you to know. Hybrid techniques may be used when one side is more at risk than the other.
- Maturity (typical)
- Prepubescent (Tanner 1-2)
- Principle
- Iliotibial-band autograft routed over-the-top of the lateral femoral condyle and under the intermeniscal ligament - NO tunnels across either physis (true physeal-sparing)
- Maturity (typical)
- Pre/early pubescent, substantial growth remaining
- Principle
- Femoral AND tibial tunnels confined entirely within the epiphysis, sparing both physes
- Maturity (typical)
- Mid-pubertal (intermediate)
- Principle
- One side crosses the physis (e.g. vertical transtibial tunnel) with an epiphyseal or over-the-top femoral side, using soft-tissue graft only across the physis
- Maturity (typical)
- Near maturity / closing physes
- Principle
- Standard anatomical vertical central tunnels with soft-tissue graft and fixation away from the physis (no bone block across an open physis)
- Maturity (typical)
- Skeletally mature
- Principle
- Adult principles, with adolescent reinjury-prevention rehabilitation
Protecting the physis. Physeal risk is reduced by avoiding large peripheral tunnels, avoiding hardware or bone blocks crossing the growth plate, minimising repeated drilling, keeping tunnels as central and vertical as is compatible with safe reconstruction, and following growth clinically and radiographically when risk exists. Near maturity, transphyseal reconstruction may be suitable with small, central, steep tunnels and soft-tissue graft fixation away from the physis. Avoid bone plugs or fixation crossing an open physis unless maturity and technique make it safe.
- Potential advantages
- Commonly used, soft-tissue graft, avoids bone plug across physis
- Important cautions
- Small graft diameter and hamstring weakness may matter in small children
- Potential advantages
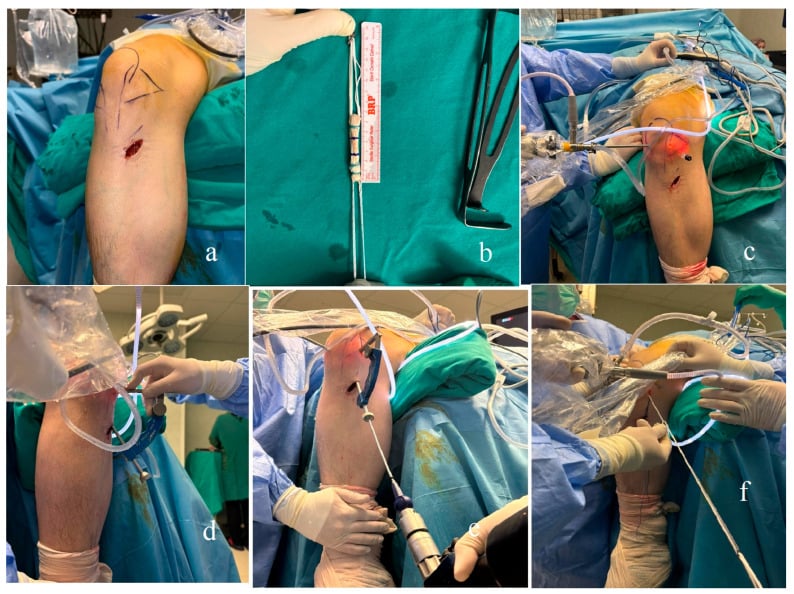
- In a paediatric meta-analysis (12 studies, 659 patients) graft rupture was 3.5% versus 12.4% for hamstring - roughly a quarter of the failure rate - with higher Lysholm scores and comparable contralateral-injury and growth-disturbance rates
- Important cautions
- Technique, graft thickness and donor-site morbidity require experience. Use the SOFT-TISSUE quadriceps graft over open physes: rupture rates did not differ with or without a bone block, so the bone block adds physeal risk for no measured gain
- Potential advantages
- Strong adult graft with bone-to-bone healing
- Important cautions
- Generally avoided with substantial growth remaining because bone blocks can injure physes
- Potential advantages
- No donor-site morbidity
- Important cautions
- Generally avoided in young active athletes because failure risk is higher
- Potential advantages
- May reduce rotational instability in very high-risk selected patients
- Important cautions
- Indications in skeletally immature patients remain selective and evolving
Complications and Follow-up
The early complications:
- Missed tibial spine avulsion
- Locked knee from a bucket-handle meniscus or displaced fragment
- Persistent extension loss
- Arthrofibrosis
- Recurrent giving way before definitive treatment
- Missed collateral, posterolateral or osteochondral injury
The late complications:
- Secondary meniscal tear after recurrent instability
- Chondral injury and early degenerative change
- Graft rupture
- Contralateral ACL tear
- Growth disturbance after physeal injury
- Limb-length difference or angular deformity
- Persistent quadriceps weakness
- Fear of return to sport
Follow-up should monitor symptoms, effusion, extension, graft stability, meniscal symptoms, strength, movement quality, sport exposure and growth when physes remain open.
Rehabilitation and Return to Sport
Rehabilitation is part of the treatment decision. A technically good reconstruction can fail if strength, landing mechanics and confidence are not restored.
Early phase. Control pain and effusion, restore full extension, recover quadriceps activation and normalise gait, protecting any meniscal repair or tibial spine fixation restrictions where relevant.
Intermediate phase. Restore progressive flexion and functional range, and build quadriceps, hamstring, hip and trunk strength. Improve neuromuscular control and correct dynamic valgus and poor landing mechanics, maintaining cardiovascular conditioning without pivoting exposure.
Return-to-sport criteria. Return to pivoting sport should include:
- No effusion or pain response to training
- Full extension and functional flexion
- Quadriceps and hamstring strength symmetry
- Hop testing and side-to-side performance
- Quality of landing, cutting and deceleration mechanics
- Psychological readiness and confidence
- Sport-specific graded exposure
- An ongoing injury-prevention programme
A time point is not a clearance test. A child who swells, limps, lands poorly, lacks strength or lacks confidence is not ready for unrestricted pivoting sport.
Which figures to quote. The widely quoted pooled return-to-sport figures from the largest review (105 studies, 8294 patients) are 44.0% after conservative management and 92.6% after physeal-sparing reconstruction, and it is tempting to lead with them. Their confidence intervals are 1.8-92.7% and 73.2-100%: they overlap across almost the whole range, which means the included studies disagreed so completely that the apparent gap is not established.
Lead with the precise ones. From the same review, instability was 35.9-100% without reconstruction and 0-7.4% with it; pair that with the halving of medial meniscal injury after early reconstruction set out in the Overview. A family can act on those. Quoting a number whose interval starts at 1.8% as though it were 44% is the kind of precision a parent will remember and a colleague will check.
Secondary injury falls unevenly. Across 24 studies and 1254 skeletally immature patients, graft failure was 8.3% with no significant difference between girls and boys, but contralateral ACL injury occurred in 22.5% of girls against 8.7% of boys (odds ratio 3.0). One in three skeletally immature girls sustained either a graft failure or a tear of the other knee, so in girls the uninjured knee is the higher-risk knee. The prevention programme therefore becomes part of the treatment rather than an optional extra, and the other knee must be discussed at consent along with the reconstructed one.
Maturity does not protect. Overall secondary injury was 24%, almost identical to published rates in skeletally mature patients under 25, and the authors conclude that skeletal maturity alone does not appear to determine this risk. Do not reassure a family that a child's knee is more forgiving: the driver is activity exposure and neuromuscular control, not open physes. The counselling line worth rehearsing is that the operation addresses this knee, while the landing-mechanics and neuromuscular programme is what protects both.
Guidelines, Registries & Global Practice
Paediatric ACL injury is a global problem with consistent biology but variable access to MRI, paediatric sports surgery and supervised rehabilitation. The evidence base is dominated by consensus statements and observational cohorts rather than randomised trials, so guidance converges on principles rather than rigid algorithms.
Global epidemiology
- Incidence is rising in children and adolescents worldwide, driven by year-round youth sport, early single-sport specialisation and increased recognition on MRI.
- Female adolescents carry a disproportionately high risk of both index and contralateral ACL injury, particularly around peak height velocity.
- In younger (prepubescent) children the bony tibial-spine (intercondylar eminence) avulsion is relatively more common than midsubstance rupture; the proportion of midsubstance tears rises through adolescence.
- Secondary meniscal and chondral damage accumulates with delay and recurrent instability, making time-to-stability a key modifiable outcome.
Society guidance side by side
- Emphasis
- Shared decision-making, prevention, criterion-based return to sport
- Practical position
- Individualise by skeletal maturity, instability and sport; avoid a single age cut-off
- Emphasis
- Surgical stabilisation for the unstable pivoting knee, meniscal preservation
- Practical position
- Favour timely reconstruction to protect the meniscus; physeal-respecting technique by maturity
- Emphasis
- MRI access, specialist paediatric referral, structured rehabilitation
- Practical position
- Refer the unstable immature knee to paediatric/sports specialists rather than default watchful waiting
- Emphasis
- Technique by growth remaining, growth surveillance
- Practical position
- Physeal-sparing or all-epiphyseal for substantial growth remaining; transphyseal near maturity
- Emphasis
- Injury prevention (neuromuscular training), graft and tunnel safety
- Practical position
- Embed prevention programs and follow growth where physes are open
Where societies differ, the difference is one of emphasis and resource assumption rather than contradiction: all accept that an unstable, meniscus-threatening knee should be stabilised, and all accept that growth must be respected.
Registry and surveillance notes
- National ligament/ACL registries (for example the Scandinavian knee ligament registries and similar national datasets) capture mostly skeletally mature patients, so dedicated paediatric data come largely from multicentre study groups such as PLUTO and institutional series.
- Registry-style signals that are clinically robust: young age and return to pivoting sport are strong predictors of graft rupture and contralateral injury; female sex amplifies contralateral risk.
- Implant/graft survivorship data in children remain limited; this is an explicit area where pooled prospective cohorts are still maturing.
High- versus limited-resource practice
- Well-resourced settings: prompt MRI, paediatric sports surgeons, formal maturity assessment (bone age, standing alignment), graft choice flexibility and criterion-based return-to-sport testing.
- Limited-resource settings: diagnosis may rely more on clinical examination and plain radiographs; MRI and physeal-sparing expertise may be less available, increasing the relative role of structured rehabilitation and activity modification while access to specialist reconstruction is arranged.
- Across all settings the universal priorities are the same: recognise the intra-articular injury, exclude a tibial-spine avulsion on X-ray, protect the meniscus, respect the physis and clear sport on criteria rather than the calendar.
Controversies and Areas of Uncertainty
- Non-operative versus early reconstruction: consistent observational evidence links delay and persistent instability to meniscal and chondral damage, but high-quality randomised data are scarce, so selection (truly stable, low-demand, adherent) remains a judgement call.
- Type-II tibial spine fractures: optimal management is still debated; reduction and fixation are favoured when there is an extension block, irreducible displacement or residual laxity.
- Best graft in the small child: quadriceps tendon shows promising lower rupture rates versus hamstring in pooled paediatric data, but graft sizing, donor-site morbidity and surgeon experience temper a universal recommendation.
- Lateral extra-articular augmentation: may reduce rotational failure in very high-risk patients, but indications in skeletally immature knees remain selective and evolving.
- Maturity assessment method: no single tool is definitive; bone age, Tanner stage, growth velocity and alignment imaging are combined when the decision is close.
- Return-to-sport thresholds: criterion-based testing is endorsed, but the exact battery, pass thresholds and timing that minimise reinjury are not standardised.
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“A 13-year-old has a pop, rapid swelling and instability after pivoting during sport. How do you assess and manage the injury?”
“Why does skeletal maturity matter when choosing ACL reconstruction technique in a child?”
“A 9-year-old has a knee locked in flexion after a fall from a bicycle. Lateral radiograph shows a displaced anterior intercondylar eminence fragment. How do you manage this?”
Recognise
- Pivot or landing
- Pop
- Rapid effusion
- Giving way
- Lachman
Image
- X-ray first
- Tibial spine
- MRI ACL
- Meniscus and cartilage
- Physes
Treat
- Restore extension
- Fix displaced tibial spine
- Selected rehabilitation
- Maturity-specific reconstruction
- Meniscal repair when possible
Follow
- Instability
- Extension
- Meniscus symptoms
- Growth disturbance
- Return-to-sport criteria
“Think swollen pivot knee, X-ray for tibial spine, MRI for full injury pattern, maturity-based treatment, meniscal preservation and criterion-based return to sport.”
Evidence Base
Paediatric ACL consensus
- Paediatric ACL care requires attention to prevention, diagnosis, treatment, rehabilitation and shared decision-making.
- Management should consider skeletal maturity, instability, sport demands and associated injuries.
- Return to sport should be criterion-based and prevention-focused.
Early versus delayed treatment
- 30 studies, 50 cohorts, 1,176 patients aged 19 or under
- Delay beyond 12 weeks: ANY meniscal tear odds ratio 0.23 favouring early surgery (p = 0.006), and IRREPARABLE meniscal tear odds ratio 0.31 (p = 0.001) - the tear is not just commoner after delay, it is likelier to be unsalvageable
- STABILITY WAS NOT THE DIFFERENCE: KT-1000 side-to-side laxity did not favour either timing, whether compared as mean difference (p = 0.413) or as the proportion exceeding 3 mm (p = 0.181). Return to pre-injury competition was 57 to 100 per cent in BOTH operative groups
- Non-operative management performed badly and inconsistently: residual instability in 20 to 100 per cent, and return to pre-injury sport in only 6 to 50 per cent
- So the argument for early surgery is meniscal and chondral preservation, NOT better final stability - a distinction that matters when a family asks what the operation buys
Selected References
-
Ardern CL, Ekas GR, Grindem H, et al. 2018 International Olympic Committee consensus statement on prevention, diagnosis and management of paediatric anterior cruciate ligament injuries. Br J Sports Med. 2018;52:422-438. PMID: 29478021
-
James EW, Dawkins BJ, Schachne JM, et al. Early operative versus delayed operative versus nonoperative treatment of pediatric and adolescent anterior cruciate ligament injuries: a systematic review and meta-analysis. Am J Sports Med. 2021;49:4008-4017. PMID: 33720764
-
Kay J, Memon M, Shah A, et al. Earlier anterior cruciate ligament reconstruction is associated with decreased risk of medial meniscal and articular cartilage damage in children and adolescents. Knee Surg Sports Traumatol Arthrosc. 2018;26:3738-3753. PMID: 29876862
-
Pierce TP, Issa K, Festa A, Scillia AJ, McInerney VK. Pediatric anterior cruciate ligament reconstruction: a systematic review of transphyseal versus physeal-sparing techniques. Am J Sports Med. 2017;45:488-494. PMID: 27045088
-
Fury MS, Paschos NK, Fabricant PD, et al. Assessment of skeletal maturity and postoperative growth disturbance after ACL reconstruction in skeletally immature patients: a systematic review. Am J Sports Med. 2022;50:1430-1441. PMID: 33984243
-
Jin H, Tahir N, Jiang S, et al. Management of anterior cruciate ligament injuries in children and adolescents: a systematic review. Sports Med Open. 2025;11(1):40. PMID: 40263204
-
Zacharias AJ, Whitaker JR, Collofello BS, et al. Secondary injuries after pediatric anterior cruciate ligament reconstruction: a systematic review with quantitative analysis. Am J Sports Med. 2021;49:1086-1093. PMID: 32809855
-
Rangasamy K, Baburaj V, Gopinathan NR, Dhillon MS, Parikh SN. Quadriceps tendon autograft is promising with lower graft rupture rates and better functional Lysholm scores than hamstring tendon autograft in pediatric ACL reconstruction. A systematic review and meta-analysis. J Orthop. 2024;49:156-166. PMID: 38223427
-
Yellin JL, Fabricant PD, Gornitzky A, et al. Rehabilitation following anterior cruciate ligament tears in children: a systematic review. JBJS Rev. 2016;4:e4. PMID: 27490007
-
Elnewishy A, El Menawy Z, Zahed M, et al. Suture fixation versus screw fixation in pediatric tibial eminence fractures: a systematic review and meta-analysis. Cureus. 2025. PMID: 41487842