Rare injury, high complication burden, urgent anatomical reduction
- Delbet type I transphyseal injuries have the greatest femoral-head perfusion concern.
- Displacement, intracapsular pressure, fracture location and reduction quality drive complication risk.
- A displaced intracapsular femoral neck fracture in a child needs urgent senior paediatric orthopaedic planning.
- Closed reduction is acceptable only if anatomical; open reduction is safer than accepting varus or rotational malreduction.
- Follow-up must continue after union because avascular necrosis and growth disturbance may declare late.
- “A painful log roll after high-energy trauma is enough to demand hip-specific imaging.
- “Do not force frog lateral positioning in a painful or unstable fracture; use a safe lateral view.
- “Implant choice matters, but the principles are more important: anatomical reduction, stable fixation and no joint penetration.
- “Coxa vara is often a sign of malreduction, fixation failure, non-union or growth disturbance rather than a minor radiographic detail.
Overview
Paediatric femoral neck fractures are rare compared with adult hip fractures, but they are treated with a different level of urgency because the biology is different. The child has an open physis, a cartilage-rich proximal femur, a vulnerable femoral-head blood supply and many years of growth remaining.
What is at stake. A well-aligned fracture can heal quickly. A poorly reduced or vascularly compromised fracture can leave the child with avascular necrosis, coxa vara, non-union, limb-length difference and early hip degeneration.
Do not reassure the family simply because the fracture looks small. The femoral head may be threatened by vascular disruption, intracapsular pressure and growth-plate injury even when the initial radiograph does not look dramatic.
Mechanism. Most injuries follow high-energy trauma: road trauma, fall from height, sports collision or crush injury. A low-energy femoral neck fracture is not routine trauma until proven otherwise. It should trigger consideration of bone cyst, tumour-like lesion, metabolic bone disease, endocrine disease, infection, non-accidental injury in the right age group, or medication-related bone fragility.
The clinical sequence. In practice the steps run:
- Identify the fracture and associated injuries
- Classify with Delbet type and displacement
- Decide whether the fracture is intracapsular and whether decompression is relevant
- Restore an anatomical reduction
- Stabilise the fracture without violating the joint
- Protect weight bearing
- Follow for union, femoral-head shape, neck-shaft angle and growth
Pathophysiology
The proximal femur in a child is not a smaller adult hip. The proximal femoral physis contributes to growth, the greater trochanter has its own apophysis, and the femoral head relies heavily on vessels that run near the femoral neck.
The femoral head and its vessels. The head is an articular segment at risk of avascular necrosis and collapse. Displacement can directly injure its blood supply through the retinacular vessels, which is why anatomical reduction and the avoidance of repeated forceful manipulation matter.
Capsular pressure. In Delbet I and II injuries the intracapsular haematoma may raise pressure within the capsule. That is the reason capsular decompression enters senior planning for displaced intracapsular fractures.
The physis. The proximal femoral physis is threatened in transphyseal injuries and by fixation choices. Protecting it has to be balanced against the need for stable fixation.
Neck mechanics. Vertical or varus fracture lines create shear and instability, so varus malreduction and inadequate fixation are not accepted. Progressive varus later on reflects collapse, malunion, non-union or growth disturbance, which is why the neck-shaft angle is measured during follow-up rather than only checking union.
Urgency in this injury is not about getting the fracture to unite. The femoral head can lose perfusion, the neck can collapse into varus and the physis can arrest.
Classification
The Delbet classification describes fracture location. Location correlates with femoral-head perfusion risk and fixation strategy: the more proximal the fracture, the greater the threat to the femoral-head blood supply, and the pooled avascular-necrosis risk falls stepwise from roughly 38% in type I to 28%, 18% and about 5% in type IV. Name the type, then always pair it with displacement, reduction quality, child age and associated injuries.
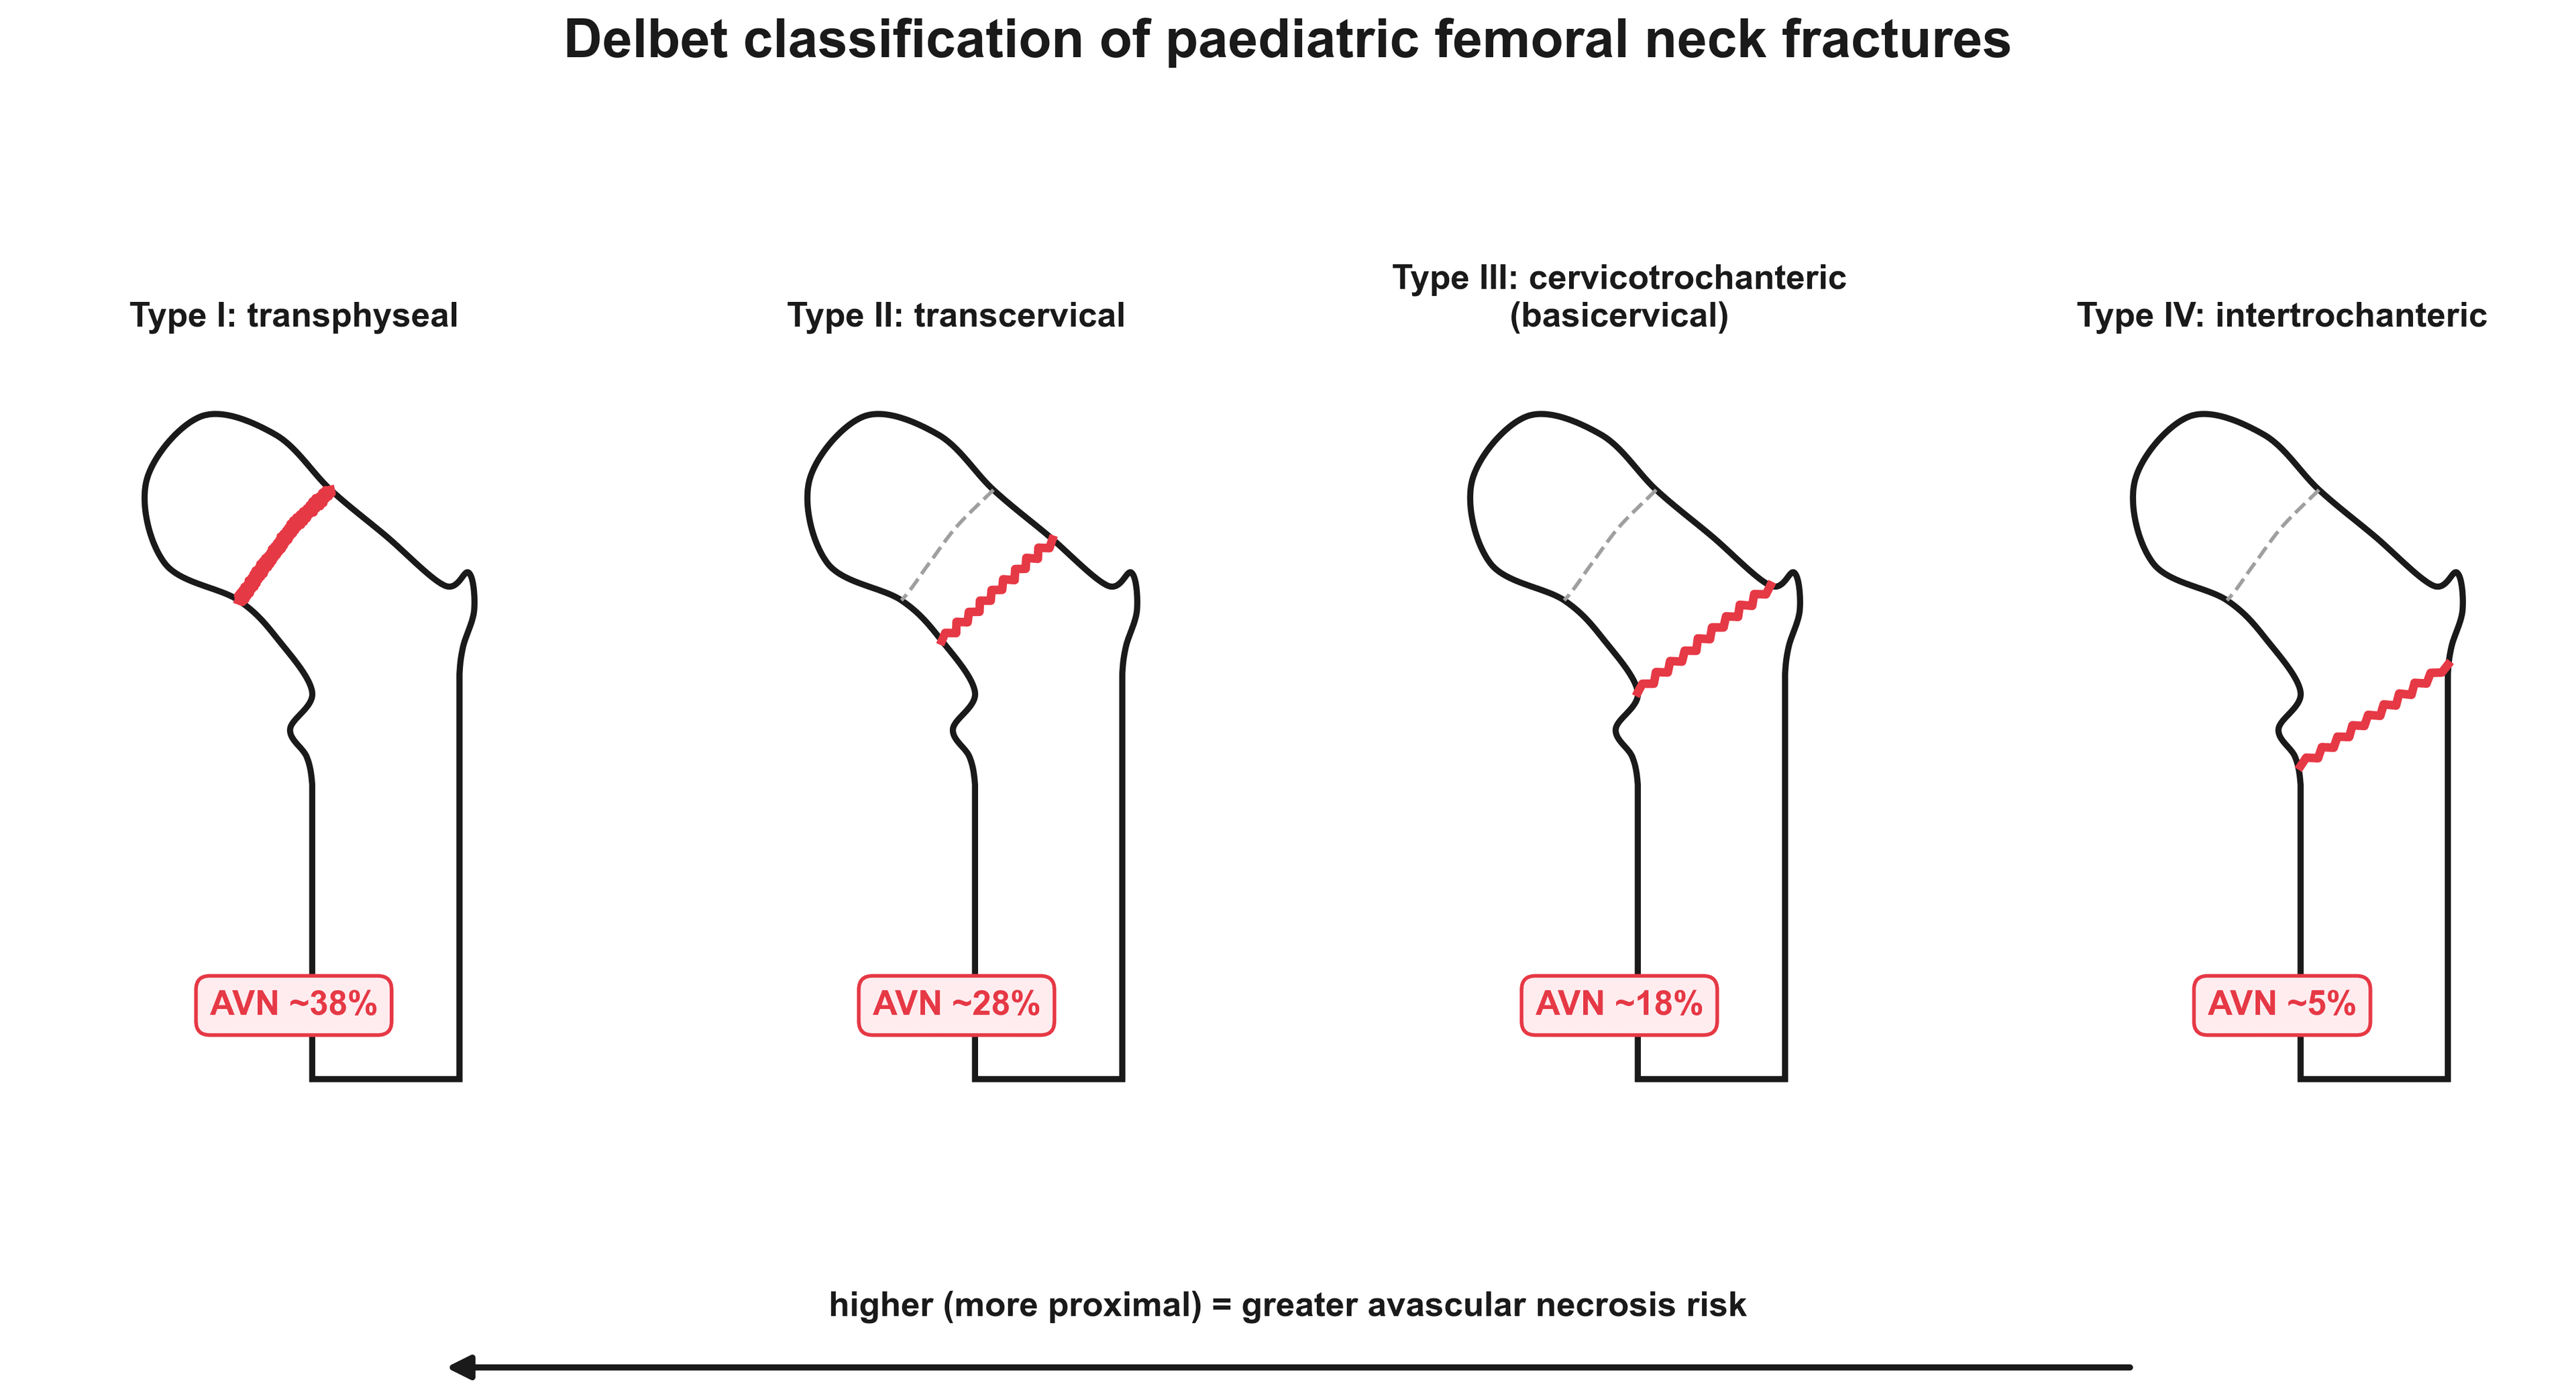
- Type I, transphyseal. Through the proximal femoral physis at the head-neck junction, with or without hip dislocation. It carries the greatest avascular necrosis and growth-plate concern because the injury is closest to the femoral head and physis, and reduction and stabilisation are time-sensitive.
- Type II, transcervical. Through the femoral neck. The classic high-risk paediatric femoral neck fracture, with high AVN, non-union and displacement risk, and usually treated operatively when displaced.
- Type III, basicervical or cervicotrochanteric. At the base of the neck. AVN risk is lower than in types I and II, but coxa vara, varus collapse and fixation failure remain major concerns, so stability and the neck-shaft angle are monitored.
- Type IV, intertrochanteric. Between the greater and lesser trochanters, and extracapsular. AVN risk is lower than in the intracapsular patterns and mechanical stability matters more than femoral-head perfusion, but displacement, comminution and child size still matter and AVN vigilance is still required.
Displacement. Displaced fractures need urgent reduction and stable fixation. Varus displacement is especially important because it increases shear, non-union risk and coxa vara, and rotational malalignment is easy to underestimate on a single AP image.
What else changes the plan. The same Delbet type may need different treatment depending on:
- Age and skeletal maturity
- Fracture level, verticality, Pauwels angle and comminution
- Polytrauma and an associated ipsilateral femoral shaft fracture
- A low-energy mechanism or underlying bone lesion
- Whether an anatomical closed reduction can be obtained
- Whether fixation must cross the physis to achieve stability
Clinical Presentation
History
Typical presentation. The child presents after high-energy trauma with severe hip or groin pain and inability to bear weight. Ask exactly where it hurts: the groin, lateral hip, thigh or knee.
Mechanism and function. Ask about road trauma, fall height, sports collision, crush injury or a direct lateral blow to the hip, and whether the child could stand, transfer or bear weight. Most true paediatric femoral neck fractures are high-energy, and a low-energy injury needs a pathology workup. Inability to weight bear supports urgent hip imaging and protected handling.
Preceding symptoms. A previous limp, night pain, fever, weight loss or a known bone lesion suggests pathological fracture, tumour, infection or metabolic bone disease.
Associated trauma. Ask about head, chest, abdominal, pelvic, femoral shaft, knee and neurological symptoms. High-energy trauma can produce competing injuries and a missed ipsilateral femoral shaft fracture.
Timing. Record the time of injury, the transfer and any delay in presentation. It frames urgency, counselling and the discussion of complication risk.
Examination
Examine the child using trauma principles before focusing on the hip. A displaced femoral neck fracture is painful, and repeated log rolling or forced positioning is unnecessary.
- Assess
- Trauma survey, haemodynamics, head, chest, abdomen, pelvis and other limb injuries.
- Why it matters
- Do not let the hip fracture distract from polytrauma.
- Assess
- Shortening, external rotation, guarding and severe pain with gentle movement.
- Why it matters
- Supports displaced proximal femur injury and need for protected handling.
- Assess
- Groin tenderness, proximal femur tenderness and pain with gentle log roll.
- Why it matters
- Confirms hip source when pain is reported in thigh or knee.
- Assess
- Femoral shaft swelling, knee injury and distal femoral physeal tenderness.
- Why it matters
- Avoid missed associated shaft or distal injury.
- Assess
- Open injury, crush trauma or threatened skin.
- Why it matters
- Changes antibiotic, debridement and fixation timing.
- Assess
- Distal perfusion, motor function and sensation.
- Why it matters
- Documents baseline in high-energy trauma.
A child with a painful knee after trauma can still have a hip fracture. Some children describe thigh or knee pain, so a hip injury can be missed if the assessment stops at the knee. Hip examination and pelvis imaging are essential when the mechanism is high energy or weight bearing is impossible.
Investigations
Radiographs first. Obtain an AP pelvis and a safe lateral view of the injured hip, which together confirm the Delbet level and displacement. Do not force frog-lateral positioning in a painful fracture: a cross-table lateral or other safe lateral projection is preferable. The AP pelvis gives the contralateral hip for comparison and helps identify associated pelvic injury.
The whole femur. Image it when the mechanism is high energy, when thigh pain is present or when an ipsilateral shaft fracture is possible. A femoral shaft fracture can distract attention from a proximal femoral injury, and the reverse is also true. Pelvic and wider trauma imaging as indicated prevents a missed shaft, pelvic, abdominal or head injury.
CT is useful when fracture anatomy is unclear, when reduction planning is difficult, when displacement is subtle, or when an associated pelvic or acetabular injury is suspected. It should answer a management question and should not delay urgent treatment of an obvious displaced fracture.
MRI and laboratory work are considered when the mechanism is low energy, when there was preceding pain, when the radiograph shows a lesion, or when infection or tumour is possible. The answer changes biopsy caution and definitive management.
Watching for AVN. Developing avascular necrosis is looked for on serial radiographs, with MRI if concern persists. MRI can help if AVN is suspected before radiographic collapse is obvious.
Differential Diagnosis
A child with a painful, non-weight-bearing hip after trauma does not always have a femoral neck fracture, and each alternative has a different urgency, imaging pathway and pitfall. The dangerous traps are a slipped capital femoral epiphysis (SCFE) mislabelled as a transphyseal fracture, and a low-energy "fracture" that is really a pathological lesion.
- Discriminating features
- Fracture follows clear high-energy trauma; SCFE is usually atraumatic or trivial trauma in an older, often overweight or endocrine-predisposed child with chronic groin or knee pain.
- Key pitfall
- Forcing reduction of an unrecognised acute-on-chronic SCFE as if it were a fracture can precipitate osteonecrosis.
- Discriminating features
- Low-energy mechanism, preceding limp or night pain, lytic or expansile lesion (unicameral bone cyst, aneurysmal bone cyst, non-ossifying fibroma, fibrous dysplasia) or permeative malignant pattern.
- Key pitfall
- Stabilising or biopsying through the wrong approach before staging a possible malignancy.
- Discriminating features
- Fever, raised inflammatory markers, refusal to weight bear without clear trauma; effusion on ultrasound.
- Key pitfall
- Attributing an irritable hip to minor trauma and missing joint sepsis.
- Discriminating features
- Fixed deformity, empty acetabulum on radiograph; may coexist with a Delbet I injury.
- Key pitfall
- Missing an associated transphyseal fracture during or after relocation.
- Discriminating features
- Localised lateral tenderness, intact neck-shaft architecture, avulsed apophysis.
- Key pitfall
- Over-treating a benign avulsion as an unstable neck fracture.
- Discriminating features
- Mechanism inconsistent with injury, age under walking, delayed presentation, other injuries of differing ages.
- Key pitfall
- Failing to safeguard while focusing only on the fracture.
Both cross the proximal femoral physis. The history (clear high-energy trauma versus atraumatic chronic symptoms), the child's age and habitus, and the contralateral hip usually separate them. Treating an acute slip with forceful reduction is a recognised route to osteonecrosis.
Management
The first hours. Start with analgesia, trauma assessment and immobilisation, and keep the child non-weight bearing in a safe position. Avoid repeated painful examination and forced frog-lateral positioning. Involve senior paediatric orthopaedics early, especially if the fracture is displaced, intracapsular, transphyseal, pathological or part of polytrauma.
How urgent. Displaced or unstable fractures need urgent anatomical reduction and stable fixation. Delbet type, displacement and reduction quality influence the urgency of fixation and the intensity of follow-up, and in practice urgency is judged on displacement, pain, transfer time and theatre access. Pooled data have not shown that operating within 24 hours lowers AVN; Controversies below explains why expedient treatment is still the practice.
Reduction. The goal is an anatomical reduction, checked on AP and lateral imaging, because poor reduction increases AVN, non-union and coxa vara risk. Closed reduction is reasonable if it produces a truly anatomical result without forceful repeated attempts. If it leaves varus, translation, rotation or a blocked reduction, open reduction is appropriate: a small incision is not a virtue if the price is malreduction.
Fixation. The implant is chosen by child size, fracture level, stability and physeal status. Options include cannulated screws, pins, paediatric hip screw constructs, plates or other proximal femoral fixation, depending on age and pattern, and the construct must hold the reduction during healing. The rules that apply to all of them:
- Stability usually matters more than avoiding the physis at all costs in a dangerous unstable fracture
- Screw threads should not distract the fracture
- Implants must not enter the joint
- Multiple views are needed to confirm implant position
- Cast or spica support may be used in younger children, depending on fixation and compliance
Capsular decompression. Many surgeons consider aspiration, capsulotomy or open decompression for displaced intracapsular fractures, because capsular haemarthrosis may increase pressure around the femoral head. The evidence is not uniform (see Controversies), but in a high-risk displaced Delbet I or II fracture decompression should be part of senior planning rather than an afterthought.
Aftercare. The child usually needs protected or non-weight bearing, serial radiographs, wound review, implant checks and progressive rehabilitation once healing allows. Protect the fixation until union, then restore motion and gait: fixation failure, coxa vara and stiffness are preventable follow-up targets. Tell the family early that the fracture may unite before the femoral-head risk is fully known.
Specific Scenarios
Undisplaced fracture. It is not automatically harmless. Confirm it on high-quality AP and lateral imaging, treat it as high risk even when displacement is absent, and review it serially. Many paediatric femoral neck fractures still undergo fixation because secondary displacement is dangerous. Non-operative care is rare, reserved for a very selected stable pattern under specialist oversight with protected weight bearing and close monitoring, and only where follow-up will be reliable. Counsel about AVN and late deformity.
Displaced intracapsular fracture. The classic urgent case. Classify it as Delbet I or II where appropriate, reduce it anatomically, fix it stably, consider capsular decompression, and watch carefully for AVN, non-union and coxa vara.
Pathological fracture. A low-energy mechanism, preceding pain or a visible lesion changes the problem. Stabilise the fracture while investigating the underlying diagnosis, and do not rush into biopsy through an inappropriate approach if malignancy is possible. The radiographic pattern directs the search among cyst, non-ossifying fibroma, fibrous dysplasia, infection, metabolic bone disease and malignancy.
Polytrauma. Follow trauma priorities first and coordinate timing with head, chest, abdominal and vascular injuries. Competing injuries should not create unnecessary delay in a displaced intracapsular fracture once the child is safe for surgery.
Complications and Follow-up
- What it looks like
- Pain, stiffness, sclerosis, fragmentation, collapse or loss of femoral-head sphericity.
- Why it matters
- Can declare late and may occur despite fracture union.
- What it looks like
- Falling neck-shaft angle from malreduction, fixation failure, non-union, physeal injury or collapse.
- Why it matters
- Shortens the limb, weakens abductors and may need osteotomy.
- What it looks like
- Persistent fracture line, pain, implant failure or varus progression.
- Why it matters
- Often reflects shear, poor reduction, unstable fixation or biological compromise.
- What it looks like
- Varus, rotation or translation after healing.
- Why it matters
- Produces limp, pain and abductor dysfunction.
- What it looks like
- Premature closure, proximal femoral growth disturbance or limb-length difference.
- Why it matters
- Growth consequences may outlast fracture healing.
- What it looks like
- Collapse, incongruity and altered proximal femoral mechanics.
- Why it matters
- Explains why surveillance often extends beyond union.
What follow-up tracks. Weight bearing progresses only as fixation and healing allow. Alongside the radiographs, follow pain, range, gait and abductor strength.
How long. Surveillance has to run past union. In a level I paediatric trauma cohort of 70 patients followed to union, osteonecrosis occurred in 20 (29%) and was diagnosed at a median of 7.8 months, long after most of these fractures have united and long after a routine fracture clinic would have signed the child off. A normal early radiograph does not exclude AVN. Warn the family at the outset that a good six-week film does not settle the question; otherwise the first sign of collapse is a limping child returning months later.
What predicted it. In the same cohort, displacement and fracture location were the independent predictors on multivariable analysis, while age, fixation type, mechanism, postoperative alignment and capsular decompression were not, a reminder that much of what gets argued about in theatre is less predictive than the injury the child arrived with.
When avascular necrosis does occur, grade it with the Ratliff classification, which describes the pattern and predicts prognosis.
- Type I, total head involvement: the whole capital epiphysis is avascular. The commonest and worst pattern, typically from a Delbet I or II injury disrupting the lateral epiphyseal vessels.
- Type II, partial or localised: segmental involvement of part of the head.
- Type III, an area limited to the femoral neck between the fracture line and the physis, sparing the epiphysis. The best prognosis.
Ratliff type correlates with the long-term Harris hip score and osteoarthritis risk, so naming it guides counselling and the aggressiveness of intervention (containment, osteotomy or salvage).
Relative trochanteric overgrowth. A specific growth sequela the examiner expects. If the proximal femoral capital physis arrests (from the injury, from fixation crossing it, or after AVN) while the greater trochanteric apophysis keeps growing, the trochanter ends up relatively high. That shortens the abductor lever arm and the femoral neck (coxa breva) and produces abductor weakness and a Trendelenburg gait, even when the neck-shaft angle is acceptable. It is distinct from coxa vara, a true reduction in the neck-shaft angle, though the two often coexist.
Treating it. Recognition matters because management differs. A young child with remaining growth can be treated with greater trochanteric epiphysiodesis to let the head and neck "catch up", whereas an established deformity in the older child needs trochanteric transfer (distal-lateral advancement) to restore the abductor moment arm. In follow-up, measure the articulotrochanteric distance, not just the neck-shaft angle.
Clinical Reasoning Notes
- Say clearly
- This is a paediatric femoral neck fracture, not an adult hip fracture.
- Why it matters
- Signals different vascular, growth and fixation risks.
- Say clearly
- Delbet type plus displacement, verticality and associated injuries.
- Why it matters
- Delbet type alone is incomplete.
- Say clearly
- Displaced intracapsular patterns are urgent because of femoral-head perfusion risk.
- Why it matters
- Prevents routine-list thinking.
- Say clearly
- Anatomical reduction, stable fixation, capsule pressure management where indicated and long surveillance.
- Why it matters
- Keeps decision-making focused on avoidable complications.
- Say clearly
- Age, skeletal maturity, polytrauma, low-energy mechanism, associated shaft/pelvic injury and closed-reduction quality.
- Why it matters
- Explains why the same Delbet type may need different treatment.
Common pitfalls
- Treating the injury like an adult neck-of-femur fracture.
- Saying "hip fracture" without naming Delbet type.
- Forgetting to ask why a low-energy fracture happened.
- Accepting varus reduction.
- Avoiding open reduction when closed reduction is poor.
- Focusing on implant type but not reduction quality.
- Missing joint penetration on postoperative imaging.
- Stopping follow-up once the fracture unites.
Counselling points
Families need a clear explanation that this is rare and serious. The fracture can heal but still develop late femoral-head or growth problems. They should understand the need for repeat imaging, protected weight bearing, monitoring for pain or stiffness, and longer follow-up than many other childhood fractures.
Guidelines, Registries and Global Practice
There is no single randomised trial or dedicated international guideline for this rare injury; practice is built from cohort series, two meta-analyses and society fracture-management principles. The picture below is a global synthesis rather than any one country's protocol.
Global epidemiology
- Paediatric femoral neck fractures represent less than 1 percent of all paediatric fractures and roughly 1 percent of hip fractures across age groups.
- Bimodal mechanism: high-energy trauma (road traffic, falls from height) in most series, with a smaller pathological-fracture group.
- Delbet type II (transcervical) is the most common pattern; type I (transphyseal) is the rarest but carries the highest osteonecrosis risk.
- Pooled osteonecrosis rates by Delbet class are approximately 38, 28, 18 and 5 percent for types I to IV respectively (Moon and Mehlman), with contemporary cohorts reporting overall AVN around 23 to 29 percent.
- Emphasis
- Anatomical reduction and stable internal fixation; spica supplementation in young children; implant sized to the child.
- Practical takeaway
- Stability plus anatomy is the universal core principle.
- Emphasis
- Urgent treatment of displaced fractures, consideration of capsular decompression, and prolonged AVN surveillance.
- Practical takeaway
- Treat displaced intracapsular injuries as emergencies and watch the head long term.
- Emphasis
- Senior decision-making, network transfer to a paediatric orthopaedic centre, and clear complication counselling.
- Practical takeaway
- Escalate early; these are not routine list cases.
- Emphasis
- Reduction quality as the dominant modifiable factor; honest acknowledgement that timing and decompression evidence is weak.
- Practical takeaway
- Frame timing and decompression as rational but unproven.
Registry and high- versus limited-resource practice
- Unlike adult hip fractures, this injury is too rare for dedicated arthroplasty-style registries; evidence comes from single-centre cohorts and the pooled meta-analyses above. National paediatric trauma networks (rather than implant registries) are the practical data source.
- High-resource settings: rapid imaging, sub-specialist paediatric orthopaedic cover, image-intensifier-guided reduction and fixation, and structured multi-year AVN surveillance.
- Limited-resource settings: delayed presentation is common and a recognised cause of established non-union and coxa vara in toddlers; valgus osteotomy with minimal fixation is a described salvage where early anatomical fixation was not feasible.
- Regardless of setting, the modifiable lever is the same — achieve and hold an anatomical reduction and follow the head for years.
Controversies and Areas of Uncertainty
Paediatric femoral neck fracture is often taught as if it were settled, and it is not. A consultant-level answer names where the evidence genuinely conflicts and then states a defensible position.
- The two positions
- Some series suggest earlier reduction protects the head; pooled meta-analysis (AlKhatib) found no significant timing effect, and Spence found a timing signal that was confounded by injury severity.
- Defensible practical stance
- Treat displaced Delbet I or II fractures expediently as best practice, but do not promise the family that an overnight operation prevents AVN.
- The two positions
- Open reduction allows anatomical reduction under vision; closed reduction avoids further surgical insult and was associated with lower AVN in long-term subgroups (Dong 2025).
- Defensible practical stance
- Aim for a closed anatomical reduction; convert to open only when closed reduction is not anatomical. Quality of reduction beats route.
- The two positions
- Biologically attractive (relieves tamponade on retinacular vessels); but Spence found decompression was not an independent predictor of AVN.
- Defensible practical stance
- Discuss explicitly for displaced intracapsular injuries; it is low-morbidity and biologically rational even though high-level proof is lacking.
- The two positions
- Avoiding the physis protects growth; crossing it may be unavoidable for stability in proximal Delbet I or II fractures.
- Defensible practical stance
- Accept controlled physeal crossing when stability demands it, then counsel about and monitor for growth arrest.
- The two positions
- Cannulated screws, paediatric hip screw or plate constructs each have advocates; no implant has been shown to change AVN or coxa vara rates.
- Defensible practical stance
- Choose by child size, fracture level and stability, not dogma; stability and reduction matter more than the device.
The effect sizes. Across 34 studies and 1332 children, the largest pooled paediatric dataset, the significant predictors of osteonecrosis were initial displacement (RR 2.98), poor reduction quality (RR 2.43), Delbet type I or II (RR 1.96) and age 12 or older (RR 1.40). The timing question looks different: pooling six comparative studies and 231 fractures, surgery under versus over 24 hours gave OR 1.19 (95% CI 0.56 to 2.51). That is no significant effect, and the confidence interval is wide enough that a real effect cannot be excluded either. In the same analysis, displacement carried OR 3.81 and Delbet I or II OR 2.43.
Reading them together. The fracture's biology outweighs the clock by a wide margin, and the one large lever the surgeon actually holds is reduction quality. In the long-term (5-year-plus) subgroups, delayed reduction did increase AVN (RR 2.63) and closed reduction outperformed open (RR 0.40). Expedient treatment therefore remains the right practice, because an unhurried anatomical reduction by an experienced surgeon beats a fast imperfect one. Before quoting the reduction-route finding, note its caveat: the apparent advantage of closed reduction may partly reflect that more severe fractures get selected for open surgery.
Against the single-centre cohort. The 70-patient cohort under Complications found postoperative alignment was not predictive, whereas the 1332-child pooled analysis found poor reduction quality was. Quote both, and say which dataset each comes from.
The strongest single message from the modern evidence is that reduction quality is the dominant surgeon-controlled determinant of outcome. Time, route and implant are secondary and contested.
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“A child presents after a fall from height with a displaced transcervical femoral neck fracture. How do you manage it?”
“A child sustains a femoral neck fracture after a minor fall from standing height. What changes in your assessment?”
“The parents of a child with a displaced Delbet type II fracture ask whether operating tonight and decompressing the joint will save the femoral head. What do you tell them, and what does the evidence show?”
Classify
- Delbet I: transphyseal
- Delbet II: transcervical
- Delbet III: basicervical
- Delbet IV: intertrochanteric
- Always add displacement
Treat
- Trauma assessment
- Urgent senior review
- Anatomical reduction
- Stable fixation
- Consider decompression
Avoid
- Delay
- Varus reduction
- Joint penetration
- Missed shaft fracture
- Early discharge from surveillance
Follow
- Union
- AVN
- Coxa vara
- Non-union
- Physeal arrest and LLD
Evidence Signals
Moon and Mehlman: the landmark AVN meta-analysis defining Delbet risk
- Pooled 360 paediatric femoral neck fractures (25 Cincinnati cases plus 20 literature reports with patient-level data).
- Osteonecrosis rate fell stepwise by Delbet class: type I 38 percent, type II 28 percent, type III 18 percent, type IV 5 percent.
- On logistic regression, fracture type and age were the only independent predictors; type I, II and III were 15, 6 and 4 times more likely to develop AVN than type IV.
Early versus late treatment: time-to-surgery did not independently change AVN
- Six comparative studies, 231 paediatric femoral neck fractures.
- No statistically significant difference in osteonecrosis between treatment under 24 hours versus over 24 hours (OR 1.19, 95 percent CI 0.56 to 2.51), nor between open and closed reduction (OR 1.62, 95 percent CI 0.82 to 3.22).
- Displaced fractures (OR 3.81) and Delbet type I or II fractures (OR 2.43) carried significantly higher AVN risk.
Contemporary risk-factor meta-analysis: what predicts AVN in 1332 children
- Thirty-four studies, 1332 patients (1340 fractures) — the largest pooled paediatric dataset to date.
- Significant AVN predictors: age 12 years or older (RR 1.40), Delbet type I or II (RR 1.96), initial displacement (RR 2.98) and poor reduction quality (RR 2.43).
- In long-term (5 year or more) subgroups, delayed reduction increased AVN (RR 2.63) and closed reduction and internal fixation reduced AVN versus open reduction (RR 0.40).
Anatomical reduction outweighs every other variable for long-term outcome
- 26 surgically treated Delbet type II and III fractures followed into adulthood (mean 157 months).
- AVN occurred in 23 percent and correlated with non-anatomic reduction, poor early Ratliff grade, lower adult Harris hip score and later osteoarthritis.
- Non-anatomic reduction correlated with all three principal complications; coxa breva and limb-length discrepancy did not predict poor clinical outcome.
Evidence Base
Single-centre risk-factor analysis: displacement and location, not decompression, predicted AVN
- 70 patients followed to union; osteonecrosis occurred in 20 (29 percent), median time to diagnosis 7.8 months.
- Fracture displacement and fracture location were the independent multivariable predictors of osteonecrosis.
- Age, fixation type, mechanism, postoperative alignment, performance of reduction and capsular decompression were NOT predictive.
Comprehensive review of proximal femoral fractures in childhood
- Delbet classification both guides management and provides prognostic clues.
- Universal agreement that anatomic reduction and stable internal fixation, supplemented by spica in younger children, are essential for good outcomes.
- The role of capsular decompression, implant choice and configuration, and surgical timing remain genuinely debated.