Radiation Safety, Modality Selection & the Growing Skeleton
Ultrasound: DDH (less than 6mo), joint effusion, soft tissue, guided aspiration — no radiation
Radiograph: Fracture screening, alignment, ossification centre assessment — low radiation
MRI: Complex fractures (physeal), infection, tumour, cartilage — no radiation
CT: Minimise in children — use only for complex fractures, spinal trauma, or tumour characterisation
Fluoroscopy: Intraoperative only — mandatory ALARA (pulse mode, collimation, shielding)
Key: Non-ionising modalities (USS, MRI) first. CT only when absolutely essential and with paediatric protocols.
- Children are 3-5 times more radiosensitive than adults due to rapidly dividing cells and longer remaining lifespan for stochastic effects to manifest.
- ALARA principle is paramount in paediatric imaging: use non-ionising modalities (USS, MRI) first whenever possible.
- Ossification centres appear sequentially: CRITOE for the elbow, specific timetables for the hip, knee, and wrist.
- The growing skeleton creates unique imaging challenges: unfused growth plates mimic fractures, ossification centres mimic avulsion fractures, and cartilaginous structures are radiolucent.
- Ultrasound is the preferred first-line investigation for many paediatric conditions: DDH (before 6 months), joint effusion, soft tissue masses, and guided procedures.
- “CRITOE: Capitellum (1yr), Radial head (3yr), Internal (medial) epicondyle (5yr), Trochlea (7yr), Olecranon (9yr), External (lateral) epicondyle (11yr) — the order of elbow ossification centre appearance.
- “The trapped medial epicondyle: following an elbow dislocation, the medial epicondyle avulsion may be trapped within the joint mimicking the trochlea. Compare with the contralateral elbow and check CRITOE sequence — if the trochlea appears before the medial epicondyle, it is a displaced medial epicondyle.
- “Image Gently campaign principles: reduce dose (lower kVp, mAs), use appropriate collimation (include only what is necessary), and scan once (avoid repeat/unnecessary imaging).
- “Remodelling potential: greatest in younger children, closer to the physis, and in the plane of motion of the adjacent joint. Angular deformity opposite the direction of joint motion has the least remodelling potential.
- “Greenstick and torus (buckle) fractures are unique to children due to the more porous, elastic nature of the paediatric cortex.
Overview
Paediatric imaging needs a fundamentally different approach from adult imaging. Three principles underpin every decision: radiation safety, the growing skeleton and the clinical context. The first two have sections of their own below.
The clinical context. Children cannot reliably describe their symptoms, and examination findings may be non-specific. The differential diagnosis for a musculoskeletal complaint is also different from an adult's.
Radiation Safety
Why children are more radiosensitive. Children are 3-5 times more radiosensitive than adults. The CHILD mnemonic collects the reasons.
CHILDWhy Children Are More Radiosensitive
Hook:CHILD: Cells dividing rapidly, Higher organ doses, Immature DNA repair, Longer lifespan, Dose accumulation.
ALARA in practice. ALARA, As Low As Reasonably Achievable, is paramount in paediatric imaging. In practice it comes down to six habits:
- Always consider whether imaging is necessary; clinical assessment alone may suffice, and the Ottawa ankle rules apply from age 6
- Use non-ionising modalities first: ultrasound for soft tissue, MRI for complex assessment
- If ionising imaging is needed, use paediatric protocols with reduced kVp and mAs
- Collimate tightly, including only the anatomy needed and avoiding whole-body scatter
- Shield radiosensitive organs, the gonads and thyroid, when they are in or near the beam
- Scan once, avoiding unnecessary repeat imaging
The Image Gently campaign provides protocols for paediatric dose reduction.
How Large Is the Risk, Actually?
Paediatric CT is treated differently from adult CT because the harm has been measured directly in children. A candidate who can quote both the relative and the absolute figures will handle this station far better than one who can only say "minimise radiation".
The relative risks. In a British cohort (Pearce) of about 178,000 patients first scanned before age 22, a cumulative red-marrow dose of roughly 30 mGy or more (mean 51 mGy) carried a relative risk of leukaemia of 3.18 compared with under 5 mGy. Cumulative brain doses of 50-74 mGy carried a relative risk of brain tumour of 2.82.
An Australian data-linkage study (Mathews) of 10.9 million people, 680,211 of them exposed to CT under age 20, found overall cancer incidence 24% higher in the exposed (IRR 1.24), rising by 0.16 with each additional scan. The risk was greater the younger the child at exposure.
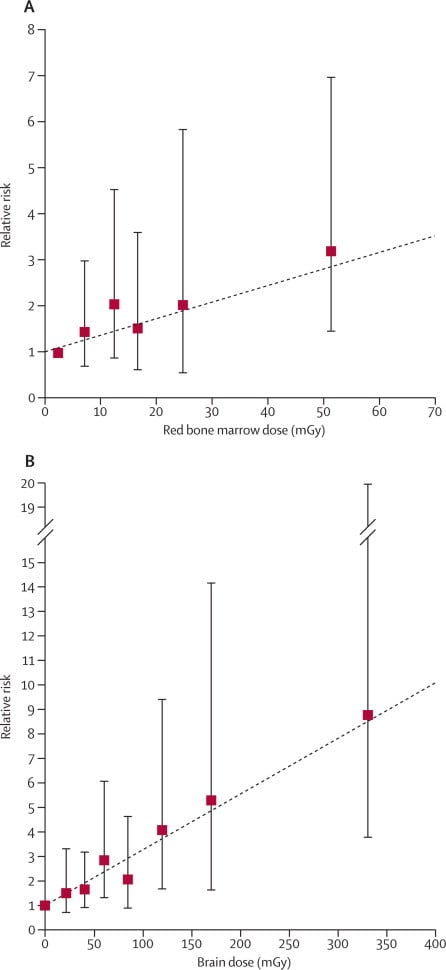
The absolute risk. This half matters just as much in a consent conversation. Those relative risks sit on a very small baseline: the absolute excess in the British data was about one extra leukaemia and one extra brain tumour per 10,000 head CTs within ten years for children under 10; in the Australian cohort it was 9.38 excess cancers per 100,000 person-years.
Say both: quoting only the relative risk frightens families out of scans they need, and quoting only the absolute risk excuses scanning without thought. A necessary CT still benefits the child: the target is the unnecessary scan, not CT itself.
Variation in dose. Across seven US health systems, effective dose per paediatric CT ranged from 0.03 to 69.2 mSv, a spread of more than a thousandfold for scans doing the same job. Modelling on that data suggested that reducing the highest-quartile doses to the median would prevent about 43% of the projected radiation-induced cancers.
The most actionable finding concerns variation rather than volume, and it turns ALARA from an attitude into a target. Most of the avoidable harm comes from a high-dose minority of scans, so child-sized protocols, scanning only the indicated region and avoiding multiphase acquisitions are worth more than agonising over whether to scan at all.
The limits. State them honestly, because the examiner may press. These are observational studies, and reverse causation cannot be fully excluded: a child scanned for a subtle early symptom may already have had the disease that later declares. The projected cancer counts are modelled on linear-no-threshold assumptions, whose validity at low doses is debated, rather than observed.
Contemporary doses are lower than those of the 1985-2005 era these cohorts studied, which strengthens the case for optimisation. The pragmatic consensus is to justify and optimise, not to refuse necessary CT.
The Growing Skeleton
Ossification centres. Ossification centres appear sequentially, at predictable ages, and can mimic avulsion fractures. Knowing their sequence and timing is fundamental to paediatric image interpretation, and its key clinical use is distinguishing a normal centre from a fracture fragment. The elbow is the most commonly tested sequence: its six centres appear in the order CRITOE.
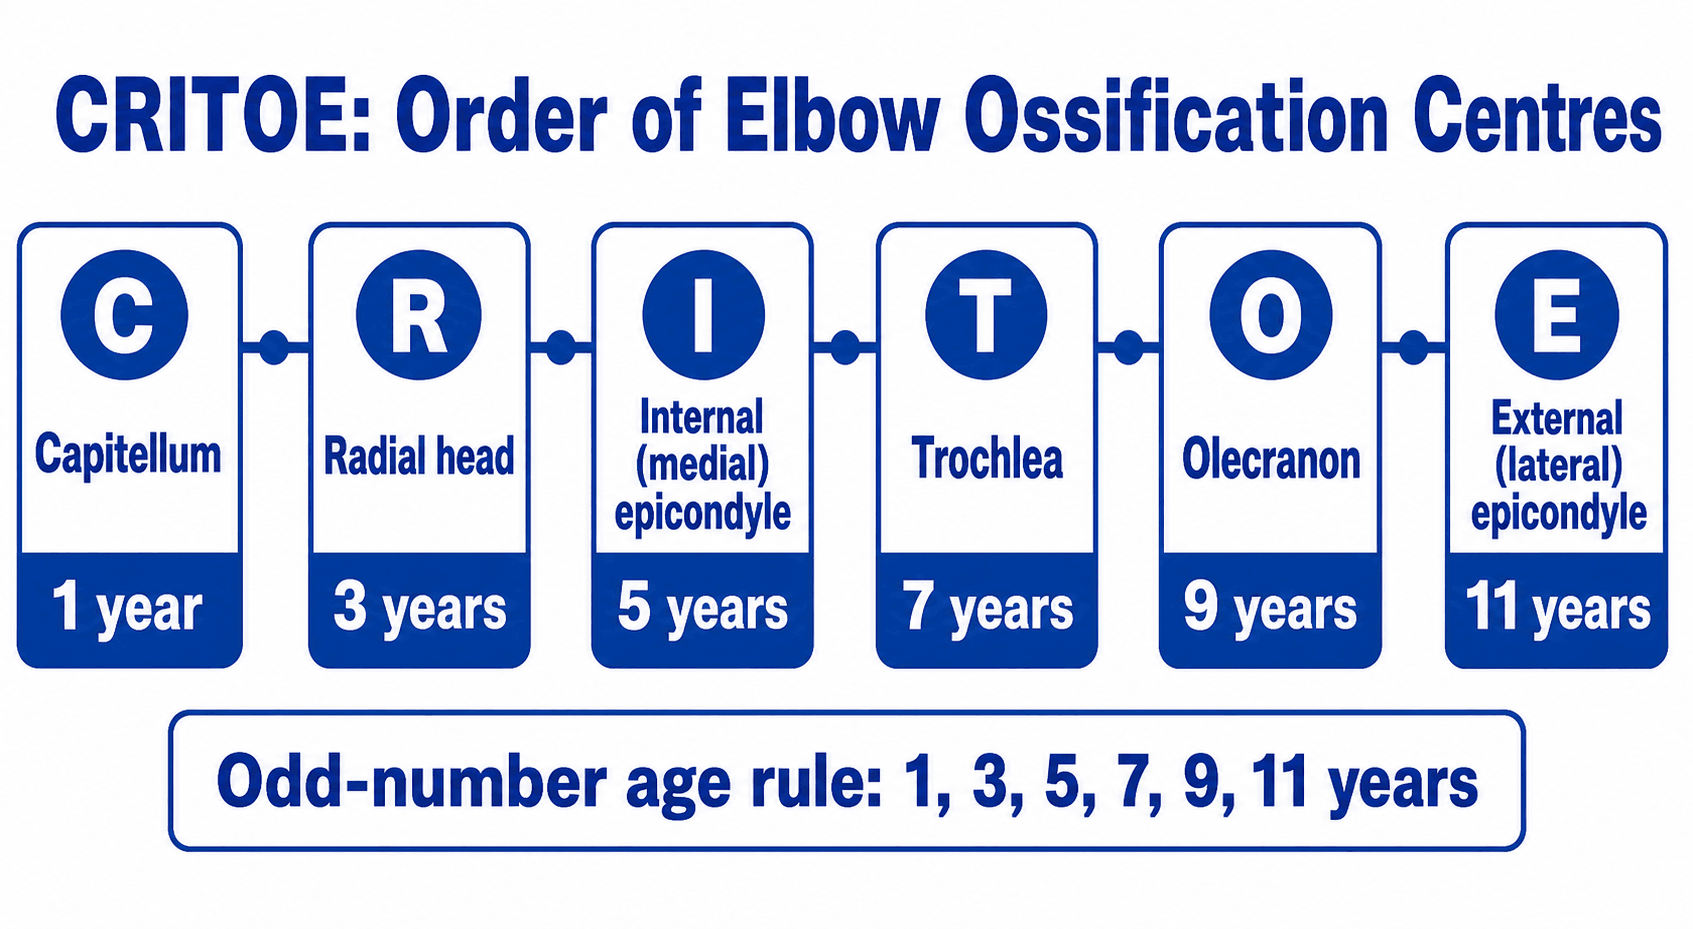
CRITOEElbow Ossification Centre Sequence
Hook:CRITOE: 1-3-5-7-9-11 years.
The trapped medial epicondyle. This is the critical clinical application of CRITOE. After a paediatric elbow dislocation, the medial epicondyle, avulsed by the ulnar collateral ligament, can become trapped within the joint, and on the post-reduction radiograph it may be misinterpreted as the trochlea.
If the trochlea is 'present' but the medial epicondyle is not visible in its normal position, the medial epicondyle is trapped in the joint and requires open surgical removal. Check the CRITOE sequence and compare with the contralateral elbow.
The hip. The femoral head ossification centre appears at 3-6 months. Until it does, radiographs cannot visualise the cartilaginous femoral head, and that is what decides how DDH is imaged (Modality Selection, below).
The wrist. The carpal ossification centres appear in a roughly circular sequence. The capitate (1-3 months) and hamate (2-4 months) come first, and the pisiform is the last carpal bone to ossify, at approximately 10-12 years. The distal radial epiphysis ossification centre appears at approximately 1 year.
Comparison views. When it is uncertain whether a density is a normal ossification centre or a fracture fragment, obtain comparison views of the contralateral, uninjured side. Both limbs should show symmetric ossification patterns.
The physis. The growth plate is the weakest link in the paediatric musculoskeletal chain, weaker than the ligaments and bone around it. What would be a ligament injury in an adult is a physeal fracture in a child, and an unfused growth plate can itself mimic a fracture.
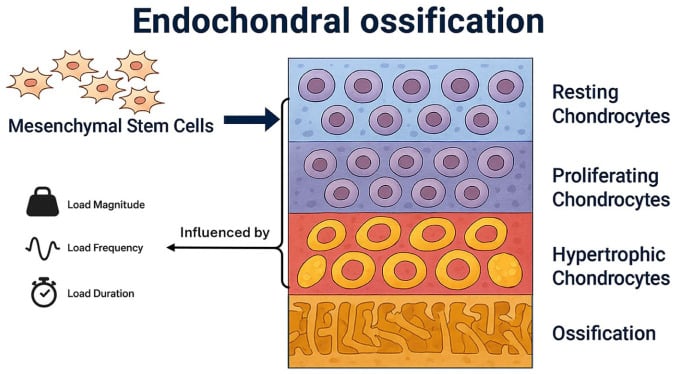
Unossified cartilage. Articular and epiphyseal cartilage are radiolucent, and MRI or ultrasound may be needed to evaluate them.
Remodelling. Children can correct angular deformity through growth. The potential is greatest in younger children, close to the physis and in the plane of motion of the adjacent joint.
Paediatric Fracture Patterns
The paediatric skeleton produces fracture patterns not seen in adults, for three reasons: the physis is the weakest mechanical link, the periosteum is thicker and more metabolically active, and the cortex is more porous and elastic. That porous, elastic cortex is why greenstick and torus fractures are unique to children.
Plastic deformation (bowing). The bone bends beyond its elastic limit but does not fracture, so the radiograph shows a curved bone with no fracture line, and comparison views may be required. It is most common in the ulna and fibula. A plastically deformed ulna may prevent reduction of an associated radial fracture, or closed reduction of a radial head dislocation (a Monteggia equivalent).
Torus (buckle) fracture. The metaphyseal cortex fails in compression and buckles outward without disrupting completely. It is most common at the distal radius and radiographically subtle: look for a small cortical irregularity or bump on the dorsal cortex. It is very stable, is treated in a splint or cast for 3-4 weeks and has an excellent prognosis.
Greenstick fracture. One cortex fractures completely while the opposite cortex bends, as a green stick breaks. The intact periosteum on the compression side acts as a tether: it maintains alignment but may prevent complete reduction. If the fracture is not fully reduced, the intact cortex acts as a spring and the fracture may re-angulate in the cast.
Complete fractures. Thick periosteum can prevent significant displacement even when the fracture is complete, a pattern more common in younger children.
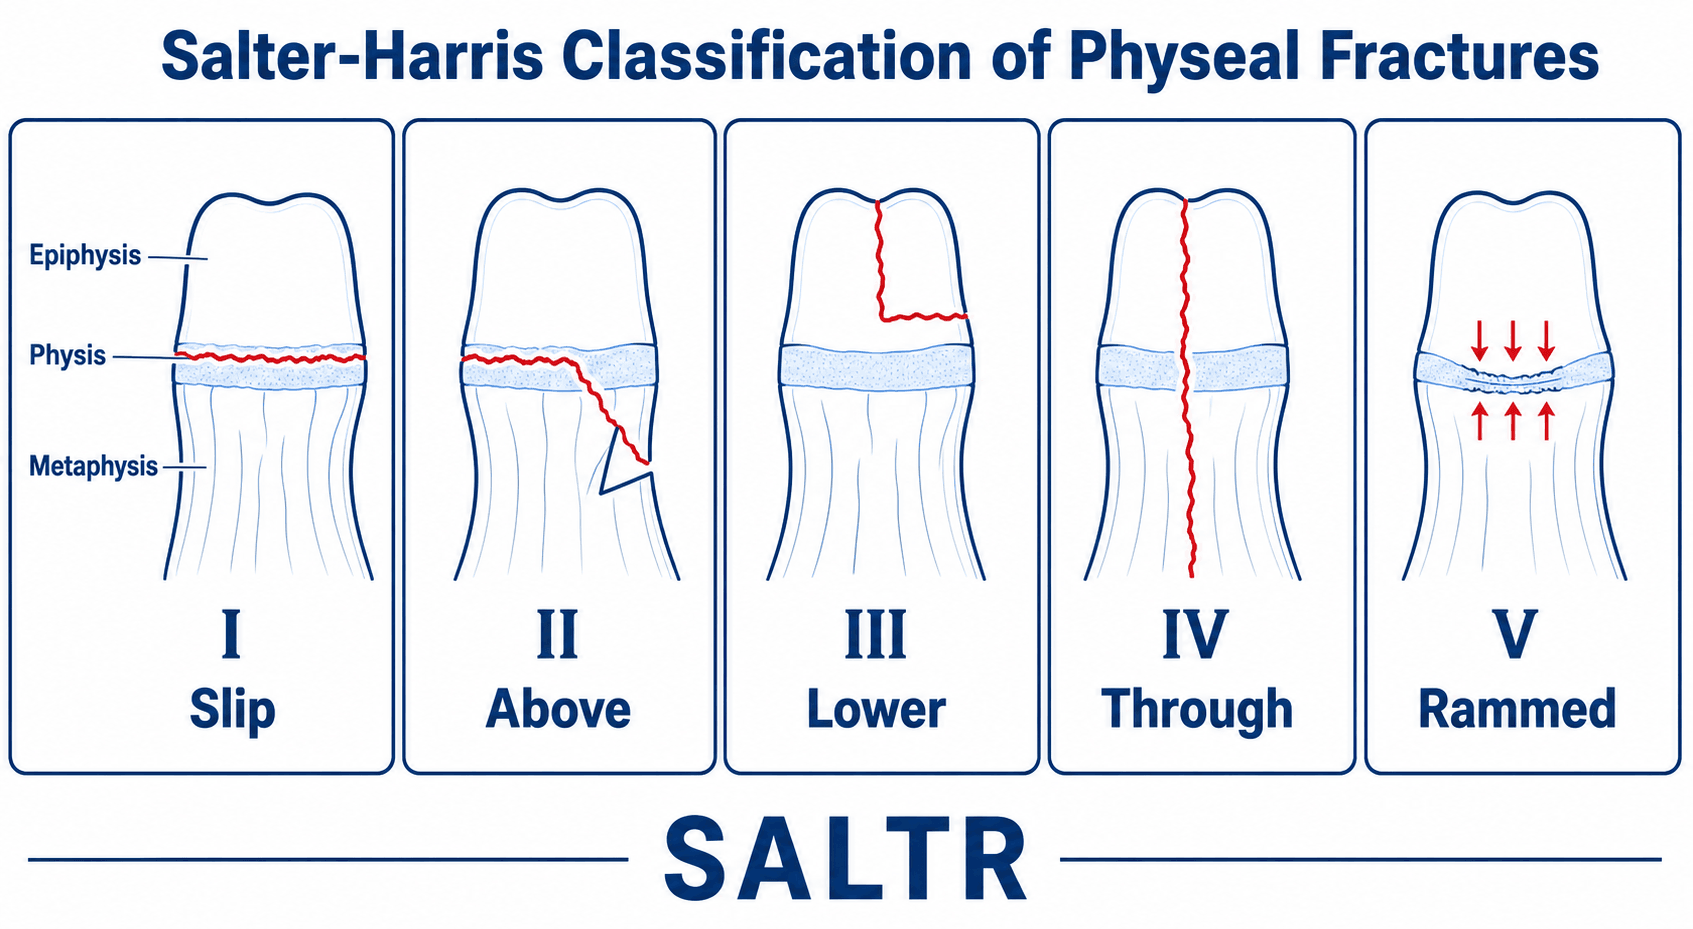
Physeal (Salter-Harris) fractures. Because the physis is the weakest link, this is where the growing skeleton fails. Salter-Harris classifies these injuries I-V, and SALTR recalls the fracture lines.
- SALTR
- Slip
- Fracture line
- Through the physis alone
- Imaging and significance
- The radiograph may be normal; diagnosed by point tenderness over the growth plate
- SALTR
- Above
- Fracture line
- Through the physis and out into the metaphysis (the Thurston-Holland fragment)
- Imaging and significance
- The most common type
- SALTR
- Lower
- Fracture line
- Through the physis into the epiphysis and the joint
- Imaging and significance
- Requires anatomical reduction
- SALTR
- Through
- Fracture line
- Through metaphysis, physis and epiphysis
- Imaging and significance
- Requires anatomical reduction
- SALTR
- Rammed
- Fracture line
- A crush of the physis
- Imaging and significance
- Radiographically occult; the worst prognosis for growth arrest
Modality Selection
- Preferred Imaging
- Ultrasound (hip USS, Graf classification)
- Rationale
- Femoral head not yet ossified; ultrasound shows the cartilaginous anatomy, with no radiation
- Preferred Imaging
- AP pelvis radiograph (Perkins, Hilgenreiner lines)
- Rationale
- Femoral head ossification centre now visible; the radiograph is standard
- Preferred Imaging
- AP pelvis + frog lateral radiograph. Blood tests (CRP, FBC)
- Rationale
- Differential: irritable hip vs Perthes vs septic arthritis. USS if effusion suspected
- Preferred Imaging
- AP + lateral elbow radiograph. Comparison views if needed
- Rationale
- Assess fat pads, anterior humeral line and CRITOE centres (below)
- Preferred Imaging
- MRI (if management would change)
- Rationale
- MRI shows physeal oedema and confirms the diagnosis
- Preferred Imaging
- Consider point-of-care ultrasound before defaulting to splint-and-review
- Rationale
- Radiation-free; supplements the standard pathway (below)
- Preferred Imaging
- Ultrasound (detects effusion + guides aspiration)
- Rationale
- No radiation; real-time guided aspiration for diagnostic synovial fluid analysis
- Preferred Imaging
- Skeletal survey (full-body radiograph series)
- Rationale
- Standardised protocol with a repeat survey (Non-Accidental Injury, below)
- Preferred Imaging
- MRI (no radiation, excellent soft tissue contrast)
- Rationale
- Avoids CT radiation; shows cartilaginous structures, physeal involvement and marrow pathology
The anterior fat pad. A genuinely normal anterior fat pad is powerful negative evidence after elbow trauma, with a sensitivity of 96.4% and a negative predictive value of 98.2% for the absence of fracture. Its apical angle separates normal (mean 14.7 degrees) from abnormal (mean 27.0 degrees) fat pads. An elevated fat pad means an occult fracture until proven otherwise.
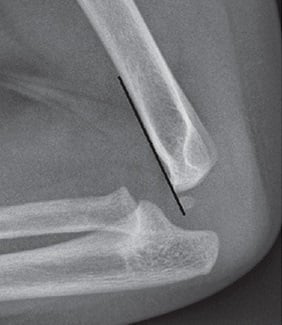
The occult elbow fracture. When the radiograph is normal, ultrasound can show lipohaemarthrosis, the posterior fat pad sign and cortical disruption. In 34 children with normal radiographs it identified 13 fractures, and all 21 with a normal scan had no fracture at follow-up, allowing immobilisation and review to be safely de-escalated. It is radiation-free and cheaper, but highly operator-dependent and validated only in small single-centre series, so it supplements rather than replaces the standard pathway.
Normal Variant versus Pathology
The single most common interpretive error in paediatric imaging is mistaking a normal developmental appearance for pathology, or pathology for a normal appearance. Use this differential whenever a finding looks abnormal in a child.
- Benign developmental explanation
- Physis (growth plate) — smooth, regular, expected location
- True pathology to exclude
- Salter-Harris fracture — irregular widening, metaphyseal/epiphyseal extension
- Discriminator
- Compare with contralateral side; physis is symmetric and smooth
- Benign developmental explanation
- Ossification centre appearing on schedule (CRITOE order)
- True pathology to exclude
- Avulsion fracture — fragment displaced, surrounding soft-tissue swelling
- Discriminator
- Check CRITOE order; an out-of-sequence centre means a fragment, not a centre
- Benign developmental explanation
- Normal variant ossification (e.g. distal femoral, calcaneal apophysis)
- True pathology to exclude
- Osteochondritis/Perthes — sclerosis, collapse, fragmentation with symptoms
- Discriminator
- Bilateral and asymptomatic favours variant; unilateral and painful favours disease
- Benign developmental explanation
- Normal metaphyseal step or developmental cortical irregularity
- True pathology to exclude
- Torus (buckle) fracture — focal buckle with point tenderness and mechanism
- Discriminator
- Clinical tenderness and mechanism; comparison view of the other limb
- Benign developmental explanation
- Physiological bowing of infancy/toddler
- True pathology to exclude
- Plastic deformation fracture or rickets/dysplasia
- Discriminator
- Age, symmetry, metaphyseal cupping/fraying (rickets) vs trauma history
- Benign developmental explanation
- —
- True pathology to exclude
- Non-accidental injury — fractures of varying ages, classic metaphyseal lesions, rib fractures
- Discriminator
- Always consider NAI; correlate with history, perform skeletal survey, safeguard
Skeletal Maturity (Bone Age)
Growth remaining. Estimating skeletal maturity is a core paediatric imaging skill because management timing in paediatric orthopaedics depends on growth remaining, not chronological age. The standard film is an AP radiograph of the left hand and wrist.
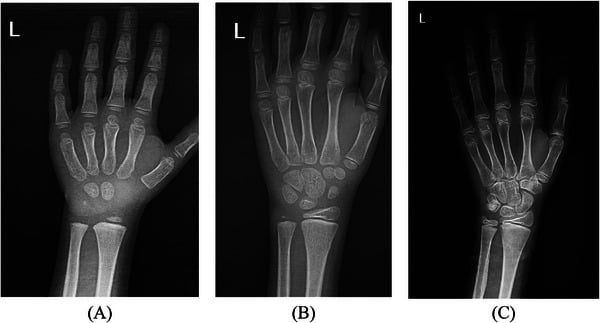
Greulich-Pyle and Tanner-Whitehouse. Greulich-Pyle is the most widely used method: the hand and wrist film is compared against the closest age and sex standard in the atlas, a gestalt match that is quick but observer-dependent. Tanner-Whitehouse (TW2/TW3) scores the maturity of individual hand and wrist bones and sums them to a maturity score, which is more reproducible but slower.
Risser and Sanders. Deformity work uses two further maturity indicators, one pelvic and one hand-based. The Risser sign grades ossification of the iliac apophysis from 0 to 5 and indicates how much spinal growth remains. The Sanders classification, a hand-based staging, tracks the adolescent growth spurt more precisely than Risser and is important around peak height velocity.
What it decides. Skeletal age informs:
- The timing of guided growth or epiphysiodesis, and of deformity correction: act while the physes are open
- Limb-length discrepancy prediction and equalisation planning; the Menelaus, Moseley and multiplier methods all need skeletal, not chronological, age
- Scoliosis progression risk: a low Risser or early Sanders stage means more growth and a higher risk of curve progression
- Endocrine and growth-disorder work-up, where bone age is advanced or delayed relative to chronological age
- Prognosis and the window for intervention in conditions such as Perthes disease and SUFE
Non-Accidental Injury
The skeletal survey. Recognising inflicted injury is a medico-legal and safeguarding imperative, and the skeletal survey is the screening tool. It is a standardised, individually collimated series, not a single "babygram": AP and lateral skull, AP chest, AP abdomen and AP views of all limbs, covering the axial skeleton and all long bones, hands and feet.
A repeat survey at about 11-14 days reveals healing fractures that were invisible acutely. In infants, cranial imaging (CT or MRI) is added for suspected head injury.
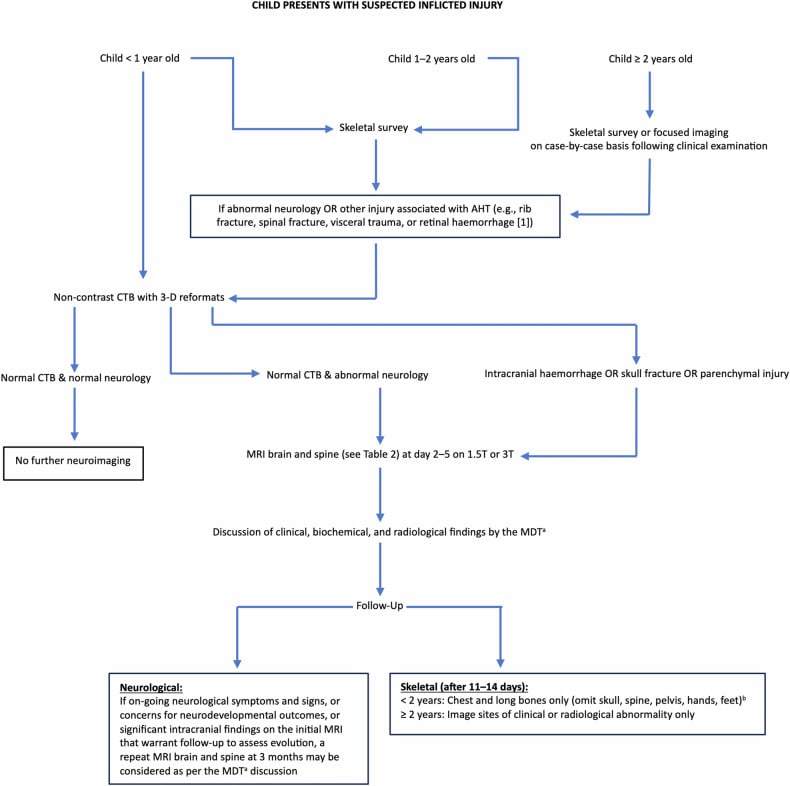
Specificity for abuse. The Kleinman framework grades fractures by how specific they are for abuse:
- High specificity: classic metaphyseal lesions (CML, the "corner" or "bucket-handle" fracture), posterior rib fractures, and scapular, spinous-process and sternal fractures
- Moderate specificity: multiple fractures (especially bilateral), fractures of different ages or stages of healing, vertebral body fractures, digital fractures and complex skull fractures
- Low specificity, common but non-specific: clavicle, long-bone shaft and linear skull fractures, whose significance depends on the history
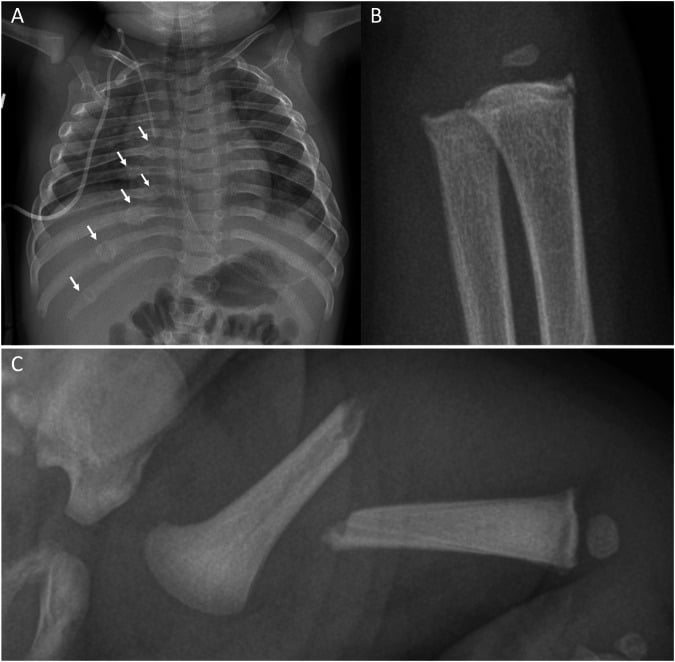
Red flags. Be alert to an injury inconsistent with the stated mechanism or developmental stage, such as a femur fracture in a non-ambulant infant, and to delayed presentation, a changing history and multiple injuries. Any suspicion mandates documentation, senior or child-protection referral and safeguarding. Imaging supports the multidisciplinary assessment but does not replace it.
Guidelines, Registries & Global Practice
Paediatric imaging is governed by convergent international frameworks. The unifying principle worldwide is justification plus optimisation (ALARA/ALARP) under the EURATOM Basic Safety Standards and ICRP recommendations, operationalised through diagnostic reference levels (DRLs) and child-sized protocols.
Global epidemiology and burden. Paediatric CT use rose sharply in the 1990s-2000s then plateaued/declined after the dose-risk evidence emerged (Miglioretti 2013; Mathews 2013). Effective dose per paediatric CT varies more than 1000-fold between scans and institutions, so the dominant driver of population radiation risk is unoptimised technique rather than the number of scans. DDH affects roughly 1-3 per 1000 live births for true dislocation, with higher rates for instability/dysplasia, and is more common in girls, breech presentation, and those with a positive family history — driving the global debate over universal versus selective ultrasound screening.
- AAOS / ACR (US)
- ACR Appropriateness Criteria + Image Gently; justify and optimise every study
- BOA-BOAST / NICE (UK)
- IR(ME)R regulations; clinician must justify each exposure; NICE imaging guidance
- AO / EFORT (Europe)
- EURATOM Basic Safety Standards; EuroSafe Imaging; national DRLs
- AAOS / ACR (US)
- AAOS guideline: selective USS for risk factors (breech, family history, clinical instability); no universal USS
- BOA-BOAST / NICE (UK)
- UK NIPE: clinical screening at birth and 6-8 weeks plus selective USS for risk factors
- AO / EFORT (Europe)
- Several European systems (e.g. Germany, Austria) use universal Graf USS screening
- AAOS / ACR (US)
- Radiograph; treat positive fat pad as occult fracture; USS emerging adjunct
- BOA-BOAST / NICE (UK)
- Radiograph plus splint-and-review at 7-14 days; comparison views if needed
- AO / EFORT (Europe)
- Radiograph with CRITOE assessment; USS used in some centres (Burnier)
- AAOS / ACR (US)
- Prefer MRI where it answers the question; reserve CT for cortical/operative planning
- BOA-BOAST / NICE (UK)
- MRI preferred for physeal and soft-tissue questions to avoid dose
- AO / EFORT (Europe)
- MRI-first for cartilage/physis; CT for fracture geometry and 3D planning
Registries and audit. There is no single global paediatric imaging registry, but dose audit is registry-like: national DRL surveys (e.g. UK PHE/HPA, US ACR Dose Index Registry, EU EUCLID project) benchmark paediatric doses by age/weight band, and paediatric DRLs are typically 50-70% lower than adult values for the same examination. For DDH and implant-related paediatric work, arthroplasty registries (NJR, AOANJRR, SHAR) inform downstream practice but do not capture screening imaging.
High- versus limited-resource practice. In well-resourced settings, MRI and high-quality ultrasound are widely available, enabling radiation-free pathways (USS-first for DDH and effusion, MRI for physeal/marrow/tumour questions). In limited-resource settings, MRI access, sedation capacity, and trained paediatric sonographers may be scarce, so radiographs and clinical decision rules carry more weight; here the priorities shift to avoiding unnecessary radiographs, using comparison views judiciously, and reserving CT for clearly decisive indications.
Controversies & Areas of Uncertainty
Universal versus selective DDH ultrasound screening. Universal Graf ultrasound, used in parts of Europe, detects more dysplasia but increases over-treatment and cost; selective screening, as in the US and UK, may miss some late-presenting cases. No high-quality trial has resolved which strategy improves long-term hip outcomes, so practice remains region-dependent.
Routine comparison radiographs of the uninjured limb. Long taught for the elbow, comparison views add radiation and often little value when a structured CRITOE and line analysis is applied. Many paediatric centres now reserve them for genuinely equivocal cases.
Point-of-care ultrasound for fractures. Evidence for ultrasound in the occult elbow fracture and in distal forearm fractures is growing, but it is mostly single-centre and operator-dependent. In most guidelines ultrasound is an adjunct, not yet a replacement for radiographs.
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“A 7-year-old boy falls off monkey bars and presents with elbow pain and swelling. The lateral elbow radiograph shows a posterior fat pad sign but no visible fracture.”
“An examiner asks you why radiation dose management is particularly important in children and what principles you would apply.”
“A 4-year-old has sustained an elbow dislocation. The post-reduction radiograph appears satisfactory, but you notice that the trochlea ossification centre appears to be present while the medial epicondyle is not visible.”
Radiation Safety (CHILD)
- Children are 3-5x more radiosensitive than adults
- ALARA: justify, use non-ionising modalities first, paediatric protocols, collimate, shield
- USS and MRI preferred over CT whenever possible
- Image Gently: child-size-specific protocols reduce dose by 20-50%
- Pearce et al. 2012: direct evidence linking childhood CT to cancer risk
CRITOE (Elbow Ossification)
- C: Capitellum (1yr), R: Radial head (3yr), I: Internal/medial epicondyle (5yr)
- T: Trochlea (7yr), O: Olecranon (9yr), E: External/lateral epicondyle (11yr)
- CRITICAL: trochlea ALWAYS after medial epicondyle — if trochlea without M.E. = TRAPPED
- Comparison views essential when in doubt about normal vs pathological
- Posterior fat pad sign = occult fracture in trauma
Modality Selection
- DDH: USS before 6 months (Graf), radiograph after 6 months (Perkins/Hilgenreiner)
- Joint effusion/septic arthritis: USS (no radiation, guides aspiration)
- Complex fracture/physeal injury: MRI (no radiation, shows cartilage and physis)
- NAI: skeletal survey (standardised protocol, repeat at 2 weeks)
- CT: ONLY when essential (complex fractures, spinal trauma, tumour)
Paediatric Fracture Patterns
- Plastic deformation: bowed bone, no fracture line (ulna/fibula)
- Torus (buckle): cortical compression failure, subtle bump (distal radius)
- Greenstick: one cortex fractured, opposite bends
- Salter-Harris: I (normal X-ray), II (most common), III-IV (ORIF), V (retrospective)
- Remodelling: best in younger children, near physis, in plane of motion
Evidence Base
Childhood CT and Subsequent Leukaemia and Brain Tumour Risk
- Retrospective cohort of 178,604 patients (leukaemia analysis) and 176,587 (brain tumour analysis) first scanned under age 22 in Great Britain (1985-2002).
- Cumulative red-marrow doses of about 30 mGy or more (mean 51 mGy) gave a relative risk of leukaemia of 3.18 (95% CI 1.46-6.94) versus under 5 mGy.
- Cumulative brain doses of 50-74 mGy (mean 60 mGy) gave a relative risk of brain tumour of 2.82 (95% CI 1.33-6.03).
Pediatric CT Use, Dose and Projected Cancer Risk
- Across seven US health systems, paediatric CT use roughly doubled (under-5s) to tripled (5-14y) between 1996 and 2005 before declining.
- Effective dose per scan varied enormously (0.03 to 69.2 mSv), showing wide, often unjustified, dose variability.
- An estimated 4 million annual paediatric CTs project to about 4,870 future cancers; reducing the highest-quartile doses to the median could prevent roughly 43% of these.
Image Gently Campaign — Optimising Paediatric Dose
- Promotes child-size-specific CT protocols: reduce kVp/mAs for body size, scan only the indicated region, and avoid multiphase scanning.
- Core slogan: image gently — child-size the dose, scan only when needed, and scan only the indicated area once.
- Adopted internationally and complemented by Image Wisely (adults) and the EuroSafe/EURATOM dose-optimisation frameworks.
Cancer Risk After Childhood CT — 11 Million Australians
- Population data-linkage cohort of 10.9 million people; 680,211 exposed to CT under age 20 (mean follow-up 9.5 years; mean dose 4.5 mSv/scan).
- Overall cancer incidence was 24% higher in exposed individuals (IRR 1.24, 95% CI 1.20-1.29), rising by 0.16 per additional CT scan.
- Risk was greater with younger age at exposure, spanning solid cancers, leukaemia and myelodysplasia (absolute excess 9.38 cancers per 100,000 person-years).
Direct cohort evidence (Pearce, Miglioretti, Mathews) plus society campaigns strongly support radiation dose minimisation and protocol optimisation in children.