Piriformis Anatomy
Overview
The piriformis is a flat, pyramidal muscle in the posterior gluteal region and the landmark that organises the neurovascular structures leaving the pelvis. Almost all significant structures leave through the greater sciatic foramen, and each is described by whether it passes above or below this muscle.
It is examined from two directions. For the surgeon it is the landmark of the posterior hip approach, where the sciatic nerve and its variations must be found. For the clinician it is the site of piriformis syndrome, an extra-spinal cause of sciatica.
Attachments, Innervation and Relations
Origin. The muscle arises from the anterior surface of the sacrum, from segments S2 to S4 between the anterior sacral foramina. It also takes origin from the gluteal surface of the ilium near the posterior inferior iliac spine, with a minor contribution from the sacrotuberous ligament.
Course and insertion. It leaves the pelvis through the greater sciatic foramen, which it fills almost completely, leaving small gaps above and below. It inserts on the superior border and medial aspect of the apex of the greater trochanter, and its tendon often blends with the tendons of obturator internus and the gemelli.
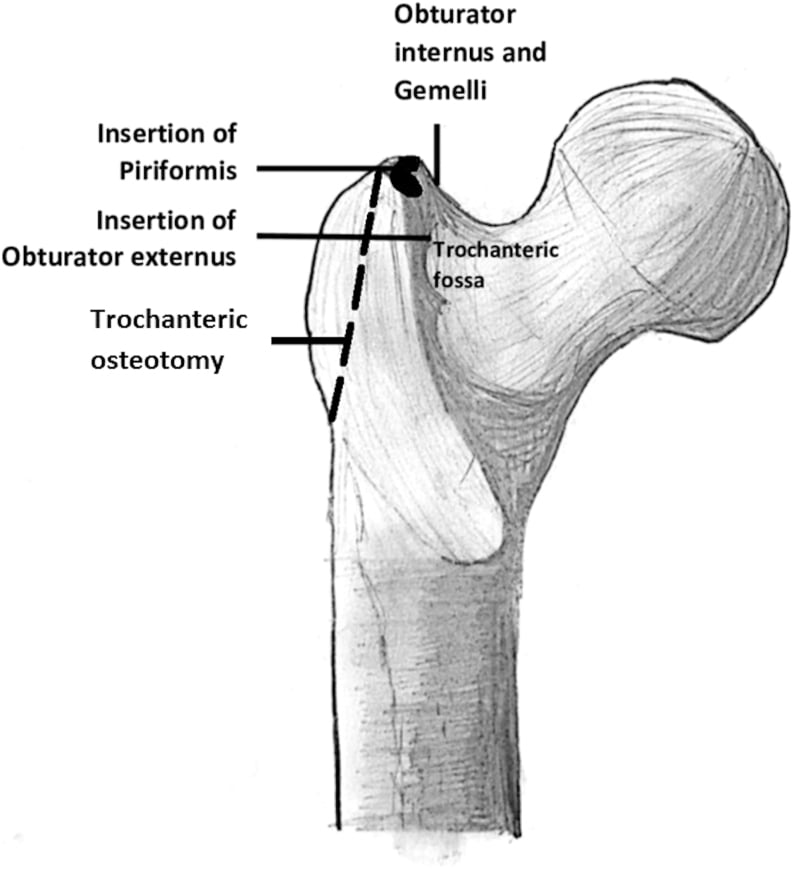
Innervation. The nerve to piriformis (S1, S2, sometimes L5) arises directly from the anterior divisions of the sacral plexus within the pelvis and enters the anterior (deep) surface of the muscle immediately. Because the supply is this direct, the muscle is rarely affected by extra-pelvic pathology, unlike the sciatic nerve.
Action. Piriformis is the primary external rotator of the extended hip. Once the hip is flexed beyond about 60-90 degrees it becomes an abductor.
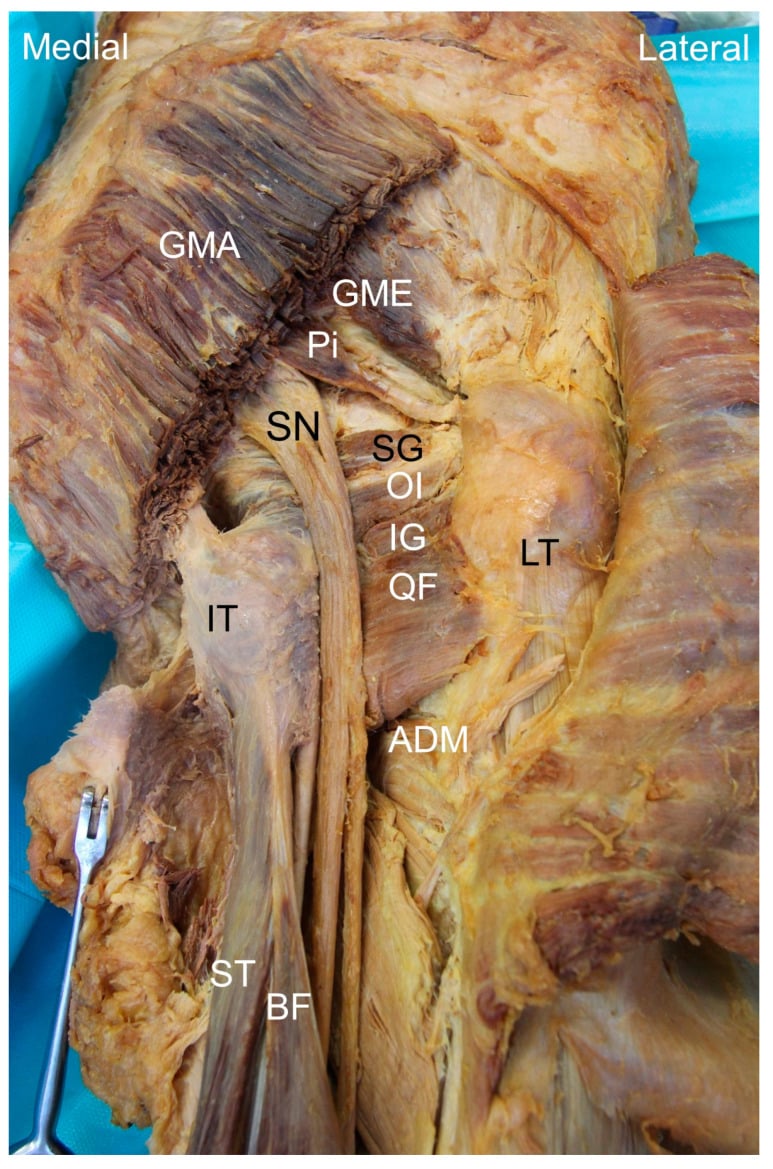
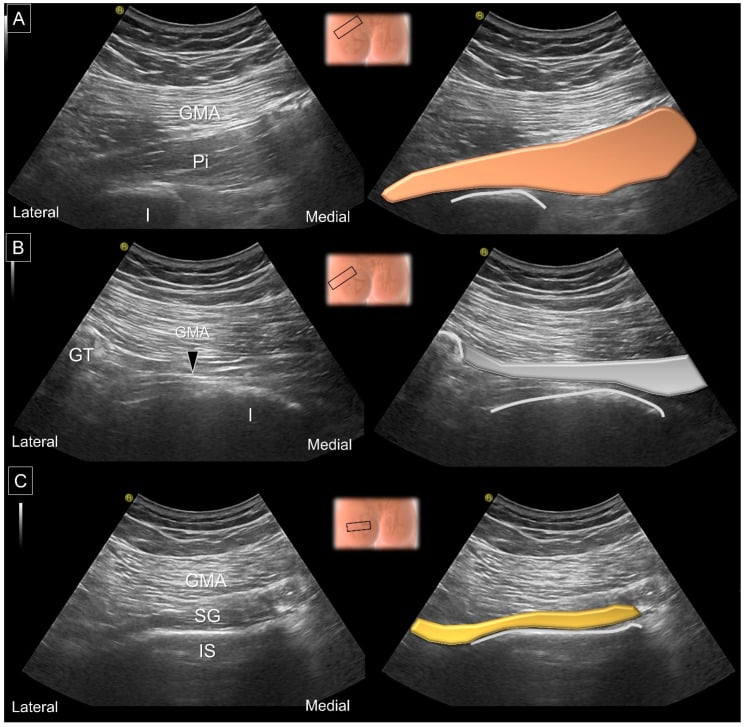
Relations. Gluteus maximus covers the muscle completely behind. In front, on its pelvic surface, lie the sacral plexus and, medially, portions of the rectum. The superior gluteal nerve and artery lie above it; the sciatic nerve, the inferior gluteal neurovascular bundle and the posterior cutaneous nerve of the thigh lie below, and the sciatic nerve typically emerges at the inferior border, deep to the muscle belly.
The two compartments of the foramen. Piriformis divides the greater sciatic foramen in two. The supra-piriform compartment transmits only the superior gluteal nerve and vessels; everything else leaves through the infra-piriform compartment, and the pudendal nerve goes on to Alcock's canal.
- Nerves
- Superior Gluteal
- Vessels
- Superior Gluteal
- Other
- -
- Nerves
- Sciatic, Inf Gluteal, Pudendal, Post Cutaneous Thigh, N to OI/QF
- Vessels
- Inferior Gluteal, Internal Pudendal
- Other
- Pudendal N goes to Alcock's canal
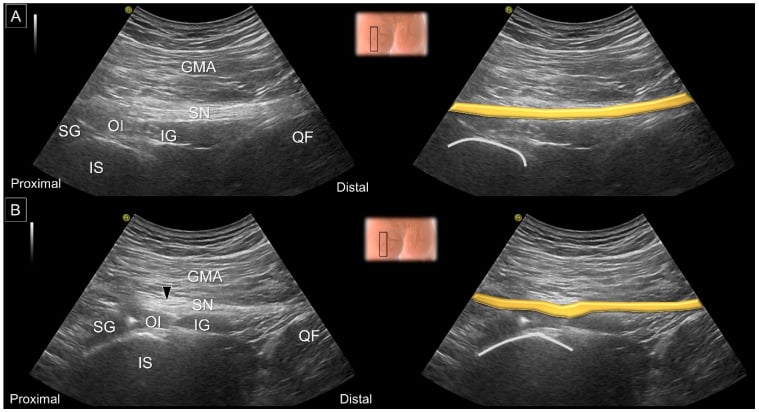
The short external rotators. Below piriformis the short rotators follow caudally in order: superior gemellus, obturator internus, inferior gemellus and quadratus femoris. Obturator externus is not part of this row; it lies deeper, at the trochanteric fossa.
Surface Anatomy
The piriformis line. Draw a line from the posterior superior iliac spine (PSIS) to the greater trochanter; the superior border of piriformis roughly corresponds to it.
Palpation. Deep palpation in the mid-buttock, midway between the PSIS and the greater trochanter, may elicit tenderness in piriformis syndrome, but direct palpation is difficult through the overlying gluteus maximus. Palpating with the patient seated, hip flexed, may make the muscle more accessible as it emerges from under gluteus maximus. Tenderness at the greater sciatic notch is a sensitive sign of deep gluteal pathology.
The piriformis fossa in antegrade nailing. The piriformis fossa is a classic landmark for antegrade femoral nailing, and examiners probe both the choice of entry and a naming catch. There are two antegrade start points:
- Piriformis fossa - the depression just medial to the tip of the greater trochanter, collinear with the femoral canal and shaft axis, suited to a straight nail
- Greater-trochanter tip - suited to a trochanteric-entry nail with a proximal bend
The risk of a medial start. A piriformis-fossa start point that is too medial or too posterior endangers the medial femoral circumflex artery and the femoral-head blood supply, a recognised cause of avascular necrosis. That is why piriformis-entry antegrade nailing is avoided in children and adolescents, in whom a trochanteric or more lateral entry is preferred to protect the still-vulnerable supply. The start point also lies close to the abductors and the superior gluteal nerve.
The nomenclature trap. The piriformis tendon actually inserts on the greater trochanter, so the "piriformis fossa" entry, the trochanteric or digital fossa medial to the tip, is a slight misnomer and a favourite exam catch.
Pathology: Piriformis Syndrome
Piriformis syndrome is extra-spinal sciatica. The sciatic nerve, usually its peroneal division, is compressed by the muscle belly or tendon. The peroneal division is more lateral and susceptible to compression against the ischium.
Aetiology. Causes are primary or secondary:
- Primary - an anatomical anomaly (Beaton type B); less than 15%
- Secondary - macrotrauma (a fall on the buttock), microtrauma (wallet neuritis, overuse) or hypertrophy
Presentation. The pain is a deep ache in the buttock, radiating down the posterior thigh and leg as sciatica but usually sparing the foot, unlike true discogenic sciatica. It worsens after sitting for 20 minutes and on walking up stairs or inclines.
The straight leg raise. Typically the SLR is negative or positive only at the extremes of range, unlike a disc herniation.
Classification Systems
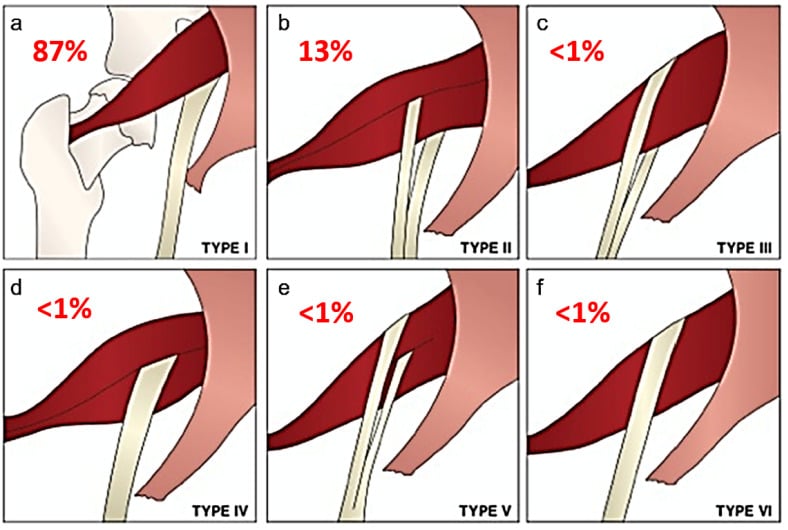
Beaton and Anson. The classification describes the relationship of the sciatic nerve to piriformis, by whether the nerve is split into its common peroneal (CPN) and tibial (TN) divisions and where each passes:
- Type A (unsplit) - the whole nerve passes below piriformis; normal, 85-90%
- Type B (split) - the CPN pierces piriformis and the TN passes below
- Type C (split) - the CPN passes above and the TN below
- Type D (unsplit) - the entire nerve pierces the muscle; rare
- Type E (split) - the CPN passes above and the TN pierces the muscle; very rare
- Type F (unsplit) - the entire nerve passes above the muscle; extremely rare
How often the nerve is abnormal. Smoll's pooled cadaveric meta-analysis put the prevalence of an anomaly at 16.9%, which leaves type A at about 83%, a little under the figure above. In up to 15-20% of cases the sciatic nerve, or its common peroneal division, passes through or above the muscle.
Type B and the syndrome. Type B is the most common variant and predisposes to entrapment. A piriformis-sciatic anomaly is, however, not more frequent in patients with piriformis syndrome than in cadavers (Smoll), so the anatomy alone does not explain the syndrome.
Clinical Assessment
Provocative tests. The named provocation tests are:
- FAIR test - flexion, adduction and internal rotation stretch the piriformis and compress the sciatic nerve; pain is positive
- Pace's sign - pain and weakness on resisted abduction and external rotation of the thigh, sitting
- Freiberg's sign - pain on passive internal rotation of the extended hip
Deep gluteal syndrome. Piriformis syndrome is one subset of deep gluteal syndrome; the others include gemelli-obturator internus syndrome, ischiofemoral impingement and proximal hamstring tendinopathy. The point of maximal tenderness and the exact provocation manoeuvres help distinguish them.
- Distinguishing feature
- Buttock pain, sitting intolerance, notch tenderness; foot usually spared
- Key test / finding
- FAIR test; relief after image-guided block
- Distinguishing feature
- Dermatomal pain often to foot; back pain; positive neural tension
- Key test / finding
- Positive SLR; MRI lumbar spine; EMG paraspinal changes
- Distinguishing feature
- Pain in the ischiofemoral space; long-stride pain
- Key test / finding
- Narrowed ischiofemoral and quadratus femoris space on MRI; quadratus femoris oedema
- Distinguishing feature
- Ischial tuberosity pain on sitting and loading
- Key test / finding
- Tenderness at ischium; MRI tendinopathy or avulsion
- Distinguishing feature
- Deep gluteal pain; part of deep gluteal syndrome spectrum
- Key test / finding
- Tenderness more inferolateral; endoscopic findings
- Distinguishing feature
- Pain over the SIJ, rarely below knee
- Key test / finding
- Cluster of provocation tests; diagnostic SIJ block
Investigations
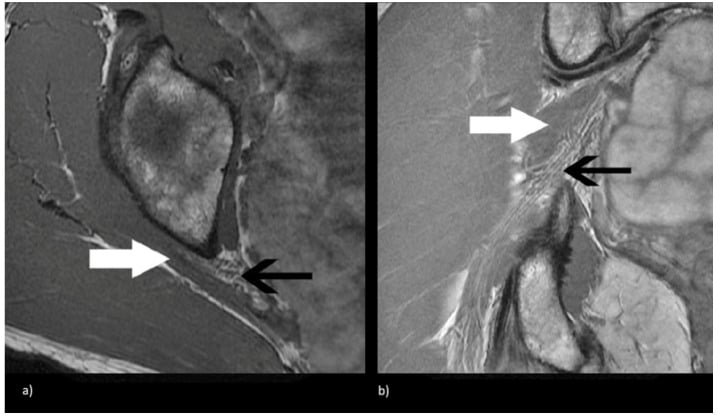
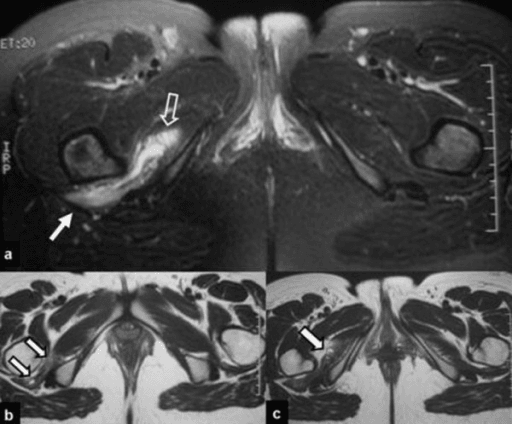
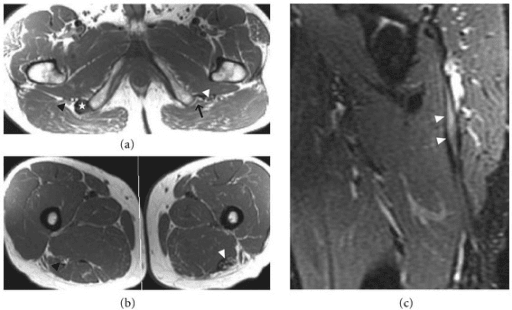
MR neurography. This is the gold-standard imaging test. It can show piriformis hypertrophy or asymmetry and an anomalous course of the nerve, and increased signal in the sciatic nerve on T2 indicates neuritis.
Diagnostic injection. Local anaesthetic is injected into the muscle belly under CT or ultrasound guidance. Immediate relief of the sciatic symptoms is a positive test and confirms the diagnosis; the block is often considered the most definitive confirmation.
Electrophysiology. EMG is usually normal in early changes. The H-reflex may be delayed on the affected side when the hip is held in the FAIR position (dynamic testing). EMG helps rule out L5/S1 radiculopathy, because the paraspinal muscles should be normal in piriformis syndrome.
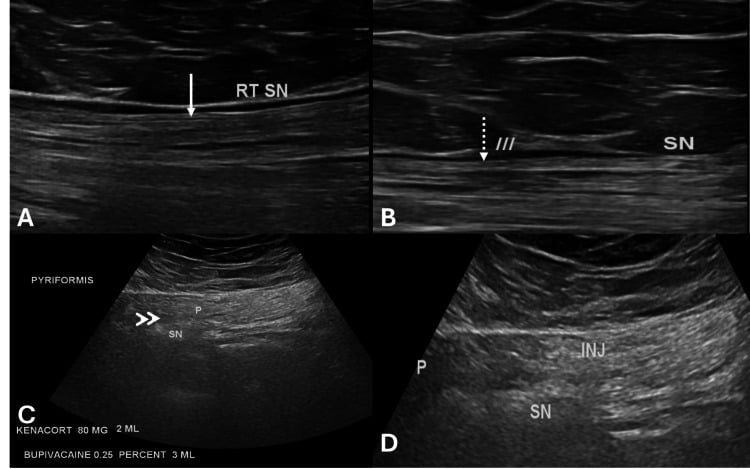
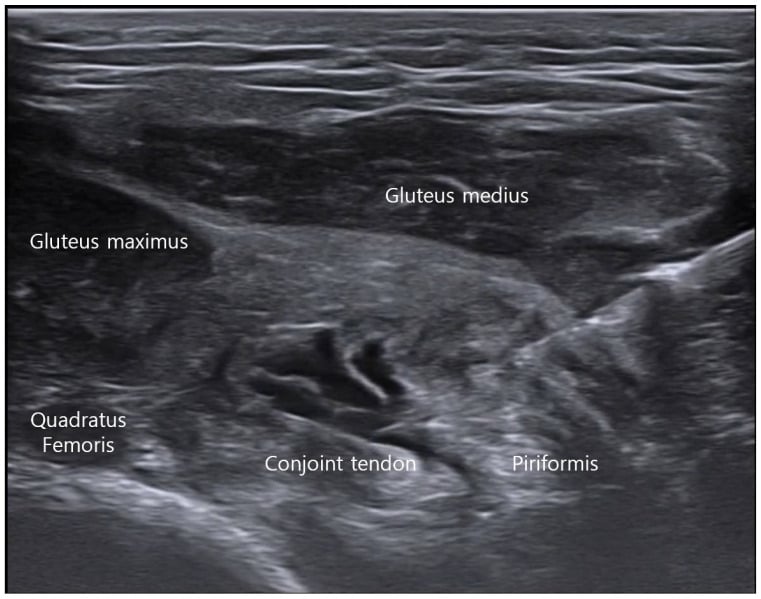
Management
Treatment escalates by stage.
- Treatment
- Rest, NSAIDs, Stretching
- Evidence
- First line. 70% success.
- Treatment
- Physiotherapy (gluteal strengthening)
- Evidence
- Address biomechanics.
- Treatment
- Injection (Steroid/Botox)
- Evidence
- Diagnostic and Therapeutic.
- Treatment
- Surgical Release
- Evidence
- Last resort.
Botulinum toxin. It paralyses the muscle, inducing atrophy and relieving the compression, and its effects last 3-6 months.
When to operate. Surgical release should only be considered after failure of at least 6 months of conservative therapy.
Surgical Technique
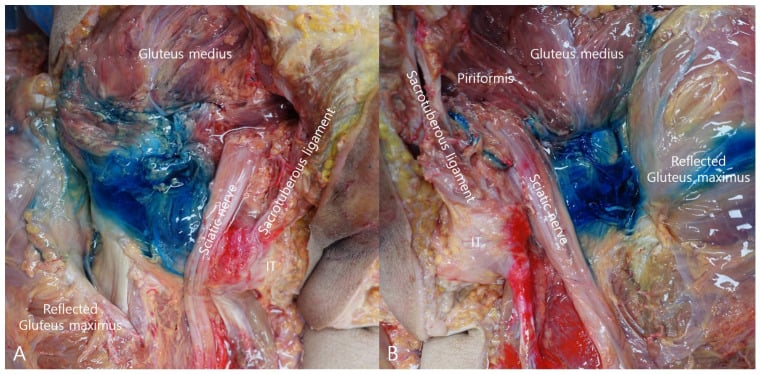
Piriformis release. The indication is failure of conservative management with a positive diagnostic block. The approach is posterior (Kocher-Langenbeck) or endoscopic, and endoscopic release is becoming increasingly common because of its lower morbidity. The steps:
- Identify the sciatic nerve distally.
- Trace it proximally to the inferior border of piriformis.
- Identify any bands or a split nerve (type B).
- Tenotomise piriformis at the reflected tendon (insertion).
- Observe decompression of the nerve.
Protect the superior gluteal vessels superiorly.
In the posterior hip approach. Piriformis is a key landmark, usually the highest tendon identifiable; the gemelli are smaller. Its tendon is tagged and released to mobilise the femur and is often repaired at the end of surgery to restore stability. "Find the nerve, then find the muscle" is a safe adage.
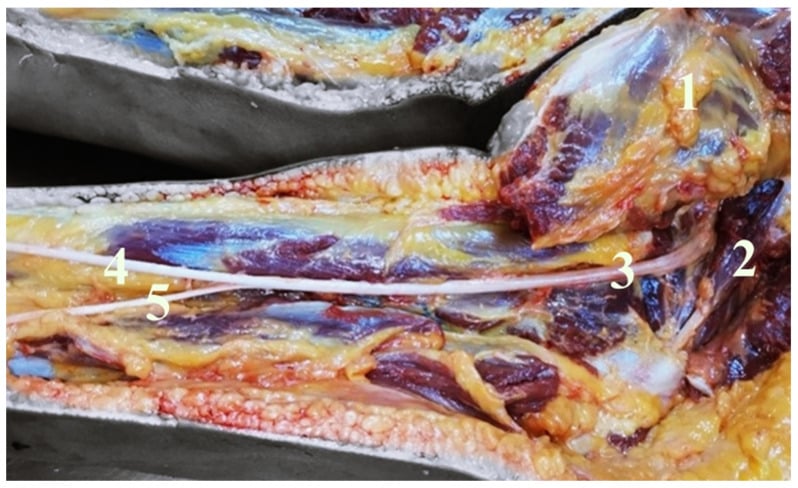
The aberrant sciatic nerve. Blind dissection or retractor placement can injure a nerve that runs through or above the muscle. Identify the nerve early, especially if the anatomy looks abnormal.
The superior gluteal artery. It exits the notch just superior to piriformis. Vigorous retraction or blind placement of a Charnley retractor pin into the ilium can lacerate it, and the artery retracts into the pelvis, so the result is massive haemorrhage within the pelvis.
The medial femoral circumflex artery. The deep branch of the MFCA is the dominant blood supply to the adult femoral head, continuing as the lateral epiphyseal (retinacular) vessels, and its constant relationship to the short external rotators is examinable. It runs along the inferior border of obturator internus and the gemelli, then crosses deep (anterior) to the obturator externus tendon before piercing the capsule near the superior border of the gemelli.
What may be divided. Releasing piriformis and the conjoint tendon (obturator internus plus gemelli) is safe, but the obturator externus tendon must be preserved because it shields the MFCA. The Ganz surgical hip dislocation is built around keeping obturator externus intact. The danger zone is aggressive dissection at the quadratus femoris and lesser-trochanter region, or dividing obturator externus, which can injure the MFCA and cause avascular necrosis of the femoral head.
Complications
The complications of release and of the posterior approach are:
- Sciatic nerve injury - direct trauma or traction
- Bleeding - the inferior gluteal vessels are often adherent to the deep surface
- Incomplete release - failure to identify anomalous bands
- Instability - after total hip replacement, failure of the repair increases the risk of posterior dislocation
Rehabilitation Protocol
After release the patient bears weight immediately but avoids deep flexion and stretching for 2 weeks. Gentle neural gliding exercises start at week 2. Gluteus maximus and medius strengthening aims to correct pelvic mechanics.
Prognosis
Conservative treatment gives variable results, and stretching works for mild cases. An injection gives good short-term relief and predicts surgical success. Surgery succeeds in 80-90% of properly selected patients, those with a positive block.
Guidelines, Registries & Global Practice
Global epidemiology. Piriformis syndrome is cited as a cause in roughly 5-6% of patients presenting with sciatica, though this figure is contested because the diagnosis lacks an accepted reference standard. A piriformis-sciatic nerve anatomical anomaly is present in about 17% of cadavers worldwide (Smoll meta-analysis) but is not over-represented in symptomatic patients. Female predominance is reported in most series, often quoted around 2:1 to 6:1.
Society Positions on Diagnosis and Management
- Diagnostic stance
- Diagnosis of exclusion; image-guided diagnostic block central
- Management emphasis
- Conservative first; ultrasound-guided injection; endoscopic release in refractory deep gluteal syndrome
- Diagnostic stance
- Sciatica pathway prioritises excluding lumbar disc/stenosis; piriformis labelled when spine is normal
- Management emphasis
- Physiotherapy and activity advice first-line; injection and surgery reserved for failures
- Diagnostic stance
- Subset of deep gluteal syndrome; favours MR neurography where available
- Management emphasis
- Stepwise: physiotherapy, image-guided injection (steroid or botulinum toxin), then endoscopic decompression
- Diagnostic stance
- Piriformis is the key landmark in the Kocher-Langenbeck and posterior hip approaches
- Management emphasis
- Identify and protect sciatic nerve at the inferior border; repair short external rotators to lower posterior dislocation risk
Registry and Outcome Notes
- Arthroplasty registries (NJR-UK, AJRR-USA, AOANJRR-Australia, SHAR-Sweden): do not track piriformis pathology directly, but record nerve-injury and dislocation outcomes relevant to the posterior approach where the piriformis is released and repaired. Sciatic/peroneal palsy after primary THA is consistently rare (around 0.1-1%).
- Posterior approach: remains the most common worldwide workhorse exposure; soft-tissue (capsule and short external rotator) repair is associated with reduced posterior dislocation in registry and cohort data.
High- vs Limited-Resource Practice Variation
- High-resource settings: MR neurography, ultrasound-guided injection, and endoscopic deep gluteal decompression are available; diagnosis is refined with dynamic imaging.
- Limited-resource settings: diagnosis is clinical (symptom quartet plus provocative tests); landmark or fluoroscopic injection and open release predominate, with greater reliance on physiotherapy and activity modification.
Controversies & Areas of Uncertainty
Some authors argue piriformis syndrome is over-diagnosed and that most "extra-spinal sciatica" is better captured by the broader term deep gluteal syndrome. The anatomical anomaly is not more common in symptomatic patients (Smoll), undermining a purely structural explanation.
There is no accepted reference standard. FAIR, Pace and Freiberg signs have limited and poorly quantified accuracy. Response to an image-guided diagnostic block is the most relied-upon confirmation but is not formally validated.
MR neurography can show piriformis asymmetry, sciatic nerve hyperintensity and anomalous course, but findings overlap with asymptomatic individuals, so imaging supports rather than establishes the diagnosis.
Randomised data (Fishman) favour botulinum toxin A over steroid, but trials are small and heterogeneous; optimal dose, target (belly vs tendon) and guidance modality remain debated.
MCQ Practice Points
Q: Which structure exits the Greater Sciatic Foramen SUPERIOR to the Piriformis? A: Superior Gluteal Nerve and Vessels. Everything else is inferior.
Q: What is the action of the Piriformis when the hip is flexed to 90 degrees? A: Abduction. In extension, it is an External Rotator.
Q: The Nerve to Piriformis is derived from which segments? A: S1 and S2. (Anterior rami).
Q: In the Beaton Type B anomaly, which component of the sciatic nerve pierces the muscle? A: Common Peroneal Nerve. The Tibial nerve passes inferiorly.
Q: Where does the Piriformis originate? A: Anterior surface of the Sacrum.
Viva Scenarios
Practise clinical reasoning and management decisions out loud
“You are performing a posterior approach for a THR. You see the short external rotators. How do you identify the Piriformis?”
“45F with 6 months of buttock and posterior leg pain. MRI Lumbar Spine is normal. What is your differential?”
“During a sciatic nerve exploration, you find the Common Peroneal Nerve passing THROUGH the piriformis. What type of anomaly is this?”
Anatomy
- Origin: Anterior Sacrum
- Insert: Superior GT
- Nerve: N to Piriformis (S1-2)
- Passes: Greater Sciatic Foramen
Relationships
- Superior: Sup Gluteal N/A
- Inferior: Sciatic N, Inf Gluteal
- Anterior: Sacral Plexus
- Posterior: Gluteus Maximus
Clinical
- Action: ER (Ext), Abd (Flex)
- Test: FAIR Test
- Syndrome: Sciatica + Normal MRI
- Variant: CPN pierces (Type B)
Evidence Base
The key conceptual point comes from Smoll's meta-analysis — the piriformis-sciatic anomaly is common (~17%) but NOT more frequent in symptomatic patients, so the anomaly alone does not explain the syndrome. The remaining studies anchor diagnosis (Hopayian's four features), injection accuracy (Finnoff — ultrasound far better than fluoroscopy), treatment (Fishman botulinum toxin; Kay deep-gluteal decompression), and the THA nerve-palsy risk that makes the piriformis landmark surgically important (Farrell).
Botulinum Toxin A and Physical Therapy
- Double-blind placebo-controlled trial using electrophysiologic (FAIR-test H-reflex) selection
- Botulinum toxin A gave more pain relief than lidocaine-plus-steroid (P less than 0.05) and than placebo (P = 0.001) on the visual analog scale
- H-reflex prolongation over 1.86 msec (3 SD) in the FAIR position was a clinical indicator of piriformis syndrome
Piriformis and Sciatic Nerve Variation Meta-analysis
- Systematic review and meta-analysis pooling 18 studies and 6,062 cadavers
- Pooled prevalence of a piriformis-sciatic nerve anomaly was 16.9% (95% CI 16.0-17.9%)
- Anomaly prevalence in piriformis-syndrome surgical series (16.2%) did not differ significantly from cadavers (P = 0.824)
Surgical Management of Deep Gluteal Syndrome
- Systematic review of 28 studies (481 patients) on surgery for sciatic nerve entrapment in deep gluteal syndrome
- Commonest causes: iatrogenic (30%), piriformis syndrome (26%), trauma (15%), non-piriformis muscle pathology (14%)
- Improvement in pain at final follow-up reported in all 28 studies; endoscopic procedures had major complications in 0% and minor in fewer than 1%