Risk Stratification | Cardiovascular Assessment | Medication Management | Functional Capacity
- Functional capacity under 4 METs predicts increased perioperative cardiac complications
- Beta-blockers should NOT be started perioperatively - increased stroke risk (POISE trial)
- Metformin is traditionally held on the day of surgery to reduce lactic acidosis risk
- Aspirin continuation recommended for patients with coronary stents in past 12 months
- Delay elective surgery 4-6 weeks after acute MI or coronary intervention
- “RCRI score (Revised Cardiac Risk Index) stratifies cardiac risk - 6 predictors
- “Stop smoking minimum 4 weeks before surgery for wound healing benefit
- “HbA1c greater than 8.5% associated with increased infection and complications
- “Patients on oral anticoagulants need bridging plan individualized to thrombotic risk
Overview
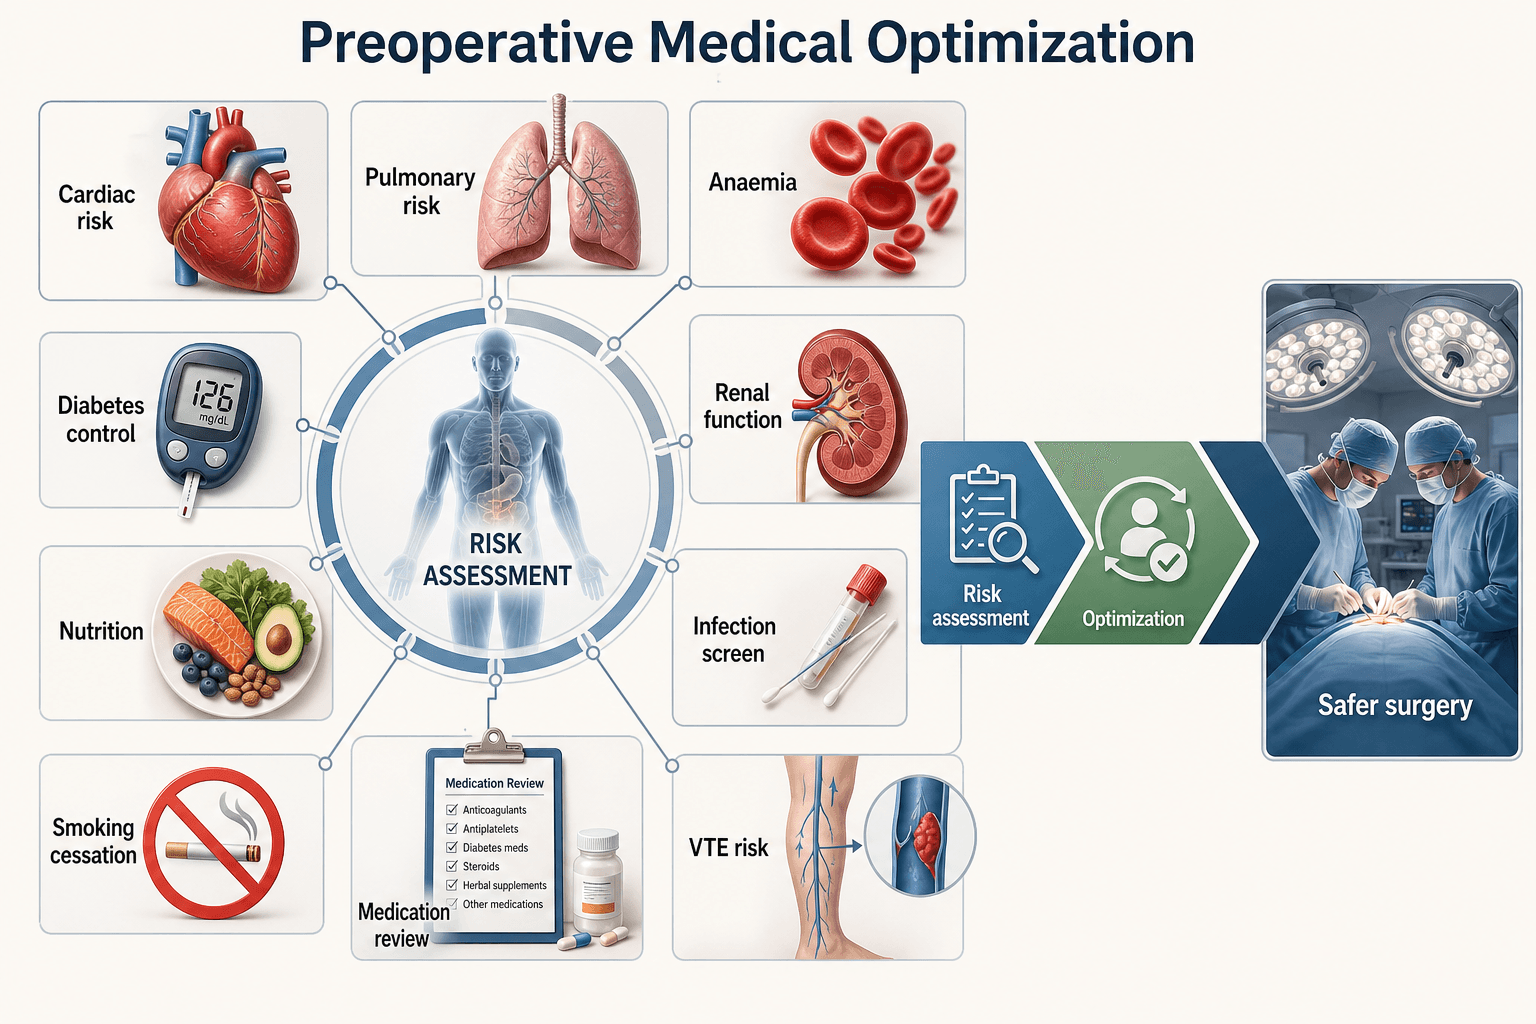
Preoperative medical optimisation is the structured process of identifying, quantifying and modifying a patient's medical risk before elective or semi-elective surgery. The aim is to reach the best achievable physiological state rather than to clear every abnormality, to communicate the risk for informed consent, and to plan the right level of perioperative monitoring.
It is a high-yield non-operative topic for the orthopaedic candidate, and it recurs across the MCQ, viva and clinical components because the same principles apply to elective arthroplasty, fracture surgery and revision procedures.
Three questions. Every assessment answers the same three:
- How fit is the patient? ASA grade and functional capacity in METs
- What is the risk of this operation? Cardiac, pulmonary, bleeding and infection risk
- What can be modified before surgery? Glycaemic control, anaemia, smoking, anticoagulation and cardiac medication
Stratify, then optimise. ASA, RCRI and functional capacity together place the patient in a low, intermediate or high-risk band, and the band decides who needs cardiology, CPET or biomarker input. Optimisation then targets the modifiable factors with the strongest evidence (smoking, glycaemic control, anaemia and a clear plan for interrupting and resuming medication) and ends with the postoperative level of care, ward or HDU/ICU.
Principles of Risk Stratification
ASA physical status. The ASA grade is the first summary of how fit the patient is, and each grade carries a perioperative plan.
- Definition
- Healthy patient
- Examples
- No organic, physiologic, biochemical abnormality
- Perioperative Management
- Routine perioperative care
- Definition
- Mild systemic disease
- Examples
- Well-controlled HTN, BMI 30-40, social smoker
- Perioperative Management
- Standard care with monitoring
- Definition
- Severe systemic disease
- Examples
- Poorly controlled DM, COPD, BMI greater than 40, active smoker
- Perioperative Management
- Preoperative optimisation, HDU consideration
- Definition
- Life-threatening disease
- Examples
- Recent MI under 3 months, sepsis, ESRF
- Perioperative Management
- ICU planning, intensivist involvement
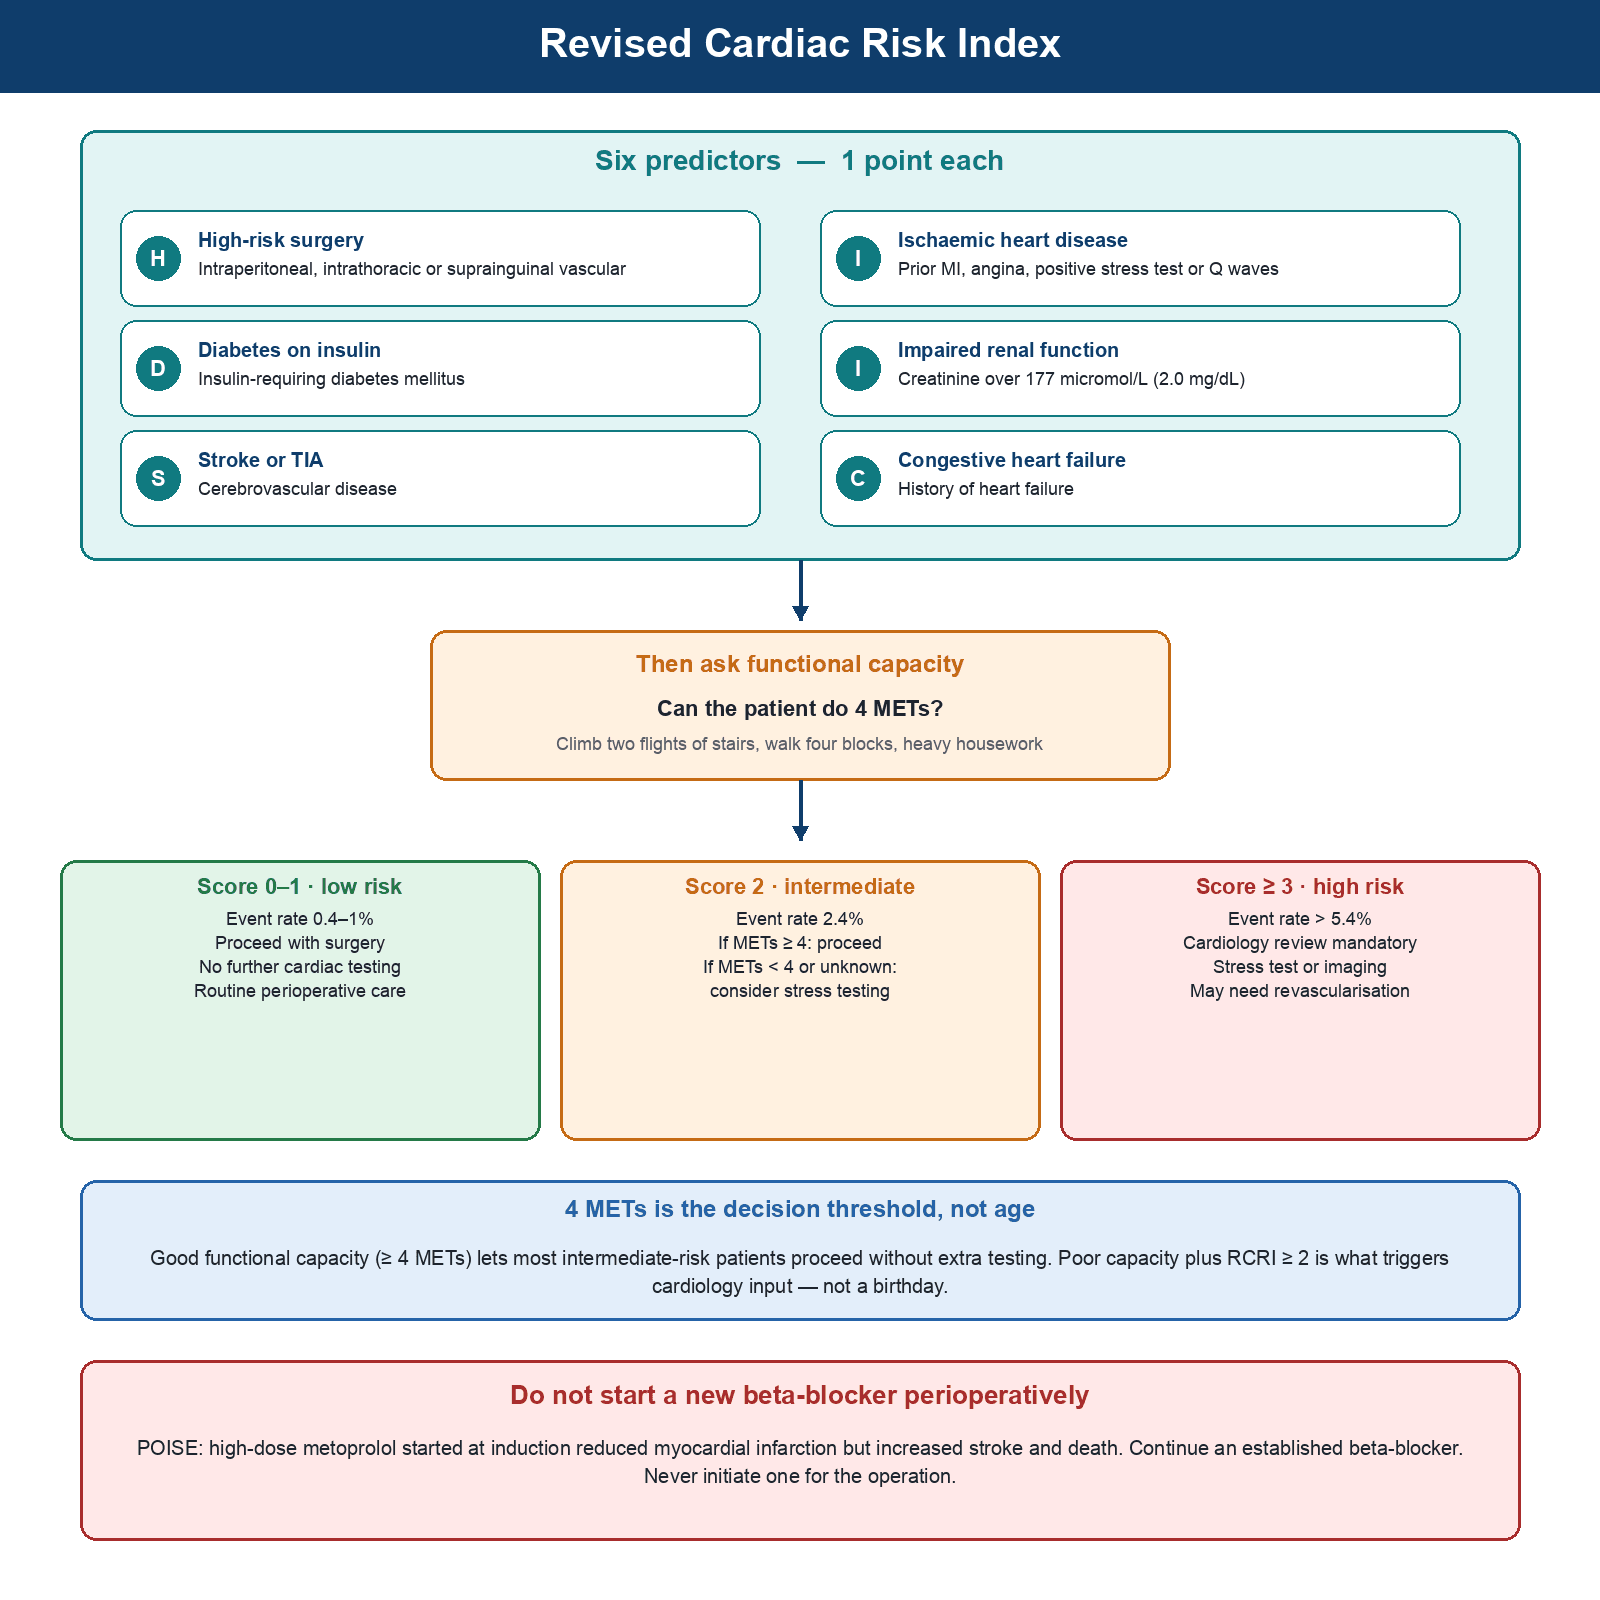
The Revised Cardiac Risk Index. The RCRI is the gold standard for cardiac risk. It has six predictors, each scoring one point:
HI DISCRCRI - 6 Predictors
Hook:One point for each. Hypertension is not one of them.
What the score means. The total sets the event rate and the next step.
- Event rate
- 0.4-1%
- Management
- Proceed with surgery. No further cardiac testing; routine perioperative care.
- Event rate
- 2.4%
- Management
- Consider cardiology consultation. Assess functional capacity: above 4 METs, proceed; under 4 METs or unknown, consider stress testing.
- Event rate
- greater than 5.4%
- Management
- Cardiology consultation mandatory, with functional capacity assessment and stress testing or coronary imaging. May need coronary revascularisation before surgery.
Functional capacity. 4 METs is the critical threshold: the effort of climbing 2 flights of stairs, walking 4 blocks on level ground or doing heavy housework. Patients who cannot reach 4 METs have significantly increased perioperative cardiac complications and need further evaluation before major surgery. Capacity is read with the score, and age alone does not trigger a stress test.
Who needs stress testing.
- RCRI score 2 or more with functional capacity under 4 METs
- Recent MI (4-6 weeks ago) before elective surgery
- Unstable angina or decompensated heart failure
- High-risk surgery (vascular, prolonged)
Who does not. Testing is unnecessary with:
- Good functional capacity (above 4 METs), regardless of RCRI
- Low-risk surgery (arthroscopy, minor procedures)
- A stress test within the past year and no change in status
- An asymptomatic ASA 1-2 patient
Respiratory Optimisation
ARISCAT. Pulmonary risk is scored with ARISCAT, which awards points for the factors below.
- Points
- 3 points
- Clinical Significance
- Decreased respiratory reserve
- Points
- 16 points
- Clinical Significance
- High risk group
- Points
- 8 points
- Clinical Significance
- Baseline hypoxaemia
- Points
- 17 points
- Clinical Significance
- Active inflammation
- Points
- 11 points
- Clinical Significance
- Impaired oxygen delivery
- Points
- 15 points
- Clinical Significance
- Direct pulmonary impact
Smoking cessation. The benefit accrues with time off cigarettes:
- 48-72 hours: carbon monoxide levels fall and oxygen-carrying capacity improves
- 4 weeks: mucociliary function improves, sputum volume normalises and postoperative pulmonary complications fall by 20%
- 8 weeks, the optimum: wound complications are significantly reduced, immune function improves and cardiovascular benefits are established
Cessation under 4 weeks may INCREASE pulmonary complications because sputum production increases. A minimum of 4 weeks is required for benefit. If the patient cannot stop 4 or more weeks before, continue smoking up to surgery rather than stopping 1-2 weeks before.
Helping the patient stop. Motivational interviewing is combined with pharmacotherapy (nicotine replacement as patches, gum or lozenges, varenicline or bupropion) and referral to a national smoking-cessation or quitline service.
Perioperatively. Expect increased airway reactivity and use bronchodilators. Target SpO2 above 95%, with aggressive pulmonary toilet and early mobilisation.
Laboratory and Investigation Optimisation
Targeted testing. Preoperative investigations are driven by the history, examination and planned surgery, and requested selectively to detect and optimise modifiable disease before anaesthesia. Routine testing in healthy ASA 1-2 patients undergoing low-risk procedures does not improve outcomes and delays surgery, so test on comorbidity and procedure risk rather than age alone. International guidance (NICE, ANZCA, ESA) converges on no routine testing for fit ASA 1-2 patients undergoing minor surgery.
- ASA 1-2 Under 40
- Not routine
- ASA 1-2 Over 40
- If significant blood loss expected
- ASA 3-4 Any Age
- Always
- ASA 1-2 Under 40
- Not routine
- ASA 1-2 Over 40
- If on ACE-I, diuretics, diabetes
- ASA 3-4 Any Age
- Always
- ASA 1-2 Under 40
- Not routine
- ASA 1-2 Over 40
- If diabetic or obese
- ASA 3-4 Any Age
- Always
- ASA 1-2 Under 40
- Only if bleeding history
- ASA 1-2 Over 40
- If on anticoagulation
- ASA 3-4 Any Age
- If liver disease or anticoagulated
- ASA 1-2 Under 40
- Not routine
- ASA 1-2 Over 40
- Over 45 or cardiac history
- ASA 3-4 Any Age
- Always
- ASA 1-2 Under 40
- Not routine
- ASA 1-2 Over 40
- If cardiopulmonary symptoms
- ASA 3-4 Any Age
- If moderate-severe lung/cardiac disease
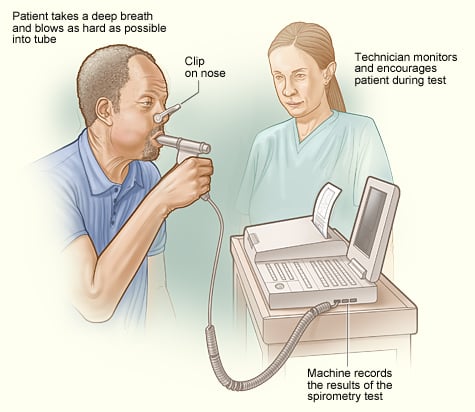
Preoperative anaemia. Treating anaemia before surgery reduces transfusion requirements and improves outcomes. The work-up starts 4-6 weeks before surgery.
- Identify: screen high-risk patients (age over 65, known CKD, inflammatory arthritis, previous transfusion) with FBC, iron studies (ferritin, transferrin saturation), B12 and folate.
- Find the cause: iron deficiency (ferritin under 30 or TSAT under 20%), chronic disease (high ferritin, low TSAT), B12 or folate deficiency (macrocytic anaemia), or CKD (low EPO production).
- Treat for at least 4 weeks: oral iron 200mg elemental iron daily, or IV iron (Ferinject 1000mg) if oral iron is not tolerated or time is critical; IM hydroxocobalamin for B12 deficiency; EPO if CKD and Hb under 100.
- Recheck 1 week before: expect an Hb rise of 10-20 g/L with 4 weeks of treatment and document it. Plan transfusion if Hb is still under threshold and surgery cannot be delayed.
Medication Management
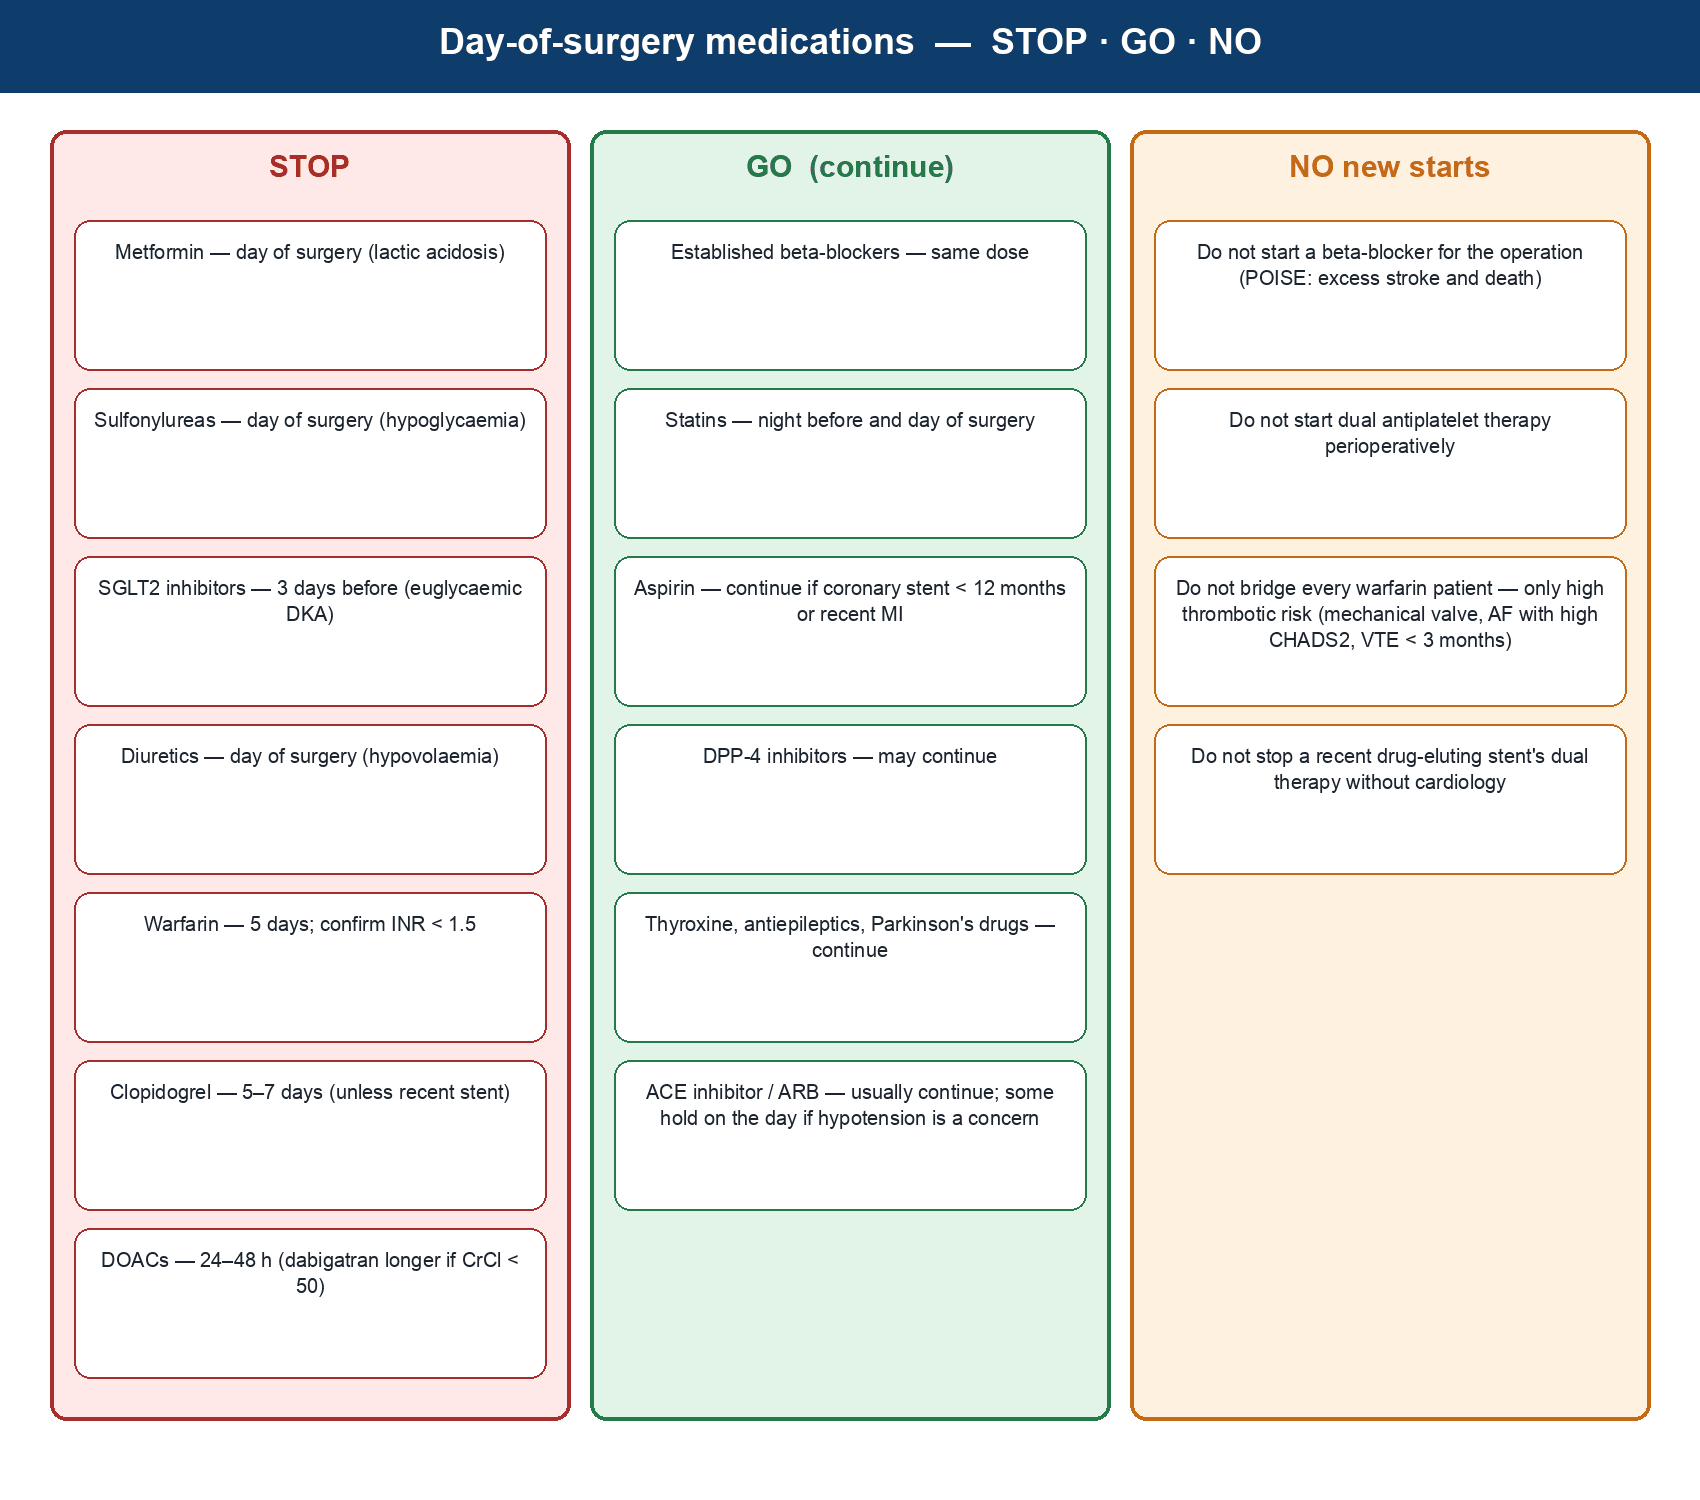
Day-of-surgery medication is sorted into three groups: stop it, continue it, or never start it for the operation.
Warfarin. Thrombotic risk decides whether the interruption is bridged. A mechanical heart valve, atrial fibrillation with CHADS2 greater than 4, or VTE within 3 months is high risk and is bridged with LMWH.
- 5 days before: stop warfarin, check the INR and assess thrombotic risk.
- Day before surgery: confirm INR under 1.5. If it is still elevated, consider vitamin K 1-2 mg orally. If bridging, the last LMWH dose is 24 hours before surgery.
- Day of surgery: an INR under 1.5 is needed for neuraxial anaesthesia. Proceed, and document that haemostasis is achieved.
- 12-24 hours after: resume warfarin the evening of surgery or the next morning if haemostasis is good. Restart LMWH bridging 24 hours postoperatively if thrombotic risk is high.
Antiplatelets. Aspirin is usually continued, especially with a coronary stent under 12 months old or a recent MI, and neurosurgery is the exception. In a stented patient, any change to dual therapy needs cardiology.
- Mechanism
- COX-1 irreversible inhibitor
- Stop Before Surgery
- 7 days (context-dependent)
- Special Considerations
- CONTINUE if coronary stent under 12 months or recent MI
- Mechanism
- P2Y12 inhibitor
- Stop Before Surgery
- 5-7 days
- Special Considerations
- Dual antiplatelet if stent - cardiology consult required
- Mechanism
- Reversible P2Y12 inhibitor
- Stop Before Surgery
- 5 days
- Special Considerations
- Faster offset than clopidogrel - useful for urgent surgery
- Mechanism
- P2Y12 inhibitor
- Stop Before Surgery
- 7 days
- Special Considerations
- Most potent - highest bleeding risk
Bare metal stent: minimum 30 days dual antiplatelet therapy. Drug-eluting stent: minimum 6-12 months dual antiplatelet therapy. Premature cessation risks stent thrombosis (20-45% mortality). Consult cardiology before stopping - may continue aspirin + clopidogrel through surgery for some procedures.
Antiplatelet management is individualised to stent type, timing and thrombotic risk.
DOACs. These are simpler than warfarin: offset is predictable from the half-life and no bridging is required. They are restarted 24-48 hours after surgery once haemostasis is secure.
- Half-life
- 12 hours
- Renal Clearance
- 27%
- Stop Before Surgery
- 24-48h before (CrCl greater than 50)
- Half-life
- 5-9 hours
- Renal Clearance
- 33%
- Stop Before Surgery
- 24-48h before (CrCl greater than 50)
- Half-life
- 12-17 hours
- Renal Clearance
- 80%
- Stop Before Surgery
- 48-72h if CrCl under 50
- Half-life
- 10-14 hours
- Renal Clearance
- 50%
- Stop Before Surgery
- 24-48h before (CrCl greater than 50)
Dabigatran: idarucizumab (Praxbind) - monoclonal antibody, immediate reversal. Xa inhibitors (apixaban, rivaroxaban, edoxaban): andexanet alfa (limited availability) or 4-factor PCC (Prothrombinex).
Insulin. Reduce long-acting basal insulin (glargine, detemir) by 20-25% and hold short-acting bolus insulin, in type 1 and insulin-treated type 2 diabetes alike. In type 1 diabetes, give 5% dextrose with an insulin sliding scale if the patient will be nil by mouth for more than 6 hours, check blood glucose hourly intraoperatively and 2-hourly postoperatively, and target 6-10 mmol/L perioperatively.
Oral agents in type 2 diabetes.
- Metformin: hold on the day of surgery (lactic acidosis risk)
- Sulfonylureas: hold on the day of surgery (hypoglycaemia risk)
- SGLT2 inhibitors: hold 3 days before (DKA risk)
- GLP-1 agonists: hold on the day of surgery
- DPP-4 inhibitors: can continue
The metformin hold is the traditional teaching, and the Controversies section sets out how weak its evidence is.
HbA1c greater than 8.5% (greater than 69 mmol/mol) is associated with significantly increased perioperative complications: infection (2-3x risk), wound dehiscence, prolonged LOS and ICU admission. Consider delaying elective surgery to optimise control; a minimum of 6-8 weeks is needed to improve HbA1c. Discuss risk versus benefit with the patient and anaesthetist.
Cardiovascular drugs. Established cardiac medication is mostly continued, and nothing new is started for the operation.
- Perioperative Action
- CONTINUE
- Rationale
- Withdrawal causes rebound tachycardia and ischaemia. Continue at same dose.
- Perioperative Action
- DO NOT START
- Rationale
- POISE trial: increased stroke and mortality. Only continue if already established.
- Perioperative Action
- CONTINUE (controversial)
- Rationale
- May cause intraoperative hypotension. Some hold on day of surgery. No consensus.
- Perioperative Action
- CONTINUE
- Rationale
- Anti-inflammatory effect. Reduced perioperative MI. Give night before surgery.
- Perioperative Action
- HOLD on day of surgery
- Rationale
- Risk of hypovolaemia and electrolyte disturbance.
Venous Thromboembolism (VTE) Prophylaxis
Stopping and restarting therapeutic anticoagulation is only half of perioperative haematology. Every surgical patient also needs a VTE risk assessment and a prophylaxis plan for the operation itself, and orthopaedic surgery, especially arthroplasty and hip-fracture surgery, is among the highest-risk.
Risk assessment. A structured tool (the Caprini score, or the NICE VTE risk-assessment tool) is weighed against the bleeding risk. Higher VTE risk and lower bleeding risk push towards pharmacological prophylaxis; the reverse favours mechanical methods alone.
- Examples
- Early mobilisation, graduated compression stockings, intermittent pneumatic compression
- Role
- Used in most patients; the sole method when bleeding risk is high
- Examples
- LMWH, fondaparinux, DOAC (rivaroxaban/apixaban/dabigatran), aspirin, warfarin
- Role
- Added for moderate-to-high VTE risk once bleeding risk is acceptable
Duration after arthroplasty. Prophylaxis is extended, roughly 28 to 35 days after total hip replacement and about 10 to 14 days after total knee replacement, and it is also standard for hip-fracture surgery.
Choice of agent. This is debated. LMWH and the DOACs are effective, and aspirin has gained favour after arthroplasty, with large trials suggesting broad equivalence for many patients; efficacy is balanced against wound-bleeding risk. The highest-risk joints get mechanical and pharmacological prophylaxis combined, with the first pharmacological dose timed to balance VTE prevention against postoperative bleeding.
Fasting, Prehabilitation and Enhanced Recovery (ERAS)
The way the patient is prepared for surgery and recovered from it also changes outcomes. Fasting, prehabilitation and the ERAS bundle are frequently examined.
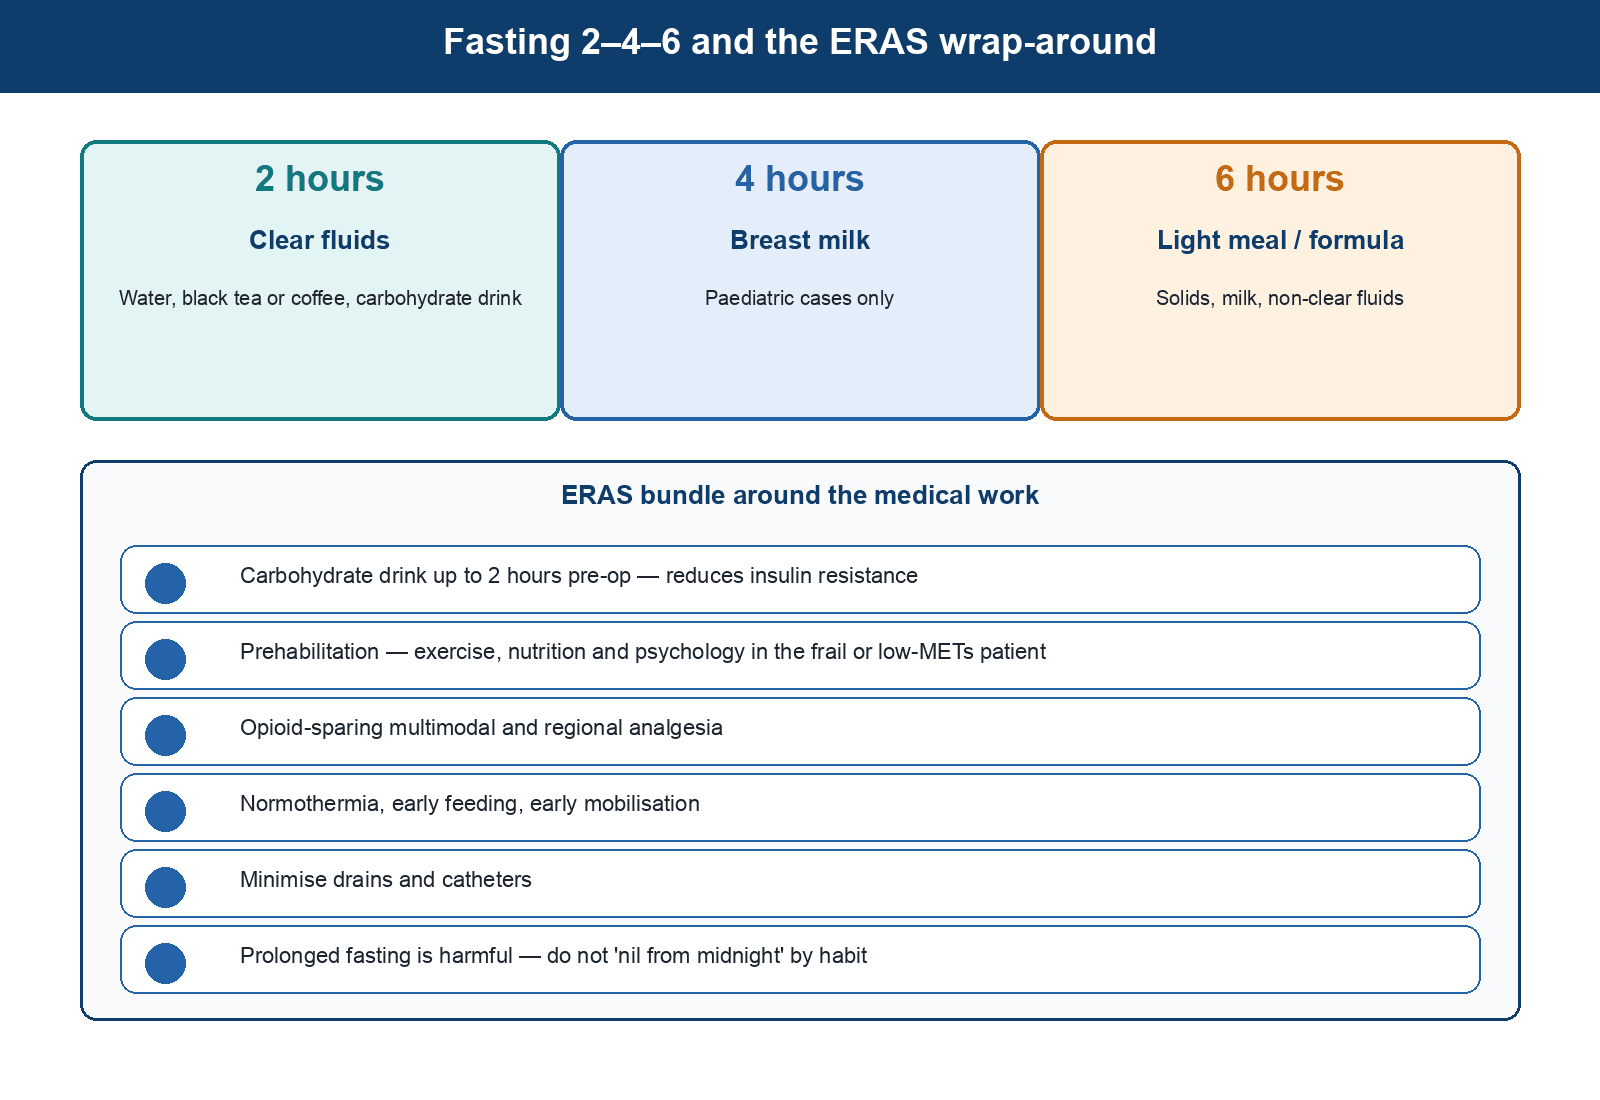
Fasting: the 2-4-6 rule. Before anaesthesia:
- Clear fluids up to 2 hours
- Breast milk up to 4 hours
- A light meal, non-clear fluids or formula up to 6 hours
Prolonged fasting is harmful (dehydration, insulin resistance, patient discomfort) and should be avoided.
Carbohydrate loading. A clear carbohydrate drink up to about 2 hours preoperatively reduces insulin resistance and improves patient well-being, and it is a core ERAS element.
Prehabilitation. Structured preoperative exercise, nutritional and psychological optimisation builds functional reserve before surgery, and is particularly valuable in the frail or low-METs patient.
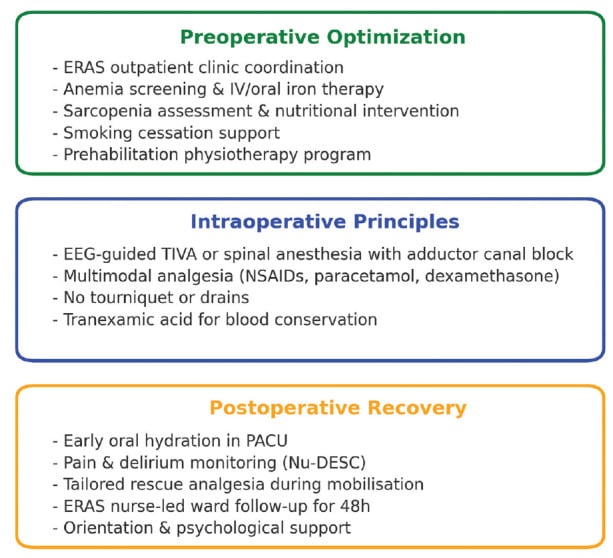
Enhanced Recovery After Surgery. ERAS is a multimodal bundle of minimal fasting and carbohydrate loading, opioid-sparing multimodal and regional analgesia, normothermia, early feeding, early mobilisation, and minimising drains and catheters. It reduces length of stay and complications across elective orthopaedics.
Guidelines, Registries & Global Practice
Global Epidemiology
Worldwide, more than 300 million major surgical procedures are performed annually, and the proportion involving older patients with cardiovascular, respiratory and metabolic comorbidity continues to rise. Cardiac complications remain a leading cause of perioperative death after noncardiac surgery, and preoperative anaemia affects roughly one in three surgical patients (Fowler 2015). These figures make structured preoperative optimization a globally relevant, exam-favoured topic rather than a single-country concern.
Side-by-Side Society Guidance
- Cardiac Risk Tool
- RCRI + stepwise algorithm, biomarkers (BNP/troponin)
- Perioperative Beta-Blocker
- Continue if established; do not start de novo
- Distinctive Emphasis
- Functional capacity and METs central to the algorithm
- Cardiac Risk Tool
- RCRI / NSQIP + NT-proBNP, troponin surveillance
- Perioperative Beta-Blocker
- May start only with careful titration days ahead
- Distinctive Emphasis
- Strong push for biomarker-guided risk and PMCM clinics
- Cardiac Risk Tool
- Selective testing by ASA grade and surgical severity
- Perioperative Beta-Blocker
- Continue established therapy
- Distinctive Emphasis
- Routine testing minimised; perioperative medicine pathways
- Cardiac Risk Tool
- RCRI plus mandatory NT-proBNP/BNP screening
- Perioperative Beta-Blocker
- Avoid initiation; continue chronic therapy
- Distinctive Emphasis
- Postoperative troponin surveillance strongly recommended
The biggest international divergence is biomarker screening: Canadian (CCS) and European (ESC) guidance recommend routine preoperative NT-proBNP/BNP and postoperative troponin surveillance in higher-risk patients, whereas US (ACC/AHA) and UK (NICE) guidance are more selective. All major societies agree on NOT starting beta-blockers de novo (POISE) and on minimising routine testing in fit ASA 1-2 patients.
Registry and Outcome Evidence
Arthroplasty registries (NJR England and Wales, AOANJRR Australia, AJRR USA, Swedish SHAR, Norwegian and NZJR) consistently link uncontrolled diabetes, high BMI, current smoking and anaemia to higher revision and periprosthetic joint infection rates, reinforcing why modifiable comorbidities are optimised before elective joint replacement.
High- vs Limited-Resource Practice Variation
Dedicated preoperative assessment clinics, CPET and biomarker testing, IV iron and erythropoietin pathways, anaesthetist-led optimisation and HDU/ICU step-down beds are routinely available.
Optimization relies on robust clinical assessment (functional capacity, ASA, RCRI), targeted rather than routine investigations, oral iron and locally available antiplatelet/anticoagulant reversal, with judicious case selection where critical-care backup is scarce.
Medicolegal Principles (Universal)
Document ASA and RCRI scores, functional capacity, the medication interruption/resumption plan and patient-specific consent. The commonest sources of litigation worldwide are failure to identify a high-risk patient, anticoagulation/antiplatelet errors around surgery, and proceeding despite a clearly modifiable risk factor.
Controversies & Areas of Uncertainty
Holding versus continuing remains debated. Continuing risks refractory intraoperative hypotension; holding may risk rebound hypertension. Many centres now hold the morning dose for major surgery, but high-quality RCT evidence is limited and guidance is not uniform.
Common practice uses 8.0-8.5% to defer elective arthroplasty, but the evidence base is observational and the ideal cut-off is contested. Chronic control matters more than a single value, and rigid thresholds risk inequity for patients who never reach target.
The traditional teaching to stop metformin on the day of surgery rests on weak evidence; the absolute risk of lactic acidosis is very low in patients with normal renal function. Practice is shifting toward continuing metformin for minor surgery with preserved renal function.
Routine NT-proBNP/BNP and postoperative troponin surveillance (favoured by CCS/ESC) improve risk discrimination but generate downstream testing and uncertainty about how to act on isolated troponin rises. Adoption varies widely between countries.
MCQ Practice Points
Q: Which of the following is NOT a component of the Revised Cardiac Risk Index? A: Hypertension. The six RCRI predictors are: high-risk surgery, ischemic heart disease, CHF, cerebrovascular disease, diabetes on insulin, and creatinine greater than 177.
Q: What functional capacity threshold predicts increased perioperative cardiac complications? A: Under 4 METs. Patients unable to climb 2 flights of stairs or walk 4 blocks have significantly increased cardiac risk.
Q: What did the POISE trial demonstrate about starting beta-blockers perioperatively? A: Increased stroke (OR 2.17) and mortality despite reducing MI. Only continue beta-blockers if patient already established on therapy.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“68-year-old male for elective THA. Previous MI 18 months ago (DES), diabetes on insulin, Cr 160. On aspirin, ticagrelor, metoprolol. Climbs 1 flight only. How to optimize?”
“62-year-old female, HbA1c 9.8%, listed for revision TKA in 2 weeks. Previous wound infections. Patient keen to proceed. Your plan?”
“74-year-old woman with atrial fibrillation (CHA2DS2-VASc 4) on rivaroxaban presents with a displaced intracapsular hip fracture. CrCl 55 mL/min. Last dose was this morning. How do you plan timing and anticoagulation?”
RCRI Score (6 Predictors)
- HI DISC: High-risk surgery, Ischemic heart disease, Diabetes on insulin, Impaired renal (Cr greater than 177), Stroke/TIA, CHF
- Score 0-1 = low risk (0.4-1%), proceed with surgery
- Score 2 = intermediate (2.4%), assess functional capacity
- Score 3+ = high risk (greater than 5%), cardiology consult
Functional Capacity
- 4 METs = critical threshold (climb 2 flights, walk 4 blocks)
- Under 4 METs + RCRI greater than 1 = further cardiac testing
- Good functional capacity (greater than 4 METs) = proceed regardless of RCRI
Medication Management
- STOP: warfarin 5d, clopidogrel 5-7d, metformin day of, SGLT2i 3d before
- CONTINUE: aspirin (if stent under 12mo), beta-blockers, statins
- NEVER START: new beta-blockers perioperatively (POISE - increased stroke)
- DOACs: stop 24-48h depending on renal function, no bridging needed
Diabetic Optimization
- HbA1c greater than 8.5% = delay elective surgery 6-8 weeks to optimize
- Day of surgery: hold metformin, reduce basal insulin 20-25%, hold bolus insulin
- IV dextrose if NPO greater than 6h, target BGL 6-10 mmol/L
- Poor control = 2-3x infection risk
Smoking and Anemia
- Minimum 4 weeks cessation for benefit - under 4 weeks may worsen outcomes
- Optimal cessation 8 weeks - reduces wound complications from 31% to 5%
- Anemia: treat if Hb under 130 (M) or 120 (F), IV iron if time-critical
- Expect Hb rise 10-20 g/L with 4 weeks treatment
Evidence Base and Key Trials
POISE Trial - Perioperative Beta-Blocker Initiation
- 8351 patients with, or at risk of, atherosclerotic disease undergoing noncardiac surgery across 190 hospitals in 23 countries
- Randomized to extended-release metoprolol succinate vs placebo started 2-4h before surgery, continued 30 days
- Fewer reached the cardiovascular composite endpoint (5.8% vs 6.9%, HR 0.84) and fewer had MI (4.2% vs 5.7%, HR 0.73)
- BUT excess deaths (3.1% vs 2.3%, HR 1.33) and stroke (1.0% vs 0.5%, HR 2.17), driven by hypotension and bradycardia
Preoperative Smoking Cessation Before Joint Replacement
- Randomized trial of 120 patients in 3 Danish hospitals undergoing elective hip or knee replacement
- Counselling plus nicotine replacement 6-8 weeks before surgery (cessation or at least 50% reduction)
- Overall complication rate 18% with intervention vs 52% in controls (p=0.0003)
- Wound-related complications 5% vs 31% (p=0.001); fewer cardiovascular events and reoperations
Revised Cardiac Risk Index (RCRI) - Derivation and Validation
- Prospective cohort of 4315 patients aged 50+ undergoing elective major noncardiac surgery
- Six independent predictors: high-risk surgery, ischaemic heart disease, heart failure, cerebrovascular disease, insulin-treated diabetes, creatinine over 2.0 mg/dL (177 micromol/L)
- Major cardiac complication rates with 0, 1, 2 and 3+ factors were 0.5%, 1.3%, 4% and 9% in derivation
- Validation cohort (n=1422) rates were 0.4%, 0.9%, 7% and 11%; outperformed prior indices on ROC analysis