Idiopathic Scaphoid Osteonecrosis | Proximal Pole Disease | Diagnosis of Exclusion
- Diagnosis of exclusion: Preiser is idiopathic AVN with NO acute fracture - rule out occult fracture/nonunion first
- Retrograde blood supply: dorsal scaphoid branch of the radial artery enters distally, so the PROXIMAL pole is most ischaemic
- MRI is the key test: diffuse low T1 signal of the scaphoid; Stage I is MRI-only with normal radiographs
- Kalainov MRI split: complete (entire scaphoid) vs partial (proximal pole only) necrosis - guides graft suitability
- Salvage when collapsed/arthritic: proximal row carpectomy and four-corner fusion give the most reliable pain relief
- “Scaphoid is the 2nd most common carpal bone for AVN after the lunate
- “Proximal pole disease = retrograde, distally-entering blood supply
- “Normal X-ray does not exclude Preiser - get an MRI
- “No level I evidence and no formal guideline - treatment is staged and individualised
Overview and Epidemiology
Preiser disease is idiopathic avascular necrosis (osteonecrosis) of the scaphoid occurring without an acute fracture, first described by Georg Preiser in 1910. The scaphoid is the second most common carpal bone to undergo osteonecrosis, after the lunate in Kienbock's disease.
Why it is examined. The condition is rare but a classic exam topic, because it forces reasoning from first principles: scaphoid vascular anatomy, the difference between AVN and nonunion, and a staged treatment algorithm where no guideline exists.
Who gets it. Adults, typically aged 30-50. Both sexes are affected, with a female predominance in several surgical series, and the disease is usually unilateral. Only a few hundred cases exist in the world literature: a pooled review of 53 publications captured only around 170 patients in a century.
A diagnosis of exclusion. Insidious pain without significant trauma is the giveaway in the history. Before calling it Preiser disease, exclude an occult fracture or an established nonunion, which carries proximal-pole AVN of its own.
Both can show proximal-pole sclerosis, but Preiser disease has no fracture line: the necrosis is primary and idiopathic, not the result of a displaced fragment losing its blood supply. In nonunion, the AVN is a consequence of a fracture that failed to heal. On MRI, Preiser typically shows necrosis confined to the zone of dead bone, whereas a nonunion shows a discrete fracture line. Getting this distinction right changes both the diagnosis and the operation.
Natural history. The disease evolves over months to years:
- Early (Stages I-II): a viable scaphoid may revascularise or remain stable
- Mid (Stage III): fragmentation and loss of proximal-pole volume
- Advanced (Stage IV): collapse and peri-scaphoid arthritis, a SNAC-like pattern
Pathophysiology and Anatomy
The blood supply. Roughly 70-80% of the scaphoid's blood, including the entire proximal pole, comes from the dorsal scaphoid branch of the radial artery. It enters distally, near the dorsal ridge and waist, and runs retrograde toward the proximal pole. The distal pole and tubercle are supplied by volar branches.
Why the proximal pole dies first. No vessel enters the proximal pole directly, so it is the watershed, last to perfuse and first to die. The same anatomy explains the delayed union of proximal pole fractures, and why they fail to unite.
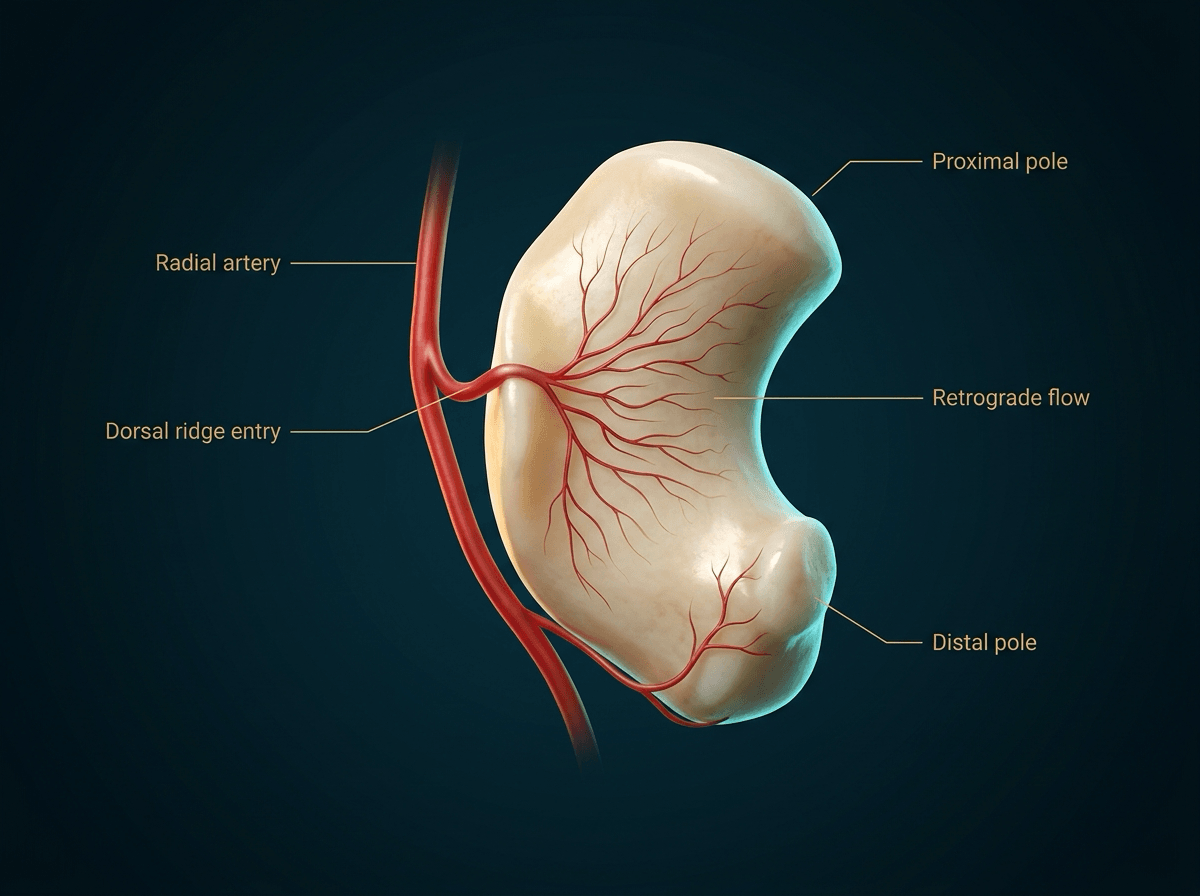
Aetiology. Multifactorial and, by definition, often unknown. The recognised associations are:
- Slender ("type 2") scaphoid morphology, with a sparser intra-osseous vascular network (discussed below, with the strength of the evidence)
- Repetitive load and vibration: manual labour, drilling and impact sports, causing cumulative microtrauma to a marginally perfused bone
- Drugs: corticosteroids, cytotoxic chemotherapy and alcohol, the last two implicated in case reports
- Systemic disease: systemic lupus erythematosus, vasculitis, sickle cell disease, gout and renal disease
- Idiopathic: in many patients no cause is ever identified, and this is the "core" Preiser group
The cascade. From perfusion to arthritis, in order:
- Compromised perfusion of a marginally vascularised (often slender) scaphoid
- Ischaemia of the proximal pole, the watershed zone
- Osteocyte death
- Subchondral microfracture and fragmentation
- Loss of scaphoid height, carpal malalignment (DISI) and instability
- Peri-scaphoid radiocarpal and midcarpal arthritis
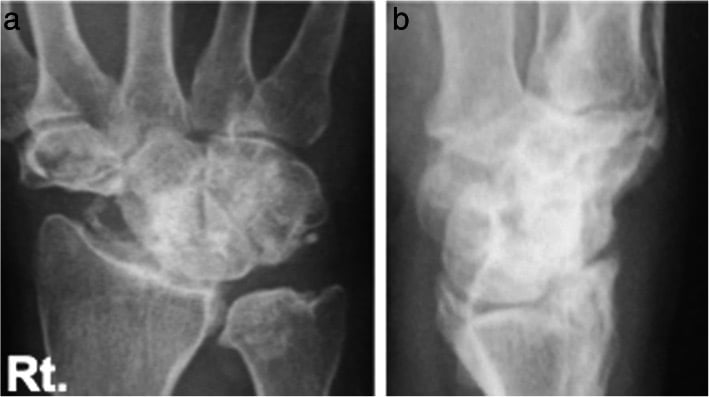
Why dead bone looks dense. Increased density does not mean more bone. Living bone around the dead segment continues to be remodelled and partly resorbed while the dead trabecular bone is not, so the necrotic area looks relatively sclerotic on radiographs. The same principle applies in Kienbock's disease and femoral head AVN.
Paediatric and Immature-Scaphoid Disease
Preiser disease is exceptionally rare before complete scaphoid ossification. In a child, compare with the opposite wrist and require a coherent pattern across radiographs, CT and MRI: sclerosis or segmentation alone can reflect developmental anatomy, whereas diffuse marrow-signal abnormality without oedema or a fracture line supports osteonecrosis.
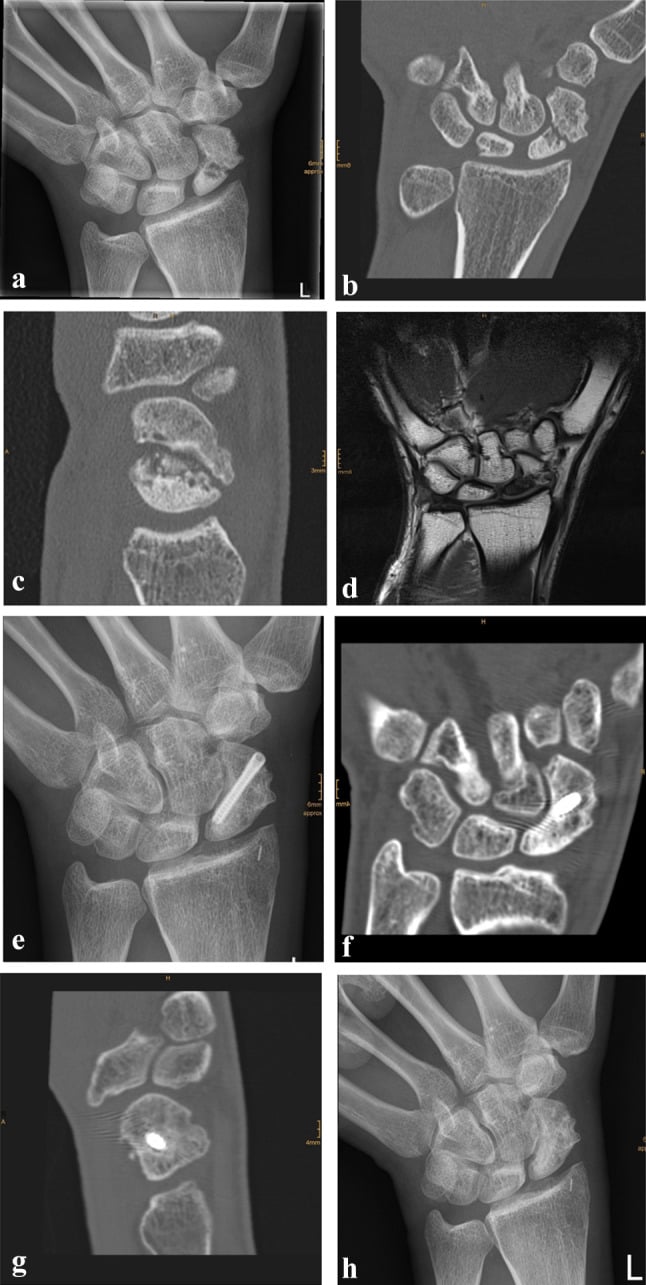
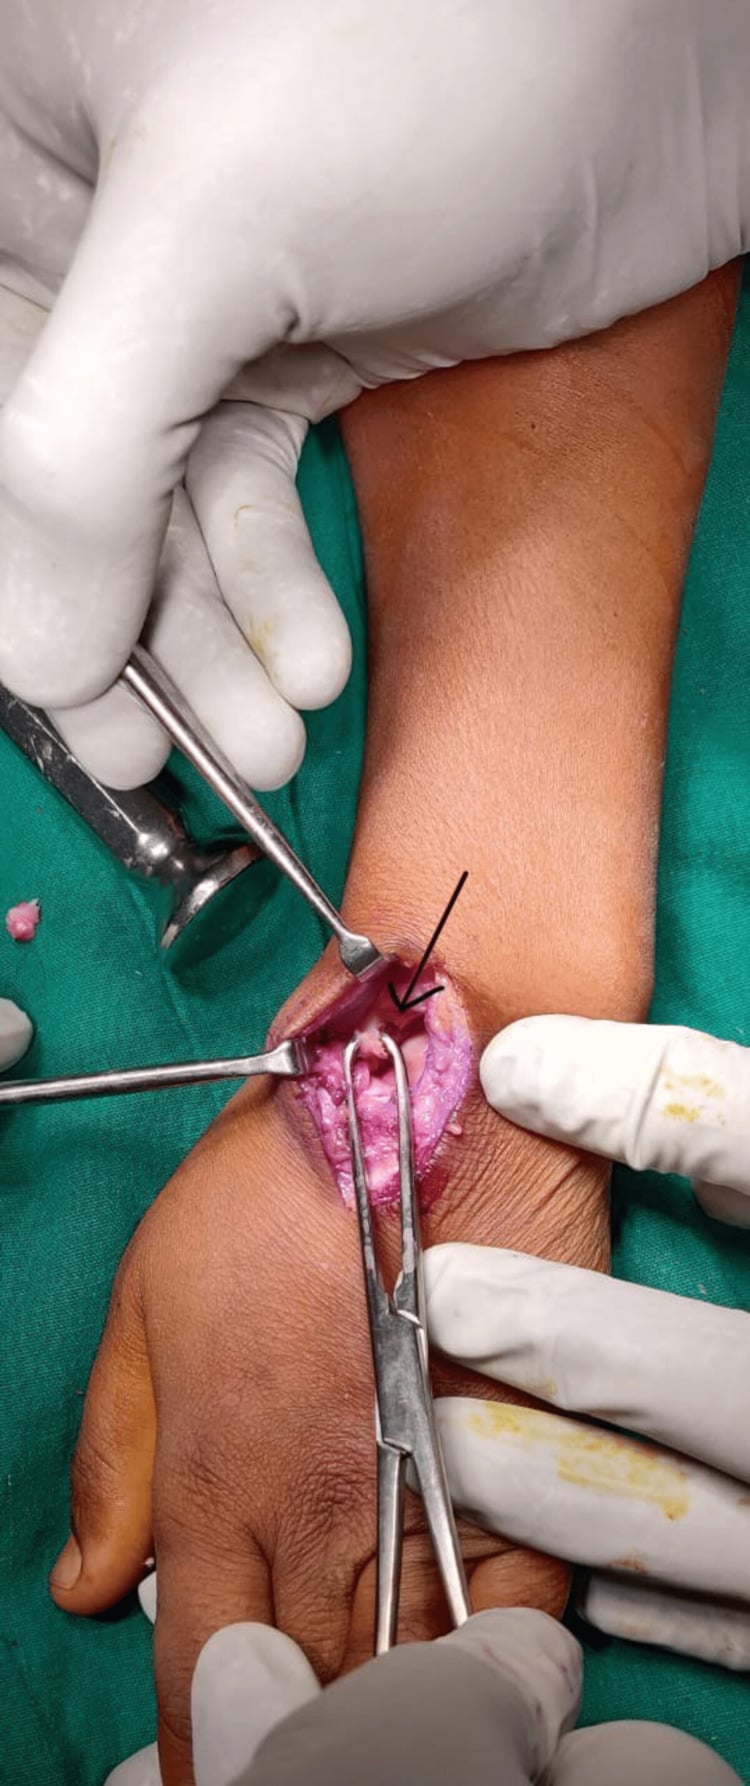
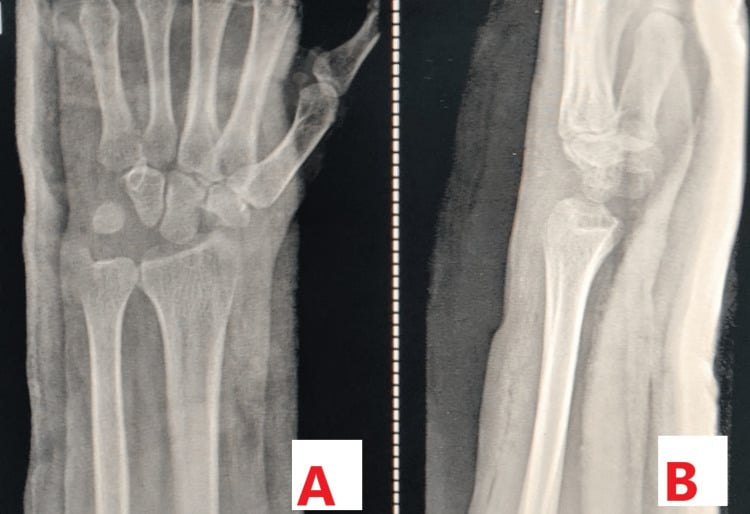
The reported case. A 10-year-old with an incompletely ossified scaphoid illustrates both the diagnostic difficulty and the capacity for recovery. Initial radiographs showed osteosclerosis, CT showed segmentation and collapse of the ossific nucleus, and both T1- and T2-weighted MRI showed low signal throughout the scaphoid. The imaging did not show the oedema or fracture morphology expected after an acute injury.
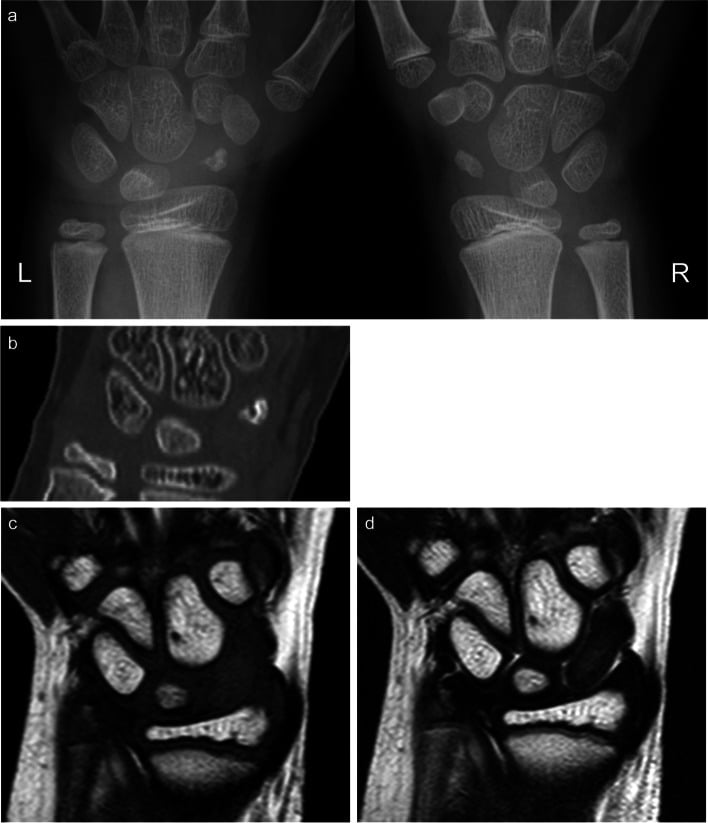
Recovery. Because the ossific nucleus remained biologically active, three weeks in a thumb-spica cast followed by two months in an orthosis was followed by progressive remodelling. The distal pole remodelled first and the proximal pole followed by one year; the whole scaphoid had remodelled by two years, and growth was normal at five years.
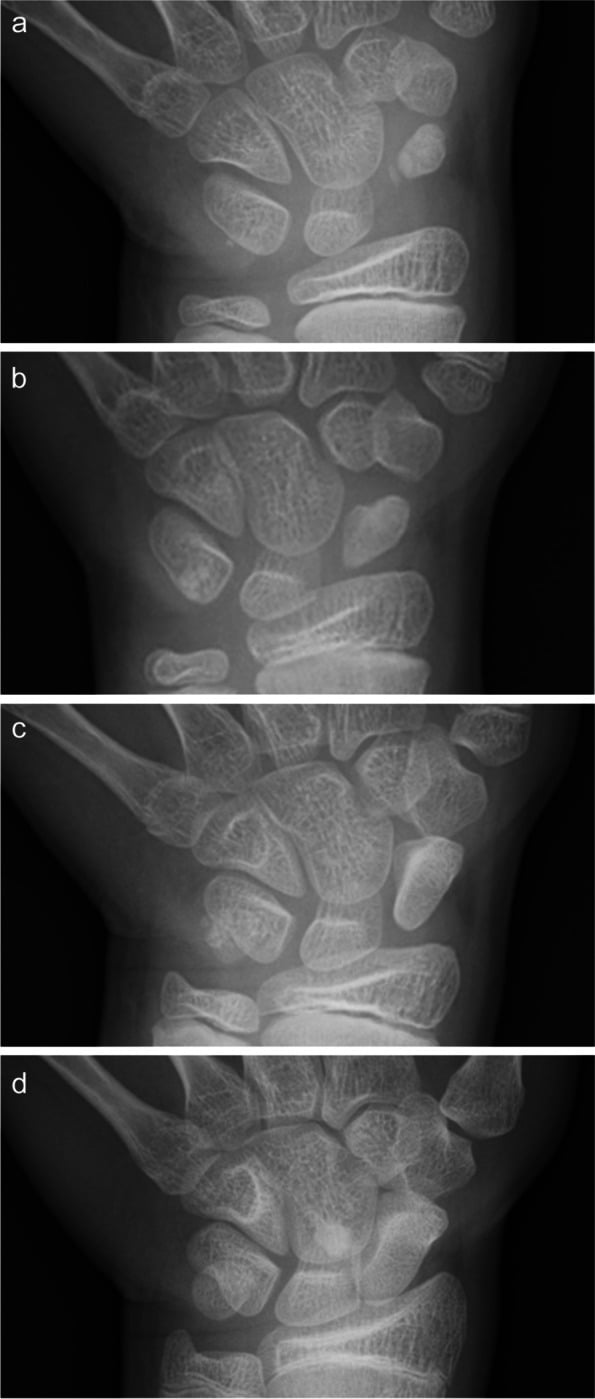
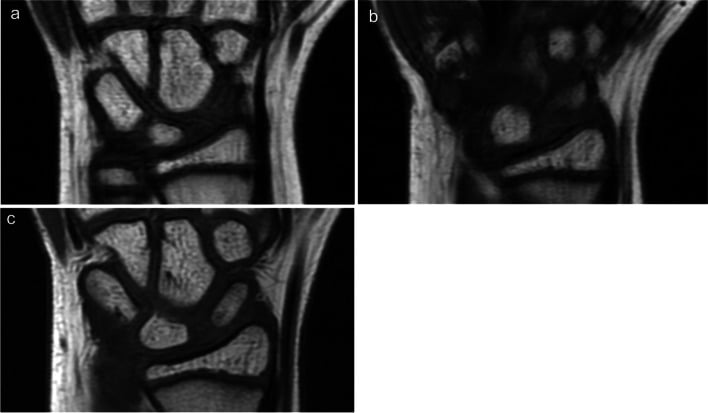
This is a single immature-skeleton case, not evidence that established adult Preiser disease will recover with immobilisation. In adults, progression is more common and the decision still depends on stage, viable bone, cartilage and carpal alignment.
Scaphoid Morphology: the Slender (Type 2) Scaphoid and the Contralateral Wrist
The slender scaphoid. The constitutional factor most often invoked for idiopathic scaphoid necrosis is shape. Scaphoid morphology is broadly divided into a wide (type 1) and a slender (type 2) form, and the slender scaphoid carries a sparser intra-osseous vascular network. That leaves its already-marginal proximal pole even more vulnerable when perfusion is challenged by load, drugs or systemic disease.
The evidence for it. In the Mayo series of 39 operated wrists, Amundsen and colleagues assessed the unaffected contralateral wrist in patients with unilateral disease and found a slender scaphoid in half of the wrists that could be evaluated (four of eight). The shape being present in the healthy wrist too is what supports a constitutional predisposition rather than a purely acquired insult.
How loosely to hold it. The association rests on a handful of contralateral wrists in one retrospective series with no control group, and the authors themselves write only that a slender scaphoid is potentially more common. It is a plausible mechanism with a reasonable anatomical basis, not an established risk factor.
Put the other wrist to work. Because Preiser disease is usually unilateral, the contralateral scaphoid is a free control. Image it:
- to establish the patient's baseline morphology
- to exclude asymptomatic bilateral disease
- as an anatomical template for reconstruction planning
The classic Preiser vignette is a constitutional-plus-mechanical two-hit: a slender, marginally perfused scaphoid (the predisposition) in someone who loads it hard - the vibrating drill, the impact sport - or who carries a systemic insult (corticosteroids, chemotherapy, connective-tissue disease). The model holds that neither hit alone reliably kills the bone and that together they do, which would explain why so many cases remain labelled idiopathic. With the slender-scaphoid association unproven, use it to build the vignette, not as an established mechanism.
Classification Systems
Herbert-Lanzetta stages the disease on plain radiographs; Kalainov and Schmitt read the extent and pattern of necrosis on cross-sectional imaging.
The original and most widely used staging system, based on plain radiographs and carrying treatment implications (see the treatment algorithm under Management).
- Radiographic findings
- Normal radiograph; MRI shows AVN
- Scaphoid status
- Structurally intact
- Radiographic findings
- Sclerosis / density change, normal shape
- Scaphoid status
- Intact, no fragmentation
- Radiographic findings
- Fragmentation / cystic change
- Scaphoid status
- Proximal pole losing volume
- Radiographic findings
- Collapse with peri-scaphoid arthritis
- Scaphoid status
- Fragmented, arthritic carpus
Stage IV is the prognostic watershed. Once peri-scaphoid arthritis is established, joint-preserving surgery is no longer effective and salvage is required.
Clinical Assessment
History. Insidious radial-sided or dorsal wrist pain, worse with activity, with no significant trauma or pain disproportionate to a trivial injury. Grip strength falls and wrist motion is progressively lost. Ask about steroid use, chemotherapy, connective-tissue disease and vibration exposure: a drill operator or manual worker with months of unexplained radial wrist pain is the classic vignette.
Examination. Tenderness over the anatomical snuffbox and scaphoid, dorsoradial fullness, reduced flexion-extension that is painful at the extremes, and a weak, painful grip. The Watson (scaphoid shift) test may be positive if carpal instability has developed. The findings are non-specific; imaging makes the diagnosis.
The differential. Radial-sided wrist pain in an adult has several mimics, and MRI is the single best discriminator. Preiser disease shows diffuse low T1 marrow signal of the scaphoid without a fracture line; each alternative has its own pattern.
- Typical features
- Insidious radial wrist pain, no acute fracture
- Key imaging discriminator
- Diffuse low T1 scaphoid signal, NO fracture line
- Distinguishing point from Preiser
- Primary idiopathic AVN of an intact scaphoid
- Typical features
- Prior wrist injury, snuffbox pain
- Key imaging discriminator
- Discrete fracture line plus proximal-pole sclerosis
- Distinguishing point from Preiser
- AVN is secondary to a fracture that failed to unite
- Typical features
- Acute fall on outstretched hand, focal tenderness
- Key imaging discriminator
- Fracture line on MRI/CT, bone oedema
- Distinguishing point from Preiser
- Acute trauma and a true fracture, not idiopathic AVN
- Typical features
- Trauma, dorsal SL tenderness, positive Watson
- Key imaging discriminator
- SL gap (Terry-Thomas), DISI; scaphoid marrow normal
- Distinguishing point from Preiser
- Ligamentous instability; scaphoid signal is normal
- Typical features
- Radial styloid pain, positive Finkelstein
- Key imaging discriminator
- Tenosynovitis of first dorsal compartment; bone normal
- Distinguishing point from Preiser
- Tendon, not bone, pathology
- Typical features
- Older patient, base-of-thumb / radial pain
- Key imaging discriminator
- Joint-space loss and osteophytes; no diffuse AVN
- Distinguishing point from Preiser
- Degenerative joint disease rather than osteonecrosis
Investigations
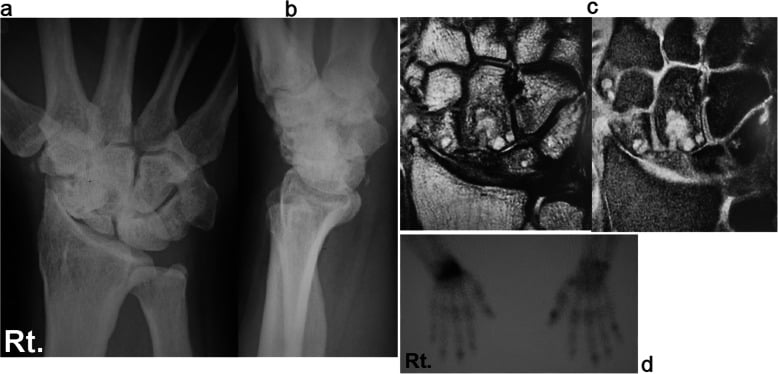
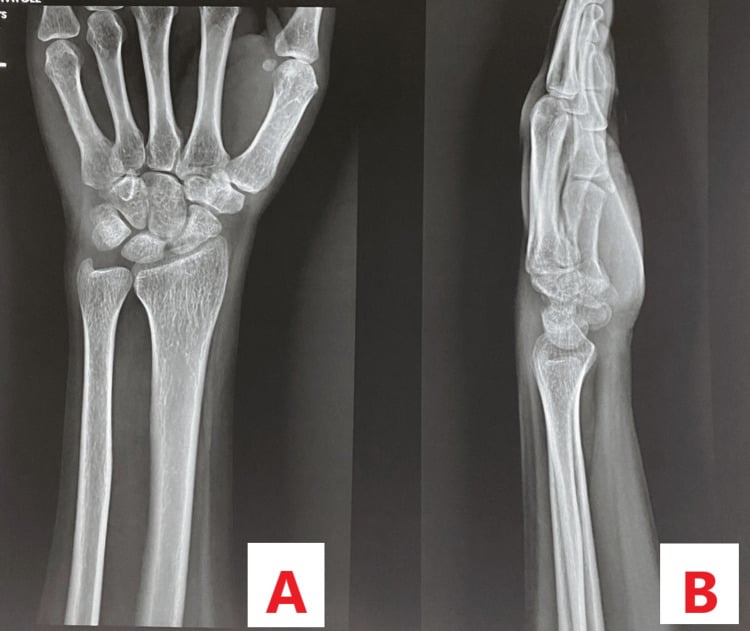
Plain radiographs first. PA, lateral and scaphoid (ulnar-deviation) views give the Herbert-Lanzetta stage: sclerosis in Stage II, fragmentation and cysts in Stage III, collapse and peri-scaphoid arthritis in Stage IV, and any DISI on the lateral. Films are normal in Stage I, so a normal radiograph never excludes the diagnosis.
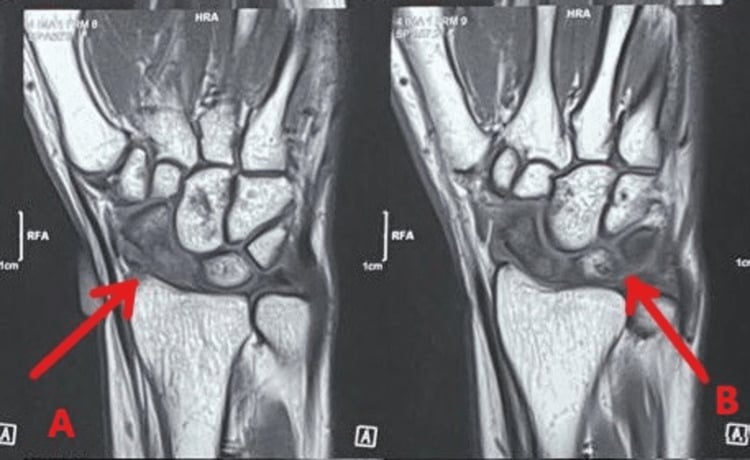
MRI is the key test. Use T1 and T2 sequences and consider contrast. Diffuse low T1 signal confirms AVN, and the absence of a fracture line distinguishes Preiser disease from nonunion. MRI also detects Stage I disease, assesses lunate viability and separates complete from partial necrosis (Kalainov), which guides graft suitability.
CT for bony detail. CT defines trabecular detail, fragmentation, cyst location, collapse and any subtle fracture line, so it excludes an occult fracture or nonunion and plans surgery. Sagittal-oblique reformats along the scaphoid axis are the most useful.
Arthroscopy in selected cases. It assesses the cartilage directly, allows articular damage to be graded and can be combined with debridement. It helps decide between joint-preserving surgery and salvage when imaging is equivocal.
Management Algorithm
Staged care without a guideline. There is no level I evidence and no society guideline, and management is built on small case series. Immobilise early disease, graft viable non-arthritic scaphoids, and salvage once the carpus collapses or arthritis appears.
- Preferred treatment
- Immobilisation + activity change
- Alternative
- Observation with serial MRI
- Notes
- Some viable scaphoids revascularise
- Preferred treatment
- Vascularised bone graft
- Alternative
- Closing radial wedge osteotomy
- Notes
- Best window for joint preservation
- Preferred treatment
- VBG if no arthritis
- Alternative
- Salvage if cartilage damaged
- Notes
- Decision hinges on arthritis and necrosis extent
- Preferred treatment
- PRC or four-corner fusion
- Alternative
- Total wrist fusion (end-stage)
- Notes
- Joint-preserving surgery no longer effective
Stage III and the evidence. In the systematic review of case series, proximal row carpectomy gave the best pain relief and motion in Stage III, while the algorithm still grafts a Stage III wrist without arthritis. Assess the cartilage and carpal alignment carefully before choosing.
Indications. Stage I disease, a viable scaphoid, the low-demand or reluctant patient, and significant comorbidity.
The regimen. A cast or splint for several weeks to months unloads the scaphoid and allows revascularisation. Combine it with activity and occupational modification, moving away from vibration or heavy impact work, with NSAIDs for symptoms and hand therapy to maintain motion.
Surveillance. Serial radiographs and repeat MRI detect revascularisation or progression. Some early, viable scaphoids recover without surgery; others progress and need an operation. Conservative care suits genuinely early, viable disease and is temporising once fragmentation or arthritis appears.
Complications
- Early complications
- Persistent pain
- Late complications
- Progression to collapse / arthritis
- Management
- Convert to surgery
- Early complications
- Pedicle injury, stiffness
- Late complications
- Incomplete revascularisation, ongoing arthritis
- Management
- Salvage procedure
- Early complications
- EPL rupture, hardware irritation, DRUJ symptoms
- Late complications
- Stage progression despite pain relief
- Management
- Tendon reconstruction, revision
- Early complications
- Stiffness, CRPS
- Late complications
- Radiocapitate arthritis over time
- Management
- Convert to fusion
- Early complications
- Nonunion, hardware prominence
- Late complications
- Adjacent-joint arthritis
- Management
- Revision / total fusion
Progression. Untreated, or after surgery that only treats symptoms, the disease runs on to fragmentation, scaphoid collapse, DISI and peri-scaphoid arthritis. Some early viable scaphoids instead revascularise and stabilise.
CRPS. Complex regional pain syndrome is a risk after any wrist surgery; minimise it with early motion and good analgesia.
Stiffness. It is common after prolonged immobilisation or fusion, and early hand therapy mitigates it.
Clinical Relevance and Outcomes
- Pain relief
- Variable; some full recovery
- Motion
- Often preserved
- Evidence
- Case reports / small series
- Pain relief
- Improved in most
- Motion
- Preserved (around half of normal)
- Evidence
- Level IV series
- Pain relief
- Good pain relief
- Motion
- Largely retained
- Evidence
- Small Level V series
- Pain relief
- Reliable pain relief
- Motion
- Roughly 50% of normal
- Evidence
- Level IV salvage data
Timing decides the outcome. Caught early and viable, the scaphoid may be preserved or even revascularise. Caught late with collapse and arthritis, salvage gives dependable pain relief but never restores a normal wrist.
- Better outcome
- I-II
- Worse outcome
- III-IV
- Better outcome
- Partial (type 2)
- Worse outcome
- Complete (type 1)
- Better outcome
- Intact
- Worse outcome
- Peri-scaphoid arthritis
- Better outcome
- Stable
- Worse outcome
- DISI / collapse
Guidelines, Registries & Global Practice
Global epidemiology. Preiser disease is rare worldwide - only a few hundred cases exist in the literature, and most hand surgeons see only one or two in a career. It clusters in adults aged 30-50, with several surgical series reporting a female predominance, and is associated with corticosteroids, chemotherapy, alcohol, connective-tissue disease and a slender scaphoid morphology. There is no population incidence figure and no implant registry, because the operations performed (grafts, osteotomies, carpectomies and fusions) are not arthroplasty.
No single global guideline - practice rests on case-series evidence. No society publishes a formal Preiser treatment guideline. Practice converges on a staging-driven algorithm derived from Level IV-V evidence.
- Staging emphasis
- Herbert-Lanzetta + Kalainov MRI
- Early disease (Stage I-II)
- Vascularized bone graft for viable, non-arthritic scaphoids
- Advanced (III-IV)
- PRC favoured; four-corner fusion if capitate arthritic
- Staging emphasis
- Herbert-Lanzetta + MRI necrosis extent
- Early disease (Stage I-II)
- Vascularized graft (Zaidemberg-type) in early stages
- Advanced (III-IV)
- Scaphoidectomy +/- implant, PRC or carpal arthrodesis
- Staging emphasis
- Herbert-Lanzetta + Kalainov + DISI assessment
- Early disease (Stage I-II)
- Closing radial wedge osteotomy as less-invasive option
- Advanced (III-IV)
- Conservative care common in elderly; salvage if disabling
- Staging emphasis
- Plain radiographs (MRI often unavailable)
- Early disease (Stage I-II)
- Immobilization and activity modification
- Advanced (III-IV)
- Total wrist fusion as reliable, low-cost salvage
Registry and high- vs limited-resource practice. Where MRI is freely available, early (Stage I) disease is detected and viable scaphoids can be grafted or simply observed before collapse. Where MRI is scarce, diagnosis is later and total wrist fusion becomes the dependable salvage because it needs no specialist implant and reliably abolishes pain. Vascularized grafting and microsurgical reconstruction are concentrated in specialist hand units.
Consent essentials (universal). For joint-preserving surgery, counsel that proximal-pole revascularisation is often incomplete and arthritis may still progress. For salvage surgery, counsel explicitly on the motion-versus-pain-relief trade-off (PRC and four-corner fusion preserve some motion; total fusion removes motion but most reliably relieves pain), and on progression risk if early disease is managed non-operatively.
Related pages: Kienbock's Disease is the same problem one bone over and the far commoner carpal osteonecrosis - worth reading alongside, because the two coexisted in two of the seven wrists in the radial-osteotomy series cited above, and radial-shortening logic crosses between them; Scaphoid Fractures and Scaphoid Nonunion for the injuries this is mistaken for and must be distinguished from - the discriminator is where the fracture line sits relative to the necrotic zone; Carpal Instability (DISI/VISI) for the collapse pattern that marks late presentation and closes the door on joint preservation; Midcarpal Arthritis for the degenerative endpoint that decides between proximal row carpectomy and four-corner fusion; and Avascular Necrosis of the Hip for the systemic risk factors - corticosteroids, chemotherapy, connective-tissue disease - that are shared across every site of osteonecrosis.
Controversies and Areas of Uncertainty
Preiser disease has no level I evidence and no consensus guideline. A strong candidate acknowledges the uncertainty rather than overstating any single procedure.
Preiser's original 1910 description was controversial and some early "cases" were probably unrecognised fractures. Modern authors restrict the term to genuinely idiopathic AVN with no fracture, but the boundary with occult fracture and nonunion remains debated.
A systematic review found surgery gave greater pain relief than conservative treatment in Stages II-III, but the evidence is entirely Level IV case series. Some early, viable scaphoids revascularise with immobilization alone, so not every patient needs an operation.
A large single-centre series found pedicled vascularized bone grafts gave functional outcomes similar to salvage procedures but preserved the scaphoid in about 70% of cases - so the trade-off (preserve a partly dead bone vs remove it) is genuinely unsettled.
Even when grafts improve MRI signal, revascularisation of the proximal pole is frequently incomplete, and arthritis can still progress. This tempers enthusiasm for grafting in wholly necrotic (Kalainov type 1) scaphoids.
Closing radial wedge osteotomy can relieve pain and preserve motion, but in published series radiographic stage still progressed in many patients - suggesting it is symptom-modifying rather than disease-modifying.
As in other end-stage carpal collapse, both salvage options give reliable pain relief with broadly comparable function; choice is driven by cartilage status, demand and surgeon preference rather than high-quality comparative data.
MCQ Practice Points
Q: Which carpal bone is the second most common site of avascular necrosis after the lunate? A: The scaphoid - idiopathic scaphoid osteonecrosis is termed Preiser disease.
Q: Why is the proximal pole of the scaphoid most affected in Preiser disease? A: The scaphoid has a retrograde blood supply - the dorsal scaphoid branch of the radial artery enters the dorsal ridge distally and runs proximally, so the proximal pole is the watershed and dies first.
Q: What is the key investigation for diagnosing early Preiser disease? A: MRI - it detects diffuse low T1 marrow signal (Stage I) before radiographic changes and distinguishes Preiser from scaphoid nonunion by the absence of a fracture line.
Q: Name the two main classification systems used in Preiser disease. A: The Herbert-Lanzetta radiographic staging (four stages) and the Kalainov MRI classification (complete vs partial necrosis).
Q: When is a vascularized bone graft appropriate in Preiser disease? A: In early disease (Herbert I-II) with a viable scaphoid and no radiocarpal arthritis or carpal instability - ideally a partial (Kalainov type 2) necrosis with viable distal bone.
Q: What is the salvage procedure favoured for advanced (Stage III-IV) Preiser disease in the systematic review evidence? A: Proximal row carpectomy - it gives reliable pain relief and preserves roughly half of wrist motion, provided the capitate head and lunate fossa cartilage are intact.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 36-year-old male drill operator presents with 4 months of insidious radial-sided wrist pain and no clear injury. Snuffbox tenderness is present. Plain radiographs of the wrist are reported as normal. How do you proceed?”
“A 40-year-old woman has 8 months of dorsoradial wrist pain. Radiographs show scaphoid sclerosis without fragmentation. MRI confirms avascular necrosis limited to the proximal pole with viable distal bone, and there is no radiocarpal arthritis or carpal instability. What are her options?”
“A 55-year-old presents late with chronic wrist pain, stiffness and weakness. Radiographs show scaphoid fragmentation and collapse with peri-scaphoid radiocarpal arthritis and a DISI deformity. MRI shows necrosis of the whole scaphoid. How do you manage this, and what does the evidence say?”
Key Concepts
- Idiopathic AVN of the scaphoid with NO acute fracture
- 2nd most common carpal AVN after the lunate (Kienbock's)
- Proximal pole most affected - retrograde, distally-entering blood supply
- Diagnosis of exclusion - rule out occult fracture / nonunion first
Classifications
- Herbert-Lanzetta (radiographic): I normal X-ray, II sclerosis, III fragmentation, IV collapse + arthritis
- Kalainov (MRI): complete (whole scaphoid) vs partial (proximal pole) necrosis
- Schmitt 3-zone model: proximal necrosis, middle repair, distal viable
Investigations
- MRI = key test: diffuse low T1, no fracture line; detects Stage I
- Radiographs: sclerosis, fragmentation, collapse, arthritis (normal in Stage I)
- CT: bony detail, exclude occult fracture, surgical planning
Treatment by Stage
- Stage I: immobilization + activity change, serial MRI
- Stage II: vascularized bone graft (or radial wedge osteotomy)
- Stage III: graft if no arthritis, else salvage
- Stage IV: PRC or four-corner fusion; total fusion for end-stage
Exam Pearls
- Normal X-ray does NOT exclude Preiser - order an MRI
- VBG only for early, viable, non-arthritic scaphoids
- Proximal-pole revascularisation after grafting is often incomplete
- No level I evidence and no formal guideline - staged, individualised care
Evidence Base
Bergman, Petit, Rabarin, Raimbeau & Bigorre
- Updated review of 53 publications and 170 patients since Preiser's 1910 description
- Scaphoid is the second most frequent carpal bone for avascular necrosis after the lunate
- Two modern imaging-based classifications now supplement the original Herbert-Lanzetta radiographic system
- Proposes a simple staged treatment algorithm given the absence of formal guidelines
Schmitt, Frohner, van Schoonhoven, Lanz & Golles
- 10 patients with primary scaphoid osteonecrosis imaged with radiographs, CT and contrast-enhanced MRI
- A three-layered architecture was found: proximal necrosis, middle repair zone, distal viable marrow
- Pathological fractures occurred exclusively within the necrotic zone, unlike scaphoid nonunion
- Three morphological stages described; the initial stage is visible only on MRI